https://www.lymedisease.org/alpha-gal-syndrome-no-tick-bite/

When alpha-gal syndrome is NOT related to a tick bite

Oct. 27, 2022

Typically, alpha-gal syndrome is associated with the bite of a lone star tick, and can result in a life-threatening allergy to red meat. But, according to Pamela Traina, the picture can be more complicated than that. She delivered the following public comments at the Oct. 25 meeting of the federal Tick-Borne Disease Working Group.

Good morning. My name is Pamela Traina. I am 55 years old and live in Los Angeles, California.

My alpha-gal diagnosis came three years ago after spending several years in and out of hospitals due to idiopathic anaphylactic reactions.

I was lucky to have an allergist who never discounted my unusual symptoms, negative allergy tests, and numerous anaphylactic reactions. It still took over two years to pinpoint the cause.

Alpha-gal is virtually unheard of in California because most people who have received an alpha-gal diagnosis live in the southeastern United States and have been infected due to being bitten by the lone star tick. The lone star tick is not found in California. I have not been to the southeastern United States and do not remember ever being bitten by a tick. Yet, I have alpha-gal syndrome. More research is required to pinpoint other possible vectors of how this condition is contracted.

Since my alpha-gal diagnosis, I have been diagnosed with multiple other food and medication allergies, including an uncommon allergy to PEG (polyethylene glycol) and polysorbate. Neither one has a diagnostic test. In addition, my Alpha-Gal test is now negative, but my sensitivity and reactions are still severe.

We need better testing, more education

Current testing is inadequate. We need more accurate testing for Alpha-Gal and other food allergies. We need answers as to why other allergies and conditions emerge after an alpha-gal diagnosis and what are the possible long-term effects of alpha-gal. We also need transparency on all medication and product labels to include inert ingredients.

Finally, hospitals and emergency staff must be educated to treat alpha-gal patients adequately. The hospital and emergency room are extremely dangerous for me due to a lack of awareness of alpha-gal.

I have had eight significant reactions since my alpha-gal diagnosis requiring er visits and hospital stays. I have endured numerous invasive and expensive tests while they search for the cause, discounting my alpha-gal diagnosis.

I have been asked if I was taking drugs and denied breathing treatments and Benadryl during a reaction because they were going to “observe” me since my symptoms didn’t present like typical anaphylaxis.

Education is required for all healthcare providers in the United States, including pharmacists, dieticians, doctors, dentists, and EMS providers, so they are aware of this condition and know how to treat it safely. It is so much more than an allergy to red meat.

Thank you for your time and the work you’re doing for the alpha-gal community.

_______________

For more:

**UPDATE**

Stating the CDC spreads ‘misinformation’ is too kind.  This corrupt agency flat out lies.

Here’s a perfect example:  https://www.lifezette.com/2022/11/the-cdc-proves-to-be-liars-again-as-hpv-related-cancers-increased-over-the-past-15-years/  Video Here (Approx. 2 Min)

The CDC Proves to Be Liars AGAIN as HPV-Related Cancers Increased over the Past 15 Years”So if the HPV vaccine does not decrease cancer, as we’ve been led to believe, then the CDC and the health officials have been lying to us all along.”

For more:

https://www.theepochtimes.com/exclusive-cdc-officials-told-they-spread-misinformation-but-still-didnt-issue-correction-emails

CDC Officials Told They Spread Misinformation but Still Didn’t Issue Correction: Emails

By Zachary Stieber
Updated: October 30, 2022

U.S. Centers for Disease Control and Prevention (CDC) officials were alerted that they spread misinformation about child COVID-19 deaths but still did not issue corrections, according to emails obtained by The Epoch Times.

Drs. Katherine Fleming-Dutra and Sara Oliver were told within days of presenting to the Advisory Committee on Immunization Practices (ACIP), the CDC’s vaccine advisory panel, in June that statistics from a preprint study they shared were wrong, the emails show. But after internal discussion about how to respond, neither the CDC nor the officials corrected the false information.

Fleming-Dutra and Oliver both referenced the study, which has not been peer reviewed, while the CDC’s advisers weighed whether to recommend the agency grant emergency authorization for COVID-19 vaccines for babies and toddlers.

The committee ultimately recommended the CDC authorize Pfizer and Moderna shots for children as young as 6 months of age and the CDC quickly accepted the recommendation.

A week later, CDC Director Dr. Rochelle Walensky appeared to cite the false statistics while urging parents to get their children vaccinated, despite no evidence the vaccines protect against severe illness and despite the clinical trials returning substandard or unreliable results for shielding against infection.

Kelley Krohnert, a citizen researcher and mother who flagged the preprint, triggered the internal discussions among CDC officials, according to the emails. When Krohnert pointed Fleming-Dutra to a blog post that detailed the issues with the study, Fleming-Dutra sent the email to others, including Oliver.

“I am not sure who this should go through. Let me know what I need to do,” Fleming-Dutra said.

Megan Freedman, a CDC health communications specialist, looped in a CDC spokeswoman, and they informed Fleming-Dutra that she and other subject matter experts “would need to determine if there’s any validity to the complaint.” If the complaint was deemed valid, possible next steps might include pulling the slide or adding a footnote, Freedman said.

Oliver jumped in, saying that Krohnert “appears [redacted], but there are my thoughts.” Her thoughts were redacted.

“I’m sure you guys can make it sound prettier, but something like this would be how I would respond,” Oliver said. “And the general sentiment that ‘even 1 death from COVID that’s preventable is too many, regardless of how you count them.’”

There’s no evidence any of the COVID-19 vaccines prevent death for small children.

(See link for article)

__________________

**Comment**

The initial version “incorrectly used” death certificate data which is notoriously wrong for many reasons (subjectivity and unreliability):  https://madisonarealymesupportgroup.com/2021/02/18/the-problem-with-cdc-death-statistics/

It’s commonly known that COVID deaths have been over-reported due to hospitals being bribed by the government to count everything as a COVID case and list everything as a COVID death even if it wasn’t the cause of death.  From the beginning numbers have been pulled out of thin air and public health officials have been pushing fear propaganda over COVID deaths, making “catastrophic errors,” despite the fact experienced epidemiologists continue to state COVID mortality is similar to flu mortality. The tests can’t even differentiate between COVID and the flu and they conveniently quit counting flu deaths – it’s all COVID now.  To date, nobody has a clue how many truly die from COVID vs how many died with COVID.  Public health notoriously mangles data in their favor for their purposes.

Please remember our own government owns over 50 “vaccine” patents.

The false stats were promoted in September and are still uncorrected. The only reason we even know about them is due to another FOIA request by The Epoch Times.  Remember – false statistics were used to take away your freedom, force you to wear ineffective, dangerous masks, isolate you, force you to repeatedly test with a faulty, inaccurate, dangerous test, the CDC manipulated, the WHO manipulated, and promote wide-spread fear.

Please remember that doctors are being censored, maligned, deplatformed and persecuted – even losing their jobs for so-called ‘misinformation.’ Others that speak out are also similarly persecuted.  And California has passed a bill to muzzle doctors.  Three medical boards are currently being sued for threatening doctors.  The private, nonprofit behind the state medical boards which started in 1912 to “consolidate” the medical industry has attacked alternative practitioners and supplements for decades. The FSMB, which lobbies probably 50 government agencies, predictably shapes international health policy in favor of Big Pharma – under the guise of protecting patients.

The Feds are asking people to rat other people out over ‘misinformation,’ Biden attempted a “disinfo” board until the public screamed bloody murder opposing it, and the FDA chief has prioritized fighting ‘misinformation,’ along with attacking anything the agency deems a threat or competition.

Yet our government public health agencies can continue to spread misinformation with abandon with no recourse.

This isn’t new.  The CDC is known to lie repeatedly, withhold, hide, and skew data for their own vested interests using their own flawed tests they have patents on, and arbitrarily cherry pick and toss inconvenient data. They have done this in Lymeland for over 40 years.

Trusting this agency is like getting behind the horse that kicks you.

For more:

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-al

“Deja Vu All Over Again”

Carl Tuttle

Hudson, NH, United States

Oct 30, 2022 — 

Sound familiar?…

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: Anie Kuster and 45 additional legislators
Date: 10/30/2022 10:01 AM
Subject: BREAKING: Marxist Medical Boards Strip Top Dr. Peter McCullough’ s Medical Credentials for Speaki ng the Truth About COVID Vaccine

BREAKING: Marxist Medical Boards Strip Top Dr. Peter McCullough’s Medical Credentials for Speaking the Truth About COVID Vaccine
https://www.thegatewaypundit.com/2022/10/breaking-marxist-medical-boards-strip-top-dr-peter-mcculloughs-medical-credentials-speaking-truth-covid-vaccine

To Representative Annie Kuster and all legislators carbon copied on this thread,

The same deplorable action took place with our coexisting pandemic of Lyme disease as physicians who treated Lyme with long-term antibiotics were also penalized by state medical boards. (See the 5min trailer below)

Under Our Skin – Extended Trailer
https://www.youtube.com/watch?v=sxWgS0XLVqw

New Hampshire along with a dozen or more other states passed laws (HB295) to protect our Lyme literate physicians.

Dr. McCullough’s loss of medical license is “Deja Vu All Over Again;” same BS, different infection.

How will our legislators allow the next Plandemic to play out?

Boston University researchers claim to have developed new, more lethal COVID strain (with 80% kill rate) Oct 17, 2022
https://www.fox29.com/news/boston-university-researchers-claim-to-have-developed-new-more-lethal-covid-strain-in-lab

Local legislation doesn’t address or investigate/interrogate the elephant in the room (CDC/FDA/NIH) and until we launch a long overdue Congressional Investigation, Covid-19 is proof that history will repeat itself.

As for our New Hampshire Dept. of Health “just following orders” does not stand up in a court of law.

How the Nazi’s defense of ‘just following orders’ plays out in the mind
https://www.pbs.org/newshour/science/how-the-nazis-defense-of-just-following-orders-plays-out-in-the-mind

Carl Tuttle
Hudson, NH

Change.org Lyme Petition:

Calling for a Congressional investigation of the CDC, IDSA and ALDF
https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf

98,573 Signatures   970,324 Views   27,791 Shares

Petition comments (15,709 as of Oct 2022)
https://www.dropbox.com/s/jh74i1mlgt89lqj/petition_comments_Oct%202022.csv?dl=0

Comments are describing a disease that is destroying lives, ending careers while leaving its victims in financial ruin. CDC’s false narrative: “Lyme is hard to catch and easily treated with 2-4 weeks of antibiotics.”

BREAKING: Marxist Medical Boards Strip Top Dr. Peter McCullough's Medical Credentials for Speaking the Truth About COVID Vaccine
One of the most respected doctors in the world and top cardiologists and epidemiologist in the country had his license revoked for…
For more:

Nearly 40% of doctors who treat Lyme/MSIDS patients have been reported to a medical board, an insurer, or has been subjected to a hospital-based quality improvement inquiry.

Put simply, doctors are afraid to treat Lyme/MSIDS patients.

https://www.lymedisease.org/9-epi-pen-a-month-mccord/

“Nine EpiPens in a month.” The burdens of Lyme, AGS, and more.

Cortney McCord delivered the following public comment at the Oct. 25 meeting of the federal Tick-Borne Disease Working Group.

I’m Cortney McCord, a registered nurse from Tupelo, Mississippi. Since May 8, 2021, I have been in a battle for my life against alpha-gal syndrome, Lyme borreliosis, bartonellosis, babesiosis, and mast cell activation syndrome.

I developed the most severe clinical presentation of alpha-gal syndrome: I react to airborne and contact exposures as well as dietary exposures to alpha-gal.

For me, it’s way more than just a meat allergy.

In January 2022, my infectious burden grew after I contracted COVID. COVID sent me into full-blown mast cell activation syndrome and made asthma and chronic urticaria a part of my daily life.

After being gaslighted by a local allergist who was ignorant of mast cell activation syndrome and airborne alpha-gal reactions, I made an appointment with expert allergist and former Working Group member Dr. Scott Commins. I am thankful to have him in my corner even if it takes a 12-hour drive to see him..

Patients like me do not have the luxury of time to sift through a myriad of ignorant doctors to find someone familiar with their condition. Because symptoms of tick-borne infections, alpha-gal syndrome, and mast cell activation syndrome are manifested in every organ system, physicians in every medical discipline should be literate in these conditions. Nobody deserves to be gaslighted because of a lack of physician education.

Another tick bite

I was bitten by another larval lone star tick at the end of this past August. In September alone, I had to use nine EpiPens. All of this from a tick the size of a speck of dirt.

In addition to long Lyme, I believe I have long COVID complicating my clinical picture.

Long COVID and long Lyme are very similar. Both Sars-CoV-2 and Borrelia burgdorferi are persistent in tissues. Both affect the host’s immune system. Both can cause mast cell activation syndrome. The medical world has no problem saying that COVID is a persistent “long” disease. Why is that not the case for persistent ‘long” Lyme borreliosis? There are stacks of good science supporting persistent “long” Lyme infection–some of which was done by current working group member Dr. Monica Embers.

I refuse to believe that this is the best that our medical and scientific community can do. Testing for both mast cell activation syndrome and tick-borne diseases is abysmal. That has to change. There should be a law requiring alpha-gal to be listed as a major allergen on every medicine, food, and consumable product that Americans have contact with. We need the Tick-borne Disease Working Group to continue in perpetuity because tick-borne conditions will affect more and more Americans as our planet warms.

Please help me. Ask Congress to address these needs. Thank you.

_________________

**Comment**

This is truly a complicated case, but most are in my experience.

While all patients deserve to be heard and treated properly, throwing yet more money at the TBDWG which is filled with people who do not believe in chronic infection, and which has done ZERO to help  patients is not helpful.  IF, and I mean IF any money is appropriated to study this, IMO – whoever is doing the work needs needs to be independently funded.  Researchers can not be the regular cast of characters – receiving grants from corrupt public health agencies, that is literally a Cabal regurgitating old, outdated, highly myopic work which is designed for a pre-determined outcome and completely ignores a huge subset of people.

Unfortunately many patients and even advocates are oblivious to the sordid backstory of the corrupt agencies controlling research and funding.  Insanity truly is doing the same thing over and over and expecting different results.  Time to ditch the public health monopoly and public health agencies controlling research, funding, doctors, testing, treatments, and “vaccines.”

For more:

https://www.lymedisease.org/mylymedata-clinician-lyme-survey-report/

Clinician Barriers to Providing Care: Why Patients Can’t Get the Care They Need

By Lyme Policy Wonk

9/29/22

Previous studies have shown that patients who have persistent or chronic Lyme disease (PLD/ CLD) have a hard time obtaining the medical care they need to get well (Johnson 2011). A new study has found that clinicians who treat this population face significant challenges in providing patients care that is local, timely, and affordable (Johnson 2022).

Between September 23 and December 1, 2021, LymeDisease.org conducted a survey of U.S. clinicians who treat PLD/CLD patients. One hundred and fifty-five clinicians from 30 states responded to the survey and 45 provided comments in the open text survey item. The results of this survey were published this week: Access to Care in Lyme Disease: Clinician Barriers to Providing Care. The primary goal of this survey was to identify the difficulties that clinicians face when caring for patients with PLD/CLD.

We are pleased to present the Clinician Barriers to Providing Care Chartbook summarizing key points from the published study.

2022 MyLymeData Chartbook

Download Your full color

2022 MyLymeData Chart Book

Clinician Barriers to Providing Care: Why Patients Can’t Get the Care They Need

Download Now

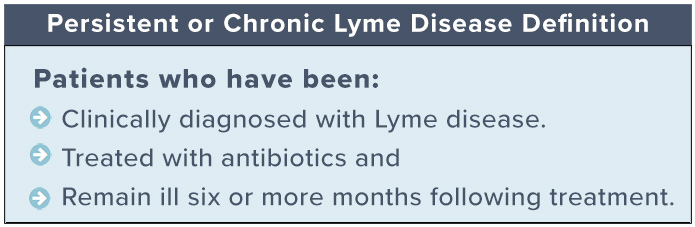
The CDC estimates that 476,000 cases of Lyme disease occur annually (Kugeler 2021). Even when diagnosed and treated early, up to 44% of patients fail treatment, with only 56% considered to have returned to health (Aucott 2022). In later disease, treatment failure rates are higher. Lyme disease patients who remain ill after antibiotic treatment are regarded as having persistent or chronic Lyme disease. These patients may have been diagnosed early or late.

Chronic Lyme disease definition

Clinicians who treat PLD/CLD

Clinicians treating patients with PLD/CLD have developed significant clinical expertise. Most clinicians (55%) are  medical doctors (MD) or doctors of osteopathy (DO); the remainder are naturopaths with prescription privileges (15%), nurse practitioners (12%) or physician assistants (6%).

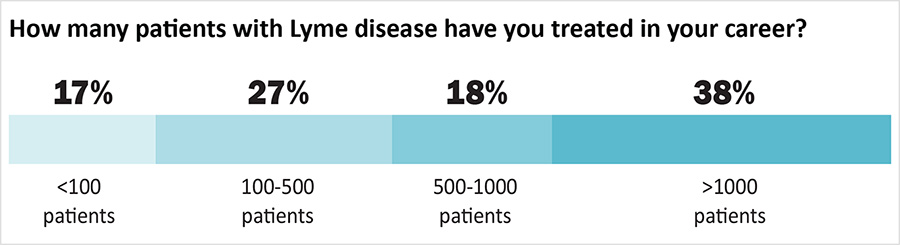
Over half of the clinicians (56%) have treated more than 500 patients and 38% have treated more than 1000 patients. Most (57%) dedicate more than half of their practice treating Lyme disease. Almost all (98%) have taken continued medical education for Lyme disease treatment. Eighty-nine percent belong to the International Lyme and Associated Diseases Society (ILADS) and most belong to other medical societies as well.

How many patients have you treated with Lyme disease?

Why Clinicians Who Treat Chronic Lyme Disease Find it Difficult to Provide Care

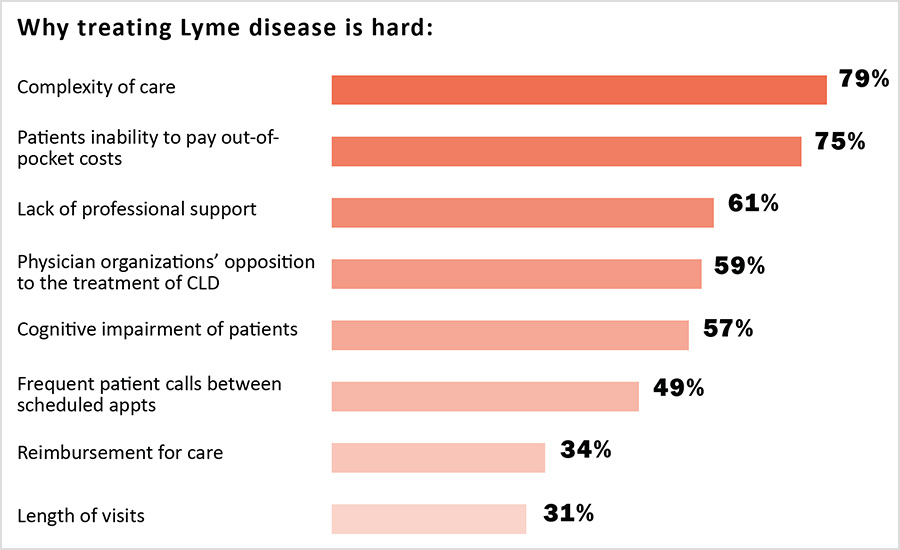
Despite their considerable expertise, clinicians report that providing care to PLD/CLD patients is challenging. In particular, the complexity of the care provided and the time it takes to provide that care make it difficult for clinicians to provide care using the traditional insurance-based healthcare model. This increases the cost of care provided to patients and makes it difficult for patients to pay for the care that can be given.

Why treating Lyme disease is hard

The complexity of care needed requires longer clinician visits than treatment for other conditions. For example, 25% of clinicians said their first consultations took more than two hours, and 44% said their follow-up visits took between one and two hours.

Clinicians reported that the length of healthcare visits for PLD/CLD coupled with the additional insurance administrative burdens and reimbursement payment issues make it hard for care to be given under a traditional insurance-based model, which typically relies on clinicians seeing a high volume of patients for short office visits. As one clinician explained:

“The most difficult problem is the cost of providing this amount of complex care on a cash basis. To really review hundreds of records, spend time with the patient and do a proper workup, takes hours. I’d like to see more support for patients and clinicians who choose to help this set of patients.”

As a result of these challenges, most PLD/CLD providers do not accept insurance:

  • 74% do not participate in insurance networks
  • 76% do not directly bill insurers
  • 77% do not participate in Medicare, Medicaid, or other government supported plans

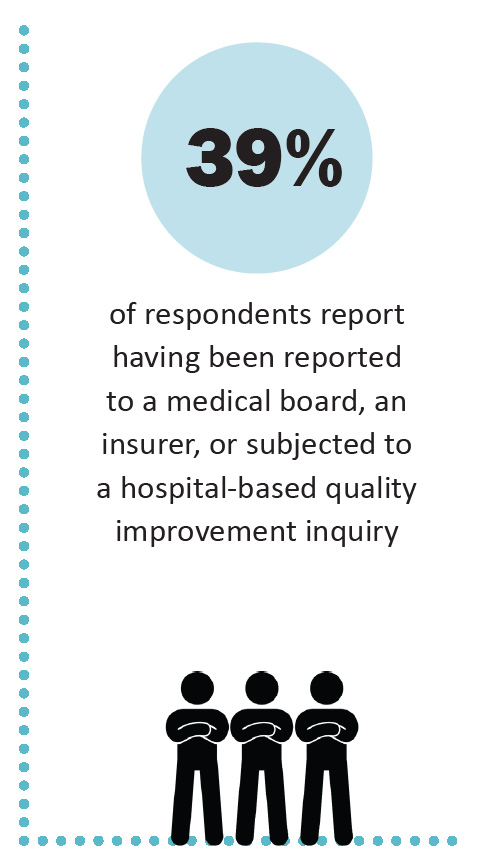
Another reason the insurance model of providing care does not work for PLD/CLD is that the risk of legal or regulatory action by medical boards, insurance companies, and other organizations is heightened for clinicians who accept insurance. Three-quarters of the clinicians who answered the survey say that they have been professionally stigmatized. More than a third (39%) report that they have been threatened with actions by medical boards, insurance companies, or hospital quality improvement committees.

One clinician commented:

“While my patients are generally very supportive, some of my colleagues have stopped speaking to me and I worry about the medico-legal repercussions of what I do.”

39 percent reported to medical board

Another said:

“I used to practice in a state where physicians who treat complex patients, including people with chronic Lyme, were specifically targeted by health insurance companies for medical board complaints and other attacks ESPECIALLY WHEN THEY HELPED PATIENTS OTHER DOCTORS GAVE UP ON. Eventually I elected to move to [a state] where there is less interruption of care and more protection of vulnerable patients from predatory insurance entities.”

One way clinicians can avoid targeting by insurance companies and other groups is by opting out of insurance networks, Medicare, and Medicaid. Clinicians who are stigmatized or don’t participate in insurance networks have fewer chances to share office space and overhead costs. This increases the cost of providing care. Treating PLD/CLD also imposed additional insurance related burdens that increase the cost of providing care exist even for clinicians who do not participate in insurance networks. These include prior authorization of medications (77%), insurance denials (71%), and other insurance-related problems (49%).

When clinicians do not participate in insurance networks, the economic burden of shouldering the cost of care is shifted to patients. This makes care more expensive for patients who have to pay for care out-of-pocket. It doesn’t come as a surprise then that 75% of clinicians say that a central problem in their practice is the patients’ inability to pay out of pocket costs. One clinician commented:

“I knew that at some point I would be forced to stop taking insurance and move forward on a cash pay only basis. Looking at the numbers, taking commercial insurance for these patients just doesn’t make any sense. I believe that the main issue that causes many of these patients to be without access to care is the amount they need to spend on their practitioners plus the out of pocket costs for out of network testing, labs, and treatment. For most of these patients that is anywhere from $10 to $20K per year. It is a huge burden.”

Essentially, the insurance model of providing healthcare is broken for patients with PLD/CLD. Not only does this increase the costs of providing care for providers and shift the cost burden to patients, it also means that patients can’t get care from their regular provider, must obtain care from places that don’t take their insurance, and need to navigate a complex healthcare maze to even find the care they need. Patient surveys published previously also identify the high cost of out-of-pocket care (Johnson 2011).

In addition, previous surveys have found that patients incur substantial diagnostic delays, misdiagnosis, see many clinicians before being diagnosed, and travel significant distances to receive care (Johnson 2011, 2014, 2020). To obtain care, 49% of patients report traveling more than 50 miles; 31% report traveling 100 miles or more for care (Johnson 2011). Because obtaining care can be expensive, inconvenient, and interfere with work responsibilities, many patients may choose not to get care at all (Johnson 2022).

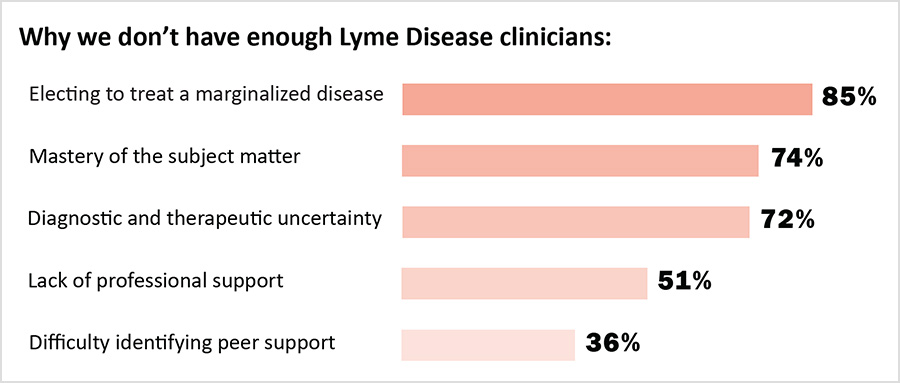
Clinicians here reported that patients with PLD/CLD often had to wait a long time for their first appointments, and that many of their patients traveled from outside their state of practice to obtain care. These factors point to a supply/demand crisis in the treatment of PLD/CLD. There are simply not enough clinicians to supply the amount of care required by patients to get well. The challenges identified by clinicians here—a broken insurance model of care, professional stigma, and heightened liability exposure—also discourage other clinicians from providing care to people with PLD/CLD.

Not enough Lyme disease clinicians

Why Early Diagnosis and Avoiding Misdiagnosis is Important

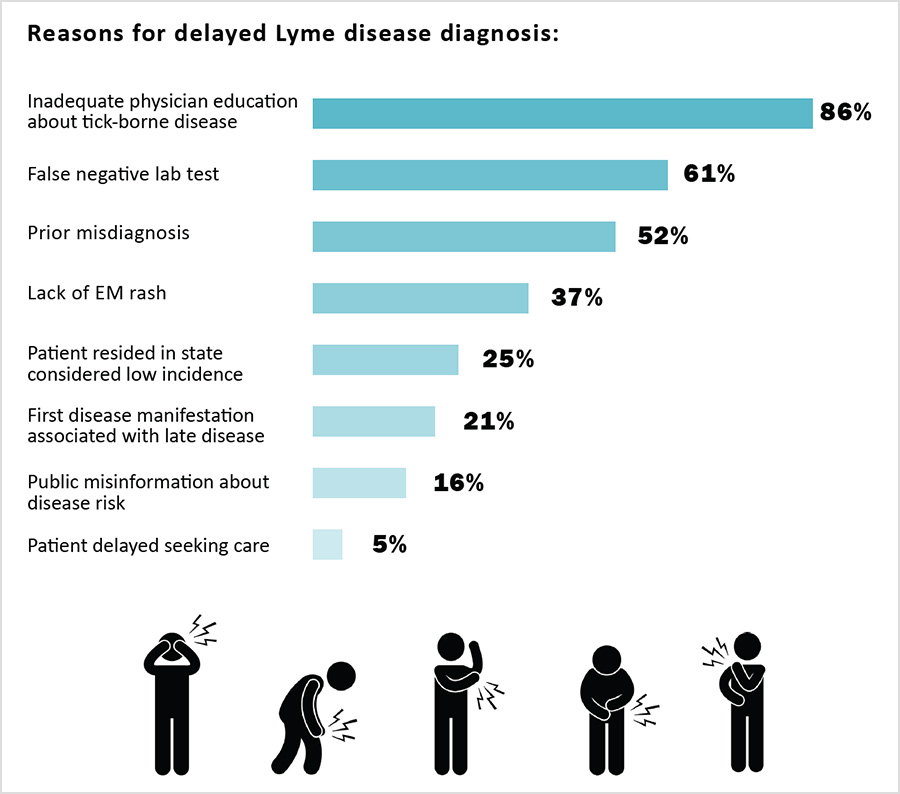
To address the supply/demand crises, it is important to reduce the number of patients who develop PLD/CLD. This requires early diagnosis and treatment. Clinicians identified inadequate physician education about tick borne diseases, false negative lab tests, and misdiagnosis as key causes of delayed diagnosis.

Delayed Lyme disease diagnosis

Nearly three quarters of patients report having initially been misdiagnosed. Misdiagnosis is often caused by the lack of education of other clinicians about tick-borne diseases (Johnson 2011, 2018). In a case series of people who might have had early Lyme disease but didn’t have a rash, 54% of Lyme disease patients who didn’t have a rash were given the wrong diagnosis (Aucott 2009). Because of this, misdiagnosis should be seen as a major risk factor for PLD/CLD.

Conclusion

The challenges identified here related to insurance and professional stigma make it hard to keep and hire clinicians who can care for the rapidly growing number of people with PLD/CLD, which is currently estimated to be slightly less than 2 million cases (Delong 2019). They also make care more costly for patients. Diagnostic delays and misdiagnosis increase the number of patients who develop PLD/CLD, exacerbating the supply/demand problem.

As Lyme disease cases rise, the demand for PLD/CLD providers will rise. The limited number of educated practitioners and the expanding number of PLD/CLD patients have created a substantial supply and demand imbalance that must be addressed.

Resolving the supply/demand imbalance is vital for PLD/CLD patients to become healthy. To do this we must:

  • improve clinician education to prevent diagnostic delay and misdiagnosis
  • retain and recruit more clinicians to address the supply demand crises by reducing professional stigma and recognizing that divergent treatment approaches exist in PLD/CLD
  • develop insurance reimbursement models that take into account the complexity of care and the time it takes to provide care.

Failing to address these issues will leave patients unable to access or afford the care that they need.

If you are a patient who is not enrolled in MyLymeData,  please enroll today. If you are a researcher who wants to collaborate with us, please contact me directly.

The MyLymeData Viz Blog is written by Lorraine Johnson, JD, MBA, who is the Chief Executive Officer of LymeDisease.org. You can contact her at lbjohnson@lymedisease.org. On Twitter, follow her @lymepolicywonk. 

MyLymeData Lyme Disease Research
About MyLymeData Lyme Disease Research

MyLymeData is one of the largest patient-driven registries in the nation, with over 17,000 patients enrolled. It was created by patients, is run by patients and will address the issues that Lyme disease patients care about. MyLymeData Viz provides the community with results from MyLymeData. If you are enrolled in MyLymeData, we thank you for providing the data that will accelerate the pace of research in Lyme disease. If you are not enrolled, please enroll today.

For more: