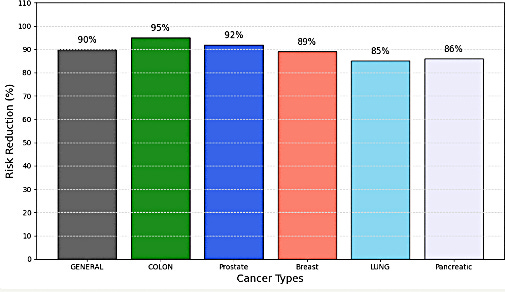
Today we announce revisions accomplished over the past few days with the assistance of AI.
Without this time-saving help, these revisions would have taken months. But we do not have months to spare as the world is dealing with an unprecedented uptick in cancers. Everyone needs this information now.
We will begin at the beginning, starting with our first 3-Supplement AI search on Cancer Risk that established the baseline. We will end with the 90 to 95 percent Optimal Cancer Risk Reduction Protocol, that we display above and once again, with analysis, at the conclusion. (See link for article)
________________
**Comment**
I learned something new. (Well, to be fair I’m always learning something new!)
I learned that it’s important to take enteric capsules of berberine, for the same reasons your proteolytic enzymes need to be enteric: to protect the supplement from stomach acid, allowing it to be dissolved in the intestines to enhance absorption and effectiveness. Berberine also outperformed Metformin.
Users in berberine clinical literature consistently report effects on energy metabolism and AMPK activation beginning to appear at the 6-8 weeks mark with consistent daily use. The most significant observations typically occur in the 6-12 week window.Source
Enter the Root6™ OTC Protocol:
Root6™ is nothing more than our basic four + Berberine and Sulforaphane. But because of synergy, the Cancer Risk Reduction is magnified, which is why cocktails of repurposed drugs work so well against cancer (very similar to how effectively they work against HIV compared with monotherapy).
New US Customs Rules Threaten Your Access to Natural Health
By The ANH Team
10/15/2026
Stronger border checks for personal imports can protect Americans from unsafe foreign products, but the same rules could also shrink consumer access and choice. Action Alert!
THE TOPLINE
New customs requirements could mean higher prices, delayed deliveries, and fewer natural health choices for consumers buying products from overseas.
Stronger scrutiny can protect consumers from unsafe products, but added costs and paperwork could also drive responsible small suppliers out of the U.S. market.
We support practical, risk-based import procedures that target illegal products while preserving access to compliant products from reputable companies.
Consumers who buy natural health products from overseas could soon face higher prices, delayed deliveries, and fewer choices. A new Customs and Border Protection (CBP) rule that comes into force on October 22, 2026 adds hurdles that may discourage smaller companies from supplying American customers. Our concern is that responsible businesses could be caught alongside sellers of unsafe or illegal products. Additionally, patients who import life-saving medications for personal use that are not currently manufactured in the US may find there are delays or even barriers at US borders which could endanger lives.
What’s Changing
Low-value packages (under $800) imported for personal use previously benefited from a customs exemption that simplified their entry into the United States. The new CBP rule removes that exemption for international mail and adds stricter requirements for mailed products overseen by agencies such as FDA.
CBP offers an electronic option for some shipments, but it still requires detailed information, someone legally responsible for the import, and a financial guarantee called a customs bond. Suppliers may need specialist help, adding costs that consumers could ultimately pay.
The rule does not itself ban all imported medicines or abolish FDA’s personal importation policy. But administrative barriers can make an established supply route unusable. (See link for article)
Episode 595: Can Lyme Affect Folate in the Brain? Dr. Lindsey Wells on Autism, PANS/PANDAS & FRAA
What if some of the depression, anxiety, brain fog, cognitive dysfunction, OCD, speech changes, and other neuropsychiatric symptoms experienced by people with Lyme and other vector-borne diseases involve more than the infection itself?
In this episode of the Tick Boot Camp Podcast, Matt Sabatello sits down with Dr. Lindsey Wells, ND, a Connecticut naturopathic physician whose work focuses heavily on children with Lyme Disease, PANS/PANDAS, autism spectrum disorder, neurodevelopmental conditions, and other vector-borne diseases.
Her study explored an intriguing question: could some people with Lyme disease, Bartonella, Babesia, or other vector-borne infections also have an immune-mediated problem that prevents enough folate from reaching the brain?
The findings open an important new area of investigation. (See link for article and interview)
_________________
**Comment**
The study found that nearly 62% of patients with tick borne illness tested positive for folate receptor alpha autoantibodies.
The study also found that Bartonella was the most common individual infection identified among FRAA-positive patients.
Important excerpt:
She discusses research suggesting that proteins associated with animal dairy may share similarities with folate receptor structures. Through a molecular mimicry mechanism, antibodies generated against those proteins could potentially cross-react with folate receptors.
Dr. Wells therefore commonly incorporates dairy removal when addressing FRAA-positive patients.
She also discusses clinical observations suggesting that FRAA levels can fluctuate and may rise during periods of infection or physiological stress.
Another important point is a routine folate blood test can not determine FRAA status. The FRAT Folate Receptor Autoantibody Test, a specialty blood test designed to detect autoantibodies to folate receptor alpha is required.
Dr. Wells has seen clinical improvements in these patients in anxiety, OCD, cognition, communication, and other neuropsch symptoms by using folinic acid (Leucovorin) as it utilizes another folate transport mechanism to deliver folate to the CNS.
Who Decides What Counts as Medicine? Rob Verkerk Explains How to Fix the Food-Drug Divide
By The ANH Team On 09/10/20260
ANH founder Rob Verkerk explains why outdated food-drug definitions restrict consumer access to natural health options—and how a more proportionate system could better protect both choice and safety.
Listen to the audio version of this article:
The following is a transcript of an interview with Rob Verkerk, PhD, and ANH-USA’s Editorial Director, Michael Ames-Sikora.
Today I’m speaking with ANH founder and executive director Rob Verkerk about Beyond Binary Food-Drug Definitions: A Case for US and EU Modernization. Accepted for publication on July 20, 2026, and expected to appear in spring 2027, the paper was written by Rob as lead author and principal investigator, ANH legal researcher Chimnonso Onyekwelu, and our general counsel, Jonathan W. Emord—the “FDA Dragon Slayer,” who holds the record for the most legal victories against the agency. At its heart, the paper asks whether laws that force products into either a food or drug category still make sense when modern science shows that foods and natural compounds can have meaningful effects on health. In the conversation that follows, Rob and I discuss the paper’s key ideas, what they mean for consumers, and how we can build a better regulatory system.
Mike Ames-Sikora: Rob, you’re the founder and executive director of ANH. What made you want to tackle the way foods and drugs are defined?
Rob Verkerk: Mike, it’s really been over 25 years that I have seen that definitions are the mechanisms that Big Pharma and Big Food use to control what you can buy, what you can say. Particularly in the drug area, the drug definition controls the therapeutic space. It also really impacts what someone can buy, what you can be told about a product, and also whether or not it’s going to actually be found in a practitioner’s toolkit.
Ames-Sikora: Your paper argues that the law draws on increasingly artificial lines between foods and drugs. Why should anyone outside the legal profession care? And why should the average consumer care?
Verkerk: Well, our paper goes back over 100 years, looking at 18 different jurisdictions around the world, but focuses especially on the US and the European system. And when you take that kind of bird’s-eye view of what has been going on for over a century, you see that the initial justification for having regulation around foods and drugs was extremely laudable. It was very well-meaning. It really was about protecting consumers from dangerous goods, mis-sold goods, mislabeled goods, and whether they were drugs or of foods. What you see over the passage of time is this sleight of hand in which essentially the definitions have now become mechanisms to control specific categories of products for the benefit of those corporations. So we now have a rather ridiculous situation where essentially foods and drugs, fast foods, and ultra-processed foods are amongst the most dangerous foods that we consume, yet they’re perfectly legal. They fit those definitions. They can be unsafe. And we’ve got a situation where drugs that are licensed, that can carry claims like safe and effective, are amongst the leading causes of death in industrialized societies. Peter Gøtzsche’s work suggests that the that drugs may in fact be the 3rd leading cause of death in industrialized societies like the US or Europe.
Ames-Sikora: Yeah, and my understanding of that statistic too is that these are not abused drugs. These are properly prescribed medications that are used as intended.
Verkerk: 100%. Yeah, properly prescribed medications. The 3rd or 4th leading cause of death in industrialized countries.
Ames-Sikora: So you argue that these definitions can protect the pharmaceutical industry’s hold on the therapeutic market. How does that work?
Verkerk: Essentially, if you want to make any kind of disease treatment, disease prevention claim, you have to be channeled down the drug pathway. So it doesn’t matter how much science you’ve got to show that turmeric or rosemary or black cohosh, name any botanical or nutrient out there, it doesn’t matter how much science says this might reduce your risk of disease, you are disallowed from making that claim. Yet if you’ve gone through the drug pathway, you’ve essentially paid to play in order to get your license. You can shout your claim from the rooftop. And in fact, what’s even more interesting, you can shout claims that the science that got you the license never made at all, given that you can also make off-label claims. So generally speaking, drug companies will get a specific claim, that’s their pay-to-play license, but then medical doctors will often use the products off-label. Now, if you’re selling a nutrient, even if it has similar effects, even if the science is comparable, even if the science is stronger than the drug with little or no side effects, you cannot make the claim because you cannot discuss the product in any way in relation to the diagnosis, treatment, or prevention of disease.
Ames-Sikora: Yeah, we saw this with the cherry and walnut growers. I remember covering that for ANH over the years. So what does this mean for prevention and for people who already live with chronic disease?
Verkerk: Well, the biggest problem is that it means they can’t get the products that are most likely to be effective. The reality is that if we talk about prevention, primary prevention is actually trying to stop a disease happening in the first place. And we know the science around primary prevention is primarily around non-pharmaceutical interventions. So things like getting people to eat the right food at the right time in the right place in the right way, getting people to move in the right way or to respond to stress in a way that doesn’t harm them, or to spend less time sitting. These are all non-pharmaceutical interventions, and there’s very, very good science around them. Yet what’s happened is that the primary prevention space increasingly is dominated by pharmaceutical interests. So, you know, the use of vaccines to prevent disease, putting people on lifelong drug use, for the use of statins amongst those over 50, for example, which is a fantastic money spinner if you’re a statin manufacturer. The evidence is relatively weak in the sense that it doesn’t work for everyone, and for some people the side effects can be atrocious. Yet that’s viewed as a standard approach, either as primary or secondary prevention.
So if you look at the incredible science that shows how micronutrients and botanical substances and other substances taken from nature’s treasure trove can be used to bring our body into balance–let’s remember that it’s not usually the drug or even the botanical, the nutrient that itself is creating the shift. What it does is change the environment or the pathway in order to allow the body to self-heal. We sometimes forget how much work our body, our immune system, our neurological system, our endocrine system is doing to get things back into order. And that’s one of the ways in which non-pharmaceutical interventions can be really, really critical for prevention. for lifelong prevention that would have a massive impact on reducing chronic and degenerative disease. But these definitions prevent anyone from talking about it, so it doesn’t find its way into the mainstream approach or vocabulary.
Ames-Sikora: What has modern nutrition science revealed that these legal categories struggle to accommodate?
Verkerk: Well, nutrition science has moved on a great deal. That’s one of our primary arguments in the paper, that essentially there’s a whole catalogue of science that shows that nutrients can have a profound effect on disease. Governments recognize this. Mike, you’ll know in our FDA Modernization Act challenge that is running currently, where basically we presented the FDA and the Department of Health and Human Services with over 100 different nutrient disease claims that government agencies themselves are making. There’s a specific clause in the FDA Modernization Act that was written by none other than Jonathan Emord in the 1990s that basically said, look, you’ve reserved any kind of disease claim to the category of drugs. But because there are nutrients out there, how about a system that if you, as the authoritative agency, determines that the science says that there is a nutrient-disease relationship, then everyone can use that. That would avoid companies having to do lots of research on nutrients and disease, and then at the end of that, possibly after having spent hundreds of thousands of dollars, to be told, sorry guys, you’re a drug, you can’t sell the product.
So this is a fantastic pathway. Now there are— we found over 400 of these claims that the National Center for Complementary and Integrative Health, the Office of Dietary Supplements, the CDC, even the FDA are making. And we presented these to the HHS and said, look, we believe that these should be able to be used as authoritative statements under the clause in the FDA Modernization Act. And they’ve said, sorry, we have a little disclaimer that says these cannot be regarded as authoritative statements under the FDA Modernization Act. So it’s a crazy situation that says we are authorities that are making authoritative statements, but in this case, we’re not going to regard these as authoritative statements. So at the moment, they’re making none. And there’s still censorship of any nutrient disease claims. So we’ve got to push that particular roadblock over.
Ames-Sikora: You know, Rob, critics might hear this and assume that you’re calling for less regulation, which could expose them to unsafe supplements or even false hope. How would your proposed approach continue to protect consumers from unsafe products and exaggerated claims?
Verkerk: Well, basically, you’ve got to match the regulatory burden to the risk and the strength of the claim to the evidence. So there’s nothing that we’re doing in terms of modernizing definitions. That’s what we’re proposing—the definitions now are outdated and they don’t match the rapid development of nutritional science and health sciences. So essentially, what we would argue is that there is no additional risk at all. In fact, quite the reverse. It would reduce the risk because more people would be encouraged to take safer products that would essentially have a big impact on reducing their health risks, as well as ensuring that that there are adequate regulations already available that prevent companies from selling unsafe products. So yeah, unfortunately, that argument doesn’t hold a lot of water. And I think another part of our argument generally around some of the other initiatives that we have is that there’s always going to be a degree of uncertainty around any claim. And we strongly advocate this idea of communicating the amount of uncertainty clearly. And of course, Jonathan Emord was central in developing the qualified health claim regimen in the United States, and that’s what it’s all about.
So it’s about accurate communication of the science, and at the moment the definitions prevent that.
Ames-Sikora: What would a more sensible system look like? And if policymakers adopted one central recommendation from your paper, what should it be?
Verkerk: It should be: modernize the definitions. We need to see the food definition broadened. We’ve known since the time of Hippocrates that foods can have medicinal effects. There is copious amounts of evidence for that. And of course, the drug definition massively overlaps the food definition with the exception of very specific exemptions. So the Dietary Supplement Health and Education Act obviously gives an exemption for dietary supplements to make structure-function claims, but they cannot in any way relate to disease. Now, we need to have a system that allows claims about effects that will also be related to disease, but the system needs to be about proportionality. So you need proportionate assessment and not just an automatic push for products that are therapeutic in action to only be forced down the drug pathway.
Ames-Sikora: Well, great. Well, I look forward to seeing this paper finally see the light of day and for it to get a reaction from the public and the scientific community.
Verkerk: Yes. In essence, Mike, what the paper is about is laying down the intellectual academic foundation for why we need to change definitions. You’re going to be very involved, as I am, as all of us will be, in the advocacy program that actually works with Congress and with senators in order to change these definitions. And the interesting thing, we’ve done a lot of work in terms of what modifications may need to be made to bring them in line with the science. And it doesn’t involve a complete rewrite of the definitions. In fact, sometimes it involves only very small changes, but they can have profound effects, and they will work for millions of Americans. And that’s the solution.
ANH-USA will launch a major advocacy program once the paper is published—and we’ll be looking for your support to push through amendments to various food and drug related definitions. Stay tuned!
FDA’s proposed GRAS reform could deliver long-overdue transparency to what’s in America’s food supply—but unless the agency modernizes its approach to natural ingredients, consumers may pay the price in reduced innovation, choice, and access.
With GRAS reform being a headline priority for Secretary Kennedy shortly after he came into office, FDA has finally moved to reform a key pathway for how certain food ingredients come to the market known as the GRAS (Generally Recognized as Safe) system. That is overdue. But the agency’s proposed cure—delivered as a proposed rule on August 10—could punish the natural product sector. Simply put, these changes could make it harder to access a variety of functional foods, health foods, and ready-to-drink products that millions of consumers rely on.
Post a comment to the FDA’s docket calling for more rational reform of the GRAS system.
Proposed changes to the FDA’s GRAS (Generally Recognized as Safe) rules—backed by RFK Jr.’s push to clean up junk and ultra-processed foods—could create a sweeping pre-approval system that threatens access to thousands of safe, natural supplement ingredients.
While reform is needed to curb harmful additives, past FDA decisions show the agency has approved questionable synthetic ingredients—raising concerns that new authority could unfairly target natural products instead.
This is a pivotal moment for health freedom: without public pushback, regulatory overreach could restrict supplement access under the guise of food safety reform.