https://brownstone.org/articles/proof-vaccines-were-military-backed-countermeasure/

Proof that the Vaccines Were a Military-Backed Countermeasure

Here is a high-level review of the manufacturing contracts between US DOD and Moderna.

Moderna’s injection, mRNA-1273 is co-owned with the US Government, as the company has been funded by the defense research grants for years and also received intellectual property transfers from the US Government, in addition to preclinical and clinical research work conducted for Moderna by the NIH Vaccine Research Center. The NIH and Moderna each have a separate Investigational New Drug number for this product.

Moderna entered 2 types of contracts with the US Government for Spikevax injection:

  • “Vaccine” contract and amendments that specifies R&D projects that the US Government ordered and paid for. Note that in Pfizer’s case no R&D activities were ordered or paid for by the US Government, as these were excluded from the scope of the contract.
  • “Manufacturing” contract(s) that ordered a large-scale manufacturing. This is different from Pfizer manufacturing contracts as the words “demonstration” and “prototype” are not used. I believe this is because OTA contracts must be for prototypes but FAR contracting doesn’t have to be.

Note on redactions. In both Moderna and Pfizer’s contracts many areas are redacted indicating a reason for redaction – the “redaction codes.” Redacted content has been given codes b (4) and b (6), standing for:

(b) (4) Disclosure of information that would affect the application of advanced technology in a U.S. weapons system,

and

(b) (6) Disclosure of information, including information of foreign governments, that would cause serious harm to relations between the United States and a foreign government or to ongoing diplomatic activities of the United States.

There are several versions of the contract available, plus amendments. The first version was signed on August 9, 2020 and the last available version is June 15, 2021. In one of them the name of the signatory on the Moderna side was redacted with (b)(6). In another version it’s unredacted – it was Hamilton Bennett, a senior director of vaccine access and partnerships.

This 35-year-old woman seems woefully underqualified, especially to “engineer the vaccine” as her role was described in the press. Moderna’s history is notable for high-profile departures of competent and experienced people. Based on press reports and accounts of insiders, Stephan Bancel’s toxic management culture led to departures of many qualified scientists including heads of R&D, Oncology, Cardiovascular, Chemistry, Rare Diseases, and even Vaccines (right around the time the company pivoted to vaccines in 2016).  Terminal incompetence is a prerequisite for terminal fraud.   (See link for article)

_______________

**Comment**

This website has posted Latypova’s important work before:   https://madisonarealymesupportgroup.com/2023/01/11/covid-gene-therapy-injections-developed-by-u-s-military-are-called-counter-measures-were-ordered-as-prototypes/

If you still believe that COVID was about public health, hopefully this article crushes that notion. You must ask yourself why information on “vaccine” manufacturer’s contracts would be redacted for “affecting the application of advanced technology in a U.S. weapons system,” and “causing serious harm to relations between the U.S. and a foreign government.”  

What on earth does a “vaccine” that is touted as preventing transmission or infection (which doesn’t), and preventing severe illness, and death (which doesn’t) have to do with U.S. weapons and harming foreign relations?  In fact, more and more is coming home to roost showing long post-COVID “vaccination” syndrome is becoming an increasingly recognized disease occurring after the COVID shots, as well as the fact they have caused more reports of adverse reactions and death than any other vaccine in the history of VAERS, which is known to only pick up 1% of reactions.

________________

And buckle up for this zinger.  You will recognize many names and agencies:

https://www.scivisionpub.com/pdfs/covid19-and-illegal-us-bioweapons-activity-an-insiders-revelations-2432.pdf

COVID-19 and Illegal US Bioweapons Activity, an Insider’s Revelations

Classen Immunotherapies, Inc., 3637 Rockdale Road, Manchester, MD. J. Bart Classen, MD* Trends in Internal Medicine Review Article ISSN 2771-5906

Citation: Classen JB. COVID-19 and Illegal US Bioweapons Activity, an Insider’s Revelations. Trends Int Med. 2022; 2(2): 1-11.

* Correspondence: Classen Immunotherapies, Inc., 3637 Rockdale Road, Manchester, MD 21102, Tel: 410-377-8526, E-mail: classen@ vaccines.net. Received: 20 Aug 2022; Accepted: 23 Sep 2022; Published: 27 Sep 2022

ABSTRACT

Millions if not billions of people now believe that the world is under a bioweapons attack. A lot of blame has been placed on the US funding of bioweapons. Dr. Anthony Fauci, Director of the US NIAID/NIH has come under severe criticism for funding the infamous “Gain of Function” research. Many believe Fauci has not acted alone or even on his own accord. The Author worked as a fellow at NIAID/NIH from 1988 to 1991, starting soon after Fauci became head of NIAID. The author witnessed first hand infiltration of NIAID/NIH by Israel’s Mossad. While working at NIAID/NIH one or more coworkers expressed a need to “preempt the next Jewish Holocaust”. For thirty years since leaving NIH the Author has paid close attention to Mossad’s involvement in illegal US bioweapon activity and attempts to disclose his observations. The Author hopes to educate the public on the current bioweapon attack with COVID-19 and vaccines. The Author believes that Mossad intends to kill billions of people. Already 70% of the world’s population have received a COVID-19 vaccine which in all appearance has the ability to cause deadly non curable prion disease. The Author hopes the information provided will help those interested in ending this covert war.  (See link for entire paper)

_________________

Article highlights

The author claims:

  • The Covid virus spike protein is an ethnic bioweapon made to kill and disable billions of people selectively through both SARS-CoV-2 infection and, principally, nucleic acid (RNA or DNA) shots that encode the spike protein and have regulatory approval or emergency use authorization, with no manufacturer liability even for massive vaccine damage to populations.
  • Differential binding of the spike protein to ACE-2 receptor variants can lead to more damage in some ethnic groups than others.Europeans are the hardest hit, and [redacted] are relatively spared. (See here, here, and here.)
  • Blackmailer and [redacted] operative Jeffrey Epstein’s list of [redacted] intelligence assets includes Donald Trump, Dr. Scott Gottlieb, Larry Ellison, Michael Bloomberg, Bill Gates, Buzzy Krongard, and others promoting Covid jabs.
  • Dr. David Gorski, a harsh critic of doctors questioning leaky Covid spike protein-encoding nucleic acid shots having no long-term safety profile, has admitted financial ties to [redacted] operative Jeffrey Epstein through Seed Media Group.
  • Robert F. Kennedy Jr. is also listed in Epstein’s contacts as a presumptive [redacted] asset.
  • Although RFK Jr. laudably warns of vaccine harms, he blames the operation on Dr. Anthony Fauci and “big pharma corruption and greed,” steering people away from [redacted], implying he is controlled opposition.  Source

This website has also posted Classen’s work before as well:

All this murky history runs in tandem with Lyme/MSIDS which also has a bioweapon component to it, a connection with Fort Detrick, and with Fauci head of NIAID – controlling the research monies and therefore, research itself (remember he’s Mr. Science).  This history is important to review, chronicle, and share as it reveals a common black thread in an ongoing playbook that corroborates Dr. David Martin‘s work.  Once you understand how deep this goes, all the powerful people involved, as well as the vast amounts of money – it all begins to make sense.  This is why politics continues to trump science, logic, and humanity.

https://news.climate.columbia.edu/2023/03/10/tick-tock-cdc-takes-its-time-treating-chronic-lyme-disease/

Tick Tock: CDC Takes Its Time Treating Chronic Lyme Disease

BY GRACE BURNS |MARCH 10, 2023
a tick on a stalk of grass

Lyme disease is caused by a bacteria that’s spread through tick bites. If left untreated, the bacteria can affect a person’s joints, heart, and nervous system. Photo: Leroy Baptiste 

My knees buckled beneath the weight of my malnourished adolescent frame. Cold, dripping sweat met its match on the tile floor. Every ounce of strength I had cried out to my parents for help. I didn’t stay conscious long enough to realize they raced up the stairs at the sound of my fall, as if on command.

The year was 2018. Losing consciousness was among the everyday occurrences in my middle-class household in suburban West Hartford, Connecticut. Life had been this way since July 5, 2017, just days before my 17th birthday, when my legs went fully numb during a run.

Not until I was almost 20 years old was I diagnosed with chronic and neurological Lyme disease — 16 strains of it, to be precise.

I blame this delay in diagnosis on the Centers for Disease Control and Prevention (CDC)’s refusal to recognize and legitimize chronic Lyme disease. Whereas many patients with Lyme disease can recover after two to four weeks of antibiotics, others, like me, suffer long-term side effects, and no one knows why. This lack of understanding makes it difficult for any medical professional to treat me in a Lyme-specific manner. Doctors are often reluctant to acknowledge Lyme as a possible diagnosis, and are not sufficiently informed to identify symptoms.

Lyme disease is caused by a bacteria that’s spread through tick bites. If left untreated, the bacteria can affect a person’s joints, heart, and nervous system.

Tests for Lyme disease are unreliable, often producing negative results despite patients later discovering they carry upwards of 5, 10, or 16 strains of Lyme-causing bacteria. There is no proven “cure” or treatment plan for chronic Lyme disease. Stringent criteria are required by the CDC to be diagnosed with the disease, and patients are often passed off to other autoimmune or psychiatric diagnoses.  (See link for article)

_______________

**Comment**

Another harrowing story.  Fortunately, there’s a good ending as the patient got to an experienced Lyme literate doctor (LLMD) for appropriate treatment.  This really is key.  Unfortunately, insurance will typically not cover this kind of treatment due to polarity within the medical community so patients must pay out of pocket.  It’s important to understand the sordid backstory to this in order to understand that attempting to get help from mainstream medicine is like shouting at the mountain.  If you are able – GO AROUND THE MOUNTAIN.  It will save you a lot of time, money, and heart-ache in the end.

For more:

https://www.lymedisease.org/californias-first-cdc-confirmed-case-of-borrelia-miyamotoi/

California’s first CDC-confirmed case of Borrelia miyamotoi

By Lonnie Marcum

May 4, 2023

A recent case reminds us that Lyme disease isn’t the only tick-borne disease we need to worry about.

Last year, the CDC confirmed California’s first known case of Borrelia miyamotoi—a tick-borne pathogen that causes a relapsing-fever illness in humans.

This discovery highlights the need for increased awareness and surveillance of emerging tick-borne illnesses across the United States.

In this case, a man from Marin County, California, sought care at a neurology clinic in San Francisco. His symptoms included recurring fever, night sweats, mild vision changes and nausea. The fevers typically lasted one day and would recur every 10-14 days. At the time, he was also undergoing monoclonal antibody therapy for multiple sclerosis.

His standard blood work was negative for fungi, Lyme disease, brucellosis and leptospirosis. Chest x-rays and abdominal CT scans were negative as well.

The only notable blood findings were a positive antigen for Epstein-Barr virus, a low platelet count (thrombocytopenia), an elevated C-reactive protein (an inflammatory marker), and an elevated procalcitonin—a biomarker that is released in response to bacterial infections.

Specialty lab testing

Considering the patient’s immunocompromised status and continued relapsing fevers, his blood was sent to a specialty lab for next-generation DNA sequencing. The specialty lab, Karius,  says it can identify over 1000 clinically relevant pathogens including bacteria, DNA viruses, fungi, and parasites from a single blood sample.

The DNA test results came back positive for Borrelia miyamotoi and were sent to the CDC for confirmation. The CDC confirmed the patient’s blood was positive for Borrelia miyamotoi and 100% identical to an isolate that had been previously collected from an Ixodes pacificus tick in Marin County. This indicates the patient acquired the infection in California.

Borrelia miyamotoi, first identified in Japan in 1995, is considered an emerging infectious disease in Asia, Europe and the United States.

A recent study found widespread evidence of Borrelia miyamotoi in human blood samples of people living in the northeastern United States. An earlier study found evidence of tick-borne relapsing fever (TBRF) Borrelia, including Borrelia miyamotoi in the blood of 26 out of 101 samples of residents of Mendocino County, California in the 1980s.

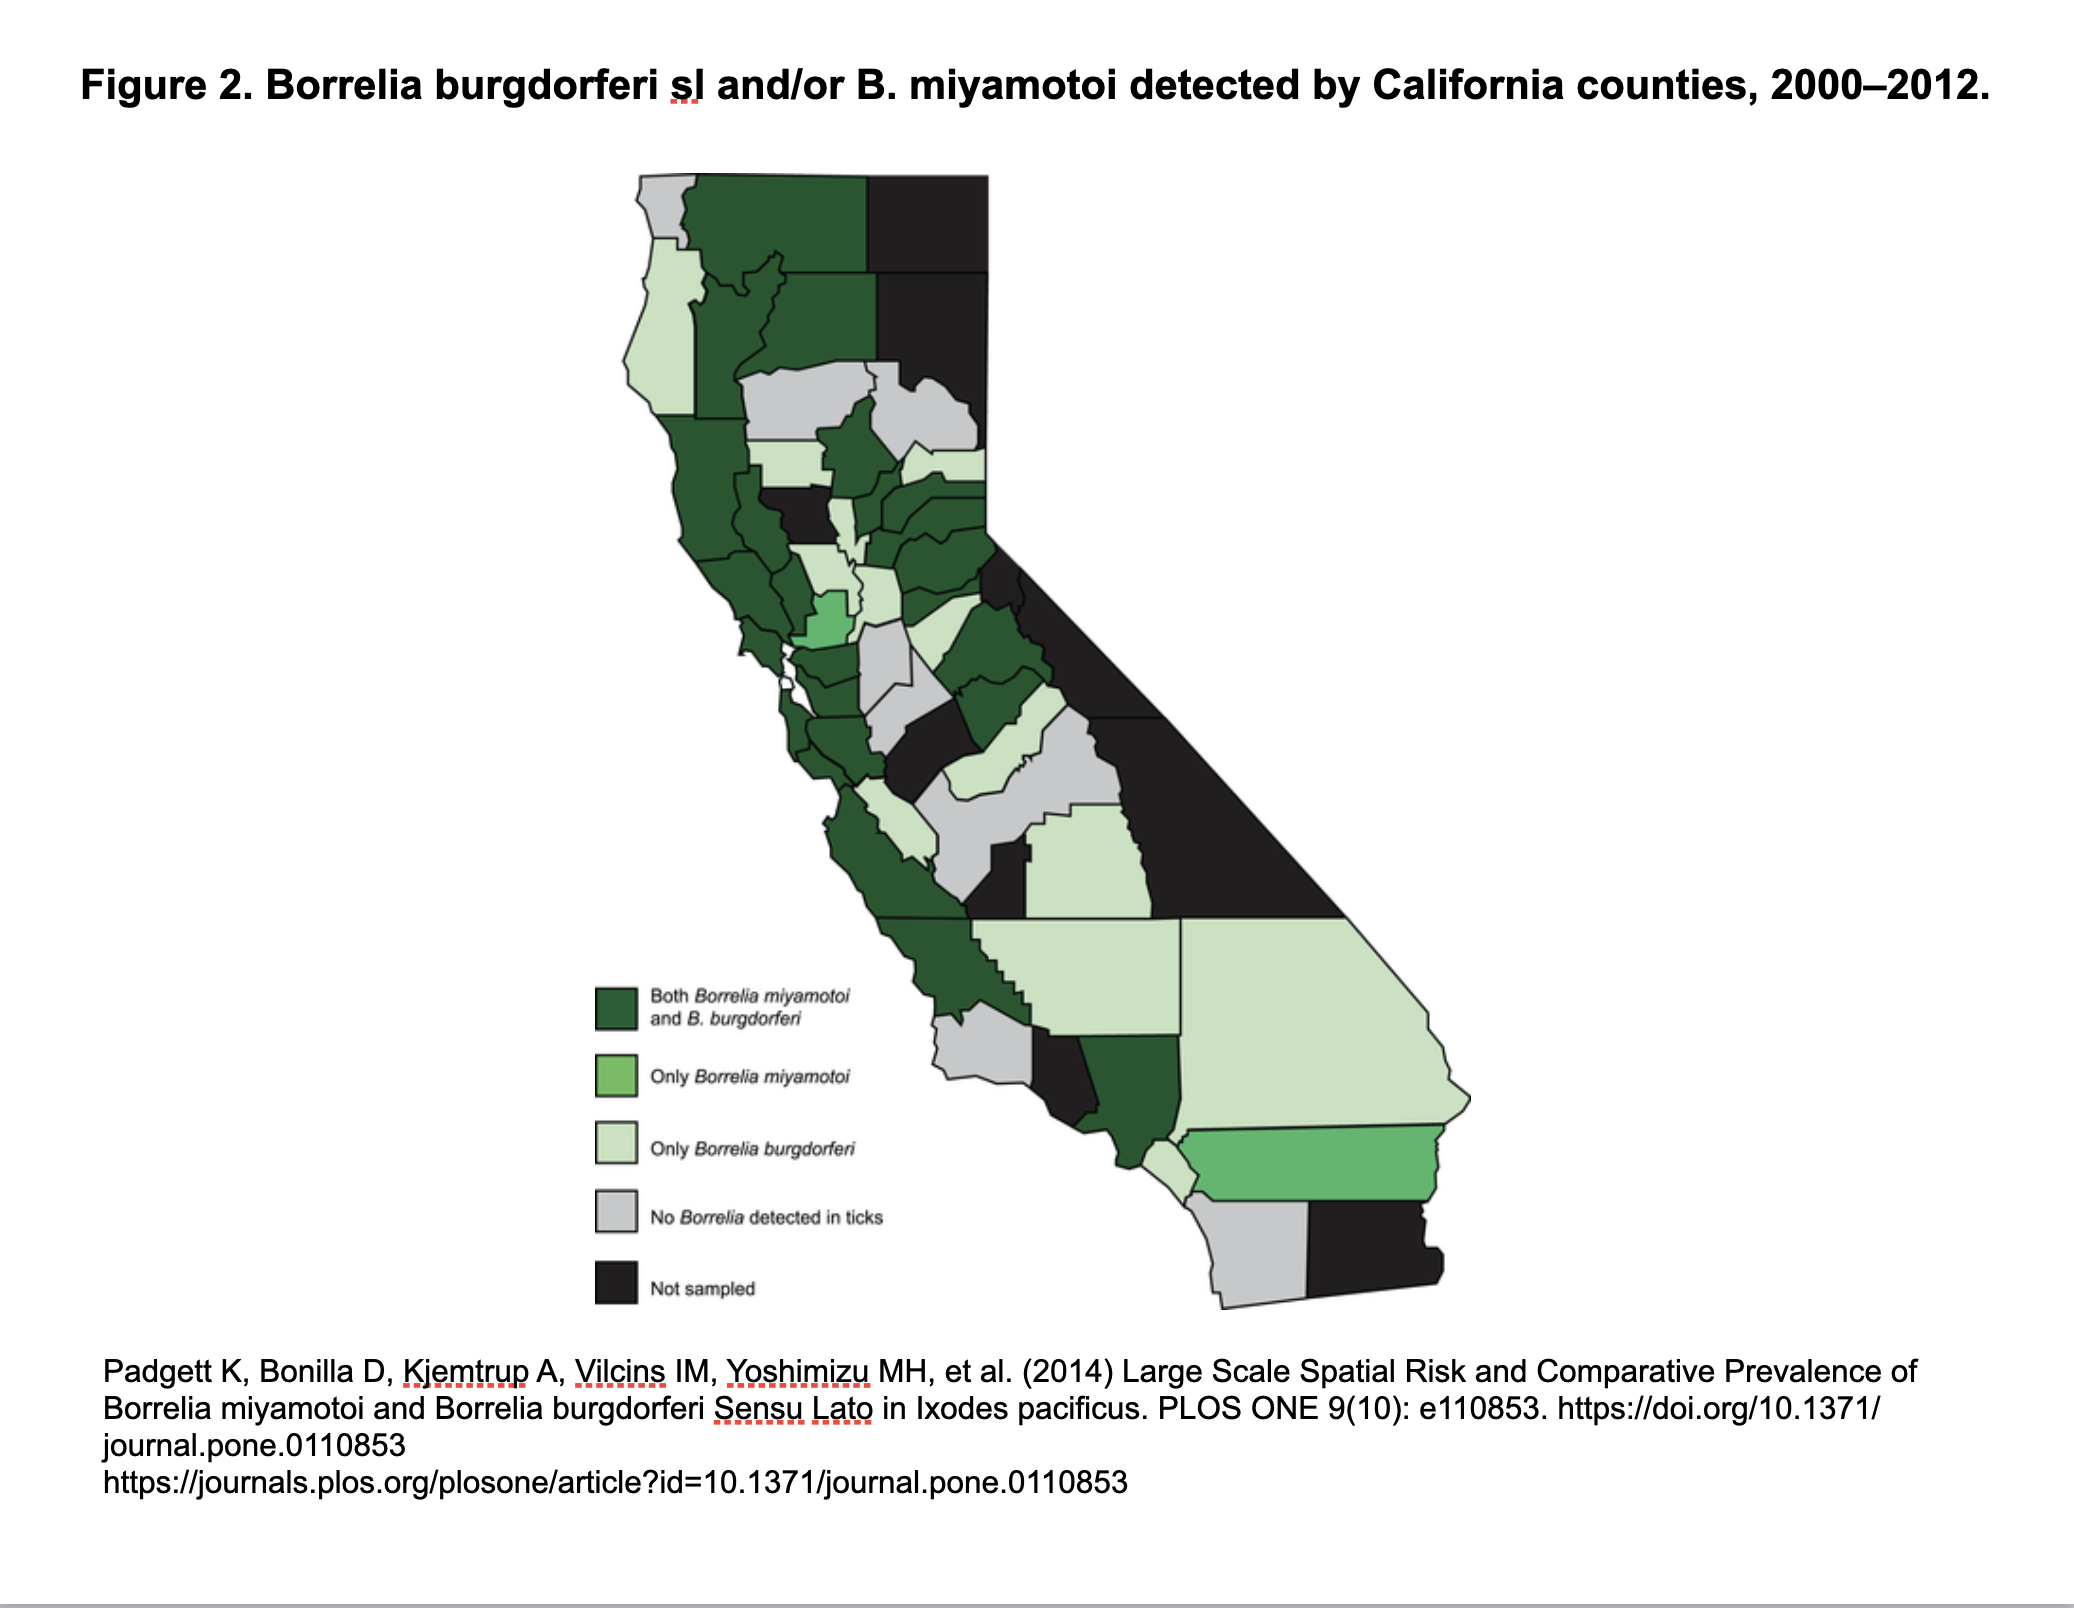
Another study found multiple species of relapsing fever Borrelia in blood samples drawn from patients in 16 out of 24 California counties. And a 13-year-long study found Borrelia miyamotoi in ticks found in 24 out of 48 counties in California (see map below).

Borrelia miyamotoi is transmitted to humans through the bite of infected blacklegged ticks. These are the same  hardbodied ticks (Ixodes scapularis, Ixodes pacificus) that transmit Lyme disease to humans and animals. Other types of North American tick-borne relapsing fever Borrelia (B. hermsii, B. turicatae, B. parkeri), are transmitted by soft-bodied ticks.

The symptoms of Borrelia miyamotoi disease are similar to those of other tick-borne illnesses, such as Lyme disease. But standard Lyme tests will be negative, making the diagnosis challenging.

TBRF

According to the CDC, the main symptoms of TBRF are high fever, headache, muscle and joint pain. Fewer than 1 in 10 patients will develop a rash. Left untreated, the symptoms typically repeat, producing a telltale pattern of relapsing fever lasting 1-3 days, followed by 7-10 days without a fever, followed by another 1-3 days of fever.

The CDC website says: “Confirmation of a diagnosis relies on 1) the use of polymerase chain reaction (PCR) tests that detect DNA from the organism or 2) antibody-based tests. Both types of tests are under development and not widely commercially available but can be ordered from a limited number of CLIA-approved laboratories.”

Treatment for TBRF involves the use of antibiotics, such as doxycycline, amoxicillin or cefuroxime . In this case the man was given a 4-week course of doxycycline and achieved complete resolution of his symptoms. One month after completing antibiotics ,follow-up laboratory testing showed complete resolution of thrombocytopenia and normalization of inflammatory markers.

All tick-borne diseases are a significant health concern worldwide, particularly in areas where ticks are prevalent. These illnesses can present with a range of symptoms, some of which can be mysterious and difficult to diagnose.

While relapsing fever Borrelia has been detected in California before, this is the first CDC-confirmed case of Borrelia miyamotoi in California.  This case highlights the need for continued education and awareness of tick-borne diseases.

As with all tick-borne illnesses, prevention is key. To reduce the risk of tick bites, take precautions when spending time outdoors, such as pre-treating shoes and clothing with permethrin, using insect repellant on yourself, your children and your pets, and performing thorough tick checks after being outdoors.

LymeSci is written by Lonnie Marcum, a Licensed Physical Therapist and mother of a daughter with Lyme. She served two terms on a subcommittee of the federal Tick-Borne Disease Working Group. Follow her on Twitter: @LonnieRhea  Email her at: lmarcum@lymedisease.org.

Reference

Rubio LA, Kjemtrup AM, Marx GE, Cronan S, Kilonzo C, Saunders MEM, et al. Borrelia miyamotoi infection in immunocompromised man, California, USA, 2021. Emerg Infect Dis. 2023 May https://doi.org/10.3201/eid2905.221638 DOI: 10.3201/eid2905.221638

Padgett K, Bonilla D, Kjemtrup A, Vilcins I-M, Yoshimizu MH, Hui L, et al. (2014) Large Scale Spatial Risk and Comparative Prevalence of Borrelia miyamotoi and Borrelia burgdorferi Sensu Lato in Ixodes pacificus. PLoS ONE 9(10): e110853. https://doi.org/10.1371/journal.pone.0110853

Additional Resources

Stanford: Tick-borne disease risk high in SF Bay Area

Yale: Tick-borne Borrelia miyamotoi widespread in northeastern US

LYME SCI: Infected ticks in California? It’s complicated.

LYME SCI: B. miyamotoi has been in California ticks for a long time

LYME SCI: Lyme-carrying ticks in West differ from their Eastern cousins

LYME SCI: How many “negative” Lyme tests are due to B. miyamotoi?

LYME SCI: Tick infection rates as high as 31% in some coastal areas of California

BALF: New interactive maps show where citizen scientists found infected ticks

For more:

And the question begging to be asked is: how many people with B. miyamotoi are falling through the cracks?  It isn’t even reportable to the CDC yet (which notoriously undercounts all things tick-borne-related).

For more:  https://igenex.com/tick-talk/what-you-need-to-know-about-borrelia-miyamotoi/

This article points out the confusion with B. miyamotoi: 

  • many separate it from other tick-borne relapsing fevers
  • while it can cause relapsing fevers, it sometimes doesn’t
  • it appears to be the only TBRF transmitted from a hard bodied tick, unlike TBRF which is mainly transmitted from a soft bodied tick (I remain skeptical of this as ticks have repeatedly been found to transmit things they shouldn’t – just like they are found in places they shouldn’t be.)
  • symptoms often resemble Lyme disease
  • you can be infected with BOTH B. miyamotoi AND Lyme disease (as well as numerous other coinfections) which will complicate symptom presentation
  • testing for B. miyamotoi is just as abysmal as it is for Lyme/MSIDS:  https://madisonarealymesupportgroup.com/2020/03/01/study-cdcs-2-tier-lyme-testing-inaccurate-in-more-than-70-of-cases/

https://www.lymedisease.org/this-easy-to-read-guide-is-packed-with-useful-information/

This easy-to-read guide is packed with useful information

By Dorothy Kupcha Leland
April 25, 2023

Hacking Lyme Disease: An Action Guide to Wellness is a compilation of articles from Dr. Marty Ross’s informative website “treatlyme.net.”

It covers a wide range of topics, including what he considers the best herbal and prescription antibiotic treatments, what to do if your previous treatments have failed to get you well, and a discussion of many alternative therapies (both pro and con).

It is not a guide to treating yourself. Dr. Ross strongly advises you to discuss these matters with your Lyme-literate practitioner. But it answers a lot of questions that Lyme patients may have, including about many alternative treatments.

The Ross Lyme Support Protocol

He outlines his own treatment guidelines for chronic Lyme and related infections, which he calls The Ross Lyme Support Protocol. He says it’s designed to:

  • Boost the immune system,
  • Improve detoxification,
  • Speed recovery,
  • Kill the infections, and
  • protect and repair from the harmful effects of the infections and the herbal and prescription antibiotics.

Dr. Ross emphasizes that treating Lyme disease is complicated. “The infection triggers an immune system cytokine reaction that affects most organs and systems of the body,” he writes. “In my experience, the great majority of people can recover if they address each of the steps in The Ross Lyme Support Protocol.”

He refers to anything that kills Lyme and related infections as “antigerms.”  These herbal and prescription antigerms include:

  • Antibiotics for bacteria like Borrelia (Lyme), Bartonella, Anaplasma, Ehrlichia, and Clostridium difficile;
  • Antifungals for intestinal yeast overgrowth;
  • Antiparasitic agents for Babesia and hidden intestinal parasites, and
  • Antivirals for chronic infections like mononucleosis and human herpesvirus 6.

However, his action steps encompass much more than just trying to eliminate bacteria. He includes recommendations regarding sleep, diet, controlling inflammation, hormones, exercise, detoxification and more.

He also discusses complicating factors such as yeast infections, mold toxin illness, and mast call activation syndrome.

A unique aspect of Hacking Lyme Disease is how it incorporates information from LymeDisease.org’s MyLymeData research project. More than 17,000 Lyme patients participate in MyLymeData, providing feedback about their treatment experiences.

Dr. Ross includes MyLymeData findings in his discussion of prescription antibiotic use as well as a wide variety of alternative medical treatments.

This easy-to-read guide is packed with lots of useful information.

TOUCHED BY LYME is written by Dorothy Kupcha Leland, President of LymeDisease.org. She is co-author of When Your Child Has Lyme Disease: A Parent’s Survival Guide. Contact her at dleland@lymedisease.org .

http://

Hacking Lyme Disease

Dr. Marty Ross

April 29, 2023

Transcript: http://lymedisease.org.au/wp-content/…

For more:

https://petermcculloughmd.substack.com/p/long-term-covid-19-vaccine-data-evidence?

Long Term COVID-19 Vaccine Data–Evidence of Sustained Vascular Injury and Thrombosis at 2 Years

Direct Observation of Retinal Blood Vessels Reveals Anticipated Disaster

MAY 5, 2023

By Peter A. McCullough, MD, MPH

Early in 2020 I published with former US FDA physician Dr. Zhang that the SARS-CoV-2 viral Spike protein was damaging blood vessels and causing blood clotting. Our observations were this was occurring at the level at the vascular endothelium. This means capillaries would be systemically injured if exposed high concentrations of the Spike protein. Dr. Bruce Patterson has demonstrated the Spike protein is long-lasting (months to years) in the human body after both severe COVID-19 infection and vaccination. This leads us to a concern, that the vaccinated would have sustained vascular damage over the long-term. Now the first two-year data report in and the news could not be worse.  (See link for article)

https://www.nature.com/articles/s41541-023-00661-7

Risk assessment of retinal vascular occlusion after COVID-19 vaccination

Jing-Xing Li, Yu-Hsun Wang, Henry Bair, Shu-Bai Hsu, Connie Chen, James Cheng-Chung Wei & Chun-Ju Lin

Abstract

Coronavirus disease 2019 (COVID-19) vaccines are associated with several ocular manifestations. Emerging evidence has been reported; however, the causality between the two is debatable. We aimed to investigate the risk of retinal vascular occlusion after COVID-19 vaccination. This retrospective cohort study used the TriNetX global network and included individuals vaccinated with COVID-19 vaccines between January 2020 and December 2022. We excluded individuals with a history of retinal vascular occlusion or those who used any systemic medication that could potentially affect blood coagulation prior to vaccination. To compare the risk of retinal vascular occlusion, we employed multivariable-adjusted Cox proportional hazards models after performing a 1:1 propensity score matching between the vaccinated and unvaccinated cohorts. Individuals with COVID-19 vaccination had a higher risk of all forms of retinal vascular occlusion in 2 years after vaccination, with an overall hazard ratio of 2.19 (95% confidence interval 2.00–2.39). The cumulative incidence of retinal vascular occlusion was significantly higher in the vaccinated cohort compared to the unvaccinated cohort, 2 years and 12 weeks after vaccination. The risk of retinal vascular occlusion significantly increased during the first 2 weeks after vaccination and persisted for 12 weeks. Additionally, individuals with first and second dose of BNT162b2 and mRNA-1273 had significantly increased risk of retinal vascular occlusion 2 years following vaccination, while no disparity was detected between brand and dose of vaccines. This large multicenter study strengthens the findings of previous cases. Retinal vascular occlusion may not be a coincidental finding after COVID-19 vaccination.

_______________

**Comment**

Not being a paid-subscriber, I could not access the study McCullough mentions; however, there have been case reports showing long post-COVID “vaccination” syndrome (LPCVS).

  • In this one, a 39 year old male with an uneventful medical history developed severe adverse reactions immediately after the third dose of Moderna.  Symptoms included brief fever, headache, flickering eyes, skin rashes, tiredness, insomnia, disorientation, dizziness (brain fog), tiredness, impaired thinking and concentration, emotional disorders, neck swelling, pulling/shaking/pulsating feeling inside the head, white light after eye closure, whole body vibration, panic attacks, pain in left ear, word finding disorders, various skin reactions, and non-specific white matter lesions in a frontotemporal distribution.
  • This retrospective analysis of clinically confirmed LPCVS states it is an “increasingly recognized disease that occurs after SARS-CoV-s vaccination and lasts for more than 4 weeks.  Important excerpt:

Although LPCVS leads to long-term disability, it is not widely recognized and not always accepted by manufacturers, health authorities, and even scientists. LPCVS should not be dismissed as a functional disorder and patients with LPCVS should be taken seriously.

  • This study asks if adverse events are being missed and then goes on to state that adverse events occurring with the COVID injections have never happened with other previously administered vaccines and are mainly vascular side effects that have occurred in the brain, vascular system of the limbs, abdomen, and heart, including CVST/CVT, VITT, DIC, DVT, PTE, CLS, AHA, ITP, SVT, cardiac arrest, HF, MI, pericarditis, and myocarditis, respectively. Ocular involvement includes uveitis, bilateral retinal detachment, central serous retinopathy, acute macular retinopathy, AAION and AZOOR, and paracentral acute middle maculopathy. The thyroid gland can also cause thyroiditis. Neurological side effects such as GBS, Bell’s palsy, stroke, and transverse myelitis have also been observed. It causes filler on the face. In addition to facial involvement, skin infections such as erythema multiforme, chilblains, and cutaneous vasculitis have also been reported. It causes autoimmune hepatitis in the liver and has caused many complications for the kidneys. Symptoms of immune rheumatologic events have also been observed in some patients. Lymphadenitis is one of the immune complications in the lymph nodes. In addition to the above, it also causes spontaneous abortion and menstrual problems in women. CVST/CVT, Cerebral venous sinus thrombosis/Cerebral venous thrombosis; VITT, Vaccine-induced immune thrombotic thrombocytopenia; DIC, Disseminated intravascular coagulation; DVT, Deep vein thrombosis; PTE, Pulmonary thromboendarterectomy; CLS, Capillary leak syndrome; AHA, Acquired hemophilia A; ITP, Immune thrombocytopenic purpura; SVT, Supraventricular tachycardia; HF, Heart failure; MI, Myocardial infarction; AAION, Arteritic anterior ischemic optic neuropathy; AZOOR, Acute zonal occult outer retinopathy; GBS, Guillain-Barré syndrome.

I think reality is beginning to come home to roost.  It’s going to be pretty hard to continue to sweep these devastating injuries and sudden deaths under the rug as they have been doing; however, until people decide to speak up and be willing to connect the dots, ‘the powers that be’ will continue to ignore what’s happening before their very eyes and pretend it doesn’t exist.

For more: