Archive for the ‘Viruses’ Category

SARS-CoV2 – Biological Weapon? Update With Professor Boyle & Another ‘Must See’ Video Showing Fauci Behind Funding China to do COVID-19 Research

**UPDATE**

When the article was written much was unknown about the impact of COVID, but even a year ago infectious disease experts called for lockdowns to be lifted.

COVID mortality is quite similar to the flu, despite the continued propaganda by corrupt public health ‘authorities’ and a complicit media.  Here we learn that only 0.9% of ‘verified cases’ died of COVID, numbering 152 not 17,000 as claimed.  This paper outlines 13 different serious flaws and inconsistencies, any one of which undermines the essential foundations of Covid-19 theory.

I do not accept the methods used by the CDC for calculating excess deaths, where they compared the 2020 all-cause death curves to those of prior years, claiming all deaths above an arbitrary average over a few years were due to Covid-19. The CDC and WHO approaches are filled with errors and many wrong assumptions.  Dr. James DeMeo

  • This study shows chances of dying from COVID for the average 50-64 year old are 1 in 19.1 million.
  • This study states COVID-19 fatality rate is the “worst miscalculation in the history of humanity.”
  • Mortality has been within the norms of any given year, and has not resulted in an excess number of deaths or a death toll higher than normal.  The collateral damage from pandemic response measures is nearly incalculable. Public health, both physical and mental, as well as the global economy, have all suffered tremendous blows.
  • As early as March, 2020 experts have been challenging the coronavirus narrative.
  • This explains the many problems with CDC death statistics.
  • Here the CDC admits to lying about COVID mortality, and here  more trickery is explained on how the CDC manipulates data.
  • https://madisonarealymesupportgroup.com/2020/03/17/stunning-insights-into-the-corona-panic-by-dr-wolfgang-wodarg/  Important quote:

We are currently not measuring the incidence of coronavirus diseases, but the activity of the specialists searching for them.  https://www.wodarg.com

https://articles.mercola.com/sites/articles/archive/2020/04/26/is-coronavirus-a-biological-weapon.aspx?  Video Interview Here

Is SARS-CoV2 a Biological Weapon?  Yes, States Francis Boyle, PhD

April 26, 2020

STORY AT-A-GLANCE

  • Francis Boyle, who drafted the Biological Weapons Anti-Terrorism Act of 1989, believes COVID-19 is a weaponized pathogen that escaped from Wuhan City’s Biosafety Level (BSL) 4 facility
  • A Lancet paper published by physicians who treated some of the first COVID-19 patients in China showed that patient zero, the one believed to have started the transmission, was nowhere near the Wuhan seafood market. What’s more, there were no bats sold in or even close to the market
  • SARS-CoV-2 appears to be a benign bat coronavirus modified to integrate spike proteins that allows the virus to enter human cells by attaching to ACE-2 receptors
  • The virus also appears to have been modified to integrate an envelope protein from HIV called GP141, which tends to impair the immune system. A third modification appears to involve nanotechnology, which allows the virus to remain airborne longer

Francis Boyle, a former advisory board member for the Council for Responsible Genetics, is a professor of international law at the University of Illinois College of Law.

His educational background1 includes an undergraduate degree from the University of Chicago, a juris doctor (lawyer) degree from Harvard and a Ph.D. in political science. For decades, he’s advocated against the development and use of bioweapons, which he suspects COVID-19 is.

In fact, Boyle was the one who called for biowarfare legislation at the Biological Weapons Convention of 1972, and the one who drafted the Biological Weapons Anti-Terrorism Act of 1989, which was passed unanimously by both houses of Congress and signed into law by George Bush Sr.

In our first, March 8, 2020, interview, Boyle shared his views on the origins of the novel coronavirus, SARS-CoV-2. Here, we continue our discussion, as more details have emerged about this virus. One of the criticisms raised since our last interview is that Boyle has no formal training in virology. When asked what makes him qualified to speak about this particular virus, he says:

“I went to the University of Chicago, which is one of the top five universities in the country, if not the world. There I took their bio pre-med sequence, which was biochemistry, population biology and genetics, and got straight A’s.

I was in there competing with all the University of Chicago bio pre-med students for grades and my biochem lab partner went to Harvard Medical School.

I won the University of Chicago’s Sigma Zi award and prize in biology for my graduating year. They gave out one per year and it usually went to seniors, but in my case, they had to make a special exception because I was a graduating junior.

So, yes, I’m not a scientist, but one of the reasons the Council for Responsible Genetics asked me to get involved was that my knowledge in this field was well-known to my life science friends there on the Harvard faculty, and that’s how I got involved here.

I had basic rudimentary training, actually very good training, at the University of Chicago, and my professors there, professor friends at Harvard in the life sciences, I guess they vouched for me. So, when I was asked to join shortly after CRG was founded in 1983, I agreed to do so and they asked me to handle their biological warfare work.”

SARS-CoV-2 — A Biological Warfare Weapon

“Novel coronavirus” means it is a new virus not previously known to previously infect humans. The currently held conventional view is that SARS-CoV-2 was transmitted through animals (zoonotic transmission), specifically bats. Boyle dismissed this notion in our initial interview, and still refutes the idea.

While a widely-cited paper,2 published in the Nature journal on February 3, 2020, claims to establish that SARS-CoV-2 is a coronavirus of bat origin that then jumped species, the work of one of the authors of that paper, Shi Zhengli, actually involved the weaponization of the SARS virus. (Another Nature paper3 published that same day reiterates the idea that the COVID-19 pandemic is zoonotically transmitted.)

However, according to Boyle, other scientific literature establishes that this is indeed an engineered synthetic virus that was not transmitted from animals to humans without human intervention.

For starters, a Lancet paper4 published February 15, 2020, by physicians who treated some of the first COVID-19 patients in China showed that patient zero, the one believed to have started the transmission, was nowhere near the Wuhan seafood market.

What’s more, there were no bats sold in or even close to the market. At least one-third of the patients reviewed also had no exposure or links to that market. This data supports the counter-hypothesis that SARS-CoV-2 was not zoonotically transmitted but is in fact an engineered virus.

Even U.S. politicians and intelligence agencies are starting to say they believe the virus leaked from the Wuhan BSL4 lab.5,6 In our first interview, Boyle discussed published research establishing that the novel coronavirus is SARS, which is a weaponized version of the coronavirus to begin with Wuhan BSL 4 lab, with added gain-of-function capabilities that increases its virulence (makes it spread easier and faster).

“I also went through the scientific article where the Australian health board working with Wuhan … genetically engineered HIV into SARS,” Boyle says. “So, that is all verified in scientific papers. In addition, it seems to me that they took that back to the [Wuhan] BSL4 and applied nanotechnology to it.

The size of the molecules are maybe 120 microns, which indicates to me we are dealing with nanotechnology. That’s [something] you need to do in a BSL4. Biological weapons nanotechnology is so dangerous, people working with it have to wear a moon suit with portable air …

We also know that one of the cooperating institutions [to Wuhan BSL4] was Harvard, and that the chairman of the Harvard chemistry department, [Dr. Charles Lieber], a specialist in nanotechnology,set up an entire laboratory in Wuhan where [according to reports] he specialized in applying nanotechnology to chemistry and biology.

My guess is, based on what I’ve read in the literature, that they tried to weaponize all that together. And that is SARS-CoV-2 that we are dealing with now.

So, it’s SARS, which is genetically engineered biowarfare agent to begin with. Second, it has gain-of-function properties, which makes it more lethal, more infectious. It has HIV in there. That was confirmed by an Indian scientist … and it looks like nanotechnology [has been used] … An MIT scientist who did a study found that it traveled 27 feet through the air. And that, I guess, was in lab conditions.

That, I think, is why it’s so infectious, and that is what I believe we are dealing with here … [This is] why the 6-foot [social distancing recommendation] by the CDC … is preposterous. Even doubling that will do you no good. If there is nanotechnology, it floats in the air …

I am not saying that China deliberately released this, shooting itself in the foot. But it was clear they were developing an extremely dangerous unknown biological weapon that had never been seen before, and it leaked out of the lab.

And as you see in the Washington Post,7 U.S. State Department officials … [reported] back to Washington that there were inadequate safety precautions and procedures in that lab to begin with. We also know that SARS has leaked out of other Chinese biological warfare labs. So right now, I believe that is what happened here …

I personally believe that until our political leaders come clean with the American people, both at the White House and in Congress and our state government, and publicly admit that this is an extremely dangerous offensive biological warfare weapon that we are dealing with, I do not see that we will be able to confront it and to stop it, let alone defeat it.”


The Origin of SARS-CoV-2

While Boyle made the origin of SARS-CoV-2 clear in our initial conversation, as I started reading some of the literature it really was shocking because one of the primary investigators on the 2015 paper8 from the University of North Carolina — “A SARS-like Cluster of Circulating Bat Coronaviruses Shows Potential for Human Emergence” — was Dr. Shi Zhengli, a virologist who in 2010 had published a paper9 discussing the weaponization of the SARS virus.

Normally, while the coronavirus found in bats may be SARS,10 it typically does not infect humans as it does not target the ACE-2 receptor. The infectious agent causing the current pandemic is called SARS-CoV-2 — SARS standing for “serious acute respiratory infection” and CoV-2 indicating that it’s a second type of SARS coronavirus known to infect humans.

SARS-CoV-2, of course, contains the genetic modification to attach to ACE2 receptors in human cells, which allows it to infect them. Zhengli’s publications show that she engineered this bat coronavirus into one that crosses species and infects humans. She has in fact been working on this for more than 10 years.

“That is why I said SARS was a bioengineered warfare weapon to begin with,” Boyle says. “And that is what … [the University of] North Carolina and … the Australian lab were trying to make even more dangerous with the gain-of-function and the HIV. So … SARS was a biological warfare [agent] to begin with, it leaked, and that is the origin of the [COVID-19] epidemic.”

In addition, an Indian paper11,12 that ended up being withdrawn due to intense political pressure, shows a specific envelope protein from the HIV virus called GP41 was integrated in the RNA sequences of SARS-CoV-2. In other words, the implication is that the HIV virus was genetically engineered into SARS.

So, in summary,

  • SARS-CoV-2 appears to be a bioengineered bat coronavirus13 — which was initially benign and nontransmittable to humans.
  • Zhengli then genetically modified the virus to integrate spike proteins that allows the virus to enter human cells by attaching to ACE-2 receptors. That was the first modification.
  • The second modification was to integrate an envelope protein from HIV called GP141, which tends to impair the immune system.
  • A third modification appears to involve nanotechnology to make the virus light enough to remain airborne for a long time, apparently giving it a range of up to 27 feet.14

Nanotech Expert With Wuhan Connection Arrested

While the BSL4 lab in Wuhan may have leaked the virus, its creation does not appear to be limited to the Chinese. As noted by Boyle in his comment above, the chairman of the Harvard department of chemistry, nanoscience expert Dr. Charles Lieber, was arrested earlier this year by federal agencies, suspected of illegal dealings with China.15 Lieber has denied the allegations.

The Wuhan University of Technology (WUT) allegedly paid him $50,000 a month from 2012 to 2017 to help establish and oversee the WUT-Harvard Joint Nano Key Laboratory. He also received another $150,000 a month in living expenses from China’s Thousand Talents program. The problem was, Harvard officials claim they had not approved the lab and didn’t know about it until 2015. Boyle comments:

“The cover story here — that Harvard didn’t know what was going on — is preposterous. I spent seven years at Harvard. I have three degrees from Harvard. I spent two years teaching at Harvard.

Of course Harvard knew that its chair of the chemistry department had this lab in Wuhan, China, where he was working on nanotechnology with respect to chemical and biological materials. That’s been reported. They didn’t say what the materials were. In addition, it has now been reported that Harvard was a cooperating institution with the Wuhan BSL4.”

Researchers Working on Gain-of-Function to Spanish Flu

If you think SARS-CoV-2 is bad, be glad it’s not the weaponized version of Spanish flu, which has also been in the works, according to Boyle. He says:

“[The University of North Carolina’s] work was existentially dangerous and they knew it at the time. If you read the UNC scientific article16 [cowritten by] the Wuhan BSL4 scientist [Shi Zhengli] … it says, ‘Experiments with the full-length and chimeric SHC014 recombinant viruses were initiated and performed before the GOF research funding pause and have since been reviewed and approved for continued study by the NIH.’

It says recombinant … So, they admit it was gain-of-function [research]. [The research] was paused by NIH17 [National Institutes of Health]. Why was it paused by NIH? Because there was a letter put out by large numbers of life scientists at the time saying this type of gain-of-function work … could be existentially dangerous if it got out in the public. Therefore, it had to be terminated … [But] the NIH was funding this in the beginning …

A footnote here: I read the NIH’s pause letter to the University of North Carolina, and UNC was doing two gain-of-function research projects. The other one was with Dr. [Yoshihiro] Kawaoka from the University of Wisconsin, who had resurrected the Spanish flu virus18 for the Pentagon.

He, according to the pause letter, was also there doing gain-of-function work on the flu virus — one could only conclude it was the Spanish flu virus. It did not say the Spanish flu, but they also put a gain-of-function pause on that type of deadly research …

I mean, the Spanish flu, we all know what that is, so imagine giving the Spanish flu gain-of-function properties, making it even more lethal and more infectious. That’s exactly what was going on there at that UNC lab …”

Disturbingly, while the NIH halted funding of this kind of gain-of-function research on lethal pathogens in 2014, it reauthorized it in December 2017,19 and Boyle suspects Kawaoka’s work may have been restarted as well, although he’s not found proof of it yet.

“So, this was existentially dangerous work that was going on at that UNC lab. Everyone knew it, NIH funded it, NIAID under Dr. Fauci funded it as well. They knew exactly how dangerous this was. They paused it and then they resumed it,” Boyle says.

Can Violations of Biowarfare Treaty Be Enforced?

As mentioned, Boyle is a professor of international law and drafted an international treaty on biowarfare agents and weapons. That law is still in force, and would provide life imprisonment for everyone involved in the creation and release of SARS-CoV-2, were it officially concluded to be a biowarfare agent.

“If you read that UNC article,20 it says exactly it was dealing with synthetic molecules … And in my biological weapons anti-terrorism act of 1989, I specifically criminalized — by that name — synthetic molecules.

That is why, at first, the whole synthetic biology movement … was set up by the Pentagons DARPA. They funded the whole thing. And it’s DARPA money that is behind synthetic biology, gene drive and all the rest of it.

And that is why at the first convention of synthetic biologists, in their final report, one of their key recommendations was the repeal of my biological weapons anti-terrorism act, because they fully intended to use synthetic biology to manufacture biological weapons …

The law still applies. It provides for life imprisonment for everyone who has done this … all the scientists involved at the University of North Carolina and everyone who funded this project, knowing that it was existentially dangerous — and that includes Fauci and [people at] the NIH … UNC, Food and Drug Administration … the Dana Harvard Cancer Institute at Harvard … the World Health Organization …”

So, just how would we get that process of justice going? Boyle explains:

“There are two ways. First, you’re going to have to pressure the Department of Justice to prosecute these people. That might be very difficult to do. Federal statutes require indictments to be brought by U.S. attorneys. However, just with respect to North Carolina, state law applies there too. I haven’t researched North Carolina law; however, I was originally hired here to teach criminal law and I taught it for seven or eight years …

To have criminal intent, one of the variants of criminal intent is the demonstration of grave indifference to human life. And that is the criminal intent necessary for homicide.

So in my opinion, and my advice would be, if we can’t get [attorney general William Pelham] Barr to sign off on prosecuting these people, that the district attorney, state’s attorney, attorney general out there in North Carolina, institute and indict everyone involved in this North Carolina work for homicide.

And that could include up to and including murder, malice of forethought. Again, one of the elements can be manifestation of grave indifference to human life. And it’s clear from this article [the 2015 UNC paper21], they knew it was gain-of-function, they paused it because it was existentially dangerous, it was then reapproved and they continued it.

So, I think a good case could be made, certainly, for indicting these people under North Carolina law by North Carolina legal authorities, if the federal government is not going to do it for us, under my law [the Biological Weapons Anti-Terrorism Act of 1989]. But again, I want to make it clear, I haven’t research North Carolina law.”

Time to Shutter All BSL4 Laboratories?

Boyle is adamant that all BSL3 and BSL4 laboratories must be closed down and all biowarfare work with lethal pathogens ceased. “They are all existentially dangerous,” he says. “This is a catastrophe waiting to happen. And it is now happened. Here we are. It’s staring us in the face.”

Certainly, COVID-19 is nowhere near as devastating as the Black Death or the Spanish flu of 1918, both of which exacted a shocking death toll, all without the aid of synthetic molecules and nanotechnology.

The very idea that any of these horrific illnesses might be brought back in turbo-charged form should be terrifying enough for the world to unite in saying “No thanks; we don’t want or need that kind of research going on.” What value have these dangerous laboratories provided to date compared to the risk they are exposing all of us to?

In closing, while Boyle believes COVID-19 has the ability to become a serious pandemic killer, I strongly disagree. Based on all the data I’ve seen so far, I believe he’s wrong on this point, and I suspect the death toll due to economic hardship and emotional stress will be far worse than the disease itself.

(See top link for sources)
_________________
**Comment**
This interview, which is lengthy but incredibly important to understand, connects the dots I’ve been collecting and sitting on.
  • Yet, Professor Boyle points out the likelihood of Lieber’s involvement due to his expertise in nanotechnology. Research has shown COVID-19 travels up to 47 feet in the air. The only way that can happen, according to Boyle, is if nanotechnology has been used.
  • Dr. Mercola and Dr. Boyle both agree that governments are piggybacking upon the virus for control, where they disagree is in the deadliness of the virus. Based upon SARS mortality, Boyle is stating mortality might be 15% or higher.  Mercola states that current information is showing mortality well under 1%.  The problem is that poor testing has resulted in a lack of good, reliable data.  Time will tell.
  • Another important point mentioned in the video is the fact that Boyle states scholarly journals are often bought off.  A a result there’s a lot of junk science being done. In the case of COVID-19, a glaring conflict of interest should have caused the rejection of an article in the Feb. 2020 issue of Nature stating that COVID-19 originated from a bat. One of the authors (Zheng-Li Shi) worked at the Wuhan Lab.
I will add to this today by adding an important video from the Next News Network with even more alarming information:
 Approx. 13 Min.
April 18, 2020

Trump Investigating 3.7 Million Obama era Grant to Wuhan Lab

  • Dr. Fauci, under the Obama administration in 2014, circumvented the Department of Homeland Security’s moratorium on coronavirus research in the U.S. by outsourcing the research to China.
  • In 2017 Dr. Fauci prophetically stated that there was going to be a “surprise” outbreak.

When a reporter asks Fauci about COVID-19 being man-made, Fauci only points to the paper (Nature?) claiming once again it’s a just virus that jumped species.

It’s not looking good for Dr. Fauci.

COVID-19 And The Elephant in The Room

https://www.europeanscientist.com/en/article-of-the-week/covid-19-and-the-elephant-in-the-room/

April 16, 2020

Covid 19 and the elephant in the room

Covid 19 and the elephant in the room
Obesity and chronic metabolic disease is killing COVID -19 patients: now is the time to eat real food, protect the NHS and save lives. 
(See link for article)
____________________
**Comment**
Important quote: 
It is well known in the medical literature that excess body fat induces immune dysregulation and chronic inflammation which is directly linked to the cytokine storm that is responsible for Acute Respiratory Distress Syndrome seen in influenza and other respiratory viruses. (4)
The article also admits that it’s highly likely another international viral pandemic will occur in the future.  By addressing the underlying factors we would have a healthier population. It goes on to say:

“Hopefully if and when that occurs a lockdown will not be required.”

Don’t hold your breath.  From where I sit and from what I’m reading, future lockdowns with decreasing civil liberties are the wave of the future unless we speak up now.

CDC Playbook: Learning From Lyme

April 25, 2020

By Alicia Cashman MS, Lyme patient and advocate

While most of the world is staggering with newly imposed social distancing measures, worrying about viruses and how to bolster the immune system, chronic Lyme patients simply carry on doing these things daily. They’ve been isolated for some time – either to avoid illness due to being immunocompromised or because they were forced into exile by authorities who tell them the illness they are struggling with simply doesn’t exist. In time, family and friends become more and more distant because they tend to believe the authorities. Authorities, after all, are honest and are looking after public health – aren’t they?

They say history repeats itself, which appears to be the case regarding COVID-19 when you study the sordid history of how Lyme disease has been and continues to be handled.
The CDC Insists Upon Using Its Own Tests

Due to decisions made at a conference in Michigan, serology testing criteria for Lyme Disease were purposely manipulated for vaccine development. To this day the CDC insists upon its own two-tiered testing which research has proven is abysmal and misses a vast majority of cases. It can’t distinguish between active, past, or reinfection.  It has now been removed, but the CDC website used to call specialized CLIA certified labs testing for tick-borne illness, “home-brewed.” I personally heard a pediatrician use those exact words at the Wisconsin State Capital in his effort of delegitimatizing patients who are forced to go to specially trained doctors using these labs to get diagnosed and proper treatment. This history is disturbing in and of itself but should particularly concern us in light of current events.

The CDC also insisted upon their own COVID-19 tests.  It was just discovered that CDC COVID-19 tests were initially contaminated with COVID-19 – making ALL numbers based upon those tests absolutely worthless. COVID-19 laced tests were also found in the UK.  Due to contamination, which they state on their website is a “problem with a reagent,” the entire United States is in lockdown. Had accurate testing been accepted by the CDC from the WHO from the start, authorities would have had accurate data to base decisions upon. This article states there are only 12 labs outside the CDC with the capability to test for the virus; however, as of the beginning of March, they hadn’t received FDA authorization to do their own testing. The CDC website states the following:

“This message is to remind clinical laboratories that this is currently the only EUA assay for severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), the virus that causes COVID-19. Any laboratory that is not designated by CDC as a qualified laboratory and is implementing a COVID-19 diagnostic test other than the CDC EUA assay must contact the FDA to obtain an EUA before any COVID-19 diagnostic testing may be performed in their facilities.”

Compare that statement with the following:

“The conference proceedings recommended a two-test methodology using a sensitive enzyme immunoassay (EIA) or immunofluorescence assay as a first test, followed by a western immunoblot assay for specimens yielding positive or equivocal results (1,2).

On July 29, 2019, FDA cleared several Lyme disease serologic assays with new indications for use based on a modified two-test methodology (4). The modified methodology uses a second EIA in place of a western immunoblot assay. Clearance by FDA of the new Lyme disease assays indicates that test performance has been evaluated and is ‘substantially equivalent to or better than’ a legally marketed predicate test.“

In other words, you better use our tests. If you think that FDA cleared tests are effective, think again. The CDC has monopolized Lyme testing since the beginning of time, dooming patients to a life-time of suffering.

This article states that only two government agencies are required by law to be “patient-centered,” the FDA and the Patient Centered Outcomes Research Institute (PCORI), yet Lyme patients continue to experience false negative results on CDC 2-tiered testing. Negative results means no diagnosis and no treatment. Patients and advocates have complained profusely with no change in testing.

The reason for insisting upon their own tests become clear when you go down rabbit-holes to discover they own patents on nearly everything surrounding the diseases they have tests for.  Please also see ConflictReport.  Dr. Fauci, director of NIAID, and a leader in the Corona Task Force has numerous patents, and a long list of conflicts of interest.

  • Journalist Mary Beth Pfeiffer summarizes CDC testing incompetence.
  • James Lyons Weiler, Phd also reveals the CDC’s testing fiasco. He knows that of which he speaks as he attempted to have the CDC test his own test for Ebola. Let’s just say he was promptly rebuffed.
  • Currently, a pathologist is suing the CDC for their willful suppression of direct detecting methods.
  • Professor Lane hit the same brick wall regarding testing.
  • Regarding COVID testing, the president of Tanzania (PhD Chemistry) punked the WHO by sending in goat, fruit, and motor-oil samples to be tested for COVID-19.  Half came back positive! 
  • The creator of the PCR states it was never created to diagnose patients but for research and manufacturing purposes.
  • Dr. David Rasnick, bio-chemist, protease developer, and former founder of an EM lab called Viral Forensics states,“I’m skeptical that a PRC test is ever true.” When asked his advice for people wanting to be tested for COVID-19, he said:
“DON’T DO IT…NO HEALTHY PERSON SHOULD BE TESTED. IT MEANS NOTHING BUT IT CAN DESTROY YOUR LIFE, MAKE YOU ABSOLUTELY MISERABLE.”
  • According to David Crowe, Canadian researcher with degrees in biology and mathematics, host of The Infectious Myth podcast, and President of the think-tank Rethinking AIDS:

“The first thing to know is that the test is not binary,” he said. “In fact, I don’t think there are any tests for infectious disease that are positive or negative. What they do is they take some kind of a continuum and they arbitrarily say this point is the difference between positive and negative.”

Further, and more importantly, COVID testing does not detect SARS-COV-2 due to the fact the virus has not been isolated/purified from all else. You can’t test for something specific if you don’t have that information.  COVID testing is not specific to a particular virus people have tested positive, then negative, then positive within hours or days.  The test simply picks up viral fragments – some of which are completely dead and benign – not causing illness at all, and some are from other strains of coronaviruses such as the common cold, but it’s all being falsely labeled COVID-19 – further inflating case numbers and fear.

Lastly, there’s the very important issue of PCR cycle threshold, which was set at 40 (although this varied from lab to lab.  Experts have weighed in stating a PCR cycle of 40 is far too sensitive and that it should be set much lower – around 30.  Cases plummeted when the cycle threshold was lowered proving this fact.  What is frightening about this is health ‘authorities’ can manipulate this cycle threshold for their own nefarious reasons.

This exact same fact is true with Lyme/MSIDS testing as well and is why research shows a majority do not test positive.

The CDC wants their own tests & patents so they can create their own vaccines and drugs they will profit from.

A vaccine called Lymerix caused Lyme-like symptoms in many. In fact, it can be directly linked to 222 deaths and hundreds of adverse reactions, and these are only the ones that were recorded.

The CDC to-date hasn’t even attempted to address the immune issues caused by Lymerix. They just deny it ever happened. In fact, another Lyme vaccine is in the works which still uses the same OspA component which is attributed with problems in the first human vaccine.

Fool me once, shame on you – fool me twice, shame on me.

COVID-19 vaccines have been fast-tracked thereby bypassing important safety studies. Dr. Hotez, a vaccine researcher, is on record stating previous respiratory vaccines caused “paradoxical immune enhancement“:

James Lyons Weiler, PhD also gives the following chilling prediction:

When Phase I trials become Phase II trials people will start getting infected w/SARS-CoV-2 following vaccination and start dying at even higher rates due to disease enhancement caused by Pathogenic Priming from SARS-CoV-2 vaccination – something the vaccine developers SHOULD have tested for in animal studies, but skipped.

Even the FDA is worried about potential risks of the PER C6 Ad5 technology (aborted fetal cells) within many COVID-19 vaccines, which not only has moral implications but oncogenicity and infectivity concerns. The vaccine also uses electricity to drive DNA into your cells.  

A group of doctors recently wrote a paper about the emergency use authorized, fast-tracked COVID “vaccines” and state they are needless, ineffective and dangerous. 

  • needless because there are effective treatments  (Scroll to comment section)
  • ineffective because they don’t stop transmission or keep you from becoming ill
  • dangerous due to causing: viral immune escape, an inevitable steep incline in future severe COVID cases, antibody-immune enhancement, a condition where the “vaccinated” suffer with more severe illness when exposed to the wild virus, but also any infection.  There are also  unsafe epitopes within the injections, and mounting reports of adverse reactions and deaths after these injections, which aren’t “vaccines.”

Faulty testing issues and the subsequent push for vaccines are uncannily similar between Lyme and COVID-19 and should strongly remind us that the CDC is a vaccine manufacturing company first and foremost – to the detriment of severely ill and desperate patients.

Why Should We Trust the CDC?

The question begging to be asked is why should anyone trust the CDC? Their track record speaks for itself. Even CDC scientists have formed a group exposing the corruption from within. They’ve also lied about flu figures for decades. The ACIP, a group within the CDC, votes “Yes” for new vaccines despite having no safety data. And let us never forget the CDC whistleblower who exposed that scientists were ordered to purposely destroy data showing that African-American males who got the MMR vaccine before 36 months had a 250% increase in autism diagnoses.

Recently, microbiologist Judy Mikovitz spoke out on the unethical behavior of Dr. Fauci, Director of the NIAID since 1984 and one of the lead members of the White House Coronavirus Task Force (NIAID and CDC are both under the HHS umbrella). Excerpt:

Dr Fauci ordered Mikovits to keep her mouth shut. When she refused, he illegally confiscated her work books and hard drives, drove her from government work + blackballed her from receiving NIH grants ending her science career.

For those of you who are unaware, Mikovits discovered that a mouse virus (XMRV) has contaminated vaccines all the way back to the 30’s. She believes the virus can be linked to diseases like chronic fatigue (CFS/ME), autism, Alzheimer’s, cancer, autoimmune, neuroimmune, central nervous system diseases, and even chronic Lyme disease. While retroviruses do not directly cause diseases by themselves they help to create acquired immune system deficiency (non-HIV AIDS) which in turn causes unrelenting inflammatory processes.  Call it a trigger, in a perfect storm of events within the body allowing disease to occur.

You may ask why you’ve never heard of XMRV before. That’s because the CDC, NIH, FDA, and other government agencies covered it up. They didn’t want to worry you, and they certainly don’t want you to question their lucrative vaccines.

XMRV remains in American vaccines.

There is much evidence showing both COVID-19 and Lyme/MSIDS have been manipulated in a lab.

Ian Lipkin, aka The Virus Hunter, has been involved with both issues due to the urging of Dr. Fauci. He denies XMRV involvement in human disease, despite Mikovitz’s group being able to transmit it from patients’ T-cells to uninfected T-cells in the laboratory. He also denies COVID-19 is a lab-made, manipulated virus.

Despite his denial, the origin of COVID-19, after boomeranging around the globe, has returned to show strong evidence that it is most likely a manipulated virus for biowarfare purposes after all.

Excerpt:

After creating the synthetic virus, which they call SHC014, Zhengli and her coauthors write that they “next synthesized a full-length SHC014-CoV infectious clone based on the approach used for SARS-CoV.”24 Other papers Zhengli co-wrote focus on the transmission of coronaviruses from one species to another, according to the documentary.

Zhengli and her fellow researchers admit they used a “reverse genetics system” to generate “a chimeric virus expressing the spike of bat coronavirus,” raising legitimate fears that COVID-19 is also reverse-engineered, according to “Tracking Down the Origin of the Wuhan Virus.”

And the real clincher:

According to Mikovits, the S proteins seen on COVID-19 that make it so transmittable to humans come from “cutting and pasting of two different viruses” and the apparent insertion of four new genes could not have been generated from a natural “zoonotic transmission.”

They had to come from a medical, bioweapons or lab setting, says Mikovits. Other scientists in the film agree that COVID-19 is a re-engineered, laboratory-driven virus.

But we were warned about this months ago, and then again recently with even more damning details.

Lyme patients are also familiar with bioweaponization. Recently, Congressman Smith announced a DOD investigation on the bioweaponization of ticks. Tick researchers have gone on record admitting to experimenting on ticks and dropping them out of airplanes.  And Kris Newby in her book “Bitten”, describes how a CIA operative dumped boxes full of crawling ticks over Cuba, returned home, and unwittingly infected his own newborn baby.  Dr. William Burgdorfer, the discoverer of the causative agent of Lyme disease worked as a bioweapons researcher for the US military and worked in programs tasked with breeding ticks and infecting them with pathogens that cause human diseases.

Besides faulty testing, a thrust to create a vaccine at all costs, a tightly controlled narrative, and bioweaponization, there is also a similar smear campaign on successful clinical treatments in both Lyme disease and COVID-19.

The CDC Slanders Competing Treatments

Authorities have purposely thwarted IV therapy for Lyme patients in a recent MMWR paper. The short recap is that the CDC cherry-picked 5 cases that had poor outcomes using IV therapy and then wrote a paper scaring the bejesus out of doctors. 

What’s interesting about the MMWR paper is that one of the authors, a CDC epidemiologist, allegedly solicited IDSA doctors for evidence of harm from IV antibiotic treatments, essentially bribing them by offering co-authorship of the report if anecdotes were used. No such solicitation was made for IV treatment success stories.  The dangling carrot has been blatantly observed with COVID treatment. There has been hot debate on Lyme treatments for decades. The MMWR paper is only one example of bias which is embedded within the CDC. There are many success stories using IV therapy by a Wisconsin Doctor and IDSA founder who disagreed with his colleagues on how to treat Lyme disease.

Meanwhile, doctors are reporting in on the success of treatments for COVID-19, but the CDC, true to form, bad-mouths any treatment or tests, other than ones they orchestrate. Based upon the CDC’s casting a dark shadow upon treatments that even patients attribute to saving their lives, numerous states (MI, NV, NY) as well as France have banned their usage for COVID-19.  It’s gotten so bad that judges are ordering hospitals to administer life-saving COVID treatment to dying patients because medical doctors kowtow to corrupt health ‘authorities’.

This tactic of politicizing clinically successful treatments is what the CDC/IDSA/NIH does. This article clearly shows the bantering common in mainstream media regarding COVID-19 treatment. The bi-partisan squabbling is tangible, and similar hit-pieces have been written about Lyme treatment for years. Lyme patients have had to straddle this polarized fence for over 40 years and this polarization continues unabated.

I was told by a front-line European doctor treating severely ill COVID-19 patients that hydroxychloroquine, commonly known as plaquenil, was used for over 70 years over the counter and was frequently given to travelers. Then, all of a sudden it became a prescription drug overnight, and now it’s being banned for use for COVID-19. This means doctors using it for COVID-19 will have their licenses revoked.

Scaring doctors and revoking their licenses is a common refrain for doctors treating Lyme disease.  My own doctor had to pay over $50,000 in legal fees fighting this battle and it’s happening not only in the U.S. but around the world due to the Iron Curtain of the CDC.

There is no question that IV therapies as well as extended antibiotics for Lyme and hydroxychlorquine for COVID-19 have side effects. No one is denying this. What’s unconscionable is that ‘authorities’ zoom in on particular treatments and microscopically nit-pick due to ulterior motives. It becomes crystal clear that the motivation is to control the narrative, and protect special interests – not to safe-guard patients.

Everyone wants double blind, placebo, randomized controlled trials (RCT); however, in the case of Lyme disease, those studies are controlled by a cabal who continue to study only the acute phase of the disease with faulty parameters for entrance into their studies. Again, testing is rigged for a predetermined outcome and they exclude a large subset of patients who don’t meet their stringent criteria.  Due to the complexity of Lyme/MSIDS, RTCs will never be done.

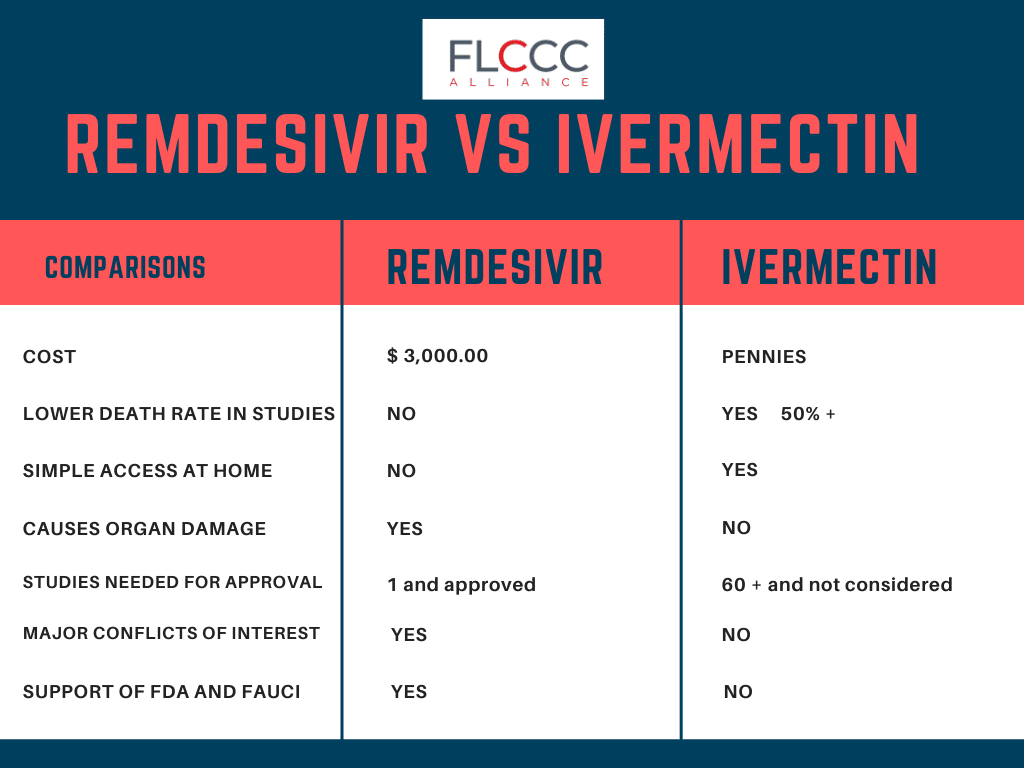
In the case of COVID-19, severe patients can quickly die, making those studies of little use in the present. Treatments are needed now, not in six months. Doctors and pharmacists go to school to learn about drugs and their interactions. How about authorities just let doctors do their jobs? I don’t see these authorities condemning cancer treatments which kill as many good cells as bad cells and cause horrific side-effects.  Why the focus on HCQ, ivermectin, and benign treatments like vitamin D, C, zinc, and quercetin?   This recent article explains why.  In essence, the CDC is in bed with Gilead Science as nine of the experts on the NIH COVID-19 Panel recommending treatment options have disclosed financial support from Gilead.  More dangling carrots.

Gilead Science created the anti-viral remdesivir which was unsuccessful for Ebola.  They are now digging it out of the drug graveyard and pushing it for COVID-19 to make up for lost profits. They did this exact same thing with AZT, a chemotherapy drug which failed for leukemia, and repurposed it for HIV patients who didn’t even have symptoms! HCQ, even though it’s clinically showing great success, stands in the way of their chosen profitable, albeit dangerous treatment. Remdesivir is not without side-effects and only showed modest benefits against COVID-19 but this is the CDC’s “golden” treatment, therefore, everything said about it is positive while they bad-mouth HCQ a direct competitor.

It’s also important to understand that the NIH owns half of the Moderna COVID vaccine. Many other conflicts of interest exist regarding this unique injection technology.

Where the handling of the two diseases drastically departs; however, is in how seriously the CDC is handling COVID-19 by enacting what most declare to be draconian measures, while continuing to downplay Lyme disease.  The learning curve for COVID-19 has been lightening fast in comparison to Lyme disease in that the conflicts of interest, the reliance upon faulty testing, and the polarization in the medical community on pretty much every aspect of the disease hasn’t budged in over 40 years.

What’s happening in the world today regarding COVID-19 is probably easier for Lyme patients to understand than the average person, but that doesn’t give them solace for the future. They will continue to wash their hands, do an entire laundry list of things to strengthen their immune systems, and will continue to be isolated. While the rest of the world returns to “normal” at some point, Lyme patients will continue living in a paradigm where the majority of doctors don’t even believe, test, or treat them, because the CDC has filled their heads with 40 year old unscientific, fraudulent dogma.

‘Closing Borders is Ridiculous’: Epidemiologist Behind Sweden’s Controversy Coronavirus Strategy

https://www.nature.com/articles/d41586-020-01098-x

‘Closing borders is ridiculous’: the epidemiologist behind Sweden’s controversial coronavirus strategy

Anders Tegnell talks to Nature about the nation’s ‘trust-based’ approach to tackling the pandemic.
Anders Tegnell attends a press conference in Solna, Sweden

Epidemiologist Anders Tegnell (centre). Credit: Jonathan Nackstrand/AFP/Getty

As much of Europe imposed severe restrictions on public life last month to stem the spread of the coronavirus, one country stood out.

Sweden didn’t go into lockdown or impose strict social-distancing policies. Instead, it rolled out voluntary, ‘trust-based’ measures: it advised older people to avoid social contact and recommended that people work from home, wash their hands regularly and avoid non-essential travel. But borders and schools for under-16s remain open — as do many businesses, including restaurants and bars. (See link for article)

_______________

**Comment**

Key Quote: 

“Our voluntary strategy has had a real effect.”

For more:  https://madisonarealymesupportgroup.com/2020/04/19/swedish-epidemiologist-lockdowns-are-not-evidence-based/

https://madisonarealymesupportgroup.com/2020/04/16/israeli-study-reveals-covid19-lockdown-was-pointless/

https://madisonarealymesupportgroup.com/2020/04/09/epidemiologist-coronavirus-could-be-exterminated-if-lockdowns-lifted/

https://madisonarealymesupportgroup.com/2020/03/31/doctors-challenging-coronavirus-crisis/

Coronavirus: Science, Policy, Politics, & 5G

CORONAVIRUS: SCIENCE, POLICY AND POLITICS

By Arthur Firstenberg

Many people are afraid of even asking whether 5G is playing a role in the COVID-19 disease that has shut down much of the world. It is similar to the fear that has prevented people from questioning the orders to stay home, wear masks, and keep six feet away from each other.

I am about truth, wherever I find it, wherever it may lead, because our world is at stake, and life itself — physical, mental, emotional and spiritual — is being dismantled. Conspiracies have no place in this effort. Neither does fear.

My opinions, based on my reading of the scientific and medical literature, as best as I can determine, are these:

  • Did 5G cause the coronavirus? No.
  • Does 5G cause disease similar to the coronavirus? Yes.
  • Did COVID-19 originate in bats? No.
  • Is COVID-19 a recombinant RNA virus, created in a laboratory, intentionally or unintentionally, as part of a research program whose purpose was to protect the population? Did it escape accidentally from a virology laboratory in Wuhan, China? Probably.

The measures that have been put in place, and accepted without question, are ineffective, destructive, and anti-life.

Masks do not protect the wearer. Medical masks are ineffective against viruses, and cloth masks provide breeding grounds for them. A 2015 study in the British Medical Journal found that:

  • Healthcare workers caught viruses from their patients 13 times more often if they wore a cloth mask than if they wore a medical mask.
  • a Chinese study found that a medical mask was no more protective against viruses than wearing no mask at all.
  • The World Health Organization warns that wearing a medical mask “may create a false sense of security” against COVID-19 and that “no evidence is available on its usefulness to protect non-sick persons.”
  • The N95 respirator, recommended for medical workers, requires training to use properly and “without training, the masks could not only expose workers to the virus but also lull them into thinking they are protected,” according to doctors at the Harvard School of Public Health. In practice, even the N95 mask has been found to be ineffective in preventing the transmission of viruses. A review of six clinical studies, published in the Canadian Medical Association Journal, found that medical workers caught viruses from their patients just as often when they used N95 respirators as when they used ordinary medical masks.

Masks are harmful to the wearer. COVID-19 kills by causing severe hypoxia (low levels of oxygen in the blood). People wearing masks rebreathe some of their exhaled air, lowering the amount of oxygen they are breathing.

“Wearing respirators come[s] with a host of physiological and psychological burdens. These can interfere with task performances and reduce work efficiency. These burdens can even be severe enough to cause life-threatening conditions if not ameliorated,” wrote the author of a 2016 article in the Journal of Biological Engineering. When the N95 respirator was tested in use in 2010, the “dead-space oxygen and carbon dioxide levels did not meet the Occupational Safety and Health Administration’s ambient workplace standards.”

Ventilators do not work and are harmful. Dr. Cameron Kyle-Sidell quit his job in the Intensive Care Unit at Maimonides Medical Center in Brooklyn because he was required to put his COVID-19 patients on ventilators that he felt were killing them because the air pressure was damaging their lungs. His coronavirus patients all had severe hypoxia but healthy respiratory muscles: they needed oxygen, he said, but not pressure.

“COVID-19 lung disease, as far as I can see, is not a pneumonia,” he said, but seems to be “some kind of viral-induced disease most resembling high altitude sickness… These patients are slowly being starved of oxygen … and while they look like patients absolutely on the brink of death, they do not look like patients dying of pneumonia.” Italian doctors agree: “Patients on ventilators deteriorate anyway, in an unexplained way… Most of these patients are plainly hypoxic.”

PCR tests are not accurate.

A March 25, 2020 paper by Carver and Jones reported that it is not possible to assess the accuracy of PCR tests because:

“There are little public data on the false positive and false negative rates of the various RT-PCR based tests.”

A false positive test means that you are diagnosed with COVID-19 when you don’t actually have it. One of the only studies to date that has attempted to estimate the frequency of false positives is Zhuang et al., “Potential false-positive rate among the ‘asymptomatic infected individuals’ in close contacts of COVID-19 patients”, Chinese Journal of Epidemiology, 2020, 41(4): 485-488 (in Chinese).

They concluded that up to 80 percent of non-symptomatic people who test positive for the coronavirus may not actually have it.

Shutdowns do not have any effect.

  • Japan, which did not shut down until April 6 and then only with voluntary measures, has 2 COVID-19 deaths per million population.
  • China, which shut down in December, has 3 deaths per million population.
  • Belarus, which never shut down, has 4 per million.
  • South Korea, which has only voluntary measures, has 5 per million.
  • Iran, which shut down in early March, has 62 per million.
  • Sweden, which did not shut down, has 156 per million.
  • Switzerland, which did shut down, has 165 per million.
  • Belgium, which did shut down, has 503 deaths per million population.
  • Vietnam, Laos and Cambodia, all close to China, have no COVID-19 deaths at all. Vietnam shut down in early February, Laos shut down in late March, and Cambodia has never shut down at all.
  • In the U.S., South Dakota, which has not shut down at all, has four times as many cases, but fewer deaths, than neighboring Montana, which is completely locked down.

Death rates in the United States have been going down, not up, since the beginning of the year. If you pay attention to the news, you might assume that record numbers of people are dying. The opposite is true. Not only has overall mortality for the United States been going steadily downward since January, but mortality has been substantially lower this year than last year. These are weekly mortality statistics for the United States from the Centers for Disease Control:

Week                   Number of Deaths 2019           Number of Deaths 2020

1                                  58,291                                           59,087

2                                  58,351                                           59,151

3                                  58,194                                           57,616

4                                  57,837                                           57,000

5                                  58,128                                           56,426

6                                  58,492                                           56,962

7                                  57,917                                           55,981

8                                  57,858                                           55,494

9                                  57,920                                           54,834

10                                  58,490                                           54,157

11                                  57,872                                           52,198

12                                  57,087                                           51,602

13                                  56,672                                           52,285

14                                  56,595                                           49,292

15                                  55,477                                           47,574

TOTAL                         865,181                                         819,659

We are told that 37,308 people have died this year from COVID-19 through April 18, yet actually 45,522 fewer people have died this year than last year during the same period of time.

RF radiation and COVID-19 cause similar disease. In my last newsletter (“Is the Sky Really Falling?”), I noted some effects of COVID-19 that are similar to effects of radio waves. The list of effects in common has grown, and includes:

  • headaches
  • dizziness
  • nausea
  • digestive problems
  • muscle pain
  • tachycardia
  • hypotension
  • cardiac arrhythmias
  • strokes
  • seizures

As many as two-thirds of people who test positive for COVID-19 have lost their sense of smell, often without any other symptoms. Patients are presenting with mental confusion, without any respiratory symptoms at all. Patients are presenting with diarrhea, vomiting, and abdominal pain. When patients with any of these symptoms test positive for the coronavirus, their illnesses are being attributed to that virus. But these are all classic symptoms of radio wave sickness.

When both the virus and RF radiation are present, the disease should be attributed to both.

And RF radiation and COVID-19 both cause hypoxia. COVID-19 impairs oxygen absorption by the blood, and RF radiation impairs oxygen use by the cells. COVID-19 would not be so severe were it not for the radiation.

Recently, there is a new symptom that is being attributed to the virus that is exactly what one would expect to see from millimeter waves: a “fizzing” sensation throughout the body. It is being described as a “buzzing sensation,” “a burning feeling,” and “an electric sensation in the skin.” It is probably wrongly being attributed to the virus, and is due instead to 5G.

It is a fact that 5G was turned on in Wuhan, China on November 1, 2019, and that the first known COVID-19 patient became ill there on November 17.  It is a fact that there is a research virology lab in Wuhan, and that researchers there coauthored a paper in 2015 with American researchers from Chapel Hill, North Carolina describing a hybrid coronavirus that they had created by attaching a spike protein from bats to a SARS coronavirus. Zheng-Li Shi, the lead researcher from Wuhan, said in an interview in Scientific American that she had worried that COVID-19 was a virus that had escaped from her lab, but she reassured the world that she had checked and it did not resemble any of the viruses that she had collected in bat caves. Yet in the next sentence she justified her claim that COVID-19 came from bats by saying that it was almost identical to a virus that she had collected in a bat cave in Yunnan.

The SARS virus has escaped from high-level containment facilities in China multiple times. As revealed by the Washington Post on April 14, 2020, U.S. Embassy officials had warned in 2018 that sloppy safety protocols for handling contagious viruses in the Wuhan lab “represented a risk of a new SARS-like pandemic.”

It is also a fact that the animal market in Wuhan does not sell bats. A YouTube video that has been shared on social media that shows bats being sold for meat at a market was actually filmed in Langowan, Indonesia, and not in China at all.

In short, 5G is part of the coronavirus equation, and everything that we have been doing to address the pandemic has more to do with politics and fear than with reality. It is time to re-open society, to take off our masks, and to open our eyes to what is really happening to our world.

Arthur Firstenberg


P.O. Box 6216
Santa Fe, NM 87502
USA
phone: +1 505-471-0129
info@cellphonetaskforce.org
https://www.5gSpaceAppeal.org

A pdf version of this newsletter is available here:

https://www.cellphonetaskforce.org/wp-content/uploads/2020/04/Choosing-Life.pdf

For Firstenberg’s Curriculum Vitae:  https://madisonarealymesupportgroup.com/wp-content/uploads/2020/04/96e76-curriculumvitaeofarthurfirstenberg.pdf

To sign the international petition to halt 5G:  https://www.5gspaceappeal.org/sign-individual

For more on 5G:  

For an interesting read on the connection between COVID-19, COVID injections, 5G, and Chemtrails.  

A few important excerpts:

…globalist entities that are behind the military deployment of 5G worldwide needed a cover for the inevitable outbreaks of both 5G Flu and 5G Syndrome.  The coronavirus pandemic has provided just that, especially in light of the fact that many of the symptoms of both are quite similar. See: Is The “Coronavirus” Actually Microwave Illness from 4G and 5G Radiation?

There have been many telltale signs that are dead giveaways about the close coordination between the military deployment of 5G just before the first major COVID-19 outbreaks around the world.  For example, Wuhan was established as China’s first 5G “Demonstration Zone” in 2019. See: Wuhan City Was expected to have 10,000 5G base stations operating by the end of 2019

Another major clue concerns the highly suspicious work being conducted at Harvard University.  The activation of 5G energy grids amps up the manifestation and severity of Covid symptoms considerably which is why Harvard’s Charles M. Lieber holds the U.S. Patent for using 5G radiation to vibrate corona virus particles from preset nanotubule containers.  The Chair of the Chemistry Department was arrested and indicted in June of 2020.

….Just how many assaults can the human body take before it starts to break down, particularly for the elderly and those with serious comorbidities. See: CHEMTRAIL SYNDROME: A Global Pandemic Of Epic Proportions

The article also points out that the aerosolized and chemically mobile aluminum oxide is “particularly toxic to the brain when permitted to pass through the blood-brain barrier.” This was accomplished through the invasive nasal COVID-19 testing which punctured the brain lining, causing some to need surgery.