All three Halcombs survived COVID, including a 95 year old. How? Watch the short video and learn about the life-saving medications that our corrupt public ‘health’ authorities and complicit media are censoring, maligning and denying.
There is complete polarization within the medical community reminiscent of Lyme/MSIDS regarding the treatment of COVID. On one hand you have mainstream doctors toeing the accepted narrative either out of ignorance, or out of fear of losing their jobs. On the other hand you have freedom-loving doctors who are putting their necks on the chopping block as they defy the establishment and advocate for the proper treatment of patients. The story is one Lyme/MSIDS patients know all too well.
Lyme/MSIDS patients quickly learn of the Lyme-underground where one must go in order to get appropriate help. Now, a wider public circle is learning what we’ve contended with for over 40 years: having to go to search out “special” doctors to receive “appropriate” treatment. Hospitals have become modern day “killing fields,” with frustrated doctors splitting off forming groups separate from mainstream medicine. These brave doctors are being attacked and threatened. Politicians and judges are now being asked to speak up for sick patients who seemingly have no recourse.
To say we are in a mess would be an understatement. The vitriol is tangible and the public is confused and being led astray – even blaming people for not succumbing to an unproven, experimentalgene therapyinjection utilizing a dangerous spike protein toxin which is related to thousands upon thousands of deaths, severe adverse reactions, and pathogenic priming or ADE, all of which are completely ignored by mainstream medicine and a complicit media. One expert warns these dangerous injections may kill up to 50 million Americans. Whistleblowers are coming out of the woodwork with crucial information:
CDC whistleblower lawsuit states nearly 50,000 people were killed within 14 days of a 1st or 2nd dose of a COVID-19 “vaccine”. Deaths are severely under counted as the corrupt CDC is counting deaths within 14 days of vaccination, as unvaccinated deaths. These statistical shennanigans have been used throughout the “plandemic” to push an accepted narrative while hiding reality. The CDC did a similar thing with the PCR test.
Pfizer whistleblower states the injections are bioweapons.
GSK whistleblower states the injections cause sterility.
Vaccine researcher admits the spike protein is a toxin that accumulates in the ovaries, testes, liver, spleen, bone marrow, and adrenal glands. It also crosses the blood brain barrier.
Vaccine expert states COVID injections drive viral mutations which will cause outbreaks.
Doctor testing “vaxxed” blood found COVID shots cause severe autoimmunity.
Pfizer scientist admits natural immunity is better than COVID shots.
Big Tech, Big Pharma,socialmedia, and a complicit media continue to censor reality and the fact the injections are causing severe adverse events including death and that there is no need for these dangerous injections due to safe, effective, cheap COVID treatments that have been proven to work. There were more than 500 deaths in the first year of remdesivir usage – the drug of choice by our corrupt health ‘authorities,’ vs 20 deaths in 19 years of ivermectin usage – the drug of choice from censored, maligned doctors. Remdesivir isn’t effective for COVID, but is manufactured by Gilead Science, a CA manufacturing company which has ties to the Pentagon and has been accused of engaging in illegal bioweapon research programs in the country of Georgia. More than 100,000 pages of classified information shows that Gilead was involved in conducting military research, biological weapons research, and other clinical experiments there that resulted in the deaths of Georgian citizens.
An antimalarial treatment made from the plant Artemisia annua (Sweet Wormwood) shows promise as a COVID-19 treatment
The drug artesunate — which contains two compounds found in Artemisia annua: artemisinin and dihydroartemisinin — is a first-line treatment for malaria
In a recent in vitro study, both pretreatment and treatment with artemisinin extracts, synthetic artemisinin and the drug artesunate were able to inhibit SARS-CoV-2 infection. However, artesunate was the most potent in terms of treatment, and from a clinical perspective may be the only one worth pursuing
Artesunate’s mechanism of action against SARS-CoV-2 is as yet unknown, but artemisinin does have confirmed antiviral activity
The World Health Organization has come out in opposition to artemisinin-based products, warning their use can bolster drug-resistant strains of malaria parasites. For this reason, people living in malaria-prone areas should be cautious about using this plant remedy
This article was previously published January 4, 2021, and has been updated with new information.
A second antimalarial treatment is now being seriously considered and evaluated for its efficacy against COVID-19. The treatment is made from the plant Artemisia annua, which most people know as Sweet Wormwood. Other names for this plant include Annual Sagewort and Sweet Annie.
Research over the past few decades has revealed multiple health benefits from this medicinal herb, which has a centuries-long history of use in folk medicine. In 2015, Chinese scientist Tu Youyou received a partial Nobel Prize in Physiology or Medicine for his discovery of artemisinin and dihydroartemisinin,1 both of which have potent malaria-fighting properties.
As reported by the University of Kentucky,2 “The popular malaria drug artesunate was developed from those compounds and is still used as a first-line treatment for the disease today.”
Artemisinin — A Viable COVID-19 Remedy?
Interestingly, in addition to having a long-standing history of being used as a highly effective antiparasitic, it also has anticancer properties. Additionally, artemisia annua has antiviral activity that might be helpful against SARS-CoV-2.
In an April 8, 2020, SEC filing, Mateon Therapeutics reported3 that “Artemisinin is highly potent at inhibiting the ability of the COVID-19 causing virus (SARS-CoV-2) to multiply while also having an excellent safety index.”
After testing the plant’s antiviral effects in a laboratory setting for a couple of years, University of Kentucky researchers are also exploring its use for the treatment of COVID-19,4 as are researchers in Denmark and Germany.5 According to the University of Kentucky:6
“Surprisingly, results showed that the plant’s leaves, when extracted with absolute ethanol or distilled water, provided more antiviral activity than the actual drug itself — meaning that an Artemisia annua-blended coffee or tea could possibly be more effective than taking the drug.”
Based on these findings, researchers have decided to test artemisinin in patients diagnosed with COVID-19. Some of the first human studies, set to investigate both the extract blended into coffee and tea, as well as the drug artesunate, were implemented by UK HealthCare.
University of Kentucky researchers have founded a company called ArtemiFlow to develop and manufacture the drug, in collaboration with the Kentucky Tobacco Research & Development Center.7 A sister company, ArtemiLife, is marketing Artemisia tea and coffee to raise research funds.
Mechanism of Action Remains Unknown
As for its mechanism of action, such details still remain to be discovered. C&EN explains:8
“When countering malaria, artemisinin exploits the parasite’s taste for hemoglobin in its host’s blood. As the parasite digests hemoglobin, it frees the iron-porphyrin heme complex from the protein.
Because this heme is toxic to the parasite, the organism normally converts the complex to a more benign crystalline form. ‘But artemisinin corrupts this heme-detoxification pathway,’ says Paul O’Neill, a medicinal chemist at the University of Liverpool.
If artemisinin does have any effect against SARS-CoV-2, though, it likely relies on a completely different mechanism than the one it uses against the malaria parasite, Harvard’s [malaria researcher Dyann F.] Wirth says.”
In Vitro Study Reports Positive Results
An in vitro study9,10 looking at the efficacy of artemisinin-based treatments against SARS-CoV-2, posted on the prepublication server bioRxiv, October 5, 2020, report promising results.
The study was a collaboration between researchers from Germany, Denmark and Hong Kong, led by Kerry Gilmore, Ph.D., from the Max Planck Institute for Colloids and Interfaces in Potsdam, Germany.
Three artemisinin extracts, as well as pure, synthetic artemisinin, artesunate and artemether were evaluated. During the initial screening for antiviral activity, a German SARS-CoV-2 strain obtained from Munich was used.
Later on, during the concentration-response phase of the trial, they used a Danish SARS-CoV-2 strain from Copenhagen. These two strains are said to be “more closely related to the majority of SARS-CoV-2 strains circulating worldwide than the Wuhan strain.”11,12
In summary, they found that both pretreatment and treatment with artemisinin extracts, synthetic artemisinin and the drug artesunate were able to inhibit SARS-CoV-2 infection of Vero E6 cells and human hepatoma Huh7.5 cells. That said, artesunate was the most potent in terms of treatment, and from a clinical perspective may be the only one worth pursuing.13,14
World Health Organization Warns Against Its Use
While the world is eager to add another remedy to its COVID-19 treatment list, the World Health Organization has come out in opposition to artemisinin-based products. In a May 27, 2020, article, C&EN reported:15
“One of the most high-profile advocates for using the herbal remedy against the novel coronavirus is Madagascar president Andry Rajoelina, who has been touting Covid-Organics, a tonic containing A. annua that the Malagasy Institute of Applied Research developed …
But health officials are deeply concerned about the promotion and use of these herbal remedies for three principal reasons. First, no evidence exists that A. annua extracts can prevent or cure COVID-19 …
Second, A. annua preparations such as teas, tonics, or herbal capsules also contain a cocktail of bioactive compounds in addition to artemisinin that can have side effects such as dizziness, hearing problems, and vomiting.
Third, and perhaps most worrying of all, widespread use of A. annua herbal extracts could bolster drug-resistant strains of malaria parasites such as Plasmodium falciparum.16
For people living in regions where malaria is endemic, exposure to subtherapeutic doses of artemisinin in A. annua may be enough to kill off some of the parasites in their bodies, but not all of them. Clearing out weakling parasites leaves more room for drug-resistant siblings to proliferate, rendering vital ACTs [artemisinin-based combination therapies] ineffective.”
According to Pascal Ringwald, who heads up the drug resistance and response unit of the WHO Global Malaria Program, artemisinin resistance is a significant problem in Southeast Asia, where Artemisia readily grows and is commonly used.17
That said, this risk is bound to be slight for Americans and people in many other Western countries where malaria is exceedingly rare. According to C&EN,18 “Scientists interviewed by C&EN agree that although this use is against WHO recommendations, it does not risk accelerating resistance because there are so few cases of malaria in the U.S.”
Two recently published studies confirm quercetin is useful as an adjunct therapy in the early outpatient treatment of mild SARS-CoV-2 infection
In one study, COVID patients who received quercetin in addition to analgesics and an antibiotic cleared the virus faster than those who only received analgesics and antibiotics, and a greater number of patients reported reduced symptoms
In the second study, daily quercetin supplementation for one month reduced the frequency and length of hospitalization, the need for noninvasive oxygen therapy, intensive care and deaths
Quercetin has antiviral, anti-blood clotting, anti-inflammatory and antioxidant properties, all of which are important in the treatment of SARS-CoV-2 infection
Quercetin also inhibits binding of specific spike proteins to your ACE2 receptors, thereby blocking the virus’ ability to infect your cells. It’s also been shown to directly neutralize viral proteins that are critical in the replication of SARS‐CoV‐2
In an August 21, 2021, newsletter,1 Dr. Michael Murray discussed the use of quercetin for respiratory infection symptoms. In November 2020, he’d suffered a “very mild and brief bout of COVID-19.”
He also recounts an anecdotal story of a friend who developed suspicious respiratory symptoms. His friend had been taking a number of supplements said to offer protection, but was still feeling awful.
As it turns out, the one thing he’d not taken was quercetin, and as soon as he did, that same day, his symptoms started to dissipate. This experience, Murray says, “is consistent with the results from two clinical trials” that were recently published.
Quercetin seems to be a safe, far less expensive, and easier-to-obtain and it works by a similar mechanism, driving zinc into the cells to stop viral replication.
Statistical Improvement in Clinical Outcomes
In the first study,2 42 COVID-19 outpatients were divided into two groups. One group of 21 patients received standard medical therapy consisting of analgesics and an antibiotic (acetaminophen 500-milligram (mg) to 1,000-mg dose if body temperature was higher than 37.5 degrees C — 99.5 F — with a maximum daily dosage of 3 grams, and 500 mg azithromycin for three consecutive days).
The other group of 21 patients received standard therapy plus the equivalent of 600 mg of quercetin per day (divided into three doses) for seven days, followed by another seven-day course of 400 mg of quercetin per day (divided into two doses).
The quercetin was used with sunflower lecithin, which has been demonstrated to increase absorption in the gut by as much as 20 times, compared to pure quercetin formulations.
The main outcomes being evaluated were virus clearance and symptoms. After one week of treatment, 16 of the 21 patients in the quercetin group tested negative for SARS-CoV-2 and 12 reported that all symptoms had diminished.
In the standard care group, only two tested negative and four had partially improved symptoms. By the end of Week 2, the five remaining patients in the quercetin group tested negative. In the standard care group, 17 of the 19 remaining patients tested negative and one had died.
“These results are impressive and hopefully additional studies will be conducted on hospitalized patients to see how quercetin might be helpful in more severe cases,” Murray wrote in his newsletter.
Can Quercetin Reduce Hospitalizations and Deaths?
The second study3 — a prospective, randomized, controlled and open-label trial — gave 152 COVID-19 outpatients a daily dose of 1,000 mg of quercetin for 30 days to evaluate its adjuvant effects in the treatment of early symptoms and the prevention of severe infection. According to the authors:
“The results revealed a reduction in frequency and length of hospitalization, in need of non-invasive oxygen therapy, in progression to intensive care units and in number of deaths. The results also confirmed the very high safety profile of quercetin and suggested possible anti-fatigue and pro-appetite properties.
QP (Quercetin Phytosome®) is a safe agent and in combination with standard care, when used in early stage of viral infection, could aid in improving the early symptoms and help in preventing the severity of COVID-19 disease. It is suggested that a double-blind, placebo-controlled study should be urgently carried out to confirm the results of our study.”
Mechanisms of Action
As noted in the first study4 above, quercetin was chosen based on the fact that it has antiviral, anti-blood clotting, anti-inflammatory and antioxidant properties, all of which are important in the treatment of SARS-CoV-2 infection. In the second study, more detailed mechanisms of action are reviewed. According to the authors:5
“SARS-CoV-2 proteases, like 3-chymotrypsin-like protease (3CLpro), papain-like pro-tease (PLpro), RNA-dependent RNA polymerase, spike (S)protein and human angiotensin-converting enzyme 2 (hACE2) are considered possible targets for developing effective anti-COVID-19 drugs.
Recently, molecular docking studies have suggested the possible binding interaction of quercetin with the 3CLpro, PLpro, and S-hACE2 complex. Some recent results, obtained by biophysical techniques, appear to support the results of the molecular docking studies.
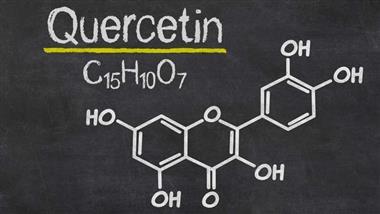
Quercetin, a flavonol not naturally present in the human body, is the most abundant polyphenol in fruits and vegetable and is widely used as a dietary supplement to boost the immune system and promote a healthy lifestyle.
Quercetin is characterized by three crucial properties: antioxidant, anti-inflammatory and immunomodulatory. The combination of these actions allows quercetin to be a potential candidate to support all unhealthy conditions where oxidative stress, inflammation and immunity are involved.”
Initially, quercetin gained attention because it’s a zinc ionophore, meaning it shuttles zinc — which has well-known antiviral effects — into your cells just like the drug hydroxychloroquine.
Some proposed the primary reason hydroxychloroquine and quercetin worked was because of this feature. Of course, you also had to take zinc along with either of them. To effectively act as a zinc ionophore, the quercetin also needs vitamin C.
Since then, other studies, including the two reviewed here, have shown quercetin has other actions that makes it useful against SARS-CoV-2 as well. As reported by Murray in his newsletter:
“In particular, quercetin exerts significant inhibition on the binding of specific spike proteins to ACE-2 receptors, thereby blocking the ability of the virus to infect human cells. Quercetin has also been shown to directly neutralize viral proteins the are critical in the replication of SARS-CoV-2.”
In some studies, quercetin has also been shown to inhibit the release of inflammatory cytokines, which could help alleviate infection-related symptoms and suppress excessive inflammatory responses from occurring. Its antioxidant effects may also help prevent tissue damage caused by scavenging free radicals, thereby aiding in the recovery process of viral infections.6
Quercetin’s Antiviral Properties
Quercetin’s antiviral properties have been attributed to three main mechanisms of action:
Inhibiting the virus’ ability to infect cells
Inhibiting replication of already infected cells
Reducing infected cells’ resistance to treatment with antiviral medication
For example, research7 funded by the U.S. Defense Advanced Research Projects Agency (DARPA), published in 2008, found it lowers your risk of viral illness such as influenza and boosts mental performance following extreme physical stress, which might otherwise undermine your immune function and render you more susceptible to infections.
Here, cyclists who received a daily dose of 1,000 mg of quercetin in combination with vitamin C (which enhances plasma quercetin levels8,9) and niacin (to improve absorption) for five weeks were significantly less likely to contract a viral illness after bicycling three hours a day for three consecutive days, compared to untreated controls. While 45% of the placebo group got sick, only 5% of the treatment group did.
Quercetin Works Against Many Common Viruses
Before the COVID-19 pandemic struck, several studies had highlighted quercetin’s ability to prevent and treat the common cold and seasonal influenza.10,11,12,13,14,15,16,17,18 By attenuating oxidative damage, it also lowers your risk of secondary bacterial infections,19 which is actually the primary cause of influenza-related deaths.
Importantly, quercetin increases mitochondrial biogenesis in skeletal muscle, which suggests part of its antiviral effects are due to enhanced mitochondrial antiviral signaling.20 Quercetin also works against other viruses, as demonstrated in the following studies:
• A 1985 study found quercetin inhibits infectivity and replication of herpes simplex virus type 1, polio-virus type 1, parainfluenza virus type 3 and respiratory syncytial virus (RSV).21
• A 2016 animal study22 found quercetin inhibited mouse dengue virus and hepatitis virus.
• Other studies have confirmed quercetin’s power to inhibit both hepatitis B23 and C24 infection.
• A March 2020 study25 found quercetin provides “comprehensive protection” against Streptococcus pneumoniae infection, both in vitro and in vivo, primarily by neutralizing pneumolysin (PLY),26 one of the toxins released from pneumococci that encourages S. pneumoniae infection to blossom in the first place.
Streptococcus pneumoniae is responsible not only for pneumonia, but can also be involved in some ear and sinus infections, meningitis and certain blood infections.27 As reported by the authors of this study:28
“The results indicated that quercetin significantly reduced PLY-induced hemolytic activity and cytotoxicity via repressing the formation of oligomers.
In addition, treatment with quercetin can reduce PLY-mediated cell injury, improve the survival rate of mice infected with a lethal dose of S. pneumoniae, alleviate the pathological damage of lung tissue and inhibit the release of cytokines (IL-1β and TNF-α) in bronchoalveolar lavage fluid.
Considering the importance of these events in antimicrobial resistant S. pneumoniae pathogenesis, our results indicated that quercetin may be a novel potential drug candidate for the treatment of clinical pneumococcal infections.”
How Quercetin Combats Inflammation and Boosts Immunity
Aside from its antiviral activity, quercetin is also known for boosting immunity and combating inflammation. As noted in a 2016 study29 in the journal Nutrients, mechanisms of action include (but is not limited to) the inhibition of:30
Lipopolysaccharide (LPS)-induced tumor necrosis factor α (TNF-α) production in macrophages. TNF-α is a cytokine involved in systemic inflammation, secreted by activated macrophages, a type of immune cell that digests foreign substances, microbes and other harmful or damaged components
LPS-induced mRNA levels of TNF-α and interleukin (IL)-1α in glial cells, which results in “diminished apoptotic neuronal cell death”
The production of inflammation-producing enzymes
Calcium influx into the cell, which in turn inhibits pro-inflammatory cytokine release, as well as histamine and serotonin release from intestinal mast cells31
According to this paper, quercetin also stabilizes mast cells, has cytoprotective activity in the gastrointestinal tract, and “a direct regulatory effect on basic functional properties of immune cells,” which allows it to inhibit “a huge panoply of molecular targets in the micromolar concentration range, either by down-regulating or suppressing many inflammatory pathways and functions.”32
Bioavailability
While quercetin does have potent antiviral effects, in order for it to work effectively you need sufficiently high dosages to raise the level of quercetin in your body’s tissues.
The relatively low absorption rate of quercetin is why a sunflower lecithin formulation was used.
Research33 published in the July-December 2021 issue of the Journal of Natural Health Products Research, found a quercertin matrix has the same total absorption rate as quercetin phytosome — and higher peak blood levels.
“Since both of these forms of quercetin produce similar blood levels, they should produce the same effects at equal dosages based upon quercetin content,” Murray wrote in his newsletter, adding:
“My dosage recommendation as part of a nutritional supplement program to support immune function is 250 mg twice daily.
And in patients with active Infection, my recommendation is … six capsules twice a day providing a total of 3,000 mg of quercetin. This high dosage should be taken for at least 10 days and then reduced to a maintenance dosage of 250 mg twice daily …
[This] high dosage may not be necessary. But my dosage calculations are based upon likely tissue concentrations needed to exert the strongest antiviral effects. And given the safety of quercetin, there is no harm at this level.”
Protocol Using Quercetin
One doctor who early brought quercetin into the limelight was Dr. Vladimir Zelenko. As hydroxychloroquine became difficult to obtain, Zelenko switched to recommending quercetin instead, as it’s readily available as an over-the-counter supplement. For a downloadable “cheat sheet” of Zelenko’s protocol for COVID-19, visit VladimirZelenkoMD.com.
Other Health Benefits of Quercetin
There are also other lesser known benefits and uses for quercetin, including the prevention and/or treatment of:34
High blood pressure35,36
Cardiovascular disease37
Obesity38 and metabolic syndrome39 (a cluster of conditions including high blood pressure, high blood sugar, high triglyceride levels and fat accumulation around the waist that raise your risk for Type 2 diabetes, heart disease and stroke)
Certain kinds of cancer, in particular leukemia, and to a lesser degree breast cancer40
Nonalcoholic fatty liver disease (NAFLD)41
Gout42
Arthritis43
Mood disorders44
Aluminum-induced neurodegenerative changes, such as those seen in Alzheimer’s, Parkinson’s and amyotrophic lateral sclerosis (ALS).45
Longevity, thanks to its senolytic benefits (clearing out damaged and worn-out cells)46,47
Research has also highlighted quercetin’s epigenetic influence and ability to:48
Interact with cell-signaling pathways
Modulate gene expression
Influence the activity of transcription factors
Modulate microRNAs
MicroRNAs used to be considered “junk” DNA. But far from being useless, research has revealed so-called “junk” DNA is actually microRNA and plays a crucial role in regulating genes that make the proteins that build your body.
The microRNA function as “on/off” switches for the genes. Depending on the microRNA input, a single gene can code for any of more than 200 protein products. Quercetin’s ability to module microRNA may also help explain its cytotoxic effects, and why it appears to improve cancer survival (at least in mice).
Burrascano webinar on borreliosis testing (Lyme and TBRF)
The name “borreliosis” can refer to two distinct but similar infections: Lyme disease and tick-borne relapsing fever (TBRF).
Both diseases result from different subspecies of Borrelia. They exhibit many of the same symptoms and both are spreading geographically.
According to world-renowned Lyme disease specialist Dr. Joseph Burrascano, these diseases present significant challenges to patients and healthcare practitioners alike.
Dr. Burrascano recently presented a webinar with IGeneX, Inc., about testing for both infections. Dr. Jyotsna Shah, president and laboratory director of IGeneX, joined him in the question and answer period.
Read the latest documents from Lyme lawsuit against IDSA
From journalist Mary Beth Pfeiffer on Facebook:
“I have posted the latest documents in the Torrey v. IDSA case on my website. As many know, the lawsuit was dismissed in federal court in Texas. More than 400 documents were filed in the case since 2017; I’ve posted the key filings.
“The dismissal will be appealed, I’m told. One good outcome is this: Eight insurance companies chose to settle the case. This development might help others to convince insurance companies that claims for care should be paid.
“This isn’t enough. But it says something about a medical system that fails to recognize the pain of many Lyme disease patients and their inability to get good care.”
Court filings
Here is background on the case from the latest court document. [Comments in brackets have been added for clarity.]
Plaintiffs sued Defendant in November 2017. Docket No. 1. Since filing their Original Complaint, Plaintiffs have maintained the allegation that Defendant [the Infectious Diseases Society of America], the Doctors [the authors of the IDSA Lyme guidelines] and the Insurance Defendants [eight insurance companies named in the original suit] have engaged in a decades-long conspiracy to deny the existence and prevent treatment of chronic Lyme disease.
Plaintiffs alleged that doctors have known for a long time that while many patients who contract Lyme disease may be cured with short-term antibiotics, up to 40 percent of patients do not respond to short-term antibiotic treatment.
These patients require long-term antibiotic treatment until the symptoms are resolved. Though the Insurance Defendants initially provided coverage for long-term antibiotic treatment of Lyme disease, the health insurance industry made a concerted effort in the 1990’s to deny coverage because long-term treatment was too expensive.
The Insurance Defendants enlisted the help of doctors who were researching Lyme disease—the IDSA panelists—and paid them large fees to develop arbitrary guidelines for testing Lyme disease.
Once these guidelines were established, the Insurance Defendants denied coverage for patients who did not meet the new stringent Lyme disease testing protocols and prevented Plaintiffs from obtaining the antibiotics needed to treat their Lyme disease.
Oklahoma Physicians Are Not Prohibited From Prescribing Off-Label Medicines to Fight COVID-19
Dr. John Campbell explains the importance of “individualized care” in medicine and the fact doctors have always been able to utilize medicine for “off label” purposes based upon exercising sound judgement. All of this changed with COVID with the censoring/banning of things like ivermectin and HCQ, which are FDA approved drugs and have a long history of safety. The attorney’s general office does not give a specific treatment for COVID, only that doctors who prescribe medications and are following the law should not fear disciplinary actions for doing what they feel is best.
This legal action needs to happen in each and every state in the U.S.
Groundbreaking: Nebraska AG Says Doctors Can Legally Prescribe Ivermectin, HCQ for COVID, Calls Out FDA, CDC, Fauci, Media for ‘Fueling Confusion and Misinformation’
At the request of the Nebraska Department of Health, on Oct. 15, Nebraska Attorney General Doug Peterson issued a legal opinion that Nebraska healthcare providers can legally prescribe ivermectin and hydroxychloroquine for the treatment of COVID, so long as they obtain informed consent from the patient.
Few subjects have been more controversial than ivermectin and hydroxychloroquine — two long-established, inexpensive medications widely and successfully used in many parts of the world for the prevention and treatment of COVID.
By contrast, the use of both medications against COVID has been largely suppressed in the U.S, where doctors have been threatened and punished for prescribing them.
On Oct. 15, Nebraska Attorney General (AG) Doug Peterson issued a legal opinion that Nebraska healthcare providers can legally prescribe off-label medications like ivermectin and hydroxychloroquine for the treatment of COVID, so long as they obtain informed consent from the patient.
However, if they did neglect to obtain consent, deceive, prescribe excessively high doses or other misconduct, they could be subject to discipline, Peterson wrote.
The AG’s office emphasized it was not recommending any specific treatment for COVID. “That is not our role,” Peterson wrote. “Rather, we address only the off-label early treatment options discussed in this opinion and conclude that the available evidence suggests they might work for some people.”
Peterson said allowing physicians to consider early treatments will free them to evaluate additional tools that could save lives, keep patients out of the hospital and provide relief for our already strained healthcare system.
The opinion, based on an assessment of relevant scientific literature, was rendered in response to a request by Dannette Smith, CEO of the Nebraska Department of Health and Human Services.
Smith asked the AG’s office to look into whether doctors could face discipline or legal action under Nebraska’s Uniform Credential Act (UCA) — meant to protect public health, safety and welfare — if they prescribed ivermectin or hydroxychloroquine.
“After receiving your question and conducting our investigation, we have found significant controversy and suspect information about potential COVID-19 treatments,” Peterson wrote.
For example, a paper published in the Lancet — one of the most prestigious medical journals in the world — denounced hydroxychloroquine as dangerous, yet the statistics were flawed and the authors refused to provide analyzed data.
The paper was retracted, but not before countries stopped using the drug and trials were cancelled or interrupted.
“The Lancet’s own editor-in-chief admitted that the paper was a ‘fabrication,’ a ‘monumental fraud’ and a ‘shocking example of research misconduct’ in the middle of a global health emergency,” Peterson wrote in the opinion.
A recently published paper on COVID recognized that “for reasons that are yet to be clarified,” early treatment has not been emphasized despite numerous U.S. healthcare providers advocating for early treatment and “scores of treating and academic physicians” — who have published papers in well respected journals — urging early interventions.
Peterson cited numerous studies showing ivermectin and hydroxychloroquine reduced mortality by up to 75% or more when used as a preventative or prophylaxis for COVID, suggesting hundreds of thousands of lives could have been saved had the drugs been widely used in America.
“Every citizen — Democrat or Republican — should be grateful for Doug Peterson’s thoughtful and courageous counteroffensive against the efforts of Big Pharma, its captive federal regulators, and its media and social media allies to silence doctors and deny Americans life-saving treatments,” Robert F. Kennedy Jr., chairman of Children’s Health Defense, told The Defender via email.
“We finally have a leader who puts constitutional rights, peer-reviewed science and human health above industry profits. Doug Peterson is uncowed and unbowed — a genuine hero on horseback for all Americans.” Kennedy said.
Children’s Health Defense President Mary Holland agreed. “This Nebraska AG opinion lets doctors get back to being doctors — without being second-guessed by government, pharmacists and others interfering in the crucial doctor-patient relationship,” Holland said.
Although the AG’s office did not rule out the possibility that other off-label drugs might show promise — either now or in the future — as a prophylaxis or treatment against COVID, it confined its opinion to ivermectin and hydroxychloroquine for the sake of brevity.
Nebraska AG highlights science on ivermectin
In his legal opinion, Peterson concluded evidence showed ivermectin demonstrated striking effectiveness in preventing and treating COVID, and any side effects were primarily minor and transient. “Thus, the UCA does not preclude physicians from considering ivermectin for the prevention or treatment of COVID,” Peterson wrote.
In the decade leading up to the COVID pandemic, Peterson found numerous studies showing ivermectin’s antiviral activity against several RNA viruses by blocking the nuclear trafficking of viral proteins, adding to 50 years of research confirming ivermectin’s antiviral effects.
In addition, safety data for ivermectin showed side effects were “vanishingly small.” The latest statistics available through VigiAccess reported only 5,674 adverse drug reactions to ivermectin between 1992 and October 13, 2021, an “incredibly low” number given that 3.7 billion doses have been administered since the 1980s, Peterson wrote.
Peterson also found that epidemiological evidence for ivermectin’s effectiveness, derived by analyzing COVID-related data from various states, countries or regions is instructive in the context of a global pandemic.
In one instance, a group of scholars analyzed data comparing COVID rates of countries that routinely administer ivermectin as a prophylaxis and countries that did not. The research showed “countries with routine mass drug administration of prophylactic … ivermectin have a significantly lower incidence of COVID-19.”
“This ‘highly significant’ correlation manifests itself not only ‘in a worldwide context’ but also when comparing African countries that regularly administer prophylactic ‘ivermectin against parasitic infections’ and African countries that do not,” Peterson wrote. “Based on these results, the researchers surmised that these results may be connected to ivermectin’s ability to inhibit SARS-CoV-2 replication, which likely leads to lower infection rates.”
Nebraska AG calls out FDA, Fauci on hypocrisy on ivermectin
Many U.S. health agencies have now addressed the use of ivermectin for COVID. The National Institutes of Health (NIH) has adopted a neutral position, choosing not to recommend for or against the use of ivermectin — a change from its position in January 2021 where it discouraged use of the drug for treatment of COVID.
Peterson wrote:
“The reason for the change is the NIH recognized several randomized trials and retrospective cohort studies of ivermectin use in patients with COVID-19 have been published in peer-reviewed journals. And some of those studies reported positive outcomes, including shorter time to resolution of disease manifestations that were attributed to COVID-19, greater reduction in inflammatory marker levels, shorter time to viral clearance, [and] lower mortality rates in patients who received ivermectin than in patients who received comparator drugs or placebo.”
Yet, on Aug. 29, Dr. Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases within the NIH, went on CNN and announced “there is no clinical evidence” that ivermectin works for the prevention or treatment of COVID. Fauci went on to reiterate that “there is no evidence whatsoever” that it works.
“This definitive claim directly contradicts the NIH’s recognition that ‘several randomized trials … published in peer-reviewed journals’ have reported data indicating that ivermectin is effective as a COVI D-19 treatment,” Peterson wrote.
In March 2021, the FDA posted a webpage, “Why You Should Not Use lvermectin to Treat or Prevent COVID-19.”
“Although the FDA’s concern was stories of some people using the animal form of ivermectin or excessive doses of the human form, the title broadly condemned any use of ivermectin in connection with COVID-19,” Peterson wrote. “Yet, there was no basis for its sweeping condemnation.”
Peterson wrote:
“Indeed, the FDA itself acknowledged on that very webpage (and continued to do so until the page changed on September 3, 2021) that the agency had not even ‘reviewed data to support use of ivermectin in COVID-19 patients to treat or to prevent COVID-19.’ But without reviewing the available data, which had long since been available and accumulating, it is unclear what basis the FDA had for denouncing ivermectin as a treatment or prophylaxis for COVID-19.
“On that same webpage, the FDA also declared that ‘[i]vermectin is not an anti-viral (a drug for treating viruses).’ It did so while another one of its webpages simultaneously cited a study in Antiviral Research that identified ivermectin as a medicine ‘previously shown to have broad-spectrum anti-viral activity.’”
“It is telling that the FDA deleted the line about ivermectin not being ‘anti-viral’ when it amended the first webpage on September 3, 2021,” Peterson noted.
Peterson said the FDA’s most controversial statement on ivermectin was made on Aug. 21, when it posted a link on Twitter to its “Why You Should Not Use lvermectin” webpage with this statement: “You are not a horse. You are not a cow. Seriously, y’all. Stop it.”
“This message is troubling not only because it makes light of a serious matter but also because it inaccurately implies that ivermectin is only for horses or cows,” Peterson wrote.
Peterson said the FDA has assailed ivermectin’s safety while ignoring the fact that physicians routinely prescribe medications for off-label use and that ivermectin is a “particularly well-tolerated medicine with an established safety record.”
Peterson added the FDA is ignoring several randomized controlled trials and at least one metaanalysis suggesting ivermectin is effective against COVID. He pointed out the Centers of Disease Control and Prevention has adopted a similar stance — unsupported by scientific evidence — and the media has fueled confusion and misinformation on the drug.
Peterson questions professional associations’ stance on ivermectin
Professional associations in the U.S. and internationally have adopted conflicting positions on ivermectin and COVID. The American Medical Association (AMA), American Pharmacists Association (APhA) and American Society of Health-System Pharmacists (ASHP) issued a statement in September strongly opposing the ordering, prescribing or dispensing of ivermectin to prevent or treat COVID outside of a clinical trial.
But their statement relied solely on the FDA’s and CDC’s suspect positions.
The AMA, APhA and ASHP also mentioned a statement by Merck — the original patent-holder — opposing the use of ivermectin for COVID because of a “concerning lack of safety data in the majority of studies.”
“But Merck, of all sources, knows that ivermectin is exceedingly safe, so the absence of safety data in recent studies should not be concerning to the company,” Peterson wrote.
Peterson called into question the objectivity of Merck in providing an opinion on ivermectin that U.S. health agencies are relying upon. “Why would ivermectin’s original patent holder go out of its way to question this medicine by creating the impression that it might not be safe?” Peterson asked. “There are at least two plausible reasons.”
Peterson explained:
“First, ivermectin is no longer under patent, so Merck does not profit from it anymore. That likely explains why Merck declined to ‘conduct clinical trials’ on ivermectin and COVID-19 when given the chance.
“Second, Merck has a significant financial interest in the medical profession rejecting ivermectin as an early treatment for COVID-19. [T]he U.S. government has agreed to pay [Merck] about $1.2 billion for 1.7 million courses of its experimental COVID-19 treatment, if it is proven to work in an ongoing large trial and authorized by U.S. regulators.”
Merck’s treatment is known as “molnupiravir,” and aims to stop COVID from progressing when given early in the course of disease. When Merck announced Oct. 1, that preliminary studies indicated molnupiravir reduced hospitalizations and deaths by half, the drug maker’s stock price immediately jumped to 12.3%.
“Thus, if low-cost ivermectin works better than, or even the same as molnupiravir, that could cost Merck billions of dollars,” Peterson wrote.
Pharma giant Merck is facing accusations of price gouging after it charged the U.S. more than $700 per patient for a taxpayer-funded coronavirus treatment that, according to research, costs just $17.74 to produce.https://t.co/BSYYnPmRBl
Peterson said based on his review of the evidence, his office did not find clear and convincing evidence that would warrant disciplining physicians who prescribe hydroxychloroquine for the prevention or early treatment of COVID after first obtaining informed patient consent.
Peterson pointed to similar findings with hydroxychloroquine — a less toxic derivative of a medicine named chloroquine — widely used since it was approved by the FDA in 1955 for treatment of malaria.
Peterson noted that as early as 2004, a lab study revealed chloroquine was “an effective inhibitor of the replication of the severe acute respiratory syndrome coronavirus (SARS-CoV) in vitro” and should “be considered for immediate use in the prevention and treatment of SARS-CoV infections.”
In 2005, another study showed chloroquine had strong antiviral effects on SARS-CoV infection and was effective in preventing the spread of SARS-CoV in cell cultures.
Other studies showed hydroxychloroquine exhibited antiviral properties that can inhibit SARS-CoV-2 virus entry, transmission and replication, and contains anti-inflammatory properties that help regulate pro-inflammatory cytokines.
Peterson wrote, “many large observational studies suggest that hydroxychloroquine significantly reduces the risk of hospitalization and death when administered to particularly high-risk outpatients as part of early COVID-19 treatment.”
Peterson said the drug is considered to be so safe it can be prescribed for pregnant women, yet during the pandemic, the FDA raised questions about hydroxychloroquine and adverse cardiac events.
These concerns prompted one group of researchers to conduct a systematic review of the hydroxychloroquine safety literature pre-COVID. Their review indicated people taking hydroxychloroquine in appropriate doses “are at very low risk of experiencing cardiac [adverse events], particularly with short-term administration” of the drug.
Researchers noted COVID itself can cause cardiac problems, and there was no reason “to think the medication itself had changed after 70 years of widespread use,” Peterson wrote.
Peterson said one piece of key flawed data had substantially contributed to safety concerns surrounding the drug — the admittedly fraudulent Lancet study that falsely claimed hydroxychloroquine increased frequency of ventricular arrhythmias when used for treatment of COVID.
The findings were so startling that major drug trials involving hydroxychloroquine “were immediately halted” and the World Health Organization pressured countries like Indonesia that were widely using hydroxychloroquine to ban it. Some countries, including France, Italy and Belgium, stopped using it for COVID altogether.
Peterson wrote:
“The problem, however, is that the study was based on false data from a company named Surgisphere, whose founder and CEO Sapan Desai was a co-author on the published paper.
“The data were so obviously flawed that journalists and outside researchers began raising concerns within days of the paper’s publication. Even the Lancet’s editor in chief, Dr. Richard Horton, admitted that the paper was a fabrication, a monumental fraud and a shocking example of research misconduct in the middle of a global health emergency.”
Despite calls for the Lancet to provide a full expansion of what happened, the publication declined to provide details for the retraction.
As with ivermectin, the FDA and NIH adopted positions against the use of hydroxychloroquine for COVID — making assertions that were unsupported by data. The AMA, APhA and ASHP, which opposed ivermectin, also resisted hydroxychloroquine for the treatment of COVID.
By contrast, the Association of American Physicians and Surgeons, and other physician groups, support the use of both ivermectin and hydroxychloroquine as an early treatment option for COVID. Peterson cited an article co-authored by more than 50 doctors in Reviews in Cardiovascular Medicine who advocated an early treatment protocol that includes hydroxychloroquine as a key component.
Governing law allows physicians to prescribe ivermectin and hydroxychloroquine, AG says
Neb. Rev. Stat. § 38-179 generally defines unprofessional conduct as a “departure from or failure to conform to the standards of acceptable and prevailing practice of a profession or the ethics of the profession, regardless of whether a person, consumer or entity is injured, or conduct that is likely to deceive or defraud the public or is detrimental to the public interest.”
The regulation governing physicians states that unprofessional conduct includes:
“[c]onduct or practice outside the normal standard of care in the State of Nebraska which is or might be harmful or dangerous to the health of the patient or the public, not to include a single act of ordinary negligence.”
Peterson said healthcare providers do not violate the standard of care when they choose between two reasonable approaches to medicine.
“Regulations also indicate that physicians may utilize reasonable investigative or unproven therapies that reflect a reasonable approach to medicine so long as physicians obtain written informed patient consent,” Peterson wrote.
“Informed consent concerns a doctor’s duty to inform his or her patient, and it includes telling patients about the nature of the pertinent ailment or condition, the risks of the proposed treatment or procedure and the risks of any alternative methods of treatment, including the risks of failing to undergo any treatment at all.”
Peterson said this applies to prescribing medicine for purposes other than uses approved by the FDA, and that doing so falls within the standard of care repeatedly recognized by the courts.
Peterson said the U.S. Supreme Court has also affirmed that “off-label usage of medical devices” is an “accepted and necessary” practice, and the FDA has held the position for decades that “a physician may prescribe [a drug] for uses or in treatment regimens or patient populations that are not included in approved labeling.”
Peterson said the FDA has stated “healthcare providers generally may prescribe [a] drug for an unapproved use when they judge that it is medically appropriate for their patient, and nothing in the federal Food, Drug and Cosmetic Act (“FDCA”) limit[s] the manner in which a physician may use an approved drug.”
In a statement to KETV NewsWatch 7, Nebraska’s Department of Health and Human Services said:
“The Department of Health and Human Services appreciates the AG’s office delivering an opinion on this matter. The document is posted and available to medical providers as they determine appropriate course of treatment for their patients.”
Comments Off on Groundbreaking: Nebraska AG Says Doctors Can Legally Prescribe Ivermectin, HCQ For COVID, Calls Out FDA, CDC, Fauci, Media For ‘Fueling Confusion & Misinformation’