Malone states the emergency use authorizations (EUA) are two years old and are expiring and need to be re-implemented, therefore there is a perverseincentive for our government to amplify the fear porn to keep the basis for the EUA alive. If a state of emergency does not continue, EUAs vanish like dust into the wind.
A perfect example is the Omicron death that wasn’t. Mainstream media widely reported the death as a “reinfection” of an unvaccinated man who previously had COVID. The problem is the man didn’t die from COVID. He died testing positive for the Omicron variant. He also had comorbidities. This singular case was blown all out of proportion and used to keep EUA alive. Don’t fall for it, and expect more of it.
China is separating family members, dragging folks from their homes, cramming them into buses & locking them up in metal boxes every time a new variant appears. Kids locked up alone, apart from their parents.
France just passed a law that excludes the unvaccinated from public places. Certificates of “vaccination” are required to go anywhere.
Italy mandated the jab for those over 50 and tightened green pass obligations even though the “vaccine” does not protect people from Covid but increases the chances of infection from Omicron and hospitalization.
In Greece, the unvaxxed who are over 60 will be fined 100 euros per month.
Massive protests occurred in the Netherlandsover the government imposed covid-19 restrictions & “vaccination” campaign. A January protest made world headlines when the police allowed (or ordered?) their dogs to launch brutal attacks against the protesters. In the midst of this upheaval, a young man named Gideon van Meijeren recently elected to the Dutch Parliament soundly confronts the Prime Minister.
Autopsy findings show vaccine induced autoimmune pathology in the heart, lung, liver, thyroid, salivary glands, and brain. Inflammatory events occur in the small blood vessels with an abundance of T-lymphocytes & sequestered, dead endothelial cells within the lumen.
The COVID-19 jabs rely on providing geneticinformation to the body to force it to produce a modified form of the spike protein, and should not be defined as a vaccine.
The spike protein is toxic in its own right and may induce adverse effects on the body
The viral vector jabs by AstraZeneca and Johnson & Johnson rely on human fetal cell lines and the majority of the protein in the jabs may be from this source, rather than from the viral vectors themselves.
COVID-19 jabs, especially if given repeatedly every few months, will likely cause lasting negative impacts on immune system function so increasing the risk of a wide range of other diseases while increasing risks of adverse reactions.
Clear evidence has emerged that data used for “vaccine surveillance” by the UK Health Security Agency (formerly Public Health England) has been accidentally or deliberately misrepresented to infer outcomes among the jabbed are better than for those who decline.
There is little or no evidence that informed consent is being, or has been, offered at any time during the “pandemic.”
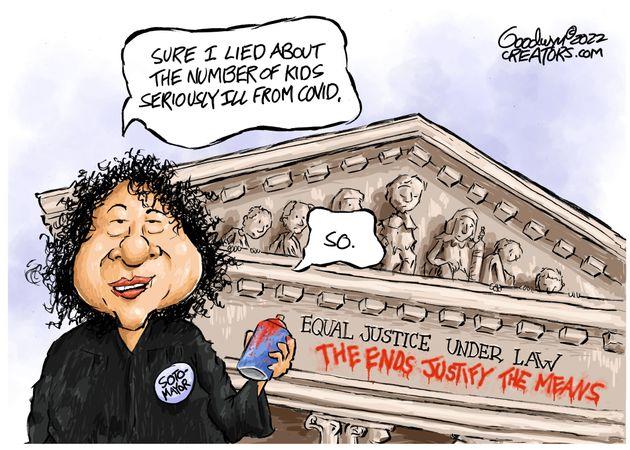
Despite the misinformation spewed forth by Justice Sotomayor, The US Supreme Court has blocked the Biden administration’s vaccine-or-test rule for US businesses, but allows vaccine mandate for most health care workers.
The National Federation of Independent Business (NFIB) argue against the Department of Labor, in the Court’s first hearing, that:
“OSHA’s sweeping regulatory dictate,” will “irreparably injure the very businesses that Americans have counted on to widely distribute COVID-19 vaccines and protective equipment to save lives—and to keep them fed, clothed, and sustained during this now two-year-long pandemic.”
The Occupational Safety and Health Administration (OSHA) rule would have required 80 million workers to get shots or periodic tests.
The OSHA ruling vote was 6-3 with Breyer, Sotomayor, and Kagan in dissent. (See link for article)
_________________
Important points:
The court allowed requiring shots for workers in nursing homes, hospitals and other facilities that receive Medicare and Medicaid payments from the federal government. (Just another reason in a very long line showing that getting government money always has strings attached.)
The vaccine mandate for healthcare workers vote was 5-4 with Thomas, Alito, Gorsuch, and Barrett in dissent, which means Roberts and Kavanaugh joined liberal justices in allowing the HHS mandate on healthcare workers to stand.
Most Americans Will Get COVID Eventually, Says Fauci
— But chances of getting sick are “very, very low” if you’re vaccinated and boosted
by Joyce Frieden, Washington Editor, MedPage Today January 12, 2022
WASHINGTON — Sooner or later, most Americans will wind up getting COVID-19, although it will likely be pretty mild for those who are vaccinated and boosted, a Biden administration official said Wednesday.
During a press briefing held by the White House COVID-19 Response Team, MedPage Today asked members of the team to elaborate on the remark that “most people are going to get COVID” made by Acting FDA Commissioner Janet Woodcock, MD, during a Senate hearing Tuesday. (See link for article)
__________________
**Comment**
Fauci finally tells the truth: COVID will NOT be eradicated and it is highly likely everyone will get it,like every other coronavirus, flu, and cold we haven’t eradicated. Logic would now follow that natural immunity would be preferred, yet our corrupt public health authorities who own the patent on the spike protein and on the injections have censored this well-known and accepted scientific fact and only push the lucrative, dangerous shots which have caused more damage than any other “vaccine” in the history of VAERS.
In a July 1, 2021, commentary in The Lancet Microbe,3 Piero Olliaro, Els Torreele and Michel Vaillant also argue for the use of absolute risk reduction when discussing vaccine efficacy with the public. They too went through the calculations, coming up with the following:
Since the beginning of the pandemic, experts have warned that the PCR test is not a valid diagnostic and produces far too many false positives, as it can pick up on “dead,” nonreplicating viral debris
The U.S. Centers for Disease Control and Prevention now admits the PCR test can remain positive for up to 12 weeks after infection. For this reason, they say most people don’t need to retest negative before ending their quarantine
The CDC also admits the PCR cannot identify active infection or measure contagiousness
People who are double-jabbed or unvaccinated and test positive for SARS-CoV-2, or have known exposure, but remain asymptomatic, now only need to isolate for five days rather than 10, but should wear a mask for another five days when at work or in public. People who are triple-jabbed do not need to isolate after exposure, but should wear a mask for 10 days
Health care workers who test positive for COVID but remain asymptomatic can return to work after seven days with a negative test, but isolation time can be cut to five days if there are staffing shortages
From the earliest days of the COVID pandemic, the PCR test has been a source of unrelenting controversy, with experts repeatedly pointing out that it’s not a valid diagnostic and produces inordinate amounts of false positives.
Importantly, a PCR test cannot distinguish between “live” viruses and inactive (noninfectious) viral particles. This is why it cannot be used as a diagnostic tool. As explained by Dr. Lee Merritt in her August 2020 Doctors for Disaster Preparedness1 lecture, media and public health officials appear to have purposefully conflated “cases” or positive tests with the actual illness in order to create the appearance of a pandemic.
Furthermore, a PCR test cannot confirm that SARS-CoV-2 is the causative agent for clinical symptoms as the test cannot rule out diseases caused by other bacterial or viral pathogens.
Almost universally, health authorities have also instructed labs to use excessively high cycle thresholds (CTs) — i.e., the number of amplification cycles used to detect RNA particles — thereby ensuring a maximum of false positives.
From the start, experts noted that a CT over 35 is scientifically unjustifiable,2,3,4 yet the U.S. Food and Drug Administration and the U.S. Centers for Disease Control and Prevention recommended running PCR tests at a CT of 40,5 and the World Health Organization recommended a CT of 45.
The pandemic of false positives was then used by world governments to implement pandemic countermeasures that have destroyed the global economy, ruined countless lives, decimated the education of an entire generation and stripped us of basic human rights and freedoms.
What the CDC’s belated admission means is that, for the past two years, Americans have unnecessarily wasted time in self-isolation — perhaps weeks — waiting for a negative test.
Time and again, the goal post for ending the pandemic theatre has been moved, and the justifications for continuing the life-destroying countermeasures have become increasingly laughable. The fearmongering over Omicron, for example, makes no rational sense based on the data available, which shows the variant is among the mildest so far, and far less likely to infect and damage the lungs.6
In the last days of December 2021, the U.S. Centers for Disease Control and Prevention issued yet another illogical protocol change.7 People who test positive for SARS-CoV-2, or have known exposure, but remain asymptomatic, now only need to isolate for five days rather than the previous 10, but should wear a mask for another five days when at work or in public. Also, they don’t need to get retested at the end of their quarantine. The stated reason? Because:
The majority of viral transmission (85% to 90%8) occurs in the first day or two before symptom onset, and two to three days after symptom onset9
The PCR test can remain positive for up to 12 weeks after you’ve recovered from the infection10,11
How is it that the CDC didn’t realize until now that the PCR test was picking up dead viral debris for three months after infection? The facts that the test, a) was far too sensitive, and b) couldn’t identify active infection, were criticisms from the start. What the CDC’s belated admission means is that, for the past two years, Americans have unnecessarily wasted time in self-isolation — perhaps weeks — waiting for a negative test.
In a December 30, 2021, appearance on MSNBC, Dr. Anthony Fauci responded to questions about the updated CDC guidance. CDC director Rochelle Walensky also tried to make sense of the new guidance in a December 29, 2021, ABC News interview (see videos above).12
Neither of them offered any explanation as for why the CDC didn’t change the rules sooner, and only now decided that keeping noninfectious people in isolation for days and weeks on end might not be so good after all.
Walensky did make a rather telling comment on CNN, though, when asked about the reasoning behind the shortened isolation guidance. “It really had a lot to do with what we thought people would be able to tolerate,” she said.13 Some have understandably translated that as “how much tyranny we thought people would be able to tolerate.”14
Differing Rules for Health Care Workers
The CDC has not given up on making the guidance as confusing as possible though. December 23, 2021, they also updated guidance for health care workers,15 stating that “Health care workers with COVID-19 who are asymptomatic can return to work after seven days with a negative test, and that isolation time can be cut further if there are staffing shortages.”16
In his MSNBC interview, Fauci was asked why health care workers are being treated differently, having to isolate for seven days rather than five, and still have to get a negative test, when the test can falsely remain positive for up to 12 weeks? What data supports this, and is it publicly available?
According to Fauci, the data to support this difference “is internal to the CDC,” but really, there’s “no specific data” to back it up, he adds. The CDC merely made “a judgment call.”
Double-Jabbed Treated the Same as Unvaccinated
The CDC’s updated guidance also puts those who have received two doses of the COVID shot in the same category as the unvaccinated, so when it comes to isolating after exposure, they have to follow the same rules, whereas those who have received a booster shot follow a different set of guidelines. As explained by the CDC:17
“For people who are unvaccinated or are more than six months out from their second mRNA dose (or more than 2 months after the J&J vaccine) and not yet boosted, CDC now recommends quarantine for 5 days followed by strict mask use for an additional 5 days.
Alternatively, if a 5-day quarantine is not feasible, it is imperative that an exposed person wear a well-fitting mask at all times when around others for 10 days after exposure. Individuals who have received their booster shot do not need to quarantine following an exposure, but should wear a mask for 10 days after the exposure.
For all those exposed, best practice would also include a test for SARS-CoV-2 at day 5 after exposure. If symptoms occur, individuals should immediately quarantine until a negative test confirms symptoms are not attributable to COVID-19.”
Fauci defended the decision to treat the double-jabbed as if they’re unvaccinated saying that those who have received a booster shot have far greater protection against the Omicron variant, compared to those who have only received one or two doses.
“When you’re infected, you’re infected,” Fauci said, and it doesn’t matter whether you’re vaccinated or not. The viral load is the same, so the risk of spreading the infection is the same. Those who have been boosted are less likely to be infected or carry a large viral load, hence they don’t need to isolate.
PCR Cannot Tell You Anything About Contagiousness
Fauci was also asked about how one can measure contagiousness. If the PCR can register positive for 12 weeks after an infection, it can’t be a reliable indicator of infectiousness. This was precisely the point that Mullis, inventor of the PCR test, attempted to make in the video at the top with respect to PCR and HIV.
So, how can we tell if we’re infectious or not? Fauci confirmed that the PCR can only tell you there’s a presence or absence of viral fragments, not whether it’s an active infection, or whether you’re actually infectious. He did not, however, provide an answer to the question as to how one can measure contagiousness.
Rapid Test Doesn’t Pick Up Omicron
Yet another confounding factor in this mess is that the rapid test apparently doesn’t pick up Omicron very well.18 Your viral load needs to be very high at the time of testing in order for the rapid test to recognize it.
This admission came within days of president Biden’s announcement that the federal government will distribute half a billion free rapid tests to homes around the country in 2022.19
It seems like a waste of resources, seeing how Omicron is starting to take over, but who knows, maybe it will pick up the common cold instead, allowing the “case” count to remain high enough to keep the charade going.
What’s the Real Death Count?
The CDC’s belated admission that the PCR test can’t identify active infection raises another question: What does this mean for those who died with a positive test? Did they actually have an active infection? If not, should they have been designated as COVID deaths?
The obvious answer to the last two questions is, of course, no. The vast majority were likely false positives, and the real death toll from COVID-19 considerably lower than we’re led to believe. The CDC undoubtedly knew this all along, seeing how they’ve been relentlessly criticized for their recommendation to run the PCR at a CT of 40. They’re trying to pretend that they just realized this, but that’s simply not believable.
My daily newsletter is still free and content will be released on Mercola.com before anywhere else. After 48 hours the articles will be transferred to my Censored Library on Substack. To view any missed content, a private membership is available for a very minimal amount with a portion of proceeds going toward our health partners who are helping in the fight to protect our freedom of speech and your right to take control of your health: https://www.mercola.com/censored-library.htm You can access the article and videos in this link for a fee.
___________________
Lastly, both Fauci and Walensky lied under oath regarding VAERS COVID injection deaths.
As of Jan. 7, 2022 there have been nearly 22,000 reported deaths after the jabs.
Comments Off on Supreme Court Blocks Biden’s OSHA Vaxx Mandate & Fauci Tells Truth About Faulty PCR Test & That We’ll All Get COVID, But Lies About Injections & Deaths
Episode #158: Chronic UTIs and Interstitial Cystitis with Ruth Kriz, MSN, APRN
Last Updated: December 14 2021
Why You Should Listen
In this episode, you will learn about chronic UTIs and Interstitial Cystitis.
Watch The Show
Listen To The Show
About My Guest
My guest for this episode is Ruth Kriz. Utilizing her functional medicine background as well as experience in microbiology and teaching pharmacology, Ruth Kriz, MSN, APRN has spent the majority of her professional career as a Nurse Practitioner working with Chronic UTI and Interstitial Cystitis patients. Her practice expanded to patients from almost all the states in the US as well as from 35 countries who came to her seeking answers beyond symptom management. Through molecular testing, an understanding of the genetics common to these patients, and an understanding of how this contributes to chronic infection and biofilms, she has been able to successfully treat this population. These factors have broad implications for other chronic infections (sinus, prostate, ear infections, wounds, etc.) as well as fibromyalgia, cardiovascular disease, and other conditions in which biofilms are an important contributor. She has closed her medical practice, but she has reinvented as a consultant to help practitioners learn how to utilize her approach for curing these patients.
Key Takeaways
How do chronic UTIs evolve into Interstitial Cystitis (IC) over time?
What are the primary contributors to chronic UTIs and IC?
How is the potential for infection best explored in these conditions?
What types of microbes are commonly found in these patients?
Do chronic Lyme disease and mold illness play a role in these conditions?
What are the key genetic contributors?
What role does ammonia play in creating the right environment for microbial overgrowth?
How might Nrf2 support be helpful in treating these conditions?
What is the role of hypercoagulation and biofilm?
How does vitamin D impact these conditions?
Is MCAS involved in chronic UTIs and IC?
Are oxalates a primary contributor?
What are some of the treatment options to explore?
Why is detoxification support important?
What is the prognosis for those dealing with chronic UTIs and IC?
Great, practical information within this video. Please watch.
Summary:
Starting at 1:00 Dr. Jane discusses “chain of custody,” or the process and verification of how an object moves from point A to point B. There are special procedures for moving samples to and from a lab for screening. COVID injection vials also have “chain of custody” where they are signed for and carefully followed.
At 2:20 Dr. Ruby discusses that in her experience those getting COVID again(which again, can’t be verified due to the PCR fraud occurring and the inability to know if something truly is COVID) have had experimental monoclonal antibodies or the jab. Getting the antibodies is like renting an army for a day. They come in, clean house, but then go away. On the other-hand, the soldiers in your immune system stay around, continuing to clean house as needed. Those getting the jab are catching every little cold bug or flu that’s going around.
at 4:30 Dr. Ruby discusses the doctors looking at “vaxxed” blood continue to follow up with patients, and at 5:04, they show a slide with strange, irregular, compact blood vessels. The patients are also doing worse clinically – struggling with weakness, fatigue, severe illnesses, autoimmunity, and even hospitalizations. Doctors looking at vial ingredients have revealed horrificfindings.
at 6:45, they discuss the fact that the Novavax shot still injects you with the toxic, bioweapon spike protein by the billions, you just get it differently. They take mRNA designed to force the development of toxic, foreign spikes in your body and they put it in a baculovirus (insect pathogenic virus) which infects moths but not humans per say. They then transport the mRNA to the moth, which then makes billions of spikes which the company then extracts and puts on a graphene sheet and then fills a vial with adjuvant. All of the COVID jabs are dangerous. There isn’t one that’s safe, and none of them are “vaccines.”
“Viruses burn down, not up.” ~ Dr. Ruby This simply means that viruses grow weaker over time, not stronger.
We are in a cold and flu season. This is nothing new, but it will all be labeled COVID.
Despite the fact the CDC recalled the PCRtest they state it can continue to be used for the rest of the year. There is absolutely no way PCR can determine what variant is causing illness.
CDC Walensky states, “These tests are not authorized for the purpose of evaluating contagiousness.” Yet, these very tests have been used to keep people from working, going to school, and participating in society.
There’s an old expression: “When you’re a hammer, everything looks like a nail”. Sometimes referred to a “Maslow’s hammer”, this expression captures the idea of the law of the instrument. The origin of the expression seems to be from the observations that if you give a boy a hammer, they start pounding away at everything. Wikipedia has a good page on the history of this expression.
Everyone testing with the BinaxNOW nasal swab test, for example should be aware that per the documents provided by Abbott to the US FDA, their test can be a false positive if the person is infected with the HKU1 virus. (See the IFU Document):
“The comparison between SARS-CoV-2 nucleocapsid protein, MERS-CoV and human coronavirus HKU1 revealed that cross-reactivity cannot be ruled out.”
This language (or similar) is found in other IFU Documents for other COVID-19 RAT tests as well.
That means the test lacks pathogen specificity, and FDA cannot tell us what the risk of a false COVID-19 indication is without follow-up PCR testing. Further, like the PCR test, the comparison was only computational, based on BLAST-determine homology, not based on studies of thousands of patients. Further, protein structure, not sequence, is important for cross-reactivity – BLAST is not refined enough a tool to determine actually binding capacity, yet the FDA allowed negative BLAST results as evidence of degree of specificity.
PCR testing is similarly fraught with its own false positive problems, in part due to the same error (allowing BLAST results instead of requiring actual data from large studies). This is an issue the CDC could be finally coming to terms with after IPAK published a peer-review study in our journal on the problem, after Dr. Sin Hang Lee published two studies, after dozens of videos and articles have been written by yours truly alerting the world of the problem of PCR false positives due to the use of high cycle thresholds, and after an uproar over the fact that the PCR tests do not rule in Influenza.
HKU1, aka HCoV-HK1, first detected in 2004 in Hong Kong, is a Betacoronavirus (because it has a Hemagglutinin esterase gene), and enters the cell via a different recept that SARS-CoV-2. Like SAR-CoV-2 and SARS-CoV-2, it is an enveloped, single-stranded RNA virus.
“Of 832 adult respiratory specimens screened, 13 (1.6%) cases of CoV-HKU1 were identified. Adults age ranged between 23 and 75 years and 6 (46%) were males. All of whom had 1 or more respiratory symptoms, and 5 (38%) also reported 1 or more gastrointestinal symptoms. Eleven (85%) reported history of smoking and 5 (38%) used inhaled steroids. Seven (54%) required hospitalization, 5 (71%) of these needed supplemental oxygen, and 2 (29%) were admitted to intensive care. Median length of hospitalization was 5 days. Eight (62%) received antibiotics despite identification of CoV-HKU1. Infectious work-up in 1 patient who died did not reveal any other pathogen. In 2 (15%) CoV-HKU1-positive adults, the only viral coinfection detected was influenza A.”
In 15% of people studied, co-infection with Influenza A was detected. That’s fairly common. For all of 2020-2021, for two years, “co-infection” of COVID-19 patients (PCR+ for SARS-CoV) was not even mentioned. Now that everyone (well, nearly everyone) is testing with in-home nasal swab kits for antibodies, many will be positive but will actually be HKU-1. Given the FDA’s allowance of specificity-by-BLAST, the problem could be much worse.
Why This is Dangerous
There are few good reasons why this is dangerous. Yes, the problem will make it appear as if more people have COVID-19 than actually do. The clinical workflow for COVID-19 is far more strenuous than for influenza A or HKU-1, so there’s the added burden on the healthcare system. I’ve heard reports that some hospitals are resorting to triage, placing non-PCR+ non-respiratory illness patients at risk (the in-hospital PCR screening adds to this as well).
However, people who have had a positive Rapid Antigen Test may also come to think of COVID-19 as mild for them, and their families – and worse – they may believe they have natural immunity and let their guard down. They may be more willing to attend a large gather, or mingle with others while symptomatic.
Third, false positives from PCR and from RAT tests alike will lead the public – and public health and medical communities – to believe that re-infection with SARS-CoV-2 is possible. The dynamics of societal responses will be flawed, leading to more quarantine, shut-downs, draconian control measures.
Fourth, the clinical care for a person who has respiratory viral infections other than SARS-CoV-2 may be different. If 15% of patients with “COVID-19” have something else, the CDC should know and medical practice should be altered to address this.
Every single person who tests positive via PCR or RAT who has clinical symptoms or who has been exposed to a confirmed case of COVID-19 should have a confirmatory Sanger Sequencing test conducted to ensure what they have (or had) was truly a SARS-CoV-2 infection. As an added benefit, unlike PCR or RAT,Sanger Sequencing can tell us what variant we have (or have had).
There are over 6,000 laboratories around the US that can conduct Sanger Sequencing, and Sin Hang Lee, MD of Millford, CT is happy to provide the information on the primers he has developed for nested primer target amplification – and for Omicron detection.
Here’s a requisition form that can be used to order the Sanger Sequencing test (I have no financial relationship w/Dr. Lee or Millford Diagnostics).
The Law of the Instrument tells us that if you only test for COVID-19, you’ll only find COVID-19. Multiplex respiratory pathogen tests are also used in some places.
Please share with doctors and nurses in your area. This could help you & your loved ones travel a safer course.
The PCR test yields 80-97% FALSE POSITIVES, and Borger says it does NOT detect a virus. He also uses the comparison of finding a wheel and a hubcap from a Mercedes in a junkyard. You can not infer you are in a Mercedes garage based on only seeing 2 parts. He states it has ZERO relevance for diagnosis. This was recently supported by a paper published by Nature.com, which found no “viable virus” in PCR positive cases.
Until We the People refuse to be tested by a test that doesn’t test for the very thing they claim it does, we can expect more lockdowns, more mandates, and more tyranny. Time to stand up and refuse to be a part of this complete farce.
Comments Off on Dr. Ruby: No Validated COVID Test, Rapid Antigen Test Not Specific, Can You Get COVID Again? Monoclonal Antibodies, Vaxxed Blood, Vial Batches, & Nebulized Peroxide Treatment