Archive for the ‘research’ Category

How to Treat Persister Lyme & Bartonella

https://www.treatlyme.net/guide/treat-persister-lyme-works

How to Treat Persister Lyme & Bartonella

By Dr. Marty Ross

Persister Lyme in a Lyme disease treatment image from Marty Ross MD

I provide a large part of the information in this article in A Lyme Disease Antibiotic Guide and in Kills Bartonella: A Brief Guide. I am including this information as a stand-alone article on persisters for those looking for information just on this topic and additional persister treatment options from those I lay out in the Lyme and Bartonella articles.

Marty Ross MD

About Persister Lyme & Bartonella

There are many reasons Lyme and Bartonella are hard to treat. One reason is persister Lyme and Bartonella germs ignore standard antibiotics. Based on numerous laboratory experiments since 2015, the Lyme germ is shown to have a growth state and a hibernating – non-growing state. These hibernators are called persisters. They do not respond to regular prescription antibiotics – although they do seem to respond to many herbal antibiotics that we use.

More recently – experiments starting in late 2019 from Ying Zhang, MD and his colleagues, show that Bartonella also has persister forms.  (See link for article)

__________________

SUMMARY of treatments Dr. Ross uses for Lyme and/or Bartonella persisters:

  • Disulfiram
  • Methylene Blue
  • Cefuroxime plus Clarithromycin plus Nitazonxanide
  • Oregano, Cinnamon, and Clove oils
  • Japanese knotweed
  • Cat’s claw
  • Azlocillin

I highly recommend reading Ross’ entire article as there are many nuances within it including Dr. Burrascano‘s use of cycling.  He and numerous patients achieved remission using this approach and current research appears to support the practice.  Not only is cycling effective, it gives the body, particularly the gut, a much needed break from harsh antibiotics.

For more:

The Bartonella Discovery Program

http://  Approx. 2 Min

Global Lyme Alliance (GLA) Chief Scientific Officer, Timothy Sellati, PhD

Learn about an exciting research project that Global Lyme Alliance is fundraising for. It will uncover the “stealth” pathogen known as Bartonella that many Americans may carry. This study can help children, parents, and grandparents who suffer from psychiatric & neurological problems, among other physical illnesses. Learn more and donate at GLA.org/bartonella

https://www.globallymealliance.org/videos/dr.-sellati-explains-the-bartonella-discovery-program

Global Lyme Alliance (GLA) has launched a crowdfunding campaign in honor of Lyme Disease Awareness Month in May. GLA will use this campaign to bring attention to another debilitating illness that also affects many people with Lyme disease. The study will look at hidden bacteria known as Bartonella, a vector-borne pathogen that many Americans may carry. Bartonella can cause Bartonellosis, an infectious disease that can affect the brain, eyes, heart, and other organs. Bartonellosis can cause depression, anxiety, OCD, and encephalitis (which can result in seizures and coma). 

Like Lyme disease, Bartonellosis is increasing in prevalence and can also go undiagnosed due to lack of awareness. Current antibiotic therapy for complicated Bartonellosis does not always eradicate the disease, and patients continue to suffer. The Bartonella Discovery Program is a project designed to help achieve the following:

  • To identify how Bartonella species interact with a patient’s immune cells, and how the intracellular, extracellular and biofilm lifestyles of Bartonella influence antibiotic susceptibility
  • To lay the foundation for drug discovery efforts to find antibiotic options that are more effective in killing and clearing these bacteria from patients
  • To use cutting edge tools to look for the bacteria in kids and young adults who suffer from an acute neuropsychological condition called PANS, and in older adults with dementia.

 “The importance of this study cannot be overstated because of the severe neuroinflammation and neuropsychiatric disorders some patients can suffer when infected with Bartonella bacteria,” says GLA’s Chief Scientific Officer Tim Sellati, PhD.

The U.S.-focused study is multinational and multi-site at premier academic institutions using top Bartonella and biofilm experts. Associate Professor Monica Embers, PhD, a microbiologist and immunologist at the Tulane National Primate Research Center who has studied the persistence of tick-borne infectious diseases despite antibiotic therapy, is The Bartonella Discovery Program Director. When asked about the impact this program could have on patients,

Dr. Embers said, “With this project, we aim to use sensitive detection methods to directly find the bacteria in patients who are suffering from clinical disease consistent with Bartonellosis.   This could tremendously impact patients who suffer from chronic disease that has been difficult to diagnose because if we can reliably detect the bacteria, it would offer direct evidence to support the diagnosis.”

Learn more and donate by clicking the link button below.

Picking Apart the TOGETHER Trial & the Latest NEJM Ivermectin Study Which Were Designed to Fail

https://flccc.substack.com/p/the-together-trial-was-designed-to

The TOGETHER Trial Was Designed to Fail

Big Pharma has been sponsoring trials to discredit cheap generic treatments for COVID since the earliest days of the pandemic.

If you read anything about the TOGETHER trial in the past few weeks (and you didn’t read it here) chances are you heard the tired trope that ivermectin doesn’t work.

When the study was published, the media urgently blasted out clickbait headlines to this effect, uncritically rehashing Big Pharma propaganda. The Wall Street Journal blared “Ivermectin Didn’t Reduce Covid-19 Hospitalizations in Largest Trial to Date” and The New York Times trumpeted, “Ivermectin Does Not Reduce Risk of Covid Hospitalization, Large Study Finds.”

The problem, as ever, is that the study was designed to fail. In a piece published by The Brownstone Institute, Dr. Pierre Kory highlights the study’s flaws:

There were no explicit exclusion criteria for trial participants on ivermectin, meaning both trial groups had access to the same drug. This is an indefensible omission given that in Brazil, where the trial was conducted, ivermectin is available over-the-counter and widely used.

The treatment window was set for only three days, an obvious “tell” of underdosing given, for example, that both Merck’s molnupiravir and Pfizer’ Paxlovid require five days. The trial actually started out testing only a single dose, presumably until the investigators realized they could never disprove anything with that regimen.

And the trial was conducted during the throes of the massive gamma variant surge, one of the most virulent and deadly COVID variants. The dosage of the trial was far lower than everyday Brazilian clinicians were prescribing patients at the time to match the strength of the strain.

It’s amazing to see so many powerful headlines for such a half-baked study, when a similar, far larger study published in January showing ivermectin led to massive reductions in COVID infection, hospitalization and mortality received virtually no media coverage.

But this is nothing new. Big Pharma has been sponsoring trials to discredit cheap generic treatments for COVID since the earliest days of the pandemic. It has addicted media companies to its bottom-line well of advertising cash, ensuring the study results are blindly parroted all over the Internet to reinforce the company line: more expensive treatments and vaccines work, cheap generic alternatives don’t. Social media companies, just as drunk on power and pharma cash, censor and shut down all dissent.

Pierre highlights a particularly aggravating example:

Clicking on a Reddit thread featuring MDs, PhDs and public health professionals discussing the randomization of the TOGETHER trial first brings users to an ominous page with a “quarantine” caveat, urging readers to “please consult your physician.”

The most grotesque perversions imaginable are readily available to any child on the Internet, but informed medical conversations come with a warning label.

Using fear to force doctors to toe the line

The TOGETHER trial is just another step on the way to destroying doctors who don’t toe the company line. California Democrats are pushing legislation (Assembly Bill 2098) that would grant the state power to rescind doctors’ medical licenses if they dissent from government positions on Covid, which are effectively dictated by Big Pharma.

To fight the malevolent forces behind these campaigns, we need to reform our dysfunctional drug approval process. Pierre’s outlines what needs to happen:

An independent board free of pharma industry conflicts must be established to oversee trials for re-purposed medicines. Recommendations should be based on trials designed by impartial experts and actual results, not the desired ones, and policymakers or prescribers who ignore the findings should be held accountable.

We must also remind academia and the regulatory agencies that observational trials data—wherein a sample of population who take a drug are compared to those who do not is equally valid at informing policy. Since Covid, regulators and academic medical centers have erroneously placed greater emphasis on large, expensive randomized controlled trials. While these trials can yield useful information, but their complexity, costs, and delays to treatment lead to errors and effectively shut out low-cost drugs from the approval process, regardless of their efficacy.

If our leaders in government fail to heed this advice, greed will continue to corrupt scientific study and erode the practice of medicine until doctors and patients are further relegated as little more than cogs in a billing machine.

You can read Pierre’s op-ed in full at The Brownstone Institute.

_________________

https://popularrationalism.substack.com/p/patient-attribution-bias-explains

Patient Attrition Bias Explains The Latest NEJM Ivermectin Study

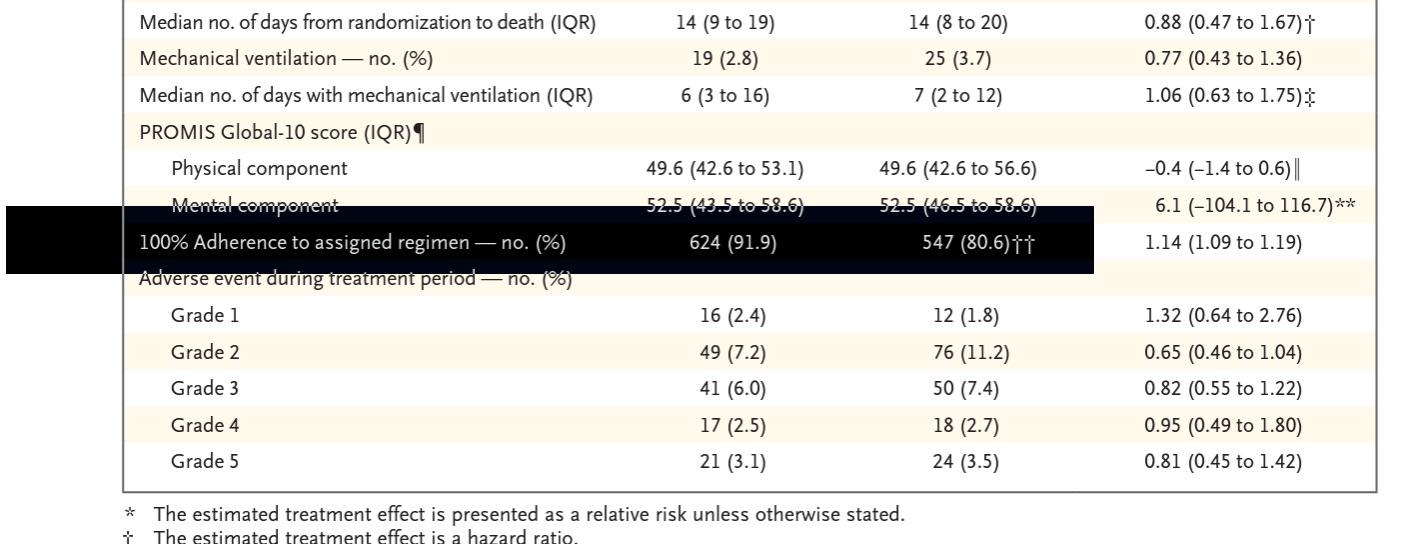
Their data show the number of people who stayed 100% on protocol. Guess which group didn’t stay on protocol?

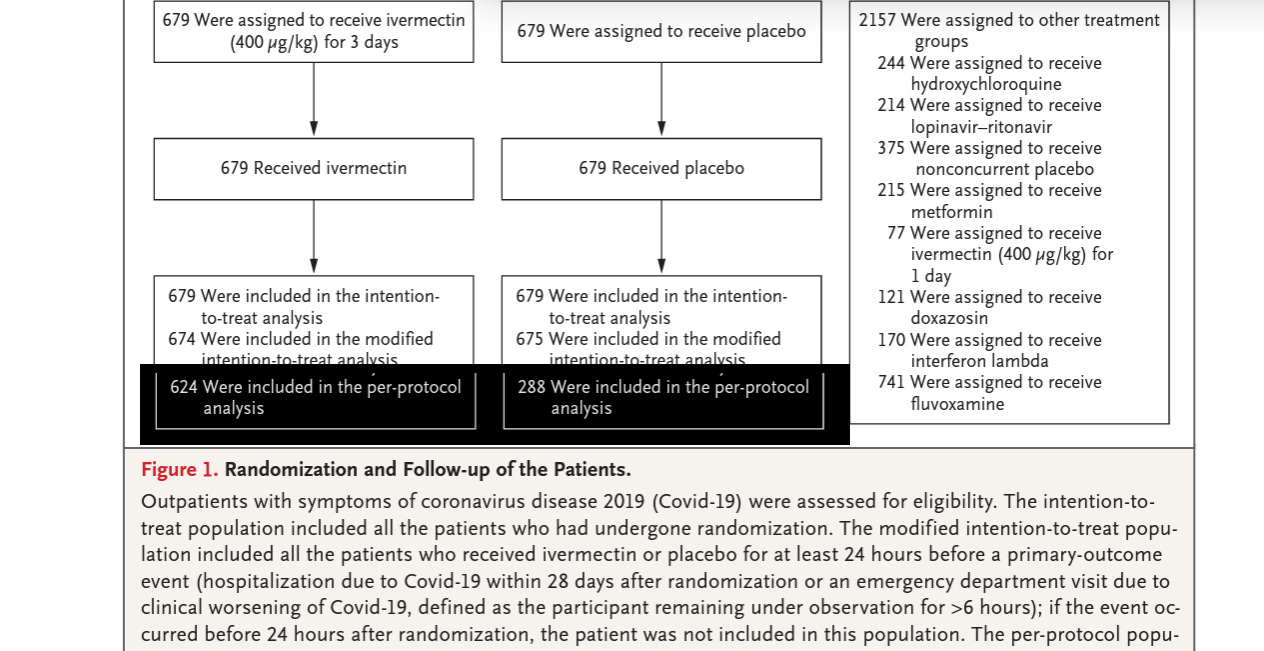
This:

Is not correct.

The study left out people who failed to adhere to the placebo treatment.

Check this out:

Both groups started with 679 people.

The Ivermectin group had 624 included after attrition.

For the per-protocol analysis, only 288 on placebo were still in the study.

Of the people who adhered to placebo with no benefit, we can expect they would have had more severe COVID-19 symptoms and sought treatment.

Note the patient attrition rate is far less in the Ivermectin group in the “100% Adherence to the assigned regime” analysis, but still biased toward people leaving the study to seek other treatment.

It’s a huge problem if more of one group is dropped from the study due to events that are clearly related to the outcomes measured.

The sickest people in the both groups would have started doing anything other than the pills they were given. The placebo group received visually identical pills in the identical packaging as the active drug, and they left in droves, whereas for the Ivermectin group, they clearly felt well enough to stay on the protocol.

Anyone can see that.

The paper is not to be taken seriously, and should be eliminated from future meta-analyses due to this obvious sign of bias.

__________________

Also see:

JAMA Ignores Peer-Reviewed Evidence & Publishes Yet Another Misleading, Underpowered IVM Study and WSJ & NY Times Mislead Public on New Ivermectin Study.

FLCCC Doctors: “We treat patients, not p-values.”

__________________

**Comment**

Dr. Kory’s outline of what needs to happen would also help those suffering in Lymeland as the very things affecting the ability to get effective COVID treatments are also affecking those with Lyme/MSIDS. We need a CDC/NIH/FDA walkaway movement.

Both of these studies serve as current reminders of the types of shenanigans that have been going on in Lymeland for over 40 years.  Similarly to statistics, you can get research to say exactly what you want it to say by design.

In turn this rigged research has been used globally against patients, similarly to how extended antibiotic treatment has been denied Lyme/MSIDS patients due to study design.  An example:

NY AG Letitia James’ “cease and desist” letters to doctors prescribing ivermectin are riddled with falsehoods. 

Excerpt:

The “deceptive acts” to which the AG referred were outlined in the letter. (Note: All of the following noted by the AG are demonstrably FALSE, as evidenced by peer-reviewed science.)

FALSEHOOD #1: Providers of ivermectin are misleading consumers as to the effectiveness of ivermectin for COVID-19.

FACT: The effectiveness of ivermectin has been proven in over 70 scientific trials.

FALSEHOOD #2: Adverse effects associated with ivermectin are increasing, as shown in a rise in calls to poison control centers reporting overdoses and adverse effects.

FACT: After the New York Times reported that the Mississippi State Department of Health attributed 70% of its calls to ivermectin adverse events, they were forced to retract the figures. In fact, the ivermectin-related calls to the Mississippi State Department of Health represented only 2% of the total calls; and that 70% of those calls (1.4% of all calls) were from people who ingested veterinary grade ivermectin. (NOTE: The FLCCC has consistently advised against the use of animal-grade ivermectin.)

FALSEHOOD #3: The National Institutes of Health has determined that there is insufficient evidence to recommend ivermectin for COVID-19

FACT: The NIH has a “neutral” stance on IVM use.

The “deceptive acts” these doctors were accused of providing were, in actuality, courageous acts of life-saving compassion. Robust epidemiological studies from around the world validate the science in the real world and point to the effectiveness of preventive protocols based around ivermectin. But the well-coordinated and well-funded media campaign against ivermectin has strangled true science and caused the senseless deaths of hundreds of thousands.

For more:

News Cycle to Shock and Distract You From What’s Important: FDA Decision on COVID Shots For Kids & The Great Reset

https://rumble.com/v136kzm-the-ultimate-goal-of-the-great-reset-is-one-world-government-dr.-reiner-fue  Video Here (Approx. 2 Min)  May 1, 2022

The Ultimate Goal of The Great Reset Is ‘One World Government’ – Dr. Reiner Fuellmich

Dr. Reiner Fuellmich describes the ultimate goal of the Great Reset is “keeping us in panic mode for as long as it takes to install this one world government”. This will be achieved through the United Nations, under complete control by the World Economic Forum, a creation of Klaus Schwab. Feullmich argues that causing “as much chaos as possible” is part of the method to influence mass obedience.

For more:

____________________

https://popularrationalism.substack.com/p/the-news-cycles-to-shock-and-distract

The News Cycles to Shock and Distract You. Why You Need to Stay Hyperfocused on FDA for One Month. This Month.

As FDA works with Pfizer/Moderna to Find Excuses to Approve of COVID-19 Vaccines for Kids Under 5 (An Impossible Task) we are about to be peppered with distracting news stories designed to distract

One month ago, I emailed close associates inviting them to join an FDA Watchdog Group bent on keeping a laser-beam-like focus on the FDA as it moves toward reconsidering approval of COVID-19 vaccines for kids under 5 years of age.

I predicted that the news cycles would be peppered with jaw-dropping distracting headlines.

Today’s is “In a stunning breach of confidentiality and secrecy, Politico obtained what it calls a draft of a majority opinion that would strike down Roe v. Wade” (CNN).

IMPORTANT CONNECTION NEXT PARAGRAPH

Don’t be distracted. Stay on focus: The move to approve COVID-19 vaccines for kids under 5 is necessary for the states to begin to mandate COVID-19 vaccines, and then all vaccines, for all children under the age of 5 – before parents begin comparing notes on vaccines for school entry.

FDA postponed the decision given insufficient (unconvincing) data. But there cannot be any convincing new data that shows individual benefit for kids under five from the COVID-19 vaccines… they do not stop transmission; under any reality-based analysis, vaccines do not stop COVID-19; kids do not get COVID-19 or die from COVID-19.

What type of evidence of individual benefit could Pfizer/Moderna/FDA cook up in two months’ time?
  • Will they show that individual children have decreased risk of death from COVID-19?
    • No, the vaccines being studied are targeting an extinct virus.
  • Will they show that Will they show that individual children have decreased risk of hospitalization from COVID-19?
    • No.
  • Will they show decreased transmission in this population?
    • No, Dr. Fantini’s results show INCREASED transmission due to vaccination against Wuhan-1 since the emergence of Beta, Gamma, Delta and Omicron.

The FDA will be able show data on antibodies. Period. Antibodies against an extinct variant, Wuhan-1.

  • The participants in the study will likely not be screened for prior immunity to COVID-19 from either natural infection, or from prior infection to viruses that confer cross-protection.
  • And the study will be adjusted for outcomes-related confounders, if necessary (p-hacking).
And we know that antibodies do not tell the full story.

Students in my Immunology course have created a visually stunning, fact-filled fact sheet showing that antibodies do not tell the entire story of our immune response to COVID-19 or to COVID-19 vaccines.

To sign up to receive information about the Fact Sheet, and how to interact with IPAK-EDU to have information sheets made for your organization, email info@ipak-edu.org subject line “Fact Sheet Zoom Meeting”.

I’m still unable to Tweet due to my sharing of Dr. Fantini’s results. That information is too dangerous. So please share this post everywhere on social media and have an impact.

_________________

The Discussion section of Fantini’s work states:

“Given the global scale and magnitude of the ongoing pandemic, including case reports of reinfection, it is clear that viral evolution will continue.”

Sign and send a petition to your governor to protect children from federal agencies & catastrophic COVID shots.

For more:

10 Signs of Recent Progress in the Lyme Disease World

https://www.lymedisease.org/10-signs-lyme-disease-progress/

10 signs of recent progress in the Lyme disease world

By Kris Newby, Invisible International

It’s easy to dwell on the negative with Lyme disease. Forty-seven years after discovery of the first case cluster in Lyme, Connecticut, there are still no reliable tests or effective vaccines on the market. Among those patients who are treated promptly, about a third go on to suffer from persistent symptoms.

But it’s important to keep things in perspective. Incremental progress is being made, albeit slowly. There’s a growing acknowledgment of the magnitude of the Lyme problem in the medical system, the government, and the media.

New diagnostics, vaccines, and therapeutics are finally working their way out of basic research labs and into clinical validation studies. Invisible’s mission is to accelerate progress on all these fronts.

Here are 10 signs of progress for the Lyme disease community:

The CDC ups annual Lyme disease cases to 476,000

After analyzing medical insurance claims data on Lyme disease in 2021, the U.S. Centers for Disease Control and Prevention upped their public-facing estimate of 300,000 annual cases to 476,000 per year. “Our results underscore the need for accurate diagnosis and improved prevention,” says the CDC. This updated estimate provides a larger “market size” that may incentivize commercial interests to develop better diagnostics, vaccines, and therapeutics.

New WHO ICD-11 Lyme disease diagnostics codes

The World Health Organization (WHO) added 15 new medical diagnostic codes for Lyme disease (aka borreliosis) complications, effective on January 1, 2022. Over time, these codes will provide patients with more avenues for medical insurance reimbursement and will enable researchers to better track and analyze Lyme disease complications, treatments, and outcomes. On the international front, the European Union is now requiring mandatory reporting of neuroborreliosis, a move that will help with research funding, prevention, and disease tracking.

More patient participation in the U.S. research agenda

Patients’ voices are starting to be heard. Since 2017, patient advocates in the HHS Tick-Borne Disease Working Group  have been effective in educating Congress and researchers on the urgent need for better diagnostics and treatments.

MyLymeData, a patient information database managed by LymeDisease.org, has quantified time-to-diagnosis, common symptoms, and treatment outcomes, providing a big-data window into the needs of patients.

Lastly, the Center for Lyme Action, founded in 2019, organized educational sessions within the US federal government to facilitate the passage of a new appropriations bill that nearly doubled the federal funding for Lyme disease to $108M in FY21.

Strong evidence of active Lyme infections after treatment

A recent spate of research studies show that Lyme disease symptoms can persist after recommended treatment protocols, challenging the widely held belief that Lyme disease can always be cured with a short course of antibiotics.

Acknowledgement that chronic Lyme is a real medical condition is the first step in justifying the development of more effective treatments for both early and late stages of the disease. A summary of this evidence can be found in here.

Recognition of the dangers of mixed tick-borne infections

When several university labs started gene sequencing and cataloging all the disease-causing microbes inside ticks, they discovered that polymicrobial infections transmitted through a single tick bite are far more common than previously thought.

In the U.S., there are at least 18 disease-causing bacteria and viruses carried by ticks. And new studies have found that the standard U.S. Lyme testing doesn’t detect the newly recognized Lyme-like bacterial species spreading in the West and Midwest.

This new information is another reason to design better screening tests and treatment guidelines for mixed tick-borne diseases. Read more here, here, and here.

Invisible International’s free medical ed courses on tick/vector-borne diseases

Invisible International’s physician education platform is the world’s first accredited curriculum focused on tick- and vector-borne diseases. These virtual courses are available at no cost for medical professionals and patients. Taught by leading experts in tick/vector-borne diseases, this platform is accelerating the movement of the latest diagnostics and treatment advice to the front lines of medical care.

New courses are added monthly and are accredited by the American Academy of Family Physicians for AMA credit. This effort is funded by the Montecalvo Family Foundation. To help Invisible integrate these courses into medical school curriculums across the U.S. and abroad, click here.

New therapeutic/treatment options on the horizon

A relatively new technology called “high throughput drug screening” enables researchers to place Lyme bacteria in an array of tiny wells and expose them to thousands of FDA-approved chemical compounds and drugs to see which ones are best at killing the microbes. The best and safest drug candidates are then retested in live mice, and, eventually, in humans. This process saves the time and money associated with large human clinical trials and speeds up the regulatory approval process.

The LymeX Diagnostics Challenge

The weak link in reducing the public health burden of tick-borne illnesses is the lack of fast, cheap, and accurate diagnostics. Lyme treatment is often delayed because the screening tests aren’t reliable in the first month after infection and not everyone produces or notices a bull’s-eye rash.

In the later stages of the disease, antibody testing can be unreliable in the sickest patients, those whose antibody production may be hobbled by concurrent infections or a weak immune system.

LymeX, a public-private partnership, will be offering prizes to incentivize the development of better Lyme diagnostics. The effort is funded with $25 million from the Steven & Alexandra Cohen Foundation and co-managed with the U.S. Department of Health and Human Services (HHS).

Invisible is joining the effort to support new diagnostic development by organizing a “Tick-borne Illness Diagnostics Development Incubator” in parallel, a yearlong collaborative forum designed to help bring these diagnostics solutions to the market faster. This effort is funded by the Lovell Family Healthcare Foundation.

Studies revealing the suicide/mental health risks of Lyme and co-infections

In a large retrospective study of nearly 7 million subjects, U.S. and Danish researchers report that patients who received a hospital diagnosis of Lyme disease—inpatient, outpatient, or at the ER—had a 28 percent higher rate of mental disorders and were twice as likely to have attempted suicide post-infection, compared to individuals without the diagnosis.

Studies like these show that undertreated Lyme disease can lead to serious mental illness, and that it should be a differential diagnosis for certain patients with sudden-onset depression, suicidal thoughts, and other mental disorders. Read more here, here, and here.

A breakthrough in public awareness of the tick-borne disease problem

A growing number of mainstream journalists, writers, and professionals have gone public with their personal stories on the emotional, financial, and societal toll of tick-borne illnesses. This is an essential step in mitigating the social stigma, medical gaslighting, and myth that Lyme disease is easy to diagnose, treat, and cure.

Notable new additions to this genre include “Chronic,” “The Invisible Kingdom,” “The Deep Places,” “What Lurks in the Woods,” and “Bitten” (my book). Invisible’s “Storytelling for Change” initiative aims to continue this momentum with a team of clinicians, researchers, and writers collaborating to produce mass media stories that explain emerging science and promote understanding of the suffering and social injustices laid on families dealing with invisible illness.

Kris Newby is Communications Director of Invisible International, a 501(c)(3) nonprofit foundation dedicated to reducing suffering from invisible illnesses.

__________________

**Comment**

Normally a positive, forward looking person – I would like to offer the following in response to these “signs of progress”.  BTW: this is not being negative, it’s being realistic.

  1. The ONLY reason the CDC ups Lyme numbers is due to ‘vaccine’ development which is a huge cash cow for them as they own patents on many vaccines. When they bring a disease into the lime-light (pun intended) it’s always for a monetary reason – not because they are concerned about patients. The CDC lies, and releases and withholds data for its own vested purposes. Even mainstream doctors state the CDC has abandoned science & public health is broken. In a huge overreach of power, a FOIA request showed the CDC tracked millions of phones (using tax-payer money) to see if Americans followed COVID lockdown orders, but also for non-COVID related programs. CDC twisted logic reiterates travel mask advice despite a court ruling and its own data. (Hopefully it is abundantly clear the CDC is not our friend)
  2. The WHO is also completely corrupt They too only advance certain diseases due to financial interests.
    1. Please read this article on how Gates has been buying the controlling interest in the WHO for over a decade through the Gates Foundation, as well as other organizations and enterprises he funds. His new book outlines the need for a firefighter-like pandemic task force named “global epidemic response and mobilization,” or GERM, that would be a part of the WHO and could stop outbreaks of disease from spreading.  According to Keean Bexte, writing for The Counter Signal reportsBill Gates has announced the creation of a pandemic “GERM” team that will monitor sovereign nations and decide when they need to suspend people’s civil liberties, force them to wear masks, and close borders.  If you believe for one second that the WHO is concerned about Lyme/MSIDS patients, you are sadly mistaken.  Further, present U.S. health care is completely controlled by by The Cares Act which is behind the Fauci Death Protocol currently being used in hospitals. Many falsely blame capitalism, but it is a form of facism called corporatism – when corporations and government merge. Our government no longer watch dogs anything. They are players – actively pursuing business ventures and making money off of severely sick people. This leaked video from “Breaking Points with Krystal and Saagar” in March, 2022, shows a Representative explaining that the most powerful committees in Congress must be bought at a price of $1 million or more. The money comes from lobbyists who pay the price in exchange for political favors.  National media is completely aware of this and both political parties are guilty of doing it. Go here for more.
  3. While patient participation in research can be helpful, it will never be taken seriously by the research community & therefore the medical profession.  As it stands, case studies aren’t taken seriously either, which is one of the main reasons why Lymeland continues to stagnate.  Fauci, emperor of NIAID and the coffer- keeper of government grant money, only acknowledges large, randomized, controlled trials (RCTs) – except when it suits his personal purpose.  What he says is the rule of law and scientists know they must take a knee to the emperor to get precious grant money.  Fauci sits on the Leadership Council of the Bill and Melinda Gates’ Global Vaccine Action Plan board which is a collaboration between WHO, UNICEF, NIAID, and the Gates Foundation.
  4. There has been strong evidence of borrelia (and many other pathogens) persistence for decades.  It hasn’t mattered.  I’m currently reading “Ending Plague, A Scholar’s Obligation in an Age of Corruption.” In it, scientist Francis Ruscetti states the government will go to any length to defend one of their own.  If they defended Gallo’s completely unethical behavior during the AIDS debacle, they will defend Fauci to the bitter end.  Fauci et al. do not believe or want borrelia persistence, therefore it shall never be – despite the evidence.  We must work outside the system to get help we desperately need.  I don’t believe this will ever change.
  5. Despite some recognition of polymicrobial infections (Lyme and company), nothing has changed.  “Official” testing continues to abysmally look for one organism and official treatment only treats one organism for a very short time.  Further, due to ‘vaccine’ development, which is the most lucrative scientific venture, therefore highly sought after and valued above all else, current research will continue to fixate on the one germ, one cure and will continue to lead the charge despite new findings.  If this officially changes I will eat my hat.
  6. Free medical ed courses for Lyme/MSIDS are not new and Invisible International is not the only place offering accredited curriculum or CME.  The fact Invisible International is unaware of this demonstrates it is not well known or used yet. Free Lyme CMEs have been in the works for a while now.  Results remain unknown at this point. The AMA, FDA and other large, professional medical and public heath groups/agencies are bullies and are completely in bed with Big Pharma.  They have a long history of monopolizing medicine and shouting down dissenters.
  7. From where I sit, the only new therapies and treatments are coming from LLMD’s and researchers who are working independently and are funded independently. This is an important distinction.  The government has been using Lyme/MSIDS patients for far too long as cogs to raise money for government research that only cripples them.  We will be far better off giving our precious pennies to independent groups with open minds and ethics.  Doing research with the government is truly crawling in bed with the enemy – and then paying them for it!
  8. Testing has been a problem forever and will continue to be a problem for multiple reasons. The first one of course is that antibodies are often not produced at various stages of the illness (or in sufficient amounts to be picked up). The second one is the arbitrary cut-off points and the fact ‘officials’ took out the most specific band in testing due to ‘vaccine’ development. The third would be the polymicrobial nature of the disease, not to mention the fact the organisms are pleomorphic and one step ahead of testing and the immunity system at all points in the game.  Please note that LymeX, is a public-private partnership, that will be offering prizes to incentivize finding better tests.  Here’s the problem: prizes don’t mean much when your discovery ends your career, which is exactly what happens to those who cross emperor Fauci. Just ask Judy Mikovitz and many, many others.
  9. While studies showing higher risk of suicide and mental health risks of Lyme/MSIDS certainly helps educate LLMD’s and patients – please remember these same patients are being gaslit everyday by doctors and health professionals. They are still being told it’s all in their head.
  10. While there is greater public awareness, the personal stories aren’t changing science and the medical profession’s attitudes and beliefs about Lyme/MSIDS. While these stories are crucial for patients I don’t see them impacting the ‘powers that be.’

I end this on a positive note: if you want true lasting help, face these facts and go around the system to get help from a Lyme literate doctor.  In my experience your best help will come from finding a local Lyme support group in your area.  These folks are the boots on the ground and will be familiar with doctors in your area.  Finding an experienced doctor is one of the first steps.  You may need more than one doctor, and it isn’t uncommon to change doctors somewhere along the line.  There’s a ton to know and a ton to learn.  Put one foot in front of the other and keep on going.  Knowledge accrues so start learning today what you can and most importantly, have grace for yourself.  This is a tough road.