https://www.zerohedge.com/political/supreme-court-blocks-bidens-osha-vaxx-mandate

Supreme Court Blocks Biden’s OSHA Vaxx Mandate

by Tyler Durden
Friday, Jan 14, 2022 –

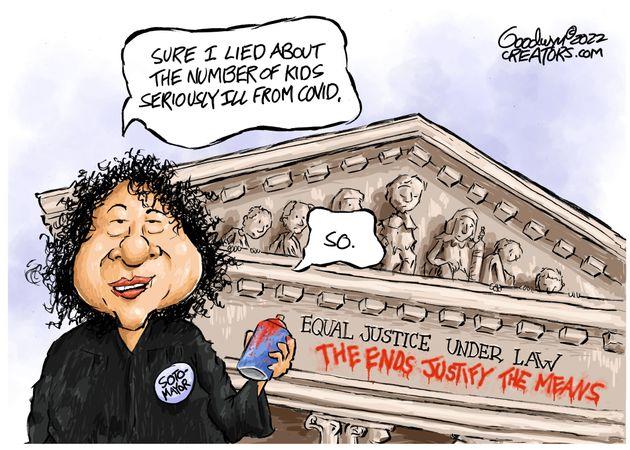
Despite the misinformation spewed forth by Justice Sotomayor, The US Supreme Court has blocked the Biden administration’s vaccine-or-test rule for US businesses, but allows vaccine mandate for most health care workers.
The National Federation of Independent Business (NFIB) argue against the Department of Labor, in the Court’s first hearing, that:

“OSHA’s sweeping regulatory dictate,” will “irreparably injure the very businesses that Americans have counted on to widely distribute COVID-19 vaccines and protective equipment to save lives—and to keep them fed, clothed, and sustained during this now two-year-long pandemic.”

The Occupational Safety and Health Administration (OSHA) rule would have required 80 million workers to get shots or periodic tests.

The OSHA ruling vote was 6-3 with Breyer, Sotomayor, and Kagan in dissent.  (See link for article)

_________________

Important points:

  • The court allowed requiring shots for workers in nursing homes, hospitals and other facilities that receive Medicare and Medicaid payments from the federal government.  (Just another reason in a very long line showing that getting government money always has strings attached.)
  • The vaccine mandate for healthcare workers vote was 5-4 with Thomas, Alito, Gorsuch, and Barrett in dissent, which means Roberts and Kavanaugh joined liberal justices in allowing the HHS mandate on healthcare workers to stand.
  • Meanwhile, nobody seems to care that these injections have caused more adverse reactions & death than any other vaccine in the history of VAERS:  https://madisonarealymesupportgroup.com/2020/12/21/warning-3150-injuries-in-1st-week-of-covid-vaccines-among-american-healthcare-workers-pregnant-women-included/  VAERS data and mounting list of adverse reactions & death in link
  • Go here for a news report explaining it.

_____________________

https://www.medpagetoday.com/infectiousdisease/covid19/96638?xid=nl_mpt_DHE_2022-01-13

Most Americans Will Get COVID Eventually, Says Fauci

— But chances of getting sick are “very, very low” if you’re vaccinated and boosted
A photo of young school children in a classroom testing themselves for COVID

WASHINGTON — Sooner or later, most Americans will wind up getting COVID-19, although it will likely be pretty mild for those who are vaccinated and boosted, a Biden administration official said Wednesday.

During a press briefing held by the White House COVID-19 Response Team, MedPage Today asked members of the team to elaborate on the remark that “most people are going to get COVID” made by Acting FDA Commissioner Janet Woodcock, MD, during a Senate hearing Tuesday. (See link for article)

__________________

**Comment**

Fauci finally tells the truth: COVID will NOT be eradicated and it is highly likely everyone will get it, like every other coronavirus, flu, and cold we haven’t eradicated. Logic would now follow that natural immunity would be preferred, yet our corrupt public health authorities who own the patent on the spike protein and on the injections have censored this well-known and accepted scientific fact and only push the lucrative, dangerous shots which have caused more damage than any other “vaccine” in the history of VAERS.

Logic would also follow that effective treatments are the best answer to something that is not going to be eradicated, yet corrupt public health officials have conveniently changed the definition as to what constitutes a “vaccine” to now include non-sterilizing, gene-therapy injections. With their tyrannical ‘top down’ approach, public health and mainstream medicine are in lockstep and doctors who dare to defy the accepted narrative are hunted down and persecuted.

What Fauci continues to spin; however, is that these fast-tracked, experimental injections which are NOT sterilizing, and don’t stop infection or transmission, are somehow protective against severe illness and death.  Boosters are quickly ineffective as well.

Further, another ‘slight of hand’ has ignored ‘absolute risk’ in calculating injection efficacy.  When it is taken into account, ALL of the shots are approximately 1% effective:  https://madisonarealymesupportgroup.com/2021/08/24/first-signs-of-what-scientists-fear-most-about-covid-jabs-german-physicians-examine-covid-vaxxed-blood-its-not-good/  Excerpt: 

In a July 1, 2021, commentary in The Lancet Microbe,3 Piero Olliaro, Els Torreele and Michel Vaillant also argue for the use of absolute risk reduction when discussing vaccine efficacy with the public. They too went through the calculations, coming up with the following:

  • Pfizer/BioNTech — Relative risk reduction: 95%. Absolute risk reduction: 0.84%
  • Moderna — Relative risk reduction: 94%. Absolute risk reduction: 1.2%
  • Gamaleya (Sputnic V) — Relative risk reduction: 91%. Absolute risk reduction: 0.93%
  • Johnson & Johnson — Relative risk reduction: 67%. Absolute risk reduction: 1.2%
  • AstraZeneca/Oxford — Relative risk reduction: 67%. Absolute risk reduction: 1.3%
And Fauci will never admit in 1,000 years that horrific contaminants have been discovered by experts across the glob.

________________

https://articles.mercola.com/sites/articles/archive/2022/01/14/covid-pcr-tests-dont-work

Bombshell Admission — The COVID Tests Don’t Work

Jan. 14, 2022

Analysis by Dr. Joseph Mercola

Story at-a-glance 

  • Since the beginning of the pandemic, experts have warned that the PCR test is not a valid diagnostic and produces far too many false positives, as it can pick up on “dead,” nonreplicating viral debris
  • The U.S. Centers for Disease Control and Prevention now admits the PCR test can remain positive for up to 12 weeks after infection. For this reason, they say most people don’t need to retest negative before ending their quarantine
  • The CDC also admits the PCR cannot identify active infection or measure contagiousness
  • People who are double-jabbed or unvaccinated and test positive for SARS-CoV-2, or have known exposure, but remain asymptomatic, now only need to isolate for five days rather than 10, but should wear a mask for another five days when at work or in public. People who are triple-jabbed do not need to isolate after exposure, but should wear a mask for 10 days
  • Health care workers who test positive for COVID but remain asymptomatic can return to work after seven days with a negative test, but isolation time can be cut to five days if there are staffing shortages

From the earliest days of the COVID pandemic, the PCR test has been a source of unrelenting controversy, with experts repeatedly pointing out that it’s not a valid diagnostic and produces inordinate amounts of false positives.

Importantly, a PCR test cannot distinguish between “live” viruses and inactive (noninfectious) viral particles. This is why it cannot be used as a diagnostic tool. As explained by Dr. Lee Merritt in her August 2020 Doctors for Disaster Preparedness1 lecture, media and public health officials appear to have purposefully conflated “cases” or positive tests with the actual illness in order to create the appearance of a pandemic.

Furthermore, a PCR test cannot confirm that SARS-CoV-2 is the causative agent for clinical symptoms as the test cannot rule out diseases caused by other bacterial or viral pathogens.

Almost universally, health authorities have also instructed labs to use excessively high cycle thresholds (CTs) — i.e., the number of amplification cycles used to detect RNA particles — thereby ensuring a maximum of false positives.

From the start, experts noted that a CT over 35 is scientifically unjustifiable,2,3,4 yet the U.S. Food and Drug Administration and the U.S. Centers for Disease Control and Prevention recommended running PCR tests at a CT of 40,5 and the World Health Organization recommended a CT of 45.

The pandemic of false positives was then used by world governments to implement pandemic countermeasures that have destroyed the global economy, ruined countless lives, decimated the education of an entire generation and stripped us of basic human rights and freedoms.

What the CDC’s belated admission means is that, for the past two years, Americans have unnecessarily wasted time in self-isolation — perhaps weeks — waiting for a negative test.

Time and again, the goal post for ending the pandemic theatre has been moved, and the justifications for continuing the life-destroying countermeasures have become increasingly laughable. The fearmongering over Omicron, for example, makes no rational sense based on the data available, which shows the variant is among the mildest so far, and far less likely to infect and damage the lungs.6

In the last days of December 2021, the U.S. Centers for Disease Control and Prevention issued yet another illogical protocol change.7 People who test positive for SARS-CoV-2, or have known exposure, but remain asymptomatic, now only need to isolate for five days rather than the previous 10, but should wear a mask for another five days when at work or in public. Also, they don’t need to get retested at the end of their quarantine. The stated reason? Because:

  1. The majority of viral transmission (85% to 90%8) occurs in the first day or two before symptom onset, and two to three days after symptom onset9
  2. The PCR test can remain positive for up to 12 weeks after you’ve recovered from the infection10,11

How is it that the CDC didn’t realize until now that the PCR test was picking up dead viral debris for three months after infection? The facts that the test, a) was far too sensitive, and b) couldn’t identify active infection, were criticisms from the start. What the CDC’s belated admission means is that, for the past two years, Americans have unnecessarily wasted time in self-isolation — perhaps weeks — waiting for a negative test.

In a December 30, 2021, appearance on MSNBC, Dr. Anthony Fauci responded to questions about the updated CDC guidance. CDC director Rochelle Walensky also tried to make sense of the new guidance in a December 29, 2021, ABC News interview (see videos above).12

Neither of them offered any explanation as for why the CDC didn’t change the rules sooner, and only now decided that keeping noninfectious people in isolation for days and weeks on end might not be so good after all.

Walensky did make a rather telling comment on CNN, though, when asked about the reasoning behind the shortened isolation guidance. “It really had a lot to do with what we thought people would be able to tolerate,” she said.13 Some have understandably translated that as “how much tyranny we thought people would be able to tolerate.”14

Differing Rules for Health Care Workers

The CDC has not given up on making the guidance as confusing as possible though. December 23, 2021, they also updated guidance for health care workers,15 stating that “Health care workers with COVID-19 who are asymptomatic can return to work after seven days with a negative test, and that isolation time can be cut further if there are staffing shortages.”16

In his MSNBC interview, Fauci was asked why health care workers are being treated differently, having to isolate for seven days rather than five, and still have to get a negative test, when the test can falsely remain positive for up to 12 weeks? What data supports this, and is it publicly available?

According to Fauci, the data to support this difference “is internal to the CDC,” but really, there’s “no specific data” to back it up, he adds. The CDC merely made “a judgment call.”

Double-Jabbed Treated the Same as Unvaccinated

The CDC’s updated guidance also puts those who have received two doses of the COVID shot in the same category as the unvaccinated, so when it comes to isolating after exposure, they have to follow the same rules, whereas those who have received a booster shot follow a different set of guidelines. As explained by the CDC:17

“For people who are unvaccinated or are more than six months out from their second mRNA dose (or more than 2 months after the J&J vaccine) and not yet boosted, CDC now recommends quarantine for 5 days followed by strict mask use for an additional 5 days.

Alternatively, if a 5-day quarantine is not feasible, it is imperative that an exposed person wear a well-fitting mask at all times when around others for 10 days after exposure. Individuals who have received their booster shot do not need to quarantine following an exposure, but should wear a mask for 10 days after the exposure.

For all those exposed, best practice would also include a test for SARS-CoV-2 at day 5 after exposure. If symptoms occur, individuals should immediately quarantine until a negative test confirms symptoms are not attributable to COVID-19.”

Fauci defended the decision to treat the double-jabbed as if they’re unvaccinated saying that those who have received a booster shot have far greater protection against the Omicron variant, compared to those who have only received one or two doses.

“When you’re infected, you’re infected,” Fauci said, and it doesn’t matter whether you’re vaccinated or not. The viral load is the same, so the risk of spreading the infection is the same. Those who have been boosted are less likely to be infected or carry a large viral load, hence they don’t need to isolate.

PCR Cannot Tell You Anything About Contagiousness

Fauci was also asked about how one can measure contagiousness. If the PCR can register positive for 12 weeks after an infection, it can’t be a reliable indicator of infectiousness. This was precisely the point that Mullis, inventor of the PCR test, attempted to make in the video at the top with respect to PCR and HIV.

So, how can we tell if we’re infectious or not? Fauci confirmed that the PCR can only tell you there’s a presence or absence of viral fragments, not whether it’s an active infection, or whether you’re actually infectious. He did not, however, provide an answer to the question as to how one can measure contagiousness.

Rapid Test Doesn’t Pick Up Omicron

Yet another confounding factor in this mess is that the rapid test apparently doesn’t pick up Omicron very well.18 Your viral load needs to be very high at the time of testing in order for the rapid test to recognize it.

This admission came within days of president Biden’s announcement that the federal government will distribute half a billion free rapid tests to homes around the country in 2022.19

It seems like a waste of resources, seeing how Omicron is starting to take over, but who knows, maybe it will pick up the common cold instead, allowing the “case” count to remain high enough to keep the charade going.

What’s the Real Death Count?

The CDC’s belated admission that the PCR test can’t identify active infection raises another question: What does this mean for those who died with a positive test? Did they actually have an active infection? If not, should they have been designated as COVID deaths?

The obvious answer to the last two questions is, of course, no. The vast majority were likely false positives, and the real death toll from COVID-19 considerably lower than we’re led to believe. The CDC undoubtedly knew this all along, seeing how they’ve been relentlessly criticized for their recommendation to run the PCR at a CT of 40. They’re trying to pretend that they just realized this, but that’s simply not believable.

My daily newsletter is still free and content will be released on Mercola.com before anywhere else. After 48 hours the articles will be transferred to my Censored Library on Substack. To view any missed content, a private membership is available for a very minimal amount with a portion of proceeds going toward our health partners who are helping in the fight to protect our freedom of speech and your right to take control of your health:  https://www.mercola.com/censored-library.htm  You can access the article and videos in this link for a fee.

___________________

Lastly, both Fauci and Walensky lied under oath regarding VAERS COVID injection deaths.

As of Jan. 7, 2022 there have been nearly 22,000 reported deaths after the jabs.

JP tells the news best:

http://

Why You Should Listen

In this episode, you will learn about chronic UTIs and Interstitial Cystitis.

Watch The Show

Listen To The Show

About My Guest

My guest for this episode is Ruth Kriz. Utilizing her functional medicine background as well as experience in microbiology and teaching pharmacology, Ruth Kriz, MSN, APRN has spent the majority of her professional career as a Nurse Practitioner working with Chronic UTI and Interstitial Cystitis patients. Her practice expanded to patients from almost all the states in the US as well as from 35 countries who came to her seeking answers beyond symptom management. Through molecular testing, an understanding of the genetics common to these patients, and an understanding of how this contributes to chronic infection and biofilms, she has been able to successfully treat this population. These factors have broad implications for other chronic infections (sinus, prostate, ear infections, wounds, etc.) as well as fibromyalgia, cardiovascular disease, and other conditions in which biofilms are an important contributor. She has closed her medical practice, but she has reinvented as a consultant to help practitioners learn how to utilize her approach for curing these patients.

Key Takeaways

  • How do chronic UTIs evolve into Interstitial Cystitis (IC) over time?
  • What are the primary contributors to chronic UTIs and IC?
  • How is the potential for infection best explored in these conditions?
  • What types of microbes are commonly found in these patients?
  • Do chronic Lyme disease and mold illness play a role in these conditions?
  • What are the key genetic contributors?
  • What role does ammonia play in creating the right environment for microbial overgrowth?
  • How might Nrf2 support be helpful in treating these conditions?
  • What is the role of hypercoagulation and biofilm?
  • How does vitamin D impact these conditions?
  • Is MCAS involved in chronic UTIs and IC?
  • Are oxalates a primary contributor?
  • What are some of the treatment options to explore?
  • Why is detoxification support important?
  • What is the prognosis for those dealing with chronic UTIs and IC?

Connect With My Guest

https://RuthKriz.com

See link for transcript

For more:

https://www.redvoicemedia.com/2022/01/ask-dr-jane-worldwide-pcr-fraud-blood-cell-death-staying-healthy/  Video Here (Approx. 13 Min)

Ask Dr. Jane

The Stew Peters Show

Jan. 12, 2022

Great, practical information within this video.  Please watch.

Summary:

  • Starting at 1:00 Dr. Jane discusses “chain of custody,” or the process and verification of how an object moves from point A to point B. There are special procedures for moving samples to and from a lab for screening. COVID injection vials also have “chain of custody” where they are signed for and carefully followed.
  • At 2:20 Dr. Ruby discusses that in her experience those getting COVID again (which again, can’t be verified due to the PCR fraud occurring and the inability to know if something truly is COVID) have had experimental monoclonal antibodies or the jab.  Getting the antibodies is like renting an army for a day. They come in, clean house, but then go away.  On the other-hand, the soldiers in your immune system stay around, continuing to clean house as needed.  Those getting the jab are catching every little cold bug or flu that’s going around.
  • at 4:30 Dr. Ruby discusses the doctors looking at “vaxxed” blood continue to follow up with patients, and at 5:04, they show a slide with strange, irregular, compact blood vessels.  The patients are also doing worse clinically – struggling with weakness, fatigue, severe illnesses, autoimmunity, and even hospitalizations. Doctors looking at vial ingredients have revealed horrific findings.
  • at 6:45, they discuss the fact that the Novavax shot still injects you with the toxic, bioweapon spike protein by the billions, you just get it differently.  They take mRNA designed to force the development of toxic, foreign spikes in your body and they put it in a baculovirus (insect pathogenic virus) which infects moths but not humans per say. They then transport the mRNA to the moth, which then makes billions of spikes which the company then extracts and puts on a graphene sheet and then fills a vial with adjuvant.  All of the COVID jabs are dangerous.  There isn’t one that’s safe, and none of them are “vaccines.”
  • At 8:30 Dr. Ruby discusses nebulized hydrogen peroxide.
  • “Viruses burn down, not up.”  ~ Dr. Ruby  This simply means that viruses grow weaker over time, not stronger.
  • We are in a cold and flu season.  This is nothing new, but it will all be labeled COVID.
  • Despite the fact the CDC recalled the PCR test  they state it can continue to be used for the rest of the year. There is absolutely no way PCR can determine what variant is causing illness.

___________________

For a bit of humor that is spot on:

http://

CDC Walensky states, “These tests are not authorized for the purpose of evaluating contagiousness.”  Yet, these very tests have been used to keep people from working, going to school, and participating in society. 

https://popularrationalism.substack.com/p/rapid-antigen-tests-cannot-distinguish

Rapid Antigen Tests Cannot Distinguish SARS-CoV-2 and HKU-1 – and That’s Dangerous

FDA Documents Show They Are Not Specific. The Law of the Instrument Tells Us That’s a Big Problem.


There’s an old expression: “When you’re a hammer, everything looks like a nail”. Sometimes referred to a “Maslow’s hammer”, this expression captures the idea of the law of the instrument. The origin of the expression seems to be from the observations that if you give a boy a hammer, they start pounding away at everything. Wikipedia has a good page on the history of this expression.

Thank goodness that regulations require that the FDA EUA documents not only be submitted, but that they can be viewed and read by anyone with access to the internet or who write to the FDA for a copy.

Everyone testing with the BinaxNOW nasal swab test, for example should be aware that per the documents provided by Abbott to the US FDA, their test can be a false positive if the person is infected with the HKU1 virus. (See the IFU Document):

“The comparison between SARS-CoV-2 nucleocapsid protein, MERS-CoV and human coronavirus HKU1 revealed that cross-reactivity cannot be ruled out.”

This language (or similar) is found in other IFU Documents for other COVID-19 RAT tests as well.

That means the test lacks pathogen specificity, and FDA cannot tell us what the risk of a false COVID-19 indication is without follow-up PCR testing. Further, like the PCR test, the comparison was only computational, based on BLAST-determine homology, not based on studies of thousands of patients. Further, protein structure, not sequence, is important for cross-reactivity – BLAST is not refined enough a tool to determine actually binding capacity, yet the FDA allowed negative BLAST results as evidence of degree of specificity.

PCR testing is similarly fraught with its own false positive problems, in part due to the same error (allowing BLAST results instead of requiring actual data from large studies). This is an issue the CDC could be finally coming to terms with after IPAK published a peer-review study in our journal on the problem, after Dr. Sin Hang Lee published two studies, after dozens of videos and articles have been written by yours truly alerting the world of the problem of PCR false positives due to the use of high cycle thresholds, and after an uproar over the fact that the PCR tests do not rule in Influenza.

HKU1, aka HCoV-HK1, first detected in 2004 in Hong Kong, is a Betacoronavirus (because it has a Hemagglutinin esterase gene), and enters the cell via a different recept that SARS-CoV-2. Like SAR-CoV-2 and SARS-CoV-2, it is an enveloped, single-stranded RNA virus.

Here’s an array of symptoms of HKU1 infection reported in 2017:

“Of 832 adult respiratory specimens screened, 13 (1.6%) cases of CoV-HKU1 were identified. Adults age ranged between 23 and 75 years and 6 (46%) were males. All of whom had 1 or more respiratory symptoms, and 5 (38%) also reported 1 or more gastrointestinal symptoms. Eleven (85%) reported history of smoking and 5 (38%) used inhaled steroids. Seven (54%) required hospitalization, 5 (71%) of these needed supplemental oxygen, and 2 (29%) were admitted to intensive care. Median length of hospitalization was 5 days. Eight (62%) received antibiotics despite identification of CoV-HKU1. Infectious work-up in 1 patient who died did not reveal any other pathogen. In 2 (15%) CoV-HKU1-positive adults, the only viral coinfection detected was influenza A.”

In 15% of people studied, co-infection with Influenza A was detected. That’s fairly common. For all of 2020-2021, for two years, “co-infection” of COVID-19 patients (PCR+ for SARS-CoV) was not even mentioned. Now that everyone (well, nearly everyone) is testing with in-home nasal swab kits for antibodies, many will be positive but will actually be HKU-1. Given the FDA’s allowance of specificity-by-BLAST, the problem could be much worse.

Why This is Dangerous

There are few good reasons why this is dangerous. Yes, the problem will make it appear as if more people have COVID-19 than actually do. The clinical workflow for COVID-19 is far more strenuous than for influenza A or HKU-1, so there’s the added burden on the healthcare system. I’ve heard reports that some hospitals are resorting to triage, placing non-PCR+ non-respiratory illness patients at risk (the in-hospital PCR screening adds to this as well).

However, people who have had a positive Rapid Antigen Test may also come to think of COVID-19 as mild for them, and their families – and worse – they may believe they have natural immunity and let their guard down. They may be more willing to attend a large gather, or mingle with others while symptomatic.

Third, false positives from PCR and from RAT tests alike will lead the public – and public health and medical communities – to believe that re-infection with SARS-CoV-2 is possible. The dynamics of societal responses will be flawed, leading to more quarantine, shut-downs, draconian control measures.

Fourth, the clinical care for a person who has respiratory viral infections other than SARS-CoV-2 may be different. If 15% of patients with “COVID-19” have something else, the CDC should know and medical practice should be altered to address this.

Fifth, co-housing non-COVID19 respiratory patients with COVID-19 patients can place them at risk of SARS-CoV-2 infection. Being sick already, they may have a more difficult clinical course as a result. Here’s a case of a woman who had HKU-1 infection on the day of entry and tested positive for COVID-19 on Day 3 of hospitalization.

Every single person who tests positive via PCR or RAT who has clinical symptoms or who has been exposed to a confirmed case of COVID-19 should have a confirmatory Sanger Sequencing test conducted to ensure what they have (or had) was truly a SARS-CoV-2 infection. As an added benefit, unlike PCR or RAT, Sanger Sequencing can tell us what variant we have (or have had).

There are over 6,000 laboratories around the US that can conduct Sanger Sequencing, and Sin Hang Lee, MD of Millford, CT is happy to provide the information on the primers he has developed for nested primer target amplification – and for Omicron detection.

Here’s a requisition form that can be used to order the Sanger Sequencing test (I have no financial relationship w/Dr. Lee or Millford Diagnostics).

The Law of the Instrument tells us that if you only test for COVID-19, you’ll only find COVID-19. Multiplex respiratory pathogen tests are also used in some places.

Please share with doctors and nurses in your area. This could help you & your loved ones travel a safer course.

__________________

For more:

Until We the People refuse to be tested by a test that doesn’t test for the very thing they claim it does, we can expect more lockdowns, more mandates, and more tyranny.  Time to stand up and refuse to be a part of this complete farce.

https://popularrationalism.substack.com/p/sars-cov-2-spike-protein-takes-the

SARS-CoV-2 Spike Protein Takes the Gloves Off and Causes Chronic Inflammation

Studies show the NLRP3 Inflammasome response is unleashed by the Spike protein. It’s around for 4 months. Aberrant NLRP3 inflammasome response leads to chronic illness and death. What you can do.

I enjoy doing research, but I hate it when the evidence is so depressing. Thank goodness for Dr. Levy. You’ll see why at the end.

This is the study that set me off:

Long-lived macrophage reprogramming drives spike protein-mediated inflammasome activation in COVID-19 https://www.embopress.org/doi/full/10.15252/emmm.202114150

The NLRP3 Inflammasome Response

The NLRP3 Inflammasome response is one of the myriad normal responses by which mammalian immune systems activate against viral infection. It’s supposed to be a short-term response than shuts down after the pathogen is defeated.

Good news: Spike protein primes the NLRP3 Inflammasome.

During infection, the NLRP3 Inflammasome response does its jobs.

Very bad news: Spike protein primes the NLRP3 Inflammasome, is systemic, and is found 4 months following injection.

After injection (and during Long-Haul COVID (LHC)), the NLRP3 Inflammasome response and must be doing chronic, systemic damage.

Spike Not Localized

The spike protein is not localized but is, per this Harvard study, systemic following injection

Circulating Severe Acute Respiratory Syndrome Coronavirus 2 (SARS-CoV-2) Vaccine Antigen Detected in the Plasma of mRNA-1273 Vaccine Recipients https://academic.oup.com/cid/advance-article/doi/10.1093/cid/ciab465/6279075

It is around for a lot longer than the virus:

While this Ogata study found the antigen up to15 days in 3/15 patients (20%),

This study found it in circulating exosomes up to 4 months(!)

Exosomes Cutting Edge: Circulating Exosomes with COVID Spike Protein Are Induced by BNT162b2 (Pfizer-BioNTech) Vaccination prior to Development of Antibodies: A Novel Mechanism for Immune Activation by mRNA Vaccines https://pubmed.ncbi.nlm.nih.gov/34654691/

Boosters Mean Repeated Chronic Inflammation

With never-ending boosters, we’re going to see chronic illness in the vaccinated at rates that are undeniable. None of it will be attributed to the vaccine.

More boosters means more chronic illness and death. Science tells us we can expect increased cancer, neurodegenerative disease, and a host of sublethal inflammation-mediated symptoms.

Here is a sample of articles that tell us this is necessarily so.

Aberrant NLRP3 Inflammasome Activation Ignites the Fire of Inflammation in Neuromuscular Diseases https://pubmed.ncbi.nlm.nih.gov/34199845/

NLRP3 Inflammasome Activation in Cancer: A Double-Edged Sword

https://www.ncbi.nlm.nih.gov/labs/pmc/articles/PMC7360837/

Inflammasomes: An Emerging Mechanism Translating Environmental Toxicant Exposure Into Neuroinflammation in Parkinson’s Disease https://www.ncbi.nlm.nih.gov/labs/pmc/articles/PMC6659017/

Be aware of SARS-CoV-2 spike protein: There is more than meets the eye https://pubmed.ncbi.nlm.nih.gov/34100279/

What You Can Do

Ok, so what’s the solution?

  1. Remove all other sources of toxins in your life. Thoroughly and urgently. You cannot afford these toxins. (I offer Environmental Toxicology in the Fall – email info@ipak-edu.org subject line “EnvTox” if you’d like me to offer access as pay-per-view (no instructor).
  2. Sign up for my new course in immunology. We start in the second week of January.
  3. And/Or sign up for Dr. Brownstein’s new course Wholistic Approaches to Human Health.
  4. Read this article by Dr. Levy – Canceling the Spike Protein Striking Visual Evidence Editorial by Thomas E. Levy, MD, JD http://orthomolecular.org/resources/omns/v17n24.shtml
  5. Fund the IPAK Spike Protein Oncogenic Potential Study (new in 2022) VISIT HERE.

For more:

__________________

https://popularrationalism.substack.com/p/studies-needed-on-the-oncogenic-potential?

Studies Needed on the Oncogenic Potential of COVID-19 Vaccinations

Fact Checkers deny it but present no new data. We’re doing Science – and taking deep dive into the question of plausibility using molecular evidence using Systems Biology

There has been some discussion on the oncogenic potential of SARS-CoV-2 vaccination – the ability of exposure to COVID-19 vaccines to increase the risk of cancers.

This study area is obviously high priority given the disease burden that could result from mass exposures. To assess plausibility, mechanisms of action (disease pathophysiology) studies are needed.

A little background, and some detail on our project:

Background

Autoimmunity or other molecular antagonism against important cellular processes can lead to cancer. Disruption of processes that mediate DNA replication and repair, for example, or regulate cell division can be oncogenic. Given the importance of immune surveillance in our bodies against new precancerous cells, autoimmunologic impairment of the immune proteins and cells would not only spell disaster for infections, but could also lead to unchecked cancer growth.

The evidence in support of these possibilities is diverse, but hard evidence is difficult to find.

In my April 2020 paper warning against pathogenic priming, I wrote:

Pathogenic Priming

“Remarkably, over 1/3 (11/27) of the immunogenic proteins in SARS-CoV-2 have potentially problematic homology to proteins that are key to the human adaptive immune system (emboldened in Table 1). Mapping of the overall gene list to Pathways via Reactome.org revealed that many functions of the human adaptive immune system might be impacted via autoimmunity against these proteins and their interactors, including MCH(sic) Class I and Class II antigen presentation, PD-1 signaling, cross-presentation of soluble exogenous antigens and the ER-Phagosome pathway.”

This sounds like an argument for vaccination, but it’s not. Subclinical mumps, measles and pertussis infections are well established in the vaccinated. Similarly, following vaccination, the repeated exposure to SARS-CoV-2 virus in the vaccinated might lead to silent, subclinical disease processes due to SARS-CoV-2 virus infection in spite of – or because of – vaccination. These chronic exposures may be more prevalent in the vaccinated than in those with natural immunity. Thus, the question is not merely “does vaccination increase the risk of cancer”, but is better posed as “does repeated exposure to SARS-CoV-2 infections in the vaccinated lead to increased risk of cancer”?.

Dr. Ryan Cole’s Observations

While pooh-poohed by so-called “Fact Checkers”, Dr. Ryan Cole of Idaho saw and in Aug, 2021 reported an uptick in uterine cancers in women who had been vaccinated.

Dr. Cole reported that he was seeing increases is herpes virus, mononucleosis, shingles, human papillomavirus, and uterine cancers:  This doctor trained at the Mayo Clinic and runs the largest independent testing laboratory in Idaho. Listen to what his lab testing is showing:

Dr. Burkhardt reported that 93% of post-inoculation autopsies showed lymphocyte penetration in all organs and tissues, and Dr. Bhakdi commented on autopsy findings that cells in the lymph nodes being destroyed following vaccination.

Summary:
The vaccines are bad news. Fifteen bodies were examined (all died from 7 days to 6 months after vaccination; ages 28 to 95). The coroner or the public prosecutor didn’t associate the vaccine as the cause of death in any of the cases. However, further examination revealed that the vaccine was implicated in the deaths of 14 of the 15 cases. The mos…  Read more

Publications providing evidence of immune impairment

A number of publications support plausibility, and some have been dismissed without new evidence by so-called “Fact Checkers”. Important, the loss of CD8 cells in long-haul COVID was noted by Dr. Bruce Patterson (who I interview on Unbreaking Science on Jan 31, 2020). These are the natural killer cells Dr. Cole was concerned about.

We know that yes, loss of CD8 cells are associated with increased risk of cancer.

This study

is cited by these authors from the University of Texas MD Anderson Cancer Center, Houston, TX, who wrote:

“For instance, SARS CoV-2 proteins, can hijack the human immune response to pathogens and the DNA damage repair system, thereby damaging both innate and adaptive immunity”

The fact-checkers claim that Dr. Cole is mistaken, yet there it is.

Increase in All-Cause Mortality in the UK and Indiana

Unreported Truths
Vaccinated English adults under 60 are dying at twice the rate of unvaccinated people the same age

What We Should Expect in the Molecular and Epidemiologic Evidence

If vaccination sets forth a cascade of events that leads to increased cancer risk in the vaccinated, we should see biological pathways related to the specific cancer types being reported as elevated, including blood cancers and per Dr. Cole, uterine cancers.

In the epidemiologic data, there should be a pulse in the risk of cancer types that is not explained by the increased risk of cancer progression due to the cessation of cancer screening visits that occurred during the lockdown. Unlike the temporary pulse from lock-down related cancers, we should see a sustained increased in cancer rates over time in the vaccinated compared to the unvaccinated. This aspect of this question is not part of the current study, but will be part of another study we will launch later this year.

IPAK SARS-CoV-2 Spike Protein Oncogenic Potential Study

Most of the people vaccinated in the US received spike-only vaccines. Here’s what we intend to do

  1. Using the known and published immunogenic epitopes in the SARS-CoV-2 spike protein, identity homologies (similarities) with known oncogenic proteins that could lead to autoimmunity against key cancer-related proteins. For this, we’ll canvas the Human Protein Atlas for genes which if mutated confer cancer risk and use the methodology laid out in (Lyons-Weiler, 2020).
  2. Using pathway analyses, we will characterize which biological pathways are likely to be most influenced.
  3. We will write the results up for peer-reviewed publication.
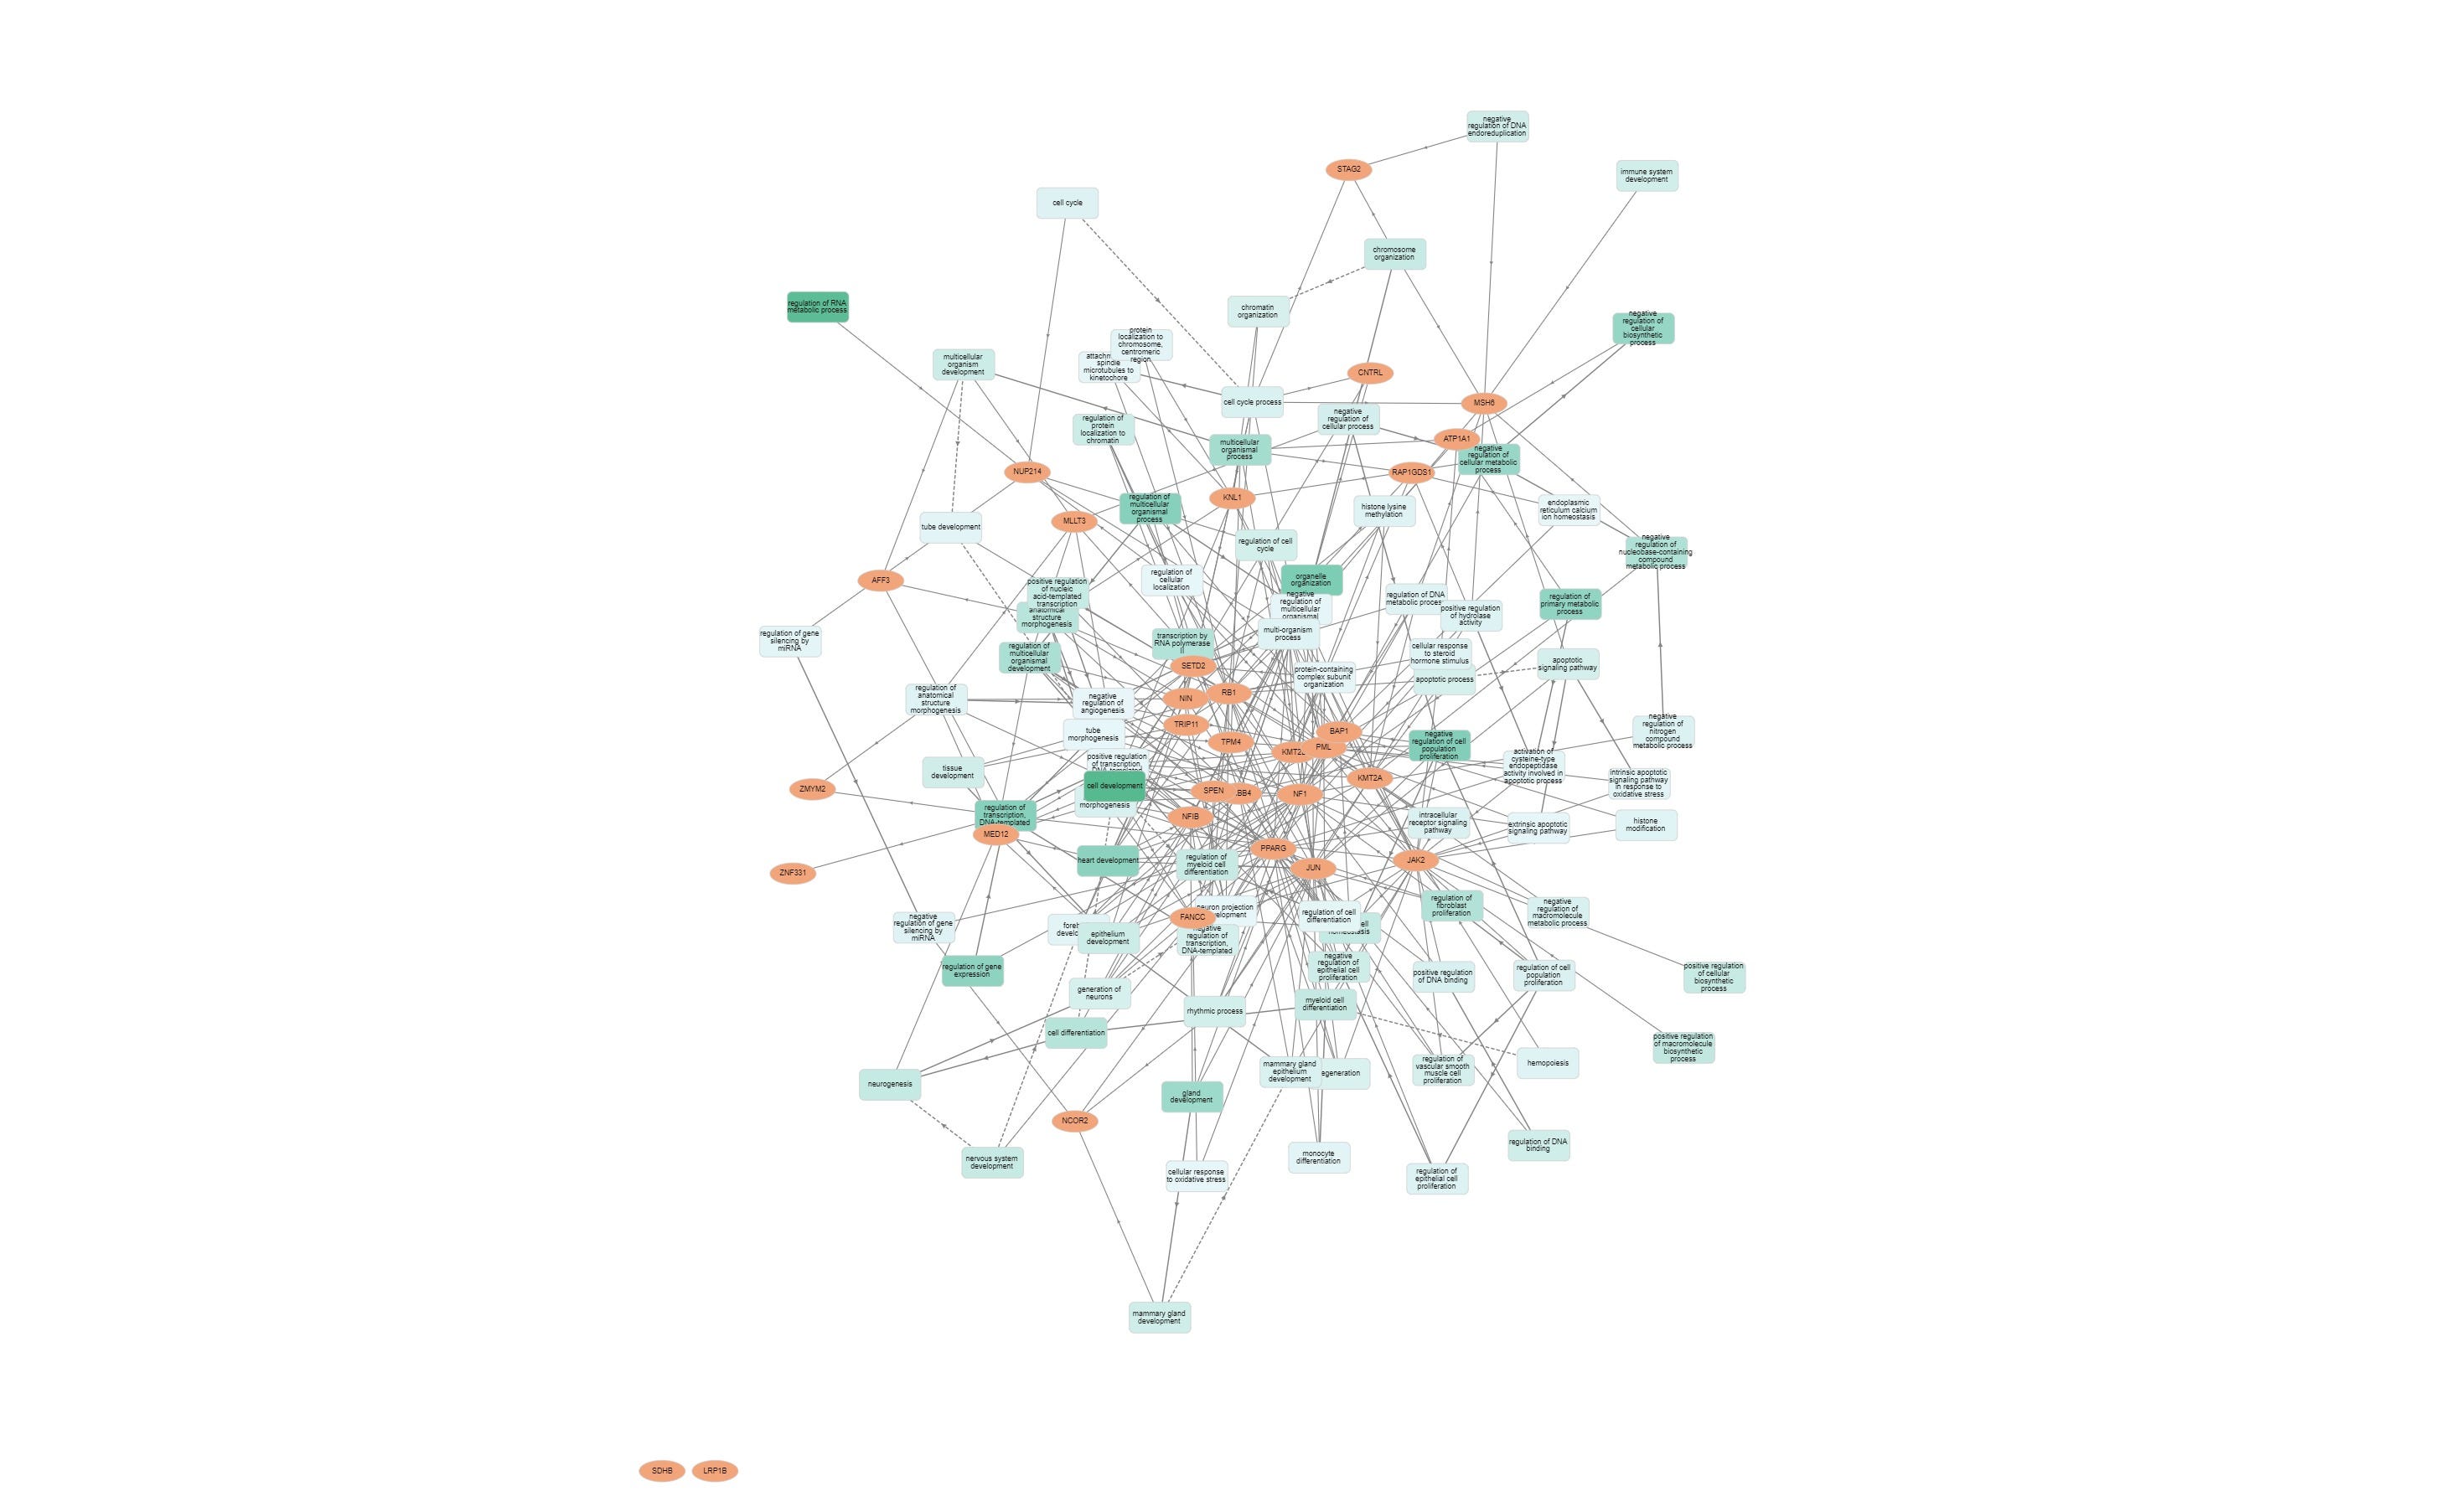
  4. Our preliminary analysis tells us so far that yes, there appear to be impacted biological pathways (preliminary data):

Obviously, I hope this hypothesis is wrong, so we will attempt to disprove it via statistical hypothesis testing using gene enrichment analysis, a statistical technique conducted at the biological pathway level.

All of our studies are funded by the public. We have set up a dedicated donation portal for small monthly donations to IPAK, The Institute for Pure and Applied Knowledge, a not-for-profit in the Commonwealth of Pennsylvania, dedicated to this project. Funds used underwrite the costs of the study as well as any publication fees if we opt for open-access publication (an added step that we prefer to increase distribution).

All knowledge generated by IPAK via research is public domain – none of the knowledge can be used by IPAK for profitable ventures.

So, let’s see whether the hypothesis of increased oncogenic potential is plausible.

https://www.medpagetoday.com/special-reports/exclusives/96412

COVID Vaccine Booster Efficacy Against Infection May Fade Quickly

— New U.K. data suggest steep drop-off in protection, potentially giving Omicron more power
People wearing face masks walk past a bus stop ad encouraging Covid booster vaccinations in central London.

Real-world data from the U.K. showed that efficacy of a third dose of a COVID-19 vaccine waned significantly at the 10-week mark, leaving boosted individuals at risk of infection with Omicron.

In a December 23 U.K. Health Security Agency (HSA) technical briefing, vaccine efficacy against symptomatic infection generally fell to around 40% some 2.5 months after a booster dose. (See link for article)

_________________

Summary:

  • HSA assessed 147,597 Delta and 68,489 Omicron cases from November 27 to December 17.
  • The Pfizer primary series & booster, showed efficacy against symptomatic disease was 70% immediately after the third dose but fell to 45% at 10 weeks or longer.
  • Having a Pfizer primary series but a Moderna booster saw protection against symptomatic disease hover around 70% to 75% for up to 9 weeks post-boost.
  • Having a primary series of AstraZeneca, efficacy peaked at 60%, 2 to 4 weeks after either a Pfizer or Moderna booster, then fell to 35% with Pfizer and 45% with Moderna by around 10 weeks.
  • They omitted efficacy against severe disease, hospitalization, and death because there weren’t enough Omicron cases admitted to the hospital.
  • Data from Israel also suggests waning efficacy after boosters, but the ‘powers that be’ still illogically recommend more boosters despite the fact.
  • Data from Israel also showed a doubling in the rate of infection with Delta in ages 60 & up within 4-5 months after a 3rd shot and no indication of reduced efficacy against severe disease.  (But remember, they are not looking at absolute risk reduction so it’s all skewed to make the jabs appear efficacious).
  • Yet the vaccine cultists keep recommending more jabs.  Peter Hotez, MD, PhD, is pushing a 4th shot for healthcare workers due to exposure to Omicron (despite there not being enough Omicron hospitalizations to even use for the study). Hotez is worried about instability in the health system but never stops to ponder the instability caused by the jabs themselves.  This one-sided thinking is prolific regarding these shots.
  • The article then delves into the oft repeated mantra that these jabs somehow “reduce illness” and proceeds to rattle off all sorts of numbers which you can read for yourself.  They end the litany with the following caution: “the findings have low confidence because these are early analyses with small numbers of hospitalizations, limited follow-up time, minimal adjustment for previous infection, and limited spread into the most vulnerable age group.“

By Alan Foos

https://www.amazon.com/Lyme-Disease-Medical-Fraud-Statistics-ebook/dp/B01M2679DA/ref=monarch_sidesheet  (Book written in 2016)

Millions are suffering with Lyme disease while being drained further by a predatory medical industry, criminal CDC and fraudulent pharmaceutical industry. You probably know some if you aren’t one. They’re being treated for bipolar disorder, fibromyalgia, MS, Alzheimer’s, MS, schizophrenia, personality disorder or many other bogus diseases. The money is in drugs that don’t work, especially psychoactives which in the long term will create the symptoms they are supposed to treat. If you were blind sided by Lyme, you likely lost your career, maybe your home and family. Here is how I fared for 47 years, what I learned that would have saved me all those nightmares. It would have also saved my wife who was also destroyed by Lyme disease and our three children born with it. I give you no illusions or false promises, only how I met God, fought the fight and won the game long before I found out about Lyme. Also, you may request a link to a FLIPPING BOOK online version of the book which is much easier to use. For an example of a technical flipping book I’ve written, see http://foosresearch.appspot.com

https://www.foosresearch.com/lymelikeme.html  (From 2020)

Foos writes about his long struggle Lyme disease.  This is not for the faint of heart – but no Lyme/MSIDS story ever is.  The desperation is tangibly felt, as is the cruel, abusive attitudes of clueless doctors who are much more willing to write you off as a nut-job than a person struggling with numerous pathogens – any one of which can kill you but together put you in a pit of despair so deep you wonder if you will ever be able to crawl out of it.

Foos was particularly challenged with a complete mental and physical breakdown and a near death experience. He had severe infections in his sinuses, facial tissues, legs and feet.  Struggling with involuntary facial contortions and facial agony, Foos, like so many, had to find answers for himself.  Being a biologist and soils engineer, he labored day and night slaving in the lab to learn the scientific properties of bentonite.