Archive for the ‘Testing’ Category

CPAC Warns: Lyme Risk Higher Than Ever

https://www.lymedisease.org/capc-parasite-forecast-2023/

CAPC warns that Lyme disease risk is higher than ever

April 20, 2023

The nonprofit Companion Animal Parasite Council (CAPC) — the nation’s leading source on parasitic diseases that threaten the health of pets and people — is warning that the risk of Lyme disease is higher than ever.

In its 2023 Parasite Forecast, CAPC documents how the blacklegged ticks that spread Lyme disease are expanding into new geographical areas. This increases the risk of Lyme disease outside of historically endemic places like the Northeast and Upper Midwest.

Parasite infections are real and can be harmful and even deadly to pets and people. Lyme disease is a predominant One Health issue, an approach calling for the collaborative efforts of multiple disciplines working to attain optimal health for animals, people and the environment.

11 years of forecasts

“Because of the zoonotic potential of pathogens like Lyme disease, we started providing annual forecasts eleven years ago to alert communities about the risks they pose to people and pets,” says Dr. Christopher Carpenter, DVM, and Chief Executive Officer of CAPC.

“Lyme disease, in particular, is an important One Health pathogen that occurs in both veterinary and human medical settings. CAPC’s Pet Parasite Forecast is critical to alerting pet owners, veterinarians and physicians to the risks this year and reinforcing CAPC’s recommendation that all pets need to be annually tested and protected year-round.”

In its 2023 annual forecast, CAPC reports the risk of acquiring Lyme disease in 2023 is elevated due to the expansive nature of the blacklegged tick vector (Ixodes scapularis).

This increase in Lyme prevalence can be attributed to land use, human population growth, urbanization, and changes in wildlife host density and location. Risks have also increased due to rehoming of pets, as well as changes in:

  • Distribution and prevalence of vector (tick) populations
  • Shifting wildlife populations and their infiltration into newly developed and reclaimed areas
  • Short- and long-term changes in climatic conditions
  • Changes in habitat due to natural or human-induced processes

Lyme Disease Forecast

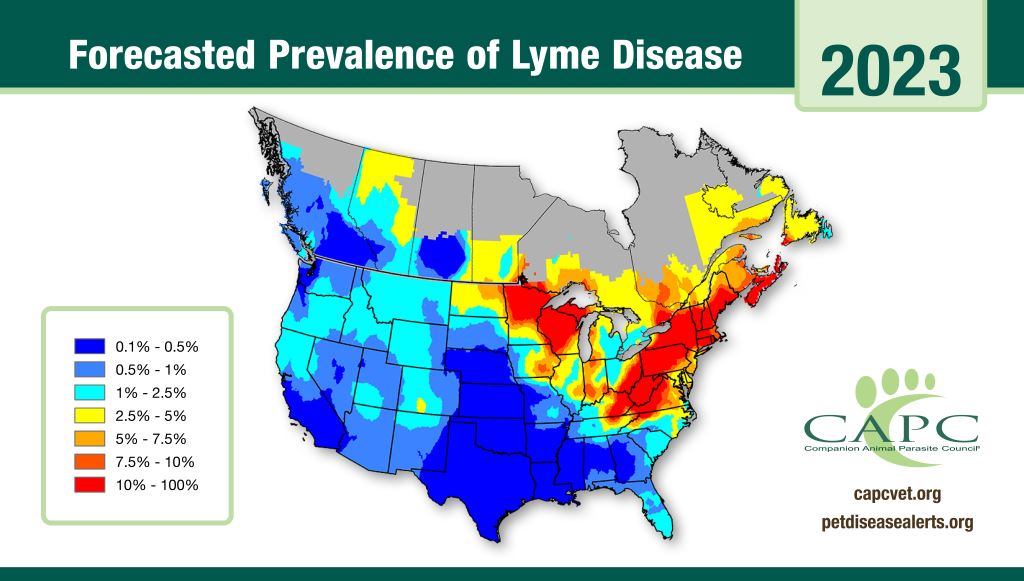
For 2023, CAPC predicts Lyme disease is a high threat and continues to expand southward and westward outside of the historically high-risk areas in the Northeast and Upper Midwest, including Wisconsin, Minnesota and the upper peninsula of Michigan.

There is a higher-than-average seroprevalence predicted in northeastern Tennessee, western Michigan and Ohio, with high-risk “hot spots” expected in northwestern and southwestern Michigan, and southern and northeastern Ohio.

A higher-than-normal risk is also expected in North Dakota, northeastern South Dakota, Iowa, Illinois, and eastern Kentucky. The southward movement of Lyme is evident in the increasing risk in the Carolinas and Tennessee.

In addition, CAPC reports a northern expansion into Canada, including southern regions of Ontario, Quebec and Manitoba, as well as on New Brunswick and Nova Scotia, due to increased Lyme detection in Canadian dogs. Pets living in or traveling to these areas are considered at high risk.

Testing and Prevention Strategies

The 2023 forecasts – supported by ongoing research by parasitologists and statisticians in leading academic institutions across the United States – highlight areas where more should be done to lower the risk of companion animals’ exposure to disease vectors, such as ticks.

The foundation of these prevention strategies are recommendations that veterinarians and pet owners test their pets annually for disease and protect their pets with products that kill or repel ticks year-round.

A vaccination for Lyme disease should always be considered for pets in high-risk areas. Lyme disease, in particular, is an important One Health pathogen that impacts the health of both pets and people.

Veterinarians play an important role in preventing zoonotic disease in pets, as well as people, by implementing effective parasite control programs. In regions with historically high prevalence and in forecasted regions of increased risk, veterinarians should reinforce their recommendations of aggressive tick control.

CAPC One Health Study

Research conducted by CAPC underscores the value of CAPC’s prevalence maps and emphasizes the importance of a One Health approach to tick-borne diseases. In 2019, a CAPC study confirmed dogs safeguard humans serving as sentinels to alert humans where they are at greatest risk for tick-borne Lyme disease.

“With dogs being tested annually for exposure to the pathogen that causes Lyme disease, we were able to study over seven years of nationwide canine diagnostic data, representing more than 16 million data points — something difficult to achieve when studying ticks and the environment directly. And unlike the challenges with access to human medical records, anonymous veterinary data does not have these privacy concerns,” said Dr. Michael Yabsley, a CAPC Board Member and professor in the Department of Population Health, College of Veterinary Medicine and Warnell School of Forestry and Natural Resources at the University of Georgia.

Results from the study – “Quantifying the relationship between human Lyme disease and Borrelia burgdorferi exposure in domestic dogs” – published in the prestigious, peer-reviewed Geospatial Health quantified the relationship between incidences of tick exposure in domestic dogs to human Lyme disease. The model established in this research broke new ground by giving residents, travelers and health care providers a county-level map to help them identify areas of high Lyme risk across the country.

“By combining sophisticated statistical modeling with this invaluable canine data, we’re enabling veterinary medicine to benefit human medicine,” said Dr. Stella Self, assistant professor in the Department of Epidemiology and Biostatistics at University of South Carolina. “This research represents the first step on the long road to developing a forecast for human Lyme disease.”

30-Day Forecast Maps for Pet Owners

Pet owners who want to monitor the activity in their county throughout the year have access to 30-Day Parasite Forecast Maps at http://www.petdiseasealerts.org. These maps, developed exclusively by CAPC, provide a local forecast for every county in the continental United States on a monthly basis. This free service helps to remind pet owners of the continuous risk in their area and the importance of annual parasite testing and year-round protection.

“Because tick-borne diseases like Lyme are ever-changing, the 30-Day Pet Parasite forecasts at http://www.petdiseasealerts.org are an invaluable tool to protect both pets and people with monthly updates that show the risk for Lyme disease in their area,” said Dr. Rick Marrinson, Past President/Board Member for CAPC and owner of Longwood Veterinary Clinic in Longwood, Florida.

Other Parasite Spread in 2023

In addition to Lyme disease, CAPC forecasts that heartworm disease, which is transmitted by mosquitoes, and tick-borne diseases ehrlichiosis and anaplasmosis, continue to spread throughout the United States in 2023. Veterinarians and pet owners are encouraged to discuss how to effectively address the increased prevalence. Annual testing and year-round use of preventive products remains the best means of providing comprehensive parasite control and disease prevention.

How the Forecasts are Created

The annual CAPC Pet Parasite Forecasts are a collaborative effort between parasitologists and statisticians in leading academic institutions across the United States. These scientists engage in ongoing research and data interpretation to better understand and monitor vector-borne disease agent transmission and changing life cycles of parasites. The forecasts are based on many factors, including temperature, precipitation, and population density.

About the Companion Animal Parasite Council

The Companion Animal Parasite Council is an independent not-for-profit foundation comprised of parasitologists, veterinarians, as well as medical, public health and other professionals, who provide information for the optimal control of internal and external parasites that threaten the health of pets and people.

Formed in 2002, CAPC works to help veterinary professionals and pet owners develop the best practices in parasite management that protect pets from parasitic infections and reduce the risk of zoonotic parasite transmission.

SOURCE OF PRESS RELEASE: The Companion Animal Parasite Council 

Lyme Cabalist Develops Test for Pfizer Lyme Vaccine Trials: Yet More Proof of a Conspiracy

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/31520021

To: The FDA… What shenanigans are taking place here?

Carl Tuttle

Hudson, NH, United States

APR 23, 2023 — 

Please see the following inquiry/complaint sent to the FDA.

Dr. Gary Wormser has developed diagnostics for Pfizer’s Lyme vaccine trial?

What shenanigans are taking place here? This is a huge red flag! Controlling the Lyme disease narrative for the past 30yrs and now the outcome of a vaccine trial?

I believe the FDA will refuse to respond to my complaint so PLEASE demand an answer to this citizens complaint by sending an email to  the Center for Biologics Evaluation and Research at ocod@fda.hhs.gov referencing my letter below. Everyone has permission to cut and paste my correspondence.

Complaint sent to the Center for Biologics Evaluation and Research at the FDA:

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: ocod@fda.hhs.gov
Cc: Brennan, Patti (NIH/NLM) [E], Schor, Nina (NIH/OD) [E], Gregurick, Susan (NIH/OD) [E], michael.lauer@nih.gov, lyric.jorgenson@nih.gov
Date: 04/18/2023 11:34 AM
Subject: Clinical Trial of a 6-Valent OspA-Based Lyme Disease Vaccine (VLA15)

An Efficacy, Safety, Tolerability, Immunogenicity, and Lot-Consistency Clinical Trial of a 6-Valent OspA-Based Lyme Disease Vaccine (VLA15) (VALOR)
https://clinicaltrials.gov/ct2/show/NCT05477524

Apr 18, 2023

Food and Drug Administration
Center for Biologics Evaluation and Research (CBER)
10903 New Hampshire Avenue
Silver Spring, MD 20993-0002

Re: ClinicalTrials.gov Identifier: NCT05477524

To whom it may concern,

For the past thirty years there has been a handful of academics controlling the Lyme disease narrative who have a vested interest in bringing an “OspA-Based” Lyme disease vaccine to market. Most of these individuals hold patents on technology that would pay out handsomely in royalties.  It would be a flagrant conflict of interest if these individuals reside on Pfizer’s Endpoint Adjudication Committee deciding who has or does not have Lyme disease.

There is another concern here as discovered through the Open Payments Search Tool.

“The Open Payments Search Tool is used to search payments made by drug and medical device companies to physicians, physician assistants, advanced practice nurses and teaching hospitals.”

Dr. Gary Wormser received $156,000 in 2021 and in one of his recent publications he claims to have developed “Lyme diagnostics for a Lyme vaccine trial” for Pfizer:

Lack of Convincing Evidence that Borrelia burgdorferi Infection Causes Either Alzheimer’s Disease or Lewy Body Dementia
https://doi.org/10.1093/cid/ciab993
Gary P Wormser, Adriana Marques, Charles S Pavia, Ira Schwartz, Henry M Feder, Jr, Andrew R Pachner

COI Statement….

Disclosures: Dr. Wormser reports receiving research grants from the Institute for Systems Biology for exploring biomarkers for outcome of Lyme disease, Pfizer, Inc for developing Lyme diagnostics for a Lyme vaccine trial, NIH/Tufts for Xenodiagnosis to assess persistence of Borrelia, and CSU/NIH. He has been an expert witness in malpractice cases involving Lyme disease and was an expert witness regarding babesiosis; employed by New York Medical College; and is an unpaid board member of the non-profit American Lyme Disease Foundation. He reports no money paid to anyone for U.S. Patent No. 10,669,567 B2 ( HIGH SENSITIVITY METHOD FOR EARLY LYME DISEASE DETECTION Issue Date: June 2, 2020 Inventors: John T. Belisle, Claudia R. Mollins, Gary P. Wormser).

Dr. Marques has a patent US 8,926,989 B2 and 9310367 for compositions and methods for screening for Lyme disease; and is an unpaid Scientific Advisor to the Global Lyme Alliance and to the American Lyme Disease Foundation. Dr. Schwartz has been on the External Advisory Committee for Oklahoma InBRE. Other None

End of COI statement

______________________________

The CDC requires “new tests” to be cleared by the FDA. Is Wormser’s Lyme diagnostics for this clinical trial FDA approved? What behind the scenes shenanigans are going on here?

From the CDC website:

CDC supports the development of new tests
https://www.cdc.gov/lyme/diagnosistesting/index.html

“New tests may be developed as alternatives to one or both steps of the two-step process. Before CDC will recommend new tests, they must be cleared by the Food and Drug Administration (FDA).”

Additional concerns:

There were neurological complications with the previous “OspA-Based” Lyme vaccine (LYMErix) as published in the International Journal of Risk & Safety in Medicine. Reports of cerebral ischemia, transient Ischemic attacks, demyelinating events, optic neuritis, transverse myelitis, and non-specific demyelinating conditions are evaluated in this paper. To my knowledge, there were no studies to determine why LYMErix caused these serious complications.

Neurological complications of vaccination with outer surface protein A (OspA).
Marks DH.
http://www.ncbi.nlm.nih.gov/pubmed/21673416

REPORT ON LYMErix prepared for the 2001 Advisary Committee Meeting:(personal Dropbox storage area)
https://www.dropbox.com/s/sodqs3pdeeesktf/Sheller%20Lymerix.pdf?dl=0

Excerpt

“The people who have contacted us were, prior to vaccination with LYMErix, healthy, active and energetic. Indeed, the very reason they sought the LYMErix vaccine was their desire to preserve their healthy, active lifestyle. However, what they experienced was a dramatic degradation of their health and quality of life. As will be described below, these previously healthy individuals are now afflicted with painful, at times debilitating arthritic symptoms, including joint pain and swelling, as well as extremely severe Lyme-disease-like symptoms which have persisted to this day.”

Below is the link to the Final Judgement and Approval of the class action against SmithKline Beecham as a settlement was awarded to these individuals.

JUDGEMENT, FINAL ORDER AND DECREE GRANTING FINAL APPROVAL OF THE CLASS ACTION SETTLEMENT: (personal Dropbox storage area)
https://www.dropbox.com/s/v3gyw4fv8nst9bz/2003_Vaccine_Judgement_Final_Sttle_Apprvl..pdf?dl=0

Summary of this inquiry:

  1. Who are the individuals residing on the Endpoint Adjudication Committee in North America?
  2. Is Wormser’s “Lyme diagnostics for a Lyme vaccine trial” FDA approved?
  3. Through informed consent have the study participants been advised of Neurological Complications from the previous “OspA-Based” Lyme vaccine and are they made aware of the class action settlement?

Let us not forget that Pfizer paid the largest fine for health care fraud in 2009:

Justice Department Announces Largest Health Care Fraud Settlement in Its History Pfizer to Pay $2.3 Billion for Fraudulent Marketing  https://www.justice.gov/opa/pr/justice-department-announces-largest-health-care-fraud-settlement-its-history

Please provide a prompt reply to this inquiry/complaint and answer all three questions.

Respectfully submitted,

Carl Tuttle
Hudson, NH

Cc: Patricia Flatley Brennan, RN, PhD Director National Library of Medicine

Nina F. Schor, MD, PhD, NIH Deputy Director for Intramural Research
Susan K. Gregurick, PhD, NIH Associate Director for Data Science
Michael Lauer, MD, NIH Deputy Director for Extramural Research
Lyric Jorgenson, PhD, Acting NIH Associate Director for Science Policy

________________

**Comment**

It’s all right here in purple crayon, and is yet more proof the government uses people, social media, mainstream media, and “vaccine” manufacturing companies as subsidiaries for their own nefarious purposes.

For more on Wormser:

  • Immunetics, Inc. (the developer of the insensitive C6 Lyme test, which he promotes).
  • Abbott, Institute for Systems Biology
  • Rarecyte, Inc.
  • Quidel Corporation
  • Insurance companies, by serving as an expert witness in court cases against doctors for treating outside IDSA guidelines
  • NIH: by receiving large shares of grants for Lyme-related research and by being influential in the selection of grant recipients.
  • IDSA – by being chairman of the Lyme guidelines revision panel which is opposed toand biased against chronic/persistent Lyme
Wormser serves the commercial interests of profit-making companies, and trivializes the effects of Lyme on patients as proven by his appearance in Under Our Skin, a documentary on the ravages of chronic Lyme disease

Cast Reports: Orbital Myositis Due to Lyme Disease

https://danielcameronmd.com/case-reports-orbital-myositis-due-to-lyme-disease/

CASE REPORTS: ORBITAL MYOSITIS DUE TO LYME DISEASE

myositis-lyme-disease

In their article “Two Cases of Orbital Myositis as a Rare Feature of Lyme Borreliosis,” Sauer et al. describe two female patients with focal orbital myositis due to Lyme disease. [1]

Orbital myositis is typically caused by systemic disease, such as Grave’s disease, or haematological disorders like lymphomas, the authors explain. In these cases, myositis is often bilateral. It has been reported, as well, as a rare manifestation of Lyme disease.

In these two cases, myositis was confirmed by MRI findings.

Patient #1: 68-year-old female

“The 68-year-old patient had acute and recurrent episodes (lasting from 2 to 4 weeks, 2 to 4 times each year) of right orbital swelling and pain,” the authors wrote.

Each episode resolved spontaneously or with steroids and nonsteroidal anti-inflammatory drugs.

Lyme disease was suspected since the patient was living in a rural area of France, highly endemic for Lyme disease, and she recalled having numerous tick bites and had a history of an erythema migrans rash and arthralgia.

Testing for Lyme disease was positive and the woman began treatment with doxycycline. Within 3 weeks, her symptoms had resolved.

“We reported the cases of two patients who presented with orbital myositis caused by Borrelia infection.”

Patient #2: 13-year-old female

The 13-year-old adolescent complained about unilateral orbital swelling complicated with exophthalmia and horizontal diplopia.

“MRI showed a hyperintense signal of right inferior and medial rectus muscles,” the authors wrote.

The woman was living in an area endemic for Lyme disease and had a recent tick bite followed by an Erythema migrans rash.

Lyme disease testing was positive and she was treated successfully with 4 weeks of doxycycline.

The authors reported, “a resolution of ocular symptoms and a decrease of the MRI signal intensity were observed within 1 month.”

The authors conclude:

  • “Orbital myositis is an unusual manifestation of Lyme disease, although it is likely that the condition is underdiagnosed.”
  • Unexplained muscle swelling occurring in a patient who has had a rash or a recent history of a tick bite in an endemic area for Lyme disease should prompt consideration of this diagnosis.”
References:
  1. Sauer A, Speeg-Schatz C, Hansmann Y. Two cases of orbital myositis as a rare feature of lyme borreliosis. Case Rep Infect Dis. 2011;2011:372470. doi: 10.1155/2011/372470. Epub 2011 Jul 28. PMID: 22567470; PMCID: PMC3336248.

________________

**Comment**

Where to even begin……

  1. Rarely reported is a far different matter than rarely occurs.  Everything about Lyme/MSIDS is downplayed. This most probably happens a lot.
  2. I hesitate to ponder what would have occurred if they hadn’t each tested positive, which is akin to winning the lottery with tests that miss 70% and in this case, 86% of cases.  Current 2-tiered CDC testing also completely omits testing for any coinfections which are quite common.
  3. The second patient had a tick-bite followed by the bullseye rash.  This proves she is infected with Lyme.  No testing required since the rash is diagnostic for Lyme – yet ‘the powers that be’ continue to take the deadly “wait and see” approach and continue to utilize faulty, inadequate testing for diagnosis and treatment.  It seems nothing ever changes.
  4. They continue to treat infected patients with the inadequate and limited mono-therapy of doxycycline, despite research and reality proving this doesn’t work.
  5. Like all other studies, these patients need lengthy follow-up.  IF that occurred, I guarantee that research would prove the current therapy simply doesn’t work.

For more on eye issues with Lyme/MSIDS:

Bedridden Woman Diagnosed with ALS, Ended Up Having Lyme/MSIDS

https://twitter.com/dralmiller/status/1575837175484411905

Tweet from Dr. Alfred Miller:

Recent case: 30 y/o female, bedridden, returned from the Mayo Clinic diagnosed with ALS.This patient was then properly tested for Borrelia & coinfections.  Results confirmed Borrelia & Bartonella infection.Appropriate antibiotics began. Now patient able to ascend & descend stairs.   
Although this is a year old, it’s a potent reminder that things are often not what they seem – particularly with neurological diseases that have been slapped with a label but have many causes.
Dr. Miller has been an outspoken advocate for Lyme/MSIDS patients for years.  He started on this journey after his own daughter in law was given an ALS diagnoses but struggled with tick-borne illness.  Like so many patients, she tested on the CDC ELISA testing, and was told it couldn’t be Lyme/MSIDS.  Miller wouldn’t accept this prognosis and sent her blood to a specialty lab where sure enough, it came back positive.
Miller believes all patients who have been given a diagnosis of a neurodegenerative disease—including ALS, MS, lupus, and fibromyalgia—should be evaluated for Lyme disease.

Our most ardent supporters are usually infected or have loved ones that are infected.  All of a sudden, they “get it,” after having to travel the same pot-holed riddled path as suffering patients and see for themselves the complete mismanagement of a complex disease that hasn’t made any forward progress in over 40 years.
This is the reason I feel strongly the CDC/FDA/NIH should not be given one more dime.  These agencies don’t care about public health at all and are in fact complicit in a crime against sick patients, whom they not only haven’t helped them one tiny bit, but have in fact abused and neglected them.
For more on Dr. Miller:

FDA Draft Guidance Addresses Clinical Development of Drugs to Treat Early Lyme – Parts 1 & 2

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/

FDA draft guidance addresses clinical development of drugs to treat early Lyme disease

Carl Tuttle

Hudson, NH, United States

APR 2, 2023 — 

The FDA is drafting guidance for Lyme Disease Drug Development. Not surprisingly they have completely mischaracterized the disease and target patient population. It looks like we have an important opportunity to educate them before sick patients aren’t included in the cohorts eligible to receive treatment. Similar to the vaccine, working with the wrong population will make treatments look effective even if they are not. It also prevents drug developers from being able to address what the real disease is and does. April 3 at 11:59 pm is the deadline for comments. Please consider commenting and/or sharing with others.

Announcement:
https://www.raps.org/news-and-articles/news-articles/2023/2/fda-draft-guidance-addresses-clinical-development

Draft Guidance: 
https://www.fda.gov/media/164949/download

Comment Here
https://www.regulations.gov/commenton/FDA-2022-D-2315-0002

Carl Tuttle’s Submitted comment…

Early Lyme Disease as Manifested by Erythema Migrans: Developing Drugs for Treatment; Guidance for Industry – DRAFT GUIDANCE

Office of Communications,
Division of Drug Information Center for Drug Evaluation and Research
Food and Drug Administration

Focusing on the early stage of Lyme disease with bulls-eye rash is the root cause of this failed Public Health Response. Less than 50% of Lyme patients developed that rash as recorded by Epidemiologists in the State of Maine.

2011,  42% developed the rash:  http://www.maine.gov/dhhs/mecdc/infectious-disease/epi/vector-borne/lyme/documents/2011-lyme-legislature.pdf

2012,  49% developed the rash:  http://www.maine.gov/dhhs/mecdc/infectious-disease/epi/vector-borne/lyme/documents/2012-lyme-legislature.pdf

2013,  51% developed the rash:  http://www.maine.gov/dhhs/mecdc/infectious-disease/epi/vector-borne/lyme/documents/2013-lyme-legislature.pdf

2014,  57% developed the rash:  http://www.maine.gov/dhhs/mecdc/infectious-disease/epi/vector-borne/lyme/documents/2014-lyme-legislature.pdf

Lyme was pigeonholed into the category of “Hard to Catch and Easily Treated” through an elaborate scheme focusing on the acute stage of disease with bulls-eye rash and early treatment while avoiding the horribly disabled Lyme patient population. [i] The Centers for Disease Control financed the dishonest science using taxpayer dollars [ii] under grant# RO1 CK 000152 [iii] which has misguided a nation of intelligent physicians through the deliberate suppression of evidence of persistent Borrelia infection after aggressive antibiotic treatment. [iv]

This well-orchestrated scheme has misclassified Lyme as a low-risk and non-urgent health threat which actually belongs in the same health threat category as AIDS, Zika, cancer etc. and requires a Manhattan Project to understand how the infection it disables its victim just like untreated strep throat leads to rheumatic fever causing irreversible heart damage, untreated HIV leads to AIDS with substantial disability and death and untreated syphilis leads to progressive disability and dementia. Patients with a prolonged exposure to the Lyme disease pathogen are almost always incapacitated. Many these patients are often diagnosed with the chronic diseases of our time with no known etiology as exposed in the “Under our Skin” extended trailer:

Under Our Skin – Extended Trailer (please watch)
https://www.youtube.com/watch?v=sxWgS0XLVqw

There are no guidelines for treating the late stage disabled Lyme patient (who ends up bedridden or in a wheelchair) listed in the recently revised IDSA Lyme Treatment Guideline because that class of patient has been deliberately avoided at all costs so as not to expose the truth while keeping the current paradigm intact.

In fact, the IDSA does not want clinicians to rule out Lyme in patients who have been diagnosed with the chronic diseases of our time:

June article in Medscape by past IDSA president Paul Auwaerter

A Quick Tour of the New Lyme Disease Guideline
https://www.medscape.com/viewarticle/951589

Paul G. Auwaerter, MD

June 14, 2021

Excerpt:

“Of importance, the guideline goes out of its way to cite the lack of evidence for performing Lyme disease tests, specifically routine testing in cases where there’s no evidence or link to Lyme disease. Examples include someone who is asymptomatic after a tick bite, even when they have a neurologic condition such as amyotrophic lateral sclerosis, multiple sclerosis, Parkinson’s disease, dementia, or any kind of new-onset seizures or psychiatric illness. In children, behavioral and developmental disorders don’t warrant assessing a Lyme disease serology.”

____________________________________

I sent an email to Dr. Auwaerter pointing out that a recent study identified tick-borne infections in nine out of ten institutionalized adolescents: [v] [vi]

Study detects tick-borne illness in teens hospitalized for depression
https://www.lymedisease.org/hospitalized-teens-lyme-depression/

-Ten patients were diagnosed with DSM-5 Major Depressive Disorder, seven were additionally diagnosed with Generalized Anxiety Disorder, and three had made serious suicide attempts.

-Ten adolescents picked at random with mental illness severe enough that they required institutionalization— nine of them had evidence of tick-borne infections and nine had evidence of autoimmune encephalitis.

__________________________________________

Instead of playing along with the dishonesty by avoiding the truth/evidence that Lyme is a disabling disease, our public health officials responsible for this travesty should be thoroughly investigated and held accountable to ensure this atrocity will never repeat itself.

Summary:

Stop focusing on the early stage of Lyme disease with bulls-eye rash and find a cure for all stages of the disease. Include patients in this study who are horribly disabled by an infection capable of destroying lives, ending careers while leaving its victims in financial ruin as reported by the Lyme patient population for the past thirty years!

Respectfully submitted,

Carl Tuttle
Hudson, NH

References (please read them!)

  1. NEWS: Former patient who testified as a child about Lyme disease recalls encounter with Sen. Ted Kennedy 
    https://www.lymedisease.org/186/
    Evan White testified from his wheelchair in 1993 at Senator Ted Kennedy’s Hearing, Washington DC
    Excerpt: 
    “No one could hear or feel the moment of that child and not be moved,” Kennedy explained to the [Boston] Globe at the time. Anyone who wasn’t moved, he said, “hasn’t got a heart.”
  2. Feb 4, 2020 complaint regarding the misuse of taxpayer dollars  https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/25876147
  3. Subjective Symptoms after Treatment of Lyme Disease  https://reporter.nih.gov/search/14E9C8084784C1D47598B8961CAA4A01A2FFCEB861BF/projects?shared=true&legacy=1
  4. Lyme borreliosis: diagnosis and management  https://www.bmj.com/content/369/bmj.m1041/rr-1
  5. A Quick Tour of the New (IDSA) Lyme Disease Guideline  https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/29231613
  6. A Quick Tour of the New (IDSA) Lyme Disease Guideline #2  https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/29263852

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/3146

FDA draft guidance addresses clinical development of drugs to treat early Lyme disease Part 2

Carl Tuttle

Hudson, NH, United States
APR 4, 2023 — 

As a follow-up to my previous comment to the FDA regarding “drugs to treat early Lyme disease,” please take a moment to read the comment below registered by the team at TruthCures. We all agree that early Lyme with bulls-eye rash does not represent the entire patient population and has been used by the IDSA and CDC to control and manipulate the narrative in order to support the vaccine business model of patent royalties and pharmaceutical profits. Chronic Lyme disease DOES NOT fit that model!

Comment from TruthCures:

Response to Docket No. FDA-2022-D-2315 for “Early Lyme Disease as Manifested by Erythema Migrans: Developing Drugs for Treatment”

As a patient advocacy organization working to bring valid diagnostics and effective treatments to people with Lyme disease (LD), TruthCures supports innovation in therapeutics and properly designed trials to ascertain their efficacy. Thank you for the opportunity to comment on this guidance.

Trial Population

The trial population suggested in this guidance consists of “…subjects with early localized (i.e., a single EM lesion) or early disseminated (i.e., multiple EM lesions) disease, who reside in or traveled to a Lyme-endemic area.” Limiting any therapeutic trial to only cases presenting with erythema migrans (EM) rash will restrict the trial population to a minority cohort that may not be representative of the broader patient population.

The Centers for Disease Control and Prevention (CDC) estimates 476,000 LD cases in the United States each year (Kugeler et al 2021). However, in 2020, only 44,937 LD cases were reportable as “confirmed” or “probable” based on CDC surveillance criteria (CDC 2020). For diagnosis of a reportable case of early LD, CDC surveillance criteria require either a physician-diagnosed EM rash or laboratory confirmation of infection by methods that may include culture, nucleic acid amplification, immunohistochemical assay on biopsy or autopsy tissues, or two-tier serological testing (CDC 2022).

In clinical practice, diagnostic criteria set forth by the Infectious Diseases Society of America are virtually indistinguishable from the CDC surveillance criteria (IDSA 2006). With both sets of criteria requiring physician-diagnosed EM rash and/or laboratory confirmation, it stands to reason that the vast majority of EM rashes are being counted in the reported surveillance cases. In the public discourse, the absence of such context promotes a misconception that the prevalence of EM rash is based on the total of LD cases rather than the reported cases, creating an inflated perception of the prevalence of EM rash with Lyme.

A simple mathematical analysis illustrates the staggering difference between the narrative and reality.

● The literature frequently cites an EM rate of 60% – 80% (IDSA 2006, Steere et al 1998, CDC 2021). For calculation purposes we will use 70%.
● The public incorrectly believes EM cases are calculated as 70% of 476,000, or 333,200.
● Published studies state the EM rate is calculated based on reported LD cases—those meeting the IDSA and/or CDC surveillance reporting criteria (Kugeler 2020, Smith et al 2002, Seltzer et al 2000). For 2020, EM cases
would be 70% of 44,937, or 31,456.
● Therefore, the effective rate of EM is about 6.6% (31,456 out of 476,000).

It should not have to be said that results of a treatment trial limited to 6.6 percent of patients would not necessarily extrapolate to the entire Lyme disease patient population—particularly when it is unclear why the minority exhibit a distinct cutaneous manifestation. Indeed, Kannangara and Patel note, “EM seems to correlate more with the arthropod than the associated pathogen. The common belief is that EM is caused by B. burgdorferi. The presence of an organism in a skin biopsy culture or PCR does not necessarily mean that it is the cause of EM.” (Kannegara 2020)

Efficacy Endpoints

From the guidance document:

“Clinical success should be defined as resolution of EM and continued absence of objective manifestations of Lyme disease without need for additional antibacterial treatment for Lyme disease.”

“Clinical failure should be defined as the presence of unresolving or recurrent EM, objective manifestations of Lyme disease, or the need for additional antibacterial treatment for Lyme disease.”

Remission of cutaneous symptoms has not been determined to correlate with disease cure (IDSA 2006, Steere et al 2016, Feder et al 2011), and, as is common knowledge, there is no diagnostic method available to determine either cure or disease stage.

It is commonly reported in the literature that EM rash resolves on its own in three to four weeks (Kardos 2002, Feder 1993, Nadelman 1997, Wheaton 2012, Dressler 1999). Therefore, the definition of clinical success (“resolution of EM”) could not necessarily be attributed to the treatment. Likewise, clinical failure could not be attributed to lack of efficacy if efficacy itself is not ascertainable. Lacking the ability to determine success or failure based on EM resolution, an alternative would be to run a separate trial to determine whether the therapeutic has any effect on time to resolution of EM.

Additionally, there is the possibility that patients present with EM rash and no other symptoms. In these cases, without the ability to correlate disease cure with resolution of EM, there is no other way to gauge efficacy of a therapeutic.

Conclusion

Using only patients who present with EM rash for a therapeutic efficacy trial would exclude 93% of patients, with no insight into the factors (e.g. genetic or comorbidities) that cause certain people to develop the rash. Resolution of EM rash is not an indication that Lyme disease has been cured or spirochetes eradicated.

TruthCures’ mission is to enable Lyme disease victims to obtain a valid diagnosis and effective medical care. While we support endeavors to discover novel treatments, we believe valid diagnostics must come first. As long as Lyme disease cannot be accurately and consistently diagnosed, therapeutics cannot be developed for the right patients using the right efficacy endpoints.

Following a complaint to FDA’s Office of Criminal Investigation, TruthCures presented to investigators in-person, in October 2021. We provided evidence that Lyme disease diagnostics have been predicated on improperly cleared devices going all the way back to 1995. The investigators agreed with our diagnostic device regulatory expert’s assessment of those devices. We suggest focusing FDA’s Lyme disease efforts on completing that investigation so valid tests can be developed and marketed rather than daisy-chaining off a manipulated standard.

It is well known that seronegative Lyme presents one of the biggest challenges in validating diagnostics. The gap between reported surveillance cases (44,937 in 2020) and CDC’s estimated annual cases (476,000) indicates more than 400,000 patients per year may be falling through the cracks due to the inability of serology to properly diagnose them. Many of these victims lose everything—family, friends, job, home, retirement savings, education, and more—due to chronic illness and the stigma of having a “contested” disease. We respectfully request you take a step back and reassess whether it makes sense to produce any guidance that effectively leaves those patients out of the equation once again.

REFERENCES

  • Kugeler KJ, Schwartz AM, Delorey MJ, Mead PS; Hinckley AF. Estimating the
    Frequency of Lyme Disease Diagnoses, United States, 2010-2018. Emerg Infect Dis
    2021;27: 616-619.
  • Centers for Disease Control and Prevention. “2020 Lyme Disease Data: Provisional Data.” Centers for Disease Control and Prevention, 2020,https://www.cdc.gov/lyme/datasurveillance/provisional-lyme-cases.htm
  • Centers for Disease Control and Prevention. “2022 Lyme Disease Surveillance Case Definition.” Centers for Disease Control and Prevention, U.S. Department of Health and Human Services, 1 Jan. 2022, www.cdc.gov/lyme/resources/2022-surveillance-case-definition.html
  • Infectious Diseases Society of America. “The Clinical Assessment, Treatment, and Prevention of Lyme Disease, Human Granulocytic Anaplasmosis, and Babesiosis: Clinical Practice Guidelines by the Infectious Diseases Society of America.” Clinical Infectious Diseases, vol. 43, no. 9, 1 Nov. 2006, pp. 1089-1134.
  • Steere AC, Sikand VK, Meurice F, et al. Vaccination against Lyme disease with recombinant Borrelia burgdorferi outer-surface lipoprotein A with adjuvant. N Engl J Med. 1998;339(4):209-215. doi: 10.1056/nejm199807233390401.
  • Centers for Disease Control and Prevention. “Signs and Symptoms of Untreated Lyme Disease.” Centers for Disease Control and Prevention, U.S. Department of Health and Human Services, 2021. https://www.cdc.gov/lyme/signs_symptoms/index.html
  • Smith, R. P., Schoen, R. T., Rahn, D. W., Sikand, V. K., Nowakowski, J., Parenti, D. L., …& Steere, A. C. (2002). Clinical characteristics and treatment outcome of early Lyme disease in patients with microbiologically confirmed erythema migrans. Annals of Internal Medicine, 136(6), 421-428.
  • Seltzer, E. G., Gerber, M. A., Cartter, M. L., Freudigman, K., & Shapiro, E. D. (2000). Long-term outcomes of persons with Lyme disease. JAMA, 283(5), 609-616.
  • Kannangara, Don Walter and Patel, Pritiben. “Report of Non-Lyme, Erythema Migrans Rashes from New Jersey with a Review of Possible Role of Tick Salivary Toxins.” Journal of Medical Entomology, vol. 57, no. 1, 2020, pp. 28-34.
  • Kardos, Marton, et al. “Erythema migrans resolving without antibiotic treatment in a patient with confirmed Lyme disease.” Journal of the American Academy of Dermatology, vol. 47, no. 3, 2002, pp. S204-S207. doi: 10.1067/mjd.2002.123625.
  • Feder, Henry M. Jr., et al. “A Critical Appraisal of ‘Chronic Lyme Disease’.” New England Journal of Medicine, vol. 328, no. 7, 1993, pp. 921-924. doi: 10.1056/NEJM199304013281311.
  • Nadelman, Robert B., et al. “Does this Patient Have Lyme Disease?” Annals of Internal Medicine, vol. 127, no. 12, 1997, pp. 1109-1113. doi: 10.7326/0003-4819-127-12-199712150-00005.
  • Wheaton, Anne J., et al. “Lyme Disease in Primary Care Practice.” Journal of the American Board of Family Medicine, vol. 25, no. 6, 2012, pp. 817-820. doi: 10.3122/jabfm.2012.06.120055.
  • Dressler, Franz, et al. “The Clinical Spectrum and Treatment of Early Lyme Borreliosis in Patients with Skin Manifestations Only.” Journal of the American Academy of Dermatology, vol. 41, no. 3 Pt 1, 1999, pp. 1-7. doi: 10.1016/S0190-9622(99)70134-7.
  • Steere, A. C., Strle, F., Wormser, G. P., Hu, L. T., Branda, J. A., Hovius, J. W., … & Stanek, G. (2016). Lyme borreliosis. Nature Reviews Disease Primers, 2, 16090.
  • Feder, H. M., Johnson, B. J., O’connell, S., Shapiro, E. D., Steere, A. C., Wormser, G.P., & Ad Hoc International Lyme Disease Group. (2007). A critical appraisal of “chronic Lyme disease”. New England Journal of Medicine, 357(14), 1422-1430.