Archive for the ‘Activism’ Category

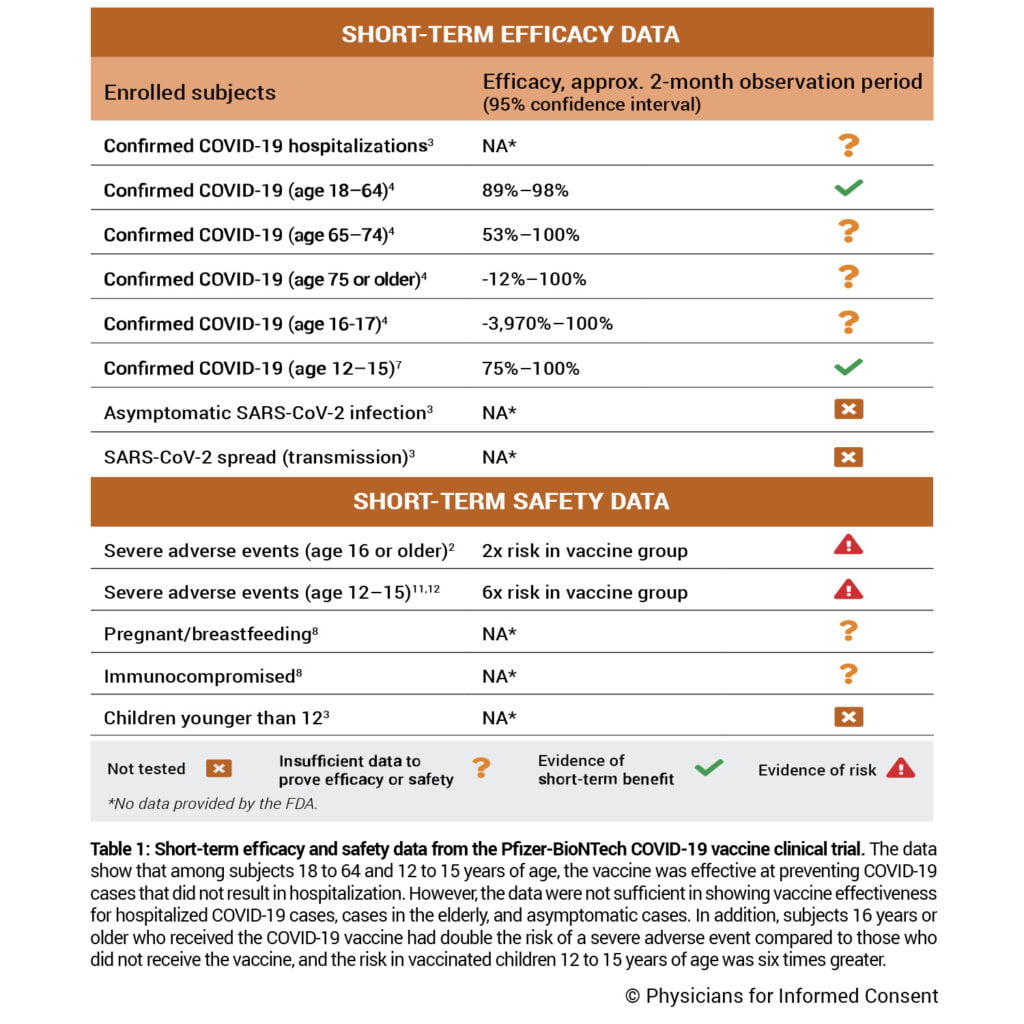
1 in 9 “Vaccinated” Adolescents Suffered a Severe Adverse Event

https://physiciansforinformedconsent.org/physicians-for-informed-consent-updates-its-pfizer-biontech-covid-19-vaccine-risk-statement-for-healthcare-providers-and-families/PIC fact-checks the fact-checkers on a regular basis. Check out our press releases and posts on social media. It takes our volunteers hundreds of tireless hours to bring PIC’s education initiatives to the public.

Educational document highlights Pfizer clinical trial finding that 1 in 9 vaccinated adolescents suffered a severe adverse event

NEWPORT BEACH, CALIF. (PRWEB) JUNE 8, 2021

Physicians for Informed Consent (PIC), an educational nonprofit organization focused on science and statistics, recently published an update of its Pfizer-BioNTech COVID-19 Vaccine Risk Statement, which includes key questions and answers about the clinical trial data. The Pfizer COVID-19 vaccine is the first COVID-19 vaccine to receive expanded emergency use authorization (EUA) for adolescents; however, the vaccine is still not FDA-approved.

The PIC Pfizer-BioNTech COVID-19 Vaccine Risk Statement (VRS) answers important questions such as:

  • How effective is the vaccine in children, adults, and the elderly?
  • Is the vaccine effective in preventing hospitalizations and deaths?
  • Is the vaccine effective and safer than the COVID-19 virus?
  • Does the vaccine prevent the spread of the virus?

The updated document indicates that for children 12 to 15 years of age, the Pfizer COVID-19 vaccine clinical trial found the overall incidence of severe adverse events during the two-month observation period to be 10.7% or 1 in 9 in the vaccinated group. In addition, the incidence of COVID-19 in the unvaccinated group was 1.6%; therefore, there were almost seven times more severe adverse events observed in the vaccinated group than there were COVID-19 cases in the unvaccinated group.

Furthermore, since only about 1,100 vaccinated children 12 to 15 years of age were observed in the clinical trial, there were not enough children included in the trial to be able to prove the vaccine is safer than the disease in children 12 to 15 years of age. The chance of a child 0 to 17 years of age contracting SARS-CoV-2 and dying from COVID-19 is 1 in 290,000.

Anyone considering the COVID-19 vaccine must be informed of known and potential benefits and risks, and the extent to which benefits and risks are unknown. For example, the clinical trial did not have enough statistical power to measure the vaccine’s ability to prevent hospitalizations and deaths, and did not assess if the vaccine prevents asymptomatic infection or spread (transmission) of the virus.

“PIC is committed to making the available data more accessible to everyone researching COVID-19 vaccines,” said Dr. Shira Miller, PIC founder and president. “Our concise, reader-friendly document assists healthcare providers and parents in making informed decisions for the children in their care.”

Physicians for Informed Consent’s body of physicians, scientists, statisticians and healthcare workers is trusted by both patients and practitioners for providing scientific data on infectious diseases and vaccines. To download your copy of the VRS “Pfizer-BioNTech COVID-19 Vaccine: Short-Term Efficacy & Safety Data,” visit physiciansforinformedconsent.org/COVID-19-vaccines.

###

VIEW the press release on PRWeb.
SHARE the press release on Facebook.
SHARE the press release on Twitter.
SHARE the press release on Instagram.
SHARE the press release on LinkedIn.


About Physicians for Informed Consent
Physicians for Informed Consent is a 501(c)(3) educational nonprofit organization focused on science and statistics. PIC delivers data on infectious diseases and vaccines, and unites doctors, scientists, healthcare professionals, attorneys, and families who support voluntary vaccination. In addition, the PIC Coalition for Informed Consent consists of more than 250 U.S. and international organizations. To learn more or to become a member, please visit physiciansforinformedconsent.org.

Biden’s FDA Chief Pick Used to Work as Big Pharma Consultant & Has Millions in Pharma Investments

**UPDATE Jan. 15, 2022**

It appears HELP Committee votes 13-8 in favor of Califf’s return to the agency despite Bog Pharma ties.  Well, he’ll be in good company with all the rest who have Big Pharma ties…..

https://www.activistpost.com/2021/12/bidens-pick-for-fda-chief-formerly-worked-as-a-big-pharma-consultant-has-millions-in-big-pharma-investments

Biden’s Pick for FDA Chief Formerly Worked as a Big Pharma Consultant, Has Millions in Big Pharma Investments

By B.N. Frank

The Food and Drug Administration (FDA) is supposed to protect Americans from unsafe products.  They have a long history of not doing so.  One glaring example, earlier this year, the agency approved an Alzheimer’s drug that:

Recently the drug company cut the price for the controversial drug in half.  But I digress.

Decisions that benefit industries while putting Americans at risk seem to be the norm at the FDA.  Experts continue to blame the agency for significantly contributing to the Opioid Crisis.  Nevertheless, Biden’s pick for the new chief has considerable ties to Big Pharma and it’s not going unnoticed. (See link for article)

__________________

Summary:

  • Dr. Robert Califf was FDA commissioner during the last year of the Obama administration.
  • According to the article he “skated” through a congenial Senate confirmation hearing on Tuesday with the only stumble occurring when pressed about the FDA’s role and failings in the opioid crisis.
  • Califf has made millions as a consultant for more than a dozen pharmaceutical corporations and holds millions more in pharmaceutical investments (at least 8 million).
  • Nine out of the last 10 FDA commissioners went on to work for Big Pharma or serve on a prescription drug company’s board of directors.
  • Go to top link for the senate confirmation hearing.

For more: 

Harvard Scientist Dr. Lieber Found Guilty. Nanowires, DOD, CCP, Wuhan, COVID, 5G, Carbon Nanotubes, Military “Vaccines”, Spike Ferritin Nanoparticles & More

https://www.the-scientist.com/news-opinion/harvard-chemist-found-guilty-of-lying-about-chinese-funding

Harvard Chemist Found Guilty of Lying About Chinese Funding

In a win for the US Department of Justice’s China Initiative, Charles Lieber was convicted of hiding his financial ties to China from federal agencies.
Chloe Tenn
Dec 22, 2021

Yesterday, after deliberating for just under three hours, a Boston jury found renowned Harvard chemist and nanoscientist Charles Lieber guilty of lying to the US Defense Department and National Institutes of Health about financial support from a Chinese foreign talent program, reports Science. The verdict, which was unanimous, also convicted Lieber for failing to report income from the program on his federal income tax forms or to disclose a Chinese bank account that was used for the payments.  (See link for article)

https://www.newstarget.com/2021-12-22-harvard-scientist-dr-charles-lieber-nanowires-dod-ccp-wuhan-covid-5g-vaccine-bioweapons

Harvard scientist Dr. Charles Lieber, nanowires, DoD, CCP, Wuhan, covid, 5G, carbon nanotubes (CNT), military vaccines, SpFN Spike Ferritin Nanoparticles and more

12/22/2021 / By Mike Adams

File all this under “true conspiracies.” See the two podcasts below for even more details on this breaking story. I went on the Alex Jones Show today for 5 segments to discuss this in more detail. Those segments will be posted below as they are available via Brighteon.

You need to listen to at least the Part 1 Situation Update podcast below to get up to speed (about 45 min) in order to get the full background on this story.

The quick summary summary of the story is that Harvard scientist Dr. Charles Lieber was convicted yesterday on all six counts after lying to authorities about receiving millions of dollars from communist China as he shared his groundbreaking technology with a Wuhan technology institute. (See RT.com) Also arrested were two Chinese nationals, one was a female “academic” who was also a lieutenant in the People’s Liberation Army, and another person caught trying to smuggle biological weapons out of Boston’s Logan airport (MERS and SARS strains).

Dr. Lieber is a genius-level scientist who specializes in exotic nanowire technology and how it interfaces with human neurology and biology. (See link for article)

________________

For more: 

Excerpt:

So, it’s SARS, which is genetically engineered biowarfare agent to begin with. Second, it has gain-of-function properties, which makes it more lethal, more infectious. It has HIV in there. That was confirmed by an Indian scientist … and it looks like nanotechnology [has been used] … An MIT scientist who did a study found that it traveled 27 feet through the air. And that, I guess, was in lab conditions.

GLA Interview With Ross Douthat, NY Times Columnist & Author of “The Deep Places”

https://www.globallymealliance.org/blog/global-lyme-alliance-interview-with-ross-douthat-new-york-times-columnist-and-author-of-the-deep-places?

Global Lyme Alliance (GLA) and Ross Douthat, New York Times Columnist, discuss his journey with Lyme disease and the publication of his new book.
GLA: Can you briefly summarize your experience with Lyme disease?

RD: I first got sick in the summer of 2015, when I was moving with my family from Washington DC to what we thought was our dream house in the Connecticut countryside; I was almost certainly tick-bitten while we were doing the inspection on the house, and I unwisely wandered down into the meadows. But we were still in Washington when I fell apart: It started with a red spot on my neck, which was diagnosed as a boil; them came neck stiffness and headaches, and then a full-body collapse, with terrible migratory pain, insomnia, phantom heart attack, the works. And the doctors in D.C. couldn’t see anything wrong in my bloodwork – my first Lyme tests were negative – and they had no idea what was wrong with me, so they prescribed Xanax and sleeping pills and sent me to a psychiatrist (who, to his credit, told me I probably had a physical illness).

Only when we actually managed to make the move to the northeast, when I had been sick for months, did I see doctors who knew something about Lyme and prescribed a trial of antibiotics. That stabilized me: I was able to sleep and eat again, I stopped going to the ER. But the illness didn’t go away: I was still in pain all of the time, with constantly shifting symptoms all around my body. So at that point I entered the strange world of chronic-Lyme treatment, shuttling between doctors and treatment protocols until – after about eighteen months of simple misery – I finally found one that helped me start to make progress, very slowly, toward the health that now six years later I mostly, but not completely, regained.

GLA: Tell us about your new book. What can others with Lyme & chronic illness hope to get out of reading it? How about those without?

RD: It’s a memoir of the experiences described above, with some details on the history of the Lyme disease debate worked in: It’s partially a medical odyssey, partially a family drama, partially a real-estate horror story with our dream house playing the role of Hill House or the Overlook, and partially a psychological and sometimes spiritual story about what it’s like to live with a disease that official medicine isn’t even sure exists. To people with chronic illness, I hope that it offers a mixture of recognition – meaning that they’ll be able to see their own experiences mirrored in some of my mine – and encouragement, evidence that it’s actually possible to make real progress against even the most intractable-seeming disease. To people outside this world, I hope its testimony will make it possible to see a little more clearly just how serious these mysterious chronic illnesses can be: Whether or not they’re fully convinced of the reality of Chronic Lyme specifically, I want them to be convinced that these kind of illnesses aren’t just a matter of a few aches and pains blown out proportion, that they can really steal your life away, and that they deserve an attention from official medicine that they do not currently receive.

GLA: When and where can we buy it?

RD: Anywhere and everywhere (hopefully), from Amazon to your local bookstore.

GLA: What made you speak out and share your story?

RD: Well, I write for a living, so having something this interesting and harrowing happen to me was natural fodder for my work. They say that you should write what you know, and I now know more about this subject than I ever expected, and it’s one of those stories that you just feel like you have to tell – indeed it’s kind of a relief to have it finally out in the world, after I’ve lived inside it for so long.

So that’s the personal side. And then more practically I felt that the only way that our understanding and treatment of these kind of conditions will get better is if people speak out and describe what it’s like to actually go through it, what chronic Lyme is like from the inside – so I hope I’ve helped with that kind of public understanding, even a little bit, by putting my story out in public. And then finally, regardless of what happens with the medical establishment or the culture, I hope that people who are going through the experience themselves will be able to take a certain kind of help and solidarity from my story, and feel a little more encouraged, a little less alone.

~Ross Douthat (C) Abigail Douthat
GLA: How did your experience with Lyme change you? How did your family and friends act during this time?

RD: My friends and family acted as well as anyone could be reasonably expected to act, confronted with a mysterious and medically-controversial illness that for months and years I couldn’t figure out how to treat. Which is to say that people who have to live with the chronically ill have their own kind of challenges, and in the cases of spouses and family, their own particular afflictions, the burden of which needs to be taken seriously in thinking about the scope of suffering caused by this kind of disease.

As for how it changed me – well, at my best I would say that it has made me more appreciative of the ordinary graces of life, the kind of simple things that you take for granted until they’re taken from you. I would also say that it’s made me considerably more open-minded about the sheer weirdness and mystery inherent in reality, all the things that still fall outside, or on the fringes, of what the current scientific consensus understands. Which is not to say that I’ve become anti-science; most of the things that helped me get better were, in their own way, scientific, the results of research or experimentation or both. But I have a new appreciation, shall we say, for the ways in which actual science and the current scientific consensus aren’t always one and the same.

GLA: Were you surprised about the reaction to the recent op-ed and the amount of attention it received?

RD: No, not really: These kind of conditions are extremely common, hard to talk about, and surrounded by clouds of skepticism, so I took it for granted that once I wrote about the full weirdness of my experience I would get some kind of strong reaction – and I wasn’t disappointed!

GLA: What if any recommendation do you have for convincing the NIH, CDC, and IDSA that Lyme and tick-borne diseases are chronic in nature and constitute a major, growing epidemic in the United States?

RD: The simplest answer is that they should consider funding tests of antibiotic treatment for chronic Lyme symptoms that actually follow the methods that doctors who have had success treating chronic patients. Doing this is difficult, as I write in my book, because the treatment protocols are so complex, so tailored to the individual patient, and take so long to really work that it’s hard to design a normal controlled study. But I think we can do better than the current alleged “gold standard” studies, which have looked at the effects of taking a single antibiotic for an extra 4-11 weeks. We need studies that look at the effects of multiple antibiotics, over longer periods of time, which “pulsing” and other mechanisms worked in, and with coinfection diagnosis and appropriate treatment included as well. Those would take work and effort and funding, but it should be possible to set them up. From what I’ve seen and read and experienced, it’s no surprise that studies that just give chronic patient an extra few weeks of antibiotics, even IV antibiotics, don’t show results, because for doctors who treat long term, that’s not what usually *gets* results.

GLA: Will you make any changes in your lifestyle or behavior now that you’ve been through this?

RD: You mean, besides showering more often after going in the woods? I think the biggest changes I’ve tried to make are psychological – trying to sustain the feeling of gratitude and appreciation that I get from ordinary experience on the days when I’m feeling a lot better.  Of course I try to eat healthier and get more exercise, but I’m not sure I’m that much more successful at either now than before. I do think – or hope, at least – that in addition to being more open-minded than I used to be, I’m also somewhat more charitable: Because the cliché, that you never know what someone is going through in secret, is really, really true.

GLA: Ultimately, these advances will allow us to find a cure for Lyme disease and other tick-borne illnesses. How would you encourage patients embarking upon their Lyme journey? What do you wish you had known when you first started out?

RD: Honestly I hesitate with this kind of question because if I’d known when I started out exactly how hard the road back toward would health would be, it would have been the opposite of encouraging! But I suppose the best thing to say is that you need to be realistic and optimistic at the same time. If you get very sick before you get diagnosed, it really can be difficult to get better, and nobody should sugar-coat that for you. At the same time, you really *can* get better, which on the worst days can be impossible to believe. So being able to keep going over a long haul of recovery – months when you hope for weeks, years when you hope for months – is really essential, and one of the things that you should keep you going is the knowledge that so many other people have made this journey, or are making it right now, and their experiences prove that progress is possible, recovery is possible, and everything that you need to do and try in order to get there will seem worth it, eventually, in the future that’s waiting for you even now.

For more: https://madisonarealymesupportgroup.com/2021/12/07/deep-places-explores-one-mans-lyme-fight/

More Children Have Died From COVID Shot Than From COVID & CDC Walensky Lies About Myocarditis

Despite the fact Vietnam has paused COVID shots due to a spate of deaths and adverse events, the CDC admits the shots put you are risk for heart inflammation and heart disease, and heart attacks, the Biden Administration continues to peddle them with abandon, even using the patriotism card, and supposedly uniting across the political aisle. This recent video also shows the completely contradictory advice from corrupt public health ‘officials.’  They are even pushing the jabs via commercials.

But a reality check shows a new study out of South Africa on the Omicron variant which demonstrates reality and history:

  • 80% lower risk of hospitalization
  • 70% lower risk of severe illness
So much for the dire prediction of severe illness and death for the leprous unvaccinated.

And, as if we didn’t see this coming a mile away:  Anthony Fauci just stated this past weekend that you will not be considered fully “vaccinated,” unless you are up-to-date on booster shots.

As of December 10, the Vaccine Adverse Events Reporting System (VAERS) had 8,515 cases of anaphylaxis possibly associated with COVID vaccines in the United States, also see the latest VAERS reporting here.

https://articles.mercola.com/sites/articles/archive/2021/12/21/more-children-died-from-vaccine-than-from-covid

More Children Have Died From COVID Shot Than From COVID

Analysis by Dr. Joseph Mercola Fact Checked
more children died from vaccine than from covid

Story at-a-glance

  • One team published an engineering analysis to determine the current underreporting factor (URF) from the VAERS information and found the factor to be 41. When applied against the government data they found 173% more children died from the vaccine than from the illness
  • Using this same URF, the number of deaths from COVID rose to 815,326 and the number permanently disabled to 1,338,404. To date, the total reported deaths from the infection is 803,043, which means the shot has killed more children and adults than the virus
  • Although there is little reason to give children the shot, officials are spinning the idea that it is needed for herd immunity. Yet, health officials must be aware there is a significant lack of evidence to support this, and children are dying in the process
  • Pilot deaths and injuries affect commercial flights, logistical distribution of goods and military readiness. In one affidavit as part of a federal lawsuit against the military vaccine mandate, physician Lt. Col. Theresa Long alleges protocols are not followed after the COVID shot

Many scientists and health experts have warned that vaccinating children against COVID-19 is unnecessary and extremely risky. Since the beginning of the pandemic, it has been obvious that children were at exceptionally low risk for hospitalization and death from the infection.1 Despite this, massive efforts are underway to ensure that every child gets a shot.

If the current data from the Vaccine Adverse Events Reporting System (VAERS)2 are any indication of what the future holds, we are facing the greatest public health calamity in modern history. I believe it is not a new COVID-19 variant causing this, but the current vaccination campaign. Unfortunately, I have no doubt that the deaths caused by the vaccines will end up far exceeding the number of deaths from the illness.

Despite the clear and present dangers of this genetic therapy, vaccine makers, encouraged and endorsed by government health agencies, are steamrolling ahead with trials and recommendations for the shot in children. In May 20213 parents found out that their children can get vaccinated without their consent if they fall under something called the “mature minor” doctrine.

This allows providers to treat minors, without parental consent, under certain circumstances. The age group under question was between ages 14 and 18 when there is a “rebuttable presumption of capacity, and the physician may treat without parental consent unless the physician believes that the minor is not sufficiently mature to make his or her own health care decisions.”

In July, two lawsuits were filed in federal court that challenged the Washington D.C. city law which allowed minors to be vaccinated without parental consent.4 In September 2021, The Guardian reported that children aged 12 to 15 in the U.K. may be administered a COVID-19 shot by teams in the school system without parental consent.5

If parents do not consent but the child wants the vaccine, the team can determine if a 12-year-old is able to make an informed decision. Most recently, one California mother spoke to the news media and expressed outrage after the school system allegedly offered her son a pizza in exchange for his taking the genetic therapy shot.6

With each passing month, it becomes more obvious that the battleground in the fight for liberty and freedom has been taken to our young children. A recent review of data7 from the CDC and the Vaccine Adverse Event Reporting System (VAERS) shows that more children have died from the vaccine than have died from the illness.

VAERS Underreporting Factor Affects Data

To compare the number of deaths from COVID illness against those who have died from the genetic therapy injection, we must address the known underreporting factor in VAERS. To date, the VAERS database is the only reporting system used by the CDC and FDA that is accessible to the public. According to VAERS, it:8

“… is a passive reporting system, meaning it relies on individuals to send in reports of their experiences. Anyone can submit a report to VAERS, including parents and patients.”

Additionally, it is the only area where the public, including doctors and other medical professionals, can voluntarily report vaccine adverse events, including death. According to VAERS,9 health care professionals are mandated by law to report serious injury adverse events that occur within a specified time period after the shot, and those events that are listed by the manufacturer as a contraindication to further doses.

However, the system only “encourages” providers to report events after vaccination whether the shot caused the event or not. In other words, the system depends on the health care professionals’ knowledge that the VAERS system exists and their willingness to spend time filling out the document which asks for:10

Medical information and history on the patient The facility where the injection was given
The contact information on the person completing the form The vaccine type, manufacturer and lot number
The best doctor or healthcare professional to contact about the adverse event What area of the body where the vaccine was injected
A description of the adverse events and treatment The results or outcome of the adverse events
Medical tests and laboratory results that were done Any vaccines that were given in the month before the genetic therapy injection was given.
The manufacturer, lot number and site where those additional injections were given Any adverse events to any previous vaccines the patient may have had
The patient’s race and ethnicity The date and time the adverse event started
The patient’s age at the time of vaccination Allergies to medications, foods or other products
Whether the patient was pregnant at the time of vaccination Any illnesses in the month leading up to the vaccination
Any chronic or long-standing health conditions Any prescriptions, over-the-counter medications, dietary supplements or herbal remedies being taken at the time of vaccination

While much of this information is necessary for data tracking, you can see how the time-consuming nature of filling out this form can easily become overwhelming when doctors have multiple patients with adverse events from the COVID-19 shots.11 Lack of knowledge of the system, and a growing physician shortage12 with subsequent lack of time have also likely contributed to the underreporting factor (URF).

In an early grant report submitted by the U.S. Department of Health and Human Services, which is part of the VAERS system, the writers admitted that:13

“Although 25% of ambulatory patients experience an adverse drug event, less than 0.3% of all adverse drug events and 1-13% of serious events are reported to the Food and Drug Administration (FDA). Likewise, fewer than 1% of vaccine adverse events are reported.”

As of December 3, 2021, there were 946,461 adverse events and 19,886 deaths reported to the system.14 If only 1% of the events are reported, this translates to 94.64 million adverse events and 1.98 million deaths. To ascertain a better estimate of how many people have been injured from the current genetic injection, the issue of the URF was again addressed in a paper published in November 2021.15

The process for defining a new URF was published in a 62-page paper.16 Using an engineering analysis of the available data and judgment based on peer reviewed literature and expertise of the scientists, an underreporting factor of 41 was determined.

Agency Data Show 173% More Children Died From Shot Than Virus

In this short video, you’ll hear just several of the stories of parents who are grieving the loss of their children after giving them a “vaccine” they were promised would protect them. Many, thinking they were doing the right thing, took an experimental shot and have left devastated parents and families behind.

While evaluating the data, one of the writers of the paper, Steve Kirsch, recognized the gravity of the situation as it relates to the number of children who have died after taking the vaccine versus the number who have died from the illness. CDC data ending December 8, 2021,17 shows 757 children younger than 18 were listed as casualties of COVID-19.

He points out that many of these deaths, like those in adults, are likely children who died with COVID and not from COVID.18 However, to maintain simplicity, he used those numbers for comparison. Then, using data from VAERS ending December 3, 2021, he found 32 deaths from the vaccine.

Using the URF of 41, this suggests there have been 1,312 deaths that are likely to have been caused by the injection as compared to the 757 deaths the CDC records as having been caused by the illness. If you do the math, this means the shot has killed roughly 173% more children than the illness.

Using the same URF of 41 and the current data ending December 3, 2021, from OpenVAERS we can estimate there should have been 38,804,901 reports and 815,326 deaths. This is vitally important as the total number of deaths recorded for COVID-19 as of December 15, 2021. is 795,839.19 This means the shot has currently killed more children and adults than the virus.

Adverse Event VAERS20 Using URF
Deaths 19,886 815,326
Anaphylaxis 8,432 345,712
Miscarriage 3,230 132,430
Permanently disabled 32,644 1,338,404
Severe allergic reaction 35,009 1,435,369
Hospitalizations 102,857 4,217,134
Bell’s Palsy 11,896 487,736
Myocarditis/Pericarditis 16,918 693,638

Pilot Deaths, Injuries and Shot Mandates Affect Shortage

Pilot deaths and injuries affect commercial flights, logistical distribution of goods and military readiness. In mid-2020, thousands of pilots were laid off or decided to retire when flights were canceled around the country and around the world during lockdowns. Government mandates for the genetic therapy shot have also curbed the hiring of potential aviators.21

It takes up to two years to train a pilot, and Boeing estimates there will be a need for more than 600,000 new pilots over the next two decades. After the release of the shot in 2021, some noted an excessive number of pilot deaths in 2021, versus the number who died in 2019 and 2020.22

As the data on this situation continue to be released, it’s important to note that one Army flight surgeon has also stepped forward to warn that the COVID jab may increase the risk of sudden cardiac death among military pilots.23

Physician Lt. Col. Theresa Long filed an affidavit alleging the Army isn’t following DOD protocols to screen for side effects of myocarditis associated with the Pfizer and Moderna shots. The affidavit is part of a federal lawsuit against the vaccine mandate for the U.S. military. In the affidavit Long claims:24

“… there is no functional myocardial screening currently being conducted … it is my professional opinion that substantial foreseen risks currently exist, which require proper screening of all flight crews. Based on the DOD’s own protocols and studies, the only two valuable methodologies to adequately assess this risk are through MRI imaging or cardio biopsy which must be carried-out.”

In October 2021, The Defender,25 the publication of the Children’s Health Defense, asked a question that many may have overlooked. Are these “vaccine” mandates that appear to be reducing critical services and personnel, such as pilots, health care providers and first responders, an intentional sabotage designed to weaken America and expand control?

The loss of critical pilots is not only the result of death, but also life-altering disabilities after the shot. The Defender26 covered Sen. Ron Johnson’s, R-Wis., expert panel on COVID vaccine injuries, during which a 33-year-old commercial airline pilot from Cleveland, Mississippi, testified about his injuries.

Cody Flint had been healthy with no underlying medical conditions before receiving Pfizer’s genetic therapy injection. His first dose was February 1, 2021. Within 30 minutes he developed a severe headache that evolved into a burning sensation in his neck. Two days later he realized something wasn’t right, but only after having taken his airplane into the air. He described what happened next:27

“I was starting to develop tunnel vision and my headache was getting worse. Approximately two hours into my flying I pulled my airplane up to turn around and felt an extreme burst of pressure in my ears. Instantly I was nearly blacked out, dizzy, disoriented, nauseous and shaking uncontrollably. By the grace of God, I was able to land my plane without incident, though I do not remember doing this.”

The doctors initially told him he had an attack of vertigo and a severe panic attack. However, without a history of either, and a continuing decline of his medical condition, the doctors then told him that ”only an adverse reaction to the Pfizer vaccination or major head trauma could have caused this much spontaneous damage.”

After one year and numerous spinal taps and two surgeries, Flint shared that the “vaccine” stole his career and his future. He spent all his savings to pay his medical bills and his family “is on the verge of losing everything we have.”

Statistical Tricks Behind Fear Mongering

It is important to note here that the claims made by Pfizer that the vaccine is 95% effective is not an effectiveness rating you may imagine. You might think that 95% effective means that the shot protects 95 out of 100 people.

But that is something called a relative risk reduction, which actually is the difference in event rates for both groups being studied.28 In other words, it’s the reflection of the number of “vaccinated” people who got COVID during the trials compared to the number who were not “vaccinated”. If you look at the absolute risk reduction, which is far more relevant for public health measures, you’ll see that number is actually less than 1%.29

This means that out of 100 people who got the injection, it is effective for less than one person. While this makes the vaccine of dubious benefit, it also speaks to the propaganda and fear-mongering vaccine makers and vaccines stakeholders have used to promote the dangerous shot — especially when the National Institutes of Health says absolute risk reduction “is the most useful way of presenting research results.”30

Experts Are Using Herd Immunity Reasoning to Convince Parents

Since children have little reason to get the COVID shot, health officials are spinning the idea that they should be vaccinated for the sake of herd immunity. They want you to believe that not only should you look at the people around you as vectors of disease, but also that children could be asymptomatic carriers and supposedly silently spreading a deadly disease to Grandma’s house.

What they aren’t telling you, and the media is not covering, are the studies that show children are not driving the pandemic, and in fact appear less likely to transmit COVID-19 than adults.31 The Children’s Health Defense noted:32

“In short, public health leaders say, parents must ‘vaccinate the young to protect the old.’ Given the federal government’s estimate that one vaccine injury results from every 39 vaccines administered, it seems clear that officials expect children to shoulder 100% of the risks of COVID vaccination in exchange for zero benefit.“

Herd immunity occurs when enough people have acquired immunity to an infectious disease so that it no longer is widely spread in the community. This is calculated using a reproductive number or R0.33 This is the estimated number of new infections that may occur from one infected person. R1 means that one person who is infected is expected to infect one other person.

When R0 is below 1 it indicates that cases are declining and R0 above 1 suggests that they are on the rise. While it’s far from an exact science, a person’s susceptibility to infection is known to vary depending on factors including age, health and contacts within the community.

The initial calculation for COVID-19 health intervention tracking was based on assumptions that each person had the same susceptibility and would mix randomly with others in the community. However, a study published in Nature Reviews Immunology34 suggested the herd immunity threshold for COVID-19 may need adjustment since children are less susceptible to the disease. The scientists wrote:35

“Another factor that may feed into a lower herd immunity threshold for COVID-19 is the role of children in viral transmission. Preliminary reports find that children, particularly those younger than 10 years, may be less susceptible and contagious than adults, in which case they may be partially omitted from the computation of herd immunity.“

In other words, the idea that we must vaccinate children to protect adults is not backed by evidence in this illness. After decades of studying vaccine research and holding responsible positions in health care, you would hope that individuals like Dr. Anthony Fauci,36 director of the National Institute of Allergy and Infectious Diseases and Dr. Rochelle Walensky,37 director of the Centers for Disease Control and Prevention, should understand the science.

If an assumption is made that these individuals do understand the science that doesn’t support vaccinating children, and they have at least glanced at the VAERS data collected by the CDC and FDA, then you must ask the question — what is the underlying goal of “vaccinating” children with a potentially lethal and disabling shot when they have an exceedingly low risk of severe COVID-19 or dying from the illness?

– Sources and References

___________________

**Comment**

The answer to that question is the key to the puzzle and has ZERO to do with health.

DO NOT COMPLY.

And this telling video details how myocarditis concerns are growing. Jefferey Jaxen goes through the VAERS data as well.  Coroner states they are dealing with multiple cases.