https://www.lifezette.com/2021/12/big-pharma-exec-admits-gene-therapy-marketed-as-vaccines-as-they-push-depopulation-with-gates-klaus

Big Pharma Exec Admits Gene Therapy Marketed As Vaccines As They Push Depopulation With Gates & Klaus

Depopulation fanatics want to force you to inject drugs for your health?

Stefan Oelrich, president of Bayer’s Pharmaceuticals Division, admitted to international “experts” this week that the mRNA COVID-19 shots are indeed “cell and gene therapy” marketed as “vaccines” in order to get trust from the public.

Oelrich said this while speaking at the World Health Summit, which took place in Berlin back in October.

“We are really taking that leap [to drive innovation] – us as a company, Bayer – in cell and gene therapies … ultimately, the mRNA vaccines are an example for that cell and gene therapy. I always like to say: if we had surveyed two years ago in the public – ‘would you be willing to take a gene or cell therapy and inject it into your body?’ – we probably would have had a 95% refusal rate,” Oelrich said.  (See link for article)

https://www.lymedisease.org/multiplex-test-on-horizon/

LYME SCI: A test to find many infections at once is on the horizon

Dec. 13, 2021

By Lonnie Marcum

What if you had access to a single test that could detect 3 different kinds of vector-borne bacteria all at the same time?  Well, it looks like researchers out of North Carolina State University and Galaxy Labs have done just that.

Research led by Ricardo Maggi, Ed Breitschwerdt, and colleagues has led to the development of a new test utilizing a multiplex droplet digital PCR “BBB ddPCR” that can simultaneously detect the three B’s—Babesia, Bartonella and Borrelia from both the Lyme and relapsing fever complex. (Maggi et al., 2021)

Once this combined test is clinically validated and available for clinical use, it will lead to improved diagnostics for patients with Lyme and other vector-borne diseases.

Humans and animals are greatly affected by tick-borne diseases. Currently, 75% of all vector-borne disease cases reported in the U.S. are caused by ticks. And 82% of the tick-borne cases are due to Lyme disease. (Rosenberg et al., 2018)

“Standard” tests fall short

Despite recent advancements for diagnostic testing for other illnesses, the CDC continues to recommend tests for Lyme and other tick-borne diseases that were designed more than three decades ago—and fall way short of what’s needed.

For example, the CDC-endorsed two-tier test for Lyme disease predates a full understanding of the immune response to Lyme disease. It has several technical limitations, including the inability to differentiate between active infection, past infection, and reinfection. (Branda et al., 2018; Schutzer et al., 2019)

The standard test combination also misses 89% of early infection (false-negatives), cannot detect all strains of disease-causing Borrelia, and suffers from cross-reactivity with other infectious diseases leading to false-positives. (Steere et al., 2008; Cook, Puri, 2016)

“The ability to co-amplify multiple vector-borne pathogens within a single sample with high sensitivity will greatly enhance the efficiency and efficacy of clinical diagnostic testing, particularly of volume-limited or otherwise hard to obtain sample matrices,” the authors state.

New approaches needed

New diagnostic approaches have been effectively applied to diseases such as Zika. And COVID-19, a disease discovered less than two years ago, already has better diagnostic tools available to it than tick-borne infections identified nearly a century ago.

Importantly, serology testing for COVID was deemed unreliable and unsuitable for diagnosis, yet serology remains the diagnostic standard of care for tick-borne diseases. (Serology tests look for antibodies in blood serum.)

All tick-borne diseases face major hurdles that prevent accurate early diagnosis and treatment. Serology as a diagnostic standard of care is problematic for all infections, but is especially problematic for immune-evasive, low-abundance infections.

Microbial testing techniques

Commonly used diagnostic techniques for tick-borne diseases include both direct and indirect detection methods, though some are only used in research studies. Both direct and indirect diagnostic methods are prone to false-negative and false-positive results.

For this reason, many experienced Lyme and tick-borne disease practitioners will recommend a combination of both direct and indirect tests, or a series of tests to confirm a diagnosis.

  • Direct detection methods directly confirm the presence of a pathogen. Direct methods for tick-borne diseases include: growing the pathogen in culture; microscopic examination of blood or tissue; polymerase chain reaction (PCR) which detects the DNA of one pathogen; quantitative PCR (qPCR) detects the quantity of a pathogen; multiplex PCR detects DNA of more than one pathogen; and fluorescence in situ hybridization (FISH) “maps” the genetic material in cells.
  • Indirect detection  methods detect the host immune system’s response to infection, providing indirect evidence of infection. Indirect  methods are able to determine if there has been recent or prior exposure to a pathogen. These methods, however, cannot confirm if an infection is active, nor whether it has been cleared. The most frequently used indirect serologic tests for tick-borne diseases include ELISA (enzyme-linked immunosorbent assay); IFA (immunofluorenscence antibody test); immunoblots like the Western blot; enzyme-linked immunospot (ELISPOT); and lymphocyte transformation tests (LTTs). (Springer et al., 2021)

Looking for antibodies

Both direct and indirect detection techniques have their strengths and weaknesses. For example, the most common tests for Lyme disease, the ELISA and Western blot, both  look for antibodies generated as the immune system tries to fight the infection.

Immunocompromised patients who do not mount a proper immune response, or those who receive early treatment may not develop detectable antibodies.

In addition, intracellular, low-yield and stealth pathogens like Borrelia and Bartonella are notoriously difficult to find by direct detection techniques like PCR.

The main reason for this is that little DNA from “low abundance” pathogens is found in blood. If there’s not enough DNA in the blood sample, standard PCR  cannot detect it.

Because of this, blood has not been the preferred sample type for detecting Borrelia burgdorferi DNA by PCR. However, PCR has had more success detecting the relapsing fever species of Borrelia, due to the higher levels of spirochetes in the blood. Conventional PCR, however, can be useful for the detection of Borrelia DNA from skin biopsies of Lyme-associated rashes, the fluid or tissue from joints (synovial fluid and synovium.)

The new approach

The research team, led by Dr. Ricardo Maggi and Dr. Ed Breitschwerdt at NCSU and Dr. Jennifer Miller at Galaxy Diagnostics, based their new multiplex droplet digital PCR assay “BBB ddPCR” on a wealth of knowledge they’ve gained from developing better diagnostics for Bartonella.

They recently published a paper explaining how their “BAPGM enrichment” along with the ddPCR improves upon the standard qPCR for Bartonella. (Maggi et al., 2020)

The proprietary BAPGM™ liquid culture increases the number of bacteria in a blood sample, allowing easier detection by PCR. With the “ddPCR, instead of running one PCR on one sample, the extracted DNA gets generated into 10,000-20,000 droplets. We then run a PCR reaction on each droplet,” explains Amanda Elam, PhD. “Bartonella ddPCR alone is incredible, increasing sensitivity about 10 times over standard PCR.”

The new assay, called the “multiplex BBB ddPCR,” detected DNA from 24 species of Babesia, 31 Bartonella species, and 13 Borrelia species (from the Lyme disease, relapsing fever, and cluster of Borrelia associated with reptiles).

The assay also detected two Theileria species (T. equi and T. cervi), as well as Chlamydophila felis DNA from naturally infected animals.

The authors state, “The multiplex BBB ddPCR assay presented herein reliably detected single and co-infections involving vector-borne pathogens from the genera Babesia, Bartonella, Borrelia, and Theilaria, using a variety of animal and human clinical samples, vectors, and experimentally infected tissues and cell-lines.”

Bringing new tests to market takes time

As Amanda Elam, Phd, CEO & Co-founder of Galaxy Labs, explained during this year’s Invisible International conference, the development process for commercializing a new test, from prototype to clinical validation to FDA approval, can take 5-10 years.

Elam says it may be another two years before the multiplex BBB ddPCR test is available to the public. She anticipates the individual ddPCR tests for Bartonella, Babesia and Borrelia will be available sooner.

The researchers state they have future plans to add other vector-borne organisms such as Anaplasma, Ehrlichia, and Rickettsia species to the existing multiplex ddPCR platform. In my opinion, a single assay able to detect multiple species of the most common tick-borne diseases would have profound effects on both animal and human medicine.

Early diagnosis is critical

Patients who receive early diagnosis and prompt treatment for tick-borne diseases tend to get better. But what about the huge percentage of patients who are not diagnosed quickly? In fact, fewer than 12% of the 14,000+ patients in LymeDisease.org’s patient-led research project, MyLymeData, received a diagnosis within the first month after the tick bite. (Johnson, 2019)

A delayed diagnosis is critical to understanding why so many patients are left with debilitating symptoms after standard treatment for Lyme. (Fallon et al., 2008; Fallon et al., 2012) During the months to years that patients suffer without a diagnosis, the untreated infection spreads throughout the body, embedding itself deeply into connective tissues where standard antibiotics have a hard time reaching. (Cabello et al., 2017; Caskey, Embers, 2015; Embers et al., 2012; Gadila et al., 2021)

One study demonstrated that delaying treatment by as little as 9-19 days is predictive of persistent Lyme symptoms. (Bouquet et al., 2016) During this time, infection can spread to the organs, brain, bone marrow, and heart. (Coughlin et al., 2018; Novak et al., 2019)

Early diagnosis of tick-borne diseases can save lives. Using advanced molecular detection techniques, these researchers have shown how an improved multiplex assay can more rapidly diagnose patients infected with multiple pathogens, speeding the delivery of life saving treatment.

Here’s what we need

We currently need better diagnostic tools for all tick-borne diseases including:

  • Anaplasmosis,
  • Babesiosis (Babesia duncani, Babesia microti),
  • Borrelia miyamotoi disease,
  • Bourbon virus disease,
  • Colorado tick fever,
  • Ehrlichiosis (E. chaffeensis, E. ewingii, E. muris),
  • Heartland virus disease,
  • Lyme disease (Borrelia burgdorferi, B. mayonii)
  • Powassan virus disease,
  • Rocky Mountain spotted fever,
  • Rickettsiosis (R. parkeri, R 364D),
  • S.T.A.R.I. (Southern Tick-Associated Rash Illness)
  • Tick-borne relapsing fever (B. hermsii, B. turicatae, B. parkerii)
  • Tularemia

I’ve written about several other types of advanced diagnostics on the horizon. I look forward to seeing promising tests like these become more widely available.

LymeSci is written by Lonnie Marcum, a Licensed Physical Therapist and mother of a daughter with Lyme. She serves on a subcommittee of the federal Tick-Borne Disease Working Group. Follow her on Twitter: @LonnieRhea  Email her at: lmarcum@lymedisease.org.

References

Bouquet J, et al (2016) Longitudinal Transcriptome Analysis Reveals a Sustained Differential Gene Expression Signature in Patients Treated for Acute Lyme Disease. Am Society Micro. DOI: 10.1128/mBio.00100-16

Branda JA., et al. (2018) Advances in Serodiagnostic Testing for Lyme Disease Are at Hand, Clinical Infectious Diseases, Volume 66, Issue 7, 1 April 2018, Pages 1133–1139, https://doi.org/10.1093/cid/cix943

Cabello FC, Godfrey HP, Bugrysheva JV, Newman SA. (2017) Sleeper cells: the stringent response and persistence in the Borreliella (Borrelia) burgdorferi enzootic cycle. Environ Microbiol 19(10):3846-3862, 2017. doi: 10.1111/1462-2920.13897

Caskey JR, Embers ME. (2015) Persister Development by Borrelia burgdorferi populations in vitro. Antimicrob Agents Chemother 59(10):6288-6295, 2015. DOI: 10.1128/AAC.00883-15

Cook, MJ., Puri BK. (2016) Commercial test kits for detection of Lyme borreliosis: a meta-analysis of test accuracy. Int’l J of Gen Med. DOI https://doi.org/10.2147/IJGM.S122313

Coughlin, J.M., Yang, T., Rebman, A.W. et al. (2018) Imaging glial activation in patients with post-treatment Lyme disease symptoms: a pilot study using [11C]DPA-713 PET. J Neuroinflammation 15, 346. https://doi.org/10.1186/s12974-018-1381-4

Embers ME, Barthold SW, Borda JT, Bowers L, Doyle L, Hodzic E, Jacobs MB, Hasenkampf NR, Martin DS, Narasimhan S, Phillippi-Falkenstein KM, Purcell JE, Ratterree MS, Philipp MT. (2012) Persistence of Borrelia burgdorferi in rhesus macaques following antibiotic treatment of disseminated infection. PLoS One 7(1):e29914, 2012. https://doi.org/10.1371/journal.pone.0029914

Fallon BA, Keilp JG, Corbera KM, Petkova E, Britton CB, Dwyer E, Slavov I, Cheng J, Dobkin J, Nelson DR, Sackeim HA. (2008) A randomized, placebo-controlled trial of repeated IV antibiotic therapy for Lyme encephalopathy. Neurology. 70(13):992-1003. doi: 10.1212/01.WNL.0000284604.61160.2d. Epub 2007 Oct 10. PMID: 17928580.

Fallon, Brian & Petkova, Eva & Keilp, John & Britton, Carolyn. (2012). A Reappraisal of the U.S. Clinical Trials of Post-Treatment Lyme Disease Syndrome. The open neurology journal. 6. 79-87. 10.2174/1874205X01206010079.

Gadila SKG, Rosoklija G, Dwork AJ, Fallon BA and Embers ME (2021) Detecting Borrelia Spirochetes: A Case Study With Validation Among Autopsy Specimens. Front. Neurol. 12:628045. doi: 10.3389/fneur.2021.628045

Johnson, Lorraine (2019): 2019 Chart Book — MyLymeData Registry. (Phase 1 April 27, 2017. Sample 3,903). figshare. Preprint. https://doi.org/10.6084/m9.figshare.7849244

Maggi R, Breitschwerdt EB, Qurollo B, Miller JC. Development of a Multiplex Droplet Digital PCR Assay for the Detection of Babesia, Bartonella, and Borrelia Species. Pathogens. 2021; 10(11):1462. https://doi.org/10.3390/pathogens10111462

Maggi RG, Richardson T, Breitschwerdt EB, Miller JC. Development and validation of a droplet digital PCR assay for the detection and quantification of Bartonella species within human clinical samples. J Microbiol Methods. 2020 Sep;176:106022. doi: 10.1016/j.mimet.2020.106022. Epub 2020 Aug 11. PMID: 32795640.

Novak P, Felsenstein D, Mao C, Octavien NR, Zubcevik N (2019) Association of small fiber neuropathy and post treatment Lyme disease syndrome. PLoS ONE 14(2): e0212222. https://doi.org/10.1371/journal.pone.0212222

Rosenberg R, Lindsey NP, Fischer M, et al. (2018) Vital Signs: Trends in Reported Vectorborne Disease Cases — United States and Territories, 2004–2016. MMWR Morb Mortal Wkly Rep 2018;67:496–501. DOI: http://dx.doi.org/10.15585/mmwr.mm6717e1

Schutzer, S.E., et al. (2019) Direct Diagnostic Tests for Lyme Disease, Clinical Infectious Diseases. 3/15, 68 (6), 1052–1057. doi: https://doi.org/10.1093/cid/ciy614

Springer, A., Glass, A., Probst, J. et al. Tick-borne zoonoses and commonly used diagnostic methods in human and veterinary medicine. Parasitol Res 120, 4075–4090 (2021). DOI: https://doi.org/10.1007/s00436-020-07033-3

Steere, A. C., McHugh, G., Damle, N., & Sikand, V. K. (2008). Prospective study of serologic tests for lyme disease. Clinical infectious diseases : an official publication of the Infectious Diseases Society of America, 47(2), 188–195. https://doi.org/10.1086/589242

https://danielcameronmd.com/lyme-arthritis-in-children-can-present-throughout-the-year/

Lyme arthritis in children can present throughout the year

Lyme arthritis in children

Lyme arthritis in children can present throughout the year for those living in areas endemic for Lyme disease, according to a study by Sundheim and colleagues. In their article, “Seasonality of Acute Lyme Disease in Children,” investigators described 690 children with Lyme disease residing in three endemic regions of the United States. [1]

The study’s objective was to “evaluate the seasonality of pediatric Lyme disease in three endemic regions in the United States,” writes Sundheim. Participants had been treated at 8 different medical centers throughout the Northeast and UpperMidwest.

Of the 690 children with Lyme disease, 77 (11.2%) had a single EM lesion, 247 (35.7%) had early disseminated disease, and 366 (53.1%) had arthritis, wrote the authors. “Children with early and early-disseminated Lyme disease most frequently presented in the summer months (June through August).”

The authors acknowledged that results could not be applied to non-endemic areas of the country, as all the participating centers were located in regions endemic for Lyme disease.

The authors did not routinely test for co-infections. “Multiplex polymerase chain reaction panels for tick-borne co-infections have demonstrated that a substantial portion of adults with Lyme disease have co-infections.”

Editor’s comments: Sundheim et al. dismissed 2,490 children (78.3%) as clinical mimics. It would have been helpful if the authors had followed up these children to determine whether any of them might have presented with Lyme disease over time.

The authors did not appear to look for other manifestations of Lyme disease and focused rather on individuals with “early (single EM lesion), early-disseminated (multiple EM lesions, headache, cranial neuropathy, or carditis), or late (arthritis).”

References:
  1. Sundheim KM, Levas MN, Balamuth F, et al. Seasonality of Acute Lyme Disease in Children. Trop Med Infect Dis. Nov 9 2021;6(4)doi:10.3390/tropicalmed6040196

**UPDATE April 2022**

Similarly to Fauci’s flip-flipping on the uselessness of masks and the “fatal flaw” in the COVID tests, Fauci pre-2019 stated:

“The Most Potent Vaccination Is Getting Infected Yourself” ~ Dr. Fauci

https://www.zerohedge.com/covid-19/another-study-finds-natural-immunity-protects-better-against-infection-pfizer-vaccine

Another Study Finds That Natural Immunity Protects Better Against Infection Than Pfizer Vaccine

by Tyler Durden
Monday, Dec 13, 2021

Authored by Noah Carl via DailySceptic.org,

At the end of August, a study was published showing that natural immunity provides much better protection against infection than the Pfizer vaccine. It was described by UCL’s Francois Balloux as “a bit of a bombshell”.

Subsequent studies have compared natural and vaccine-induced immunity at the cellular level. One found that infection-induced antibodies “exhibited superior stability and cross-variant neutralization breadth” than vaccine-induced antibodies, suggesting that people who’d already been infected had better immunity against the then-novel Delta variant.

However, as I noted in my write-up of the “bombshell” study, its findings still needed to be replicated.

After all, certain datasets or methods of analysis can sometimes yield quirky results, which don’t survive independent empirical tests.

Encouragingly, the findings now have been replicated – by another team of Israeli researchers, using a different data set.  (See link for article)

https://alexberenson.substack.com/p/vaccinated-english-adults-under-60

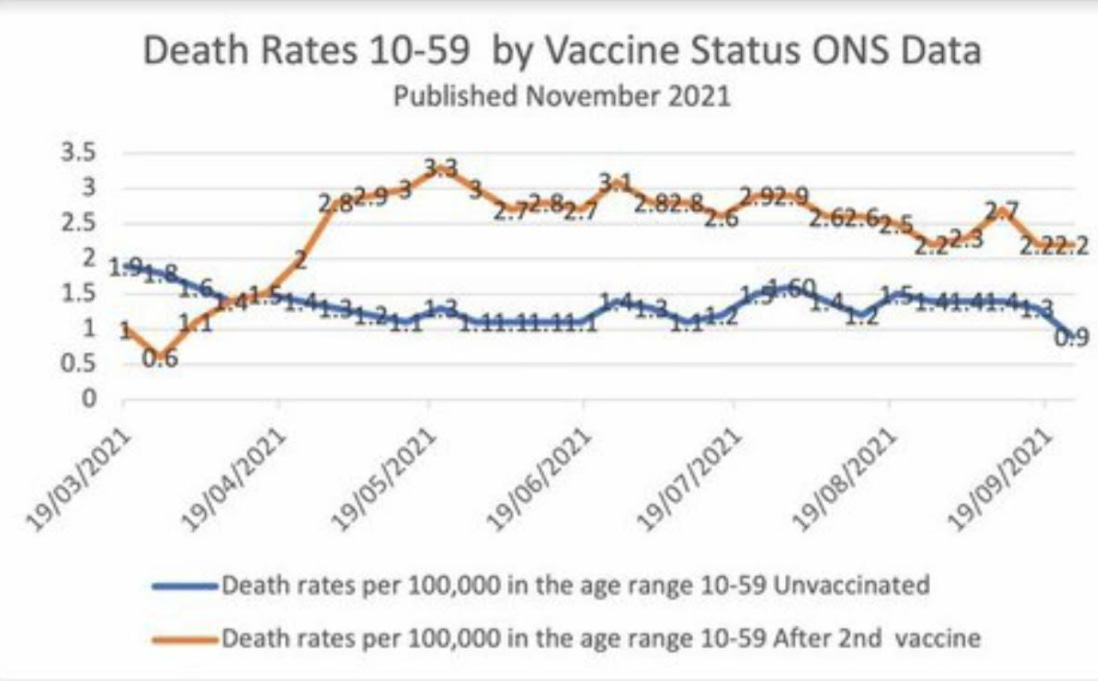
Vaccinated English adults under 60 are dying at twice the rate of unvaccinated people the same age

And have been for six months. This chart may seem unbelievable or impossible, but it’s correct, based on weekly data from the British government.

The brown line represents weekly deaths from all causes of vaccinated people aged 10-59, per 100,000 people.

The blue line represents weekly deaths from all causes of unvaccinated people per 100,000 in the same age range.

I have checked the underlying dataset myself and this graph is correct. Vaccinated people under 60 are twice as likely to die as unvaccinated people. And overall deaths in Britain are running well above normal.  (See link for article)

___________________

**Comment**

In October Berenson posted the COVID injections will prohibit you from acquiring full immunity even if you were infected and recovered from COVID.  He reprinted the following quote from UK Health Security Agency data:

“N antibody levels appear to be lower in people who acquire infection following two doses of vaccination.” (Page 23)

The injections interfere with your body’s innate ability after infection to produce antibodies against the spike protein and other pieces of the virus, which means the “vaccinated” are far more vulnerable to mutations even after infection and recovery.

Further, more data from the UK hows the double jabbed have lost 50% of their immune system capability and are losing a further 4-5% every week.  Further:

Everybody over 30 will have lost 100% of their entire immune capability (certainly for Covid and most likely for viruses and certain cancers – following the evidence from Cole Diagnostics in Idaho and Dr Nathan Thompson and Dr Ralph Baric) within 18 weeks.  Source

The COVID injections wiping out your immunity has been discussed before, by numerous experts.  To watch a board-certified pathologist explain how these shots reprograms the innate immune response, go here.

It’s worrisome that vaccination appears to deplete neutralizing Abs against the Spike protein gained by infection. It’s puzzling that vaccination appears also to deplete neutralizing Abs against the RBD (receptor-binding-domain) SARS-CoV-2 protein because the vaccines do not target that protein. – Dr. James Lyons Weiler

Important quotes:

To boost the immune system to produce more antibodies that do not work is madness. (Regarding boosters)

From an evolutionary standpoint, durable immunity to SARS-CoV-2 is expected to be more resilient and far, far more effective – and last decades – where dozens of types of memory B- and T-cells have been generated, preventing the emergence of types that can surpass the immune escape threshold. Multifactorial approaches to control viremia are also available – and will help reduce viremia in every patient, instead of forcing them to sit at home and incubate new variants (See: Who Are the World’s Leading Authorities in COVID-19 Treatments?).  Dr. James Lyons Weiler  Source

https://thefreethoughtproject.com/new-bill-to-force-the-unvaccinated-to-pay-for-health-care/

unvaccinated

New Bill to Strip the Unvaccinated of Health Insurance if They Get Sick, Force Them to Pay Out of Pocket

To those who are paying attention, the demonization and discrimination against the unvaccinated is eerily similar to extremely dark times throughout human history. These historical events are riddled with the suffering and death of millions of innocent people all because the media and government dehumanized a group of people and convinced the majority that they need to rid themselves of the “unclean.”

Unscientific vaccine mandates are laying waste to human rights across the planet. Lacking all logic and reason, even if you’ve had covid-19 and have superior immunity over someone who only took the jab, you are denied entry into public places and treated like a second-class citizen.

In Australia and Austria, the unvaccinated are fined and even arrested if they attempt to go out in public. Mainstream news outlets across the world continue to shame the unvaccinated, stoking fear and hatred against them over their personal medical choices.

President Biden even took to demonizing the unvaccinated, blaming them for the economic downturn, supply chain debacle, and claimed — without merit — that they are “costing jobs.”

Now, the state of Illinois is taking the segregation and discrimination against the unvaccinated one step further by attempting to strip them of their health insurance if they get sick from covid-19 — forcing them to pay for their medical treatment out of pocket.

“I think it’s time that we say: ‘You choose not to get vaccinated, then you’re also going to assume the risk that if you do catch COVID, and you get sick, the responsibility is on you,’” State Representative Jonathan Carroll told the Chicago Sun-Times this week.

(See link for article)

_____________________

**Comment**

This is so predicable, and has been acutely felt by Lyme/MSIDS patients for 40 years.

Those that claim to be following the “science,” lead by no other than real live Dr. Evil who claims HE IS science, are “trying to do the right thing,” as if the only right thing is taking an experimental, fast-tracked jab that has caused more injury and death than any other vaccine in the 30 years of VAERS.

Further:

  • the latest headlines show hospitalizations are spiking — among the fully “vaccinated”
  • states with the highest “vaccination” rates are currently seeing the highest hospitalization rates, including Vermont, which has more than 72%  fully “vaccinated”
  • New Hampshire’s new daily cases shot up 84% in November (compared with a 7 percent jump over the same period nationwide), despite 63 percent of its population being fully inoculated
  • New Mexico, new daily cases are up 46% in the same period, even though 63%  are fully “vaccinated”
  • New York, Minnesota, Rhode Island, Massachusetts, and California are all seeing similar spikes despite over 60% being “vaccinated”

The ivermectin arm of the U.K’s PRINCIPLE trial is “currently paused due to supply issues,” according to the trial’s website. Guess who manufacturers ivermectin? Merck – the company that was accused of fraud, deceit, negligence, falsifying data, paid $4.85 billion settlement with injured plaintiffs over Vioxx when it did not disclose known heart attack risk in its clinical trial data, and who is in bed with our government, paying it royalties.

Here’s what you need to know:

  • The cost of a complete five-day course of Molnupiravir is $700 — or $70 per pill. That amounts to a 4,000% markup over what it costs Merck to make the drug.
  • Citing 2013 prices provided by the WHO, Campbell said a five-day course of ivermectin — 10 3mg pills — costs $0.53. (However, at today’s U.S. prices, 10 3mg pills cost about $39).

The company said that it has “concluded that the probability of ivermectin providing a potentially safe and efficacious treatment option for SARS-CoV-2 infection is low and have prioritized internal efforts towards the development of alternate candidates that provide a higher probability of success for the treatment of COVID-19.”

Ha, ha, ha….seriously, this is laughable if it wasn’t killing people.

OK, so you know ivermectin works and you are basically taking your marbles and going home to create your own game, a patented drug which will make you a whole lot more money. I get it, out with the old in with the new.

__________________

https://www.theblaze.com/news/judge-holds-hospital-in-contempt-of-court-for-refusing-ivermectin-covid-patient

Judge holds hospital in contempt of court for refusing ivermectin to COVID patient on ventilator, ignoring court order

A Virginia hospital was held in contempt of court Monday after refusing to administer ivermectin to a woman who has been battling COVID-19 since early October.

What are the details?

Kathleen Davies, a 63-year-old northern Virginia woman, became severely ill with COVID in October, and she has been on a ventilator since Nov. 3.

Davies was prescribed ivermectin by her family doctor, but she could not complete her regimen upon being admitted to the Fauquier Hospital in Warrenton. That’s because the northern Virginia hospital refused to administer the drug, “citing medical, legal and practical concerns,” the Fauquier Times reported.  (See link for article)

________________

**Comment**

A family member who works at the hospital urged the hospital to give her ivermectin to no avail. Then in Dec. they took legal action and a circuit court judge ordered the hospital to give her the drug.  The hospital ignored the order.

The hospital is relying on “consensus” medicine and the fact the patient’s doctor does not have hospital privileges.

The judge then ruled that this is not state law and again ordered the hospital to permit giving ivermectin.

Hospital: “Talk to the butt.”

The judge finally held the hospital in contempt of court for “needlessly interposing requirements that stand in the way of the patient’s desired physician administering investigational drugs as part of the Health Care Decisions Act and the federal and state Right to Try Acts.” and imposed daily $10,000 fines retroactive to Dec. 9, 2021.

The judge gave the hospital until 9 p.m. on Monday to administer ivermectin, or he would levy additional fines.

Kathleen Davies was given ivermectin at 8:45 p.m.

And that is what it takes to save lives in the crazy, topsy-turvy world of COVID where experimental, fast-tracked, never approved for human use injections, that don’t stop transmission or infection, are ineffective, and which have caused more adverse reactions and death than any other “vaccine” in 30 years are accepted without hesitation and proven, cheap, effective drugs with decades of safety behind them are denied to dying patients. Please also read this important article on how hospitals get money for utilizing “consensus based” medicine even when it doesn’t work and costs lives.

The hospital payments include:

  • A “free” required PCR test in the Emergency Room or upon admission for every patient, with government-paid fee to hospital.
  • Added bonus payment for each positive COVID-19 diagnosis.
  • Another bonus for a COVID-19 admission to the hospital.
  • A 20 percent “boost” bonus payment from Medicare on the entire hospital bill for use of remdesivir instead of medicines such as Ivermectin.
  • Another and larger bonus payment to the hospital if a COVID-19 patient is mechanically ventilated.
  • More money to the hospital if cause of death is listed as COVID-19, even if patient did not die directly of COVID-19.
  • A COVID-19 diagnosis also provides extra payments to coroners.

Please see this article where ivermectin saved more patients from the jaws of death.

“Consensus based” medicine starts at the top with corrupt public health agencies, but 12,700 doctors and scientists have signed the Rome Declaration and have endorsed ivermectin as a COVID treatment.

An internist ultimately administered a five-day course of 24 milligrams of ivermectin, from November 8 through November 12.  The doctor stated: “Every day after ivermectin, there was accelerated and stable improvement,” said Dr. Bain, who administered the drug in two previous court cases after hospitals refused. “Three times we’ve shown something,” he told me. “There’s a signal of benefit for ventilator patients.”

  • With only a 10-20% chance of survival, the judge listed ivermectin’s possible side-effects from a government website: dizziness, pruitus, nausea/diarrhea, and stated that effects were so minimal that the patient’s condition outweighs risks by 100-fold.
  • A Kool-aid drinking doctor had the audacity to state that the risk of ivermectin gives no benefits.
  • This patient’s case is the costliest with three decisions, four court appearances, and now an appeal that is certainly moot. The attorney battled another case in the same health system that involved Nurije Fype, age sixty-eight. Her case inspired Dr. Ng to file suit. Fype, who is probably only alive today due to judicious treatment with ivermectin, is now four and a half months downstream and doing great.
  • Sun Ng, a 71-year-old man who spent 22 days on a ventilator with COVID-19, was discharged following a court-mandated successful treatment cycle of ivermectin.  Source

In other words, Ng made a FULL RECOVERY – and so did 80-year-old Judith Smentkiewicz, also on a ventilator with a 20% chance of survival. 

Also read this doctor’s experience with 0/2000 hospitalizations utilizing early treatment which includes ivermectin.  Here’s another doctor’s experience saving 1,700 utilizing HCQ, zinc, and azithromycin.

How many more cases must be presented before doctors smell a rat? 

Answer: cases don’t matter. 

All that matters is “consensus based” medicine (think Communism) where corrupt public health ‘authorities’ proclaim science, and Dr. Evil has been at it a long time.

And speaking of Communism, COVID investigator funded by Chinese Communist Party just removed from WHO team, is now calling on ‘Justice’ for online threats, and Dr. Evil, the doctor who has no qualms funding research that forced children to ingest harmful and dangerous chemotherapy drugs, on abominable experiments on dogs, and torturing monkeys, putting fetal scalps on rats, and taking American tax-dollars to fund illegal ‘gain of function’ research to make coronaviruses more virulent in humans is calling for his comrade’s protection. He also sees no problem with conflicts of interest.


Summary:

  • Koopmans was listed as one of 28 members on WHO’s Scientific Advisory Group for the Origins of Novel Pathogens (SAGO)
  • SAGO’s updated member list fails to include Koopmans as a contributor to the effort to allegedly uncover the origins of COVID-19
  • The National Pulse unearthed her role on a scientific advisory board of the Centers for Disease Control of Guangdong China
  • She has also authored scientific research papers and journal articles supported by Chinese Communist Party grants