Author Archive

PIC Updates ‘Aluminum – Vaccine Risk Statement’ to Include Association Between Aluminum & Asthma

https://physiciansforinformedconsent.org/pic-updates-its-aluminum-vaccine-risk-statement-document-includes-data-on-association-between-aluminum-in-vaccines-and-childhood-asthma/

PIC Updates Its ‘Aluminum – Vaccine Risk Statement’: Document Includes Data on Association Between Aluminum in Vaccines and Childhood Asthma
Physicians for Informed Consent (PIC) Updates Its ‘Aluminum – Vaccine Risk Statement’: Document Includes Data on Association Between Aluminum in Vaccines and Childhood Asthma

According to PIC, adverse effects of aluminum may not be restricted to neurological conditions*

Physicians for Informed Consent (PIC) has released an update to its Aluminum  – Vaccine Risk Statement (VRS) titled “Aluminum in Vaccines: What Parents Need to Know.” The concise, two-page educational document — which serves to answer important questions about the risks of aluminum-containing vaccines — now includes important data about a study’s link between aluminum in vaccines and asthma. Asthma is a disease that affects the lungs. It causes repeated episodes of wheezing, breathlessness, chest tightness, and nighttime or early morning coughing.

Developed from data compiled by the Centers for Disease Control and Prevention (CDC), U.S. Food and Drug Administration (FDA), and the Agency for Toxic Substances and Disease Registry (ATSDR), the PIC document provides reader-friendly Q&As on topics such as:

  • Why is aluminum in vaccines?
  • Which vaccines contain aluminum?
  • How much aluminum is in vaccines?
  • Is exposure to aluminum from vaccines safe?

The document explains that both the FDA and ATSDR have raised concerns about the negative effects of aluminum exposure in humans. Scientific studies have shown that small amounts of aluminum can interfere with cellular and metabolic processes in the nervous system. Some of the most damaging effects of aluminum range from motor skill impairment to encephalopathy (altered mental state, personality changes, difficulty thinking, loss of memory, seizures, coma, and more).

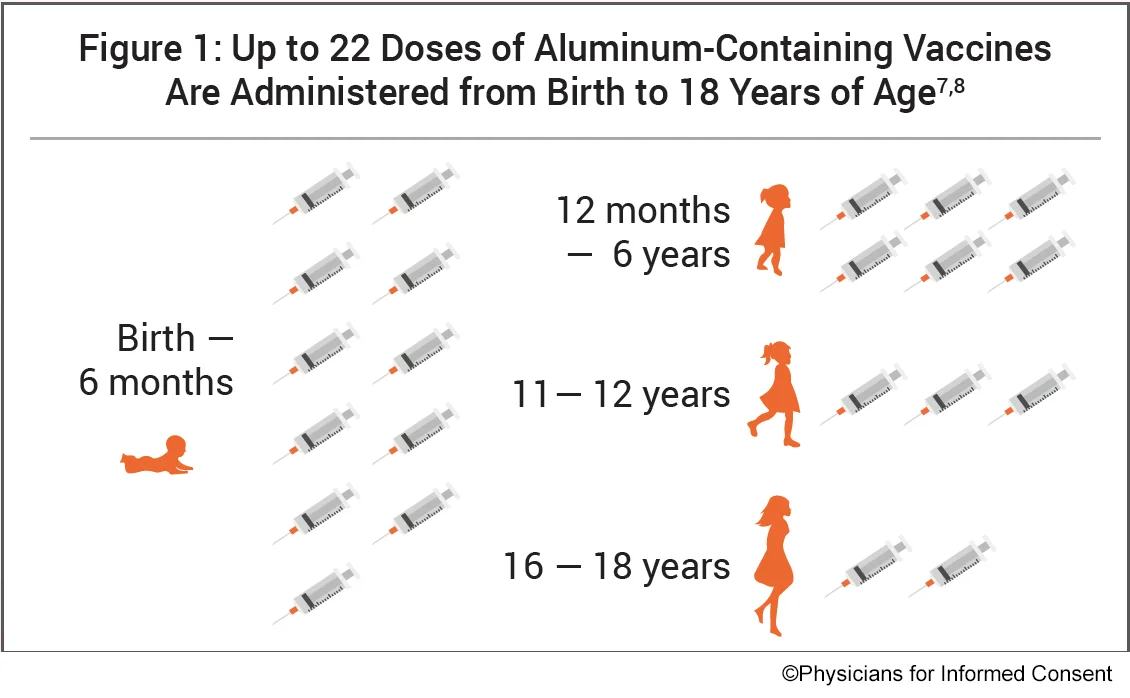
Studies have also shown that adverse effects of aluminum may not be restricted to neurological conditions.* A study referenced in the PIC document and published in Academic Pediatrics found that asthma occurred in 1 in 183 vaccinated children for every 1 mg (1,000 mcg) increase in aluminum exposure. In the United States, up to 22 doses of aluminum-containing vaccines are administered to children, with 11 doses administered from birth to 6 months of age.

“Overexposure to aluminum may lead to significant harm,” said Dr. Shira Miller, founder and president of Physicians for Informed Consent. “In California, where PIC is headquartered, since Senate Bill 277 (SB 277) was enacted in 2015, numerous doses of aluminum-containing vaccines are mandated for public and private K-12 school attendance — with no exceptions for religious or personal belief exemptions. PIC asserts that vaccine mandates are unscientific and unethical and a threat to public health. SB 277, and any other law that coerces vaccination, needs to be repealed.”

To read or download the educational document “Aluminum in Vaccines: What Parents Need to Know,” please visit physiciansforinformedconsent.org/aluminum.

* In 2008, the Agency for Toxic Substances and Disease Registry (ATSDR), a division of HHS, used studies of the neurotoxic effects of aluminum to determine that no more than 1 milligram (mg) (1,000 micrograms [mcg]) of aluminum per kilogram (kg) of body weight should be taken orally per day to avoid aluminum’s negative effects.

Physicians for Informed Consent is a 501(c)(3) nonprofit educational organization focused on science and statistics. PIC delivers data on infectious diseases and vaccines, and unites doctors, scientists, healthcare professionals, attorneys, and families who support voluntary vaccination. In addition, the PIC Coalition for Informed Consent consists of over 300 U.S. and international organizations. Click here to make a donation.

Press Contact:
info@picphysicians.org
925-642-6651

CLICK HERE to view on Newswire.
CLICK HERE to share on Twitter.
CLICK HERE to share on Facebook.
CLICK HERE to share on Instagram.
CLICK HERE to share on LinkedIn.

Genomic Confirmation of Borrelia garinii, United States

https://wwwnc.cdc.gov/eid/article/29/1/22-0930_article

Volume 29, Number 1—January 2023
Natalie RudenkoComments to Author , Maryna Golovchenko, Ales Horak, Libor Grubhoffer, Emmanuel F. Mongodin1, Claire M. Fraser, Weigang Qiu, Benjamin J. Luft, Richard G. Morgan, Sherwood R. Casjens, and Steven E. Schutzer


Abstract

Lyme disease is a multisystem disorder primarily caused by Borrelia burgdorferi sensu lato. However, B. garinii, which has been identified on islands off the coast of Newfoundland and Labrador, Canada, is a cause of Lyme disease in Eurasia. We report isolation and whole-genome nucleotide sequencing of a B. garinii isolate from a cotton mouse (Peromyscus gossypinus) in South Carolina, USA. We identified a second B. garinii isolate from the same repository. Phylogenetic analysis does not associate these isolates with the previously described isolates of B. garinii from Canada.

_________________

Important excerpt:

How and when B. garinii arrived in South Carolina remains unknown. There were no reported Lyme disease outbreaks in the southeastern United States in humans at the time the strains were deposited in the repository or during the subsequent 2 decades. This finding minimizes the urgency for an immediate new search for B. garinii in this region. Nonetheless, clinical vigilance for B. garinii in humans in this region seems warranted.


True to form, the CDC downplays the finding of a new strain which very well could explain why sick patients continue to be mis or undiagnosed due to faulty testing and strain diversity, which will never be picked up using current 2-tiered CDC testing because it doesn’t look for other strains.

But, truth be damned.  It just doesn’t matter to corrupt public health.

3 Reasons Lyme/MSIDS Patients Remain Sick: Dormancy/Persisters, Biofilm, Co-Infection

https://parasitesandvectors.biomedcentral.com/articles/10.1186/s13071-019-3495-7

Metamorphoses of Lyme disease spirochetes: phenomenon of Borrelia persisters

Abstract

The survival of spirochetes from the Borrelia burgdorferi (sensu lato) complex in a hostile environment is achieved by the regulation of differential gene expression in response to changes in temperature, salts, nutrient content, acidity fluctuation, multiple host or vector dependent factors, and leads to the formation of dormant subpopulations of cells. From the other side, alterations in the level of gene expression in response to antibiotic pressure leads to the establishment of a persisters subpopulation. Both subpopulations represent the cells in different physiological states. “Dormancy” and “persistence” do share some similarities, e.g. both represent cells with low metabolic activity that can exist for extended periods without replication, both constitute populations with different gene expression profiles and both differ significantly from replicating forms of spirochetes. Persisters are elusive, present in low numbers, morphologically heterogeneous, multi-drug-tolerant cells that can change with the environment. The definition of “persisters” substituted the originally-used term “survivors”, referring to the small bacterial population of Staphylococcus that survived killing by penicillin. The phenomenon of persisters is present in almost all bacterial species; however, the reasons why Borrelia persisters form are poorly understood. Persisters can adopt varying sizes and shapes, changing from well-known forms to altered morphologies. They are capable of forming round bodies, L-form bacteria, microcolonies or biofilms-like aggregates, which remarkably change the response of Borrelia to hostile environments. Persisters remain viable despite aggressive antibiotic challenge and are able to reversibly convert into motile forms in a favorable growth environment. Persisters are present in significant numbers in biofilms, which has led to the explanation of biofilm tolerance to antibiotics. Considering that biofilms are associated with numerous chronic diseases through their resilient presence in the human body, it is not surprising that interest in persisting cells has consequently accelerated. Certain diseases caused by pathogenic bacteria (e.g. tuberculosis, syphilis or leprosy) are commonly chronic in nature and often recur despite antibiotic treatment. Three decades of basic and clinical research have not yet provided a definite answer to the question: is there a connection between persisting spirochetes and recurrence of Lyme disease in patients?

______________

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6287027/


Abstract

Lyme borreliosis (LB) is the most common tick-borne disease caused by the spirochete Borrelia burgdorferi in North America and Borrelia afzelii or Borrelia garinii in Europe and Asia, respectively. The infection affects multiple organ systems, including the skin, joints, and the nervous system. Lyme neuroborreliosis (LNB) is the most dangerous manifestation of Lyme disease, occurring in 10–15% of infected individuals. During the course of the infection, bacteria migrate through the host tissues altering the coagulation and fibrinolysis pathways and the immune response, reaching the central nervous system (CNS) within 2 weeks after the bite of an infected tick. The early treatment with oral antimicrobials is effective in the majority of patients with LNB. Nevertheless, persistent forms of LNB are relatively common, despite targeted antibiotic therapy. It has been observed that the antibiotic resistance and the reoccurrence of Lyme disease are associated with biofilm-like aggregates in B. burgdorferi, B. afzelii, and B. garinii, both in vitro and in vivo, allowing Borrelia spp. to resist to adverse environmental conditions. Indeed, the increased tolerance to antibiotics described in the persisting forms of Borrelia spp., is strongly reminiscent of biofilm growing bacteria, suggesting a possible role of biofilm aggregates in the development of the different manifestations of Lyme disease including LNB.

________________

https://www.fortunejournals.com/articles/serological-and-pcr-evidence-of-infection-in-105-patients-with-sppt.html

Serological and PCR evidence of Infection in 105 Patients with SPPT

Alexis Lacout1*, Marie Mas4, Michel Franck2, Véronique Perronne3, Julie Pajaud2, Pierre Yves Marcy5, Christian Perronne3

*Corresponding Author: Alexis Lacout, Centre de diagnostic ELSAN, Centre Médico–Chirurgical, 83 avenue Charles de Gaulle, 15000, Aurillac, France

Received: 11 December 2020; Accepted: 22 December 2020; Published: 05 January 2021

Citation: Alexis Lacout, Marie Mas, Michel Franck, Véronique Perronne, Julie Pajaud, Pierre Yves Marcy, Christian Perronne. Serological and PCR evidence of Infection in 105 Patients with SPPT. Archives of Microbiology & Immunology 5 (2021): 139-150.

Abstract

Introduction: The main aim of this study is to determine the nature of the exposure of patients presenting with polymorphic signs and symptoms to the parasite Babesia, through the study of serology. The secondary aim is to report the different serological or PCR results observed in these patients.

Material and methods: The following serologies were performed in all patients looking for: Babesia divergens, Borrelia, Bartonella, Coxiella burnetii, Anaplasma phagocytophilum. The following PCRs were performed looking for: Borrelia spp, Babesia spp, Bartonella (Bartonella spp, B. quintana, B. Henselae,) Coxiella spp, Anaplasma spp, Ehrlichia spp, Rickettsia spp, most often on several matrices (venous blood, capillary blood, urine and saliva).

Results: In this study, 105 patients were included, 62 females and 43 males, sex ratio F/M was 62/43 = 1.44; mean age was 45.5 year old (range; 5 years, 79 years old).

  • Of the 105 serologies for B. divergens, 41% were found to be positive.
  • Of the 104 serologies for Borrelia, 19.2% were found to be positive.
  • Of the 95 serologies for Anaplasma, 27.3% were found to be positive.

Borrelia spp, Babesia spp, Bartonella spp, Coxiella spp, Anaplasma spp, Ehrlichia spp, Rickettsia spp were found by using rtPCR.

Conclusion: Our study has shown that patients with SPPT/PTLDS, a syndrome close to fibromyalgia, could harbor several tick borne microorganisms. Microbiologic analyses should thus not be merely limited to Borrelia’s research alone.

______________

**Comment**

These relatively recent studies (within the past few years) reveal what Lyme literate doctors and their patients have been experiencing from the beginning.  They also reaffirm what many independent researchers have globally been writing about for years.  There are many other reasons patients remain ill as well but these three are biggies.

Yet, reality is best summed up by the following quote from the first study listed above:

Three decades of basic and clinical research have not yet provided a definite answer to the question: is there a connection between persisting spirochetes and recurrence of Lyme disease in patients?

Isn’t that sad?

The same, of course, can be said of biofilm and coinfections as well. Decades have gone by with no definitive answers because The Cabal doesn’t want the truth to be known. Why? Quite simple: a chronic, relapsing illness doesn’t fit their “vaccine” narrative which is the favored golden calf and cash cow of research institutions and our government, which have a cozy relationship with Big Pharma and Big Media.  This is quite convenient for all of them as they control all the messaging as well as threaten, censor, and ban doctors who dissent.

This has been blatantly exposed during the time of COVID but is nothing new.  Lymeland has been riddled with the exact same issues for 40 years.  Unfortunately, even well-meaning advocates and patients evidently can not see this and continue to demand more money and become giddy when they get it from the very agencies behind this debacle, who are incidentally profiting from it.

It’s a hot-mess for sure, but one thing is certain: we must stop playing into their hands by being ignorant or filled with “hopium,” a term I use to describe how hope can become a drug that stops you from thinking critically, logically, and honestly.

For more:

An Insider’s View: COVID-19 Hospital Treatment

https://covid19criticalcare.com/an-insiders-view-covid-19-treatment-in-hospital/  Video Here (Approx. 1 hour 20 Min)

An Insider’s View: COVID-19 Treatment in Hospital

Published On: December 21, 2022

The first 10 minutes is a powerful video about an actual patient who was granted the right to try ivermectin, which ended up saving his life.  I’ve posted this before, but it’s worth repeating. The remaining time is a compelling webinar to end 2022 with Betsy Ashton, Dr. Pierre Kory, and special guests filmmaker Connor Callanan, that documented his dad’s hospital treatment and attorney Ralph Lorigo.

The video by Connor can also be found here

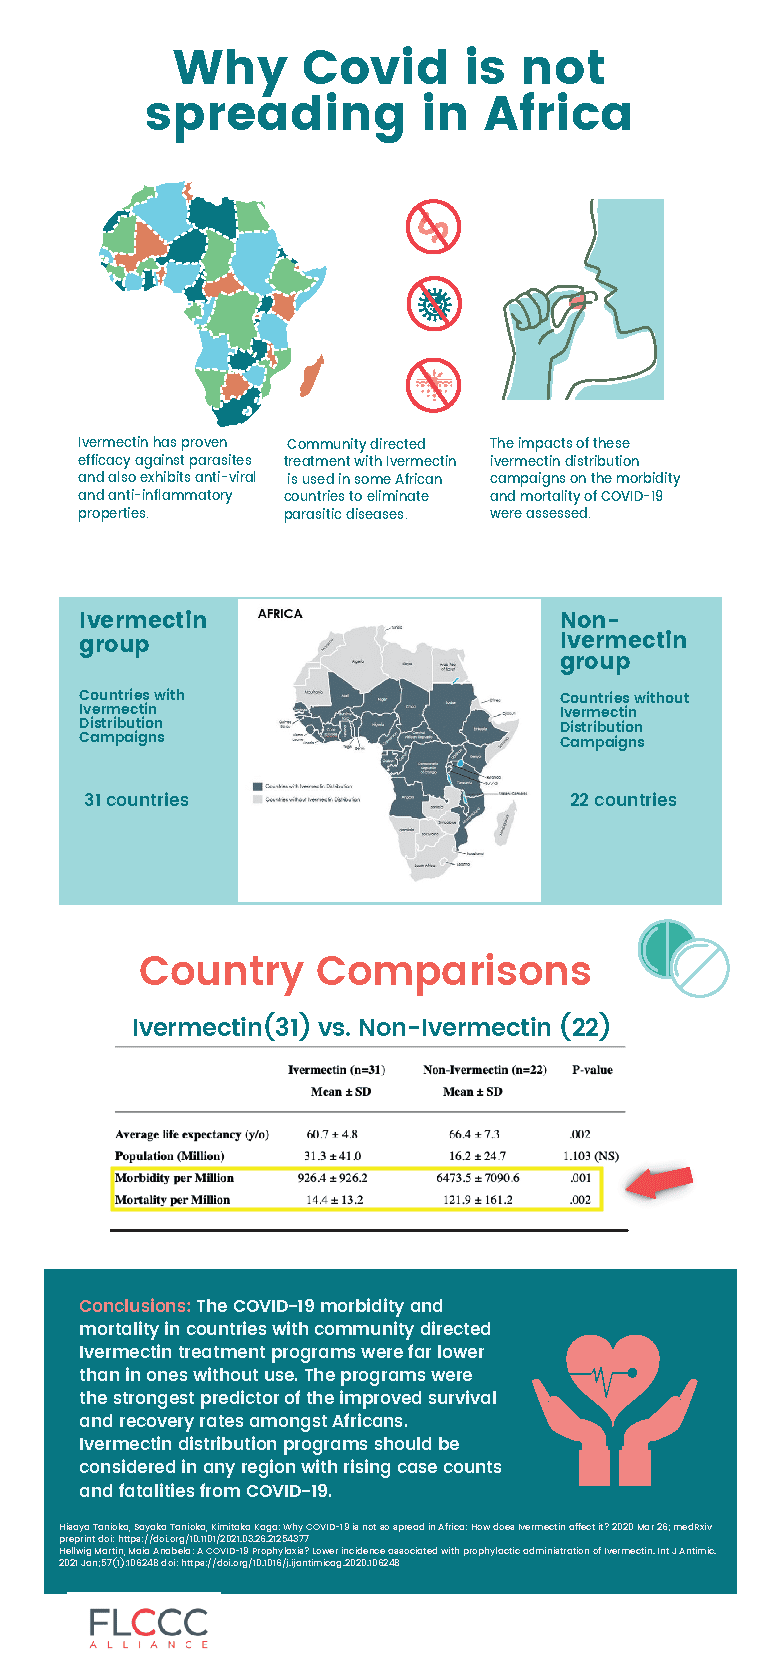
Meanwhile, in the real world, there is no apparent COVID in Africa which just happens to have a community directed ivermectin treatment program which is the strongest predictor of improved survival and recovery rates of COVID.  Yet, China, with it’s three year lockdown and tyrannical ZERO COVID policy which is an utter flop, is experiencing a COVID resurgence with even CCP leaders becoming ill and dying.

But, the band plays on…..

For more:

The CARES Act provides incentives for hospitals to use treatments dictated solely by the federal government under the auspices of the NIH. These “bounties” must paid back if not “earned” by making the COVID-19 diagnosis and following the COVID-19 protocol.

The hospital payments include:

  • A “free” required PCR test in the Emergency Room or upon admission for every patient, with government-paid fee to hospital.
  • Added bonus payment for each positive COVID-19 diagnosis.
  • Another bonus for a COVID-19 admission to the hospital.
  • A 20 percent “boost” bonus payment from Medicare on the entire hospital bill for use of remdesivir instead of medicines such as Ivermectin.
  • Another and larger bonus payment to the hospital if a COVID-19 patient is mechanically ventilated.
  • More money to the hospital if cause of death is listed as COVID-19, even if patient did not die directly of COVID-19.
  • A COVID-19 diagnosis also provides extra payments to coroners.

CMS implemented “value-based” payment programs that track data such as how many workers at a healthcare facility receive a COVID-19 vaccine. Now we see why many hospitals implemented COVID-19 vaccine mandates. They are paid more.

Outside hospitals, physician MIPS quality metrics link doctors’ income to performance-based pay for treating patients with COVID-19 EUA drugs. Failure to report information to CMS can cost the physician 4% of reimbursement.

No Apparent COVID in Africa But Tolerance Cometh: IgG4 After Multiple mRNA Doses

http://  Approx. 14 Min

No Apparent COVID in Africa

Dec. 28, 2022

Dr. John Campbell

Dr. Campbell states he is getting reports that there is virtually ZERO COVID in Uganda.  Surveys were given to community health partners including doctors, nurses, and medical officers around the country.  He states:

“No one is getting ‘vaccinated.’ They don’t see any COVID. They’re not getting tested. Clinically they are not seeing it in the hospitals. They are not seeing people come in with respiratory distress and other complications of COVID. The government aren’t even publishing guidelines anymore.”

Last year I posted how mainstream media simply can’t fathom why Africa remains relatively unscathed from COVID despite the fact they have community directed ivermectin treatment programs to fight river blindness.  Ivermectin, of course, has been discredited and banned by corrupt public health ‘authorities’ despite mounting evidence they simply ignore.  In fact, ivermectin programs were the strongest predictor of improved survival and recovery rates of COVID in Africa, but nobody in power cares.

For more:

Meanwhile, China’s 3 year lockdown, mandated masking, and ZERO COVID policy is a complete and utter flop with CCP leaders now sick and dying from COVID.  Their answer?  Allowing the public to purchase the Pfizer COVID drug Paxlovid which is:

Paxlovid has cost U.S. taxpayers $10.6 BILLION

_______________

https://unglossed.substack.com/p/boosting-tolerance-igg4

Tolerance Cometh: IgG4 After Multiple-mRNA Doses

IgG4 surges, and lab-apparent T Cell targeting of infected cells declines following a 3rd Dose of the Pfizer/BioNTech Covid vaccine, in a new study from Bavaria.

Spike-overload finally seems to be showing a concrete effect in the repeat-injected: B Cells in two separate cohorts were found to be self-switching to IgG4 class antibodies, associated with tolerance and anti-inflammatory response, after the 3rd dose.

Commenter Jim H did me the splendid favor of directing my attention to a new pre-print about IgG4. It’s a game-changer.1

So, let’s review this incredible and totally unforeseeable2 discovery.  (See link for article)

According to Dr. James Lyons Weiler:

The Entire Warning Re: Pathogenic Priming Has Been Missed By Allopathic Medicine and by Many Who Discuss the Perils of COVID-19 “Vaccines”

The lesson from pathogenic priming is simple: more exposures means more immune disasters. In thrombocytopenia and other forms of immunopenia, for example, the scientific literature cites the IPAK April 2020 finding that 1/3 of the proteins to which SARS-CoV-2 shows risk of autoimmunity via pathogenic priming involve the immune system.

My predictions from April 2020 have sadly been born out by the scientific literature.

In 2020 alone, 14 studies cite the original Pathogenic Priming results, I’m sad to say, with evidence of myriad autoreactogenicity (see them here).

Far from beating my chest, I am deeply saddened that the way to avoid pathogenic priming induced morbidity and mortality is avoid repeated exposures to SARS-CoV-2 proteins. Obviously, with eternal boosters, the cycle of

vaccine → infect → vaccinate → infect —>…

will be eternal for those stuck in that loop, with I would expect 4-6 infections per year for some – their immune systems being confused, Th2-skewed, class-shifted, ground to dust.  Source

Weiler is offering a course called “Exploring Mechanisms of Vaccine Injury/Potential Recovery Protocols – Iatrogenic Illness in Partnership with VITA” that is now being considered for CMEs for physicians.  He asks all of us to send this information to medical practitioners as there’s no time to sound more warning bells.  He states:

Other than this, all I can do at this point is share my remorse and sadness that more people were not warned in time.

Indeed.