Archive for the ‘Testing’ Category

Dr. Kinderlehrer’s Experience With Tick-borne Illness & His New Book

https://www.lymedisease.org/kinderlehrer-book-intro-excerpt/

“If the cure doesn’t work, it means you don’t have Lyme disease” (NOT!)

Jan. 13, 2021

New Hampshire Right-to-Know Law & the Lyme Study Commission

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf

New Hampshire Right-to-Know Law and the Lyme Study Commission

JAN 13, 2021 — 

As a result of NH House Bill 490 a committee was established to study the limitations of serological diagnostic tests in determining the presence or absence of Lyme and other tick-borne diseases and the development of appropriate methods to educate physicians and the public with respect to the inconclusive nature of prevailing test methods.

I made the following statement in the December Zoom meeting:

“Current FDA approved testing is no better than a coin toss”

We will present documentation in ongoing meetings to support this claim.

Below is a 15yr old example: (Aucott was past Chair of the TBDWG and Auwaerter was past president of the IDSA)

Two-Year Evaluation of Borrelia burgdorferi Culture and Supplemental Tests for Definitive Diagnosis of Lyme Diseasehttps://jcm.asm.org/content/43/10/5080
Peggy Coulter,  Clara Lema,  Diane Flayhart,  Amy S. Linhardt,  John N. Aucott,  Paul G. Auwaerter, and  J. Stephen Dumler

Published 2005

Comparisons with qualitative clinical assessments

“Overall, initial serologic tests agreed with possible or probable clinical Lyme disease diagnosis in only 50% (40/80) of cases.” [COIN TOSS]

Lyme Study Committee Home Page:http://www.gencourt.state.nh.us/statstudcomm/details.aspx?id=1515&rbl=1&txtbillnumber=hb490

Under the New Hampshire Right-to-Know Law, documents shared with the Lyme Study Committee members must be made public.

The following list of documents have been posted to the Committee Website.

The first two letters below are extremely disturbing and should be shared widely:

1. Dr. Richard Shulik’s 2010 testimony for House Bill 1326 (passed as HB 295)
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/Dr.%20Richard%20Shulik’s%202010%20testimony%20for%20House%20Bill%201326%20(passed%20as%20HB%20295).msg.pdf

Ten years ago, Dr. Richard Shulik (Clinical psychologist) reported on the experiences of Lyme patients from his practice in Londonderry and the difficulties obtaining treatment. Dr. Shulik’s comment: “To say the least, these are nightmarish experiences which I would not wish upon anyone.”

2. Registered Complaint to the NH Dept of Health
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/Registered%20Complaint.pdf

I sent this registered letter to Dr. Jose Montero, past Director of the NH Department of Health in 2010 and coordinated an onsite meeting which included Dr. Lynn Durand, currently a member of our study commission. The letter identifies five cases where a negative Elisa led to patient harm. These cases were summarized by a Lyme treating clinician here in New Hampshire.

3. LYME DISEASE BILL BECOMES LAW
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/LYME%20DISEASE%20BILL%20BECOMES%20LAW.pdf

House Bill 295 (Passed in 2011) protects physicians’ rights to determine the most appropriate treatment protocol for their patients..

4. 10 Things you Should Know About New IDSA Guidelines
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/10%20Things%20you%20Should%20Know%20About%20New%20IDSA%20Guidelines.pdf

A reposting of the article from Lorraine Johnson, CEO of lymedisease.org

5. Letter Regarding Testimony Submitted
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/Letter%20Regarding%20Testimony%20Submitted.pdf

Notice of my letter to the editor of the BMJ published June 2020 (Evidence of persistent infection after extensive antibiotic treatment)

6. NH DHHS Health Alert
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/NH%20DHHS%20Health%20Alert.pdf

DHHS is instructing the physician not to run the Western blot after a negative Elisa. So how do we rule out a false negative Elisa?????

7. Galaxy Diagnostics Launches the Most Sensitive Test Available for Direct Detection of Lyme Disease
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/Galaxy%20Diagnostics%20Launches%20the%20Most%20Sensitive%20Test%20Available%20for%20Direct%20Detection%20of%20Lyme%20Disease.pdf

“Galaxy validation data (unpublished) shows that the Nanotrap® Urine Test will often confirm active infection in patients with negative TTT (Two-Tiered Testing) results.”

8. Written Public Comment
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/Written%20Public%20Comment.pdf

Patient testimony across America is describing an experience that doesn’t resemble anything that our public health officials are telling us about Lyme disease. The truth about this life-altering/life-threatening infection remains well hidden from the public through an elaborate racketeering scheme now on trial in Texas District Court.

9. TBDWG Meeting Nov 17 9am Online
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/TBDWG%20Meeting%20Nov%2017%209am%20Online.pdf

Written public comment directed to Dr. David Walker, Co-Chair of the Tick-Borne Disease Working Group. During the July 8th meeting he was recorded saying that persistent infection is a “religious belief.”

10. TBDWG October 27, 2020 – Written Public Comment
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/TBDWG%20October%2027,%202020%20-%20Written%20Public%20Comment.pdf

The CDC’s refusal to acknowledge persistent infection has left hundreds of thousands (if not millions worldwide) in a debilitated state as the disease has been misclassified decades ago as a low-risk and non-urgent health threat. (Hard to catch and easily treated) Failure to recognize this pathogen as an antibiotic resistant/tolerant superbug leaves everyone in our state of New Hampshire vulnerable to its incapacitating outcome.

11. HB490 included a section on available treatment protocols
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/HB490%20included%20a%20section%20on%20available%20treatment%20protocols.pdf

Indirect serologic testing as you know is looking for elevated antibodies to the pathogen in question. Since humans do not produce antibodies against Borrelia (the causative agent of Lyme disease) for 4-6 weeks after a tick bite, relying on antibody production misses early detection. Antibody tests cannot be used to gauge treatment failure or success.

12. Tuttle directs pointed questions to TBD Working Group member Shapiro
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/Tuttle%20directs%20pointed%20questions%20to%20TBD%20Working%20Group%20member%20Shapiro.pdf

Carl Tuttle, a long-time Lyme activist from New Hampshire, gave the following remarks by telephone to the Tick-Borne Disease Working Group on Sept. 15.

13. House Bill 363 and the NH DHHS
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/House%20Bill%20363%20and%20the%20NH%20DHHS.pdf

In 2015 House Bill 363 required the NH DHHS to include a link to the International Lyme and Associated Diseases Society on its Internet website. Although the DOH adhered to those requirements, they do not have any references to ILADS in their official Health Alert going out to our medical community.

14. New Hampshire State House Hearing of 01.28.2010
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/New%20Hampshire%20State%20House%20Hearing%20of%2001.28.2010.pdf

Dr. Shulik’s testimony followed by a letter to the Editor-in-Chief of The New England Journal of Medicine. What we have here is collusion to deny a chronic disease; a disease that has spiraled out of control into a 21st century plague. The medical establishment has been led to believe that “chronic Lyme” is a fictitious disease and hundreds of thousands perhaps millions of patients around the globe are left untreated/undertreated and suffering.

15. limitations of serological diagnostic tests Rep Woods letter Oct 2020
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/limitations%20of%20serological%20diagnostic%20tests%20Rep%20Woods%20letter%20Oct%202020.pdf

The letter calls attention to a partial list of studies identifying treatment failure through direct detection methods with some of these references dating back thirty years.

16. 2010 Letter Jose T. Montero, MD, Director
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/2010%20Letter%20Jose%20T.%20Montero,%20MD,%20Director.pdf

Official registered complaint filed with the NH Dept of Health. Here we are ten years later!

17. Antibiotic treatment duration for Lyme disease
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/Antibiotic%20treatment%20duration%20for%20Lyme%20disease.msg.pdf

“…longer treatment durations were associated with better treatment response—with most high responders and well patients reporting treatment durations of four or more months and many reported durations exceeding a year. As the chart below reveals, those treated for less than a month were unlikely to report improvement.”

18. DDD CT, antibiotics-Oct 2020, 09-00725
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/DDD%20CT,%20antibiotics-Oct%202020,%2009-00725.pdf

Efficacy of Double‐Dose Dapsone Combination Therapy in the Treatment of Chronic Lyme Disease/Post‐Treatment Lyme Disease Syndrome (PTLDS) and Associated Co‐infections: A Report of Three Cases and Retrospective Chart Review

19. 2009 Letter to Quest Diagnostics
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/2009%20Letter%20to%20Quest%20Diagnostics.pdf

Could you please tell me why Quest Labs’ Western blot Lyme test doesn’t include band 31 and 34? Is it possible that your exclusion of these bands is missing many Lyme cases since band 31 and 34 are highly specific to Borrelia burgdorferi and were originally chosen for vaccine development?

20. EvidenceofPersistence-V2
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/EvidenceofPersistence-V2.pdf

The following is a list of over 700 peer reviewed articles that support the evidence of persistence of Lyme and other tick-borne diseases. It is organized into different categories—general, psychiatric, dementia, autism and congenital transmission.

21. Treatment Delays and the Increase Risk of Persistent Illness in Lyme Disease
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/Treatment%20Delays%20and%20the%20Increase%20Riskof%20Persistent%20Illness%20in%20Lyme%20Disease.pdf

From the Johns Hopkins study:

“One-third of Lyme disease patients report delayed treatment of greater than 30 days

Carl Tuttle’s comment: Humans do not produce antibodies to Lyme disease for 4-6 weeks after a tick bite so serology has always been the wrong diagnostic tool.

22. The Staggering Cost of Lyme Disease and Other Tick-Borne Illnesses
http://www.gencourt.state.nh.us/statstudcomm/committees/1515/documents/The%20Staggering%20Cost%20of%20Lyme%20Disease%20and%20Other%20Tick-Borne%20Illnesses.pdf

From the IgeneX survey:

Lyme disease has been detected in all 50 states. The high cost of Tick-Borne Disease misdiagnosis.

According to the survey:

· 45% of patients needed more than three years to obtain the proper diagnosis

· 65% of patients were forced to quit a job or cut back on their hours due to their symptoms

· 24% of patients saw more than ten doctors before receiving a proper diagnosis

· 86% of patients suffer from long-term side effects from not having been diagnosed sooner

_______________________

For more:  https://madisonarealymesupportgroup.com/2020/09/25/why-should-we-care-about-lyme-disease-a-colorful-tale-of-government-conflicts-of-interest-probable-bioweaponization-and-pathogen-complexity/

https://madisonarealymesupportgroup.com/2020/04/26/cdc-playbook-learning-from-lyme/

https://madisonarealymesupportgroup.com/2020/07/30/how-the-cdc-uses-their-own-guidelines-to-rig-the-system/

https://madisonarealymesupportgroup.com/2018/03/17/nice-lyme-guidelines-human-rights-of-lyme-patients/

Stealth Infections & Their Detection

Dr.-Schwarzbach-Stealth-Infections-and-their-Detection (1)  pdf here

iu-105

Armin Schwarzbach PhD

Medical doctor and Specialist for Laboratory Medicine

Augsburg, Germany

AONM Annual Conference London, November 19th 2017

______________________

**Comment**

Excellent presentation on the following stealth pathogens:

  • Mycoplasma
  • Bartonella
  • Babesia
  • Ehrlichia/Anaplasma
  • Chlamydia pneumoniae
  • Yersinia
  • Coxsackie viruses (B1, A7, A16) and many others 
  • Borrelia burgdorferi , in all its forms

While Dr. Schwarzbach wants to blame “ecosystem disruption” for the mess we are in, I think it more likely to be due to laboratory experimentation/manipulation (bioweaponization), dropping ticks from airplanes, and migratory birds and animals transporting ticks far and wide:

https://madisonarealymesupportgroup.com/2020/09/25/why-should-we-care-about-lyme-disease-a-colorful-tale-of-government-conflicts-of-interest-probable-bioweaponization-and-pathogen-complexity/

Alpha-gal Syndrome – Symptoms, Diagnosis, & Treatment

https://www.lymedisease.org/alpha-gal-syndrome/

There is growing evidence that certain types of tick bites can trigger alpha-gal syndrome (AGS) a life-threatening allergy to red meat and meat-related products.

In some individuals, it appears tick bites can result in the sensitization to a carbohydrate known as galactose-alpha-1,3-galactose, or “alpha-gal” for short. This sugar molecule is found in most mammals you might be likely to eat, but not in fish or fowl.

Most recognized food allergies, such as to peanuts or shellfish, will prompt an immediate reaction after being consumed. That’s not the case with AGS, however, which can take up to eight hours (or even more) after exposure to produce a reaction.

Note: exposure to alpha-gal via inhalation, injected drugs or vaccines can cause an immediate reaction.

Alpha-gal syndrome - meats that contain alpha-gal

Examples of commonly consumed mammalian meats that contain alpha-gal include beef, pork, lamb, goat, venison and buffalo. Common foods that are derived from mammals include lard, milk, cream, ice cream, and cheese—although the majority of AGS patients do tolerate dairy products.

Personal products that use ingredients containing “hydrolyzed protein” (gelatin), lanolin, glycerin, collagen, or tallow are particularly problematic.

Additional products that can bring on an alpha-gal reaction are jello, gelatin capsules, certain medications, pig or cow heart valves, surgical mesh, certain vaccines and unlabeled “natural flavorings” in foods.

Some people with AGS also react to carrageenan, a common food additive made from red algae, which also contains alpha-gal. (So even being strictly vegan won’t necessarily protect you from AGS reactions.)

How are ticks involved in alpha-gal syndrome?

Alpha-gal meat allergy has been reported all over the world including Asia, Australia, Central America, Europe, Germany, Japan, South Korea, and the United States.

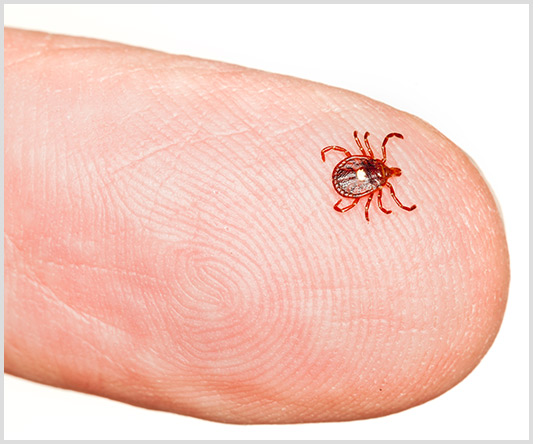
The tick species most often associated with Alpha-gal syndrome is the lone star tick

In the U.S., the tick species most often associated with AGS is the lone star tick (Amblyomma americanum) found throughout the South, East and parts of the Midwest. Recent research suggests that the blacklegged tick (Ixodes scapularis and Ixodes pacificus) may also be implicated in alpha-gal syndrome.

The Asian longhorned tick (Haemaphysalis longicornis), the primary trigger of AGS in Asia, has shown up in the US recently, but has yet to be implicated in AGS here. The Cayenne tick (Amblyomma cajennese) found in southern Texas and Florida has also been linked to AGS in Central America, but not yet in the U.S.

While no known pathogen has been linked to triggering AGS, more research is needed to understand the mechanism and the role that ticks play. Currently the thought is that the tick saliva plays a role in activating the allergy to alpha-gal.

Who’s at risk for AGS?

Alpha-gal syndrome is a much more common allergy in the U.S. today than it was a decade ago, with the number of laboratory-confirmed cases growing from 12 in 2009 to over 34,000 in 2019. Unfortunately, AGS has no insurance billing code (ICD code), nor is it a reportable illness to the CDC.

Experts agree alpha-gal syndrome is under-reported in geographic areas where tick bites are common.

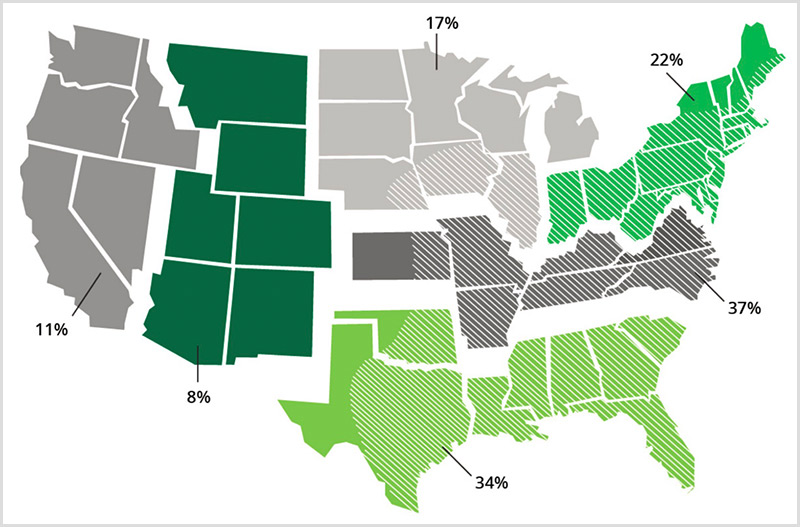
Alpha-gal syndrome Lone Star Tick in the United States

Surveillance for IgE to alpha-gal. Percent positive rates are presented for IgE to alpha-gal within each of six regions in the United States, 2012-2013 (7300 samples). Diagonal white lines on the map represent the known geographic distribution of the lone star tick (Data and map, Viracor-IBT Laboratories; Tick Distribution, CDC).

For now, the biggest risk factor for AGS appears to be repeated bites by ticks that contain alpha-gal in their saliva and salivary glands. It is not understood why, but not everyone who is bitten by a tick containing alpha-gal will develop AGS.

While both children and adults can acquire AGS, most cases have been reported in adults.

Certainly, if a patient with recent tick exposure presents with sudden onset anaphylaxis and recurrent gastrointestinal symptoms, AGS should be considered.

Alpha-gal syndrome is a much more common allergy in the U.S. today than it was a decade ago, with the number of laboratory-confirmed cases growing from 12 in 2009 to over 34,000 in 2019.

What are the symptoms of alpha-gal syndrome?

The symptoms of alpha-gal syndrome are often delayed, making it much harder to pinpoint the trigger. Someone may wake up at 3 o’clock in the morning in the throes of serious allergic reaction, and have no idea it was brought on by a hamburger they ate the night before.

Symptoms can range from itching and stomach upset to breathing difficulty and full anaphylaxis. AGS reactions often start with itching of the palms of hands and soles of feet.

Common symptoms of AGS include:

  • 90% have skin symptoms: itching “pruritus,” flushing “erythema,” hives “urticaria” (swollen, pale red bumps or “wheals” on the skin), angioedema (swelling in deep layers below the skin)
  • 60% develop anaphylaxis (a potentially deadly reaction that can restrict breathing)
  • 60% have gastrointestinal symptoms (abdominal pain, diarrhea, acid reflux, cramping, vomiting)
  • 30-40% experience cardiac symptoms: rapid decrease in blood pressure (hypotension, POTS); palpitations (atypical chest symptoms)
  • 30-40% experience respiratory symptoms (wheezing, coughing, shortness of breath)
  • 20% of patients will have GI symptoms alone (may present like irritable bowel syndrome)
  • 3-5% develop mast cell activation syndrome
  • arthritis (rare)
  • mouth swelling, sores (rare)

How is AGS diagnosed?

If you experience symptoms after eating mammalian meat products, immediately notify your primary care physician or allergist. Unlike most tick-borne pathogens, the onset of AGS usually takes at least 4-6 weeks from the time of the tick bite. Complicating things further, about a third of patients do not recall a tick bite.

Your doctor should be able to determine if you have AGS based upon your clinical symptoms and a positive blood test: immunoglobulin E (IgE) to the oligosaccharide glactose-alpha-1,3 galactose (alpha-gal.)

In the U.S., Viracor is the main laboratory for AGS testing. The Viracor “specific IgE galactose-alpha-1,3-galactose” test can be taken at most commercial laboratories like Labcorp and Quest and shipped to Viracor.

Warning: The test for alpha-gal is often mistaken for “alpha-galactosidase” or “a-galactosidase A deficiency”—note these are the wrong tests! Because the test is so new, it is recommended to take the proper testing codes with you to the doctor and the laboratory. Click here to download and print a PDF on the proper testing codes for alpha-gal syndrome.

How is Alpha-gal syndrome treated?

There are currently no U.S. FDA-approved medications for the treatment of AGS. As with most allergies, the mainstay of management is avoidance of the allergen. Therefore, the best practice is to avoid exposure to:

  1. Mammalian meats
  2. Personal products containing mammalian derivatives
  3. Medical products containing mammalian proteins, derivatives or parts
  4. Medications containing mammalian proteins or derivatives

Knowing you must avoid mammalian products is only half the battle, as these products have worked their way into nearly every level of our modern life.

For instance, gelatin is the main ingredient of jellybeans, candy corn, marshmallows, puddings and the capsules of many medications. Chicken and turkey sausages may be stuffed in pork casings, lard (rendered pork fat) is found in many pre-made gravies, sauces, soups, candies, chips, fries, and more.

As with all serious allergies, it is important to have the proper diagnosis and be prepared with how to respond in the event of an emergency. Most allergists will recommend wearing a medical alert bracelet and carrying an EpiPen and an antihistamine with you at all times.

Avoiding alpha-gal hidden components

Mammalian proteins and parts can be found in many medications and medical products. . Because the source of many ingredients is not listed on product labels, your pharmacist may need to contact the manufacturer. Have your pharmacist ask specifically if it contains galactose-alpha-1,3-galactose, alpha-gal, mammalian meat, or any animal by-products.

Common sources of alpha-gal include:

  1. heart valve replacement derived from pig or cow,
  2. monoclonal antibodies (cetuximab)
  3. vaccines (zostavax, MMR and some flu),
  4. pancreatic enzyme replacement therapy,
  5. thyroid hormone replacement,
  6. fillers in medications (magnesium stearate, stearic acid, lactic acid, glycerin, gelatin, lactose)
  7. antivenom,
  8. protein powders,
  9. vaginal capsules
  10. heparin

Alpha-gal & co-infections

Ticks that carry alpha-gal are known to carry many other pathogens that can be simultaneously transmitted to humans. It is possible to acquire any of these other tick transmitted diseases and also have alpha-gal syndrome. It is also possible to have AGS alone.

Ticks that carry alpha-gal are known to carry many other pathogens

The lone star tick, the primary source of AGS in the U.S., is known to transmit the following diseases:

  • human monocytotropic ehrlichiosis (HME)
  • ehrlichiosis (Ehrlichia chaffeensis, Ehrlichia ewingii, and Panola Mountain ehrlichia)
  • Rocky Mountain spotted fever (RMSF)
  • tularemia (Francisella tularensis)
  • Heartland virus
  • Bourbon virus
  • Q fever
  • tick paralysis
  • STARI, an illness similar to Lyme disease, caused Borrelia lonestari
With alpha-gal recently discovered in blacklegged ticks, we may also begin to see an increase in AGS in patients with Lyme disease, anaplasmosis, babesiosis, ehrlichiosis, relapsing fever borreliosis, Powassan virus disease, and other diseases transmitted by these ticks.

How to prevent alpha-gal syndrome

For now, the best way to avoid getting AGS is to avoid tick bites. This means wearing tick repellent when working, hiking or playing in grassy or wooded areas where ticks are found. Protecting your pets and doing thorough tick checks after being outdoors is helpful.

If you are bitten by a tick, we suggest following these eight steps.

What to do if you have alpha-gal syndrome?

Learning you have an allergy to all mammalian products can be overwhelming. Because this is such a newly discovered condition there are few resources available.

When it comes to making medical decisions, it’s important to have a knowledgeable provider who understands the risks versus benefits of certain medications and procedures. Vaccines that contain gelatin are one of the riskier products, but if you need a rabies shot, for instance, your doctor may determine the benefits outweigh the risks and take the necessary steps to mitigate the adverse effects.

To learn more about the history, symptoms and how to diagnose alpha-gal syndrome listen to this interview with Dr. Scott Commins, of the University of North Carolina.

Additional help can be found at:

References:

  1. CDC | Alpha-gal allergy
  2. HHS | Alpha-Gal Syndrome Subcommittee Report to the Tick-Borne Disease Working Group
  3. Commins SP, Satinover SM, Hosen J, Mozena J, Borish L, Lewis BD, Woodfolk JA, Platts-Mills TA. (2009) Delayed anaphylaxis, angioedema, or urticaria after consumption of red meat in patients with IgE antibodies specific for galactose-alpha-1,3-galactose. J. Allergy and Clin Immunol 123(2):426-33. doi: 10.1016/j.jaci.2008.10.052.
  4. Commins, S. P., James, H. R., Kelly, L. A., Pochan, S. L., Workman, L. J., Perzanowski, M. S., Kocan, K. M., Fahy, J. V., Nganga, L. W., Ronmark, E., Cooper, P. J., & Platts-Mills, T. A. (2011). The relevance of tick bites to the production of IgE antibodies to the mammalian oligosaccharide galactose-α-1,3-galactose. J. Allergy and Clin Immunol, 127(5), 1286–93.e6. DOI: https://doi.org/10.1016/j.jaci.2011.02.019
  5. Commins SP (2020) Diagnosis & management of alpha-gal syndrome: lessons from 2,500 patients, Expert Review of Clinical Immunology, 16:7, 667-677, DOI: 10.1080/1744666X.2020.1782745
  6. Fiocchi A, Restani P, Riva E, Qualizza R, Bruni P, Restelli AR, Galli CL. (1995)  Meat allergy: I–Specific IgE to BSA and OSA in atopic, beef sensitive children. J Am Coll Nutr. 14(3):239-44. doi: 10.1080/07315724.1995.10718502. PMID: 8586772.
  7. Hamsten C, Tran TAT, Starkhammar M, Brauner A, Commins SP, Platts-Mills TAE, van Hage M. (2013) Red meat allergy in Sweden: association with tick sensitization and B-negative blood groups. J. Allergy and Clin Immunol. 132(6):1431-1434. doi: 10.1016/j.jaci.2013.07.050. Epub 2013 Oct 4. PMID: 24094548; PMCID: PMC4036066.
  8. Kuehn BM. (2018) Tick Bite Linked to Red Meat Allergy. JAMA. 23;319(4):332. doi: 10.1001/jama.2017.20802. PMID: 29362779.
  9. Mullins RJ, James H, Platts-Mills TA, Commins S.(2012) Relationship between red meat allergy and sensitization to gelatin and galactose-α-1,3-galactose. J. Allergy and Clin Immunol. 129(5):1334-1342.e1. doi: 10.1016/j.jaci.2012.02.038. Epub 2012 Apr 3. PMID: 22480538; PMCID: PMC3340561.
  10. Platts-Mills, TAE, Schuyler, AJ,Commins,SP, et. al ( 2018) Characterizing the Geographic Distribution of the Alpha-gal Syndrome: Relevance to Lone Star Ticks (Amblyomma americanum) and Rickettsia. J. Allergy and Clinical Immun 141;2. DOI: https://doi.org/10.1016/j.jaci.2017.12.470
  11. Wilson JM, Schuyler AJ, Workman L, Gupta M, James HR, Posthumus J, McGowan EC, Commins SP, Platts-Mills TAE.  (2019) Investigation into the α-Gal Syndrome: Characteristics of 261 Children and Adults Reporting Red Meat Allergy. J. Allergy and Clin Immunol Pract. 7(7):2348-2358.e4. doi: 10.1016/j.jaip.2019.03.031.

________________

**Comment**

I feel compelled to share the experiences of others as often it’s the only way we move forward in ‘Lymeland.’ In this case, many patients have been using ivermectin and fenbendazole with success. Make sure to work with your practitioner who knows everything you are taking as there can be synergystic effects and counter-indications for taking certain things together and/or due to medications/supplements for your pre-existing conditions. As always: this is never intended as medical advice or diagnosis.

In this case, a patient followed the advice of Dr. Makis and did two weeks of ivermectin and fenbendazole and then waited two weeks. She then consumed a 100% beef hamburger with no reactions. Prior to this treatment her life was extremely limited in that she couldn’t go out to eat or even attend family gatherings as she suffered with violent vomiting and anaphylaxis after ingestion, topical application, and even inhalation of any animal product.

While she does not mention specific dosages, the treatment was based upon Dr. Makis’ success treating Lyme disease in a similar fashion but using ivermectin and doxycycline. The protocol for that is

Ivermectin Cream applied topically on the tick bite

Doxycycline (100mg, 7 days a week for 30-60 days)

Ivermectin (1mg per 1kg body weight, 7 days a week for 30-60 days)

The rest of this protocol may also be beneficial, but not crucial for Lyme and Lone Star:

  • Tocotrienol and Tocopherol forms (all 8) of Vitamin E (400-800mg per day, 7 days a week). A product called Gamma E by Life Extension or Perfect E are both great.
  • Bio-Available Curcumin (600mg per day, 2 pills per day 7 days a week). A product called Theracurmin HP by Integrative Therapeutics is bioavailable.
  • Vitamin D (62.5 mcg [2500 IU] seven days a week).
  • CBD oil (1-2 droppers full [equal to 167 to 334 mg per day] under the tongue, 7 days a week) CBD-X: The most potent full spectrum organic CBD oil, with 5,000 milligrams of activated cannabinoids and hemp compounds CBD, CBN & CBG per serving.
  • Fenbendazole (300mg, 7 days a week) or in the case of severe turbo cancers up to 1 gram — for prophylaxis one 150mg tablet once or twice per week
  • Hydroxychloroquine (10mg/kg/day 7 days a week) – for prophylaxis one 200mg tablet once or twice per week
  • ImmunX immune support which also greatly increases the bioavailability of both Fenbendazole and Hydroxychloroquine (2 capsules per day)  for prophylaxis 2 capsules per day
  • Removing sugars and carbohydrates (cancer food) from your diet and replacing table sugar with a zero glycemic index, zero calorie, keto friendly rare sugar like AlluX

Differentiating RA from Lyme, Sleep Meds, & CD-57 Test

https://globallymealliance.org/dear-lyme-warrior-help-6/

lyme warrior
 

by Jennifer Crystal

Every few months, Jennifer Crystal devotes a column to answering your questions. Do you have a question for Jennifer? If so, email her at lymewarriorjennifercrystal@gmail.com.

How do you differentiate rheumatoid arthritis (RA) from Lyme disease?

These two diagnoses are often mixed up, since symptoms are similar. A good Lyme Literate Medical Doctor (LLMD) should be able to distinguish Lyme from rheumatoid arthritis (RA) and other conditions that Lyme can mimic, such as Chronic Fatigue Syndrome, Multiple Sclerosis (MS), and lupus. They will run specialized tests for Lyme and other tick-borne diseases, and will be able to make a clinical diagnosis.

Though both Lyme and RA can cause joint inflammation and pain, the way this pain presents can help doctors distinguish between the two. Pain from RA tends to be symmetrical; a patient might experience it in both hands, both wrists, or both knees. Conversely, Lyme pain tends to be localized and/or migratory; a patient might only have pain in one wrist, or might have an aching left elbow one day and an inflamed right knee the next.

In his book Why Can’t I Get Better? Solving the Mystery of Lyme & Chronic Disease, Richard I. Horowitz, MD notes, “Rheumatoid arthritis can look a lot like Lyme disease. Like lupus, it is a chronic systemic inflammatory disease that primarily affects the joints, but it also may involve inflammation in tendons, ligaments, muscle, bone, and many organs in the body. To establish a diagnosis of rheumatoid arthritis, the joint score (counting and mapping the joints involved at each visit), the presence of synovitis (inflammation in the synovial membrane surrounding the joints), and the physical exam (range of motion, presence of increased fluid in the joints, nodules, and deviations in the joints) are the focus of the criteria. We can get signs of inflammation in both diseases (including positive ANAs and rheumatoid factors), but the presence of positive anti-CCP antibodies differentiates it from Lyme disease and is a more specific marker for true rheumatoid arthritis.”

In one of your articles, you mentioned that you take medication to help you sleep. I am worried about being on an addictive sleep medication. I am happy to be able to sleep through the night now, but I struggle with the knowledge that I’m on this drug. Any advice?

I had these exact same concerns when I first started taking sleep medication more than ten years ago. I didn’t want to be on an addictive medication; I worried about long-term effects; and I wanted to be able to sleep naturally. Luckily, my doctors gave me some good advice. My LLMD reminded me that without sleep, my body could not heal from Lyme disease, babesiosis, ehrlichiosis, and chronic Epstein-Barr virus. My sleep doctor told me that Western medicine is good for a crisis situation, while Eastern medicine is good for getting at the root cause of a medical issue; both are necessary for optimal health. At my worst points of illness, I had literally been awake for weeks. That was a crisis situation that required narcotic sleep medication.

After a short period, that medication helped restore my system to a point where I could sleep with a non-addictive sleep aid. If I hadn’t taken the narcotic—which I did not become addicted to, despite my worries—I might never have gotten to that point.

The sleep medication I still take is considered non-addictive, though I’m sure I wouldn’t sleep without it. I have been on it under close supervision from my doctor for over a decade, and we have not seen any issues. I have never increased my dose. Would it be nice to be able to sleep naturally? Sure. But I’d prefer to be able to sleep at all, and if that means taking a controlled medication, then that’s what my body needs to function. My doctor calls this effective use of medication, versus abuse.

In addition to medication, I also do neurofeedback, and practice good sleep hygiene: I keep the same sleep and wake times, I shut down screens and do quieter activities before sleep, I don’t read or watch TV in bed, I keep my room quiet and dark, and I nap in the early afternoon. If you’re following good sleep hygiene and following your doctor’s recommendations for safely using medication, I think you can rest easy.

Is the CD-57 test accurate?

The CD-57 test is a marker of natural killer cells and T lymphocytes. In layman’s terms, it is a way of measuring immune function against persistent conditions such as Lyme disease. The IGeneX lab website states, “In cases of chronic diseases, including Lyme disease, the number of CD57 NK cells has been shown to be below normal.” They also recognize, though, that “the utility of this test is controversial…This test measures only the CD57 NK cells and may be useful for patients with known Lyme disease who present with chronic symptoms. If the count is low, the cause of symptoms may be from Borrelia burgdorferi. If the count is normal, the cause may still be from Lyme disease, but it could also be due to some other agent.”

I’m not a medical practitioner and I can’t give medical advice, but I can tell you about my own experience with this test. When I was first sick, my doctor ran this test often, but he was afraid I was getting too connected to the results when the real marker of whether I was getting better was how I was feeling. Since then, we haven’t tested it that often, but we have used it at critical junctures as a way to corroborate clinical evidence of relapse. The first time I thought I was in remission, my CD57 was very low (16; below 60 is considered active infection), but I felt great. Just a few months later, I completely relapsed, after a perfect storm of stress factors and no antibiotic defense enabled spirochetes to flare. The low CD57 marker, then, should have forewarned me that my body was in danger of relapse.

A decade later, I experienced another flare up of symptoms that felt closer to relapse than I’d been in a long time. Again, my CD57 was low. After some tweaks to treatment and additional rest, I started to feel better, and the number came up. So in my experience, the CD57 test has been helpful, but it isn’t a tell-all; I would not recommend using it strictly as a diagnostic tool.

For more blogs, click here


jennifer crystal_2

Opinions expressed by contributors are their own.

Jennifer Crystal is a writer and educator in Boston. Her memoir about her medical journey is forthcoming. Contact her at lymewarriorjennifercrystal@gmail.com.

_____________________

For more on sleep:  

More on the CD-57 test: