More young Canadians died from ‘unintentional side effects’ of the pandemic, not COVID
Author of the article: Denette Wilford
Publishing date: Jul 13, 2021
(Getty Images)GETTY IMAGES
A new report shows that during the pandemic, there were more deaths from “unintentional side effects” than COVID-19, particularly among younger Canadians.
The latest data from Statistics Canada, released Monday, is titled “Provisional death counts and excess mortality, January 2020 to April 2021,” and found there were 5,535 deaths in those younger than 65 years of age.
There were 1,380 COVID-related deaths for that same age group, according to StatCan.
That’s more than four times the amount of deaths.
The report from the Canadian Vital Statistics Death Database suggests that “the excess mortality is, in large part, related to other factors such as increases in the number deaths attributed to causes associated with substance use and misuse, including unintentional (accidental) poisonings and diseases and conditions related to alcohol consumption.”
Aside from in-person support being cut or reduced to social-distancing measures, StatCan also suggests the “economic, social, and psychological impacts of the pandemic as well as the public health measures in place may have played a role in increasing alcohol use among some individuals.”
Lawmakers push for Lyme disease research as tick population climbs
Changing climate conditions help drive up number of cases, as infecting insects thrive in warm, humid environments
Lyme disease is the most common vector-borne illness in the United States, appearing in all 50 states and the District of Columbia. (Edwin Remsberg/VWPics via Getty Images file photo)
Tick-borne disease is on the rise across the nation, and lawmakers are pushing to invest more this year in diagnostics and research to help the hundreds of thousands of Americans diagnosed with Lyme disease each year.
Lyme disease is the most common vector-borne illness in the United States, appearing in all 50 states and the District of Columbia. Roughly 476,000 Americans are diagnosed with Lyme every year, according to the Centers for Disease Control and Prevention. The number of actual infections is likely higher, experts say, as many infected people do not receive a test and Lyme disease tests are often inaccurate.
Although under diagnosed, Lyme costs the U.S. health care system more than $1.3 billion in direct U.S. medical costs, according to estimates, and tens of billions more in indirect medical costs.
“People know somebody who has Lyme, or they have constituents that have come to talk about it, and they all have the same story: It’s very difficult to diagnose and very difficult to treat,” Rep. Josh Gottheimer, a Congressional Lyme Caucus member, said in describing a recent groundswell of Capitol Hill interest.
(See link for article)
______________________
**Comment**
The problem with this article is many of the premises are inaccurate yet continually touted as established facts.
Ticks are marvelously ecoadaptive.They are impervious to weather. If they are stressed they will hide under leaf-litter, snow, mulch, plants, etc. When conditions are better, out they come. Independent research has proven this but has been ignored because the ‘climate change’ agenda is powerful and backed by a lot of money and powerful people/institutions who profit from it.
The fact there isn’t accepted treatment should indicate there is a sordid back-story that isn’t being told by our corrupt public health ‘authorities.’ Similarly to COVID, there are effective treatments(although admittedly individually determined) that continue to be ignored, censored, and denied. This has gone on for over 40 years and continues to this day.
The fact testing isn’t reliable also indicates a fundamental flaw in this story. Due to the false stance taken on this complex illness, and the fact the only accepted research is done by a conflict-riddledCabal, we remain and will continue to remain in the Dark Ages with Lyme/MSIDS.
The federal government is always whining about needing more money, despite the fact the CDC’s operating budget has averaged about $7.2 billion per year since 2016. It’s budget was $10 billion in 2008 before Congressional investigations found that the agency wastes millions and spends lavishly. For example, It spent:
The CDC spent its AIDS and HIV Prevention fund in 2007 on erotic writing, a drag queen contest, and a San Francisco workshop called “how to flirt with greater finesse.”
The CDC is NOT a neutral government agency, and has its own private slush fund called the CDC Foundation. The Bill and Melinda Gates Foundation has given $2.3 million so far to the CDC in 2021. You can see all Gates to CDC contributions here, and only the United States government gives more to the World Health Organization than the Gates Foundation.
The CDC Foundation’s other donors come from pharmaceutical companies and big tech firms such as Bayer, Facebook, GlaxoSmithKline and Merck. They sell drugs and don’t care about public health. These relationships are incestuous – for example, former CDC chief Julie Gerberding left her position at the CDC to become President of Merck’s vaccine division.
Regarding the increasing tick population, it is highly probable our own government is partially if not wholly to blame. (This is another reason they push the climate agenda. It’s a slight of hand to stop us from asking relevant questions.)
The reference to COVID must be addressed. The only reason it is considered a ‘pandemic’ is due to the WHO changing the definition 1 month before the Swine Flu ‘pandemic’ that wasn’t, and taking away the criteria that it is highly deadly – because COVID is not highly deadly, with the vast majority being asymptomatic or mild cases.
The push for more federal funding to go to the exact people who have done nothing for Lyme/MSIDS patients for over 40 years is illogical. I completely disagree that the “lack of funding contributes to major knowledge gaps surrounding the disease.” What is causing major knowledge gaps is scientific bias and conflicts of interests.Until those are dealt with, we will get no where.
It is well established that early detection is imperative; however, doctors due to the IDSA guidelines continue to take a “wait and see” approach, delaying life-saving treatment. These same people refuse to treat people with obvious Lyme rashes and make up all kinds of excuses. And, of course, many never see or get the rash at all.
While I surely do not have all the answers, one thing I do know: giving our corrupt public health ‘authorities’ more money to continue doing biased research is NOT the answer. They’ve been using sick patients to raise monies for their own nefarious ends for far, far too long. Insanity is doing something over and over and expecting different results. Time to take our precious pennies and put them toward independent research.
The physical symptoms of chronic Lyme disease and fibromyalgia are challenging on their own. But when your mental capacities start to waver, it can take levels of frustration and fear to a whole new level.
Why are Lyme and fibromyalgia sufferers so prone to brain and neurological symptoms, and what can you do to find effective and lasting relief?
Join an updated live webinar with Dr. Bill Rawls, author of the best-selling book Unlocking Lyme, who knows firsthand what it’s like to live with Lyme brain and fibro fog. He’ll explain why Lyme disease and fibromyalgia tend to target the brain, and share insights on the best herbs and other natural lifestyle remedies for overcoming symptoms and reducing the risk and severity of long-term degenerative cognitive conditions such as dementia.
You’ll learn exactly what you need to clear the fog and restore healthy cognitive and neurological function, so that you can get back to thinking and feeling like yourself again.
• Why cognitive symptoms like confusion, short-term memory loss, anxiety, anger, and depression are so common in chronic illness patients such as those with Lyme disease, fibromyalgia, and Long COVID.
• How microbes, inflammation, and immune dysfunction disrupt cognitive function
• The best herbs and natural remedies for restoring and protecting brain health
• Numerous insights during the live Q&A with Dr. Rawls
About Dr. Bill Rawls
Bill Rawls, M.D., is a physician and leading expert in Lyme disease, integrative health, and herbal medicine. In the middle of his successful medical career, Dr. Rawls’ life was interrupted by Lyme disease. In his journey to overcome it, he explored nearly every treatment possible – from conventional medicine to a range of alternative therapies. In the more than 12 years since his recovery, Dr. Rawls has helped thousands of patients find their path to healing from Lyme disease and chronic illness. He is the author of the best-selling book Unlocking Lyme, and the Medical Director of RawlsMD.com and Vital Plan, an online holistic health company and Certified B Corporation®.
The vast majority of people who are getting injected for the Wuhan coronavirus (Covid-19) will die within a few short years from heart failure, warns Dr. Charles Hoffe, M.D., a medical practitioner in British Columbia, Canada.
In one of his latest updates, Dr. Hoffe explains that he is observing in his patients who took an mRNA (messenger RNA) “vaccine” from either Pfizer-BioNTech or Moderna that their capillaries are now plugging up, which he says will eventually lead to a serious cardiovascular event.
No fewer than 60 percent of people who take an mRNA injection will suffer from these blood clots – and in the end, an overwhelming majority will end up six feet under due to the damage caused.
“We now know that only 25 percent of the ‘vaccine’ injected into a person’s arm actually stays in your arm,” Dr. Hoffe explains one his blog.
“The other 75 percent is collected by your lymphatic system and literally fed into your circulation so these little packages of messenger RNA, and by the way in a single dose of Moderna ‘vaccine’ there are literally 40 trillion mRNA molecules.”
This panel of doctors also explain the mechanism of COVID injection injury. The spike protein circulates throughout the entire body.
**Comment**
After having patients complain of breathlessness and other concerning symptoms, Dr. Hoffe has been performing D-dimer tests on these “vaccinated” patients, which led him to discover that at least 62 percent of them have microscopic blood clots.
The idea of altered blood cells due to COVID isn’t new, a fact this website posted on back in May 2020 due to the seminal work of Italian pathologists utilizing 50 autopsies showing micro throbs, in the heart, brain, and kidneys, meaning the patients did not die of interstitial pneumonia as told initially, they died from a blood condition called disseminated intravascular coagulation (DIC) also found in the x-rays of the lungs.
It is only logical that the injections used for COVID would also alter blood vessels, and this is being seen on a daily basis.
In June, a study came out showing hyperinflammatory responses and coagulation disorders leading to congestions of microvessels to be key drivers. The authors found significant changes in lymphocyte stiffness, monocyte size, neutrophil size and deformability, and heterogeneity of erythrocyte deformation and size. Although some of these changes recovered to normal values after hospitalization, others persisted for months after hospital discharge, evidencing the long-term imprint of COVID-19 on the body.
The good news of course is there are cheap, effectivetreatments for COVID. Unfortunately, these treatments are being highly censored.
Please notice the word microscopic blood clots. This means it will not be picked up unless looked for specifically utilizing specific tools. This is also where you should question to word rare, in that ‘authorities’ are stating it’s a rare occurrence. There are numerous reasons for an effect to go unnoticed. One reason would be they are utilizing the wrong tools when looking for it, and the other is doctors, let alone patients, don’t even know about the VAERS reporting system (click on link to see the plethora of blood clotting cases) – as only 1% of vaccine injuries are reported.
The reason this should be especially concerning to Lyme/MSIDS patients is because a Russian study shows Lyme can also cause blood clots. Coinfections can as well, as risk factors for splanchnic vein thrombosis include infections.
Interestingly, heparin, a blood thinner, helps many MSIDS patients: http://aac.asm.org/content/48/1/236.full.pdf Similarly with Bartonella, some respond miraculously to Heparin, which is a blood thinner. In the above link, heparin was found to inhibit Babesia growth. Horowitz also found it helps clear the parasites from the body.
Heparin helped my husband immensely. His blood looked like snot and continually clotted in catheters. He immediately felt improvement (energy, clearer mind) when heparin was added to his treatment protocol.
Hopefully it’s clear that infected Lyme/MSIDS patients are already in a high risk category due to infections. Getting an experimental, fast-tracked injection known to cause blood clots on top of this risk is dangerous.
Important quote:
“The most alarming part of this is that there are some parts of the body like the brain, spinal cord, heart and lungs which cannot [regenerate],” he says. “When those tissues are damaged by blood clots, they are permanently damaged.” Dr. Hoffe
I just posted a perfect example of that here. A man went into the ER with a severe headache after the COVID shot. While there, he was diagnosed with Lyme Disease.
DOCTORS BELIEVE SPAULDING’S IMMUNE SYSTEM, WHICH WAS FIGHTING LYME DISEASE, WAS OVERSTIMULATED BY THE COVID VACCINE CAUSING IT TO ATTACK THE MYELIN — THE PROTECTIVE INSULATION THAT SURROUNDS NERVES, INCLUDING THOSE IN THE BRAIN AND SPINAL CORD.
Treatment was immediate and successful in arresting the progression of the disease, but not before Spaulding was almost completely paralyzed.
Almost completely paralyzed.
The insanity of what’s occurring in the world can not be overstated. Workers are now going door to door trying to get people to receive these injections. Further, our current regime is planning to work with SMS carriers to dispel misinformation about vaccines that is sent over social media and text messages. In other words, censor your private communications.
This should trouble you.
These door to door workers have no medical training, do not know your medical history, but are trying to force you to make a major medical decision on the spot. Don’t fall for it.Don’t give them information, just ask them to leave. Do not allow bullies to affect your personal medical decision.
Your decision to receive medical treatment, including injections, is between you and your health care professional. Shame on our government. They are an embarrassment.
Go here for a great read written by a Constitutional attorney on the topic of door to door COVID strike-force teams.
Ivermectin is an antiparasitic drug that may be even more useful against COVID-19 than hydroxychloroquine (HCQ). However, like HCQ, use of ivermectin has been globally suppressed, discouraged and even warned against, despite decades of safe use for other ailments
In the U.S., the Frontline COVID-19 Critical Care Alliance (FLCCC) has been calling for widespread adoption of Ivermectin, both as a prophylactic and for the treatment of all phases of COVID-19
What makes ivermectin particularly useful in COVID-19 is the fact that it works both in the initial viral phase of the illness, when antivirals are required, as well as in the inflammatory stage, when the viral load drops off and anti-inflammatories become necessary
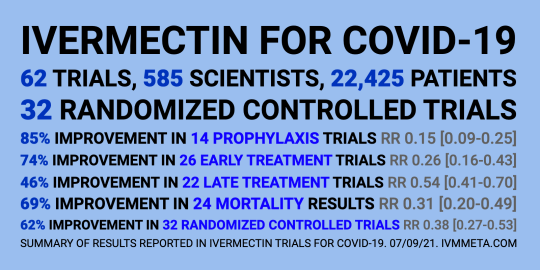
A scientific review funded by the WHO found ivermectin reduced COVID-19 deaths by 75%. It also increased viral clearance. A meta-analysis of a greater number of studies found a 68% reduction in deaths
Despite robust scientific support for ivermectin, the WHO, the U.S. FDA and NIH all refuse to recommend the drug on grounds of insufficient evidence
When it comes to the treatment of COVID-19, many Western nations have been hobbled by the politicization of medicine. Throughout 2020, media and many public health experts warned against the use of hydroxychloroquine (HCQ), despite the fact that many practicing doctors were praising its ability to save patients. Most have been silenced through online censorship. Some even lost their jobs for the “sin” of publicly sharing their successes with the drug.
Another decades-old antiparasitic drug that may be even more useful than HCQ is ivermectin. Like HCQ, ivermectin is on the World Health Organization’s list of essential drugs, but its benefits are also being ignored by public health officials and buried by mainstream media.
Ivermectin is a heartworm medication that has been shown to inhibit SARS-CoV-2 replication in vitro.1 In the U.S., the Frontline COVID-19 Critical Care Alliance (FLCCC) has been calling for widespread adoption of Ivermectin, both as a prophylactic and for the treatment of all phases of COVID-19.2,3
In the video above, Dr. John Campbell interviews Dr. Tess Lawrie about the drug and its use against COVID-19. Lawrie is a medical doctor and Ph.D. researcher who has done a lot of work in South Africa.
She’s also the director of Evidence-Based Medicine Consultancy Ltd.,4 which is based in the U.K., and she helped organize the British Ivermectin Recommendation Development (BIRD) panel5 and the International Ivermectin for COVID Conference, held April 24, 2021.
Ironically, as a consultant to the World Health Organization and many other public health organizations, her largest clients are the very ones who are now actively suppressing the use of this drug.
Ivermectin Useful in All Stages of COVID
What makes ivermectin particularly useful in COVID-19 is the fact that it works both in the initial viral phase of the illness, when antivirals are required, as well as the inflammatory stage, when the viral load drops off and anti-inflammatories become necessary.
According to Dr. Surya Kant, a medical doctor in India who has written a white paper6 on ivermectin, the drug reduces replication of the SARS-CoV-2 virus by several thousand times.7 Kant’s paper led several Indian provinces to start using ivermectin, both as a prophylactic and as treatment for COVID-19 in the summer of 2020.8
In the video, Lawrie reviews the science behind her recommendation to use ivermectin. In summary:
•A scientific review by Dr. Andrew Hill at Liverpool University, funded by the WHO and UNITAID and published January 18, 2021, found ivermectin reduced COVID-19 deaths by 75%. It also increased viral clearance. This finding was based on a review of six randomized, controlled trials involving a total of 1,255 patients.
•Lawrie’s meta-analysis, published February 8, 2021, found a 68% reduction in deaths. Here, 13 studies were included in the analysis. This, she explains, is an underestimation of the beneficial effect, because they included a study in which the control arm was given HCQ.
Since HCQ is an active treatment that has also been shown to have a positive impact on outcomes, it’s not surprising that this particular study did not rate ivermectin as better than the control treatment (which was HCQ).
•Adding two new randomized controlled trials to her February analysis that included data on mortality, Lawrie published an updated analysis March 31, 2021, showing a 62% reduction in deaths.
When four studies with high risk of bias were removed during a subsequent sensitivity analysis, they ended up with a 72% reduction in deaths. Sensitivity analyses are done to double-check and verify results.
WHO Still Refuses to Recommend Ivermectin
Curiously, when the WHO finally updated its guidance on ivermectin at the end of March 2021,9,10 they gave it a thumbs-down, saying more data are needed. They only recommend it for patients who are enrolled in a clinical trial. Yet they based their negative recommendation on a review that included just five studies, which ended up showing a 72% reduction in deaths.
Lawrie points out discrepancies in this WHO analysis, such as two studies deemed by Lawrie to have a high risk of bias being listed by the WHO team to have a low risk of bias. (In the interview, she explains why she considers them to have a high risk of bias.)
What’s more, in the WHO’s summary of findings, they suddenly include data from seven studies, which combined show an 81% reduction in deaths. The confidence interval is also surprisingly high, with a 64% reduction in deaths on the low end, and 91% on the high end.
What’s more, their absolute effect estimate for standard of care is 70 deaths per 1,000, compared to just 14 deaths per 1,000 when treating with ivermectin. That’s a reduction in deaths of 56 per 1,000 when using ivermectin. The confidence interval is between 44 and 63 fewer deaths per 1,000.
Despite that, the WHO refuses to recommend this drug for COVID-19. Rabindra Abeyasinghe, a WHO representative to the Philippines, commented that using ivermectin without “strong” evidence is “harmful” because it can give “false confidence” to the public.11
As noted by Daniel Horowitz in an April 1, 2021, article in The Blaze,12 “That sure sounds a lot like telling people if they wear a mask indoors, they won’t get COVID. Tragically, when they invariably do get the virus, the global health elites have nothing to treat them with.”
Doctors Urge Acceptance of Ivermectin to Save Lives
As mentioned earlier, in the U.S., the FLCCC has also been calling for widespread adoption of ivermectin, both as a prophylactic and for the treatment of all phases of COVID-19.13,14
FLCCC president Dr. Pierre Kory, former professor of medicine at St. Luke’s Aurora Medical Center in Milwaukee, Wisconsin, has testified to the benefits of ivermectin before a number of COVID-19 panels, including the Senate Committee on Homeland Security and Governmental Affairs in December 2020,15 and the National Institutes of Health COVID-19 Treatment Guidelines Panel January 6, 2021.16 As noted by the FLCCC:17
“The data shows the ability of the drug Ivermectin to prevent COVID-19, to keep those with early symptoms from progressing to the hyper-inflammatory phase of the disease, and even to help critically ill patients recover.
Dr. Kory testified that Ivermectin is effectively a ‘miracle drug’ against COVID-19 and called upon the government’s medical authorities … to urgently review the latest data and then issue guidelines for physicians, nurse-practitioners, and physician assistants to prescribe Ivermectin for COVID-1918 …
… numerous clinical studies — including peer-reviewed randomized controlled trials — showed large magnitude benefits of Ivermectin in prophylaxis, early treatment and also in late-stage disease. Taken together … dozens of clinical trials that have now emerged from around the world are substantial enough to reliably assess clinical efficacy.
… data from 18 randomized controlled trials that included over 2,100 patients … demonstrated that Ivermectin produces faster viral clearance, faster time to hospital discharge, faster time to clinical recovery, and a 75% reduction in mortality rates.”19
A one-page summary20 of the clinical trial evidence for Ivermectin can be downloaded from the FLCCC website. A more comprehensive, 31-page review21 of trials data has been published in the journal Frontiers of Pharmacology.
At the time of this writing, the number of trials involving ivermectin has risen to 55, including 28 randomized controlled trials. A listing of all the Ivermectin trials done to date, with links to the published studies, can be found on c19Ivermectin.com.22
The FLCCC’s COVID-19 protocol was initially dubbed MATH+ (an acronym based on the key components of the treatment), but after several tweaks and updates, the prophylaxis and early outpatient treatment protocol is now known as I-MASK+23 while the hospital treatment has been renamed I-MATH+,24 due to the addition of ivermectin.
The two protocols25,26 are available for download on the FLCCC Alliance website in multiple languages. The clinical and scientific rationale for the I-MATH+ hospital protocol has also been peer-reviewed and was published in the Journal of Intensive Care Medicine27 in mid-December 2020.
NIH Loosens Restrictions, FDA Warns Against Prophylactic Use
In mid-January 2021, the NIH did revise its guidelines on ivermectin, in large part thanks to the data presented by Kory and others. However, while the NIH no longer warns against its use, they also do not outright recommend it, and they did not grant ivermectin emergency use authorization.
As a result, many patients in the U.S. still struggle to access the drug, as many doctors are unwilling to prescribe it off-label against health officials’ recommendations.
The U.S. Food and Drug Administration has adopted an even less favorable stance, March 9, 2021 actually issuing a consumer warning March 5, 2021, to not use ivermectin as a prophylactic.28 The FDA also has not approved ivermectin for prevention of or treatment for SARS-CoV-2.29
The International Ivermectin for COVID Conference
April 24 through 25, 2021, Lawrie hosted the first International Ivermectin for COVID Conference online.30 Twelve medical experts31 from around the world shared their knowledge during this conference, reviewing mechanism of action, protocols for prevention and treatment, including so-called long-hauler syndrome, research findings and real world data.
All of the lectures, which were recorded via Zoom, can be viewed on Bird-Group.org.32 In her closing address, Lawrie stated:33
“The story of Ivermectin has highlighted that we are at a remarkable juncture in medical history. The tools that we use to heal and our connection with our patients are being systematically undermined by relentless disinformation stemming from corporate greed.
The story of Ivermectin shows that we as a public have misplaced our trust in the authorities and have underestimated the extent to which money and power corrupts.
Had Ivermectin being employed in 2020 when medical colleagues around the world first alerted the authorities to its efficacy, millions of lives could have been saved, and the pandemic with all its associated suffering and loss brought to a rapid and timely end.
Since then, hundreds of millions of people have been involved in the largest medical experiment in human history. Mass vaccination was an unproven novel therapy. Hundreds of billions will be made by Big Pharma and paid for by the public.
With politicians and other non-medical individuals dictating to us what we are allowed to prescribe to the ill, we as doctors, have been put in a position such that our ability to uphold the Hippocratic oath is under attack.
At this fateful juncture, we must therefore choose, will we continue to be held ransom by corrupt organizations, health authorities, Big Pharma, and billionaire sociopaths, or will we do our moral and professional duty to do no harm and always do the best for those in our care?
The latter includes urgently reaching out to colleagues around the world to discuss which of our tried and tested safe older medicines can be used against COVID.”
During the conference, Lawrie proposed that doctors around the world join together to form a new people-centered World Health Organization. “Never before has our role as doctors been so important because never before have we become complicit in causing so much harm,” she said.
“We now have four large randomized control trials totaling over 1,500 patients each trial showing that as a prophylaxis agent [against COVID-19] it is immensely effective,” Kory said. “You will not get sick. You will be protected from getting ill if you take it in early outpatient treatment.”