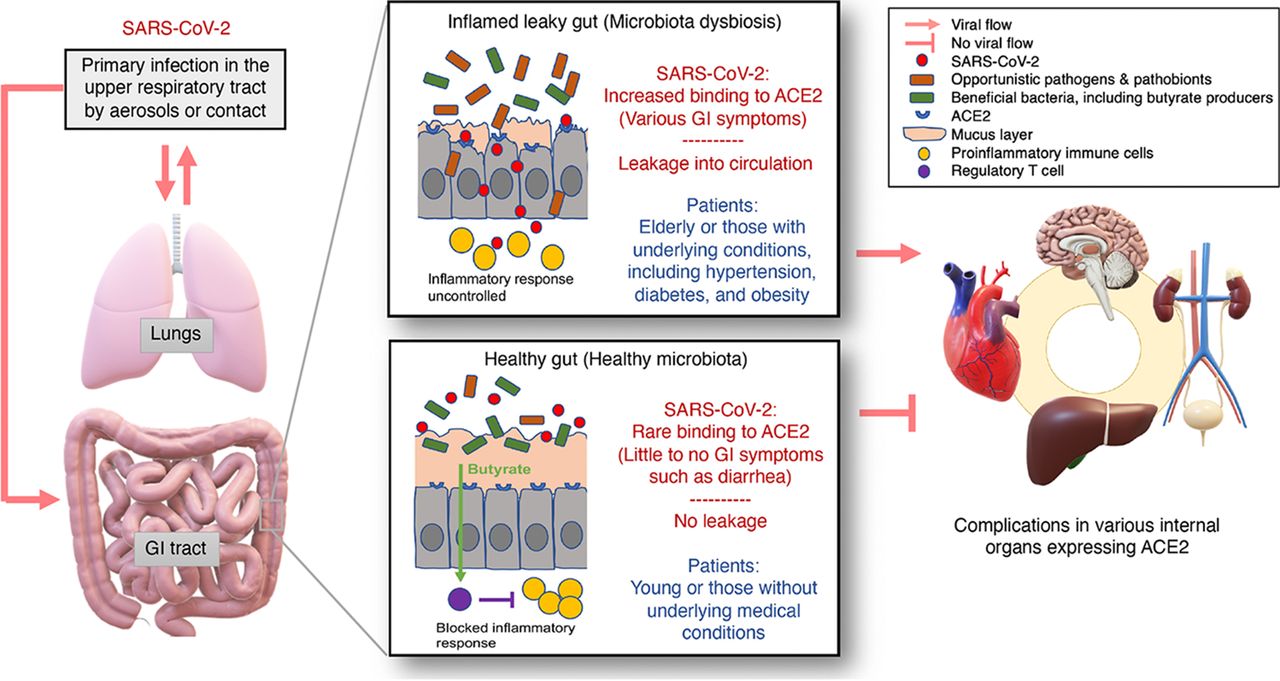
https://journals.asm.org/doi/10.1128/mbio.03022-20?

mBio

Volume 12, Number 1
23 February 2021
 
ABSTRACT
 
Coronavirus disease 2019 (COVID-19), which has been declared a pandemic, has exhibited a wide range of severity worldwide. Although this global variation is largely affected by socio-medical situations in each country, there is also high individual-level variation attributable to elderliness and certain underlying medical conditions, including high blood pressure, diabetes, and obesity. As both elderliness and the aforementioned chronic conditions are often associated with an altered gut microbiota, resulting in disrupted gut barrier integrity, and gut symptoms have consistently been associated with more severe illness in COVID-19 patients, it is possible that dysfunction of the gut as a whole influences COVID-19 severity. This article summarizes the accumulating evidence that supports the hypothesis that an altered gut microbiota and its associated leaky gut may contribute to the onset of gastrointestinal symptoms and occasionally to additional multiorgan complications that may lead to severe illness by allowing leakage of the causative coronavirus into the circulatory system.
 

For more: 

https://www.activistpost.com/2021/09/september-is-suicide-prevention-month-cell-phone-and-wifi-radiation-can-disrupt-the-blood-brain-barrier-cause-it-to-leak-etc.

September is Suicide Prevention Month; Cell Phone and WiFi Radiation Can Disrupt the Blood Brain Barrier, Cause it to Leak, etc.

By B.N. Frank

While genetics as well as poor diet and lifestyle choices can have significant impacts on behavioral, emotional, mental, and physical health, environmental toxins can play a role too.  Research has already determined that exposure to sources of wireless radiation is biologically harmful (see 1, 2, 3).  In fact, it can actually disrupt the blood-brain barrier (see 1, 2).

Need more research links?  See 1, 2, 3, 4, 5, 6, 7, 8, 9, 10.

Of course there are definitely other environmental toxins that can also cause brain and mental health issues.  If you’re feeling blue, it’s not a bad idea to think about reducing exposure to them too. (See link for videos)

___________________

**UPDATE**

The FCC knew cell phones exceeded radiation limits but hid this from the public and from the courts.

https://www.activistpost.com/2021/09/the-dubious-history-of-u-s-wireless-radiation-safety-limits-no-update-since-1996-despite-research-and-lawsuits

The Dubious History of U.S. Wireless Radiation Safety Limits; No Update Since 1996 Despite Research and Lawsuits

By B.N. Frank

The Federal Communications Commission (FCC) is supposed to protect Americans from the telecom and cable industries.  Instead, the regulatory agency has catered to these industries for decades (see 1, 2).  Lawsuits have been filed against it for NOT protecting the public from unsafe levels of cell phone and WiFi radiation, 5G on Earth (see 1, 2, 3, 4, 5, 6), in space (see 1, 2) and also for allowing telecom and cable companies to overcharge Americans for decades.

Last month, a federal court ruled in favor of organizations and petitioners that claim the agency is not adequately protecting the public from harmful wireless radiation exposure.

Thanks to Environmental Health Trust for creating and posting this tell-all timeline:  (See link for article)

____________________

**Comment**

I must also add that Big Pharma and corrupt public health ‘authorities’ also want us to believe that “vaccines” are “safe and effective.”

The problem is, has always been, and will always be – this is a false statement. 

https://www.lymedisease.org/revisiting-anthropologists-view/

TOUCHED BY LYME: Revisiting an anthropologist’s view of Lyme-related suicide

I first came across Aaron Jackson in 2018, when he submitted a guest blog for our website. It was titled An anthropologist’s view of Lyme disease and suicide.

Aaron was the anthropologist in question. As a Lyme-infected person who had tried to take his own life, he was uniquely qualified to discuss this topic.

His article clearly hit a responsive chord with our readers. It became one of our website’s most-accessed blogs that year.

I recently heard from Aaron again. He lives and works in Australia now. His research focuses on fatherhood, caregiving, and disability.

He has written a book called “Worlds of Care: The Emotional Lives of Fathers Caring for Children with Disabilities,” recently published by University of California Press.

Aaron was propelled into the world of caregiving after the birth of his severely disabled son, Takoda. The book uses his personal experience caring for Takoda as a springboard for larger discussions about fatherhood, caregiving and our cultural ideas of masculinity.

He also includes some of his personal experience with Lyme disease. The following excerpt of his book talks about how Lyme thrust him into the depths of despair, and what ultimately came of it.

Worlds of Care

My ordinary patterns of everyday life deteriorated. The world around me no longer hummed with vibrancy or possibility. I couldn’t climb a short flight of stairs without almost collapsing, forget about kickboxing. I no longer had the stamina to play with my children or take care of them the way I was used to doing.

The roles and responsibilities that shored up my identity as a father and caregiver were lost to me. I became dependent on my spouse for care.

So, on a quiet morning at the end of summer, I tried to take my life

˜˜˜˜

A poignant epilogue to the book tells us that young Takoda died unexpectedly in his sleep in 2019. He was 8 years old.  (See link for article)

Click here for more information about the book. You can follow Aaron Jackson on Twitter @Kodacruz.

TOUCHED BY LYME is written by Dorothy Kupcha Leland, LymeDisease.org’s Vice-president and Director of Communications. She is co-author of When Your Child Has Lyme Disease: A Parent’s Survival Guide. Contact her at dleland@lymedisease.org .

_____________________

For more:

https://www.nejm.org/doi/full/10.1056/NEJMc2112974?

Vaccine-Induced Thrombocytopenia with Severe Headache

To the Editor:

Vaccine-induced immune thrombotic thrombocytopenia (VITT), a serious adverse event after vaccination with ChAdOx1 nCoV-19 (AstraZeneca) or Ad26.COV2.S (Johnson & Johnson–Janssen), is caused by platelet factor 4 (PF4)–dependent, platelet-activating antibodies.1-3 High-dose immune globulins and anticoagulation are the main treatments.4,5 In this report, we present evidence that vaccine-induced thrombocytopenia (VIT) without associated cerebral venous sinus thrombosis (CVST) or other thromboses and with severe headache as the heraldic symptom may precede VITT (“pre-VITT syndrome”).

Eleven patients presented with severe headache in the absence of CVST 5 to 18 days after ChAdOx1 nCoV-19 vaccination.

  • All the patients had thrombocytopenia (low platelets in the blood which can cause hemorrhaging)
  • high d-dimer levels (a test to detect blood clots – a high level indicates clot formation and breakdown in the body)
  • high levels of anti–PF4–heparin IgG antibodies
  • during follow-up, intracranial hemorrhage occurred in three patients (Patients 1, 2, and 3), with radiologic evidence of new CVST in Patients 2 and 3 (Figure 1, and Table S1 in the Supplementary Appendix, available with the full text of this letter at NEJM.org).
  • Only two patients (Patients 2 and 4) were initially admitted with conditions that met the criteria for VITT; both patients had pulmonary embolism, and additional splanchnic vein thrombosis was present in Patient 2.

In Patient 2, anticoagulation treatment had been initiated several days earlier for pulmonary embolism (without diagnosis of VITT) but was stopped after the onset of headache, shortly before CVST developed.

  • In two patients (Patients 1 and 3), peripheral thromboses were eventually identified during follow-up.

Thrombotic complications did not develop in seven of the patients (Patients 5 through 11); all but one of these patients received high-dose immune globulin, glucocorticoids, or therapeutic-dose anticoagulation within 5 days after headache onset. In contrast, in all four patients with subsequent thrombosis (Patients 1 through 4), therapeutic-dose anticoagulation either was not started until 6 to 9 days after headache onset or was stopped prematurely before the development of CVST.

Although the combination of thrombocytopenia and severe headache due to CVST has been recognized as the typical presentation of VITT,1,2 the experience with these 11 patients suggests that VIT with severe headache, elevated d-dimer levels, and strongly positive results on anti–PF4–heparin IgG enzyme-linked immunosorbent assay may precede VITT.

Our findings have immediate implications for clinical practice: in this pre-VITT syndrome, severe headache may not develop as a symptom secondary to CVST but instead may precede CVST by several days, potentially in association with microthrombosis in smaller cortical veins.

Consequently, patients who present with severe headache 5 to 20 days after adenovirus vector vaccination against coronavirus disease 2019 should undergo immediate testing for thrombocytopenia and d-dimer levels and, if available, testing for anti–PF4–heparin IgG antibodies.

When these antibodies are present at high titers, patients are at imminent risk for CVST, and it is likely that this condition can be prevented with immediate treatment, such as with intravenous immune globulin. The decision to initiate therapeutic-dose anticoagulation is a difficult one; the risk of emerging thrombosis, including CVST, has to be balanced against the risk of intracranial hemorrhage on an individual basis (e.g., with consideration of platelet count and fibrinogen levels).

Farid Salih, M.D.
Charité-Universitätsmedizin Berlin, Berlin, Germany

Linda Schönborn, M.D.
Universitätsmedizin Greifswald, Greifswald, Germany

Siegfried Kohler, M.D., Christiana Franke, M.D., Martin Möckel, M.D., Thomas Dörner, M.D., Hans C. Bauknecht, M.D., Christian Pille, M.D., Jan A. Graw, M.D.
Charité-Universitätsmedizin Berlin, Berlin, Germany

Angelika Alonso, M.D.
University Hospital of Mannheim, Mannheim, Germany

Johann Pelz, M.D.
University Hospital of Leipzig, Leipzig, Germany

Hauke Schneider, M.D., Antonios Bayas, M.D., Monika Christ, M.D.
University Hospital of Augsburg, Augsburg, Germany

Joji B. Kuramatsu, M.D.
University Hospital of Erlangen, Erlangen, Germany

Thomas Thiele, M.D., Andreas Greinacher, M.D.
Universitätsmedizin Greifswald, Greifswald, Germany

Matthias Endres, M.D.
Charité-Universitätsmedizin Berlin, Berlin, Germany

Supported by Deutsche Forschungsgemeinschaft project number 374031971–TRR 240 (to Prof. Greinacher) and EXC-2049–390688087 NeuroCure under the German Excellence Strategy (to Prof. Endres) and by the Domagk-Programm of the Universitätsmedizin Greifswald (to Dr. Schönborn).

Disclosure forms provided by the authors are available with the full text of this letter at NEJM.org.

This letter was published on September 15, 2021, at NEJM.org.

Profs. Greinacher and Endres contributed equally to this letter.

___________________

**Comment**

Both Thrombocytopenia and severe headaches are common with Lyme/MSIDS patients.

Therapy for thrombocytopenia requires treatment or removal of the underlying infection, in addition to maintenance of platelet counts and hemostatic function.

Hopefully it’s clear that a Lyme/MSIDS patient getting a COVID shot could be diagnosed with thrombocytopenia that either already exists or worsens after the injection.  Treating the underlying infection is imperative but won’t be considered by mainstream medicine.

For more:

Go here for the latest VAERS data and the mounting list of adverse reactions and deaths.

https://thenewamerican.com/new-study-half-of-hospitalized-covid-patients-have-mild-case-are-asymptomatic-or-in-hospital-for-another-reason/

New Study: Half of Hospitalized COVID Patients Have Mild Case, Are Asymptomatic, or in Hospital for Another Reason

New Study: Half of Hospitalized COVID Patients Have Mild Case, Are Asymptomatic, or in Hospital for Another Reason
Hispanolistic/E+/Getty Images

About three million people in the United States with the China Virus have been admitted to hospitals in the past year, data from the Centers for Disease Controls show.

Yet not all of those hospitalized with the virus were hospitalized because of the virus. Instead, the Atlantic reported on September 13, they went into the hospital for another reason, but tested positive after they were there.

That means the data on hospitalizations with the virus might not tell us what we think it does.

(See link for article)

_______________________
**Comment**
Once again, data is being twisted to provoke fear for a bigger agenda.

The important issue here is how the “virus” is affecting any given individual.

Due to vast testing being done at hospitals, they are recording incidental COVID cases that never would have been recorded otherwise. The past CDC director has admitted that hospitals have a monetary incentive to over count COVID deaths.  This has occurred in Wisconsin and in every state.  It’s notoriously been done in nursing homes.  Remember that even the CDC has withdrawn EUA for the PCR test as it can’t distinguish between COVID and the flu.  Further, the CDC stopped counting the flu to purposely pad COVID cases.

Important quotes:

Let’s read that again: About 50 percent of COVID-positive VA patients in the hospital were there for another reason or had a mild case of the disease.

Of vaccinated patients, 57 percent presented with mild or asymptomatic disease, and “unvaccinated patients have also been showing up with less severe symptoms, on average, than earlier in the pandemic,” the Atlantic reported:

While the authors want to give credit to the “vaccines”, historically it is known that viruses weaken over time.

The most logical conclusion is to refine the definition of hospitalization.

 “Those patients who are there with rather than from COVID don’t belong in the metric.”

I’m not downplaying the fact people can become very ill from COVID.  I was one such case.  What is despicable; however, is the fact our corrupt public health ‘authorities’ are censoring and denying cheap, effective, successful treatments that is killing thousands upon thousands as well as continues to push a narrative that our only hope is a fast-tracked, experimental gene therapy injection that is literally maiming and killing thousands more.