US COVID-19 Vaccines Proven to Cause More Harm than Good Based on Pivotal Clinical Trial Data Analyzed Using the Proper Scientific Endpoint, “All Cause Severe Morbidity”
Classen Immunotherapies, Inc, 3637 Rockdale Road, Manchester, MD J. Bart Classen, MD* Trends in Internal Medicine Research ArticleCitation: Classen B. US COVID-19 Vaccines Proven to Cause More Harm than Good Based on Pivotal Clinical Trial Data Analyzed Using the Proper Scientific Endpoint, “All Cause Severe Morbidity”. Trends Int Med. 2021; 1(1): 1-6. *Correspondence: J. Bart Classen, MD, Classen Immunotherapies, Inc, 3637 Rockdale Road, Manchester, MD 21102, Tel: 410-377-8526, E-mail: Classen@vaccines.net.
Received: 24 July 2021; Accepted:25 August 2021
ABSTRACT Three COVID-19 vaccines in the US have been released for sale by the FDA under Emergency Use Authorization (EUA) based on a clinical trial design employing a surrogate primary endpoint for health, severe infections with COVID-19. This clinical trial design has been proven dangerously misleading. Many fields of medicine, oncology for example, have abandoned the use of disease specific endpoints for the primary endpoint of pivotal clinical trials (cancer deaths for example) and have adopted “all cause mortality or morbidity” as the proper scientific endpoint of a clinical trial. Pivotal clinical trial data from the 3 marketed COVID-19 vaccines was reanalyzed using “all cause severe morbidity”, a scientific measure of health, as the primary endpoint. “All cause severe morbidity” in the treatment group and control group was calculated by adding all severe eventsreported in the clinical trials. Severe events included both severe infections with COVID-19 and all other severe adverse events in the treatment arm and control arm respectively. This analysis gives reduction in severe COVID-19 infections the same weight as adverse events of equivalent severity.
Results prove that none of the vaccines provide a health benefit and all pivotal trials show a statically significant increase in “all cause severe morbidity” in the “vaccinated” group compared to the placebo group.
The Moderna immunized group suffered 3,042 more severe events than the control group (p=0.00001).
The Pfizer data was grossly incomplete but data provided showed the vaccination group suffered 90 more severe events than the control group (p=0.000014), when only including “unsolicited” adverse events.
The Janssen immunized group suffered 264 more severe events than the control group (p=0.00001).
These findings contrast the manufacturers’ inappropriate surrogate endpoints:
Janssen claims that their vaccine prevents 6 cases of severe COVD-19 requiring medical attention out of 19,630 immunized.
Pfizer claims their vaccine prevents 8 cases of severe COVID-19 out of 21,720 immunized.
Moderna claims its vaccine prevents 30 cases of severe COVID-19 out of 15,210 immunized.
Based on this data it is all but a certainty that mass COVID-19 immunization is hurting the health of the population in general.
Scientific principles dictate that the mass immunization with COVID-19 vaccines must be halted immediately because we face a looming vaccine induced public health catastrophe.
____________________
**Comment**
Important quote:
Clinical trial data show there were actually few very “severe” cases of COVID-19 in either the vaccinated or the placebo group.
This fact is ignored by our corrupt public health ‘authorities’ who are pushing a continual narrative of fear, aided and abetted by a bought outmedia. According to Doctors for COVID Ethics, these injections are “needless, ineffective, and dangerous.”
Also important from the study:
Moderna data shows that only one of 15,166unvaccinated patients required admission to an intensive care unit for COVID-19.
Data provided by Janssen shows that only a few of the “severe” COVID-19 infections required medical intervention, yet the vaccinated group had 595 severe Grade 3 or 4 events in the first 28 days post immunization.
Table S10 in the appendix published in the New England Journal of Medicine [4] , shows only 2 of 19,514 patients immunized with the Janssen vaccine needed medical intervention for severe COVID-19 infections starting 14 days after immunization, while only 8 of 19,544 controls needed medical intervention for severe COVID-19 infections starting 14 days after placebo, where the infection was confirmed by a central lab. This benefit, reduction in 6 case of COVID-19 requiring medical intervention, in 19,630 vaccinated patients is simply statistically insignificant in a population that has a hundred fold more severe events of any cause.
Reductions in infection rates, hospitalization rates and even death with COVID-19 are poor surrogate markers for health and are not proper primary endpoints for a vaccine clinical trial.
Science thus does not support a health benefit with COVID-19 vaccines. All arguments for immunization are purely philosophical and based on false, discredited, assumptions.
Earlier this week I posted this article which methodically goes through the data and math required to understand “vaccine” efficacy. Again, as with the article above, in order to have good data, you must “count things and divide things which matter.” Regarding efficacy, it’s imperative to know how many infected people went on to die in each group. The author states that while “vaccine” manufacturers proclaim “vaccine” efficacy of 90% or better, no information is available to suggest that the death rate (what truly matters) is any different in the vaccinated vs the unvaccinated. Further, for certain age groups, the number actually leans towards a higher death rate among the “vaccinated.”
And then there’s the important issue of absolute risk. Go here to read an important article that explains how “vaccine” manufacturers are purposely using a statistical trick to make the injections look far more protective than they are.
In a July 1, 2021, commentary in The Lancet Microbe,3 Piero Olliaro, Els Torreele and Michel Vaillant also argue for the use of absolute risk reduction when discussing vaccine efficacy with the public. They too went through the calculations, coming up with the following:
Dr. Richard Urso discusses scientifically unsupported lockdowns, which are causing excess deaths, and the seasonal nature of Covid-19. (Jan. 22, 2021)
(01:04) Covid-19 is a seasonal illness
(02:35) Experts arguing lockdowns cause deaths, suicides, mental health issues…
(03:22) Businesses shut down and newly created reliance on govt
(03:47) Vaccine passports
(04:29) Lockdown caused poverty and connection to health and illness
(04:59) Great Barrington Declaration
(05:35) Lockdowns not supported by science
(05:51) Fear and PCR tests
(06:15) Covid-19 diagnosing protocol changed to include clinical diagnosis after Biden elected president
DR. RICHARD URSO (PART 4): COVID-19 TREATMENT EXISTS & CONFLICTS OF INTEREST (9:16)
Dr. Richard Urso discusses successful treatment protocols, including hydroxychloroquine and iverectin, that have always been available and are purposely being ignored for political and financial conflicts of interest within the FDA, CDC and NIH. (Jan. 22, 2021 interview.)
Dr. Urso has successfully treated 200+ Covid-19 patients and prophylaxed 400+ people using various treatment protocols.
(00:40) Drug treatment protocols
(05:04) Treating his first Covid-19 patient
(05:55) Go to outpatient drugs
(06:28) Covid-19 prophylaxis
(06:57) Why has the FDA not approved certain drugs used in the treatment of Covid-19?
(07:38) Conflicts of interest within FDA, CDC and NIH
(08:50) Part 5 preview: Vaccines
Calling mRNA “vaccines” gene therapies that the media have oversimplified based on a “faulty assumption,” Michigan molecular biologist Christina Parks gave a chilling testimony at a hearing on Michigan HB 4471, which would prohibit employers from discriminating against an individual who has not received the shot.
Saying mandates “basically take away our freedom of choice,” Parks said the faulty assumption is that vaccines prevent transmission when in actuality they don’t. “Does the vaccine for DTaP prevent transmission?” she asks. “No. Does the vaccine for flu prevent transmission? No.
“Do the vaccines for COVID prevent transmission? No. In fact they were never designed to do that.” As far as the “95% effective” goes, that isn’t even a reality, she said, because the Delta variant is predominant now — and “these vaccines have no ability to prevent infection by and transmission of the Delta variant.” She doesn’t mention the fact when absolute risk is taken into account these injections are less than 1% effective. She also doesn’t mention that without looking at infection rates, efficacy numbers convey nothing useful. Statistical ‘slight of hand’ shenanigans are misleading the public. Further, these injections have caused more adverse reactions and death than all the vaccines reported to VAERS in the past 30 years.
Asking the legislature to base their decisions on real data, Parks pointed out that, as someone with a Ph.D., she is among those who are most vaccine hesitant for the COVID vaccines. And, aside from understanding the science of what the vaccines can and cannot do, she is also keenly aware of why people — especially Blacks — with less than a college education are also hesitant to trust the government’s vaccine recommendations.
The question, she said, is “who are we going to exclude from the workforce? Are we going to continue with discrimination and segregation in the United States of America?”
10 Minutes of Powerful Truth: “Vaccine” Mandates are Illegal
Tricia Lindsay gives a very powerful speech to the public about how the US government and governments around the world are violating human rights by imposing mandates and discriminate against the unvaccinated.
“This is medical rape.” Tricia Lindsay, Civil Rights Attorney
There’s been a lot of cover-up, fraud, and collusion in the public health arena. A group of inter-agency scientists formed a group called SPIDER that has delineated the corruption. These groups are known to manipulate data for their own nefarious purposes. I am elated that someone from the black community is educating others on these true racial travesties which have been covered up by our corrupt public health ‘authorities,’ because it concerns the ‘golden calf’ of vaccines – therefore it’s simply swept under the rug because, “it’s for the greater good.”
According to the U.S. Centers for Disease Control and Prevention, people who got the COVID shot early are now at increased risk for severe COVID disease
This may be a sign that antibody dependent enhancement (ADE) is occurring, or it may simply indicate that the protection offered is limited to a few months, at best
Recent research warns the Delta variant “is posed to acquire complete resistance to wild-type spike vaccines.” This could turn into a worst-case scenario that sets up those who have received the Pfizer shots for more severe illness when exposed to the virus
To “stay ahead of the virus,” the Biden administration is now considering recommending a booster shot five months after the initial two doses rather than waiting eight months, as previously suggested
Israeli data show Pfizer’s shot went from a 95% effectiveness at the outset to 39% by late July 2021, when the Delta strain became predominant. The U.S. Food and Drug Administration’s expectation for any vaccine is an efficacy rate of at least 50% compared to placebo
The official COVID-19 vaccine narrative changes rapidly these days. It took just one month for it to go from “if you’re vaccinated you’re not going to get COVID,”1 including the Delta variant,2 to “people who got vaccinated early are at increased risk for severe COVID disease.”3
From the get-go, I and many other medical experts have warned of the possibility of these shots causing antibody dependent enhancement (ADE), a situation in which the shot actually facilitates a cascade of disease complications rather than protects against it. As a result, you may suffer more severe illness when encountering the wild virus than had you not been “vaccinated.”
While we don’t yet have definitive proof that ADE is occurring, we are seeing suspicious signs that it might be. Data showing those who got the shot early this year are now at increased risk of severe infection could be such a sign. At bare minimum, it’s an indication that the protection you get from these shots is very temporary, lasting only a few months.
This makes sense when you consider they program your body to produce just one type of antibody against a specific spike protein. Once the spike protein, or other elements in the virus, starts to mutate, protection radically diminishes. Worse, the vaccine facilitates the actual production of the variants because it is “leaky” and provides only partial ineffective immune protection.
Natural immunity is far superior, as when you recover from the infection, your body makes antibodies against all five proteins of the virus, plus memory T cells that remain even once antibody levels diminish. This gives you far better protection that will likely be lifelong, unless you have impaired immune function.
Real-world data from Israel confirms this, showing those who have received the COVID jab are 6.72 times more likely to get infected than people with natural immunity.4,5,6
CDC Admits ‘Vaccine’ Immunity Doesn’t Last
In an August 20, 2021, report, BPR noted:7
“’The data we will publish today and next week demonstrate the vaccine effectiveness against SARS COVID 2 infection is waning,’ the CDC director [Rochelle Walensky] began … She cited reports of international colleagues, including Israel ‘suggest increased risk of severe disease amongst those vaccinated early.’
Fear not, the same people who tried to sell Americans immunity through a jab and promised to hand back the freedoms they impeded on have a plan, and they’re not leaving much room for personal choice.
‘In the context of these concerns, we are planning for Americans to receive booster shots starting next month to maximize vaccine induced protection. Our plan is to protect the American people and to stay ahead of this virus,’ Walensky shared …
The CDC director appears to all but admit that the vaccine’s efficacy rate has a strict time limit, and its protections are limited in the ever-changing environment.
‘Given this body of evidence, we are concerned that the current strong protection against severe infection, hospitalization and death could decrease in the months ahead. Especially among those who are higher risk or those who were vaccinated earlier during the phases of our vaccination roll out,’ Walensky explained …
Starting September 20, Americans who completed their two doses of the Pfizer or Moderna vaccine at least eight months ago will be eligible for a booster shot. The goalposts back to a ‘normal’ society continue to be moved further and further. When will Americans, especially those who complied with initial vaccinations, have had enough?”
Data Reveal Rapidly Waning Immunity From Shots
Indeed, Israeli data show Pfizer’s shot went from a 95% effectiveness at the outset, to 64% in early July 2021 and 39% by late July, when the Delta strain became predominant.8,9 Meanwhile, the U.S. Food and Drug Administration’s expectation for any vaccine is an efficacy rate of at least 50%.
Pfizer’s own trial data even showed rapidly waning effectiveness as early as March 13, 2021. BMJ associate editor Peter Doshi discussed this in an August 23, 2021, blog.10
By the fifth month into the trial, efficacy had dropped from 96% to 84%, and this drop could not be due to the emergence of the Delta variant since 77% of trial participants were in the U.S., where the Delta variant didn’t emerge until months later. This suggests the COVID shot has a very temporary effectiveness regardless of new variants.
What’s more, while Israeli authorities claim the Pfizer shot is still effective at preventing hospitalization and death, many who are double-jabbed do end up in the hospital, and we’re already seeing a shift in hospitalization rates from the unvaccinated to those who have gotten one or two injections. For example, by mid-August, 59% of serious COVID cases were among Israelis who had received two COVID injections.11
Vaxxed Over Age 50 at Increased Risk for Serious Infection
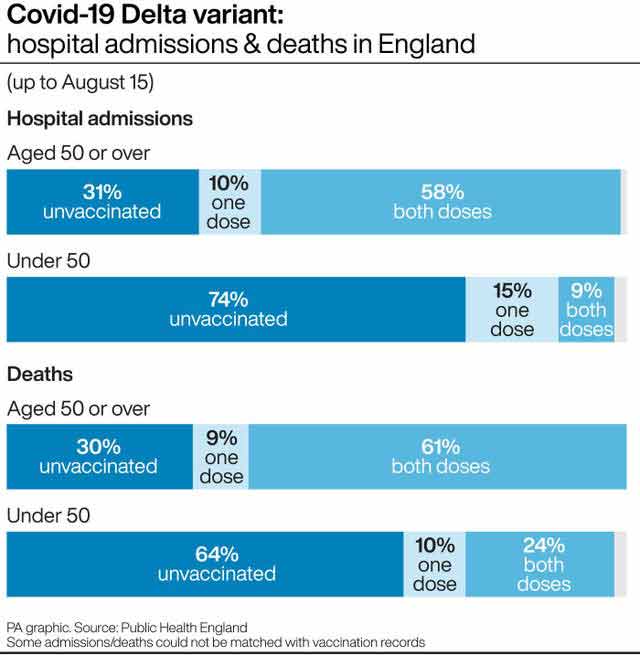
Data from the U.K. show a similar trend among those over the age of 50. In this age group, partially and fully “vaccinated” people account for 68% of hospitalizations and 70% of COVID deaths.12
80% of COVID Hospitalizations in Massachusetts Were Vaxxed
Data13 from the U.S. Centers for Disease Control and Prevention also raise questions about the usefulness of the COVID shots. Between July 6 and July 25, 2021, 469 COVID cases were identified in a Barnstable County, Massachusetts, outbreak.
Of those who tested positive, 74% had received two COVID injections and were considered “fully vaccinated.” Even despite using different diagnostic standards for non-jabbed and jabbed individuals, a whopping 80% of COVID-related hospitalizations were also in this group.14,15
The CDC also confirmed that fully vaccinated individuals who contract the infection have as high a viral load in their nasal passages as unvaccinated individuals who get infected, proving there’s no difference between the two, in terms of being a transmission risk.16
If vaccination status has no bearing on the potential risk you pose to others, why do we need vaccine passports? According to Harvard epidemiologist Martin Kulldorff, this evidence demolishes the case for passports.17 They clearly cannot ensure safety, as evidenced by outbreaks where the vaccination rate was 100%. Examples include outbreaks onboard a Carnival cruise liner18 and the HMS Queen Elizabeth, a British Navy flagship.19
Study Predicts Pfizer Shot Will Enhance Delta Infectivity
A study20 posted August 23, 2021, on the preprint server bioRxiv now warns the Delta variant “is posed to acquire complete resistance to wild-type spike vaccines.” This could essentially turn into a worst-case scenario that sets up those who have received the Pfizer shots for more severe illness when exposed to the virus. As explained by the authors:21
“Although Pfizer-BioNTech BNT162b2-immune sera neutralized the Delta variant, when four common mutations were introduced into the receptor binding domain (RBD) of the Delta variant (Delta 4+), some BNT162b2-immune sera lost neutralizing activity and enhanced the infectivity.
Unique mutations in the Delta NTD were involved in the enhanced infectivity by the BNT162b2-immune sera. Sera of mice immunized by Delta spike, but not wild-type spike, consistently neutralized the Delta 4+ variant without enhancing infectivity.
Given the fact that a Delta variant with three similar RBD mutations has already emerged according to the GISAID database, it is necessary to develop vaccines that protect against such complete breakthrough variants.”
Proactive Use of COVID Shots Drive Dangerous Mutations
It’s now clear that early warnings against mass vaccination during an active outbreak are being realized. It’s not the unvaccinated that are driving mutations; it’s the vaccinated, as the injections simply do not prevent infection.
The end result, if we keep going, will be a treadmill of continuous injections to keep up with the merry-go-round of waning effectiveness in general combined with the emergence of vaccine-resistant variants. As reported by Live Science:22
“Vaccine-resistant coronavirus mutants are more likely to emerge when a large fraction of the population is vaccinated and viral transmission is high … In other words, a situation that looks a lot like the current one in the U.S.
The mathematical model,23 published July 30 in the journal Scientific Reports, simulates how the rate of vaccination and rate of viral transmission in a given population influence which SARS-CoV-2 variants come to dominate the viral landscape …
If viral transmission is low, any vaccine-resistant mutants that do emerge get fewer chances to spread, and thus, they’re more likely to die out, said senior author Fyodor Kondrashov, who runs an evolutionary genomics lab at the Institute of Science and Technology Austria.”
These findings come as no surprise to those familiar with previous research showing the same exact thing. As explained in “Vaccines Are Pushing Pathogens to Evolve,” published in Quanta Magazine,24
“Just as antibiotics breed resistance in bacteria, vaccines can incite changes that enable diseases to escape their control.”
The article details the history of the anti-Marek’s disease vaccine for chickens, first introduced in 1970. Today, we’re on the third version of this vaccine, as within a decade, it stops working. The reason? The virus has mutated to evade the vaccine. As a result of these leaky vaccines, the virus is becoming increasingly deadly and more difficult to treat.
A 2015 paper25 in PLOS Biology tested the theory that vaccines are driving the mutation of the herpesvirus causing Marek’s disease in chickens. To do that, they vaccinated 100 chickens and kept 100 unvaccinated. All of the birds were then infected with varying strains of the virus. Some strains were more virulent and dangerous than others.
Over the course of the birds’ lives, the unvaccinated ones shed more of the least virulent strains into the environment, while the vaccinated ones shed more of the most virulent strains. As noted in the Quanta Magazine article:26
“The findings suggest that the Marek’s vaccine encourages more dangerous viruses to proliferate. This increased virulence might then give the viruses the means to overcome birds’ vaccine-primed immune responses and sicken vaccinated flocks.”
Vaccinated People Can Serve as Breeding Ground for Mutations
Before 2021, it was quite clear that vaccines push viruses to mutate into more dangerous strains. The only question was, to what extent? Now all of a sudden, we’re to believe conventional science has been wrong all along. Here’s another example: NPR as recently as February 9, 2021, reported that “vaccines can contribute to virus mutations.” NPR science correspondent Richard Harris noted:27
“You may have heard that bacteria can develop resistance to antibiotics and, in a worst-case scenario, render the drugs useless. Something similar can also happen with vaccines, though, with less serious consequences.
This worry has arisen mostly in the debate over whether to delay a second vaccine shot so more people can get the first shot quickly. Paul Bieniasz, a Howard Hughes investigator at the Rockefeller University, says that gap would leave people with only partial immunity for longer than necessary.”
According to Bieniasz, partially vaccinated individuals “might serve as sort of a breeding ground for the virus to acquire new mutations.” This is the exact claim now being attributed to unvaccinated people by those who don’t understand natural selection.
It’s important to realize that viruses mutate continuously and if you don’t have a sterilizing vaccine that blocks infection completely, then the virus mutates to evade the immune response within that person. That is one of the distinct features of the COVID shots — they’re not designed to block infection. They allow infection to occur and at best lessen the symptoms of that infection. As noted by Harris:28
“This evolutionary pressure is present for any vaccine that doesn’t completely block infection … Many vaccines, apparently, including the COVID vaccines, do not completely prevent a virus from multiplying inside someone even though these vaccines do prevent serious illness.”
In short, like bacteria mutate and get stronger to survive the assault of antibacterial agents, viruses can mutate in vaccinated individuals who contract the virus, and in those, it will mutate to evade the immune system.
In an unvaccinated person, on the other hand, the virus does not encounter the same evolutionary pressure to mutate into something stronger. So, if SARS-CoV-2 does end up mutating into more lethal strains, then mass vaccination is the most likely driver.
What NFL Outbreak Can Tell Us
As reported August 27, 2021, by MSN,29 as players were encouraged to get the COVID shot for everyone’s safety, separate testing rules were put into place. Players who have gotten the jab only need to test every two weeks, while unvaccinated players undergo daily testing.
The relaxed testing requirement for double-jabbed players was used as incentive to go ahead and get the shot. As reported by MSN, “Conversely, the continued daily testing would become part of a punitive system that would make life so annoying for the unvaccinated that they would eventually get on board.”30
Well, this didn’t work out as planned. Nine Titans players and head coach Mike Vrabel have now tested positive, showing it really doesn’t matter if you’re double-jabbed or not. The infection spreads among the vaxxed just the same. As noted by MSN:31
“The pandemic is in a phase where the unvaccinated are facing the vengeance of a more aggressive strain of COVID-19. It’s also an era when the vaccinated are grappling with the reality that their shots are mitigating their symptoms and medical complications, but not completely preventing them from becoming infected or transmitting COVID to others.”
To remedy the matter, the NFL Players Association, the union representing players of the National Football League, is now calling for a return to daily testing of all players, regardless of COVID jab status. Time and again, we find that incentives fall far short of their initial promise. This has been the case for masks as well.
First, we were told that if we got the COVID shot, we didn’t need to wear masks anymore. Of course, universal mask recommendations returned full force when it became apparent that breakthrough infections were still occurring at a surprising rate.
Now, routine testing with a test known to produce false positives at a rate of about 97%32 is promoted again, regardless of injection status, and there’s no reason to assume the same won’t happen with vaccine passports. We’re promised freedom if we give up medical autonomy, but freedom will never actually be granted. They’ll just continue to move the goal post.
It is highly likely, in fact even predictable, that despite its dramatic ineffectiveness, the requirement for one or two COVID jabs will soon be turned into three, and vaccine passport holders who don’t want to get that third shot will be back at Square 1. They’ll be just as undesirable as those who got no shots.
Considering the speed at which SARS-CoV-2 is mutating, you can be assured there will be a fourth shot,and a fifth and, well, you get the idea. Vaccine passports and COVID jab requirements will simply lead to a situation where you have to keep getting additional shots or lose all your privileges.
Of course, every single injection comes with health risks, and the risk for an adverse event will probably get bigger and bigger with each additional shot, and you don’t need to be a modern-day Nostradamus to see where this will lead us.
Five-Month Booster Shot Now Under Consideration
Unfortunately, rather than accepting reality — which is that SARS-CoV-2 is here to stay, just like any number of other common cold and influenza viruses — and stopping the merry-go-round of injections that only make matters worse, President Biden said he’d spoken with Dr. Anthony Fauci about giving booster shots at the five-month mark after the initial round of injections rather than waiting eight months, as previously suggested.33
While Fauci quickly responded34 that eight months was still the goal, he also said that “we are open to data as they come in” if the Food and Drug Administration and the Advisory Committee on Immunization Practices determine a sooner timeline is necessary.
Israel began administering a third booster shot to people over the age of 60 July 30, 2021. August 19, eligibility for a booster was expanded to include people over the age of 40, as well as pregnant women, teachers and health care workers, even if they’re younger than 40. Initial reports suggest the third dose has improved protection in the over-60 group, compared to those who only got two doses of Pfizer.35 According to Reuters:36
“Breaking down statistics from Israel’s Gertner Institute and KI Institute, ministry officials said that among people aged 60 and over, the protection against infection provided from 10 days after a third dose was four times higher than after two doses. A third jab for over 60-year-olds offered five to six times greater protection after 10 days with regard to serious illness and hospitalization.”
Anyone who thinks one or more booster shots are the answer to SARS-CoV-2 is likely fooling themselves though. I look forward with trepidation to data on hospitalization and death rates, not to mention side effect rates, in the months to come.
Knowing what we already know about the risks of these shots and their tendency to encourage mutations, it seems reasonable to suspect that all we’re doing is digging ourselves an ever-deeper, ever-wider hole that’s going to be increasingly difficult to get out of.
It’s gotten so bad, state attorney generals have had to call out the FDA, CDC, Fauci, and the media for ‘fueling confusion and misinformation’ by interfering with the treatment of COVID patients. Both Nebraska and Oklahoma doctors are now free to prescribe off-label medications such as ivermectin and HCQ for COVID without fear of disciplinary action from corrupt groups like the AMA and state medical boards.
This legal action needs to happen in each and every state in the U.S.
The story of the powerful players colluding together to suppress any knowledge of a drug that could end the pandemic
This “must see” video not only goes through Ivermectin research but reveals the players censoring it, while pushing their own lucrative drug Remdesivirwhich doesn’t work.
The story is actually a familiar one to Lyme/MSIDS patients.
Regarding COVID, a similar smear campaign occurred over hydroxychloroquine (HCQ) in which a fraudulent study had to be retracted from a prestigious science journal. Currently, the FDA , DOJ, AMA, APhA, ASHP are trying to ban any treatments that help with COVID, but support mandated COVID injections, despite the record-breaking adverse reactions such as antibody dependent enhancement, microclotting, risk of prion and parkinson’s disease, and deaths. These injections are less than 1% effective when absolute risk is taken into account. Conflict-riddled ‘authorities’ are completely ignoring natural immunity, and have manipulated data to blame the pandemic on the unvaccinated when it is the “vaccinated” who are driving COVID to mutate and causing the explosion in ‘break-through cases‘ resulting in hospitalization and death, which have been vastly underreported.
The author points out that Fauci made the unusual move of announcing at a press conference from the White House in April, 2020 that the anti-viral Remdesivir for COVID diminishes time to recovery. He doesn’t discuss mortality at all.
NIAID(where Fauci works)actually paid for the NIH study he alludes to. Being fully aware of the study he also knew that midway through it the primary end-point was changed from mortality to time to recovery. This was obviously done because researchers saw that remdesivir had no significant impact on mortality. Changing endpoints midway in a study should raise a lot of red-flags.
Meanwhile, using evidence based on much larger studies, the WHO did not recommend remdesivir as they stated that there is no evidence that it improves survival or any other metric in patients.
and omitting absolute risk are continually being used to mislead the public into believing the accepted narrative that HCQ and Ivermectin are ineffective and/or dangerous, but that the COVID-19 injections are safe and effective.
The video then explains how at least 7members of the COVID-19 treatment panel have financial ties to Gilead Sciences.
The three co-chairs who select the other panel members do not disclose financial ties to Gilead, but two of the chairs both receive financial support from Gilead. The third co-chair was one of the authors of the NIAID funded remdesivir study. His name is not listed as a study author, you have to dig for it by looking at the financial disclosure form of conflicts of interest.
These conflict-riddled panelists push the drug they make money from but know full well it has no effect on COVID-19 survival. This is professional negligence of the worst sort that has potentially resulted in millions of deaths globally.
They choose to suppress ivermectin with study after study proving its effectiveness on mortality, and push their own ineffective drug.
Similarly to how Sweden has acted as a placebo arm in this vast evil experiment by refusing to lock down and force masks, resulting in ZERO COVID deaths, the state of Uttar Pradesh, India, which has about 70% of the U.S. population, chose to authorize ivermectin for those testing positive, for their primary contacts and for health care workers.Ivermectin brought COVID deaths down to ZERO.
Ivermectin could have ended the pandemic LAST SUMMER.