Doctors attempting to treat COVID are experiencing the same censorship, bullying, denial, and attacks that Lyme literate doctors have been experiencing for over 40 years. Perhaps this will open up some eyes in medicine that the ‘powers that be’ control a narrative which forces doctors to treat a certain way. Perhaps people will begin to understand and appreciate the corruption in public health. Perhaps this will bring the needed change in medicine that we’ve been waiting for. I’m not holding my breath, but there’s always hope.
And this telling video details how myocarditis concerns are growing. Jefferey Jaxen goes through the VAERS data as well. Coroner states they are dealing with multiple cases.
Dr. Linda Wastila: Why are we Accepting Myocarditis as an Acceptable Side Effect for COVID Vaccine
Nov. 7, 2021
by Brian Shilhavy Editor, Health Impact News
Our most-read article last week, by far, was the article on Senator Ron Johnson’s Roundtable discussion held in Washington D.C. where doctors, scientists, and COVID-19 vaccine injured victims met to discuss COVID-19 “vaccine” mandates.
The entire recording of this event is over 3.5 hours long, and so I have been watching it and breaking up the speakers into individual videos to make it easier to watch this truly historical event that happened at our nation’s capital last week.
10 of these powerful presentations were published with that article last week, and you can watch them here:
One of the most powerful presentations was given by Dr. Linda Wastila, who is a PhD professor and heads the Department of Pharmaceutical Health Services Research at the University of Maryland. (Source.)
We are citizens who have done our civic duty, but when we suffer serious adverse effects, we’re left high and dry by the FDA, the CDC, the NIH and medical professionals.
We are scientists alarmed by the toxic environment in academia and scientific publishing.
We are military leaders concerned about vaccine safety in the armed services.
We are clinicians who want to treat patients harmed by the vaccines but whose practices are limited by our employers and professional boards.
And we are lawyers and patient advocates seeking help for our injured clients and their families.
We are the people you haven’t heard from.
And we have nothing, absolutely nothing to personally gain from being here. Indeed, we have everything to lose, including our jobs, our titles, our livelihoods.
But we don’t intend to go away until we see some real change.
Dr. Wastila later in the meeting gave another presentation about VAERS (Vaccine Adverse Event Reporting System) and the “science of vaccine safety.”
Dr. Wastila is very critical of the CDC for using sound bytes with the public and stating that COVID-19 vaccines are “safe.”
The statement that everyone by now has heard come out of the mouth of CDC Director Rochelle Walensky many times, and which is fraudulently printed on the CDC website, is:
Millions of people in the United States have received COVID-19 vaccines under the most intense safety monitoring in U.S. history.
Dr. Wastila states:
The impression is the system is so finely tuned that even the rarest needle in the haystack will be found.
I am afraid that is just not the case.
Now remember, the reason Senator Johnson invited Dr. Wastila is because drugs and drug safety is her area of expertise.
She states that the process to determine if there are problems that need to be addressed based on reported side effects in VAERS is a very slow process, and she uses myocarditis as an example.
It took four months into Israel’s national vaccine campaign to recognize this side effect. That’s besides the fact that myocarditis generally strikes within days of dosing, particularly the second dose.
So officials were experiencing this side effect for months before officials recognized the vaccine as the cause.
This delay in detecting, researching, and acknowledging side effects is normal.
And it is devastating.
The patients at this meeting today know that devastation first hand.
But it’s also devastating because unless you first recognize harms soon after they occur, you can’t use that knowledge in the next person about to get the vaccine.
I am stunned when I hear people dismiss myocarditis as an acceptable side effect, especially for young people.
Because myocarditis is life-threatening, and a life-disabling condition.
As I reported last week, the CDC admits that myocarditis is caused by COVID-19 vaccines, but they dismiss it as “rare.”
Myocarditis and pericarditis after COVID-19 vaccination are rare. As of October 27, 2021, VAERS has received 1,784 reports of myocarditis or pericarditis among people ages 30 and younger who received COVID-19 vaccine. Most cases have been reported after mRNA COVID-19 vaccination (Pfizer-BioNTech or Moderna), particularly in male adolescents and young adults. Through follow-up, including medical record reviews, CDC and FDA have confirmed 1,005 reports of myocarditis or pericarditis. CDC and its partners are investigating these reports to assess whether there is a relationship to COVID-19 vaccination.
Why are we continuing to inject children with these shots? Under what possible logic or ethics is 1,784 reports of myocarditis or pericarditis among people under the age of 30 acceptable?
There are far more reports of myocarditis or pericarditis following COVID-19 shots than following ALL vaccines for the past 30+ years recorded in VAERS.
And we know this is only a fraction of the actual cases because VAERS is under-reported, and many of these cases have already led to deaths.
The CDC and FDA have never conducted a study to determine what this under-reported factor is, but independent scientists have, and we have previously published the analysis conducted by Dr. Jessica Rose, who has determined that a conservative under-reported factor would be X41.
That would put the truer picture of young people suffering from myocarditis closer to 74,928 cases, and now they have just begun to inject 5 to 11 year olds.
Watch Dr. Linda Wastila’s presentation. This is our Rumble and Bitchute channels.
______________
Myocarditis-induced Sudden Death after BNT162b2 mRNA COVID-19 Vaccination in Korea: Case Report Focusing on Histopathological Findings
_________________
More Hospitalizations For “Vaccinated” Kids Than From COVID
In Pfizer’s FDA briefing document using unverified and misleading math, they admit there may be more hospitalizations among children for myocarditis — than from COVID.
“Under Scenario 3 (lowest incidence), the model predicts more excess hospitalizations due to vaccine-related myocarditis/pericarditis compared to prevented hospitalizations due to COVID-19 in males and in both sexes combined,” states Pfizer in page 33 of the document.
A preprint from University of California Davis found that “for boys 12-15 without medical comorbidities receiving their second mRNA vaccination dose, the rate of CAE [cardiac adverse event ] is 3.7 to 6.1 times higher than their 120-day COVID-19 hospitalization risk as of August 21, 2021″
A recent study of the Danish population published in the Pediatric Infectious Disease Journal found that “the incidence of myopericarditis after COVID-19 vaccination among males appears higher than reports from the United States“
If you take the 128 reported vaccine deaths among those ages 12-24 as a baseline, and utilize Kirsch, Rose, and Crawford’s estimate that VAERS undercounts fatal reactions by a factor of 41, that would amount to 5,248 deaths
There are essentially zero COVID deaths for healthy children
More than half of children likely already had COVID
2,433 Dead Babies in VAERS as Another Study Shows mRNA Shots Not Safe for Pregnant Women
by Brian Shilhavy Editor, Health Impact News
Excerpts:
Last month (October, 2021) the New England Journal of Medicine admitted that the original study used to justify the CDC and the FDA in recommending the shots to pregnant women was flawed. (Source.) Since then, researchers in New Zealand have conducted a new study on the original data, and concluded:
A re-analysis of these figures indicates a cumulative incidence of spontaneous abortion ranging from 82% (104/127) to 91% (104/114), 7–8 times higher than the original authors’ results. (Source.)
And yet, the CDC and FDA still continue to recommend the shots for pregnant women….
Shilhavy points out the fact that Dr. Jessica Rose has given a conservative estimate that VAERS reporting is under-reported by a factor of X41, which means…..
There have probably been at least 99,753 fetal deaths following COVID-19 injections so far.
(See link for article and video of fetal adverse reactions)
The district of Cuxhaven, Germany confirmed on Wednesday, November 3, 2021, that a 12-year-old child died two days after taking the Pfizer vaccine. Police are investigating and an autopsy was ordered due to the short interval between vaccination and death. The result of the autopsy is still pending and is expected to be released this week at the earliest.
“The current status of the autopsy suggests a connection,” Kirsten von der Lieth, press spokeswoman for the district said about the vaccine and the child’s death.
Athletes Around the World are Dropping Like Flies with Heart Problems
by Brian Shilhavy Editor, Health Impact News
Someone has put together a video montage showing the sheer volume of athletes around the world dropping like flies with heart problems, and the corporate media calls this a “mystery.” How many people ever heard of the word “myocarditis” prior to the COVID shots? But don’t blame it on the “vaccines.” That would be politically incorrect.
Meanwhile, athletes like Green Bay Packer Aaron Rodgers are crucified for not getting jabbed. It doesn’t matter to critics that he’s allergic to two of the shots and the third one wasn’t available due to being temporarily pulled for clotting issues at the time players were getting vaccinated.
He spoke with doctors and instead chose an immunization protocol that took multiple months to complete.
The article points out that it must have worked as Rodgers looked completely healthy despite having COVID-19.
Best parts of the interview:
“How about we teach people how to be healthy?
You have a right to make a decision about your body. That should be an unalienable right for all people to make an educated decision based on what they think is best for them.” Aaron Rodgers
Rodgers went on to call out the billions in our tax dollars that are flowing into the bank accounts of Big Pharma.
“Let’s move this forward with some love and connection, that’s what we need in this world. Let’s communicate instead of canceling someone or silencing someone. That gets us nowhere.” Aaron Rodgers
The following letters written by Lyme advocate Carl Tuttle were written to rebut this Medscape article, which tries to make the reader feel sorry for researchers that have actively worked against Lyme patients and the doctors who dare treat them. A few details about Leonard Sigal:
In the book “Cure Unknown,” Sigal actually bragged that the money he received as payments from the Insurance Defendants was a great fund for his children’s college educations
This testimony written by Lyme patient and advocate Kathy White for the Kansas Senate states these payments Sigal & others received deprived suffering patients from proper diagnosis, treatment, and insurance coverage
On August 12, 1996 Dr. Leonard Sigal gave a deposition and testified that he reviewed many Lyme disease files for insurance companies, almost always denied coverage, and charged $560 an hour to perform his work. He testified that he reviewed files for most of the Insurance Defendants …
The Insurance Defendants paid Dr. Sigal to improperly deny insurance coverage to Lyme disease patients and to improperly influence the treating doctors to not provide long-term treatment for chronic Lyme patients.
And this is information only on Sigal. There is a litany of misdeeds done by The Cabal. The Medscape article is like ripping a scab off of Lyme/MSIDS patients. No wonder Tuttle took them to task. Personally, I view Medscape as “yellow journalism.” I only read it to understand how the enemy thinks.
Judge Dismisses Lyme Disease Lawsuit Against IDSA, Doctors, but the Ordeal Has Left Its Scars
Nov 6, 2021 —
The following letter was mailed directly to Robert N. Brisco, Chief Executive Officer of WebMD, parent company of Medscape and forwarded to the editors of Medscape via email. There was no response whatsoever from Medscape. Go figure! If you are as outraged as I am over the continued collusion to deny chronic Lyme disease why not voice your opinion to the Medscape editors: editor2@webmd.net
MEDSCAPE MEDICAL NEWS
Judge Dismisses Lyme Disease Lawsuit Against IDSA, Doctors, but the Ordeal Has Left Its Scars
“The cause of PTLDS [chronic Lyme] is still under investigation, and the evidence does not support the idea of a persistent bacterial infection.”
Dear Mr. Brisco,
In reference to the recent Medscape article above I would like to call attention to the following letter addressed to Brenda Fitzgerald, MD former Director of the CDC. As you know, culture is the diagnostic gold standard for many bacterial infections but there appears to be a double standard in the case of Lyme disease especially when it threatens a thirty-year narrative.
Postmortem examination to discover the cause of death also appears to have been thrown out the window when Lyme disease is involved.
Seronegative Lyme in which no one will test positive using the current twenty-five-year-old two-tier testing algorithm has been suppressed for decades.
And you wonder why patients have filed a lawsuit against the Infectious Diseases Society of America (IDSA)?
What are the chances that the information/references in my 2017 letter below addressed to Dr. Fitzgerald will find its way into a Medscape article? For the record, there was no response from Fitzgerald, Redfield or current CDC Director Rochelle P. Walensky, MD.
Cc: Tara Haelle, Independent science/health journalist, Timothy Flanigan, MD Professor, Brown University, Leonard Sigal, MD, Berkshire Medical Center, Daniel McQuillen, MD, President of IDSA, Raymond J. Dattwyler, MD, Professor New York Medical College
Letter to Brenda Fitzgerald, MD Director US Centers for Disease Control:
———- Original Message ———-
Dear Dr. Fitzgerald,
Untreated strep throat leads to rheumatic fever which can cause irreversible heart damage but rapid culture tests for strep available in the primary care setting has virtually eliminated rheumatic fever and the life-threatening complications associated with that disease.
Misdiagnosed and untreated Lyme disease creates the same life-altering/life-threatening consequences but this has been hidden from the worldwide medical community and general population. Just ask Duke University Professor Neil Spector who required a heart transplant after his Lyme infection went four years untreated. Spector’s laboratory tests (serology) were repeatedly negative. Faulty/misleading antibody tests are the root cause of unimaginable pain and suffering.
Lyme disease is capable of producing sudden death with no warning signs; [1,2,3,] heart damage requiring transplant, [4] paralysis with seizures, [5] lymphoma [6] and persistent infection after antibiotic treatment [7, 8,9,10,11] along with congenital transmission [12] and ability to create wheelchair bound patients [13]. The last time we recognized a disease with this potential to cause serious harm, (Zika) the CDC wanted 1.8 billion for research. [14]
Quote from Senator Richard Blumenthal:
“Today for me culminates more than a decade of work and probably a decade more, because I’ve seen firsthand the devastating, absolutely unacceptable damage done by Lyme disease to individual human beings, Connecticut children and residents whose lives have been changed forever as a result of Lyme disease”
In regards to laboratory testing (culture), please see the following quote from Dr. Kenneth Liegner:
“In 1991 the Lyme disease organism, Borrelia burgdorferi, was grown from the cerebrospinal fluid of my patient Vicki Logan at the Centers for Disease Control in Fort Collins, Colorado despite prior treatment with intravenous antibiotics. Her case made the front page of the New York Times Science Times in August of 1993.” -Kenneth Liegner, MD
Lyme patient Vicki Logan’s 1991 positive culture test performed by the Centers for Disease Control should have set off a red flag but was ignored while the focus remained on discrediting the sick and disabled Lyme patient population. [15]
Here are links to the seven page autopsy results of patient Vicky Logan showing histopathologic findings consistent with neurologic manifestations of chronic Lyme disease.
The destructive nature of Borrelia is evident in Vicky Logan’s liver (nutmeg liver), kidneys, heart, lungs and brain. The patient died after the insurer refused additional IV antibiotic therapy.
I would like to point out the following case study from Stony Brook Lyme clinic. I understand the patient received thirteen spinal taps, multiple courses of IV and oral meds, and relapsed after each one, proven by CSF antigens and/or PCR. The only way this patient (said to be a physician) remained in remission was to keep her on open ended clarithromycin- was on it for 22 months by the time of publication.
Seronegative Chronic Relapsing Neuroborreliosis. https://www.ncbi.nlm.nih.gov/pubmed/7796837
Lawrence C.a · Lipton R.B.b · Lowy F.D.c · Coyle P.K.d
aDepartment of Medicine, bDepartment of Neurology, and cDivision of Infectious Diseases, Albert Einstein College of Medicine, and dDepartment of Neurology, State University of New York at Stony Brook, New York, NY., USA
We report an unusual patient with evidence of Borrelia burgdorferi infection who experienced repeated neurologic relapses despite aggressive antibiotic therapy.Each course of therapy was associated with a Jarisch-Herxheimer-like reaction. Although the patient never had detectable free antibodies to B. burgdorferi in serum or spinal fluid, the CSF was positive on multiple occasions for complexed anti-B. burgdorferi antibodies, B. burgdorferi nucleic acids and free antigen.
________________________
For the past three decades, Lyme disease has been portrayed as hard to catch and easily treated [16] while those who control the narrative (through editorial censorship) refuse to recognize this pathogen as an antibiotic resistant/tolerant superbug by suppressing evidence of persistent infection.[17] This misclassification has all but eliminated government funding that should have been equal to or greater than AIDS or Zika which are also life-altering/life-threatening infections in need of cures.
What we are dealing with here is an antibiotic resistant/tolerant superbug but the focus over the past three decades (as seen in the Lancet article) has been to discredit the sick and disabled along with the practitioners attempting to help these patients as opposed to finding new antimicrobials effective in eradicating all forms of the Borrelia spirochete; L-forms, round bodies and persister cells.
The truth about this devastating disease has been kept from the public for 43 years and there are no Public Service Announcements informing the public that you could become horribly disabled or die from Lyme disease
A worldwide community of physicians has been influenced by the ongoing disinformation campaign aimed at promoting the idea that Lyme is little more than a nuisance disease as health agencies across the globe are blindly following what has been deceitfully established here in the U.S.
We are dealing with a life-altering/life-threatening infection with faulty/misleading antibody tests, inadequate treatment, no medical training and absolutely no disease control.
This has been a 43 year epic failure on the part of the CDC and now you inherited this travesty.
Will you continue to turn a blind eye to this 21st Century plague?
A response to this inquiry is requested.
Carl Tuttle
Independent Researcher
Lyme Endemic Hudson, NH USA
Reviewer, American Journal of Infectious Diseases
Information Doctors Have Died For with Dr. Carrie Madej
October 11th, 2021
Dr. Madej is a highly credentialed doctor who has been literally had to flee the country for her life. She is back now with a vengeance and shows us what is in the vaccines. She takes us under her microscope to show us what is really go on from hydrogel to computer chips.
When I published my study on pathogenic priming in April, 2020, it was meant as a warning. The evidence was in from past COVID vaccine development attempts: vaccination against coronaviruses had led to DISEASE ENHANCEMENT.
I had hoped vaccine makers would have paid heed and would have excluded the unsafe epitopes from their vaccines. I gave them a roadmap.
Now, in Belgium, 100% of ICU admissions are among the vaccinated. Only 40% of the Belgium population are vaccinated*
I’m ready to call it: The COVID-19 vaccination program causes Disease Enhancement, likely via numerous possible means: from molecular mimicry leading to autoimmunity, or antibody-dependent enhancement, Pathogenic Priming has Antwerp, Belgium in its grip
Hospital Saint Vincent in Antwerp, Belgium — 100% of the patients in the ICU unit are inoculated
Transcript (Google Translated):
Dr. Kristiaan Deckers, GZA Hospitals
“even more radical about for those who would faithfully think that the intensive care now follows with not vaccinated that is no longer correct us right now we see a large majority are so-called breakthrough infections and that is different from to me a few weeks ago indeed not a majority vaccinated patients in intensive had at the moment that is no longer the case have the patients we have now put on intensive. I checked it yesterday are actually all vaccinated.”
Lyons-Weiler J. Pathogenic priming likely contributes to serious and critical illness and mortality in COVID-19 via autoimmunity. J Transl Autoimmun. 2020 Apr 9;3:100051. doi: 10.1016/j.jtauto.2020.100051. PMID: 32292901; PMCID: PMC7142689. https://pubmed.ncbi.nlm.nih.gov/32292901/
Recent data from the U.K. Office of National Statistics reveals people who have been double jabbed against COVID-19 are dying from all causes at a rate six times higher than the unvaccinated
In the U.S., meanwhile, the Centers for Disease Control and Prevention is propping up the official narrative with two manipulated studies — one suggesting the jab reduces all-cause mortality, and another claiming the shot is five times more protective than natural immunity
Both studies are of questionable quality and have several problems, including selection of time and date ranges that allow them to pretend that the COVID shots are safer and more effective than they really are
According to all-cause mortality statistics, the number of Americans who died between January 2021 and August 2021 is 16% higher than 2018 (the pre-COVID year with the highest all-cause mortality) and 18% higher than the average death rate between 2015 and 2019. Did COVID-19 raise the death toll despite mass vaccination, or are people dying at increased rates because of the COVID jabs?
CDC data reveal that while the number of hospitalized patients with natural immunity fell sharply over the summer, when the delta variant took over, the number of vaccinated people being hospitalized soared, from three per month on average during the spring to more than 100 a month in late summer. Since these vaccinated patients were less than six months from their second dose, they should have been at or near maximum immunity
While recent data from the U.K. Office of National Statistics (ONS) reveal people who have been double jabbed against COVID-19 are dying from all causes at a rate six times higher than the unvaccinated,1 the U.S. Centers for Disease Control and Prevention is propping up the official narrative with a “study”2 that came to the remarkable conclusion that the COVID shot unbelievably reduces your risk of dying from all causes, which includes accidents (but excluding COVID-19-related deaths). As reported by CNN Health, October 22, 2021:3
“The research team was trying to demonstrate that the three authorized Covid-19 vaccines are safe and they say their findings clearly demonstrate that. ‘Recipients of the Pfizer-BioNTech, Moderna, or Janssen vaccines had lower non-COVID-19 mortality risk than did the unvaccinated comparison groups,’ the researchers wrote in the weekly report4of the U.S. Centers for Disease Control and Prevention.
The team studied 6.4 million people who had been vaccinated against Covid-19 and compared them to 4.6 million people who had received flu shots in recent years but who had not been vaccinated against coronavirus.
They filtered out anyone who had died from Covid-19 or after a recent positive coronavirus test … People who got two doses of Pfizer vaccines were 34% as likely to die of non-coronavirus causes in the following months as unvaccinated people, the study found.
People who got two doses of Moderna vaccine were 31% as likely to die as unvaccinated people, and those who got Johnson & Johnson’s Janssen vaccine were 54% as likely to die …”
Two key takeaways from those paragraphs are:
the researchers admit they intended to demonstrate that the shots are safe and effective, and stats can be manipulated to find what you want to find
people who got the Janssen shot did in fact have a higher death rate than the unvaccinated (54% likelihood, compared to the unvaxxed).
Are the Shots Reducing All-Cause Mortality?
The researchers hypothesize that people who get the COVID jab may be healthier overall than those who abstain, and have healthier lifestyles. In my view, this is classic Orwellian doublespeak, as most of the brainwashed don’t understand the fundamentals of healthy behavior.
I suspect their new propaganda has more to do with the fact that they only looked at data through May 31, 2021. By mid-April, an estimated 31% of American adults had received one or more shots.5 As of June 15, 48.7% were fully “vaccinated.”6 So, we can assume that by the end of May, somewhere in the neighborhood of 45% of eligible Americans were double jabbed, give or take a couple of percentage points.
The reason I suspect statistical tomfoolery is because this is precisely how the CDC invented the “pandemic of the unvaccinated” myth, where they claimed 99% of COVID-19 deaths and 95% of COVID-related hospitalizations were occurring among the unvaccinated.7
To achieve those statistics, the CDC included hospitalization and mortality data from January through June 2021, a timeframe during which the vaccinated were still in a minority.
Here, we again see them use a seven-month span of time when vaccination rates were low. More importantly, however, is that the chosen cutoff date also obscures a rapid rise in vaccine-related deaths reported to the U.S. Vaccine Adverse Events Reporting System (VAERS).
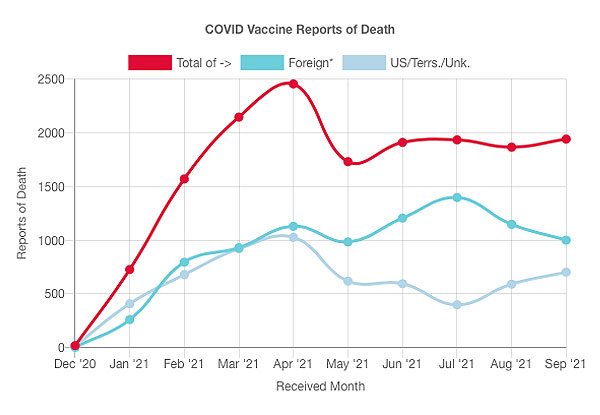
Look at the graph below, obtained from OpenVAERS mortality reports page.8 As you can see, reports of deaths following the COVID jab peaked right at the beginning of April 2021, then dropped down again during the month of April. Interestingly enough, the study notes that the daily vaccination rate has declined by 78% since April 13, 2021.
However, while the daily vaccination rate has plummeted since April, reported deaths have remained high and relatively steady. Could this be a hint that people are dying from shots they received earlier in the year?
As of January 1, 2021, only 0.5% of the U.S. population had received a COVID shot, so comparing death rates of the vaxxed and unvaxxed in December 2020 and January 2021 may not be all that fruitful. Why not include July, August and September in the analysis instead?
As you can see, reported deaths were significantly elevated during these months, compared to December and January. And, while not shown in that graph, between September 3, 2021, and October 22, 2021, the total cumulative reported death toll shot up from 7,6629,10 to 17,619.11 In other words, it more than doubled in about seven weeks — a timeframe that was not included in the CDC’s analysis.
What’s more, while the study was large and sociodemographically diverse, the authors admit that “the findings might not be applicable to the general population.”
Also, recall they changed the definition of “vaccinated” to include someone who is two weeks past their second dose (for two dose regimens). This would obfuscate the truth as there were tens of millions that received one jab or more but were not considered “vaccinated.”
Why Is All-Cause Mortality Higher in 2021?
According to all-cause mortality statistics,12 the number of Americans who died between January 2021 and August 2021 is 16% higher than 2018, the pre-COVID year with the highest all-cause mortality, and 18% higher than the average death rate between 2015 and 2019. Adjusted for population growth of about 0.6% annually, the mortality rate in 2021 is 16% above the average and 14% above the 2018 rate.
The obvious question is, why did more people die in 2021 (January through August) despite the rollout of COVID shots in December 2020? Did COVID-19 raise the death toll despite mass vaccination, or are people dying at increased rates because of the COVID jabs?
In a two-part series,13 Matthew Crawford of the Rounding the Earth Newsletter examined mortality statistics before and after the rollout of the COVID shots. In Part 1,14 he revealed the shots killed an estimated 1,018 people per million doses administered (note, this is doses, not the number of individuals vaccinated) during the first 30 days of the European vaccination campaign.
After adjusting for deaths categorized as COVID-19 deaths, he came up with an estimate of 200 to 500 deaths per million doses administered. With 4 billion doses having been administered around the world, that means 800,000 to 2 million so-called “COVID-19 deaths” may in fact be vaccine-induced deaths. As explained by Crawford:15
“This does not even include vaccine-induced deaths that have not been recorded as COVID cases, though I suspect that latter number is smaller since the only good way to hide the vaccine mortality signal is to smuggle deaths through the already-established COVID death toll.”
Corroborating Crawford’s calculations are data from Norway, where 23 deaths were reported following the COVID jab at a time when only 40,000 Norwegians had received the shot. That gives us a mortality rate of 575 deaths per million doses administered. What’s more, after conducting autopsies on 13 of those deaths, all 13 were determined to be linked to the COVID jab.16
Is the COVID Jab Responsible for Excess Deaths?
Crawford goes on to look at data from countries that have substantial vaccine uptake while simultaneously having very low rates of COVID-19. This way, you can get a better idea as to whether the COVID jabs might be responsible for the excess deaths, as opposed to the infection itself.
He identified 23 countries that fit these criteria, accounting for 1.88 billion individuals, roughly one-quarter of the global population. Before the COVID jabs rolled out, these nations reported a total of 103.2 COVID-related deaths per million residents. Five nations had more than 200 COVID deaths per million while seven had fewer than 10 deaths per million.
As of August 1, 2021, 25.35% of inhabitants in these 23 nations had received a COVID jab and 10.36% were considered fully vaccinated. In all, 673 million doses had been administered. Based on these data, Crawford estimates the excess death rate per million vaccine doses is 411, well within the window of the 200 to 500 range he calculated in Part 1.
Another interesting data dive was performed by Steve Kirsch, executive director of the COVID-19 Early Treatment Fund. In the video “Vaccine Secrets: COVID Crisis,”17 he argues that VAERS can be used to determine causality, and shows how the VAERS data indicate more than 300,000 Americans have likely been killed by the COVID shots.18Anywhere from 2 million to 5 million have also been injured by them in some way.
What Do the VAERS Data Tell Us?
In a September 18, 2021, interview with The Covexit podcast, Jessica Rose, Ph.D., who holds degrees in applied mathematics, immunology, computational biology, molecular biology and biochemistry, also discussed what the VAERS data tell us about the safety of the COVID shots.
Rose covers issues such as the magnitude of the side effects compared to other vaccination programs, the problem of under-reporting, and how causality can be assessed using the Bradford Hill Criteria. You can find a PDF of the slide show that Rose presents here.19 Here’s a summary of some of the key points made in this interview:
Between 2011 and 2020, the number of VAERS reports ranged between 25,408 and 49,412 for all vaccines. In 2021, with the rollout of the COVID shots, the number of VAERS reports shot up to 521,667, as of September 3, 2021, for the COVID shots alone. (Fast-forward to October 22, 2021, and the report tally for COVID-related adverse events has ballooned to 837,593.20)
Between 2011 and 2020, the total number of deaths reported to VAERS ranged between 120 and 183. In 2021, as of September 3, the reported death toll had shot up to 7,662. As of October 22, 2021, the death toll was 17,619.21
Cardiovascular, neurological and immunological adverse events are all being reported at rates never even remotely seen before.
The estimated under-reporting factor (URF) is 31. Using this URF, the death toll from COVID shots is calculated to be 205,809 as of August 27, 2021; Bell’s palsy 81,747; herpes zoster infection 149,017; paresthesia 305,660; breakthrough COVID 365,955; myalgia 528,457; life threatening events 230,113; permanent disabilities 212,691; birth defects 7,998.
The Bradford Hill Criteria for causation are all satisfied. This includes but is not limited to strength of effect size, reproducibility, specificity, temporality, dose-response relationship, plausibility, coherence and reversibility.
CDC Claims COVID Jab Beats Natural Immunity
If you think the CDC’s claim that the COVID jab lowers all-cause mortality is a low point in its irrational vaccine push, prepare to let your expectations sink even lower, with even more egregious Orwellian doublespeak implementation. October 29, 2021, the CDC released yet another study, this one claiming the COVID jab actually offers five times better protection against COVID-19 than natural immunity. As reported by Alex Berenson in an October 30, 2021, Substack article:22
“Yesterday the Centers for Disease Control, America’s not-at-all-politicized public health agency, released a new study purporting to show that vaccination protects against COVID infection better than natural immunity. Of course, a wave of stories about the benefits of mRNA vaccination followed.
To do this, the CDC used some magic statistical analysis to turn inside raw data that actually showed almost four times as many fully vaccinated people being hospitalized with Covid as those with natural immunity — and FIFTEEN TIMES as many over the summer. I kid you not.
Further, the study runs contrary to a much larger paper from Israeli researchers in August. As my 2-year-old likes to say, How dey do dat? Well, the Israeli study drew on a meaningful data set in a meaningful way to reach meaningful conclusions.
It counted infections (and hospitalizations) in a large group of previously infected people against an equally large and balanced group of vaccinated people, then made moderate adjustments for clearly defined risk factors.
It found that vaccinated people were 13 times as likely to be infected — and 7 times as likely to be hospitalized — as unvaccinated people with natural immunity. In contrast — how do I put this politely? — the CDC study is meaningless gibberish that would never have been published if the agency did not face huge political pressure to get people vaccinated.”
Data Manipulation Is Apparently a CDC Specialty
Berenson goes on to dissect the study in question, starting with its design, which he calls “bizarre.” The CDC analysts looked at data from 200,000 Americans hospitalized with “COVID-like” illness between January and August 2021 in nine states. Two groups were then compared:
Those who had confirmed COVID at least 90 days before and received another COVID test at the time of their hospitalization
Those who had been fully vaccinated for at least 90 days, but not more than 180 days, before their admittance and received another COVID test at the time of their hospitalization
Berenson points out what I stressed earlier, which is that choosing certain time or date ranges will allow you to make the shots appear a whole lot better than they actually are. Here, by choosing a 90- to 180-day inclusion range, they’re looking at a best-case scenario, as we now know the shots quit working after a handful of months. So, they’re only looking at that short window during which the COVID shots are at maximum effectiveness.
The 90-day criterion also ends up excluding the vast majority of patients hospitalized with COVID-like illness, both vaccinated and unvaccinated. While Berenson doesn’t address the vaccinated, few if any could have been fully vaccinated for at least 90 days prior to March, so why include January and February? Just about everyone was by definition unvaccinated at that time.
As for those with natural immunity, only 1,020 of the 200,000 patients hospitalized between January and August had a previously documented COVID infection. As noted by Berenson:23
“Given the fact that at least 20% of Americans, and probably more like 40%, had had COVID by the spring of 2021, this is a strikingly small percentage — and certainly doesn’t suggest long COVID is much of a threat.“
Of the 1,020 with natural immunity, only 89 tested positive for COVID, while 324 of the 6,328 vaccinated patients who met the study criteria tested positive. Of note here is two things:
There were more vaccinated patients hospitalized for COVID-like illness than those with natural immunity; this despite including months when vaccination rates were in the fractional and single digits
A greater number of vaccinated patients tested positive for breakthrough infection than patients with natural immunity
Hospitalization Rate Among Vaccinated Is Soaring
Berenson continues:24
“And the CDC didn’t have, or didn’t publish, figures on how many people were actually in the two groups … Instead it compared the PERCENTAGE OF POSITIVE TESTS in the two groups. But why would the percentage of positive tests matter, when we don’t know how many people were actually at risk? …
[A]mazingly, the statistical manipulation then got even worse. The natural immunity group had an 8.7% positive test rate. The fully vaccinated group had a 5.1% positive test rate. So the natural immunity group was about 1.7 times as likely to test positive. (1.7x 5.1 = about 8.7.)
With such a small number of people in the natural immunity group, that raw ‘rate ratio’ may well have failed to reach statistical significance. (We don’t know, because the CDC didn’t provide an unadjusted odds ratio with 95% boundaries — something I have never seen before in any paper.)
Instead, the CDC provided only a risk ratio that it had adjusted with a variety of factors, including ‘facility characteristics [and] sociodemographic characteristics.’
And finally, the CDC’s researchers got a number that they could publish — hospitalized people who had previously been infected were five times as likely to have a positive COVID test as people who were fully vaccinated. Never mind that there were actually four times as many people in the second group. Science!
By the way, buried at the bottom of report is some actual data. And it’s bad. The CDC divided the hospitalizations into pre- and post-Delta — January through June and June through August.
Interestingly, the number of hospitalized people with natural immunity actually fell sharply over the summer, as Delta took off. About 14 people per month were hospitalized in the winter and spring, compared to six per month from June through August. (Remember, this is a large sample, with hospitals in nine states.)
But the number of VACCINATED people being hospitalized soared — from about three a month during the spring to more than 100 a month during the Delta period. These vaccinated people still were less than 180 days from their second dose, so they should have been at or near maximum immunity — suggesting that Delta, and not the time effect, played an important role in the loss of protection the vaccine offered.”
Perhaps Rep. Thomas Massie said it best when he tweeted:25
“What do ‘road kill’ and a CDC sponsored COVID paper have in common? By the third day, they’re so picked apart they’re unrecognizable. This CDC Director is shameless for fabricating junk science with findings that stand in stark contrast to every credible academic study.”
Massie goes on to point out some obvious flaws and questions raised by the study, including the following:
The authors failed to verify recovery among those with previous infection, so any number of these “reinfections” may actually have been long-COVID.
The fact that more than 6,000 hospitalized for COVID symptoms were vaccinated, compared to just 1,000 with previous infection, counters the claim that 99% of COVID hospitalizations are unvaccinated.
The number of vaccinated people hospitalized for COVID symptoms correlate negatively with the time since vaccination; 3,625 were hospitalized within 90 to 119 days of vaccination, 2,101 within 120 to 149 days, and 902 within 150 to 179 days of vaccination. “Could initial hospitalizations be due to vaccine adverse effects or due to a temporarily weakened immune system from the vaccine?” Massey asks.26
The study only considered those with natural immunity who ended up in the hospital, and not the ones who didn’t get sick. “Natural immunity helps prevent hospitalization!” Massey says.27
Massie also notes that this paper, which is only six pages long, has an astounding 50 authors, and at least half a dozen of them disclose Big Pharma conflicts of interest. What’s more, seeing how Congress gave the CDC a cool $1 billion to promote the COVID jab, isn’t working for the CDC a conflict of interest as well?
Martin Kulldorff, Ph.D., professor of medicine at Harvard Medical School and a biostatistician and epidemiologist in the Division of Pharmacoepidemiology and Pharmacoeconomics at Brigham and Women’s Hospital, also critiqued the study in a tweet, saying:28
“This CDC study has a major statistical flaw, and the 5x conclusion is wrong, it implicitly assumes that hospitalized respiratory patients are representative of the population, which they are not. Trying to connect with authors.”
Natural Immunity Is the Best Answer
Try as the CDC might to twist the data, there’s really no question that natural immunity is superior and longer lasting than vaccine-induced immunity. This is also a long-held medical fact that has been tossed aside as too inconvenient to matter in COVID-19.
For some undisclosed reason, the government wants everyone to get the COVID injection, whether medically warranted or not. The sheer lunacy of that is cause enough to be leery and hold off on getting the risky jab. I can tell you one thing, this policy has nothing to do with safeguarding public health, because it’s driving public health in the wrong direction.
It’s quite clear that the way out of this pandemic is through natural herd immunity, and at this point, we know there’s no reason to fear COVID-19. Overall, its lethality is on par with the common flu.29,30,31,32,33 Provided you’re not in a nursing home or have multiple comorbidities, your chances of surviving a bout of COVID-19 is 99.74%, on average.34
Additionally, we also know there are several early treatment protocols that are very effective, such as the Frontline COVID-19 Critical Care Alliance I-MASK+35 protocol, the Zelenko protocol,36 and nebulized peroxide, detailed in Dr. David Brownstein’s case paper37 and Dr. Thomas Levy’s free e-book, “Rapid Virus Recovery.” Whichever treatment protocol you use, make sure you begin treatment as soon as possible, ideally at first onset of symptoms.
The reported rate of death from COVID-19 shots in VAERS, on the other hand, exceeds the reported death rate of more than 70 vaccines combined over the past 30 years, and if you are injured by a COVID shot and live in the U.S., your only recourse is to apply for compensation from the Countermeasures Injury Compensation Act (CICP).38
Compensation from CICP is very limited and hard to get. You only qualify if your injury requires hospitalization and results in significant disability and/or death, and even if you meet the eligibility criteria, it requires you to use up your private health insurance before it kicks in to pay the difference.
There’s no reimbursement for pain and suffering, only lost wages and unpaid medical bills. Salary compensation is of limited duration, and capped at $50,000 a year, and the CICP’s decision cannot be appealed.