Malone states the emergency use authorizations (EUA) are two years old and are expiring and need to be re-implemented, therefore there is a perverseincentive for our government to amplify the fear porn to keep the basis for the EUA alive. If a state of emergency does not continue, EUAs vanish like dust into the wind.
A perfect example is the Omicron death that wasn’t. Mainstream media widely reported the death as a “reinfection” of an unvaccinated man who previously had COVID. The problem is the man didn’t die from COVID. He died testing positive for the Omicron variant. He also had comorbidities. This singular case was blown all out of proportion and used to keep EUA alive. Don’t fall for it, and expect more of it.
China is separating family members, dragging folks from their homes, cramming them into buses & locking them up in metal boxes every time a new variant appears. Kids locked up alone, apart from their parents.
France just passed a law that excludes the unvaccinated from public places. Certificates of “vaccination” are required to go anywhere.
Italy mandated the jab for those over 50 and tightened green pass obligations even though the “vaccine” does not protect people from Covid but increases the chances of infection from Omicron and hospitalization.
In Greece, the unvaxxed who are over 60 will be fined 100 euros per month.
Massive protests occurred in the Netherlandsover the government imposed covid-19 restrictions & “vaccination” campaign. A January protest made world headlines when the police allowed (or ordered?) their dogs to launch brutal attacks against the protesters. In the midst of this upheaval, a young man named Gideon van Meijeren recently elected to the Dutch Parliament soundly confronts the Prime Minister.
Autopsy findings show vaccine induced autoimmune pathology in the heart, lung, liver, thyroid, salivary glands, and brain. Inflammatory events occur in the small blood vessels with an abundance of T-lymphocytes & sequestered, dead endothelial cells within the lumen.
The COVID-19 jabs rely on providing geneticinformation to the body to force it to produce a modified form of the spike protein, and should not be defined as a vaccine.
The spike protein is toxic in its own right and may induce adverse effects on the body
The viral vector jabs by AstraZeneca and Johnson & Johnson rely on human fetal cell lines and the majority of the protein in the jabs may be from this source, rather than from the viral vectors themselves.
COVID-19 jabs, especially if given repeatedly every few months, will likely cause lasting negative impacts on immune system function so increasing the risk of a wide range of other diseases while increasing risks of adverse reactions.
Clear evidence has emerged that data used for “vaccine surveillance” by the UK Health Security Agency (formerly Public Health England) has been accidentally or deliberately misrepresented to infer outcomes among the jabbed are better than for those who decline.
There is little or no evidence that informed consent is being, or has been, offered at any time during the “pandemic.”
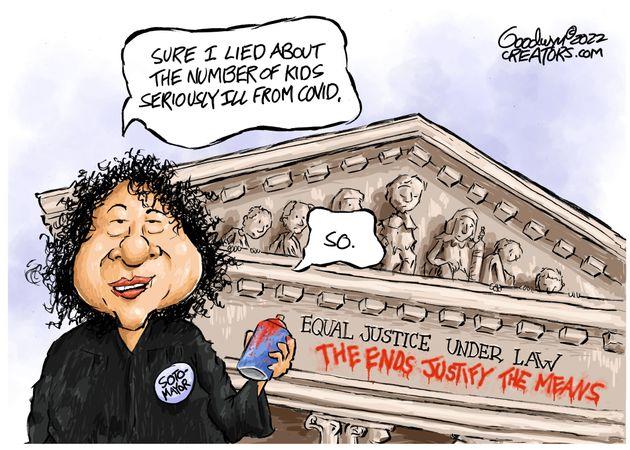
Despite the misinformation spewed forth by Justice Sotomayor, The US Supreme Court has blocked the Biden administration’s vaccine-or-test rule for US businesses, but allows vaccine mandate for most health care workers.
The National Federation of Independent Business (NFIB) argue against the Department of Labor, in the Court’s first hearing, that:
“OSHA’s sweeping regulatory dictate,” will “irreparably injure the very businesses that Americans have counted on to widely distribute COVID-19 vaccines and protective equipment to save lives—and to keep them fed, clothed, and sustained during this now two-year-long pandemic.”
The Occupational Safety and Health Administration (OSHA) rule would have required 80 million workers to get shots or periodic tests.
The OSHA ruling vote was 6-3 with Breyer, Sotomayor, and Kagan in dissent. (See link for article)
_________________
Important points:
The court allowed requiring shots for workers in nursing homes, hospitals and other facilities that receive Medicare and Medicaid payments from the federal government. (Just another reason in a very long line showing that getting government money always has strings attached.)
The vaccine mandate for healthcare workers vote was 5-4 with Thomas, Alito, Gorsuch, and Barrett in dissent, which means Roberts and Kavanaugh joined liberal justices in allowing the HHS mandate on healthcare workers to stand.
Most Americans Will Get COVID Eventually, Says Fauci
— But chances of getting sick are “very, very low” if you’re vaccinated and boosted
by Joyce Frieden, Washington Editor, MedPage Today January 12, 2022
WASHINGTON — Sooner or later, most Americans will wind up getting COVID-19, although it will likely be pretty mild for those who are vaccinated and boosted, a Biden administration official said Wednesday.
During a press briefing held by the White House COVID-19 Response Team, MedPage Today asked members of the team to elaborate on the remark that “most people are going to get COVID” made by Acting FDA Commissioner Janet Woodcock, MD, during a Senate hearing Tuesday. (See link for article)
__________________
**Comment**
Fauci finally tells the truth: COVID will NOT be eradicated and it is highly likely everyone will get it,like every other coronavirus, flu, and cold we haven’t eradicated. Logic would now follow that natural immunity would be preferred, yet our corrupt public health authorities who own the patent on the spike protein and on the injections have censored this well-known and accepted scientific fact and only push the lucrative, dangerous shots which have caused more damage than any other “vaccine” in the history of VAERS.
In a July 1, 2021, commentary in The Lancet Microbe,3 Piero Olliaro, Els Torreele and Michel Vaillant also argue for the use of absolute risk reduction when discussing vaccine efficacy with the public. They too went through the calculations, coming up with the following:
Since the beginning of the pandemic, experts have warned that the PCR test is not a valid diagnostic and produces far too many false positives, as it can pick up on “dead,” nonreplicating viral debris
The U.S. Centers for Disease Control and Prevention now admits the PCR test can remain positive for up to 12 weeks after infection. For this reason, they say most people don’t need to retest negative before ending their quarantine
The CDC also admits the PCR cannot identify active infection or measure contagiousness
People who are double-jabbed or unvaccinated and test positive for SARS-CoV-2, or have known exposure, but remain asymptomatic, now only need to isolate for five days rather than 10, but should wear a mask for another five days when at work or in public. People who are triple-jabbed do not need to isolate after exposure, but should wear a mask for 10 days
Health care workers who test positive for COVID but remain asymptomatic can return to work after seven days with a negative test, but isolation time can be cut to five days if there are staffing shortages
From the earliest days of the COVID pandemic, the PCR test has been a source of unrelenting controversy, with experts repeatedly pointing out that it’s not a valid diagnostic and produces inordinate amounts of false positives.
Importantly, a PCR test cannot distinguish between “live” viruses and inactive (noninfectious) viral particles. This is why it cannot be used as a diagnostic tool. As explained by Dr. Lee Merritt in her August 2020 Doctors for Disaster Preparedness1 lecture, media and public health officials appear to have purposefully conflated “cases” or positive tests with the actual illness in order to create the appearance of a pandemic.
Furthermore, a PCR test cannot confirm that SARS-CoV-2 is the causative agent for clinical symptoms as the test cannot rule out diseases caused by other bacterial or viral pathogens.
Almost universally, health authorities have also instructed labs to use excessively high cycle thresholds (CTs) — i.e., the number of amplification cycles used to detect RNA particles — thereby ensuring a maximum of false positives.
From the start, experts noted that a CT over 35 is scientifically unjustifiable,2,3,4 yet the U.S. Food and Drug Administration and the U.S. Centers for Disease Control and Prevention recommended running PCR tests at a CT of 40,5 and the World Health Organization recommended a CT of 45.
The pandemic of false positives was then used by world governments to implement pandemic countermeasures that have destroyed the global economy, ruined countless lives, decimated the education of an entire generation and stripped us of basic human rights and freedoms.
What the CDC’s belated admission means is that, for the past two years, Americans have unnecessarily wasted time in self-isolation — perhaps weeks — waiting for a negative test.
Time and again, the goal post for ending the pandemic theatre has been moved, and the justifications for continuing the life-destroying countermeasures have become increasingly laughable. The fearmongering over Omicron, for example, makes no rational sense based on the data available, which shows the variant is among the mildest so far, and far less likely to infect and damage the lungs.6
In the last days of December 2021, the U.S. Centers for Disease Control and Prevention issued yet another illogical protocol change.7 People who test positive for SARS-CoV-2, or have known exposure, but remain asymptomatic, now only need to isolate for five days rather than the previous 10, but should wear a mask for another five days when at work or in public. Also, they don’t need to get retested at the end of their quarantine. The stated reason? Because:
The majority of viral transmission (85% to 90%8) occurs in the first day or two before symptom onset, and two to three days after symptom onset9
The PCR test can remain positive for up to 12 weeks after you’ve recovered from the infection10,11
How is it that the CDC didn’t realize until now that the PCR test was picking up dead viral debris for three months after infection? The facts that the test, a) was far too sensitive, and b) couldn’t identify active infection, were criticisms from the start. What the CDC’s belated admission means is that, for the past two years, Americans have unnecessarily wasted time in self-isolation — perhaps weeks — waiting for a negative test.
In a December 30, 2021, appearance on MSNBC, Dr. Anthony Fauci responded to questions about the updated CDC guidance. CDC director Rochelle Walensky also tried to make sense of the new guidance in a December 29, 2021, ABC News interview (see videos above).12
Neither of them offered any explanation as for why the CDC didn’t change the rules sooner, and only now decided that keeping noninfectious people in isolation for days and weeks on end might not be so good after all.
Walensky did make a rather telling comment on CNN, though, when asked about the reasoning behind the shortened isolation guidance. “It really had a lot to do with what we thought people would be able to tolerate,” she said.13 Some have understandably translated that as “how much tyranny we thought people would be able to tolerate.”14
Differing Rules for Health Care Workers
The CDC has not given up on making the guidance as confusing as possible though. December 23, 2021, they also updated guidance for health care workers,15 stating that “Health care workers with COVID-19 who are asymptomatic can return to work after seven days with a negative test, and that isolation time can be cut further if there are staffing shortages.”16
In his MSNBC interview, Fauci was asked why health care workers are being treated differently, having to isolate for seven days rather than five, and still have to get a negative test, when the test can falsely remain positive for up to 12 weeks? What data supports this, and is it publicly available?
According to Fauci, the data to support this difference “is internal to the CDC,” but really, there’s “no specific data” to back it up, he adds. The CDC merely made “a judgment call.”
Double-Jabbed Treated the Same as Unvaccinated
The CDC’s updated guidance also puts those who have received two doses of the COVID shot in the same category as the unvaccinated, so when it comes to isolating after exposure, they have to follow the same rules, whereas those who have received a booster shot follow a different set of guidelines. As explained by the CDC:17
“For people who are unvaccinated or are more than six months out from their second mRNA dose (or more than 2 months after the J&J vaccine) and not yet boosted, CDC now recommends quarantine for 5 days followed by strict mask use for an additional 5 days.
Alternatively, if a 5-day quarantine is not feasible, it is imperative that an exposed person wear a well-fitting mask at all times when around others for 10 days after exposure. Individuals who have received their booster shot do not need to quarantine following an exposure, but should wear a mask for 10 days after the exposure.
For all those exposed, best practice would also include a test for SARS-CoV-2 at day 5 after exposure. If symptoms occur, individuals should immediately quarantine until a negative test confirms symptoms are not attributable to COVID-19.”
Fauci defended the decision to treat the double-jabbed as if they’re unvaccinated saying that those who have received a booster shot have far greater protection against the Omicron variant, compared to those who have only received one or two doses.
“When you’re infected, you’re infected,” Fauci said, and it doesn’t matter whether you’re vaccinated or not. The viral load is the same, so the risk of spreading the infection is the same. Those who have been boosted are less likely to be infected or carry a large viral load, hence they don’t need to isolate.
PCR Cannot Tell You Anything About Contagiousness
Fauci was also asked about how one can measure contagiousness. If the PCR can register positive for 12 weeks after an infection, it can’t be a reliable indicator of infectiousness. This was precisely the point that Mullis, inventor of the PCR test, attempted to make in the video at the top with respect to PCR and HIV.
So, how can we tell if we’re infectious or not? Fauci confirmed that the PCR can only tell you there’s a presence or absence of viral fragments, not whether it’s an active infection, or whether you’re actually infectious. He did not, however, provide an answer to the question as to how one can measure contagiousness.
Rapid Test Doesn’t Pick Up Omicron
Yet another confounding factor in this mess is that the rapid test apparently doesn’t pick up Omicron very well.18 Your viral load needs to be very high at the time of testing in order for the rapid test to recognize it.
This admission came within days of president Biden’s announcement that the federal government will distribute half a billion free rapid tests to homes around the country in 2022.19
It seems like a waste of resources, seeing how Omicron is starting to take over, but who knows, maybe it will pick up the common cold instead, allowing the “case” count to remain high enough to keep the charade going.
What’s the Real Death Count?
The CDC’s belated admission that the PCR test can’t identify active infection raises another question: What does this mean for those who died with a positive test? Did they actually have an active infection? If not, should they have been designated as COVID deaths?
The obvious answer to the last two questions is, of course, no. The vast majority were likely false positives, and the real death toll from COVID-19 considerably lower than we’re led to believe. The CDC undoubtedly knew this all along, seeing how they’ve been relentlessly criticized for their recommendation to run the PCR at a CT of 40. They’re trying to pretend that they just realized this, but that’s simply not believable.
My daily newsletter is still free and content will be released on Mercola.com before anywhere else. After 48 hours the articles will be transferred to my Censored Library on Substack. To view any missed content, a private membership is available for a very minimal amount with a portion of proceeds going toward our health partners who are helping in the fight to protect our freedom of speech and your right to take control of your health: https://www.mercola.com/censored-library.htm You can access the article and videos in this link for a fee.
___________________
Lastly, both Fauci and Walensky lied under oath regarding VAERS COVID injection deaths.
As of Jan. 7, 2022 there have been nearly 22,000 reported deaths after the jabs.
SARS-CoV-2 Spike Protein Takes the Gloves Off and Causes Chronic Inflammation
Studies show the NLRP3 Inflammasome response is unleashed by the Spike protein. It’s around for 4 months. Aberrant NLRP3 inflammasome response leads to chronic illness and death. What you can do.
The NLRP3 Inflammasome response is one of the myriad normal responses by which mammalian immune systems activate against viral infection. It’s supposed to be a short-term response than shuts down after the pathogen is defeated.
Good news: Spike protein primes the NLRP3 Inflammasome.
During infection, the NLRP3 Inflammasome response does its jobs.
Very bad news: Spike protein primes the NLRP3 Inflammasome, is systemic, and is found 4 months following injection.
After injection (and during Long-Haul COVID (LHC)), the NLRP3 Inflammasome response and must be doing chronic, systemic damage.
Spike Not Localized
The spike protein is not localized but is, per this Harvard study, systemic following injection
While this Ogata study found the antigen up to15 days in 3/15 patients (20%),
This study found it in circulating exosomes up to 4 months(!)
Exosomes Cutting Edge: Circulating Exosomes with COVID Spike Protein Are Induced by BNT162b2 (Pfizer-BioNTech) Vaccination prior to Development of Antibodies: A Novel Mechanism for Immune Activation by mRNA Vaccineshttps://pubmed.ncbi.nlm.nih.gov/34654691/
Boosters Mean Repeated Chronic Inflammation
With never-ending boosters, we’re going to see chronic illness in the vaccinated at rates that are undeniable. None of it will be attributed to the vaccine.
More boosters means more chronic illness and death. Science tells us we can expect increased cancer, neurodegenerative disease, and a host of sublethal inflammation-mediated symptoms.
Here is a sample of articles that tell us this is necessarily so.
Remove all other sources of toxins in your life. Thoroughly and urgently. You cannot afford these toxins. (I offer Environmental Toxicology in the Fall – email info@ipak-edu.org subject line “EnvTox” if you’d like me to offer access as pay-per-view (no instructor).
Studies Needed on the Oncogenic Potential of COVID-19 Vaccinations
Fact Checkers deny it but present no new data. We’re doing Science – and taking deep dive into the question of plausibility using molecular evidence using Systems Biology
There has been some discussion on the oncogenic potential of SARS-CoV-2 vaccination – the ability of exposure to COVID-19 vaccines to increase the risk of cancers.
This study area is obviously high priority given the disease burden that could result from mass exposures. To assess plausibility, mechanisms of action (disease pathophysiology) studies are needed.
A little background, and some detail on our project:
Background
Autoimmunity or other molecular antagonism against important cellular processes can lead to cancer. Disruption of processes that mediate DNA replication and repair, for example, or regulate cell division can be oncogenic. Given the importance of immune surveillance in our bodies against new precancerous cells, autoimmunologic impairment of the immune proteins and cells would not only spell disaster for infections, but could also lead to unchecked cancer growth.
The evidence in support of these possibilities is diverse, but hard evidence is difficult to find.
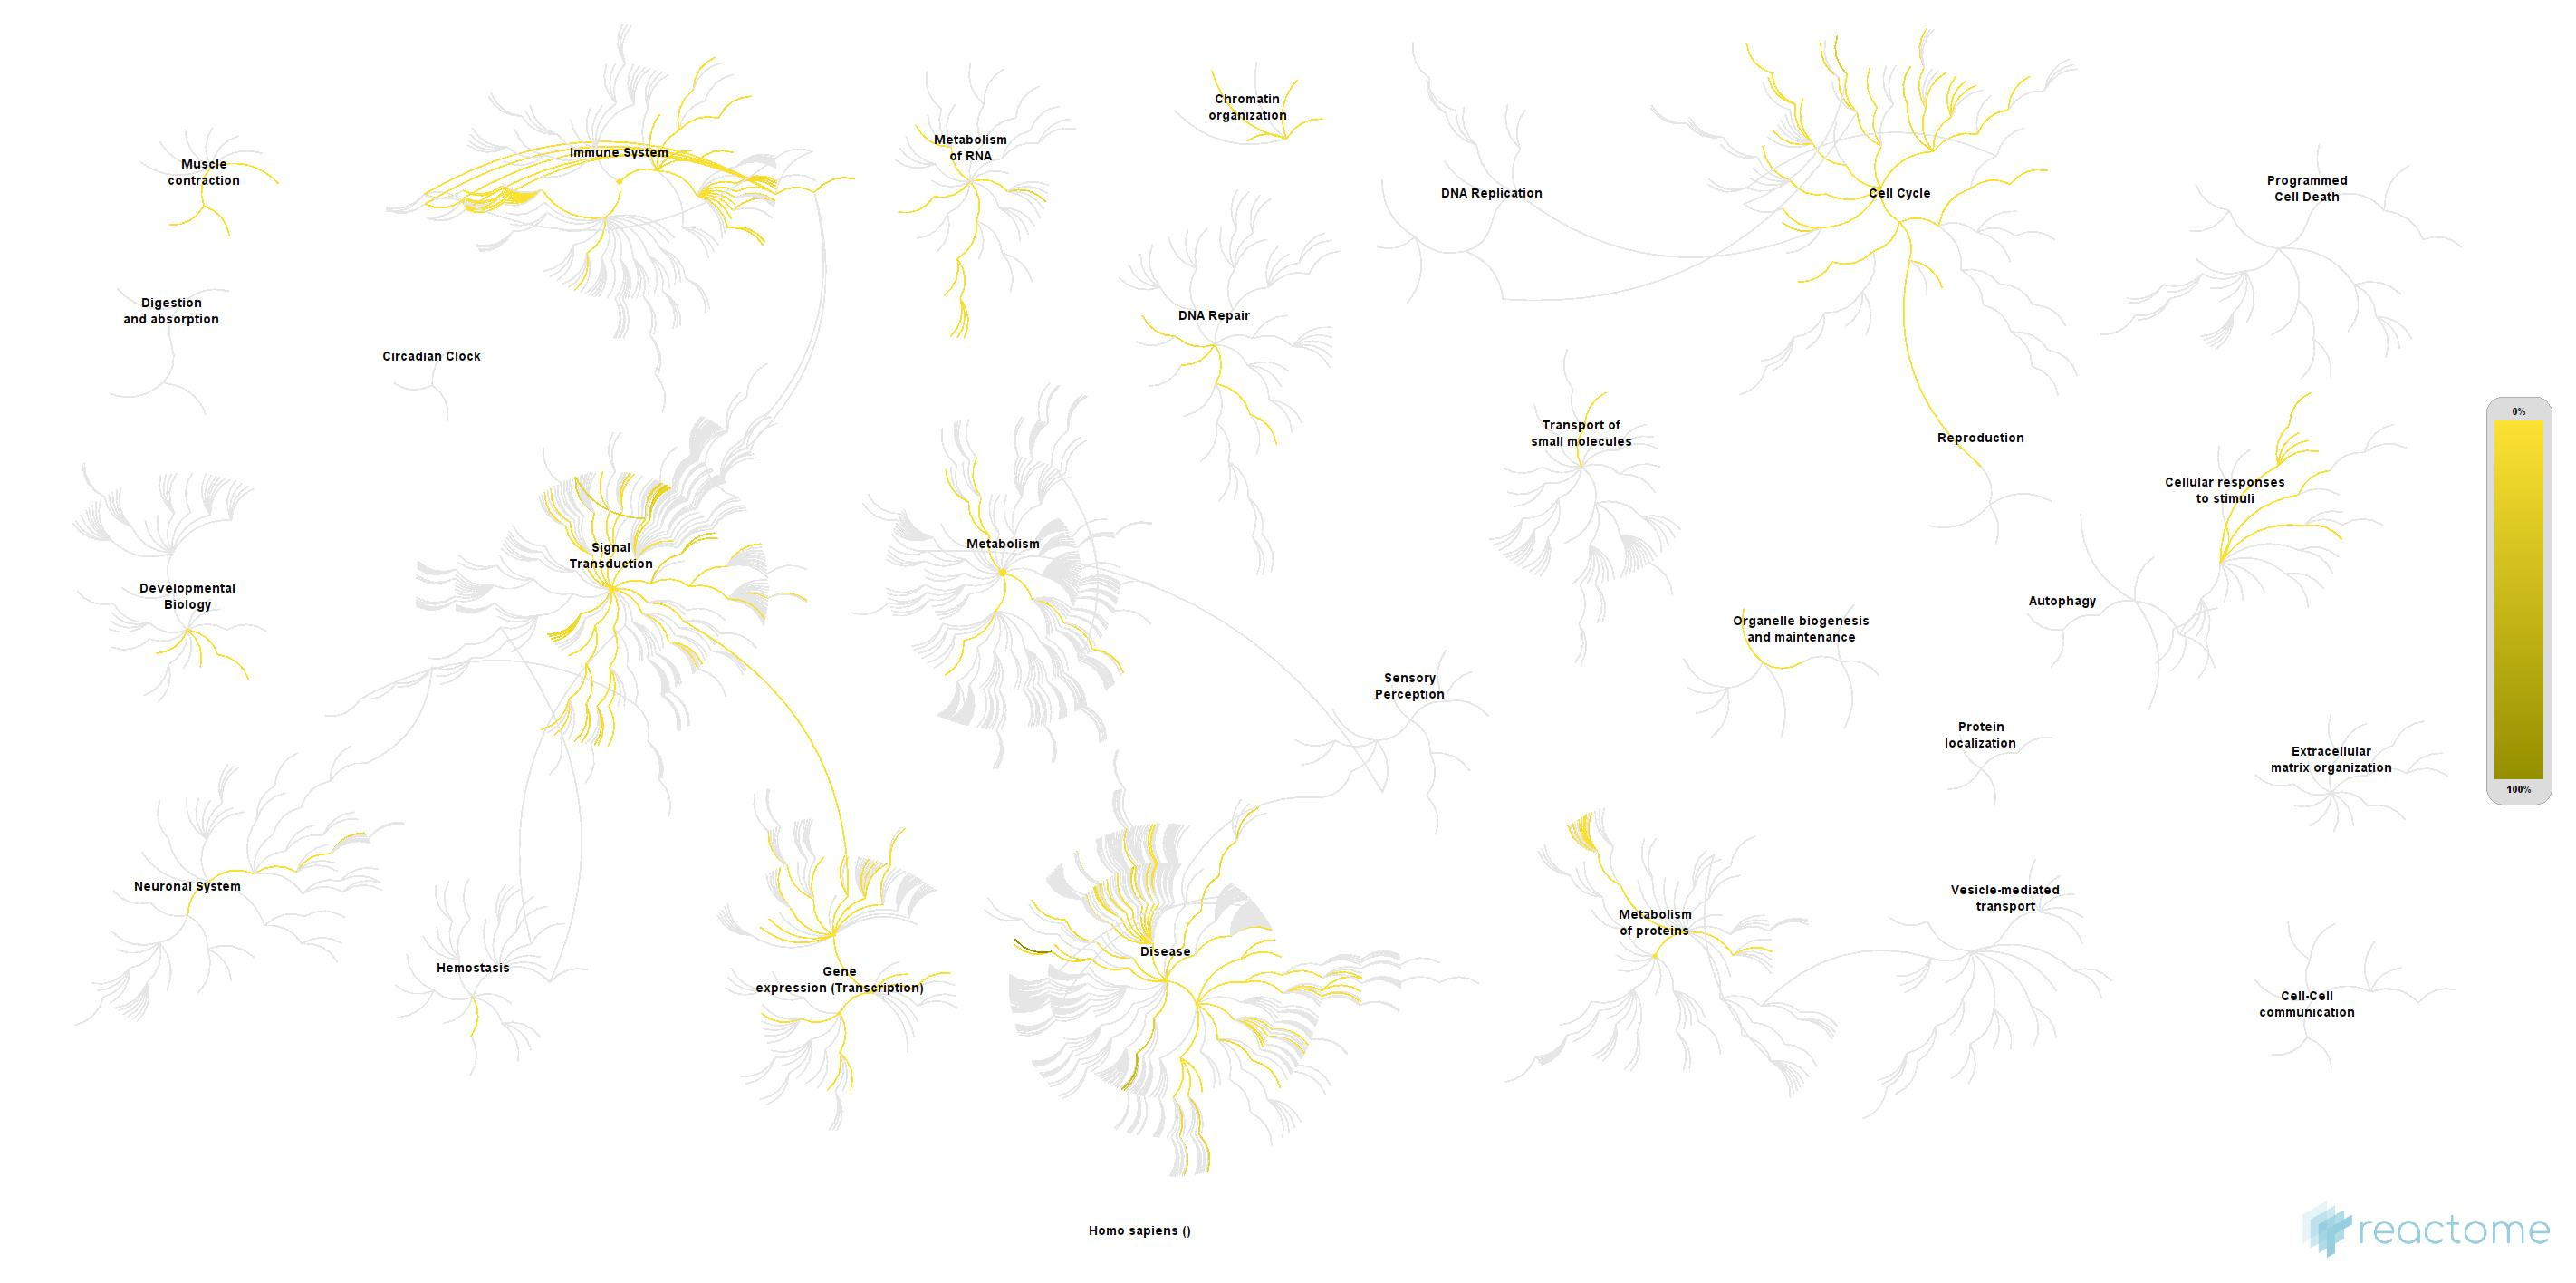
“Remarkably, over 1/3 (11/27) of the immunogenic proteins in SARS-CoV-2 have potentially problematic homology to proteins that are key to the human adaptive immune system (emboldened in Table 1). Mapping of the overall gene list to Pathways via Reactome.org revealed that many functions of the human adaptive immune system might be impacted via autoimmunity against these proteins and their interactors, including MCH(sic) Class I and Class II antigen presentation, PD-1 signaling, cross-presentation of soluble exogenous antigens and the ER-Phagosome pathway.”
This sounds like an argument for vaccination, but it’s not. Subclinical mumps, measles and pertussis infections are well established in the vaccinated. Similarly, following vaccination, the repeated exposure to SARS-CoV-2 virus in the vaccinated might lead to silent, subclinical disease processes due to SARS-CoV-2 virus infection in spite of – or because of – vaccination. These chronic exposures may be more prevalent in the vaccinated than in those with natural immunity. Thus, the question is not merely “does vaccination increase the risk of cancer”, but is better posed as “does repeated exposure to SARS-CoV-2 infections in the vaccinated lead to increased risk of cancer”?.
Dr. Ryan Cole’s Observations
While pooh-poohed by so-called “Fact Checkers”, Dr. Ryan Cole of Idaho saw and in Aug, 2021 reported an uptick in uterine cancers in women who had been vaccinated.
Dr. Burkhardt reported that 93% of post-inoculation autopsies showed lymphocyte penetration in all organs and tissues, and Dr. Bhakdi commented on autopsy findings that cells in the lymph nodes being destroyed following vaccination.
Summary:
The vaccines are bad news. Fifteen bodies were examined (all died from 7 days to 6 months after vaccination; ages 28 to 95). The coroner or the public prosecutor didn’t associate the vaccine as the cause of death in any of the cases. However, further examination revealed that the vaccine was implicated in the deaths of 14 of the 15 cases. The mos… Read more
Publications providing evidence of immune impairment
A number of publications support plausibility, and some have been dismissed without new evidence by so-called “Fact Checkers”. Important, the loss of CD8 cells in long-haul COVID was noted by Dr. Bruce Patterson (who I interview on Unbreaking Science on Jan 31, 2020). These are the natural killer cells Dr. Cole was concerned about.
is cited by these authors from the University of Texas MD Anderson Cancer Center, Houston, TX, who wrote:
“For instance, SARS CoV-2 proteins, can hijack the human immune response to pathogens and the DNA damage repair system, thereby damaging both innate and adaptive immunity”
The fact-checkers claim that Dr. Cole is mistaken, yet there it is.
Increase in All-Cause Mortality in the UK and Indiana
Unreported Truths
Vaccinated English adults under 60 are dying at twice the rate of unvaccinated people the same age
The brown line represents weekly deaths from all causes of vaccinated people aged 10-59, per 100,000 people. The blue line represents weekly deaths from all causes of unvaccinated people per 100,000 in the same age range. I have checked the underlying dataset myself and this graph is correct. Vaccinated people under 60 are twice as likely to die as unvacc… Read more Alex Berenson
What We Should Expect in the Molecular and Epidemiologic Evidence
If vaccination sets forth a cascade of events that leads to increased cancer risk in the vaccinated, we should see biological pathways related to the specific cancer types being reported as elevated, including blood cancers and per Dr. Cole, uterine cancers.
In the epidemiologic data, there should be a pulse in the risk of cancer types that is not explained by the increased risk of cancer progression due to the cessation of cancer screening visits that occurred during the lockdown. Unlike the temporary pulse from lock-down related cancers, we should see a sustained increased in cancer rates over time in the vaccinated compared to the unvaccinated. This aspect of this question is not part of the current study, but will be part of another study we will launch later this year.
IPAK SARS-CoV-2 Spike Protein Oncogenic Potential Study
Most of the people vaccinated in the US received spike-only vaccines. Here’s what we intend to do
Using the known and published immunogenic epitopes in the SARS-CoV-2 spike protein, identity homologies (similarities) with known oncogenic proteins that could lead to autoimmunity against key cancer-related proteins. For this, we’ll canvas the Human Protein Atlas for genes which if mutated confer cancer risk and use the methodology laid out in (Lyons-Weiler, 2020).
Using pathway analyses, we will characterize which biological pathways are likely to be most influenced.
We will write the results up for peer-reviewed publication.
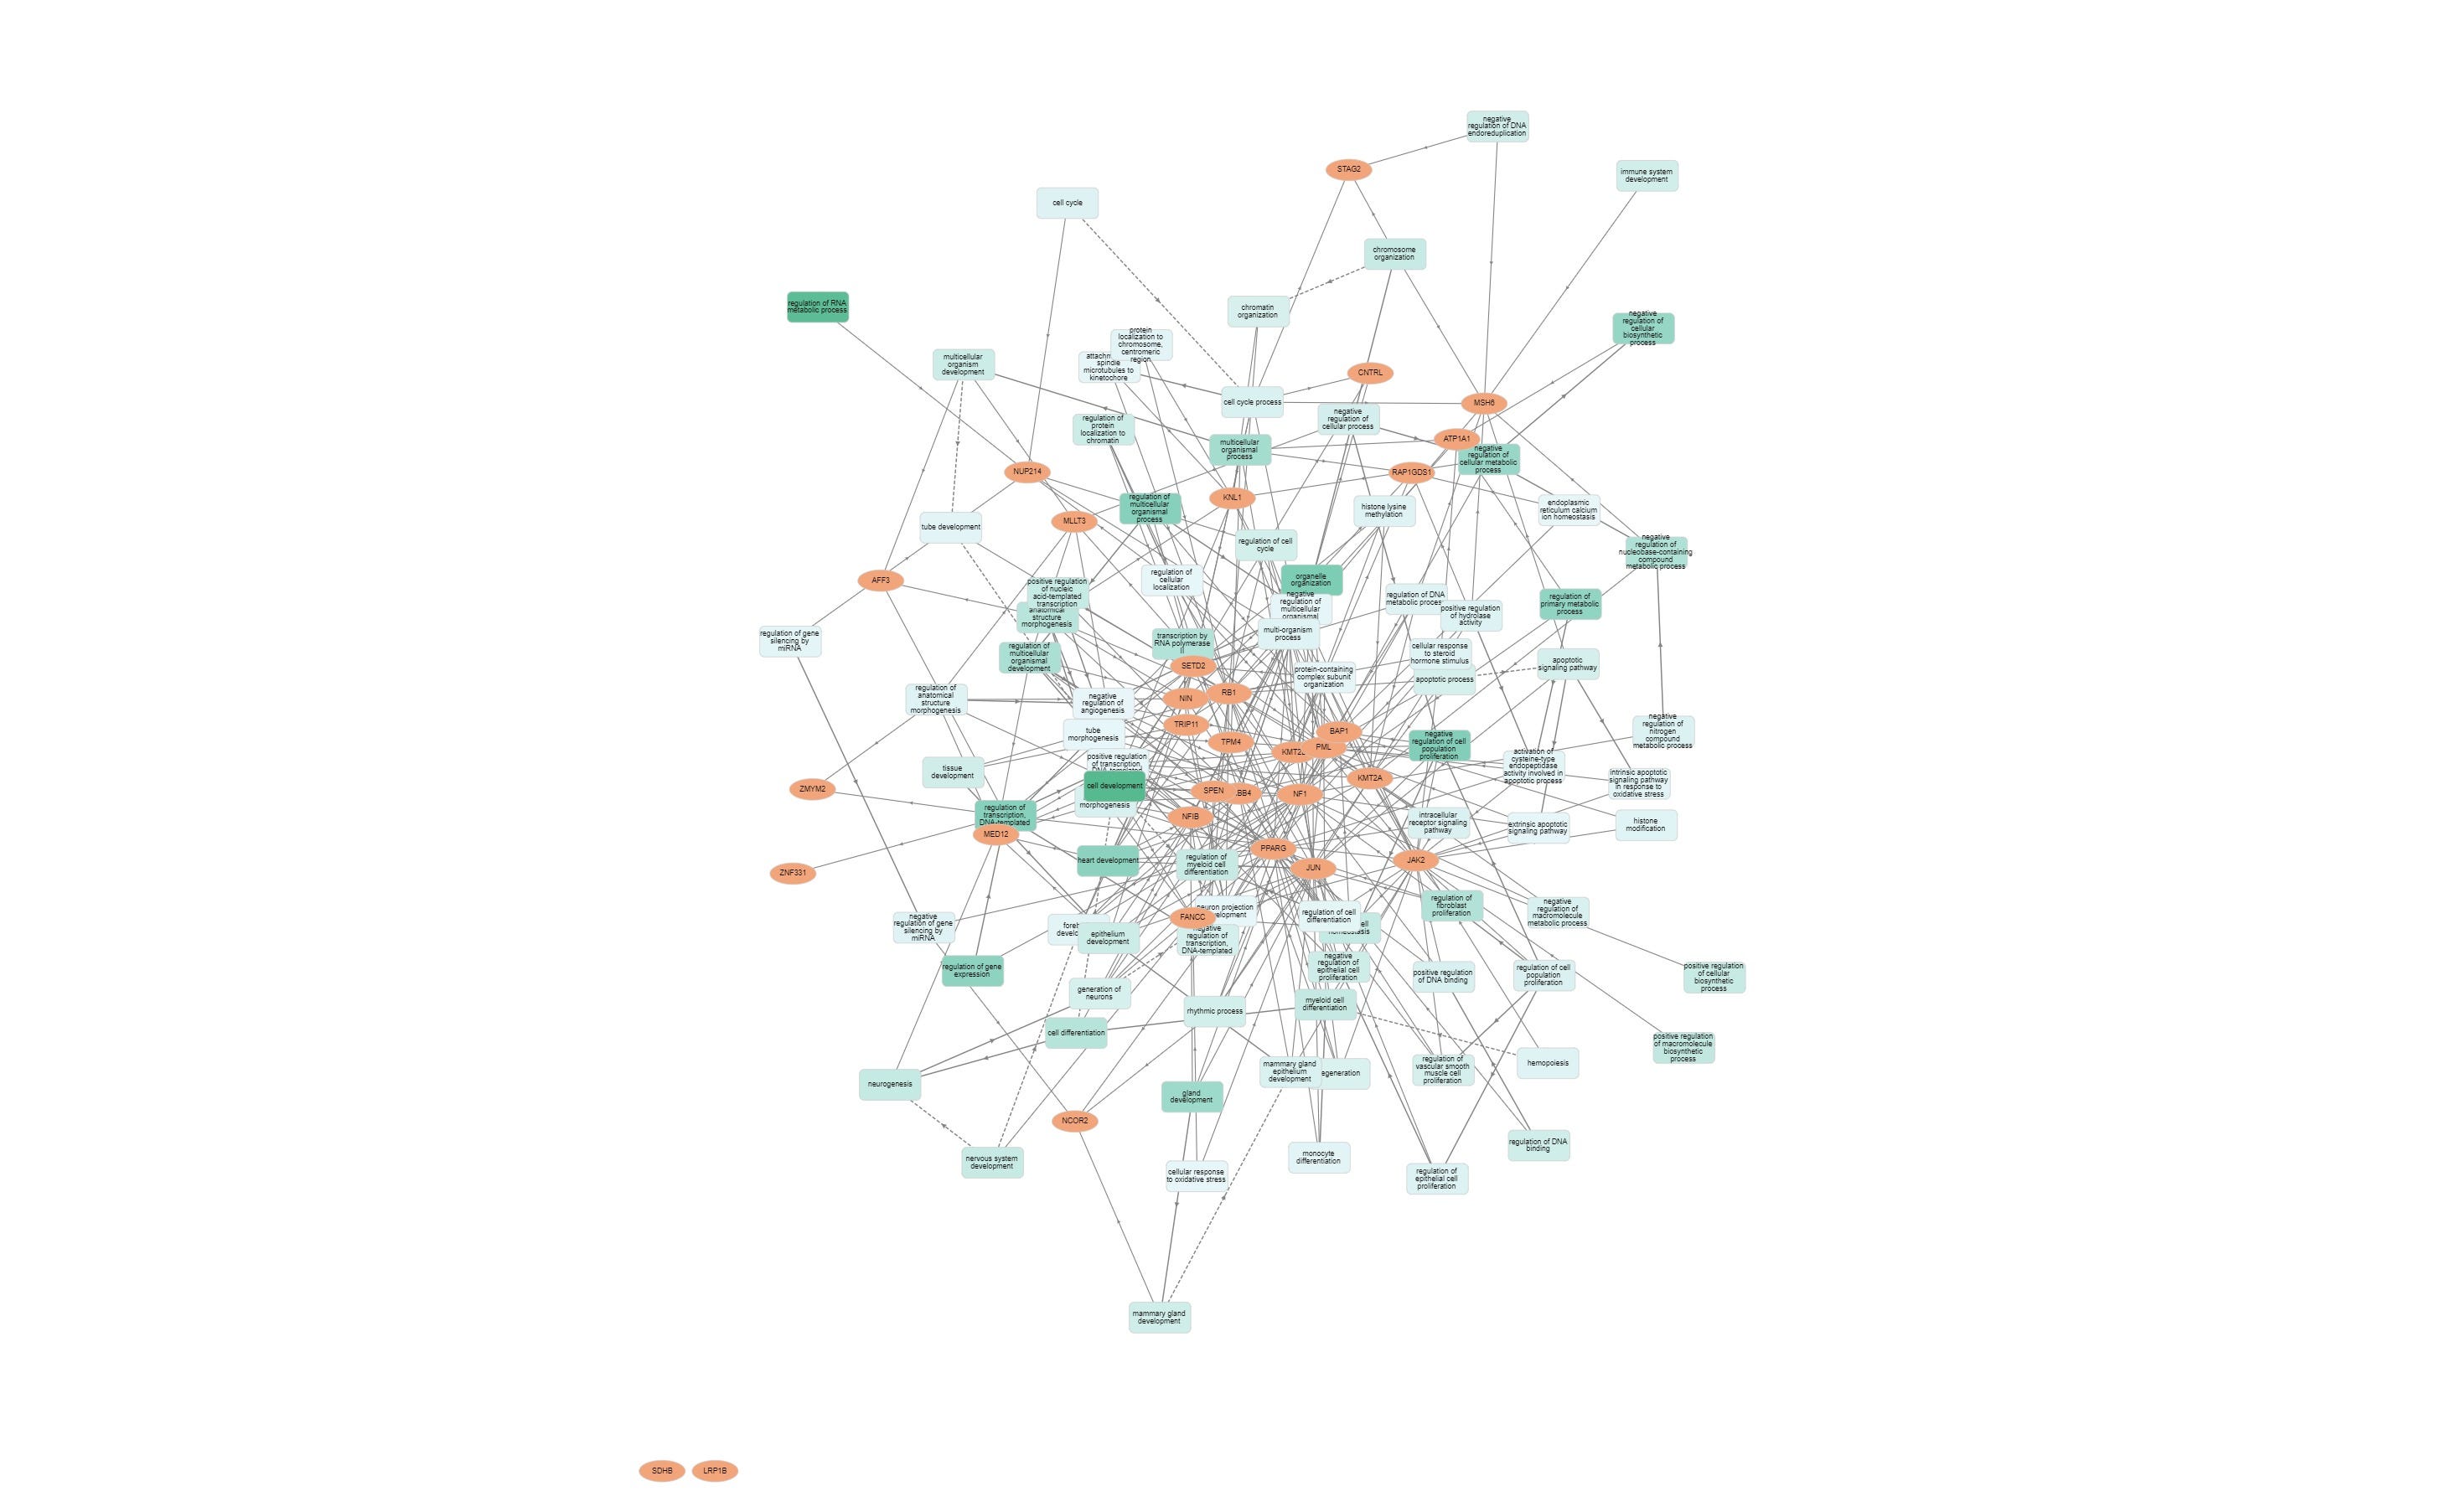
Our preliminary analysis tells us so far that yes, there appear to be impacted biological pathways (preliminary data):
Obviously, I hope this hypothesis is wrong, so we will attempt to disprove it via statistical hypothesis testing using gene enrichment analysis, a statistical technique conducted at the biological pathway level.
All of our studies are funded by the public. We have set up a dedicated donation portal for small monthly donations to IPAK, The Institute for Pure and Applied Knowledge, a not-for-profit in the Commonwealth of Pennsylvania, dedicated to this project. Funds used underwrite the costs of the study as well as any publication fees if we opt for open-access publication (an added step that we prefer to increase distribution).
All knowledge generated by IPAK via research is public domain – none of the knowledge can be used by IPAK for profitable ventures.
So, let’s see whether the hypothesis of increased oncogenic potential is plausible.
COVID Vaccine Booster Efficacy Against Infection May Fade Quickly
— New U.K. data suggest steep drop-off in protection, potentially giving Omicron more power
by Kristina Fiore, Director of Enterprise & Investigative Reporting, MedPage Today December 28, 2021
Real-world data from the U.K. showed that efficacy of a third dose of a COVID-19 vaccine waned significantly at the 10-week mark, leaving boosted individuals at risk of infection with Omicron.
HSA assessed 147,597 Delta and 68,489 Omicron cases from November 27 to December 17.
The Pfizer primary series & booster, showed efficacy against symptomatic disease was 70% immediately after the third dose but fell to 45% at 10 weeks or longer.
Having a Pfizer primary series but a Moderna booster saw protection against symptomatic disease hover around 70% to 75% for up to 9 weeks post-boost.
Having a primary series of AstraZeneca, efficacy peaked at 60%, 2 to 4 weeks after either a Pfizer or Moderna booster, then fell to 35% with Pfizer and 45% with Moderna by around 10 weeks.
They omitted efficacy against severe disease, hospitalization, and death because there weren’t enough Omicron cases admitted to the hospital.
Data from Israel also suggests waning efficacy after boosters, but the ‘powers that be’ still illogically recommend more boosters despite the fact.
Data from Israel also showed a doubling in the rate of infection with Delta in ages 60 & up within 4-5 months after a 3rd shot and no indication of reduced efficacy against severe disease. (But remember, they are not looking at absolute risk reductionso it’s all skewed to make the jabs appear efficacious).
Yet the vaccine cultists keep recommending more jabs. Peter Hotez, MD, PhD, is pushing a 4th shot for healthcare workers due to exposure to Omicron (despite there not being enough Omicron hospitalizations to even use for the study). Hotez is worried about instability in the health system but never stops to ponder the instability caused by the jabs themselves. This one-sided thinking is prolific regarding these shots.
The article then delves into the oft repeated mantra that these jabs somehow “reduce illness” and proceeds to rattle off all sorts of numbers which you can read for yourself. They end the litany with the following caution: “the findings have low confidence because these are early analyses with small numbers of hospitalizations, limited follow-up time,minimal adjustment for previous infection, and limited spread into the most vulnerable age group.“
Millions are suffering with Lyme disease while being drained further by a predatory medical industry, criminal CDC and fraudulent pharmaceutical industry. You probably know some if you aren’t one. They’re being treated for bipolar disorder, fibromyalgia, MS, Alzheimer’s, MS, schizophrenia, personality disorder or many other bogus diseases. The money is in drugs that don’t work, especially psychoactives which in the long term will create the symptoms they are supposed to treat. If you were blind sided by Lyme, you likely lost your career, maybe your home and family. Here is how I fared for 47 years, what I learned that would have saved me all those nightmares. It would have also saved my wife who was also destroyed by Lyme disease and our three children born with it. I give you no illusions or false promises, only how I met God, fought the fight and won the game long before I found out about Lyme. Also, you may request a link to a FLIPPING BOOK online version of the book which is much easier to use. For an example of a technical flipping book I’ve written, see http://foosresearch.appspot.com
Foos writes about his long struggle Lyme disease. This is not for the faint of heart – but no Lyme/MSIDS story ever is. The desperation is tangibly felt, as is the cruel, abusive attitudes of clueless doctors who are much more willing to write you off as a nut-job than a person struggling with numerous pathogens – any one of which can kill you but together put you in a pit of despair so deep you wonder if you will ever be able to crawl out of it.
Foos was particularly challenged with a complete mental and physical breakdown and a near death experience. He had severe infections in his sinuses, facial tissues, legs and feet. Struggling with involuntary facial contortions and facial agony, Foos, like so many, had to find answers for himself. Being a biologist and soils engineer, he labored day and night slaving in the lab to learn the scientific properties of bentonite.
University of Washington reports that almost a third go onto suffer persistent COVID symptoms. They found that the S1 segment of the spike protein is recoverable from human monocytes in PASC patients up to 15 months after an acute infection compared to controls.
The Royal Society’s SET-C group describe a wide range of symptoms that overlap with M.E.
Since its introduction in 2006, Seahorse XF technology has been used in over 7,000 peer-reviewed publications and AONM now offers a range of tests of mitochondrial and cellular performance using Seahorse as well as extracellular flux analysis with luciferase assays. AONM will be holding a series of webinars in the first quarter of 2022 explaining the tests.
Virtual conference on autoimmune encephalopathy (PANDS/PANDAS) takes place on Feb. 9-11.