Archive for the ‘research’ Category

Study Shows American Dog Ticks in Western U.S. Are a Separate Species

https://entomologytoday.org/2021/08/25/american-dog-ticks-western-new-species-dermacentor-similis/

Study Shows American Dog Ticks in Western U.S. Are a Separate Species

Dermacentor similis, male

Researchers have split the medically important American dog tick into two species: the existing Dermacentor variabilis in eastern states and the newly described Dermacentor similis west of the Rocky Mountains. An adult male D. similis tick is shown here. (Photo courtesy of Paula Lado, Ph.D.)

By Melissa Mayer

Melissa Mayer

Melissa Mayer

Rocky Mountain spotted fever spreads when Rickettsia rickettsia bacteria pour into a bite wound while an American dog tick takes a blood meal. Unlike some other tick-borne diseases, which require a longer bite to transmit, Rocky Mountain spotted fever infection may take place within the first 30 minutes of the tick bite.

The distribution of the American dog tick (Dermacentor variabilis) in the United States is a wide yet broken one. It’s mostly found throughout the central and eastern parts of the country—with a few western populations all the way on the other side of the Rocky Mountains. But are these widely separated populations really the same species?

In a study published this month in the Journal of Medical Entomology, a team of researchers at Ohio State University used an integrative taxonomy approach—looking at both physical and genetic evidence—to determine that the ticks formerly known as Dermacentor variabilis in the west are a new species, which they’ve named Dermacentor similis.

Wild, Wild West

Paula Lado, Ph.D.

Paula Lado, Ph.D.

“We were working on other aspects related to Dermacentor evolution and phylogenetics, and our results consistently showed a separation between populations from the western states and all other locations eastern of the Rockies,” says lead author Paula Lado, Ph.D., who is now with the Center for Vector-Borne Infectious Diseases at Colorado State University. “And that had been shown in other studies in the past, so we decided to explore the topic in depth.”

Dermacentor tick collection locations

(See link for article)

___________________

**Comment**

The study also found that ticks from Wisconsin and Michigan formed a small subcluster in the eastern group, which means there’s probably some variation there.

The difference between these ticks is in the minutia.  They both will happily infect you. While taxonomy considers this a “win” it’s just more research that doesn’t help patients at all. A tick is a tick is a tick.  All suck your blood and have the potential of transmitting life-altering pathogens into the human and animal body.

Important quotes:

And, because the American dog tick transmits the bacteria that cause Rocky Mountain spotted fever as well as other pathogens, describing a new species like D. similis means taking a close look at which diseases these ticks can carry and how well they do it, which is called vector competency.

“Splitting D. variabilis into two species may mean that they could be vectors for different pathogens,” Lado says. “In my opinion, it is crucial to determine the vector competency of the new species, D. similis. That will allow for us to know what pathogens are transmitted by both Dermacentor species.”

A word of warning on those quotes: all of these variables have been proven over time to be short-sighted as ticks can acquire the ability to transmit things they never used to transmit.  They have also been found in places they never were before.  Doctors looking at entomology maps have been misdiagnosing people for decades as the information is constantly changing, limited, and imperfect. Please see: The Confounding Debate Over Lyme in the South (Speilman’s maps)

Transmission times have been hotly contested for over 40 years. Mainstream medicine and conflict-riddled researchers and public health ‘authorities’ continue to doggedly state the party line that Lyme transmission takes at least 24-48 hours, whereas reality paints a far different picture, showing the potential transmission of Lyme (and other pathogens) can occur within a few hours.  It must also be remembered that minimum transmission time has never been determined, and some coinfections like Powassan virus can be transmitted within minutes. There’s also the sticky issue of partially fed ticks being able to transmit much sooner.

There is an absolute dearth of research on the issue of coinfected ticks and coinfected patients.  Does coinfection alter transmission times?  The coinfection issue remains in the Dark Ages, leaving patients and the doctors who dare to treat them muddling blindly through the process.  But, hey now we know some worthless information about the undersides of ticks!

Again, the only box Lyme/MSIDS fits into is “Pandora’s.” Trying to put a lid on this thing is completely futile.

For more:

Below is a picture of a tick, without food or water for days, and the thousands of eggs it laid.

Tick eggs

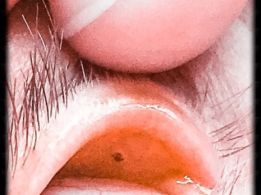
Ticks aren’t picky, and can show up in the wildest of places:

IMG_2121

636354599974837121-jcoyle-eye16059-1zz7fdgtyszqd-0lbizw1fg

Lyme Disease: A Persistent Infection

https://danielcameronmd.com/lyme-disease-persistent-infection/

LYME DISEASE: A PERSISTENT INFECTION

woman with lyme disease infection holding her head
Chronic manifestations of Lyme disease have been described for more than three decades. In 1970, Logigian and Steere described 27 patients with chronic neurologic Lyme disease, who had been ill for up to 14 years. Some improved, some relapsed and others remained ill. [1]
 

There are multiple studies indicating that Lyme disease can result in a persistent infection, causing chronic symptoms that may require treatment with extended courses of antibiotics. The National Institute of Health (NIH) conducted three Lyme disease trials, which validated the existence and severity of chronic manifestations of Lyme disease.2-4  The study’s patients were ill for years, an average of 9 years in one trial. Three of the four trials confirmed that treatment with antibiotics can fail. These patients reported severe fatigue, impaired cognitive function, pain and poor function despite antibiotic treatment.5

Some doctors have dismissed the possibility that a persistent tick-borne infection might underlie a patient’s illness,6 while other doctors believe that Lyme disease may cause a persistent infection and be an underlying cause of illness.7

Dr. Shor and colleagues summarized potential mechanisms for a persistent infection.

“Potential survival mechanisms of Lyme disease persistence include:

  • immune evasion
  • immune modulation
  • presence of subpopulations of persister cells
  • physical seclusion—within cells, collagen-rich tissues, and immunologically protected sites (CNS, joints, and eyes), is one method of immune evasion
  • biofilm generation is another recognized form of physical seclusion. Published reports document that Borrelia burgdorferi can produce biofilm in vitro and examination of infected human tissues demonstrated B. afzelii and B. burgdorferi embedded in biofilm.” [7]
Editor’s perspective: Patients are finding it increasingly difficult to locate a doctor who is willing to at least consider the presence of a persistent infection.
References:
  1. Logigian EL, Kaplan RF, Steere AC. Chronic neurologic manifestations of Lyme disease. N Engl J Med. Nov 22 1990;323(21):1438-44. doi:10.1056/NEJM199011223232102
  2. Klempner MS, Hu LT, Evans J, et al. Two controlled trials of antibiotic treatment in patients with persistent symptoms and a history of Lyme disease. N Engl J Med. Jul 12 2001;345(2):85-92. doi:10.1056/NEJM200107123450202
  3. Krupp LB, Hyman LG, Grimson R, et al. Study and treatment of post Lyme disease (STOP-LD): a randomized double masked clinical trial. Neurology. Jun 24 2003;60(12):1923-30. doi:10.1212/01.wnl.0000071227.23769.9e
  4. Fallon BA, Keilp JG, Corbera KM, et al. A randomized, placebo-controlled trial of repeated IV antibiotic therapy for Lyme encephalopathy. Neurology. Mar 25 2008;70(13):992-1003. doi:10.1212/01.WNL.0000284604.61160.2d
  5. Rebman AW, Aucott JN, Weinstein ER, Bechtold KT, Smith KC, Leonard L. Living in Limbo: Contested Narratives of Patients With Chronic Symptoms Following Lyme Disease. Qual Health Res. Mar 2017;27(4):534-546. doi:10.1177/1049732315619380
  6. Wormser GP, McKenna D, Karmen CL, et al. Prospective Evaluation of the Frequency and Severity of Symptoms in Lyme Disease Patients With Erythema Migrans Compared With Matched Controls at Baseline, 6 Months, and 12 Months. Clin Infect Dis. Jan 23 2020;doi:10.1093/cid/ciz1215
  7. Shor S, Green C, Szantyr B, et al. Chronic Lyme Disease: An Evidence-Based Definition by the ILADS Working Group. Antibiotics (Basel). Dec 16 2019;8(4)doi:10.3390/antibiotics8040269

_____________________

For more:

If you haven’t signed Lyme Advocate Carl Tuttle’s petition, please do:  https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/29506824?  The petition is calling for a congressional investigation of the CDC, IDSA, and ALDF for their mismanagement of Lyme/MSIDS – for their long denial of chronic Lyme and the damage it causes.  This denial has played out in patients not getting diagnosed and treated properly with long-term antimicrobials due to abysmal serology tests which are wrong 86% or more of the time.  It also plays out in the fact doctors who dare to treat outside the unscientific and antiquated CDC Lyme guidelines are hunted down and persecuted, making doctors afraid to treat patients.

The same government funded institutions behind the Lyme debacle are currently also behind the COVID debacle and need to be held accountable.  They have done many of the same things which has resulted in patients not getting the care they need.  These corrupt public health ‘authorities’ are the problem.

85% of Turkish MS Patients Have Lyme – Study Shows

https://storage.googleapis.com/journal-uploads/ejbps/article_issue/volume_6_april_issue_4/1553939970.pdf

FREQUENCY OF BORRELIA BURGDORFERI WESTERN BLOT AND LTT POSITIVITY AMONG MULTIPLE SCLEROSIS PATIENTS FROM TURKEY

Barbaros Çetin* Dokuz Eylul University, Faculty of Science, Department of Biology, Izmir, Turkey.

Article Received on 29/01/2019 Article Revised on 19/02/2019 Article Accepted on 12/03/2019

ABSTRACT

In Turkey, Borrelia burgdorferi infections are not well known among physicians and almost completely overlooked. On the other hand, a small number of seropositivity studies (%3.3-%73) show that Borrelia burgdorferi is common in Turkey. There is no diagnostic biological marker in multiple sclerosis (MS). Only several clinical criteria used for diagnosis. These criteria are also compatible with other diseases. Lyme disease is currently among them. In the chronic phase of Lyme, demyelination can form and this can be confused with MS.

In this study 126 patients, between ages 17 and 66, with a definite diagnosis of multiple sclerosis was evaluated, and were found according to be found positive Borrelia burgdorferi western blot and LTT test results 108 (%85.72). Only 18 (%14.28) patients have negative test results.

The results show that LYME disease is very common in Turkey and LYME patients with neurological symptoms are misdiagnosed with multiple sclerosis.

___________________

Important excerpts:

Multiple sclerosis affects at least 2.8 million people worldwide.

Worldwide, MS prevalence parallels the distribution of the Lyme disease pathogen Borrelia burgdorferi, and in America and Europe, the birth excesses of those individuals, who later in life develop MS exactly mirror the seasonal distributions of Borrelia transmitting Ixodes ticks.

According to the one of the most effective scientific papers, written by 4 Norwegian scientists, 10 of 10 MS patients were found to have a cyst form of the Borrelia spirochete bacteria. No bacteria were found in a control group. The cysts turned into spirochetal bacteria when cultured. The studies conclude that all ten MS patients have been infected with a spirochete. Concludes that MS could very well be a chronic infection.[8]

Since 1911, more than the past one hundred years, several older but also recent autopsy findings linked to in many articles found that all deceased MS patients’ brains harbored living lyme spirochetes. Even when tests, notorious for their large percentage of false negatives were used on living MS patients, staggeringly many tested positive for active Lyme borreliosis.[9]

“Spirochetes in MS” (Buzzard, E.F.), Published in the famous Lancet magazine in 1911, revealed the presence of Lyme spirochetes in the brains of MS patients. Over a period of more than a century, more than 50 international scientific papers proving the MS-Lyme relationship have been published in prestigious medical journals.[16-111] If you follow the European Medical Literature concerning Multiple Sclerosis from 1911 to 1939, you may find that in France, Germany and England, there were independent researchers all observing similar things and coming to similar conclusions:

  1. Spirochetes are often found in conjunction with the lesions in the brains of patients who have died with MS.
  2. These spirochetes can be isolated and can infect many mammalian animal models; including: mice, rats, hamsters, guinea pigs, rabbits, dogs, and primates.
  3. The spirochetes could be re-isolated from the brains of the infected animals and be inoculated into more un-infected animals and re-isolated from their brains.
  4. Multiple sclerosis may often be associated with Borrelia infection.
  5. Points out that a considerable body of clinical evidence supports the concept that cystic L-forms of Borrelia burgdorferi may cause MS. 

For more:

PTSD, COVID-19 & Lyme Disease: A Perspective

https://danielcameronmd.com/ptsd-covid-19-and-lyme-disease-a-perspective/

PTSD, COVID-19 AND LYME DISEASE: A PERSPECTIVE

man with PTSD and COVID-19 getting console in therapy

“Post-traumatic stress disorder (PTSD) is a severe mental health condition caused by a terrifying event outside the normal range of usual human experience.”[1] While it is often associated with events such as an assault or disaster, post-traumatic stress disorder can occur in people with severe health problems.

Patients with chronic Lyme disease have reported symptoms of PTSD. Now, an article entitled “PTSD as the second tsunami of the SARS-Cov-2 pandemic,” by Dutheil et al. indicates that some COVID-19 patients are experiencing post-traumatic stress disorder, as well.¹

The authors highlight several observations on the SARS-Cov-2 pandemic and PTSD that would also apply to Lyme disease patients that I have seen in my practice.

PTSD in COVID-19 pandemic

  • “With a poor understanding of viruses and spreading mechanisms, the evocation of SARS is generating a great anxiety contributing to promote PTSD.”
  • “In the families of cases, the brutal death of family members involved a spread of fear and a loss of certainty, promoting PTSD.”
  • “PTSD symptoms involve chronic severe anxiety with re-experiencing the traumatic event, flashbacks, nightmares, increased arousal, and reduced social life.”
  • “People suffering from PTSD are prone to not seek care, because of barriers such as lack of information and cost of mental health care, being afraid of stigmatization, or beliefs that symptoms may increase with time.”
  • “PTSD individuals are more at-risk of suicidal ideation, suicide attempt, and deaths by suicide, in huge proportions.”

PTSD in chronic Lyme disease

  • The poor understanding of Lyme disease and associated tick-borne illnesses has generated a great deal of anxiety.
  • The severity of chronic illness following Lyme disease involves a spread of fear and a loss of certainty.
“People suffering from PTSD are prone to not seek care, because of barriers such as lack of information and cost of mental health care, being afraid of stigmatization, or beliefs that symptoms may increase with time.”
  • I have Lyme disease patients who re-experience the traumatic event, flashbacks, nightmares, increased arousal, and reduced social life, as described by the authors.
  • I have seen Lyme disease patients who “are prone to not seek care, because of barriers such as lack of information and cost of mental health care, being afraid of stigmatization, or beliefs that symptoms may increase with time.”
  • I have seen suicidal ideation in patients I have treated. Dr. Robert Bransfield, a psychiatrist specializing in tick-borne illnesses, has described suicidal ideation, suicide attempt, and deaths by suicide in patients in his practice.²

Author’s perspective: I hope that a better understanding of post-traumatic stress disorder in COVID-19 patients will lead to a better understanding of PTSD in Lyme disease.

References:
  1. Dutheil F, Mondillon L, Navel V. PTSD as the second tsunami of the SARS-Cov-2 pandemic. Psychol Med. Apr 24 2020:1-2. doi:10.1017/S0033291720001336
  2. Bransfield RC. Aggressiveness, violence, homicidality, homicide, and Lyme disease. Neuropsychiatr Dis Treat. 2018;14:693-713. doi:10.2147/NDT.S155143

______________________

**Comment**

PTSD is very, very real.  I’ve had it myself.  My husband had it. People don’t typically understand that Lyme/MSIDS IS a brain disease and can affect you psychologically in many ways.  You can hear voices, hallucinate, have PTSD or OCD, depression, de-personalization, and so many other mental issues.

It’s important to get to the root of the issue – and that’s treating the infections; however, you may also need to address the mental health aspects as well with a trained professional.  A word of warning; however, I would highly recommend a Lyme literate professional as many patients have been abused at the hands of uneducated professionals who blindly follow the CDC/IDSA ideology.  These people can cause more harm than good.  I would also seek to get a referral from either a knowledgable patient or health professional you know and trust.

For more:

Study Shows ADE in Those Getting COVID JABS

https://www.journalofinfection.com/article/S0163-4453(21)00392-3/fulltext

Infection-enhancing anti-SARS-CoV-2 antibodies recognize both the original Wuhan/D614G strain and Delta variants. A potential risk for mass vaccination?

Published: August 09, 2021DOI:https://doi.org/10.1016/j.jinf.2021.08.010

Abstract

Antibody dependent enhancement (ADE) of infection is a safety concern for vaccine strategies. In a recent publication, Li et al. (Cell 184 :4203–4219, 2021) have reported that infection-enhancing antibodies directed against the N-terminal domain (NTD) of the SARS-CoV-2 spike protein facilitate virus infection in vitro, but not in vivo. However, this study was performed with the original Wuhan/D614G strain. Since the Covid-19 pandemic is now dominated with Delta variants, we analyzed the interaction of facilitating antibodies with the NTD of these variants.
Using molecular modeling approaches, we show that enhancing antibodies have a higher affinity for Delta variants than for Wuhan/D614G NTDs. We show that enhancing antibodies reinforce the binding of the spike trimer to the host cell membrane by clamping the NTD to lipid raft microdomains. This stabilizing mechanism may facilitate the conformational change that induces the demasking of the receptor binding domain. As the NTD is also targeted by neutralizing antibodies, our data suggest that the balance between neutralizing and facilitating antibodies in vaccinated individuals is in favor of neutralization for the original Wuhan/D614G strain. However, in the case of the Delta variant, neutralizing antibodies have a decreased affinity for the spike protein, whereas facilitating antibodies display a strikingly increased affinity.
Thus, ADE may be a concern for people receiving vaccines based on the original Wuhan strain spike sequence (either mRNA or viral vectors). Under these circumstances, second generation vaccines with spike protein formulations lacking structurally-conserved ADE-related epitopes should be considered.
_____________________
Important points:
  • Antibodies developed from the current COVID injections cause the body to overreact to mutations like Delta, proving ADE.
  • While the author recommends scrapping current jabs with newer ones, can we just admit they are all unnecessary, ineffective, and unsafe?
  • Mutations/variations are a normal, mundane aspect of viral evolution, but experts are stating that mass vaccination campaigns are causing them as they push the virus to mutate to survive.
  • Logic would indicate these vaccination campaigns should be stopped for this very reason, along with the fact these jabs have caused more reports of adverse reactions and death than any other jabs in the history of VAERS, and VAERS typically only captures 1% of reports, so it’s actually far, far worse in reality.
  • Dr. Lee Merrit explains that ALL animals in previous mRNA biologic studies DIED from ADE (antibody dependent enhancement).  Key word:  ALL
  • Natural immunity should be accepted and embraced, as historically it is the only thing that confers lasting immunity.