Archive for the ‘research’ Category

IDSA Guidelines Ignore Psychiatric Consequences of Lyme Disease

https://www.lymedisease.org/bransfield-psychiatric-lyme-disease/

27 AUG 2021

Bransfield: IDSA guidelines ignore psychiatric consequences of Lyme disease

Dr. Robert Bransfield delivered the following public comment at the recent meeting of the federal Tick-Borne Disease Working Group.

I’m a psychiatrist from New Jersey, who has treated thousands of Lyme disease patients over the past thirty years. I have also performed research. Three issues I would like to raise:

*A recent study unequivocally proves Lyme disease causes mental illnesses.

*This Working Group needs to be more attentive to the psychiatric symptom from TBD.

*The IDSA guidelines fail to recognize this causal association.

I recommend the following

The Working Group needs to gather and share information on psychiatric symptoms caused by Lyme/TBD.

Since the IDSA guidelines fail to recognize this causal association, they are outdated and the committee needs to recommend that all federal references and links to their guidelines must be removed.

To expand:

A recent article using the 7 million patients in the Danish nationwide database was published in the American Journal of Psychiatry, the number one psychiatric journal in the world. It proved the causal association between Lyme and any mental disorder, affective disorders, suicide attempts and death by suicide.

There are 400 other peer-reviewed journal articles proving the causal association between tick-borne diseases and psychiatric symptoms and 73 with dementia. Mental illness is the major cause of disability and death from tick-borne disease.

Psychiatric findings from TBD can include

  • developmental disorders
  • autism spectrum disorders
  • affective disorder
  • depression
  • anxiety disorders
  • addiction
  • opioid addiction
  • cognitive impairments
  • dementia
  • suicidality
  • violence
  • other impairments
This has caused chronic disability and deaths from suicides, drug overdoses, auto accidents and homicides.

This working group needs input from psychiatrists who understand tick-borne diseases and psychoimmunology. Addressing the causal association between tick-borne diseases and psychiatric symptoms and sharing this information with legislators and the public is critical.

When the psychiatric morbidity, mortality and disability are adequately considered, it greatly shifts risk/benefit clinical decision making involving diagnosis and treatment.

The American Psychiatric Association guidelines recognize this association, but the IDSA guidelines fail to consider the psychiatric consequences of Lyme disease. Therefore, these guidelines are outdated, unscientific, and hazardous.

The Working Group needs to recommend that all federal government links and references to these guidelines be removed.

Robert Bransfield, MD, DLFAPA, a past president of the International Lyme and Associated Diseases Society, is an internationally recognized expert in how Lyme disease affects mental health.

Dr. Bransfield’s list of 473 peer-reviewed articles that support the evidence of Lyme and other tick-borne diseases causing neuropsychiatric illness: List of citations

____________________

**Comment**

Dr. Bransfield is a true pioneer when it comes to psychiatric manifestations of Lyme/MSIDS.  He has fought long and hard on this arena.  He’s a rock star in my book.

For more:

Lyme Disease-Causing Bacteria Spotted on Routine Blood Films

https://news.mayocliniclabs.com/2021/08/11/rare-lyme-disease-causing-bacteria-spotted-on-routine-blood-films/

Rare Lyme Disease-Causing Bacteria Spotted on Routine Blood Films

Eye on Innovation features exciting advances taking place at Mayo Clinic Laboratories. This monthly series shines a spotlight on recently developed tests and highlights how Mayo Clinic translates ideas and discoveries into testing resources that improve diagnosis and care for patients across the globe.

The bacterium was revealed through Mayo Clinic Laboratories’ polymerase chain reaction (PCR) blood test for Lyme disease (Test ID: PBORR). That PCR testing is the preferred method for differentiating between the two bacteria. People who have B. mayonii infection also may test positive with the Lyme disease serology test (Test ID: LYME), but the test will not distinguish a B. mayonii infection from a B. burgdorferi infection.

It’s long been known that Lyme disease is caused by bacteria transmitted through the bite of an infected black-legged tick (otherwise known as the deer tick). The understanding for many years was that one species of bacteria was the main culprit behind Lyme disease in the United States: Borrelia burgdorferi.

But in 2016, researchers at Mayo Clinic discovered a new species of bacteria that causes Lyme disease. They named it Borrelia mayonii, after Mayo Clinic’s founders, Drs. William and Charles Mayo.

A key difference that has been noted between B. mayonii and B. burgdorferi is that B. mayonii spirochetes are found at high levels in peripheral blood, whereas B. burgdorferi spirochetes are not. Researchers surmised that meant the B. mayonii spirochetes potentially could be found on routine peripheral blood smears.

http://

Borrelia mayonii, Aug. 18, 2021

“IT IS IMPORTANT FOR PATHOLOGISTS AND LABORATORIANS TO KNOW THAT SPIROCHETES OF BORRELIA MAYONII CAN OCCASIONALLY BE SEEN ON ROUTINE PERIPHERAL BLOOD SMEARS,” SAYS BOBBI PRITT, M.D., CHAIR OF MAYO’S DIVISION OF CLINICAL MICROBIOLOGY AND THE PAPER’S LEAD AUTHOR. “OTHERWISE, THEY WOULD PROBABLY ASSUME THAT THE SPIROCHETES WERE FROM THE BORRELIA SPECIES THAT CAUSE RELAPSING FEVER, WHICH IS VERY DIFFERENT FROM LYME DISEASE.”

Because B. mayonii has only been found in the Upper Midwest of the United States, it remains a rare cause of Lyme disease and may frequently go undetected. Understanding that its spirochetes can occasionally be visualized in routine blood films may raise awareness and recognition of the uncommon bacterium, and it could point the way to more consistent and accurate diagnosis of this cause of Lyme disease.

That proved to be true earlier this year when staff in Mayo Clinic’s Division of Clinical Microbiology observed several spirochaetes on thin blood films from a specimen that had tested PCR positive for B. mayonii. The bacteria were confirmed to be B. mayonii through genome sequencing. The findings were published in July in the journal Clinical Microbiology and Infection.

___________________

**Comment**

Since Borrelia miyamotoi is not a reportable illness to the CDC, no one has any clue about prevalence, and despite authorities continually stating it’s “rare,” reports are coming in continually that it’s highly likely to be a much bigger problem than ‘authorities’ believe.  Also, despite their statement that Bm has only been found in the upper midwest in the U.S., California ticks have carried Bm for a long time, and there are reports of it worldwide.

It was recently discovered that:

For more:

Low Immune Response to COVID-19 Injections in Patients With Impaired Immune Systems & Injections Linked to Functional Neurological Disorders

https://www.technologynetworks.com/biopharma/news/low-immune-response-to-covid-19-vaccines-in-patients-with-impaired-immune-systems

Low Immune Response to COVID-19 Vaccines in Patients With Impaired Immune Systems

This article is based on research findings that are yet to be peer-reviewed. Results are therefore regarded as preliminary and should be interpreted as such. Find out about the role of the peer review process in research here. For further information, please contact the cited source.The OCTAVE study – a multi-centre UK-wide trial led by the University of Glasgow and co-ordinated by the University of Birmingham’s Cancer Research UK Clinical Trials Unit – is evaluating the immune responses to COVID-19 vaccination in patients with immune-mediated inflammatory diseases such as cancer, inflammatory arthritis, diseases of the kidney or liver, or patients who are having a stem cell transplant.

The OCTAVE trial is one of the largest studies in the world so far into post-SARS-CoV-2 vaccination in immunocompromised patients and is funded by the Medical Research Council (MRC). OCTAVE is a collaborative research project involving groups in the Universities of Glasgow, Birmingham, Oxford, Liverpool, Imperial College London and Leeds Teaching Hospitals NHS Trust.

The study used a variety of state-of-the-art immune tests performed on blood samples taken before and/or after COVID-19 vaccination in around 600 people recruited across the UK. OCTAVE’s early data show that 40% of people in the patient groups studied mounted a low serological immune response after two SARS-CoV-2 vaccines.

In addition to this, the initial data shows that approximately 11% of immunocompromised patients fail to generate any antibodies 4 weeks after two vaccines. Failure to generate antibodies is found at higher proportion in some specific patient sub-groups; in particular, in patients with ANCA-Associated Vasculitis who have received Rituximab treatment.  (See link for article)

_____________________

**Comment**
The proportion of patients with lower levels of antibody reactivity as per disease cohort compared to the baseline for healthy subjects:

  • Those with Antineutrophil Cytoplasmic Antibody (ANCA)-Associated Vasculitis (AAV) (a group of diseases characterised by destruction and inflammation of small vessels) who are being treated with Rituximab – 90%
  • Those with inflammatory arthritis – 54%
  • Those undergoing Haemodialysis (the most common kind of dialysis – a procedure to remove waste products and excess fluid from the blood when kidneys stop working properly) – 21%
  • Those on Haemodialysis receiving immunosuppressive therapy – 42%
  • Those with Hepatic (liver) disease – 51%
  • Those with solid cancer – 17%
  • Those with Haematological malignancies (blood cancers) – 39%
  • Those who have have undergone haemopoietic stem cell transplant (bone marrow transplant) – 33%

The article states there is no current agreed clinical cut off to measure COVID-19 vaccination response.

While Lyme/MSIDS isn’t stated specifically, please note the issues of inflammation, vasculitis, liver disease, and arthritis – ALL issues Lyme/MSIDS patients can suffer from.

https://www.medpagetoday.com/neurology/generalneurology/94151?

COVID Vaccines Linked to Functional Neurological Disorders

— These events may fuel vaccine hesitancy, experts say
A glitch/distortion of a computer rendering of a brain
Functional neurological disorders (FND) were found to be associated with COVID-19 vaccines, according to recent case reports.

Two cases of young women manifesting FND after COVID-19 vaccination were reported by Alfonso Fasano, MD, PhD, of the University of Toronto, and Antonio Daniele, MD, PhD, of Università Cattolica del Sacro Cuore in Rome, in a letter to the Journal of Neurology, Neurosurgery, and Psychiatry.

Two other published reports showed probable FND precipitated by COVID-19 vaccine administration, highlighting that FND should be considered when assessing post-vaccine neurologic symptoms, wrote Matthew Butler, MD, of Kings College London in England, and co-authors in the Journal of Neuropsychiatry and Clinical Neuroscience.

FND involves a disruption in normal brain mechanisms for controlling the body. It can be triggered by physical or emotional events including head injury, medical or surgical procedures, or vaccinations. People with FND may present with a range of neurological symptoms such as seizures, sensory abnormalities, gait or balance disturbance, or weakness. FND is distinct from feigning because patients perceive their symptoms as involuntary.  (See link for article)

__________________

**Comment**

The authors predictably state, despite this seriously debilitating condition that will NOT be a rare phenomenon, that it “should not hamper ongoing vaccination efforts.”

Of course their big worry is the negative impact on vaccination campaigns.  Remember, it’s all “for the greater good,” even if it isn’t good for you.

Important quote:

“In both patients, neurological symptoms were characterized by a sudden onset and overt inconsistency, as typically observed in patients with FND,” Fasano and Daniele wrote.

And of course they purposely bring in another doctor to strengthen their argument that,“correlation does not imply causation.”  This of course is true; however, they must have missed the paper that shows patterns in VAERS data that provides evidence of causality. 

And what about the fact the burden of proof of regarding “vaccine” safety should be upon the “vaccine” manufacturers and our public health authorities?

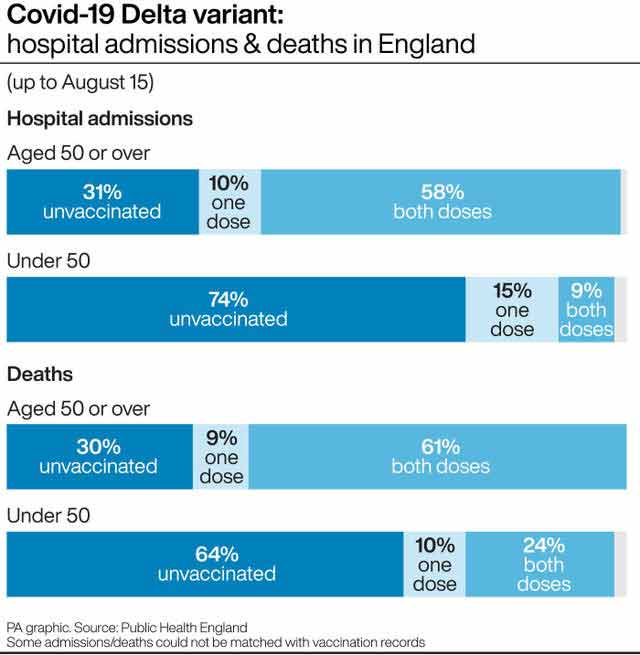
See the following graph which shows that as of August 15, 2021:

  • 58% of COVID patients admitted to hospital who were over the age of 50 had received two doses of COVID injections
  • 10% had received one dose

This means that partially or fully “vaccinated” individuals made up 68% of hospitalizations.

Regarding deaths in the over-50 group, the clear majority, 70%, are either partially or fully “vaccinated.”

Keep in mind that the author neglected to differentiate between age groups in the under-50 group.

A preprint published last month found waning immunity. People vaccinated in January had a 2.26 times greater risk for a breakthrough infection than those vaccinated in April.

“There are so many breakthrough infections that they dominate and most of the hospitalized patients are actually vaccinated,” says Uri Shalit, a bioinformatician at the Israel Institute of Technology (Technion) who has consulted on COVID-19 for the government.

Their answer?  Boosters.  However, Dvir Aran, a biomedical data scientist at Technion states “Boosters are unlikely to tame a Delta surge on their own”, and “Do not think that the boosters are the solution.”

Are you confused with the illogic yet?

The Medpage article also pointed out a paper in JAMA Neurology that discussed videos on social media showing people with severe neurological symptoms, such as convulsions and difficulty walking, after receiving a COVID-19 vaccine.

Their take-away: these videos could fuel vaccine hesitancy.
Ya think?!

Sadly, the elephant in the room that continually is ignored by mainstream medicine and the media is that there are frightening adverse reactions and deaths occurring remarkably close to injection time – minutes to months after injections.  This should be cause for immediate alarm. Further, they fuel variants and don’t stop transmission or infection.

These injections should be stopped immediately until more safety data is available.

With Three Invasive Tick Species Thriving in Connecticut, State Scientist Warns of Major Public Health Hazard

https://www.courant.com/news/connecticut/hc-news-ct-more-ticks-20210816-eafwrhehkbhspacc7r5qrw4m4m-story.html

With three invasive tick species thriving in Connecticut, state scientist warns of major public health hazard

Stratford, Ct. - 08/13/2021 - Dr. Goudarz Molaei, with Connecticut's Agricultural Experiment Station, searches for ticks trapped on a canvas dragged through shoreline vegetation. Photograph by Mark Mirko | mmirko@courant.com
Stratford, Ct. – 08/13/2021 – Dr. Goudarz Molaei, with Connecticut’s Agricultural Experiment Station, searches for ticks trapped on a canvas dragged through shoreline vegetation. Photograph by Mark Mirko | mmirko@courant.com (Mark Mirko/The Hartford Courant)

State scientist Goudarz Molaei pulled a square of cloth through brush and grass on the Stratford coast recently, then stopped and pointed to a crawling smear of larvae on the white fabric.

The tiny arachnids were either Gulf Coast or lone star ticks, two of three invasive species, along with the Asian long-horned tick, that have recently established footholds in Connecticut.

First seen only in pockets near the coast, the blood-sucking, disease-carrying ticks have spread into other parts of the state. Compared with past years, many more worried residents and visitors have submitted ticks to the Connecticut Agricultural Experiment Station, mostly deer ticks that may carry Lyme disease, Molaei said. The tally so far in 2021 is 4,700 tick submissions to the testing laboratory, compared with a total annual average of 3,000 submissions.

Milder winters and warmer temperatures overall are helping the ticks survive and thrive in Connecticut.

“This is going to be a major public health concern in the near future, if it is not already,” Molaei said.  (See link for article)

_____________________

**Comment**

Important takeaways:

  • Previously only .2% of submitted ticks were lone star ticks which increased to 4.2% this year. They transmit ehrlichiosis, STARI, spotted fever rickettsiosis, tularemia, Alpha-gal allergy, and Heartland and Bourbon Viruses.
  • The researcher states that it’s a matter of time before the entire state of Connecticut will be infested with Asian long-horned tick – the tick that can reproduce by cloning. It is supposedly less attracted to human skin but can spread diseases that make both animals and humans seriously ill.
  • The Gulf Coast tick overwintered successfully in Connecticut but currently is limited to coastal areas.  Thirty percent tested there were infected with rickettsiosis, which is similar to but less serious than Rocky Mountain Spotted Fever.
  • The deer tick, or blacklegged tick transmits Lyme disease and is active any time temperatures are above freezing.  All life stages bite humans.
  • The following percentages of ticks were sent to the Experiment Station this year:
    • 72.8% deer ticks (32% were positive for Lyme, 10% for Babesia, 4% for Anaplasmosis – and 2% tested positive for at least 2 disease agents concurrently)
    • 23.1% American dog ticks
    • the rest were lone star ticks

Asian Longhorned Tick Confirmed in Missouri

https://agriculture.mo.gov/news/newsitem/uuid/2510b251-b71d-4107-8d0b-45455a8d9834/asian-longhorned-tick-confirmed-in-missouri

July 27, 2021

Asian Longhorned Tick Confirmed in Missouri

JEFFERSON CITY —The Missouri Department of Agriculture, working in conjunction with the Missouri Department of Health and Senior Services and Missouri State University, has confirmed the first finding of an Asian longhorned tick (Haemaphysalis longicornis) in Missouri. Missouri becomes the 16th state with a presence of the tick species, following the first confirmed report of the Asian longhorned tick in the United States in 2017.

Asian longhorned ticks are light brown in color and are very small, often smaller than a sesame seed. Unlike other ticks, a single female Asian longhorned tick can produce offspring (as many as 1,000 at a time) without mating. That means individual animals could host thousands of ticks, which can cause great stress on a heavily infested animal.

The Department encourages producers to continue protective measures and to check their livestock regularly for ticks. Keeping grass and weeds trimmed and clearing away brush are important tick prevention practices. If you spot any unusual looking ticks or large infestations on your animals, contact your local veterinarian.

According to the Center for Disease Control, the Asian longhorned tick appears to be less attracted to human skin. However, ticks of any kind should be removed immediately, as they can carry diseases that affect human health. Use EPA-approved insect repellent when you will be in or near tall grasses or wooded areas.

Research on the presence of tick species in Missouri continues through a partnership between the Missouri Department of Conservation and A.T. Still University. Residents are asked to send ticks to the University through September 2022 so that University researchers can study the distribution of ticks in Missouri and any human pathogens transmitted by those ticks. For more information, or to find out how to submit a sample, visit Missouri ticks and tick-borne pathogen surveillance (atsu.edu).

To learn more about the Missouri Department of Agriculture, please visit Agriculture.Mo.Gov.

__________________

**Comment**

It spreads SFTS (sever fever with thrombocytopenia syndrome), “an emerging hemorrhagic fever,” causing fever, fatigue, headache, nausea, muscle pain, diarrhea, vomiting, abdominal pain, disease of the lymph nodes, and conjunctival congestion, but the potential impact of this tick on tickborne illness is not yet known. In other parts of the world, this Longhorned tick, also called the East Asian or bush tick, has been associated with several tickborne diseases, such as spotted fever rickettsioses, Anaplasma, Ehrlichia, and Borrelia, the causative agent of Lyme Disease.

For a 2016 literature review on SFTS:http://infectious-diseases-and-treatment.imedpub.com/research-advances-on-epidemiology-of-severefever-with-thrombocytopenia-syndrome-asystematic-review-of-the-literature.php?aid=17986
Although the clinical symptoms of SFTS and HGA are similar to each other, but the treatment methods of the two diseases are totally different. Doctors notice that the biggest difference between the clinical symptom of SFTS and HGA is that SFTS patients generally without skin rash, the dermorrhagia is also not seriously, and few massive hemorrhage cases were reported [23]. It is also reported that SFTS patients had gastrointestinal symptoms, such as nausea, vomiting, and diarrhea, which are rarely observed in HGA patients [2]. So these differences can be used as the auxiliary basis of differential diagnosis.

At present, there is still no specific vaccine or antiviral therapy for SFTSV infection. Supportive treatment, including plasma, platelet, granulocyte colony stimulating factor (GCSF), recombinant human interleukin 11, and gamma globulin is the most essential part of case treatment [44]. Meanwhile, some measures were taken to maintain water, electrolyte balance and treat complications are also very important.
Ribavirin is reported to be effective for treating Crimean-Congo Hemorrhagic Fever (CCHF) infections and hemorrhagic fever with renal syndrome, but it is still inadequate to judge the effect of ribavirin on SFTS patients because of the study limitation without adequate parameters were investigated [45]. Host immune responses play an important role in determining the severity and clinical outcome in patients with infection by SFTSV.

For Viral treatment options: https://madisonarealymesupportgroup.com/2016/03/28/combating-viruses/

And lastly, please know ticks parasitize one another, potentially spreading all manner of diseases to humans. This fact also shoots holes in the regurgitated mantra that only certain ticks carry certain pathogens.  If they are feasting on one another, they can potentially infect each other and then us: https://madisonarealymesupportgroup.com/2018/03/07/tick-bites-tick-hyperparasitism/

Also, over time, ticks can acquire the ability to transmit pathogens they didn’t transmit before.