Archive for the ‘research’ Category

Broken Science Tonight 7:30pm ET & The Illusion of Evidence Based Medicine

https://www.theepochtimes.com/dr-martin-kulldorff-how-to-dismantle-the-cartel-of-public-health-funding-and-rekindle-open-scientific-inquiry  Go here for episode

Dr. Martin Kulldorff: How to Dismantle the ‘Cartel’ of Public Health Funding and Rekindle Open Scientific Inquiry

JAN JEKIELEK

This episode will premiere on Thurs. March 31, at 7:30 p.m. ET.     

“New ideas always come from the fringe in science. So we have to encourage new ideas to come up. We can’t have science become a religion where there are dogmas.”

In this episode, filmed at Hillsdale College’s Censorship of Science conference, we sit down with Dr. Martin Kulldorff, an epidemiologist, biostatistician, and former professor of medicine at Harvard Medical School. He’s a co-author of the Great Barrington Declaration that argued for “focused protection” of the vulnerable instead of lockdowns.

Kulldorff breaks down what he sees as the “power hubs” controlling policy, research funding, and career advancement in the scientific world.

“Dr. Fauci sort of sits on the biggest chunk of infectious disease research money in the world. So it takes a bit of guts to contradict his view on pandemic strategy.”

Kulldorff is the scientific director at the Brownstone Institute and a founding fellow at Hillsdale College’s Academy for Science and Freedom.

“I’m very concerned that 400 years of enlightenment or scientific progress may come to an end. And I think we have to work very hard to avoid that.”

For more: 

http://

The Illusion of Evidence Based Medicine

Dr. John Campbell

March 26, 2022

Dr. Campbell goes through a paper that is in the British Medical Journal (BMJ) on how evidence based medicine has been corrupted by corporate interests, failed regulation, and commercialization of academia.

The Research Leader, child psychiatrist Adelaide Leemon B. McHenry, is professor emeritus Emeritus Professor at Cal State University. The research is not commissioned, but is externally peer reviewed & was published on March 16, 2022:  https://www.bmj.com/content/376/bmj.o702

Evidence based medicine has been corrupted by corporate interests, failed regulation, and commercialisation of academia, argue these authors

The advent of evidence based medicine was a paradigm shift intended to provide a solid scientific foundation for medicine. The validity of this new paradigm, however, depends on reliable data from clinical trials, most of which are conducted by the pharmaceutical industry and reported in the names of senior academics. The release into the public domain of previously confidential pharmaceutical industry documents has given the medical community valuable insight into the degree to which industry sponsored clinical trials are misrepresented.1234 Until this problem is corrected, evidence based medicine will remain an illusion.

The philosophy of critical rationalism, advanced by the philosopher Karl Popper, famously advocated for the integrity of science and its role in an open, democratic society. A science of real integrity would be one in which practitioners are careful not to cling to cherished hypotheses and take seriously the outcome of the most stringent experiments.5 This ideal is, however, threatened by corporations, in which financial interests trump the common good. Medicine is largely dominated by a small number of very large pharmaceutical companies that compete for market share, but are effectively united in their efforts to expanding that market. The short term stimulus to biomedical research because of privatisation has been celebrated by free market champions, but the unintended, long term consequences for medicine have been severe. Scientific progress is thwarted by the ownership of data and knowledge because industry suppresses negative trial results, fails to report adverse events, and does not share raw data with the academic research community. Patients die because of the adverse impact of commercial interests on the research agenda, universities, and regulators.

The pharmaceutical industry’s responsibility to its shareholders means that priority must be given to their hierarchical power structures, product loyalty, and public relations propaganda over scientific integrity. Although universities have always been elite institutions prone to influence through endowments, they have long laid claim to being guardians of truth and the moral conscience of society. But in the face of inadequate government funding, they have adopted a neo-liberal market approach, actively seeking pharmaceutical funding on commercial terms. As a result, university departments become instruments of industry: through company control of the research agenda and ghostwriting of medical journal articles and continuing medical education, academics become agents for the promotion of commercial products.6 When scandals involving industry-academe partnership are exposed in the mainstream media, trust in academic institutions is weakened and the vision of an open society is betrayed.

The corporate university also compromises the concept of academic leadership. Deans who reached their leadership positions by virtue of distinguished contributions to their disciplines have in places been replaced with fundraisers and academic managers, who are forced to demonstrate their profitability or show how they can attract corporate sponsors. In medicine, those who succeed in academia are likely to be key opinion leaders (KOLs in marketing parlance), whose careers can be advanced through the opportunities provided by industry. Potential KOLs are selected based on a complex array of profiling activities carried out by companies, for example, physicians are selected based on their influence on prescribing habits of other physicians.7 KOLs are sought out by industry for this influence and for the prestige that their university affiliation brings to the branding of the company’s products. As well paid members of pharmaceutical advisory boards and speakers’ bureaus, KOLs present results of industry trials at medical conferences and in continuing medical education. Instead of acting as independent, disinterested scientists and critically evaluating a drug’s performance, they become what marketing executives refer to as “product champions.”

Ironically, industry sponsored KOLs appear to enjoy many of the advantages of academic freedom, supported as they are by their universities, the industry, and journal editors for expressing their views, even when those views are incongruent with the real evidence. While universities fail to correct misrepresentations of the science from such collaborations, critics of industry face rejections from journals, legal threats, and the potential destruction of their careers.8 This uneven playing field is exactly what concerned Popper when he wrote about suppression and control of the means of science communication.9 The preservation of institutions designed to further scientific objectivity and impartiality (i.e., public laboratories, independent scientific periodicals and congresses) is entirely at the mercy of political and commercial power; vested interest will always override the rationality of evidence.10

Regulators receive funding from industry and use industry funded and performed trials to approve drugs, without in most cases seeing the raw data. What confidence do we have in a system in which drug companies are permitted to “mark their own homework” rather than having their products tested by independent experts as part of a public regulatory system? Unconcerned governments and captured regulators are unlikely to initiate necessary change to remove research from industry altogether and clean up publishing models that depend on reprint revenue, advertising, and sponsorship revenue.

Our proposals for reforms include: liberation of regulators from drug company funding; taxation imposed on pharmaceutical companies to allow public funding of independent trials; and, perhaps most importantly, anonymised individual patient level trial data posted, along with study protocols, on suitably accessible websites so that third parties, self-nominated or commissioned by health technology agencies, could rigorously evaluate the methodology and trial results. With the necessary changes to trial consent forms, participants could require trialists to make the data freely available. The open and transparent publication of data are in keeping with our moral obligation to trial participants—real people who have been involved in risky treatment and have a right to expect that the results of their participation will be used in keeping with principles of scientific rigor. Industry concerns about privacy and intellectual property rights should not hold sway.

Footnotes

  • Competing interests: McHenry and Jureidini are joint authors of The Illusion of Evidence-Based Medicine: Exposing the Crisis of Credibility in Clinical Research (Adelaide: Wakefield Press, 2020). Both authors have been remunerated by Los Angeles law firm, Baum, Hedlund, Aristei and Goldman for a fraction of the work they have done in analysing and critiquing GlaxoSmithKline’s paroxetine Study 329 and Forest Laboratories citalopram Study CIT-MD-18. They have no other competing interests to declare.

  • Provenance and peer review: Not commissioned, externally peer reviewed

References

  1. ↵
  2. ↵
  3. ↵
  4. ↵
  5. ↵
  6. ↵
  7. ↵
  8. ↵
  9. ↵
  10. ↵

View Abstract

_________________

**Comment**

Please also read “How Politics Corrupted Evidence-Based Medicine – and How to Fix it” by Dr. Robert Malone.

For more:

In short, science and public health is completely broken, and a powerful unelected ‘Cabal’ controls both scientific funding and health policy in America

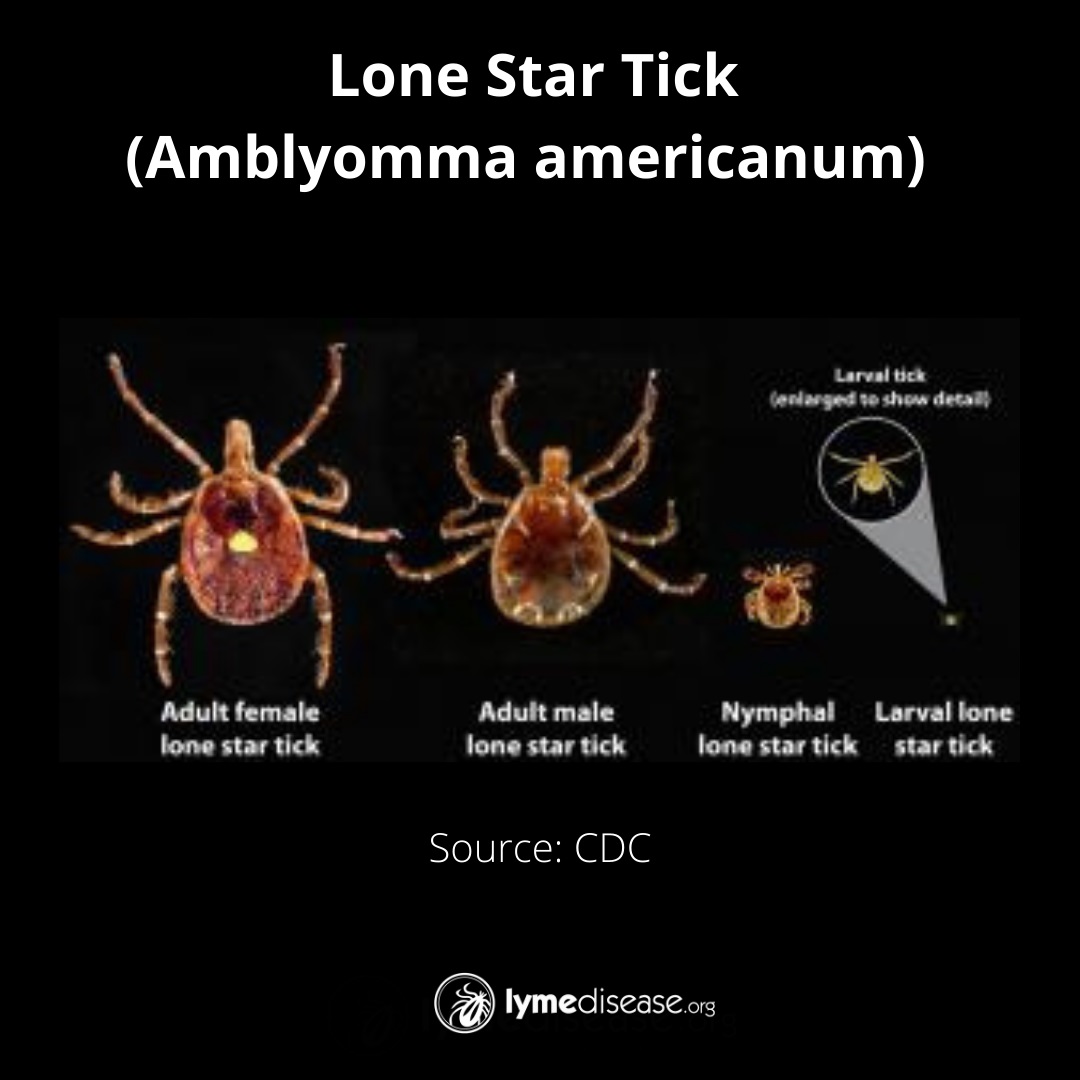
“Super-Fast” Lone Star Ticks Showing up in New Places

https://www.lymedisease.org/lyme-sci-super-fast-lone-star-ticks-are-showing-up-in-new-places/

LYME SCI: “Super-fast” lone star ticks are showing up in new places

March 30, 2022

By Lonnie Marcum

The lone star tick (Amblyomma americanum) has been rapidly expanding its range, from the Southern United States into the Northeast and Midwest.

This tick is a major vector of several viral, bacterial, and protozoan pathogens affecting humans, pets, livestock, birds and other wild animals in the United States. In some Midwestern states, it is commonly known as the “turkey tick” due to its association with wild turkeys. (Childs and Paddock, 2003)

Currently, the lone star tick is known to transmit human ehrlichiosis, tularemia, Heartland virus, Bourbon virus, Southern tick-associated rash illness (STARI) and rarely Rocky Mountain spotted fever—one of the deadliest tick-borne diseases in the US.

People bitten by a lone star tick may also develop alpha-gal syndrome—a severe allergy to meat and meat-related products.

A recent crowdsourced science project has documented the largest increase of the lone star tick in decades. Researchers documented new tick encounters in over 300 counties—including six new counties in western states—where these ticks had not been documented before.

TickSpotters program evaluates photos

In a study published in the Journal of Medical Entomology, researchers at the University of Rhode Island (URI) evaluated over 9,500 photos submitted between 2014-2019 to the TickSpotters surveillance program.

To document the changes, researchers first identified the ticks in the submitted photos, then logged the county each was reported from. They used this method to plot the geographic ranges of three medically important U.S. tick species: Amblyomma americanum, Ixodes scapularis and Ixodes pacificus. The last two are the vectors for Lyme disease.

More than 5,000 photographs of the lone star tick were received from over 1,000 counties across the US. Of those, 341 counties had no previous record of lone star ticks. The largest expansion of the lone star tick was seen in Illinois, Indiana, Kentucky, and Ohio.

In addition, the lone star tick was reported in several counties in the western US, a region not typically associated with these ticks. Notably, it was found in six new counties in California, four counties in Colorado and one new county each in Idaho, Oregon and Utah.

“The causative drivers of these upturns are complex, but have a lot to do with increased host availability, warming temperatures, and moisture availability,” researcher Heather L Kopsco, PhD, told Entomology Today,

Female lone star ticks are identifiable by a single silvery-white spot on the center of their back (scutum.) The male lone star tick is slightly smaller, with varied white streaks or spots around the margins of its body.

Finding Heartland virus in Georgia

Another recent study published in the CDC journal “Emerging Infectious Diseases” found lone star ticks infected by Heartland virus in Georgia. The article points out several major knowledge gaps and the complexity of diseases carried by the lone star tick. (Romer et al, 2022)

“Heartland is an emerging infectious disease that is not well understood,” says Emory University’s Gonzalo Vazquez-Prokopec PhD, senior author of the study.

Interestingly, the genetic analysis of the Heartland virus from Georgia shows that it is 2%-5% different from previous genetic sequences of the virus.

“These results suggest that the virus may be evolving very rapidly in different geographic locations, or that it may be circulating primarily in isolated areas and not dispersing quickly between those areas,” Vazquez-Prokopec says.

The Heartland virus wasn’t officially named until 2009. However, the CDC has since found evidence of it in wild animals in at least 13 states, including stored samples from deer dating back to 2001. (Clark et al, 2018)

Because the initial symptoms of these tick-borne viruses resemble the flu, and tests for it are not readily available, it is likely being undetected and underreported in humans.

Quick and aggressive

The lone star tick moves quickly and aggressively, says Thomas Mather, PhD, Director of the TickEncounter Resource Center and co-author of the URI study.

“It is super-fast. It can move from below your knees to the top of your head in a matter of seconds.” Mather says it is the tick most frequently found attached to humans in the South.

The greatest risk of being bitten by the adults exists in early spring through fall. Lone star ticks are found mostly in woodlands with dense undergrowth and around animal resting areas, where they will quest on tall grass and low hanging branches.

Nymphal ticks quest lower to the ground but also move fast. If you encounter a patch of larvae, you’ll find they may latch on by the hundreds. Tick Encounters recommends using sticky duct tape to remove these larvae as soon as possible.

Expanding range

The range of the lone star tick in North America has increased dramatically over the past 30 years. Large numbers have been recorded as far to the northeast as Maine, as far to the southeast as Florida, as far south as Mexico and as far west as Colorado. Recently, patchy encounters have also been noted in Canada and the West coast.

Diseases carried by lone star ticks

The following is a list of symptoms of diseases caused by the bite of the lone star tick per the CDC.

Alpha-gal Syndrome (AGS)

Reactions can include:

  • Rash
  • Hives
  • Nausea or vomiting
  • Heartburn or indigestion
  • Diarrhea
  • Cough, shortness of breath, or difficulty breathing
  • Drop in blood pressure
  • Swelling of the lips, throat, tongue, or eye lids
  • Dizziness or faintness
  • Severe stomach pain

Symptoms commonly appear 2-6 hours after eating meat or dairy products, or after exposure to products containing alpha-gal (for example, gelatin-coated medications). Personal products that use ingredients containing “hydrolyzed protein,” lanolin, glycerin, collagen, or tallow are particularly problematic.

AGS reactions can differ from person to person and range from mild to severe. Anaphylaxis (a potentially life-threatening allergic reaction involving multiple organ systems) may need urgent medical care.

People may not react after every alpha-gal exposure.

Seek immediate emergency care if you are having a severe allergic reaction.

Bourbon Virus

Scientists are still learning about possible symptoms caused by this virus.

People diagnosed with Bourbon virus disease had symptoms including:

  • fever
  • tiredness
  • rash
  • headache
  • other body aches
  • nausea, and

Patients with Bourbon virus will have low blood counts for cells that fight infection and help prevent bleeding.

There is no medicine to treat Bourbon virus disease. Doctors can only treat the symptoms. For example, some patients may need to be hospitalized and given intravenous fluids and treatment for pain and fever. Antibiotics don’t work against viruses.

Ehrlichiosis

Signs and symptoms of ehrlichiosis typically begin 1-2 weeks after the bite of an infected tick. Left untreated, ehrlichiosis can be fatal. Early treatment with doxycycline is highly effective.

Early signs and symptoms (the first 5 days of illness) are usually mild or moderate and may include:

  • Fever, chills
  • Severe headache
  • Muscle aches
  • Nausea, vomiting, diarrhea, loss of appetite
  • Confusion
  • Rash (more common in children)

About a third of people with ehrlichiosis report a rash, which can look like red splotches or pinpoint dots. This typically develops five days after the fever begins.

Early treatment can reduce your risk of developing severe illness, which can include:

  • Damage to the brain or nervous system (e.g. inflammation of the brain and surrounding tissue (called meningoencephalitis))
  • Respiratory failure
  • Uncontrolled bleeding
  • Organ failure
  • Death
Heartland Virus
  • Most people infected with Heartland virus experience fever, fatigue, decreased appetite, headache, nausea, diarrhea, and muscle or joint pain. Many require hospitalization.
  • Some people also have lower than normal counts of white blood cells (cells that help fight infections) and lower than normal counts of platelets (which help clot blood). Sometimes, liver enzymes are elevated.
  • It can take up to two weeks for symptoms to appear after an infected tick bite.
Rocky Mountain Spotted Fever

Early signs and symptoms are not specific to RMSF. However, the disease can rapidly progress to a life-threatening illness.

Signs and symptoms can include:

  • Fever
  • Headache
  • Rash
  • Nausea
  • Vomiting
  • Stomach pain
  • Muscle pain
  • Lack of appetite

While almost all patients with RMSF will develop a rash, it often does not appear early in illness, which can make RMSF difficult to diagnose. RMSF rash usually develops 2-4 days after fever begins. The appearance of the rash can vary widely. Some rashes look like red splotches and some look like pinpoint dots.

Some patients who survive severe RMSF may be left with permanent damage, including amputation of arms, legs, fingers, or toes (from damage to blood vessels in these areas); hearing loss; paralysis; or mental disability.

Southern tick-associated rash illness (STARI)

It is not known whether antibiotic treatment is necessary or beneficial for patients with STARI. Nevertheless, because STARI resembles early Lyme disease, physicians will often treat patients with oral antibiotics.

The rash of STARI is a red, expanding “bull’s-eye” lesion that develops around the site of a lone star tick bite. The rash usually appears within seven days of the tick bite and expands to a diameter of three inches or more. The rash should not be confused with much smaller areas of redness and discomfort that can occur commonly at the site of any tick bite.

Patients may also experience fatigue, headache, fever, and muscle pains. The saliva from lone star ticks can be irritating; redness and discomfort at a bite site does not necessarily indicate an infection.

Tularemia

The signs and symptoms of tularemia vary depending on how the bacteria enter the body. Illness ranges from mild to life-threatening. All forms are accompanied by fever, which can be as high as 104 °F.

“Ulceroglandular” is the most common form of tularemia and usually occurs following a tick or deer fly bite or after handing an infected animal. A skin ulcer appears at the site where the bacteria entered the body. The ulcer is accompanied by swelling lymph glands, usually in the armpit or groin.

LymeSci is written by Lonnie Marcum, a Licensed Physical Therapist and mother of a daughter with Lyme. She serves on a subcommittee of the federal Tick-Borne Disease Working Group. Follow her on Twitter: @LonnieRhea  Email her at: lmarcum@lymedisease.org.

References

Childs JE, Paddock CD. (2003) The ascendancy of Amblyomma americanum as a vector of pathogens affecting humans in the United States. Annu Rev Entomol. 48:307-37. doi: 10.1146/annurev.ento.48.091801.112728. Epub 2002 Jun 4. PMID: 12414740.

Clarke, L. L., Ruder, M. G., Mead, D. G., & Howerth, E. W. (2018). Heartland Virus Exposure in White-Tailed Deer in the Southeastern United States, 2001-2015. The American journal of tropical medicine and hygiene, 99(5), 1346–1349. https://doi.org/10.4269/ajtmh.18-0555

Guzmán-Cornejo C et al (2011) The Amblyomma (Acari: Ixodida: Ixodidae) of Mexico: identification keys, distribution and hosts. Zootaxa 2998:16–38

Kopsco HL, Duhaime RJ, Mather TN. (2021) Crowdsourced Tick Image-Informed Updates to U.S. County Records of Three Medically Important Tick Species. J Med Entomol.  11:tjab082. doi: 10.1093/jme/tjab082. Epub ahead of print. PMID: 33973636.

Monzón, J. D., Atkinson, E. G., Henn, B. M., & Benach, J. L. (2016). Population and Evolutionary Genomics of Amblyomma americanum, an Expanding Arthropod Disease Vector. Genome biology and evolution, 8(5), 1351–1360. https://doi.org/10.1093/gbe/evw080

Riemersma KK, Komar N. (2015) Heartland Virus Neutralizing Antibodies in Vertebrate Wildlife, United States, 2009-2014. Emerg Infect Dis. 21(10):1830-3. doi: 10.3201/eid2110.150380. PMID: 26401988; PMCID: PMC4593439.

Romer, Y., Adcock, K., Wei, Z., Mead, D. G., Kirstein, O., Bellman, S….Vazquez-Prokopec, G. M. (2022). Isolation of Heartland Virus from Lone Star Ticks, Georgia, USA, 2019. Emerging Infectious Diseases, 28(4), 786-792. https://doi.org/10.3201/eid2804.211540.

Springer YP, Eisen L, Beati L, James AM, Eisen RJ. (2014) Spatial distribution of counties in the continental United States with records of occurrence of Amblyomma americanum (Ixodida: Ixodidae). J Med Entomol. Mar;51(2):342-51. doi: 10.1603/me13115. PMID: 24724282; PMCID: PMC4623429.

Steinke J, Platts-Mills T, Commins, S. (2015) The alpha-gal story: lessons learned from connecting the dots. J Allergy Clin Immunol. 135(3): 589-96.

___________________

**Comment**

Great, informative article.  I disagree with the notion that the climate is causing tick movement and proliferation of disease – here’s why:

Ticks will be the last species on the planet besides the IRS.

University of Kentucky Study to Explore Why Lyme Disease Symptoms Persist For Some

http://uknow.uky.edu/research/uk-study-explore-why-lyme-disease-symptoms-persist-some

UK Study to Explore Why Lyme Disease Symptoms Persist for Some

LEXINGTON, Ky. (March 4, 2022) — Although most cases of Lyme disease can be cured with a two-to-four-week course of antibiotics, some patients still experience lingering, debilitating effects of the disease months after they finish treatment.

Researchers in the University of Kentucky’s College of Medicine are seeking to understand if the antibiotic regimen used to treat Lyme disease could also be contributing to Post-Treatment Lyme Disease Syndrome (PTLDS), which includes ongoing symptoms of pain, fatigue or difficulty thinking.

Antibiotics can cause imbalances to the gut microbiome, the trillions of microbes essential to health and immune system function. Known as dysbiosis, these disruptions are linked to various autoimmune and inflammatory diseases, as well as cardiovascular disease and depression.

The study, supported by the Global Lyme Alliance and co-led by Ilhem Messaoudi, Ph.D., and Brian Stevenson, Ph.D., in the Department of Microbiology, Immunology and Molecular Genetics, will be the first to assess the role of dysbiosis in the development of PTLDS.

Lyme disease is a tick-borne illness caused by the bacteria Borrelia burgdorferi. The Centers for Disease Control and Prevention estimates that 476,000 Americans are diagnosed with Lyme disease each year.

The research will provide new insights into the interaction between B. burgdorferi infection, antibiotics, and the gut microbiome that may lead to more effective ways to treat Lyme disease, says Messaoudi.

“Lyme disease can be just an acute episode, but for some people, it becomes a prolonged disease with a lot of complications and scientists don’t fully understand where these complications come from,” Messaoudi said. “This study may provide targets that could lead to the development of new antibiotic treatment plans that address the microbiome as well as the immune system.”

Messaoudi and Stevenson will be collaborating with researchers at the Oregon National Primate Research Center to carry out an in-depth analysis of host responses. The research will also establish an ideal animal model for future studies on the cognitive and physical effects of PTLDS.

The University of Kentucky is increasingly the first choice for students, faculty and staff to pursue their passions and their professional goals. In the last two years, Forbes has named UK among the best employers for diversity, and INSIGHT into Diversity recognized us as a Diversity Champion four years running. UK is ranked among the top 30 campuses in the nation for LGBTQ* inclusion and safety. UK has been judged a “Great College to Work for” three years in a row, and UK is among only 22 universities in the country on Forbes’ list of “America’s Best Employers.”  We are ranked among the top 10 percent of public institutions for research expenditures — a tangible symbol of our breadth and depth as a university focused on discovery that changes lives and communities. And our patients know and appreciate the fact that UK HealthCare has been named the state’s top hospital for five straight years. Accolades and honors are great. But they are more important for what they represent: the idea that creating a community of belonging and commitment to excellence is how we honor our mission to be not simply the University of Kentucky, but the University for Kentucky.

For more:

Fulminant Lyme Myocarditis Without Any Other Signs of Lyme Disease in 37 Year Old With Microscopic Polyangiitis – Case Report

https://pubmed.ncbi.nlm.nih.gov/35291336/

Fulminant Lyme myocarditis without any other signs of Lyme disease in a 37-year-old male patient with microscopic polyangiitis-a case report

Free PMC article

Abstract

Background: Lyme disease is a tick-borne multisystem infection. The most common cardiac manifestation is an acute presentation of Lyme carditis, which often manifests as conduction disorder and rarely as myocarditis.

Case summary: We report the case of a 37-year-old male with a history of microscopic polyangiitis (blood vessel inflammation or vasculitis) receiving immunosuppressive therapy. He was admitted for severe dyspnoea secondary to acute heart failure. Echocardiography and cardiac magnetic resonance imaging indicated a severely reduced left ventricular ejection fraction (LVEF) with global hypokinesia. Coronary heart disease was excluded, and endomyocardial biopsies (EMB) were performed. The left ventricular EMB revealed a rare case of fulminant Lyme carditis with evidence of typical lymphocytic myocarditis. Borrelia afzelii-DNA was detected without any relevant atrioventricular blockage or systemic signs of Lyme disease. The patient had no clinically apparent tick-borne infection or self-reported history of a tick bite. Immunological testing revealed a positive ELISA and Immunoblot for anti-Borrelia immunoglobulin G antibodies. After specific intravenous antibiotic therapy and optimized medical therapy for heart failure, the LVEF recovered, and the patient could be discharged in an improved condition. Repeat EMB a few months later revealed a dramatic regression of the cardiac inflammation and absence of Borrelia DNA in the myocardium.

Discussion: A severely reduced LVEF can be the primary manifestation of Lyme disease even without typical systemic findings and can have a favourable prognosis with antibiotic treatment. A thorough workup for Lyme carditis is required in patients with unexplained heart failure, particularly with EMB, especially in immunosuppressed patients.

For more:

Borrelia Miyamotoi Found in 3-5% of New England Blood Samples = Tens of Thousands Possibly Infected

https://www.futurity.org/borrelia-miyamotoi-new-england-ticks-2716322-2/

Another tick bacteria turns up in New England blood samples

Human blood samples from across New England show evidence of Borrelia miyamotoi, a relative of the bacteria that causes Lyme disease.

The findings add important new details to understanding the bacteria species, Borrelia miyamotoi, which was only recently found to infect humans. The tiny species is transmitted by the same deer ticks that carry the Lyme disease pathogen, and can cause meningoencephalitis and relapsing fevers.

“We thought that Borrelia miyamotoi, because it was so recently discovered, would have been more locally confined,” says Peter Krause, senior research scientist at the Yale School of Public Health and senior author of the study. “To our surprise, it was found at all our testing sites throughout New England.”

Krause and Durland Fish, professor emeritus of epidemiology (microbial diseases), were part of a team of researchers who first discovered Borrelia miyamotoi’s ability to infect humans in 2011. Graduate student researcher Demerise Johnston is first author of the new study in the journal Clinical Infectious Diseases.

By testing more than 1,100 blood samples gathered from states across New England in 2018, the team of researchers discovered that almost 3% of the study subjects showed evidence of an immune response (antibody) to Borrelia miyamotoi, with some collection sites demonstrating as much as 5%. These samples were so geographically dispersed in New England that the researchers were unable to determine whether the origin of the infection was southeastern New England, as is the case for Lyme disease and babesiosis, another tick-borne infection.

The proportion of samples containing Borrelia miyamotoi antibody was low compared to that of Lyme disease pathogen, which reached more than 15% in some areas. But Krause says the level of Borrelia miyamotoi antibodies found in the samples indicates that physicians should keep an eye out for the bacteria in patients who present with Lyme disease-like symptoms.

“We’re talking about the possibility of tens of thousands of New England residents becoming infected with Borrelia miyamotoi based on what we found,” he says. “I think it’s important for people to realize that this disease is out there.”

For the study, the researchers also looked into the prevalence of another microorganism, Babesia microti, in their samples. That species is the primary cause of human babesiosis, and it can be spread through ticks just like the other two. Their analysis suggested that around 10% of the samples showed evidence of antibodies against this pathogen. These infections can be transmitted at the same time and coinfection is possible.

“Still, Lyme predominates, but the gap is not as great as is assumed,” Krause says. “There’s more Babesia infections than people realize. Physicians working in areas where babesiosis occurs should be aware of the disease and test for it when patients have consistent symptoms.”

Borrelia miyamotoi disease is much less frequent than those for the microbial species that cause Lyme disease and babesiosis. Krause says there are dependable treatment strategies that can cure individuals who have Borrelia miyamotoi infection. Those strategies involve essentially the same antibiotic treatments that treat Lyme disease. He and his colleagues say in the study that tracking the geographic spread of the species could help health care workers be on alert for potential transmission through ticks and possibly through blood transfusions, although additional studies are needed to confirm that this could happen.

Coauthors are from the Laboratory of Emerging Pathogens at the US Food and Drug Administration and L2 Diagnostics in New Haven, Connecticut.

Source: Matt Kristofferson for Yale University