Archive for the ‘research’ Category

Military, Family Members, and Lyme: Being Shot At Not As Bad As Gaslighting, Abandonment, and Betrayal

https://danielcameronmd.com/are-military-family-members-at-risk-for-lyme-disease/

Are military family members at risk for Lyme disease?

It is often suggested that military service members are at an increased risk for contracting Lyme disease, given that they frequently work outdoors in tick-habitats, surrounded by tall grass, brush, weeds and leaf litter. But what about their family members? Are they safer?

A study by Schubert and Melanson, entitled “Prevalence of Lyme Disease Attributable to Military Service at the USMA, West Point NY: FY2016–2018,” looks at the exposure of military personnel and their families to the Ixodes scapularis (or black-legged) tick, the vector of Lyme disease. [1]

The authors examined cases of Lyme disease treated at a hospital on the West Point Military Reservation, in New York between 2016 and 2018. Out of 144 cases identified, 63 involved military personnel, but family members accounted for 81 cases.

The period prevalence of Lyme disease for military personnel was 292 encounters per 100,000 during a 3-year period. However, family members were at greater risk, with a period prevalence of 581 cases per 100,000.

These findings “show a difference in period prevalence between service members and family members,” writes Schubert, “with the family members being at higher risk to contract Lyme instead of service members, as is commonly suggested in the literature.”

The authors point out that further research is needed to determine if these findings were specific to West Point or are comparable across the military. Tick exposure, they write, may have been less at West Point than at other military locations.

“At West Point, the majority of active-duty military work indoor jobs during the academic months and spend limited time in a training field environment,” Schubert points out.

Interestingly, however, “the data presented here suggest that proper personal protective measures (Permethrin treated uniforms and tick check training) have a significant effect on Lyme disease period prevalence,” since military personnel who were better protected and trained were less likely to contract Lyme disease.

The authors did not discuss the outcomes for the 63 Lyme disease cases.

References:
  1. Schubert, S. L. and V. R. Melanson (2019). “Prevalence of Lyme Disease Attributable to Military Service at the USMA, West Point NY: FY2016-2018.” Mil Med.

_____________________

https://danielcameronmd.com/soldier-dismissed-failing-lyme-disease-treatment/

Soldier dismissed from active duty after failing Lyme disease treatment

soldier-lyme-disease-treatment

Welcome to another Inside Lyme Podcast with your host Dr. Daniel Cameron. In this episode, Dr. Cameron will be discussing the case of a 21-year-old soldier who was dismissed from active duty after failing treatment for multiple illnesses including Lyme disease.

The case was first described by Melanson and colleagues in a paper entitled “The Epistemic Fallacy: Unintended Consequences of Empirically Treating (Clinically Diagnosed) Chronic Lyme Disease in a Soldier.”1

“A 21-year-old, Division 1 student athlete patient presented with heart palpitations and frequent unprovoked adrenaline rushes,” wrote the authors. His symptoms were initially dismissed as stress.

Four months later, testing for Epstein-Barr virus was positive but serological testing for Lyme disease was negative. “He was diagnosed with EBV reactivation and prescribed rest and recovery,” the authors wrote.

The man graduated but remained on medical leave since his symptoms had not resolved.

He was presumed to suffer from persistent mononucleosis like symptoms and Traumatic brain injury (TBI) attributed to possible post-concussion syndrome related to sports injuries, the authors explained.

The patient was then treated with Hyperbaric Oxygen Therapy (HBOT). However, after two sessions, it was discontinued due to an increase in symptoms including heart palpitations, flank pain, myalgias, and neuropathy.

CLICK BELOW TO LISTEN TO PODCAST

Although repeat testing for Lyme disease was negative, the man was treated clinically for Lyme disease based on symptoms, possible tick exposure during military trainings and the lack of other definitive findings.

He received three courses of doxycycline. Further Lyme disease tests were inconclusive.

The patient was forced to stop treatment after it worsened his symptoms, causing an increase in joint pain, intermittent nerve pain, headache, fatigue, cognitive difficulties, anxiety, mild depression, and increased chest pain.

The patient then sought treatment with a functional medicine doctor. His workup focused on mycotoxicosis in part due to his living and training environments.

He had a homogeneous single nucleotide polymorphism in the MTHFR gene suggestive a low level of metabolic detoxification and an abnormal mycotoxin urine panel.   He was treated for 3 months with IV phosphatidylcholine (up to 10 amps), IV glutathione (1,200 mg), IV Leucoviron (10mg), and subcutaneous B12 (1000 micrograms). He had minor improvements in fatigue and stamina but stopped after 3 months due to cost. His follow-up urine mycotoxin urine panel was negative.

The man remained ill and “was unable to perform moderate-or-strenuous physical exercise or cognitive activity due to the following symptoms:

  • cognitive impairment affecting short-term memory and ability to focus
  • severe fatigue, and post exertion malaise
  • asthma and increasing allergic-type reactions with chemical and food sensitivities as well as histamine intolerance
  • progression to heat/ultraviolet induced urticaria

“Additionally, the patient struggled emotionally with anxiety, depression, environmental stimulation (such as bright and flashing lights and loud noises), and sensitivity to stress.

He was subsequently diagnosed with chronic fatigue syndrome/myalgic encephalomyelitis (CFS/ME) following resolved acute mycotoxicosis.

The young man was considered unfit for duty by the Army Medical Evaluation Board for the following reasons: “Lyme disease, mycotoxicosis, chronic fatigue syndrome, allergic rhinitis and vasomotor rhinitis.”

The authors did a great job of describing the severity of symptoms and poor function of a soldier despite evaluation and empiric treatments for CFS/ME, following resolved acute mycotoxicosis and Lyme disease. Unfortunately, the soldier was unfit for duty despite extensive treatment for a wide range of illnesses.

The following questions are addressed in this Podcast episode:

  1. Have you seen patients with this range of symptoms?
  2. What is HBOT?
  3. What is integrative medicine?
  4. What is empiric treatment?
  5. Was Lyme disease a consideration?
  6. What other illnesses were considered?
  7. Are their patients with Lyme disease that fail treatment?
  8. Are their patients with the other illnesses discussed failing treatment?

Read comments on this blog from FaceBook readers

Thanks for listening to another Inside Lyme Podcast. Please remember that the advice given is general and not intended as specific advice to any particular patient. If you require specific advice, please seek that advice from an experienced professional.

References:
  1. Melanson VR, Hering KA, Reilly JL, Frullaney JM, Barnhill JC. The Epistemic Fallacy: Unintended Consequences of Empirically Treating (Clinically Diagnosed) Chronic Lyme Disease in a Soldier. Med J (Ft Sam Houst Tex). Jan-Mar 2022;(Per 22-01/02/03):50-55.
Related Articles:

Lyme disease forces 24-year-old army officer out of military

Study explores the risk of tick bites among german military personnel

Military dependent child contracts Lyme disease abroad

____________________

https://www.lymedisease.org/tbdwg-feb28-malachowski/

Being shot at in combat not as bad as mistreatment for Lyme disease

Feb. 28, 2022

Col. Nicole Malachowski delivered the following public comment to the February 28, 2022, meeting of the federal Tick-borne Disease Working Group.

I’m Colonel Nicole Malachowski, United States Air Force, Retired.

Lyme disease & tick-borne illness pose a unique risk to military service members, their families, and our veterans. This cohort is high-risk, due to the unique exposures of global military service. This is a Military Readiness issue.

In 2017, after 21 years of honorable service as a fighter pilot, I was medically retired after being found “100% unfit for duty due to chronic systemic tick-borne illness.”

Since my retirement, I’ve served as a trained Air Force Wounded Warrior Program Mentor (no endorsement implied) to airmen facing medical discharge. Not a month goes by that I’m not working with someone dealing with Lyme disease.

Front line medical providers in the Department of Defense (DoD) and Veterans Administration (VA) are not properly trained to consider Lyme disease and global strains of Borrelia in their differential diagnosis.

We are medically retiring honorable service members that are undiagnosed and misdiagnosed.

Millions of dollars in training goes to waste

This is unacceptable. Our taxpayers have invested millions of dollars into the training of our military members, and in too many cases, the American public is not getting a proper return on their investment.

The CDC increased its Lyme disease case count to 476,000 annually. That number is low. Why? They choose not to include the medical records of the largest healthcare system in America: the DoD and the VA.

Even if they did, the case count would still be low because the DoD and VA rely heavily on serology and the 2-tier testing system meant for surveillance use only. Front line DoD and VA medical providers are untrained to, and uncomfortable with, making a clinical diagnosis.

It took me four years to get the VA disability system to recognize the very illness for which I was medically discharged. As part of this battle, they forced me to succumb to a psychological evaluation to ensure my chronic symptoms were not psychosomatic. The indignity of this insulting appointment was swept away by the psychiatrist’s findings, which concluded my chronic illness is, in fact, physical in nature.

Yet, she did diagnose me with “medically-induced PTSD.” She accurately pinpointed the damage done by years of struggle for diagnosis, access to care, treatment, disability benefits, and the appalling lack of support from both the DoD and VA.

Abandonment and betrayal

Think about it: I’ve been shot at in combat, but that is not what caused my PTSD.  It was caused by the unnecessary controversy surrounding Lyme disease, years of gaslighting, abandonment and betrayal by the DoD, an abysmal lack of education & awareness by front line clinicians, poor diagnostics, therapeutic standards that did not cure me, and a VA disability system that fails to understand chronic tick-borne illness.

Our service members, military families, and veterans deserve better. This requires a whole of government approach, one that the DoD and VA are uniquely suited to positively impact.

This is, indeed, a military readiness issue. You want to thank me for my service? Fix this problem. Thank you.

Col. Nicole Malachowski was the first female Thunderbird pilot. In addition to commanding a fighter squadron, she served as a White House Fellow and an advisor to First Lady Michelle Obama. She is now a professional speaker and fierce advocate for the cause of Lyme and other tick-borne diseases.

For more: 

Effectiveness of Antibiotics Reduced When Multiple Bugs Present

https://phys.org/news/2022-03-effectiveness-antibiotics-significantly-multiple-bugs.html

Effectiveness of antibiotics significantly reduced when multiple bugs present

March 19, 2022

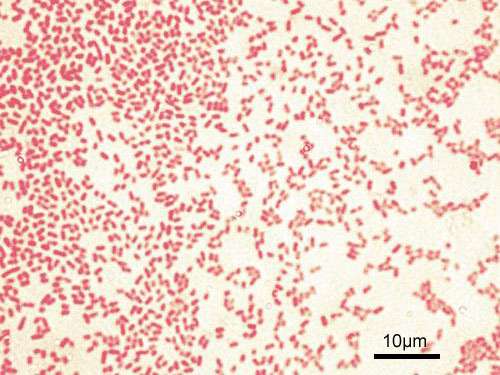
Gram-stained P. aeruginosa bacteria (pink-red rods) Credit: Wikipedia

A study has found that much higher doses of antibiotics are needed to eliminate a bacterial infection of the airways when other microbes are present. It helps explain why respiratory infections often persist in people with lung diseases such as cystic fibrosis despite treatment.

In the study, published today in The ISME Journal, researchers say that even a low level of one type of microbe in the airways can have a profound effect on the way other microbes respond to antibiotics.

The results highlight the need to consider the interaction between different species of microbe when treating infections with antibiotics—and to adjust dosage accordingly.

“People with often have co-infection with several pathogens, but the problem is we don’t take that into account in deciding how much of a particular antibiotic to treat them with. Our results might help explain why, in these people, the antibiotics just don’t work as well as they should,” said Thomas O’Brien, who carried out the research for his Ph.D. in the University of Cambridge’s Department of Biochemistry and is joint first author of the paper.

Chronic bacterial infections such as those in the human airways are very difficult to cure using antibiotics. Although these types of infection are often associated with a single pathogenic species, the infection site is frequently co-colonized by a number of other microbes, most of which are not usually pathogenic in their own right.

Treatment options usually revolve around targeting the pathogen, and take little account of the co-habiting species. However, these treatments often fail to resolve the infection. Until now scientists have had little insight into why this is.

To get their results the team developed a simplified model of the human airways, containing artificial sputum (‘phlegm’) designed to chemically resemble the real phlegm coughed up during an infection, packed with bacteria.

The model allowed them to grow a mixture of different microbes, including pathogens, in a stable way for weeks at a time. This is novel, because usually one pathogen will outgrow the others very quickly and spoil the experiment. It enabled the researchers to replicate and study infections with multiple species of microbe, called ‘poly-microbial infections’, in the laboratory.

The three microbes used in the experiment were the bacteria Pseudomonas aeruginosa and Staphylococcus aureus, and the fungus Candida albicans—a combination commonly present in the airways of people with cystic fibrosis.

The researchers treated this microbial mix with an antibiotic called colistin, which is very effective in killing Pseudomonas aeruginosa. But when the other pathogens were present alongside Pseudomonas aeruginosa, the antibiotic didn’t work.

“We were surprised to find that an antibiotic that we know should clear an infection of Pseudomonas effectively just didn’t work in our lab model when other bugs were present,” said Wendy Figueroa-Chavez in the University of Cambridge’s Department of Biochemistry, joint first author of the paper.

The same effect happened when the microbial mix was treated with fusidic acid—an antibiotic that specifically targets Staphylococcus aureus, and with fluconazole—an antibiotic that specifically targets Candida albicans.

The researchers found that significantly higher doses of each antibiotic were needed to kill bacteria when it was part of poly-microbial infection, compared to when no other pathogens were present.

“All three species-specific antibiotics were less effective against their target when three pathogens were present together,” said Martin Welch, Professor of Microbial Physiology and Metabolism in the University of Cambridge’s Department of Biochemistry and senior author of the paper.

At present antibiotics are usually only laboratory tested against the main pathogen they are designed to target, to determine the lowest effective dose. But when the same dose is used to treat infection in a person it often doesn’t work, and this study helps to explain why. The new model system will enable the effectiveness of potential new antibiotics to be tested against a mixture of microbe species together.

Poly-microbial infections are common in the airways of people with cystic fibrosis. Despite treatment with strong doses of antibiotics, these infections often persist long-term. Chronic infections of the airways in people with asthma and chronic obstructive pulmonary disorder (COPD) are also often poly-microbial.

By looking at the genetic code of the Pseudomonas bacteria in their lab-grown mix, the researchers were able to pinpoint specific mutations that give rise to this antibiotic resistance. The mutations were found to arise more frequently when other pathogens were also present.

Comparison with the genetic code of 800 samples of Pseudomonas from around the world revealed that these mutations have also occurred in human patients who had been infected with Pseudomonas and treated with colistin.

“The problem is that as soon as you use an antibiotic to treat a microbial , the microbe will start to evolve resistance to that antibiotic. That’s what has happened since colistin started to be used in the early 1990’s. This is another reminder of the vital need to find new antibiotics to treat human infections,” said Welch.

___________________

**Comment**

Hopefully it’s clear why I would post this cystic fibrosis research on a Lyme/MSIDS website.  Lyme/MSIDS is also often a polymicrobial illness involving numerous pathogens. Logic would then follow that this complex illness would also be impossible to eradicate using a singular antibiotic against multiple infections that not only require different medications individually but that synergistically would also necessitate higher doses for a longer period of time. 

This is known, appreciated, and utilized by Lyme literate doctors when treating patients, and Lyme/MSIDS patients, researchers, and doctors alike have been screaming bloody murder about this topic for decades.  But they are laughed at and ridiculed, and written off as tin-foil hat wearing nut-jobs.

Mainstream research and medicine barely even acknowledge coinfection, a fact that is seen not only in ticks but daily in humans living in the real world.  They also deny pleomorphism – or the ability of borrelia, and other pathogens to shape-shift into different forms.  Research has shown borrelia shape-shifts when threatened so it can survive.

The current simplistic view of Lyme/MSIDS is killing people, and the sooner it is recognized and addressed the better.

One would hope that research showing the very real complexities and failure of standard treatment on patients with multiple infections simultaneously would cause even the most entrenched to consider the same possibility with Lyme/MSIDS.

One can only continue to hope.

Case Study: Autopsy Results on Alzheimer’s Death Showed Chronic Brain Infection

https://web.archive.org/web/20210615055543id_/https://scivisionpub.com/pdfs/borrelia-invasion-of-brain-pyramidal-neurons-and-biofilm-borrelia-plaques-in-neuroborreliosis-dementia-with-alzheimers-phenotype-1564.pdf

Borrelia Invasion of Brain Pyramidal Neurons and Biofilm Borrelia Plaques in  Neuroborreliosis Dementia with Alzheimer’s Phenotype 

Alan B. MacDonald* 

Received 29 Janaury 2021; Accepted: 25 February 2021

ABSTRACT 

Dementia in Lyme borreliosis complex has been reported, mainly in post-mortem studies without available  antemortem evidence of active borrelia infection. Blanc in 2014 studied living patients with Lyme neuroborreliosis dementia and several dementia phenotype illnesses including an Alzheimer’s Phenotype. Herein we report an additional case study of a longitudinal evolution of European neuroborreliosis over eight years from tick bite to mild cognitive disease, to advanced dementia to death with a brain Alzheimer’s disease phenotype and concurrent borrelia deposits in brain Alzheimer’s disease sites at autopsy. 

Intrathecal borrelia specific antibodies were detected by commercial diagnostic laboratories (antemortem).  Molecular autopsy tissue imaging was completed with borrelia specific DNA probes and an immunomicroscopic  detection histopathology method. 

Results: Autopsy showed intact spirochetes, fragmented spirochetes, deposits of borrelia-specific proteins inside  plaque lesions and inside of neurons, and borrelia DNA deposits in plaque and neuronal sites. Pure Alzheimer’s  disease (without Lewy bodies) was a routine neuropathological finding. 

CSF evidence for a brain compartment immune response is established here. Intrathecal antibodies to infection  presented as oligoclonal total CSF IgG bands (n=twelve increase to n=13 bands) and separate borrelia IgG  western blot band analysis in cerebrospinal fluids (seven diagnostic borrelia CSF antibody bands). Blood western  blot disclosed triple borrelia species infection; burgdorferi European type (eighteen bands), garinii (twelve bands)  and afzelii (eighteen bands). Total borrelia IgG antibodies in blood during life were two hundred-fold higher  than normal range. Western blot of cerebrospinal fluid prior to death disclosed 7 protein bands which were not  represented in simultaneous blood western blot studies, further validating the intrathecal fingerprint of a separate  brain compartment immune response to neuroborreliosis infection. 

Conclusion: Borrelia protein antigenic stimulation of intrathecal borrelia antibodies was caused by resident  deposits of spirochetal protein deposits in plaques, in diseased neurons, and in neuropil brain sites, and in intact brain spirochetes. Deposits of borrelia proteins inside neurons and brain phagocytes and in neuropil sites (invasosomes) confirm remnants of chronic brain infection. 

For more:

Diagnosing Lyme Arthritis of the Hip in Children

https://danielcameronmd.com/diagnosing-lyme-arthritis-of-the-hip-in-children/

Diagnosing Lyme arthritis of the hip in children

lyme-arthritis-children

How can doctors distinguish a case of Lyme arthritis of the hip from transient arthritis or septic arthritis (SA) in children? A few findings from a recent review, published in the journal Cureus, may be helpful in making a correct diagnosis.

“The clinical presentation of Lyme arthritis (LA) of the hip can be similar to both acute bacterial septic arthritis (SA) and transient synovitis (TS),” explains Cruz and colleagues. ¹ “Differentiating between SA, LA, and TS of the hip can be challenging, even for the most discerning clinician.”

But, accurately diagnosing these conditions is important since treatment of each is distinct, states Cruz. So in an effort to identify any unique features, Cruz and his team performed a systematic review of all published studies involving pediatric patients with LA.

They identified 88 patients diagnosed with Lyme arthritis of the hip. The average age was 7.5 years. The authors compared these cases with those involving children with transient arthritis and septic arthritis. Transient arthritis causes hip pain and limping and occurs after a viral infection.

According to Cruz and colleagues, children with Lyme arthritis of the hip were more likely to bear weight. Still, one-third (33%) refused to bear weight but this is compared with more than 60% of the SA and TS patients who refused to do so.

Children with Lyme arthritis of the hip were less likely (23%) to have fever. Whereas more than half (53.8%) of the septic arthritis patients were febrile.

A review of laboratory data found neither the white blood count (WBC) nor the erythrocyte sedimentation rate (ESR) was a good marker for distinguishing Lyme arthritis of the hip from septic arthritis.

But, an ESR of at least 40 should prompt clinicians to obtain hip synovial fluid to evaluate for septic arthritis, Cruz says. Conversely, “an ESR less than 40 mm/hr could be worked up further with Lyme serology as LA or TS become more likely.”

A high synovial WBC of at least 65,000 cells/mm3 was proposed as a potential cutoff suggestive of bacterial septic arthritis. The synovial WBC was 47,533 – 64,242 cells/mm3 for Lyme arthritis. The synovial WBC was 105,432 – 260,214 cells/mm3 for septic arthritis.

Clinical judgment is still necessary when distinguishing these entities. And as Cruz suggests, “if significant hip irritability or other clinical signs of [septic arthritis] SA exist, then treatment for SA should be initiated.”

The authors did not discuss whether any of the children with transient arthritis might suffer from seronegative Lyme disease.

Related Articles:
References:
  1. Cruz AI, Jr., Anari JB, Ramirez JM, Sankar WN, Baldwin KD. Distinguishing Pediatric Lyme Arthritis of the Hip from Transient Synovitis and Acute Bacterial Septic Arthritis: A Systematic Review and Meta-analysis. Cureus. 2018;10(1):e2112.

For  more:

I’m not sure this study is helpful at all.  Also, it would be extremely unwise to put symptoms in a simplistic box.  Lyme/MSIDS has a way of creeping outside every body it’s put into.

Lone Star Tick Carrying Heartland Virus Found in Georgia: Researchers

https://www.theepochtimes.com/lone-star-tick-carrying-heartland-virus-found-in-georgia-researchers

Lone Star Tick Carrying Heartland Virus Found in Georgia: Researchers

By Katabella Roberts
March 17, 2022 U

Lone star ticks carrying a virus that could potentially prove fatal to humans have been discovered in Georgia, a new study reported Wednesday.

The Heartland virus is an emerging infectious disease that can cause symptoms such as fever, diarrhea, fatigue, muscle or joint pain, headache, nausea, and a loss of appetite, according to the Centers for Disease Control and Prevention (CDC).

Many individuals who have been diagnosed with the Heartland virus have had to be hospitalized due to their symptoms and some who had underlying health conditions have died.

There are currently no vaccines or medications that work to prevent or treat infection of the virus and antibiotics do not work. (See link for article)

__________________

SUMMARY:

  • 1 out of every 2,000 specimens contained Heartland virus and confirm active transmission
  • Study found here Emerging Infectious Diseases
  • Heartland virus was first discovered in two men in northwest Missouri in 2009. They were both hospitalized with high fevers, diarrhea, muscle pains, low counts of white blood cells and platelets, as well as other symptoms related to tick-borne diseases.
  • More than 50 cases have been reported in Arkansas, Georgia, Illinois, Indiana, Iowa, Kansas, Kentucky, Missouri, North Carolina, Oklahoma, and Tennessee as of Jan. 2021, however, everything reported by the CDC regarding tick-borne illness is notoriously low.
  • Retroactive analysis discovered that a 2015 death that was labeled as an unidentified illness was in fact Heartland Virus.

While the article states there aren’t any treatments for Heartland virus, that is soundly FALSE. Mainstream medicine unfortunately has bought and propagated this horrific lie. There are many anti-viral medications and supportive treatments as well as anti-microbials like blood ozone, high doses of oral or IV vitamin C, herbs, and others which work effectively for viruses.  All we have to do is look at the COVID debacle to quickly learn that those who deny viral treatments are either ignorant or have an agendaGo here for an excellent video on industry corruption and suppression of drugs that work. In fact, after my experience with the miraculous way ivermectin stopped COVID in its tracks (at every stage of the illness), I’m hoping research will be done on this drug as well as HCQ for tick-borne and mosquito-borne viruses like Heartland, Bourbon Virus, and even West Nile Virus.

Advice: the best and most effective way to deal tick-borne illness is to avoid it in the first place.  This means that you will need to preemptively plan your outdoor adventures by being prepared.  This addresses three prongs: your yard, your pets, and you.

All of this does not guarantee you will not be bitten by a tick but it will certainly help.  If you are bitten by a tick, immediately act on it.  The “Wait and See” approach has doomed thousands upon thousands to chronic/persistent symptoms that can affect your life in major ways.

Rather than give medical advice about recommended treatment, please see the International Lyme and Associated Diseases Society (ILADS – how to handle a tick bite):

“ILADS recommends that prophylaxis (preventive treatment) be discussed with all who have had a blacklegged tick bite. An appropriate course of antibiotics has been shown to prevent the onset of infection.

When the decision is made to use antibiotic prophylaxis, ILADS recommends 20 days of doxycycline (provided there are no contraindications).The decision to treat a blacklegged tick bite with antibiotics often depends on where in the country the bite occurred, whether there was evidence that the tick had begun feeding, and the age of the person who was bitten.  Based on the available evidence, and provided that it is safe to do so, ILADS recommends a 20-day course of doxycycline.

Keep in mind this advice ONLY covers Lyme disease, and ticks can spread 19 and counting other diseases – each necessitating different medications. So just because you take doxy prophylactically also doesn’t guarantee you won’t get symptoms caused by a different pathogen(s).  This is why it’s important for you to educate yourself on symptomology caused by other tick-borne infections, as well as work with a trained Lyme literate doctor who is also knowledgeable about this.

Seems nothing is a sure thing in Lyme-land, but being prepared is always the best choice and makes you a tougher target.

For more on the Lone Star tick:

For more on Heartland Virus: