Ethical Doctor Practicing Ethical Medicine Reports 0/2000 Hospitalization Rate in Patients Treated for COVID-19
Houston Methodist Tried to Defame Ethical Physician on Twitter and Revoked Her Patient Privileges Claiming She Spread “Misinformation”. She Hired a Lawyer and Methodist’s Plan Blew Up in Their Face.
Dr. Mary Talley Bowden, an Ethical Physician (ENT) who owns a private practice in Houston, Texas, was informed in mid-November by the press that her privileges to treat patients at Methodist Hospital had been revoked.
That same Ethical Physician at a press conference on Nov 17th revealed, using real world data:
Due to early and aggressive treatment, 0/2000 of her patients she treated for COVID-19 had to be hospitalized.
30% of her patients use Ivermectin.
Ivermectin is a safe, FDA-approved medicine.
None of her patients taking Ivermectin reported any side effects.
Methodist hospital was the first hospital in the country to mandate vaccines, and she reported to the press that, according to the reports she has read, they are using her as an “example”. She reported that an online group was participating in her defamation, with false online reviews of her practice, as well as calls to report her to the medical board.
As far as being an example, I say, yes, Dr. Mary Talley Bowden is an example of the new Ethical Physician that we need to spread throughout allopathic medicine in a new culture of Ethical Medicine.
The Good Doctor had some questions for Methodist:
Why do we not know how many breakthrough cases they have?
Why do we not know how many patients who have been “vaccinated” have had side effects?
Why do we not know a firm number of patients in the hospital who are “vaccinated”?
The Good Doctor said Methodist needs to share all the data.
Dr. Bowden also demanded
A return to protection of patient privacy
Protection for physicians who question the “vaccine”
Everyone’s right to bodily autonomy.
Talk about picking the wrong target: Due to the legacy press and neopress she has received, her practice is now booming. So it’s game on.
If you’re an ethical, unvaccinated primary care doctor who suddenly needs a new place to practice, Houston awaits your call.
Share this article with a displaced physician and help save lives in Houston, and also share it with physicians under fire for practicing Ethical Medicine. And share with doctors who might need to be saved from Unethical Medicine.
In case you missed it, Dr. Vliet, M.D. and Ali Shultz, J.D. just wrote a report which clearly delineates the real reason behind hospitals using the “Fauci Death Protocol”. In short, it’s MONEY. Lots of it.Excerpt:
Hospital payments include:
A “free” required PCR test in the Emergency Room or upon admission for every patient, with government-paid fee to hospital.
Added bonus payment for each positive COVID-19 diagnosis.
Another bonus for a COVID-19 admission to the hospital.
A 20 percent “boost” bonus payment from Medicare on the entire hospital bill for use of remdesivir instead of medicines such as Ivermectin.
Another and larger bonus payment to the hospital if a COVID-19 patient is mechanically ventilated.
More money to the hospital if cause of death is listed as COVID-19, even if patient did not die directly of COVID-19.
A COVID-19 diagnosis also provides extra payments to coroners.
CMS implemented “value-based” payment programs that track data such as how many workers at a healthcare facility receive a COVID-19 vaccine.Now we see why many hospitals implemented COVID-19 vaccine mandates. They are paid more.
Outside hospitals, physician MIPS quality metrics link doctors’ income to performance-based pay for treating patients with COVID-19 EUA drugs.Failure to report information to CMS can cost the physician 4% of reimbursement.
Because of obfuscation with medical coding and legal jargon, we cannot be certain of the actual amount each hospital receives per COVID-19 patient. But Attorney Thomas Renz and CMS whistleblowers have calculated a total payment of at least $100,000 per patient.
Please watch yet another powerful video of another severely ill, hospitalized patient who recovered after he was allowed ivermectin. Ivermectin works at every stage of the illness but it’s best when used early on. Unfortunately, despite these stories and the now 90 studies from 963 scientists in 27 countries showing statistically significant improvement in mortality, ventilation, ICU, hospitalization, recovery, cases, and viral clearance, the drug is still banned for COVID in hospitals and for COVID in general.
Florida doctor claims he’s treated 3,000 COVID-19 patients with human version of ivermectin
This news video may get censored, so view it quickly. The article can be found here.
In short, a Florida doctor has a target on his back and has already been suspended from one hospital and fined $500 for prescribing ivermectin for COVID. However, patients are speaking out and stating that within hours of taking it, their symptoms started to disappear.
An elderly man was suffering from non-Hodgkin’s lymphoma and just finished chemo and was one of the first patients to get the COVID shot. He got COVID months after the jab. His daughter advocated for him to receive ivermectin due to the fact she herself was successfully treated with it and that after only ONE dose she “felt so much better.” (This was my experience as well)
Not until day 6 and the patient’s transfer to the ICU did a doctor agree to try ivermectin. His daughter states he was “going downhill every day” until he was given ivermectin and there was improvement.
A retired nurse got COVID and decided against the COVID shots for personal reasons. When her oxygen became low she called the Florida doctor and he prescribed ivermectin. She states “Within two hours I was starting to breathe better.”
Congressman Neil Dunn, former Chief of Staff at the Gulf Coast Hospital wrote an Op-Ed noting several global studies that found ivermectin works for COVID. He states that those saying there’s no evidence for ivermectin are willfully ignorant of the true literature. He also states that the federal government refuses to follow the scientific evidence and take a comprehensive approach to fighting COVID.
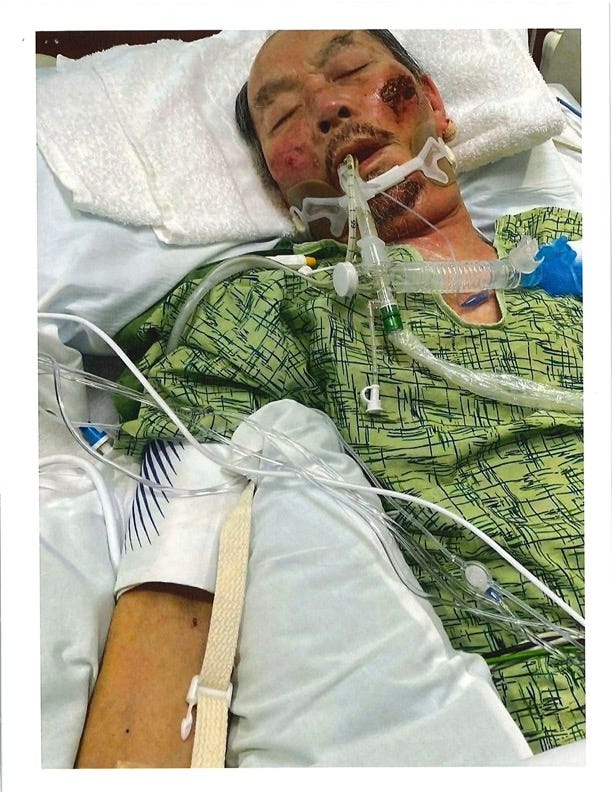
Mainstream media and the spin-doctors do not want you to know the end of the story. The elderly Sun Ng made a full recovery after a court ordered the hospital to give him ivermectin. A measly 5 days of treatment saved his life.
Sun Ng
This occurred after he had already spent 22 days on a ventilator. Imagine what would have happened if he was treated early.
Despite the court’s decision, the hospital refused to let the doctor into the hospital on the grounds that he was not “vaccinated” against COVID-19.
Following this, “An Emergency Report” was filed with the court first thing on Monday morning, Nov. 8, after brief argument from both parties, Judge Fullerton admonished Edward Hospital’s representatives and restated that he ordered them to let Dr. Bain in to the hospital on Friday to administer the life-saving drug.
12,700 doctors and scientists have signed the Rome Declaration and have endorsed ivermectin as a COVID treatment.
A Chicago-area judge saved a grandfather’s life with the single question that exposes hospitals blocking doctors from using a safe, FDA-approved drug: Why?
Sun Ng, a retired contractor from Hong Kong, traveled to Illinois to celebrate his only granddaughter’s first birthday. He got covid and was near death in a Chicago-area hospital. All other options were exhausted, but the hospital refused to give Mr. Ng a generic, FDA-approved drug with an extraordinary safety record that a doctor believed could safe his life.
Finally, a judge asked the right question about ivermectin.
“What’s the downside?”
Put another way: If a man is dying of covid in an ICU and all else has been tried, why not order a hospital to give a safe, last-ditch drug?
Edward Hospital, located near Chicago, offered three arguments as to why Sun Ng, seventy-one, should not be given ivermectin:
There could be side effects.
Ordering ivermectin would violate its policies.
Forcing the issue would be “extraordinary” judicial overreach.
On each argument, DuPage County Circuit Court Judge Paul Fullerton firmly disagreed. (See link for article)
___________________
Summary:
An internist ultimately administered a five-day course of 24 milligrams of ivermectin, from November 8 through November 12. The doctor stated: “Every day after ivermectin, there was accelerated and stable improvement,” said Dr. Bain, who administered the drug in two previous court cases after hospitals refused. “Three times we’ve shown something,” he told me. “There’s a signal of benefit for ventilator patients.”
Meanwhile Edward-Elmhurst Health, the hospital’s managing system has thwarted ivermectin, and even after Ng’s treatment benefitted him, the hospital system filed notice that it would appeal the order it had already carried out. (You call this CYA or “cover your a _ _ )
A nurse had the audacity to suggest the patient stop all care and die naturally. Wow.
With only a 10-20% chance of survival, the judge listed ivermectin’s possible side-effects from a government website: dizziness, pruitus, nausea/diarrhea, and stated that effects were so minimal that the patient’s condition outweighs risks by 100-fold.
A Kool-aid drinking doctor had the audacity to state that the risk of ivermectin gives no benefits.
This patient’s cases is the costliest with three decisions, four court appearances, and now an appeal that is certainly moot. The attorney battled another case in the same health system that involved Nurije Fype, age sixty-eight. Her case inspired Dr. Ng to file suit. Fype, who is probably only alive today due to judicious treatment with ivermectin, is now four and a half months downstream and doing great.
While Ng isn’t out of the woods, ivermectin has made a clear difference, even in his late stage of illness – Similarly to Lyme/MSIDS, imagine what would have happened if he was treated early…..
Top ICU Doctor Suspended After Suing Hospital for Banning Life-Saving COVID Treatments
In an exclusive interview with The Defender, Dr. Paul Marik said patients are dying “unnecessarily and unlawfully” because the hospital where he is director of the ICU prioritizes expensive drugs like Remdesivir while banning more effective and less costly treatments.
A top critical care physician who filed a lawsuit against Sentara Norfolk General Hospital over its ban on administering life-saving drugs to treat COVID patients, has had his hospital privileges suspended.
Dr. Paul Marik, chief of pulmonary and critical care medicine at Eastern Virginia Medical School and director of the ICU at Sentara Norfolk General Hospital, learned about the 14-day suspension when he arrived to work on Saturday and found a letter on his desk.
The letter was dated Nov. 18 — the same day Marik appeared before a judge in Norfolk Circuit Court requesting a temporary injunction to lift the ban, Marik’s attorney said.
Judge David Lannetti did not grant the temporary injunction, but did determine Marik had standing to bring his lawsuit, allowing the case to move forward which will give Marik the opportunity to “establish his right to administer life-saving treatments that patients have been prohibited access to by Sentara,” the Front Line COVID-19 Critical Care Alliance (FLCCC) said in a statement.
Sentara’s attorneys didn’t tell Marik about the suspension during Thursday’s hearing, nor did they mention it to the judge, said Marik’s attorney, Fred Taylor, a partner at the Virginia law firm Bush & Taylor.
In a Nov. 22 letter to the judge, Marik’s attorney accused Sentara of making a material misrepresentation during the hearing by failing to disclose the letter and telling the court the hospital would not retaliate against Marik for filing the lawsuit.
“Evidently Sentara chose, for reasons of its own, not to disclose this suspension either to the court or the plaintiff during the hearing,” Marik’s attorney told the judge.
In his letter, Taylor told the judge:
“The letter [from Sentara to Marik] gives no explanation whatsoever for the ‘coincidence’ of Sentara’s choosing to suspend Dr. Marik at this particular moment, leaving only one realistic conclusion. Sentara has engaged in a blatant act of retaliation against Dr. Marik for filing this suit and for exposing to the public Sentara’s unlawful unjustified denial of safe, potentially life-saving medicines to its COVID patients in violation of Virginia statutory law and public policy.”
In Sentara’s letter to Marik, hospital officials summoned Marik to a proceeding scheduled for Dec. 2 during which, the hospital said, “no lawyer representing Dr. Marik will be permitted and no recording/video or transcript … will be made.”
Sentara said its suspension of Marik was based in part on an allegation that he informed COVID patients that his “hands were tied” and there was nothing more he could do for them.
Taylor’s letter to the judge stated:
“At the just-concluded hearing on November 18, 2021, Sentara expressly represented to this Court that it would not discipline Dr. Marik in any way for informing his COVID patients that Sentara was preventing him from giving them alternative treatments that are, in his medical judgment (and based on unrefuted evidence) safe, and potentially life-saving and medically appropriate for them.
“Yet, Sentara has now done exactly that. Indeed it had apparently already done exactly that when it was representing to the Court that it would not do so. International or not, this was a materially false representation made to the court, and Plaintiff respectfully requests that Sentara be held to account for it.”
During the Nov. 18 hearing, Sentara’s attorney, Jason Davis, raised the issue of whether Marik has standing in the case. To have standing in a lawsuit, Marik needed to show he had a stake in its outcome or suffered an injury.
Sentara said Marik did not have standing to bring his case because he hadn’t been harmed.
“Obviously, patients who are dying in the ICU can’t come to court,” Marik told The Defender. “Sentara hospital lied continuously and incessantly but at this type of hearing, I was not in a position where I could challenge the falsities.”
Taylor accused Sentara of attempting to deprive Marik of standing through a “retaliatory, pretextual suspension that Sentara kept secret from the Court, perhaps hoping Dr. Marik would respond to Sentara by offering to drop his suit if Sentara would withdraw its suspension.”
In his letter to the judge, Marik’s legal team called for a supplemental hearing to redress the new facts previously hidden from the court by Sentara.
Sentara ban on certain COVID therapies violates U.S., Virginia medical laws, lawsuit alleges
Marik filed his lawsuit against Sentara Healthcare on Nov. 9, arguing the organization is endangering the lives of its COVID patients by preventing him from using his treatment protocol, which he says has reduced mortality rates in the ICU from approximately between 40% and 60% to less than 20%.
The lawsuit alleges Sentara’s ban on the use of certain therapies against COVID violates U.S. and Virginia medical laws and the concept of informed consent — whereby “patients have the right to receive information and ask questions about recommended treatments so that they can make well-considered decisions about care.”
Marik called Sentera’s ban on administering certain medicines for COVID patients “unprecedented” and “cruel” during his Nov. 18 testimony requesting a preliminary injunction to lift the ban.
In his motion, Marik said patients are dying “unnecessarily and unlawfully” because Sentara Healthcare is “preventing terminally ill COVID patients from exercising their right to choose and to receive safe, potentially life-saving treatment determined to be appropriate for them by their attending physician.”
In an interview with The Defender, Marik said the hospital is prohibiting the use of a COVID protocol called “Math +.” The protocol includes treating COVID patients with many drugs approved by the U.S. Food and Drug Administration (FDA) which has determined the drugs are safe and effective.
Instead, according to the lawsuit, Sentara recommends doctors use “toxic drugs” like Remdesivir — an expensive medication associated with severe side effects — because the hospital receives a bonus each time doctors prescribe it.
“This case is about doctors having the ability to honor their Hippocratic Oath, to follow evidence-based medicine, and to treat our patients the best we know how. Corporations and faceless bureaucrats should not be allowed to interfere with doctor-patient decisions, especially when it can result in harm or death.”
“Our COVID-19 protocol is based on the best scientific data available, yet Sentara claimed the medications I used were toxic and harmful, which is an absolute lie,” Marik told The Defender. “It is so outrageous.”
Marik explained:
“What happened was I was using MATH+ and I was using these medications, which I think are effective. All drugs we use are FDA- approved and very safe and they’ve been proven to be very effective for COVID, but I was banned from using them because they were dangerous, toxic and there was supposedly no data to support their use. It’s a big lie.
“What they [the hospital] want me to use is Remdesivir. We know Remdesivir increases death by 3%, increases the risk of hospital stay and increases the risk of kidney and liver failure. It does not improve patient outcomes. It is toxic. But the hospital gets a bonus if Remdesivir is prescribed. They profit from the expensive drug but not the cheap drug that people can afford.”
Marik, a highly published physician with 35 years of experience, said Sentara also tried to criticize his character, even though they appointed him as the director of ICU.
Marik said he could no longer stand by while patients died unnecessarily without proper treatment, so he had no choice but to file a lawsuit allowing him and his colleagues to administer a combination of FDA-approved drugs and other therapies that have saved thousands of critically ill COVID patients in the last 18 months.
Until September, doctors had been allowed to use ivermectin and the other medicines — ascorbic acid (Vitamin C) IV, bicalutamide, dutasteride, finasteride and fluvoxamine — to treat COVID patients.
But after the FDA, Centers for Disease Control and Prevention (CDC) and National Institutes of Health (NIH) warned against using ivermectin and other medicines for COVID patients, Sentara officials created new guidelines ordering doctors not to use the drugs.
Marik argued Sentara’s COVID Comprehensive Treatment Guidelines are “preventing terminally ill COVID patients from exercising their right to choose and receive safe, potentially life-saving treatment.”
Math+ protocol used around the world to safely treat COVID
According to an FLCCC press release, the MATH+ protocol, used by Marik and physicians around the world to treat COVID, is saving lives. However, since the prohibition went into place, there has seen a sharp rise in inpatient mortality.
Marik said he and his colleagues started using the Math+ to treat COVID in March 2020, because the national and international bodies provided no guidance. “So we put together guidelines and started using the protocol on March 24, and it has evolved over time as science has evolved,” he said.
The MATH+ protocol, designed for hospitalized patients, counters the body’s overwhelming inflammatory response to the SARS-CoV-2 virus.
The protocol is based on numerous medical journal publications and decades of research — and is founded upon the belief that hyper-inflammation, not the virus itself, damages the lungs and other organs and leads to death.
The MATH+ protocol is well-tolerated with no reports of adverse medical events, FLCCC said in a press release.
According to Dr. Joseph Varon, a renowned critical care specialist recently recognized by the United Nations for his life-saving work, the MATH+ COVID treatment protocol has achieved at least a 50% reduction in deaths from the virus in the hospitals where he serves as chief of staff.
“We take an oath as doctors to do no harm,” said Dr. Pierre Kory, president and chief medical officer of FLCCC. “I can’t think of a way of doing more harm to a patient than to not administer a treatment that you know can help them. No doctor should be forced to watch their patient die knowing that more could have been done to save them, and that is exactly what Sentara is doing.”
Medications are safe and FDA-approved, but hospital wants to use ‘toxic’ drugs
Marik said until Oct. 5, he was able to use most of the medications on the MATH+ protocol except for ivermectin, which was banned in May or June.
“They’re turning this into an ivermectin thing and it’s a very safe drug — more people have died from aspirin or Tylenol,” Marik said. “It is one of the safest drugs on the planet and the data is irrefutable, but somehow with COVID it has become a toxic medication.”
Marik explained:
“What do you have to lose when a patient is dying? When a patient is dying we do everything we can to save their lives and this system and many others are prohibiting them from getting every possible medication they can. That’s how we practice medicine, we do what we can to save the person.”
Marik said it is important for people to understand that 40% of drugs in the ICU are used off-label. “That’s the standard of care,” Marik said. “Pre-COVID, the FDA encouraged use of off-label drugs and you didn’t need informed consent to use them.”
Marik said 30% of drugs prescribed in the hospital settings are used off-label and 90% of people are discharged with prescriptions for drugs being used off-label.
For example, Marik said aspirin is recommended for atrial fibrillation — an irregular heartbeat — but that’s an off-label use. With MATH+, Marik said he can talk to families to see if they want to do it, but he can’t prescribe it. Their only option is to take a toxic therapy or transfer to another hospital potentially hundreds of miles away to utilize an alternative protocol.
Marik said:
“I try to emphasize these patients are dying. That’s why they’re there. It’s an absurd proposition to propose that I get consent from the family — or tell the families they have alternatives, but I can’t use them here, and then I have to transfer them to another hospital, which is very time-dependent.
“The longer I wait, the worse the outcome and it’s a major undertaking. To transfer an ICU patient hundreds of miles away to another hospital is impracticable.”
Marik said the hospital thinks they can do whatever they want because they control the media and they control the press, and he was put in a position where we had no option but to bring the suit.
Sentara pressured scientific journal to retract paper on COVID treatments co-authored by Marik
According to MedPage Today, the same day Marik filed his lawsuit, the Journal of Intensive Care Medicine (JICM) retracted an article, co-authored by Marik, on the MATH+ protocol, which includes the use of ivermectin.
Marik said the hospital pressured the journal to retract the article because it supported the use of alternative protocols, and showed a reduction in ICU mortality.
The retraction notice cited a communication it received from Sentara Norfolk General Hospital, “raising concerns about the accuracy of COVID-19 hospital mortality data reported in the article pertaining to Sentara.”
“Sentara Healthcare felt obligated to reach out to JICM with our concerns about Sentara Norfolk General Hospital data that the authors used to make conclusions, and provide accurate data to the journal. After a thorough review by JICM’s editorial board, the article was retracted. The journal followed their retraction guidelines and procedures.”
Taylor told MedPage Today in an email, the lawsuit is not about a journal article.
“This case is about whether a hospital administration can legally prohibit critically ill COVID patients from receiving information — and treatment, if they so decide it is medically appropriate for them — about safe, FDA-approved, and potentially life-saving medicines as determined by their attending physician,” Taylor said.
A Sentara spokesperson said in a statement to MedPage Today:
“Sentara generates treatment guidelines by engaging multi-disciplinary groups of clinicians to review literature, care standards and provide expert advice. In most situations, physicians are able to deviate from guidelines to individualize care for patients. However, in some scenarios, treatments that may potentially harm patients or that are widely considered to be outside the standard of care may be limited.”
The spokesperson said the CDC, NIH and FDA “currently do not recommend the use of ivermectin as a treatment for COVID-19 due to a lack of evidence regarding its safety and efficacy.”
Marik said when he and his colleagues published their paper on MATH+, they published statistics from Sentara.
“The hospital has their own protocol and they weren’t happy the director of the ICU was using his protocol and not their protocol,” Marik said. “It was a review paper and in it we quoted mortality statistics from Sentara. The chief of the hospital gave me the data on the mortality statistics, and we had approval from the Institutional Review Board to collect data and publish it.”
After it was published, Marik said they accused them of providing false and misleading data.
“The data is accurate but obviously, with time there are some additional patients that are going to die, and that’s inevitable with any paper,” Marik said. “On follow-up, mortality went from 6.6% to 10%. They complained to the medical school, and the medical school agreed with me.”
Marik said he updated the journal article to include a note, but Sentara pressured the journal to retract the article, claiming the data was false, and then used the fact the journal article was retracted against him.
Marik said he did not bring this lawsuit because he has something to gain, it’s because he has a responsibility to his patients and physicians across the country and the world.
“I think what they need to know is that the hospital is interfering with the physician and patient relationship. The physician decides what is in the best interests of the patient, and what they’re doing is unprecedented,” Marik said. “The hospital is telling me how to treat my patients, and it goes against basic Hippocraticic principles.”
Marik said he refuses to watch another patient die from COVID knowing he was not allowed to give them proven treatments that could have saved their life.
“This case is a test case that will have implications for physicians and patients across the country,” he said.
**UPDATE 2/1/24** In an effort to be balanced, please read this 48 page exposé on David Martin which shows he has served as an advisor to central banks, global economic forums, national governments, and the World Bank, and has connections to the WEF serving its interests through numerous companies he works with.
“The mark of an educated mind is to be able to entertain a thought without accepting it.” ~ Aristotle.
Dr. David Martin names those who played major roles in the greatest conspiracy against humankind in this eye-opening video with proof coming right out of the perpetrator’s mouths.
Article Excerpts: (Please see link for entire article)
David has put the names and faces of all of the major players in the theater of the COVID War onto one slide, which he says is important, because:
“we energize the forces of darkness when we anonymize them and when we see their faces on a screen, we realize that they’re merely individuals that have lost the social contract with humanity.”
“And what makes these individuals interesting is that when you look at them, you find out something very important. Almost none of them have sought public visibility. Isn’t that funny? Which makes me pick on one of them. The guy I have here, at the bottom corner. And I have to give him credit. He has done so much to stay out of sight.
“I’ve got 12 minutes left. I’ve got to spend a couple of minutes on the guy who’s paid every search engine optimization to keep his name out of search engines and I’m doing it so that is costs him sh!tloads to keep all of you silent.
DUSTIN MOSKOVITZ: EDITING THE HUMAN GENOME
“So let’s get really clear on Dustin Moskovitz. Shall we, Dustin Moskovitz?…You little piece of sh!t! Let’s talk about him for a minute. The Co-Founder of Facebook that you’ve never heard of…also the guy who founded Open Philanthropy, who was the actual check-writer for Event201. You were told that it was the World Economic Forum. You were told it was the Bill and Melinda Gates Foundation. You were told it was Johns Hopkins University. But the actual check that cleared for the program was signed by none other than Dustin Moskovitz…
“Now, I’m picking on him for a good reason. He’s a felon, he’s a criminal. He is one of the most sociopathic, psychopathic, crazy people walking the planet and he’s paid to keep his name in private. So guess what? Don’t let him! The reason why I want to give you this slide is because I want every one of them named. I want them all publicly named.
“Because it’s time that we start going through the reality of saying, ‘We the People are not going to let mass-murderers get away anonymously mass-murdering people. We are not going to allow that to happen! Not on our watch! And that’s why you have this slide…
“But let’s go back to Dustin. Isn’t it interesting that Dustin conveniently decided to shroud this entire public health crisis in a self-serving, self-interested investment objective? He owns Sherlock biosciences. Sherlock Biosciences happens to be the company that owns the CRISPR technology that is the joint venture between the United States and China on gene editing the human genome…
“Dustin Moskovitz knew that if he actually tried to take this technology into the public, nobody would be willing to do it, particularly, given the fact that it’s a JV [joint venture] between him and the government of China. That’s the reason why we’d have a problem with it. Because it feels like eugenics. You know why it feels like eugenics? Because it is eugenics, that’s why it feels like it! That’s why it feels like Cold Spring Harbor Labs…
“The only way we could get gene editing technology approved was with an Emergency Use Authorization. Not surprisingly, once everybody was distracted on vaccines and everybody was distracted on RTPCR and everybody was distracted on everything else, Sherlock Biosciences slipped their Emergency Use Authorization application into the FDA – and got it. In other words, using the cover of COVID, which all of us are pretending to talk about, the editing of the human genome was approved and not one of us said a thing.
“Now, if you were going to edit the human genome, do you think you’d need a good cover story to actually hide what you’re really doing? You’d probably find the guy who has the biggest financial interest in doing it and make sure, that while everyone is looking over at coronavirus and COVID and trying to figure out these Lab Leak Hypothesis – there’s no Lab Leak Hypothesis, because there’s no lab leak!
“So stop taking about lab leaks! there is no lab leak. This is the willful weaponization of a spike protein, that’s what it is. It’s an act of war, it’s not a leak. We need to start calling it what it is. It’s an act of war. It’s an act of war against humanity.
“But when we talk about the names of people, we humanize the sociopathic behavior. We humanize the fact that there are individuals and organizations that are willfully murdering the humanity that we know and love and we cannot let that happen on our watch. It is incumbent on all us to get those words out.”
Watch the full presentation in the link above.
THE COVID CONSPIRING STATES
“The real control is that,” (points to the slide), “what I call the ‘Atlantic Coalition of Doom.’ The Atlantic Coalition of Doom: BlackRock, AXA, the International Monetary Fund, HSBC, ICBC and you guessed it, United Healthcare…
“United Healthcare is a corrupt organization. It is a corrupt organization. It must be called what it is. It is actually the most manipulative corporate structures known to humanity, because what it does is it matches life insurance and insurance products with the delivery of healthcare, so they can so what? Manage your health? Oh-ho-ho no! Bet against the timing of your death.
“That’s the internal arbitrage. It is the wet dream of the Lloyd’s of London syndicate. They would have loved to have had this opportunity. But guess what? They didn’t. United Healthcare did. They put two things together, which means they get to manage your life so they can time your death, so they can profit on both.”
Our group has been using the PLUS Cardiac Test (GD Biosciences, Inc, Irvine, CA) a clinically validated measurement of multiple protein biomarkers which generates a score predicting the 5 yr risk (percentage chance) of a new Acute Coronary Syndrome (ACS). The score is based on changes from the norm of multiple protein biomarkers including IL-16, a proinflammatory cytokine, soluble Fas, an inducer of apoptosis, and Hepatocyte Growth Factor (HGF)which serves as a marker for chemotaxis of T-cells into epithelium and cardiac tissue, among other markers. Elevation above the norm increases the PULS score, while decreases below the norm lowers the PULS score. The score has been measured every 3-6 months in our patient population for 8 years. Recently, with the advent of the mRNA COVID 19 vaccines (vac) by Moderna and Pfizer, dramatic changes in the PULS score became apparent in most patients. This report summarizes those results. A total of 566 pts, aged 28 to 97, M:F ratio 1:1 seen in a preventive cardiology practice had a new PULS test drawn from 2 to 10 weeks following the 2nd COVID shot and was compared to the previous PULS score drawn 3 to 5 months previously pre- shot.
Baseline IL-16 increased from 35=/-20 above the norm to 82 =/- 75 above the norm post-vac
sFas increased from 22+/- 15 above the norm to 46=/-24 above the norm post-vac
HGF increased from 42+/-12 above the norm to 86+/-31 above the norm post-vac
These changes resulted in an increase of the PULS score from 11% 5 yr ACS risk to 25% 5 yr ACS risk. At the time of this report, these changes persist for at least 2.5 months post second dose of vac. We conclude that the mRNA vacs dramatically increase inflammation on the endothelium and T cell infiltration of cardiac muscle and may account for the observations of increased thrombosis, cardiomyopathy, and other vascular events following vaccination.
Here is the video and Dr. Vernon Coleman’s comments:
It’s the 22nd November 2021 and this is the moment when the jabbing has to stop.
A couple of hours ago Darren Smith, the editor of the excellent The Light Paper, sent me a paper from the medical journal Circulation which proves that the covid-19 jabbing experiment has to stop today. I believe that any doctor or nurse who gives one of the mRNA covid jabs after today will in due course be struck off the appropriate register and arrested.
The journal Circulation is a well-respected publication. It’s 71-years-old, its articles are peer reviewed and in one survey it was rated the world’s no 1 journal in the cardiac and cardiovascular system category.
I’m going to quote the final sentence of the abstract which appears at the beginning of the article. This is all I, you – or anyone else – needs to know.
`We conclude that the mRNA vacs dramatically increase inflammation on the endothelium and T cell infiltration of cardiac muscle and may account for the observations of increased thrombosis, cardiomyopathy and other vascular events following vaccination.’
That’s it. That’s the death bell for the covid-19 mRNA jabs.
The endothelium is a layer of cells lining blood vessels and lymphatic vessels. T cells are a type of white cell.
We always knew these jabs were experimental. My video in December 2020, just under a year ago, warned about these specific risks. I read out a list of possible adverse events published officially by the American Government.
But now we have the proof of the link.
The mRNA jab is, remember, known not to stop people catching covid. And it is known not to stop people spreading it. I don’t believe anyone disputes these facts.
And yet vast numbers of deaths and serious injuries have occurred among people who have been jabbed. Look at the item entitled ‘Updated: how many are the vaccines killing?’ on my websites.
Now we have the evidence to stop the jabbing programmes.
In the study quoted in Circulation, a total of 566 patients aged 28 to 97 were tested. They were equally divided among men and women.
‘At the time of this report,’ says the author, ‘these changes persist for at least 2.5 months post second dose of vaccine.’
At the very least, the use of these jabs must stop now. Immediately, until more long-term tests are done.
If there were any journalists left in the mainstream media, this news would be lead item on all TV and radio programmes and be on the front pages of all newspapers.
Thank heavens for free speech platforms such as BNT which enables me to bring you this news.
I’ve said for a year that this jab was an experiment – certain to kill and injure.
We’ve always known that to experiment on people without their full consent and understanding – after disclosing all the risks and potential side effects – is a crime.
Now the evidence exists that must stop this experiment.
If the covid jab experiment continues after today then we know for absolute sure that this is not a medical treatment, it is a cull.
Please share this video immediately with everyone you know.