Archive for the ‘Activism’ Category

Lyme: A Trigger For Hashimoto’s

https://thyroidpharmacist.com/articles/infections-as-hidden-triggers-for-hashimotos/

You can also download a free Thyroid Diet Guide, 10 Thyroid friendly recipes, and the Nutrient Depletions and Digestion chapter for free by going to www.thyroidpharmacist.com/gift. You will also receive occasional updates about new research, resources, giveaways and helpful information.

Medpage & AP News: Can’t Figure Out Why Africa Doesn’t Have COVID

**UPDATE May, 2022**

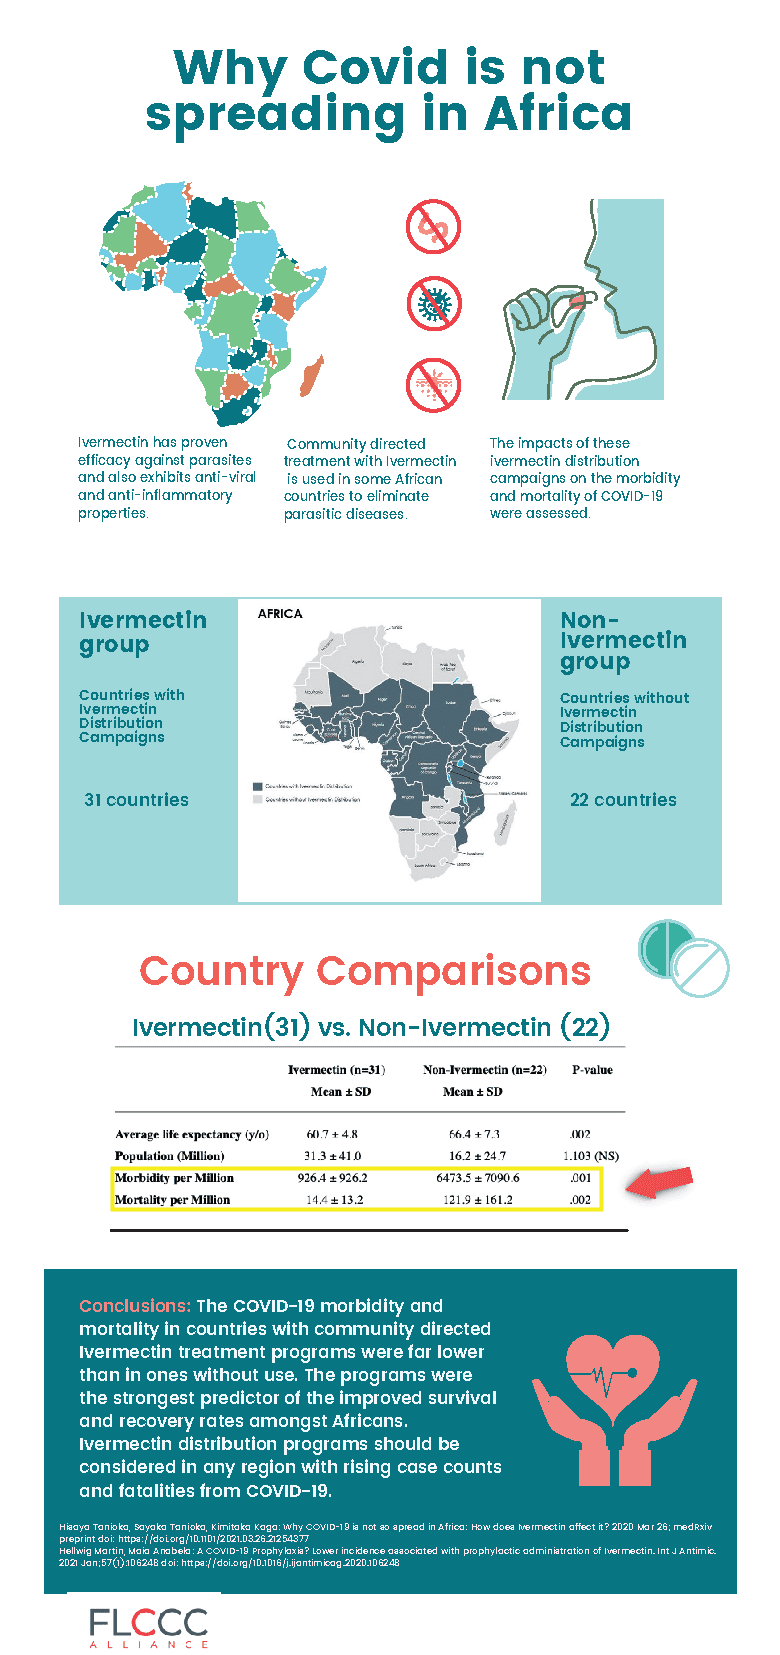
This nifty FLCCC graphic clearly shows that African countries with community directed ivermectin treatment programs had much lower morbidity and mortality and were the strongest predictor of improved survival and recovery rates of COVID.  Ivermectin distribution programs should be considered in any region with rising case counts and fatalities from COVID.

__________________

According to another doosie on Medpage, the authors are scratching their heads in perplexity over why those in Sub-Saharan Africa aren’t struggling with COVID.

Gee, could it be that everyone is taking ivermectin for river blindness, that “horse-dewormer” that supposedly doesn’t work for COVID?

More than 99% of those infected with river blindness live in 31 countries in sub-Saharan Africa: Angola, Benin, Burkina Faso, Burundi, Cameroon, Central African Republic, Chad, Republic of Congo, Côte d’Ivoire, Democratic Republic of the Congo, Equatorial Guinea, Ethiopia, Gabon, Ghana, Guinea, Guinea-Bissau, Kenya, Liberia, Malawi, Mali, Mozambique, Niger, Nigeria, Rwanda, Senegal, Sierra Leone, South Sudan, Sudan, Togo, Uganda, United Republic of Tanzania.

How have they dealt with the problem?

Between 1974 and 2002, disease caused by onchocerciasis was brought under control in West Africa by spraying of insecticides against blackfly larvae and by large-scale distribution of ivermectin since 1989.

BINGO!

But, mainstream medicine, media, and all the Pharma-shills can not see the forest through the trees because ivermectin is, as the German’s say, “Verboten!”

AP News: “Scientists mystified”

“Fewer than 6% of people in Africa are vaccinated. For months, the WHO has described Africa as ‘one of the least affected regions in the world’ in its weekly pandemic reports.”

Gibraltar, the most vaccinated region, at 140%, is canceling Christmas.

This is no surprise nor a mystery to scientists who have been paying attention,” writes James Lyons-Weiler.

Weiler also states that In April, 2020, he reported that immune deficiency due to autoimmunity against immune proteins was likely due to #PathogenicPriming from similarity between SARS-CoV-2 viral proteins and human immune proteins. Go here to watch a passionate plea from Weiler, where he explains that not a single vaccine manufacturer removed these unsafe epitopes after he notified them.

But this too is an inconvenient truth that will never be reported in the news or believed by card-carrying COVIDians.

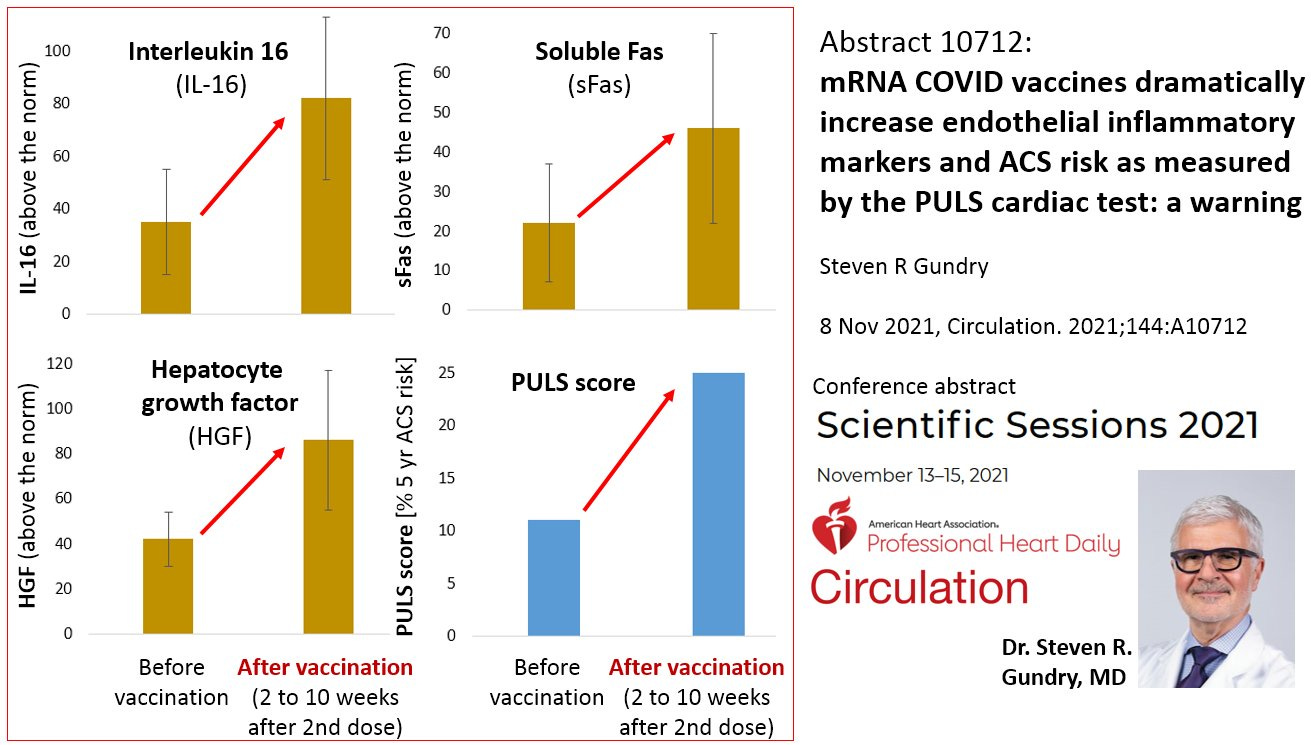
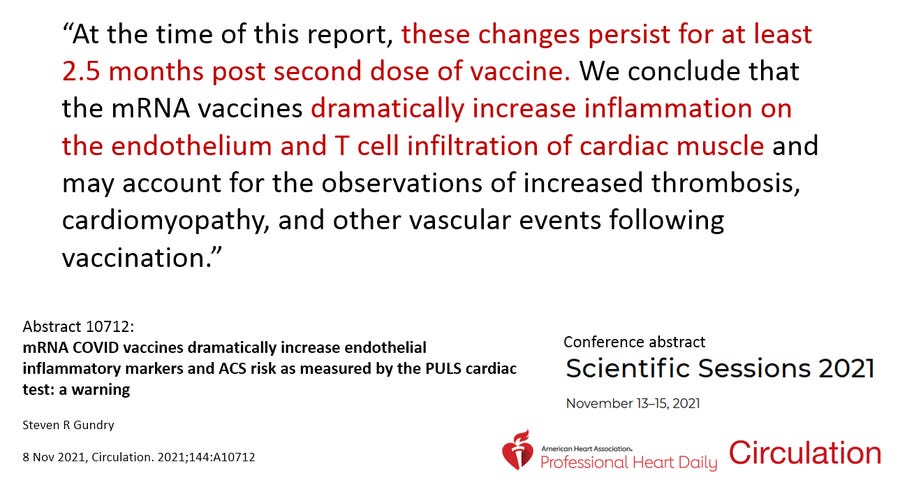
An abstract by Dr. Steven Gundry shows the COVID jabs increase endothelial inflammatory markers & acute coronary risk as measured by the PULS cardiac test which persists for at least 2.5 months post 2nd dose.  This means the jabbed’s immune system is busy fighting the spike protein for at least 2.5 months.

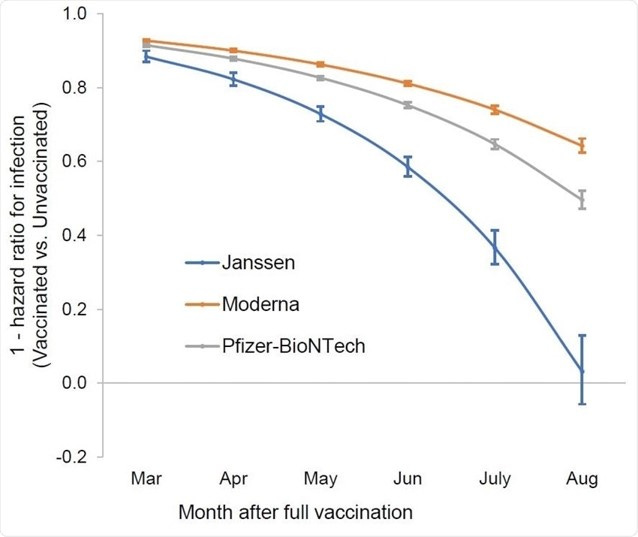
Efficacy is below 50% for every shot now and no one is addressing what happens when the “vaxxed” become infected with a mutating SARS-CoV-2 virus, when their immune systems are busy fighting an out of control spike protein in their bodies.

Please watch an SOS from Australia whose army has begun transferring positive cases and contacts to quarantine camps.

For more:

Revisiting Incarnation Children’s Center – AIDS Drug Trials Funded by Fauci

https://www.omsj.org/blogs/incarnation-childrens-center-aids-trials

Revisiting Incarnation Children’s Center – AIDS Drug Trials

February 23, 2014

(LIAM SCHEFF) –  In 2004, I broke open the NIH Clinical Trial Scandal, the internationally-covered story of hundreds of New York City orphans used by government agencies and pharmaceutical companies in deadly AIDS drug trials.

In reporting this issue, I entered the orphanage where children were being used as guinea pigs, and over a period of several years, took interviews with mothers, children and childcare workers at the Incarnation Children’s Center. I also interviewed the medical director, and investigated the FDA documentation and published medical literature on the tests and drugs used, drugs which were often force-fed through nasal and gastric tubes to the children. I reported several deaths in children, and although the mainstream denied that any deaths were due to drug toxicity, they admit that over 200 children died.

(See link for article)

_____________________

**Comment**

Your tax dollars at work, directed by Dr. Fauci, head of the National Institute of Allergy and Infectious Diseases (NIAID) since 1984 – and current Hollywood star for COVID propaganda.  Please take the time to listen to 10 full minutes of COVID contradictory propaganda from our leaders, including Fauci.

Summary:

  • NYC hired Vera Institute to create a final report on this inhumane experiment but weren’t given access to the children’s medical records. The VERA investigator refused to take data from Scheff that listed the trials, drugs used, and recorded ‘black box’ warnings.
  • The report stated that out of 532 children in the study, 25 died directly during the study, another 55 died later in foster care, and the Director at VERA as of 2009 stated that 29% of the remaining 417 had died. In a follow-up interview, the head of VERA admitted that many more children had died.
  • According to this: one staff member, Jacklyn Hoerger, spoke out about the deceitful protocol:
    • “We were told that if they were vomiting, if they lost their ability to walk, if they were having diarrhea, if they were dying, then all of this was because of their HIV infection. I just faithfully gave it as I was told by doctors.” Fauci and the NIAID claimed the drugs and vaccines were the only chance for survive.  (Sound familiar?)
    • Hoerger put that theory to the test and adopted two half-sisters. She removed the children from the experiments and watched them recover. The girls began eating properly for the first time in their lives and improved “almost instantaneously.” Hoerger concluded that the drugs were causing the children’s bodies to shut down. When the doctors and administrators found out she was ostracized as a “negligent parent.” The girls were taken from her and she wasn’t allowed to see them again.
    • Fauci wanted adherence at all costs – even the children’s well being.  No matter what happened, doctors could blame HIV; however, NIAID and their partners presumed all the children had HIV.  They never used any laboratory confirmation.  (I will add that PCR testing for HIV is just as abysmal as it is for COVID and should never be trusted by itself for diagnosis)
    • What isn’t discussed is the fact that when parents withdrew consent, their child was removed and placed in a foster home that would comply. 
  • Watch the documentary “Guinea Pig Kids”, and read Celia Farber and the late Liam Scheff’s expose’ on these crimes against humanity, which also a WBAI New York news-report
  • Both Wikipedia and the NY Times covered up the sordid details and heralded it as one of the great successes of AIDS treatment. They erroneously state that doctors obtained permission for using the foster kids, but admits that the “permissions” for many of these children are “missing,” (or were never there).  They also didn’t review the children’s medical files – but still conclude it was a medical success.
  • Fauci got away with crime, and appears to be getting away with the current crimes against humanity regarding COVID.  He’s known by many as “the Teflon man” as nothing sticks to him.

If You Read One Thing on SARS-CoV-2 Pathogenesis, Read This (Part I)

https://popularrationalism.substack.com/p/if-you-read-one-thing-on-sars-cov?

If You Read One Thing on SARS-CoV-2 Vaccine Pathogenesis, Read This (Part 1)

All of this was predicted in April 2020. Here is the undeniable evidence that mass-exposure to the SARS-CoV-2 Spike protein is a very bad idea.

In April, 2020, I predicted the spike protein would cause problems with health.

What my analysis precipitated was a flurry of studies, including laboratory work that confirmed that pathogenic priming was likely to happen.

My findings, as well as those by others who did subsequent similar analyses, point to autoimmunity as a prime driver of COVID-19 disease and of long-term reactions to COVID-19 “vaccination”.

Looking back at the list of proteins that we could see would likely become targets of our own immune system, so much pain & suffering could have been avoided. Given the tissue distribution of the self-antigens in particular, the analyses foretold of a future of clotting disorders, cardiovascular problems, issues with sperm production and female reproduction.

One of the very best summaries was published in a beautiful opus by Seneff and Nigh in the journal “International Journal of Vaccine Theory, Research and Practice” about a year after my initial predictions. That article, entitled “Worse Than the Disease? Reviewing Some Possible Unintended Consequences of the mRNA Vaccines Against COVID-19”, is as comprehensive a piece as you will find warning against the dangers of widespread exposure to the SARS-CoV-2 spike protein. I recently had occasion to re-read the article while preparing written testimony for one of the lawsuits in which I serve as expert witness, and it is absolutely, an “If you read one thing.”

Here is the section on Pathogenic Priming, Multisystem Inflammatory Disease and Autoimmunity, from their article:

“Pathogenic Priming, Multisystem Inflammatory Disease, and Autoimmunity

Pathogenic priming is a concept that is similar in outcome to ADE, but different in the underlying mechanism. We discuss it here as a unique mechanism through which the mRNA vaccines could provoke associated pathologies.

In April 2020 an important paper was published regarding the potential for self reactive antibodies to be generated following exposure to the spike protein and other antigenic epitopes spread over the length of SARS-CoV-2. Lyons-Weiler (2020) coined the phrase ‘pathogen priming’ because he believed the more commonly used ‘immune enhancement’ fails to capture the severity of the condition and its consequences. In his in silico analysis, Lyons-Weiler compared all antigenic SARSCoV-2 protein epitopes flagged in the SVMTriP database (http://sysbio.unl.edu/SVMTriP/) and searched the p-BLAST database (https://blast.ncbi.nlm.nih.gov/Blast.cgi) for homology between those epitopes and endogenous human proteins. Of the 37 SARS-CoV-2 proteins analyzed, 29 had antigenic regions. All but one of these 29 had homology with human proteins (putative self-antigens) and were predicted to be autoreactogenic. The largest number of homologies were associated with the spike (S) protein and the NS3 protein, both having 6 homologous human proteins.

A functional analysis of the endogenous human proteins homologous with viral proteins found that over 1/3 of them are associated with the adaptive immune system. The author speculates that prior virus exposure or prior vaccination, either of which could initiate antibody production that targets these endogenous proteins, may be playing a role in the development of more severe disease in the elderly in particular. In this case the pre-existing antibodies act to suppress the adaptive immune system and lead to more severe disease.

Another group (Ehrenfeld et. al., 2020), in a paper predominantly about the wide range of autoimmune diseases found in association with a prior SARS-CoV-2 infection, also investigated how the spike protein could trigger such a range of diseases. They report, in Table 1 of that reference, strings of heptapeptides within the human proteome that overlap with the spike protein generated by SARS-CoV-2. They identified 26 heptapeptides found in humans and in the spike protein. It is interesting to note that 2 of the 26 overlapping heptapeptides were found to be sequential, a strikingly long string of identical peptides to be found in common between endogenous human proteins and the spike protein. Commenting on the overlapping peptides they had discovered and the potential for this to drive many types of autoimmunity simultaneously, they comment, ‘The clinical scenario that emerges is upsetting.’ Indeed, it is.

In May of 2020 another important paper in this regard was published by Vojdani and Kharrazian (2020). The authors used both mouse and rabbit monoclonal antibodies against the 2003 SARS spike protein to test for reactivity against not only the spike protein of SARS-CoV-2, but also against several endogenous human proteins. They discovered that there was a high level of binding not only with the SARS-CoV-2 spike protein, but against a wide range of endogenous proteins. ‘[W]e found that the strongest reactions were with transglutaminase 3 (tTG3), transglutaminase 2 (tTG2), ENA, myelin basic protein (MBP), mitochondria, nuclear antigen (NA), α-myosin, thyroid peroxidase (TPO), collagen, claudin 5+6, and S100B.’ (Vojdani and Kharrazian, 2020).

These important findings need to be emphasized. Antibodies with a high binding affinity to SARSCoV-2 spike and other proteins also have a high binding affinity with tTG (associated with Celiac Disease), TPO (Hashimoto’s thyroiditis), myelin basic protein (multiple sclerosis), and several endogenous proteins. Unlike the autoimmune process associated with pathogen priming, these autoimmune diseases typically take years to manifest symptomatically.

The autoantibodies generated by the spike protein predicted by Lyons-Weiler (2020) and described above were confirmed with an in vitro study published more recently. In this follow-on paper, Vojdani et. al., (2021) looked again at the issue of cross reactivity of antibodies, this time using human monoclonal antibodies (mAbs) against the SARS-CoV-2 spike protein rather than mouse and rabbit mAbs. Their results confirmed and extended their prior findings. ‘At a cutoff of 0.32 OD [optical density], SARS-CoV-2 membrane protein antibody reacted with 18 out of the 55 tested antigens.’ These 18 endogenous antigens encompass reactivity to tissue in liver, mitochondria, the nervous and digestive system, the pancreas, and elsewhere in the body.

In a report on multisystem inflammatory syndrome in children (MIS-C), Carter et. al. (2020) studied 23 cases. Seventeen of 23 (68%) patients had serological evidence of prior SARS-CoV-2 infection.

Of the three antibodies assessed in the patient population (nucleocapsid, RBD, and spike), IgG spike protein antibody optical density (which quantifies antibody concentrations against a standardized curve (Wikipedia, 2021)), was highest (see Figure 1d in Carter et al., 2020).

MIS-C is now commonly speculated to be an example of immune priming by prior exposure to SARS-CoV-2 or to other coronaviruses. Buonsenso et. al. (2020) reviewed multiple immunologic similarities between MIS-C and disease related to prior β hemolytic Group A streptococcal infection (GAS). The authors write, ‘We can speculate that children’s multiple exposition to SARS-CoV-2 with parents with COVID-19 can work as a priming of the immune system, as happens with GAS infection and, in genetically predisposed children, lead to [MIS-C] development. Another hypothesis is that previous infections with other coronaviruses, much more frequent in the pediatric population, may have primed the child immune system to SARS-CoV-2 virus.’

In June 2019 Galeotti and Bayry (2020) reviewed the occurrence of both autoimmune and inflammatory diseases in patients with COVID-19. They focus their analysis on MIS-C. After reviewing several previously published reports of a temporal link between COVID-19 and onset of MIS-C and describing a number of possible mechanistic connections between the two, the authors noted that no causal link had been established. In a somewhat prescient recommendation, they wrote, ‘A fine analysis of homology between various antigens of SARS-CoV-2 and self-antigens, by use of in silico approaches and validation in experimental models, should be considered in order to confirm this hypothesis.’ It is precisely this type of in silico analysis (that had already been) carried out by Lyons-Weiler (2020) and by Ehrenfeld et. al. (2020) described in the opening paragraphs of this section which found the tight homology between viral antigens and self-antigens. While this may not definitively confirm the causal link hypothesized by Galeotti and Bayry, it is strong supporting evidence.

Autoimmunity is becoming much more widely recognized as a sequela of COVID-19. There are multiple reports of previously healthy individuals who developed diseases such as idiopathic thrombocytopenic purpura, Guillain-Barré syndrome and autoimmune haemolytic anaemia (Galeotti and Bayry, 2020). There are three independent case reports of systemic lupus erythemosus (SLE) with cutaneous manifestations following symptomatic COVID-19. In one case a 39-year-old male had SLE onset two months following outpatient treatment for COVID-19 (Zamani et.al., 2021).

Another striking case of rapidly progressing and fatal SLE with cutaneous manifestations is described by Slimani et.al. (2021).

Autoantibodies are very commonly found in COVID-19 patients, including antibodies found in blood (Vlachoyiannopoulos et. al., 2020) and cerebrospinal fluid (CFS) (Franke et. al., 2021).

Though SARS-CoV-2 is not found in the CSF, it is theorized that the autoantibodies created in response to SARS-CoV-2 exposure may lead to at least some portion of the neurological complications documented in COVID-19 patients. One important Letter to the Editor submitted to the journal Arthritis & Rheumatology by Bertin et. al. (2020) noted the high prevalence and strong association (p=0.009) of autoantibodies against cardiolipin in COVID-19 patients with severe disease.

Zuo et. al. (2020) found anti-phospholipid autoantibodies in 52% of hospitalized COVID-19 patients and speculated that these antibodies contribute to the high incidence of coagulopathies in these patients. Schiaffino et. al. (2020) reported that serum from a high percentage of hospitalized COVID-19 patients contained autoantibodies reactive to the plasma membrane of hepatocytes and gastric cells. One patient with Guillain-Barre Syndrome was found to have antibody reactivity in cerebrospinal fluid (CFS), leading the authors to suggest that cross-reactivity with proteins in the CFS could lead to neurological complications seen in some COVID-19 patients. In a more recent review, Gao et. al. (2021) noted high levels of autoantibodies in COVID-19 patients across multiple studies. They conclude, ‘[O]ne of the potential side effects of giving a mass vaccine could be an emergence [sic] of autoimmune diseases especially in individuals who are genetically prone for autoimmunity.’

A recent publication compiles a great deal of evidence that autoantibodies against a broad range of receptors and tissue can be found in individuals who have had previous SARS-CoV-2 infection. ‘All 31 former COVID-19 patients had between 2 and 7 different GPCR-fAABs [G-protein coupled receptor functional autoantibodies] that acted as receptor agonists. (Wallukat et. al. 2021) The diversity of GPCR-fAABs identified, encompassing both agonist and antagonist activity on target receptors, strongly correlated with a range of post-COVID-19 symptoms, including tachycardia, bradycardia, alopecia, attention deficit, PoTS, neuropathies, and others.

The same study, referencing the autoantibodies predicted by Lyons-Weiler (2020) mentioned above, notes with obvious grave concern: ‘The Sars-CoV-2 spike protein is a potential epitopic target for biomimicry-induced autoimmunological processes [25]. Therefore, we feel it will be extremely important to investigate whether GPCR-fAABs will also become detectable after immunisation by vaccination against the virus.’

We have reviewed the evidence here that the spike protein of SARS-CoV-2 has extensive sequence homology with multiple endogenous human proteins and could prime the immune system toward development of both auto-inflammatory and autoimmune disease. This is particularly concerning given that the protein has been redesigned with two extra proline residues to potentially impede its clearance from the circulation through membrane fusion. These diseases could present acutely and over relatively short timespans such as with MIS-C or could potentially not manifest for months or years following exposure to the spike protein, whether via natural infection or via vaccination.

Many who test positive for COVID-19 express no symptoms. The number of asymptomatic, PCR-positive cases varies widely between studies, from a low of 1.6% to a high of 56.5% (Gao et. al., 2020). Those who are insensitive to COVID-19 probably have a very strong innate immune system.

The healthy mucosal barrier’s neutrophils and macrophages rapidly clear the viruses, often without the need for any antibodies to be produced by the adaptive system. However, the vaccine intentionally completely bypasses the mucosal immune system, both through its injection past the natural mucosal barriers and its artificial configuration as an RNA-containing nanoparticle. As noted in Carsetti (2020), those with a strong innate immune response almost universally experience either asymptomatic infection or only mild COVID-19 disease presentation. Nevertheless, they might face chronic autoimmune disease, as described previously, as a consequence of excessive antibody production in response to the vaccine, which was not necessary in the first place.

The Spleen, Platelets and Thrombocytopenia

Dr. Gregory Michael, an obstetrician in Miami Beach, died of a cerebral hemorrhage 16 days after receiving the first dose of the Pfizer/BioNTech COVID-19 vaccine. Within three days of the vaccine, he developed idiopathic thrombocytopenic purpura (ITP), an autoimmune disorder in which the immune cells attack and destroy the platelets. His platelet count dropped precipitously, and this caused an inability to stop internal bleeding, leading to the stroke, as described in an article in the New York Times (Grady and Mazzei, 2021). The New York Times followed up with a second article that discussed several other cases of ITP following SARS-CoV-2 vaccination (Grady, 2021), and several other incidences of precipitous drop of platelets and thrombocytopenia following SARS-CoV-2 vaccination have been reported in the Vaccine Adverse Event Reporting System (VAERS).’

SARS-CoV-2 may have effects on the human vascular system, including that of the brain. The primary function of the Spike protein is to allow the entry of the virus into a host cell via binding to the ACE2 receptor located in the cell membrane. ACE2 is a type I integral membrane protein that cleaves angiotensin II in angiotensin I, thus removing angiotensin II and lowering the blood pressure.”

Since that paper was published, much more has come to light about the pathogenesis of the SARS-CoV-2 Spike Protein. I’ll be reviewing those works in Part 2.

Walensky Continues to Distort Research, And Plastic Barriers Possibly Make Things Worse in The Topsy- Turvy World of COVID Where Reality Simply Doesn’t Matter

https://reason.com/2021/11/09/the-cdcs-director-implies-that-face-masks-are-more-effective-than-vaccines-at-preventing-covid-19-infection/

The CDC’s Director Implies That Face Masks Are More Effective Than Vaccines at Preventing COVID-19 Infection

Rochelle Walensky seems to be relying on a laboratory study that did not measure infection risk.

| 

Are face masks more effective than vaccination at preventing COVID-19 infection? That is the implication of a new public service announcement from the Centers for Disease Control and Prevention (CDC) featuring Rochelle Walensky, the agency’s director.

“The evidence is clear,” Walensky says in the 37-second video, which she posted on Twitter last Friday. “Masks can help prevent the spread of COVID-19 by reducing your chance of infection by more than 80 percent, whether it’s an infection from the flu, from the coronavirus, or even just the common cold. In combination with other steps like getting your vaccination, hand washing, and keeping physical distance, wearing your mask is an important step you can take to keep us all healthy.”

If wearing a mask reduced your risk of infection by “more than 80 percent,” as Walensky seems to be saying, that safeguard would be amazingly effective. Such a risk reduction would be higher than the effectiveness rates found in several real-world studies of mRNA vaccines. (See link for article)

________________

**UPDATE, Nov. 24, 2021**

Watch a series of brief videos where Tyson Gabriel, an industrial hygienist, safety engineer, and risk manager who trains doctors and has 20 years of experience implementing exposure prevention plans in industry, and is lead researcher for his team, examined each mask study on the CDC’s website.  Also see these reports.

Once again our corrupt public health ‘authorities’ are convoluting data.

  • The author asked the CDC about this claim. When they finally responded, they did not cite any specific research to back it up and essentially gave boilerplate advice
  • It appears Walensky is relying on a laboratory study that was reported in the journal Science Advances last September where researchers used a camera to record laser-illuminated respiratory droplets from speakers wearing 14 different types of face masks which found:
    • valveless N95 mask was 99.9 percent effective at retaining “droplet sizes larger than 0.5 μm” (the estimated detection limit) Please listen to a N95 developer explain the reason your glasses fog up wearing these masks is due to holes at the top where viruses can easily gain entry. Further, he estimates that 70% of the air you are breathing does not go through the mask
    • neck gaiter seemed worse than useless and actually broke larger droplets into smaller ones
    • three-layer surgical masks and several kinds of cloth masks reduced the number of droplets detected by more than 80%. Again, the PPE N95 develper shreds this to bits by stating when you cough or sneeze with a cloth mask on, it goes right through the mask.  Another PhD in infectious disease states cloth masks offer NO protection against COVID
Based on these results of a study done in a lab the CDC’s summary says “upwards of 80% blockage has been achieved in human experiments that have measured blocking of all respiratory droplets.”

Her statement is misleading as it doesn’t include the numerous limitations in the study, and it certainly doesn’t quantify real-world implications of masks on a study contained in a lab that didn’t even measure for it. The study contained some laughable details:

  • In one particular study, the person wearing a mask spoke through a hole in a box reciting the phrase “Stay healthy, people,” but did not cough, sneeze, shout, or sing
  • Masks were clean and worn properly, which rarely happens in the real world
  • Walensky’s message assumes everyone is wearing the most effective mask
  • When parents had their child’s masks tested, the lab found Lyme, Tularemia, Ridkettsia, and other bacteria
  • Worse, Walensky’s ambiguous statement could be interpreted to mean that people who wear masks reduce their own risk of catching COVID-19 by “more than 80 percent.” The study, which looked at droplets emitted by mask wearers, provides no basis for this claim
  • There continues to be no basis in science for wearing masks unless you are trying to filter dust
  • A large meta-analysis shows that while masks may filter droplets there are numerous drawbacks which our corrupt public health ‘authorities’ never mention including that they may actually increase transmission. Every time I see someone wearing a mask, they are constantly touching it.  Constantly.  They also lower the oxygen you are breathing which is terrible for overall health
  • Walensky has repeatedly caught flak for distorting COVID-19 research
  • In a large, randomized controlled study on 6,000 people, no statistically significant difference was noted in infection rate between the mask wearing group vs the unmasked group.  These results reflect other reviews and nine other trials that found masks make little or no difference in infection rates.  But, again, none of this matters in a world without logic

https://www.nytimes.com/2021/08/19/well/live/coronavirus-restaurants-classrooms-salons

Clear barriers have sprung up at restaurants, nail salons and school classrooms, but most of the time, they do little to stop the spread of the coronavirus.
Credit…Rich Pedroncelli/File, via Associated Press

Covid precautions have turned many parts of our world into a giant salad bar, with plastic barriers separating sales clerks from shoppers, dividing customers at nail salons and shielding students from their classmates.

Intuition tells us a plastic shield would be protective against germs. But scientists who study aerosols, air flow and ventilation say that much of the time, the barriers don’t help and probably give people a false sense of security. And sometimes the barriers can make things worse.

Research suggests that in some instances, a barrier protecting a clerk behind a checkout counter may redirect the germs to another worker or customer. Rows of clear plastic shields, like those you might find in a nail salon or classroom, can also impede normal air flow and ventilation.

Under normal conditions in stores, classrooms and offices, exhaled breath particles disperse, carried by air currents and, depending on the ventilation system, are replaced by fresh air roughly every 15 to 30 minutes. But erecting plastic barriers can change air flow in a room, disrupt normal ventilation and create “dead zones,” where viral aerosol particles can build up and become highly concentrated.  (See link for article)

__________________

**Highlights**

  • A study published in June and led by researchers from Johns Hopkins showed that desk screens in classrooms were associated with an increased risk of coronavirus infection
  • In a Massachusetts school district, researchers found plexiglass dividers with side walls in the main office were impeding air flow
  • A study looking at schools in Georgia found desk barriers had little effect on the spread of the coronavirus compared with ventilation improvements and masking
  • A study published in 2014 found that office cubicle dividers were among the factors that may have contributed to disease transmission during a tuberculosis outbreak in Australia
  • British researchers have conducted modeling studies simulating what happens when a person on one side of a barrier exhales particles while speaking or coughing under various ventilation conditions. The screen is more effective when the person coughs, because the larger particles have greater momentum and hit the barrier. But when a person speaks, the screen doesn’t trap the exhaled particles — which just float around it. While the store clerk may avoid an immediate and direct hit, the particles are still in the room, posing a risk to the clerk and others who may inhale the contaminated air
  • A study published in 2013 that looked at the effect of partitions between beds in hospitals. The study showed that while some people were protected from germs, the partitions funneled the air in the room toward others
  • All the aerosol experts interviewed agreed that desk shields were unlikely to help and were likely to interfere with the normal ventilation of the room. Depending on the conditions, the plastic shields could cause viral particles to accumulate in the room
  • As with everything else in this ‘pandemic’, those in charge are simply in lockstep following corrupt public health advice without consulting with engineering experts.  It appears those in authority are tin men lacking a brain.