Archive for the ‘Activism’ Category

NIH Research Executive Received 70 Secret Royalty Payments; Colleague Got 7

**UPDATE June, 2022**

Please learn about the recent action to obtain information from the NIH on royalty payments.

https://www.theepochtimes.com/key-nih-research-executive-received-70-secret-royalty-payments-colleague-got-7

NIH Research Executive Received 70 Secret Royalty Payments; Colleague Got 7

By Mark Tapscott
Updated: May 18, 2022

Two key National Institutes for Health (NIH) executives in positions of influence on decisions about who gets grants from the agency received a total of 77 previously undisclosed royalty payments from outside firms between 2010 and 2014.

The secret royalty payments, which were first reported by The Epoch Times, are among thousands estimated to total at least $350 million paid between 2010 and 2020. Former NIH Director Dr. Francis Collins received 14 payments, Anthony Fauci, who heads NIH’s National Institute for Allergies and Infectious Diseases (NIAID), received 23, and Clifford Lane, Fauci’s chief deputy, got eight payments.

Acting NIH Director Lawrence Tabak conceded during questioning last week by Rep. John Moolenaar (R-Mich.) that the undisclosed royalties had the “appearance of a conflict of interest,” but he insisted that the agency has sufficient internal safeguards to prevent such problems. Federal law and ethics regulations bar federal employees from activities that present either the appearance or an actual conflict of interest. (See link for article)

___________________

SUMMARY:

  • NIH deputy Director for intramural research, Dr. Michael Gottesman, also received 70 payments from 2010-2014.  Gottesman provides guidance for the entire program, oversees and approves hiring of al NIH principal investigators, and is responsible for human subjects research protections, research integrity, technology transfer, animal care and use at NIH, created the post-baccalaureate training program which permits grad students to conduct thesis research, implemented loan repayment programs, created an intramural tenure track and new career track for clinical investigators, created the NIH intramural database, and spearheaded other programs in diversity, equity, research integrity, and leadership.
  • Gottesman announced his resignation in July 2021, pending selection of a successor, and plans to remain as chief of the laboratory of cell biology  in the NIH National Cancer Institute.
  • The NIH ignored the request for information until a FOIA lawsuit was filed.  It has also redacted payment amounts and payers’ identities so details remain a mystery.
  • NIH associate director for international research, Roger Glass, also received 7 royalty payments of unknown amounts from unknown payers.
  • Congressional Democrats were silent when asked about the secret royalty payments, while Republicans are calling for full disclosure with one senator calling the NIH a “dark money pit.”
  • Rep. Greg Steube (R-Fla.) called for an investigation, noting: “Of course it’s a direct conflict of interest for scientists like Anthony Fauci to rake in $350 million in royalties from third parties who benefit from federal taxpayer-funded grants.  “Anthony Fauci is a millionaire that has gotten rich off taxpayer dollars. He is a prime example of the bloated federal bureaucracy. This royalty system should be examined to ensure it isn’t making matters worse.”

For more:

DOD Edits Medical Database to Hide Military COVID-19 “Vaccine” Injuries as U.S. Military is Decimated by the Mandatory Shots

https://healthimpactnews.com/2022/dod-edits-medical-database-to-hide-military-covid-19-vaccine-injuries-as-u-s-military-is-decimated-by-the-mandatory-shots/  Go Here for Video (Approx. 21 Min)

DOD Edits Medical Database to Hide Military COVID-19 Vaccine Injuries as U.S. Military is Decimated by the Mandatory Shots

by Brian Shilhavy
Editor, Health Impact News

Lt. Col. Peter Chambers has a 38-year career in the military. He is a Green Beret Commander having served in the Special Forces, and he is a military doctor, serving as a flight surgeon and combat medic. He has earned the Purple Heart and Bronze Star Medal, as well as other military awards for his service.

Lt. Col. Peter Chambers became a whistleblower after suffering neurological issues following mandatory COVID-19 vaccines, and seeing similar vaccine injuries in other soldiers, including: strokes, blood clots, cerebral bleeding, and various neurological injuries.

He began to research vaccine injuries following the COVID-19 vaccines that were mandated for service members, in the Defense Medical Epidemiology Database (DMED) sponsored by the DOD.

He has most recently been deployed in Texas, near the Texas-Mexico border as a task force surgeon, where he began to provide “informed consent” counseling to over 3000 soldiers at the border regarding the COVID-19 vaccines, sharing with them the data he had uncovered in DMED, VAERS, NIH and other government sources.

Being in Texas, he also informed them that doctors could prescribe early treatments for COVID, such as Ivermectin, which are very effective in overcoming the symptoms associated with COVID-19.

As a result, only 6 service members out of 3000 decided to comply with the COVID-19 vaccine mandates.

Dr. Chambers was approached by a 2-star general who asked why his vaccination rates were so low, to which he replied:

Sir, we have a regulation, AR 40-562 chapter 8 paragraph 4, clearly states that under emergency use authorization, I must do informed consent. It’s a regulation.

Sir, I do things legally, morally, ethically, and first of all “do no harm.”

The general allegedly became very angry with Dr. Chambers and stated:

You will cease and desist giving those informed consents.

Dr. Chambers looked at him straight in the eye and replied:

Sir, that is an unlawful order, and I will not follow that order.

The general then allegedly fired him on the spot, and Dr. Chambers’ military career was basically over at that point.

Dr. Chambers replied:

OK. But Sir, I am the only medical doctor down here on the border. Do you have anybody else? We’re getting shot at once in a while, you know that, I am a combat trauma doctor, and I’ve stopped a lot of bleeding.

After informing the general that he had filed a whistleblower complaint, the general did some checking, and about an hour later stated that Dr. Chambers was not fired, but that he would be replaced.

Dr. Chambers had joined Dr. Theresa Long, another military doctor who is also a flight surgeon, in a lawsuit filed by Attorney Thomas Renz against the U.S. Military’s mandatory COVID-19 vaccination program.

Go to top link to listen to the whole interview between Dr. Chambers and Steve Kirsch recorded back in March of this year. It is 21 minutes long, and WELL WORTH the time.

At the end of this interview, Dr. Chambers stated:

“If we don’t stop this, our military is going to be decimated.”

Within a day or two of this interview, their whistleblower case reached the U.S. Supreme Court which ruled 6-3 against Navy Seals being entitled to a religious exemption for COVID-19 vaccine mandates.

At the same time, New York City Mayor Eric Adams issued an executive order that exempted professional sports players and the entertainment industry from having to comply with COVID-19 vaccine mandates. See:

Insanity is the New Norm in the U.S. as Professional Sports Players can be Exempt from COVID Vaccine Mandates but Navy Seals Cannot

Now, Just the News is reporting that Dr. Chambers and other military medical doctor whistleblowers can no longer depend upon the data in DMED because:

“[The] DOD took down, edited and restored the Defense Medical Epidemiology Database earlier this year after whistleblowers including Chambers testified on the reported spike (in vaccine injuries) in a legal challenge.”

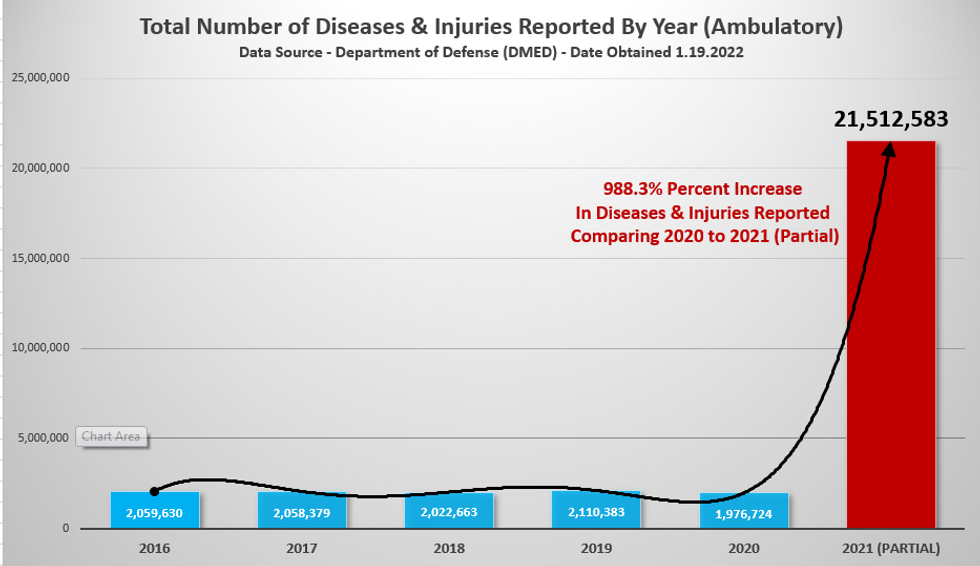
The department told PolitiFact …. the 2021 spike was the product of a “glitch” that caused severe underreporting of 2016-2020 figures. That would mean the military underreported cases by about 20 million a year during that period, whistleblower lawyer Tom Renz said.

Chambers told Just the News that DMED used to be more trustworthy than the government’s Vaccine Adverse Events Reporting System but now it’s “completely unusable” because DOD changed many diagnoses that suggested vaccine injury after the military doctors went public.

Working on the border with the Texas National Guard, he personally observed highly unusual problems in “a healthy population that should not be seeing these things,” from myocarditis to “brain bleeds,” and continues to receive similar reports in his “retirement section.”

Chambers said he developed demyelination after getting the Moderna vaccine in January 2021, which led him and Lt. Col. Theresa Long, another whistleblower, to review DMED.

(See top link for entire article and video)

__________________

**Comment**

Our military is in harms way, not just from bullets but from mandatory “vaccines” as well as tick-borne infections that do not get proper recognition.  The COVID shots in particular have been linked with heart inflammation specifically in a study involving the U.S. military.

If you are unfamiliar with the story on how the DOD “recalibrated” health surveillance data, see this article, as well as this article which states the Pentagon’s reaction only seems to be concerned with exonerating the “vaccine,” not fixing its own alleged health surveillance problem.

SUMMARY:

  • The DOD magically and suddenly discovered 5 years of “false data” only after attorney Renz came forth with shockingly dramatic increases in medical diagnoses among the military.
  • According to Horowitz, the DOD is only concerned with downplaying any potential culpability of the vaccine, not explaining how military health data could be so wrong.
  • This means the CDC was looking at data for months that showed insane safety signals and did nothing about it, and somehow nobody in HHS or the DOD all along thought the data was a “glitch.”
  • Horowitz further states that there is no way the “new” data could be updated so quickly.
  • Just take a look at the two graphs, the first of which shows the original data of total outpatient diagnoses before the Pentagon changed it:

And here is the top-line tally for 2016-2020 based on the new numbers added:

  • The mysteriously sudden changes make 2021 look exactly in line with every other year, despite COVID and “vaccine” injuries
  • The initial data downloaded by military whistleblowers makes more more sense because it accommodates both COVID and “vaccine” injury,
  • The updated data is makes zero sense as all active duty soldiers are medically screened, and obesity, diabetes, and heart conditions are very rare among this healthy population. If there is truly over 20 million diagnoses every year in the military there is something seriously wrong.
  • The silence both from the media and congressional members of the House and Senate Armed Services Committees is astounding.
  • One of two things is true:
    • there was mass “vaccine” injury in the military
    • our military is very unhealthy and the Pentagon completely lost control over epidemiological surveillance of these health issues for years
Either way, it doesn’t look good.

Go here for another article titled, “Regarding the Defense Medical Epidemiological Database Data Dump: Database Artifact, Smoking Gun, or Something in Between” by Dr. Malone.

Mum Who Thought She Had Dementia for 29 Years Discovers She Has Lyme Disease

https://www.mirror.co.uk/news/uk-news/mum-who-thought-dementia-

Mum who thought she had dementia for 29 years discovers she has Lyme disease

By Rosaleen Fenton Deputy Features Editor

Updated 12 May 2022

Mum-of-three Pauline Bowie, 54, suffered brain fog, headaches, muscle pain, carpal tunnel, and was even wetting herself after being bitten by a tick in America in 1989.

A teacher who feared she had dementia has told how she was diagnosed with Lyme disease after nearly 30 years.

She begged NHS doctors to take her symptoms seriously but they were repeatedly stumped for answers until she took matters into her own hands.

It wasn’t until Pauline sent blood samples to Armin labs in Germany in 2018 that she was finally given the diagnosis of Lyme disease, after being bitten by a tick in America in 1989.

The condition, a bacterial infection transmitted through ticks, can cause serious problems and attack the nervous system if left untreated.

Pauline had battled her illness for almost 30 years before getting antibiotics which cured all her agonising symptoms away in just four weeks.
She was prescribed 28 days of doxycycline which cleared her symptoms, but after treatment stopped they returned.

(See link for article)

__________________

**Comment**

Forty years after Lyme was “discovered” people still struggle with a similar fate: undiagnosis and stumped doctors.  Isn’t it about time for this to change?

The article states she was “cured” from all her ailments by using antibiotics in only 4 weeks, but when you read the article closely it states that after she relapsed she was treated for TWO YEARS with a combination of metronidazole and rife.  When I talk to Lyme old-timers they state metro used to be standard treatment but is completely forgotten or denied by mainstream medicine now.  This is unfortunate.  This article highlights Dr. Eva Sapi’s work showing:

Metronidazole led to reduction of spirochetal structures by ~90% and round body forms by ~80%. Tigecycline and tinidazole treatment reduced both spirochetal and round body forms by ~80%–90%.
In terms of qualitative effects, only tinidazole reduced viable organisms by ~90%. Following treatment with the other antibiotics, viable organisms were detected in 70%–85% of the biofilm-like colonies.

Metro is known for significant blow-back whereas tinidazole seems to be less prone to this.  It is what my husband and I pulsed for the ENTIRE DURATION OF TREATMENT of FIVE YEARS.  I scream that out so there is no doubt this sucker is hard to treat and takes far more than what is being given.  I ALWAYS herxed with tindy.  ALWAYS. 

A few points:

  • She felt she was losing her mind.  This is perhaps one of the toughest aspects of this illness but rarely talked about or acknowledged by corrupt mainstream medicine and public health ‘authorities.’
  • Unlike many, she actually had flu-like symptoms AND the bullseye rash. She should have been treated immediately as the rash is diagnostic for Lyme.  No testing required.
  • Some bone-head diagnosed her with ring-worm.  You seriously can’t make this stuff up.
  • Similarly to so many patients, she saw a slew of different doctors but nobody helped her.  This continues hows me three things:
  • She didn’t hear about Lyme until 2018 when she sent her own blood to Germany.  I’ve often heard this described as the “do it yourself disease.”  Mainstream medicine should be embarrassed.
  • She was prescribed 28 days of doxycycline which helped but symptoms returned once she went off the drug.  This is very, very common and only proves that the CDC monotherapy is rarely sufficient.
  • If she suffers a relapse she is given  antibiotics, but is currently enjoying remission and spends most of her days pain-free.  This also proves the point that many will manage this disease for life, and many will never be completely “cured.”  That’s not to say treatment doesn’t make all the difference in the world, but we need to be realistic about the fact this is a chronic/persistent disease for many.  If antibiotics didn’t still work for her, or the thousands of us in Lymeland, we wouldn’t take them – further proving that antibiotics can be extremely beneficial.  
  • Further proving this is a ‘do it yourself’ disease, this patient now treats herself – as so many do.

For more:

Klinghardt Institute Lyme Disease Protocols & Therapies Webinar Thursday May, 19, 2022

https://klinghardtinstitute.com/?mc_cid=0f2051eddd&mc_eid=fe12caca21

Join Dr Klinghardt this Thursday, May 19, 2022 for an update on his Lyme disease protocols and therapies.

Lyme disease is the most common vector borne disease in North America and Europe. It’s estimated that there are 300,000 new cases in the US and 100,000 new cases in Europe each year, although these numbers are likely to be underestimated as many infections go undiagnosed. With infections most common in the spring and early summer it’s important that we are all ‘Lyme aware’.

By registering for this webinar you understand that the information contained within it is the copyright of Dr Klinghardt and that NO recordings may be made.

Thursday 19th May at:
• 8.30pm UK
• 9.30pm Central Europe
• 12.30pm Pacific
•  3.30pm Eastern

If you’re unable to attend there will be a limited time replay available over the weekend.

We hope you can join us!
Dr Dietrich Klinghardt, Daniela Deiosso & the Klinghardt Institute Team

For more:

FDA Bypasses Advisory Panel, Ignores Data & Lowers Efficacy in Order to Authorize COVID Booster For Kids

https://www.medpagetoday.com/infectiousdisease/covid19vaccine

FDA Authorizes COVID Booster for Younger Kids

— Agency cites concern over Omicron, long COVID in its reasoning
FDA EUA Third dose of Pfizer-BioNTech COVID vaccine for kids ages 5 to 11 over a photo of a box of vials of Comirnaty

A third dose of Pfizer/BioNTech’s COVID-19 vaccine is authorized for kids ages 5 to 11 years, the FDA announced on Tuesday.

The third 10 μg dose may be administered to children at least 5 months after the initial primary series under the terms of the emergency use authorization (EUA), the agency said.

“While it has largely been the case that COVID-19 tends to be less severe in children than adults, the Omicron wave has seen more kids getting sick with the disease and being hospitalized, and children may also experience longer term effects, even following initially mild disease,” said FDA Commissioner Robert M. Califf, MD, in a statement.  (See link for article)

_________________

**COMMENT**

The FDA didn’t even bother to meet prior to the EUA. This is almost laughable if the consequences weren’t so dire.

Please watch this brief 12 minute video to learn that Dr. Marks lowered the 50% efficacy threshold at blocking symptomatic infection, which means they dropped a former FDA guidance requirement for EUA designation.  The latest cumulative mortality data from 46 states show ZERO COVID child deaths. Weiler recommends we each send his article to our Congressional Reps TODAY.

And go here to listen to Dr. Prasad discuss dropping the 50% efficacy requirement for EUA.

  • Dr. Weiler corrects Prasad’s false claim of 95% efficacy in the RCTs on adults (it was 75% if you include people who received a COVID-19 diagnosis before the second dose). He also neglects to point out that efficacy has dropped to less than zero in vaccination studies against recent variants, and that later studies only had to show antibody levels, which we know are short-term, unreliable measures of immunity.

__________________

https://childrenshealthdefense.org/defender/fda-pfizer-booster-kids-third-dose

FDA Authorizes Pfizer Booster for Kids 5 to 11, Bypasses Advisory Panel

By Megan Redshaw

5/17/22

The U.S. Food and Drug Administration today granted Emergency Use Authorization for Pfizer’s COVID-19 booster for children ages 5 to 11, without convening its vaccine advisory panel and despite the latest data showing higher case rates in vaccinated children compared with those not vaccinated.  (See link for article)

_________________

Important Points:

  • Booster approval is based on a study of 67 children showing antibody levels, which is a short-term and unreliable measure of immunity.  Further, this subset is not large enough to detect potential adverse events like myocarditis. Participants were only followed for 28 days.
  • There are NO studies testing the efficacy against the current COVID strains.
  • Two new studies show that for the vaxxed that get Omicron, infection provides better protection against future infections than a second booster.
  • FDA Director of the Center for Biologics Evaluation and Research, Dr. Peter Marks, admits data increasingly show protection provided by two shots wanes over time, but believes “benefits outweigh the risks.”
  • Pfizer has not published its actual data, precluding experts from conducting analysis.
  • FDA’s Peter Marks told Congress the shots for youngest kids don’t need to hit 50% efficacy threshold.
  • A study in JAMA showed protection from Pfizer’s shot turns negative among kids five months after receiving a 2nd dose, with recipients were more likely to get COVID-19 five months after being “vaccinated”.  Protection against hospitalization also waned significantly over time.
  • The Moderna shot also delivered more risk than benefit in trials for kids, and the study was also too small to assess known adverse events, yet the FDA also is fixated on authorizing it as well.
  • And while the FDA limits the J&J shot over blood clotting, experts state Pfizer and Moderna shots pose similar risks.
  • Most non-randomized studies attempting to determine vaccine efficacy had “common flaws,” giving them biases towards overestimating any clinical benefit. Flaws include:
    • no accounting for baseline prior COVID-19 infection
    • no reporting for those who received a booster within a six-month time window
    • no adjudication of hospitalization or death due to COVID-19 or other conditions

Dr. Weiler admonished us not to get distracted with the news cycle which is rigged to shock and distract us from what really matters.  Excerpt:

Don’t be distracted. Stay on focus: The move to approve COVID-19 vaccines for kids under 5 is necessary for the states to begin to mandate COVID-19 vaccines, and then all vaccines, for all children under the age of 5 – before parents begin comparing notes on vaccines for school entry.

FDA postponed the decision given insufficient (unconvincing) data. But there cannot be any convincing new data that shows individual benefit for kids under five from the COVID-19 vaccines… they do not stop transmission; under any reality-based analysis, vaccines do not stop COVID-19; kids do not get COVID-19 or die from COVID-19.

What type of evidence of individual benefit could Pfizer/Moderna/FDA cook up in two months’ time?
  • Will they show that individual children have decreased risk of death from COVID-19?
    • No, the vaccines being studied are targeting an extinct virus.
  • Will they show that Will they show that individual children have decreased risk of hospitalization from COVID-19?
    • No.
  • Will they show decreased transmission in this population?
    • No, Dr. Fantini’s results show INCREASED transmission due to vaccination against Wuhan-1 since the emergence of Beta, Gamma, Delta and Omicron.

The FDA will be able show data on antibodies. Period. Antibodies against an extinct variant, Wuhan-1.

  • The participants in the study will likely not be screened for prior immunity to COVID-19 from either natural infection, or from prior infection to viruses that confer cross-protection.
  • And the study will be adjusted for outcomes-related confounders, if necessary (p-hacking).
And we know that antibodies do not tell the full story.
The only good news is that parents are increasingly reluctant to give these clot shots to their kids.
And rightly so.
Take a gander at the latest VAERS data and the mounting list of adverse reactions and death.
