Archive for the ‘Activism’ Category

ACTION: Flood Inboxes of Task Force on Health Care Monopolies and Collusion

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/32992416

Calling on all Lyme patients, caregivers, and clinicians across the globe!
Carl Tuttle
Hudson, NH, United States
Oct 26, 2024

The following timeline for the deliberate mishandling of Lyme disease was forwarded to Attorney Katrina Rouse of the United States Antitrust Division, head of a Task Force on Health Care Monopolies and Collusion. Please forward your respectful request for an investigation into the collusion to deny chronic Lyme disease which has stifled research for better antimicrobials in treating this antibiotic resistant/tolerant superbug. Your email should describe how this denial has affected your ability to obtain treatment and affordable healthcare. What has been deceitfully established here in the US is being emulated across the globe.

Note to clinicians: Your experience on the front lines in treating chronic Lyme and witnessing the devastation first hand should be described in detail.

Let’s flood the inboxes of these two attorneys!

Contact info for Attorney Katrina Rouse and Assistant Attorney General Jonathan Kanter

Katrina Rouse: katrina.rouse@usdoj.gov

Jonathan Kanter: jonathan.kanter@usdoj.gov

Letter to Grace E. Marx, MD Medical Epidemiologist, Centers for Disease Control and Prevention:

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: “grace.marx@cuanschutz.edu” <grace.marx@cuanschutz.edu>, “gmarx@cdc.gov” <gmarx@cdc.gov>
Cc: “katrina.rouse@usdoj.gov” <katrina.rouse@usdoj.gov>, “jonathan.kanter@usdoj.gov” <jonathan.kanter@usdoj.gov>
Date: 10/25/2024 9:11 AM EDT
Subject: Tick-Borne Diseases and Associated Illnesses, Community Engagement Series: Mental Health and Neurological Effects

Tick-Borne Diseases and Associated Illnesses, Community Engagement Series: Mental Health and Neurological Effects
https://www.hhs.gov/oidp/initiatives/tick-borne-diseases-associated-illnesses-national-community-engagement-initiative/index.html3:00 pm – 3:20 pm   A Clinician Toolkit: Improving Care for Patients with Prolonged Symptoms and Concerns about Lyme Disease By Grace E. Marx, MD Medical Epidemiologist, Centers for Disease Control and Prevention

Dear Dr. Marx,

I listened to your presentation yesterday with great interest and I must congratulate you for your outstanding performance in suppressing all evidence of persistent infection; chronic Lyme disease.

We have studies proving persistent infection after antibiotic treatment for mice, dogs, ponies, monkeys, cows, iris biopsy, and ligamentous tissue but if you perform a simple Google search for the following statement, “There is no convincing scientific evidence that chronic Lyme exists” you will find the top search results are connected to “elements of academic medicine” involved in the denial of the late stage Lyme epidemic.

In 1991 the Lyme disease organism, Borrelia burgdorferi, was grown from the cerebrospinal fluid of Lyme patient Vicki Logan at the Centers for Disease Control in Fort Collins, Colorado despite prior treatment with intravenous antibiotics. The patient died when the insurer refused additional IV antibiotics. Here is a copy of Logan’s CDC positive culture report for your review.

(Vicky Logan’s Chronic Lyme Autopsy results Page #1, 2, 3, 4, 5, 6, 7)

There are 700 peer-reviewed publications referencing persistent infection and in a 2018 study all patients were culture positive even after multiple years on antibiotics so there was no relief from current antimicrobials. Some of these patients had taken as many as eleven different types of antibiotics.

Thirty-four years ago Dr. Allen Steere identified chronic Lyme disease which should have set off a red flag prompting an immediate search for better antimicrobials but then did a 180° as he became principal investigator (PI) of the Phase 3 clinical trial for the first Lyme disease vaccine. So all the eggs were put into the vaccine basket while a campaign was orchestrated to discredit the sick and disabled patient population along with the courageous clinicians attempting to help these patients. Apparently, a chronic relapsing seronegative disease did not fit the business model of patent royalties, vaccine development and pharmaceutical profits.

Here is Dr. Steere’s 1990 publication summary for your review:

The New England Journal of Medicine 

Published November 22, 1990

Chronic neurologic manifestations of Lyme disease
https://www.nejm.org/doi/full/10.1056/NEJM199011223232102

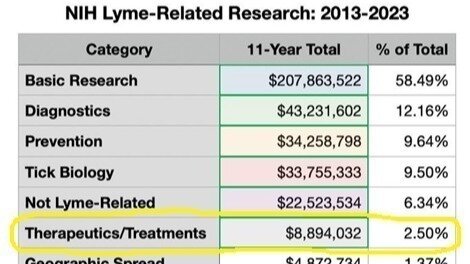
The chart below summarizes Lyme research funded by the NIH and only 2.5% has been allocated for treatment:

https://www.dropbox.com/scl/fi/4fpjivy7stiztfs5ib6sz/NIH-Lyme-Research.png?rlkey=71yrfa6r7e6osq2he7qwsjj75&dl=0

For the record there are many infections requiring long-term antibiotics so why Klempner stopped his NIH funded antibiotic treatment trials for Lyme after 90 days makes absolutely no sense whatsoever:

From the following publication:

Benefit of intravenous antibiotic therapy in patients referred for treatment of neurologic Lyme disease
https://www.dovepress.com/benefit-of-intravenous-antibiotic-therapy-in-patients-referred-for-tre-peer-reviewed-fulltext-article-IJGM

Infections requiring long-term antibiotics:

https://www.dropbox.com/scl/fi/pserdbenw4n1vovv14z2a/Infections-requiring-long-term-antibiotics.jpg?rlkey=281zg7alxl4gqm2e2jipy9szj&dl=0

Lyme misdiagnosed/undiagnosed for months, years or decades is far more incapacitating than “acute” Lyme and 2-4 weeks of antibiotics does not scratch the surface of this well-established/immune suppressive infection. These are the patients who need help the most but have been excluded in research for decades. There are countless stories of patients seroconverting after the initial few doses of Doxycycline and now that a toxin has been identified that puts Lyme disease in an altogether different category of infection:

Toxins 
Published: 21 May 2024

Borrelia burgdorferi 0755, a Novel Cytotoxin with Unknown Function in Lyme Disease
https://www.mdpi.com/2072-6651/16/6/233

So it would appear that one way to get a medical association (AMA) to go along with the suppression of evidence is to throw them a boatload of money… five million taxpayer dollars to be exact for a so-called IDSA biased “Clinician Toolkit”  (CDC grant number  NU50CK000597)

This controlling of the narrative has caused unimaginable pain and suffering all across America as insurance companies refuse to pay for long-term treatment, personal bankruptcies from out-of-pocket expenses to treat chronic infection, suicides from despair all while Valneva Received FDA Fast Track Designation for its Lyme Disease Vaccine.

Chronic Lyme must be recognized and finally addressed with 100% attention to effective antimicrobials for all stages of disease.

Question:

Is collusion to control the narrative through suppression of the truth, facts and scientific references a criminal offense?

Carl Tuttle
Hudson, NH

Cc: Assistant Attorney General Jonathan Kanter, Attorney Katrina Rouse
Attorneys for the United States Antitrust Division

Assistant Attorney General Jonathan Kanter Announces Task Force on Health Care Monopolies and Collusion
https://www.justice.gov/opa/pr/assistant-attorney-general-jonathan-kanter-announces-task-force-health-care-monopolies-and

“Every year, Americans spend trillions of dollars on health care, money that is increasingly being gobbled up by a small number of payers, providers and dominant intermediaries that have consolidated their way to power in communities across the country,” said Assistant Attorney General Jonathan Kanter of the Justice Department’s Antitrust Division. “Led by Katrina Rouse, the task force will identify and root out monopolies and collusive practices that increase costs, decrease quality and create single points of failure in the health care industry.”

“The Quiet Epidemic” Showing at the U.S. Capital Nov. 20, 2024

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/

The Quiet Epidemic Film Presentation at the U.S. Capitol November 20th

Carl Tuttle
Hudson, NH, United States
Oct 29, 2024

The Quiet Epidemic Film Presentation at the U.S. Capitol

Please join us on Capitol Hill for a special presentation of the award-winning documentary The Quiet Epidemic

Hosted by Senator Richard Blumenthal, with a special appearance by Chris Meloni, Actor & Global Lyme Alliance Celebrity Ambassador

Since the earliest days of production, the team and supporters behind The Quiet Epidemic hoped the film might one day screen on Capitol Hill, and that moment has arrived.

Please join us for a free and open to the public presentation of The Quiet Epidemic on Wednesday, November 20th, from 5:30 PM to 9:00 PM, at the U.S. Capitol. The film will be preceded by a reception and followed by a discussion and Q&A with the film’s subjects, experts and actor Chris Meloni.

While the event is free to attend, RSVPs via Eventbrite are required for entry. You’ll find a PDF invitation attached to this email which includes the RSVP link—please circulate this widely, as our team is prohibited from promoting the event on social media. Details regarding the exact venue location within the Capitol will be sent to all registrants via Eventbrite approximately one week prior to November 20th.

The Quiet Epidemic team would like to thank our generous sponsors who have made our Capitol Hill events possible: LymeLight Foundation, Global Lyme Alliance, Sarena Snider, Project Lyme, NatCapLyme and lymeLNK. Among our sponsors are The Quiet Epidemic Executive Producers Phyllis & Scott Bedford—founders of LymeLight Foundation—and Sarena Sarena, each of whom generously supported the creation of the film itself, the film’s festival tour and release, and our team since the very beginning.

Please share the Eventbrite link and the attached PDF with anyone in your network who may wish to attend this event—especally those in the Washington D.C. area. We also encourage you to invite your representatives and include a brief statement about the impact Lyme has had on your life, and the prevalence in their state.

PDF invitation

https://www.dropbox.com/scl/fi/rp1qqnln1w6ztk6yimecq/11.20.24_The-Quiet-Epidemic-on-Capitol-Hill.pdf?rlkey=ecmsm63kwn8w27pymi1x8dlqk&dl=0

This is a culminating moment for The Quiet Epidemic film and impact campaign, nine years in the making. Thank you for being a part of this journey and for making it possible in so many ways! We hope to see you in D.C.

With gratitude,
The Quiet Epidemic Team

Watch The Quiet Epidemic trailer:
https://www.youtube.com/watch?v=I4C71N290co

Brazil Faces Same Problems With Lyme Disease As Seen in the USA

http://cameronmd.com/brazil-faces-problems-lyme-disease-seen-usa/

Brazil faces same problems with Lyme disease as seen in the USA

An article published in the Brazilian Journal of Microbiology entitled “Brazilian borreliosis with special emphasis on humans and horses” examines the growing number of cases in Brazil of Lyme disease, referred to, in that country, as the Lyme-like or Baggio-Yoshinari Syndrome (BYS).

The authors take an in-depth look at BYS and how it compares to Lyme disease (LD) found in the United States. Although there are slight differences between the diseases, BYS and LD share similarities on many fronts. [1] “Despite the increasing number of suspect cases, this disease [BYS] is still neglected in Brazil by the medical and veterinary communities,” writes Basile and colleagues.

BYS causes some of the same symptoms seen in Lyme disease, such as erythema migrans, arthritis, neurological symptoms and cardiac disease. Both are difficult to diagnose.

“The disease is often unrecognized, especially at secondary or tertiary stages when patients do not remember what occurred months or years before the current disease,” stated Basile. “Certainly, many cases of unrecognized chronic neurological or articular disease are in fact cases of BYS not identified and treated at early stage.”

The capybaras, a popular Brazilian house pet, is a known reservoir for ticks infected with the Lyme-like or Baggio-Yoshinari Syndrome (BYS).

The Brazilian disease can also be multisystemic. “Baggio-Yoshinari Syndrome has been reported to cause neurological, cardiac, ophthalmic, muscle, and joint alterations in humans.” Furthermore, it has been associated with a high morbidity “due to the presence of symptom recurrence, severe reactive manifestations such as autoimmunity, and the need for prolonged treatment.”

According to Basile and colleagues, the disease progresses with recurrences, “especially if antibiotic treatment is initiated later than three months after infection.” Thus, treating the disease in its early stages is critical.

Cystic forms have been described, as well. “Because motile and spiral spirochetes were never isolated or cultured in Brazil, researchers from LIM-17 assumed that the etiological agent in Brazil was present in cystic form.”

The Brazilian patients may also be suffering from co-infections, as investigators identified other microrganisms in the blood of BYS patients. Tests showed “the occurrence of microorganisms with morphological structures similar to Mycoplasma spp., Chlamydia spp., and non-flagellated spirochetes in the peripheral blood of patients with BYS who were seropositive for B. burgdorferi sensu lato,” according to Basile. “Those patients exhibited negative serology for Mycoplasma spp. and Chlamydia spp.”

Additionally, laboratory testing for BYS is unreliable. There is a low sensitivity and specificity with the ELISA, enzyme immunosorbent assay, or western blotting for B. burgdorferi, in part because these tests utilize antigens from B. burgdorferi stricto sensu from the Northern Hemisphere.

Domestic pets have been described as potential reservoirs for ticks carrying the disease. The capybaras, a large rodent and popular house pet in Brazil, has been identified as a likely reservoir and is thus a threat in spreading the disease.

Wild and domestic animals can be infected. “Studies indicate that LB [Lyme borreliosis] in horses has clinical signs similar to the disease in humans, including fever and lethargy, arthritis, polysynovitis, lameness, muscle stiffness, abortion, meningitis, cranial neuritis, radiculoneuritis and encephalitis, uveitis, and premature death of foals,” according to Basile.

The authors’ findings reminds us that the challenges faced in the United States in gaining recognition for a disease that is growing in numbers and has the potential to cause chronic, debilitating illness is not unique to our country. The Brazilian patients suffering from the Lyme-like or Baggio-Yoshinari Syndrome are struggling to conquer the same obstacles.

“Lyme disease is a condition of extreme importance because it is a zoonosis that causes physical and psychological sequelae in affected individuals. It remains poorly investigated in Brazil, especially in the field of veterinary medicine. Therefore, studies describing the unique aspects of the disease in Brazil and the etiological agents found are needed.”

References:

  1. Basile, R.C., et al., Brazilian borreliosis with special emphasis on humans and horses. Braz J Microbiol, 2016.

Update: Oliveira from the Ministry of Health, Brasilia, DF, Brazil was not able confirm Lyme-like borreliosis in Brazil in a letter in the journal Travel Medicine and Infectious Disease.1 “The interpretations of the results have not followed those recommended by the CDC.” writes Oliveira. Only three cases of Lyme-like borreliosis were identified. “This evidence reinforces the hypothesis that Lyme borreliosis does not occur in Brazil.” writes Oliveira.

  1. de Oliveira SV, Faccini-Martinez AA, Cerutti Junior C. Lack of serological evidence for Lyme-like borreliosis in Brazil. Travel Med Infect Dis. 2018.

________________

**Comment**

Another perfect example of why the CDC must go.

This corrupt, inept organization rules the world.

Another Tabletop Exercise: DHS & CISA’s Cybersecurity Exercise on Election Day in Atlanta GA

https://www.hsgac.senate.gov/media/reps/icymi-dr-paul-requests-information-on-dhs-cisas-participation-at-election-day-cybersecurity-conference/

ICYMI: Dr. Paul Requests Information on DHS & CISA’s Participation at Election Day Cybersecurity Conference

WASHINGTON, D.C. – U.S. Senator Rand Paul (R-KY), Ranking Member of the Senate Homeland Security and Governmental Affairs Committee, sent a letter to Department of Homeland Security (DHS) Secretary Alejandro Mayorkas requesting additional information regarding DHS’s and the Cybersecurity and Infrastructure Security Agency’s (CISA) attendance at a homeland security conference in Atlanta, Georgia and participation in a large-scale cybersecurity exercise on Election Day.

The letter notes over the past several months, foreign adversaries have sought to undermine confidence in our election through a series of cyberattacks aimed at the electoral process. The American public is appropriately concerned with the integrity of our election system. However, rather than monitoring cyberthreats that may occur relative to the election, senior federal officials plan to spend Election Day participating in a four-hour “Critical Infrastructure Tabletop” led by CISA staff, followed by a networking reception.

You can read the full letter HERE.

_______________

**Comment**

Have we learned nothing about these prophetical table-top exercises?

The Election Day exercise will simulate an attack on critical US infrastructure.

As investigative Jon Rappoport states:

“If bad actors were looking to mess with electronic voting, this exercise would create a reasonable cover and method. If the actors wanted to rig electronic voting and needed an excuse to explain “anomalies” in the vote count, or to explain a sudden shut-down of key voting precincts, the cyber-exercise would provide those explanations.”

CODA: You might be interested in reading the Wikipedia entry for the group, AFCEA, which is sponsoring the cyber-security exercise. It reads in part:

“Armed Forces Communications & Electronics Association International (AFCEA), established in 1946, is a nonprofit membership association serving the military, government, industry, and academia as a forum for advancing professional knowledge and relationships in the fields of communications, information technology, intelligence and global security. AFCEA provides a forum for military, government, academic and industry communities with altogether more than 30,000 members. AFCEA supports local chapters, sponsors events, publishes a magazine, promotes STEM education and provides member benefits.

SIGNAL is a monthly AFCEA news magazine covering topics on command, control, communications, computers, intelligence, surveillance and reconnaissance (C4ISR); information security;  cybersecurity; research and development; artificial intelligence, machine learning, big data, cloud technologies,  electronics; and homeland security.

How DMSO Treats ‘Incurable’ Autoimmune and Contractile Disorders

https://www.midwesterndoctor.com/p/how-dmso-treats-incurable-autoimmune?

How DMSO Treats “Incurable” Autoimmune and Contractile Disorders

The decades of research that could have prevented an immense amount of human suffering

A Midwestern Doctor

Story at a Glance:

•DMSO is a remarkably safe substance that effectively treats a variety of conditions (e.g., chronic pain, acute injuries, and strokes) that medicine has struggled with for decades. Many readers here have already experienced profound benefits from using it.

•DMSO is a powerful (but safe) anti-inflammatory agent that is often extremely helpful for autoimmune conditions. For example, it’s frequently used to treat asthma, inflammatory bowel diseases (e.g., ulcerative colitis and irritable bowel syndrome), interstitial cystitis (painful bladder syndrome), ITP, lupus, multiple sclerosis, myasthenia gravis, scleroderma, Sjogren’s syndrome, and uveitis.

•DMSO is also remarkably effective at stabilizing and refolding proteins. This allows it to treat a variety of “untreatable” genetic disorders, and conditions characterized by the abnormal accumulation of misfolded proteins in the body (e.g., amyloidosis) or chronic deposits of excessive contractile collagen (e.g., surgical scars, abdominal adhesions, Dupuytren’s contractures, and Peyronie’s disease). Two of the most dramatic examples of this are scleroderma and fibrodysplasia ossificans progressiva—both “untreatable” conditions where DMSO can provide truly lifesaving benefits.

•In this article, I will present the wealth of evidence substantiating each of those uses, share my theory on how the unusual antimicrobial properties of DMSO explain some of these benefits, and present DMSO treatment protocols for many of those disorders. Additionally, since many readers requested it, I put together a simplified guide on how to use DMSO orally or topically.

Dimethyl sulfoxide (DMSO) is a simple and readily available naturally occurring chemical that rapidly enters the body through the skin and has a variety of remarkable therapeutic properties. When it was discovered, its proponents believed it (much like antibiotics) represented a new therapeutic principle in medicine and once adopted, would completely change how medicine was practiced. Unfortunately, the FDA conducted a reprehensible campaign against it and was able to successfully bury it.

Since there are so many uses for DMSO, to effectively present them, I’ve had to comb through well over ten thousand pages of scientific literature and then order them into a logical sequence (of what will be roughly a nine-part series). For instance, in the first part of this series, I discussed how DMSO completely changed the management of neurological injuries and showed that were it to be adopted, millions would no longer be disabled from the common emergencies we view as insurmountable within the current medical paradigm (e.g., frequent disabilities from stroke and the inevitability of becoming a paraplegic after a spinal cord injury).  (See link for article)

_______________

**Comment**

DMSO has been a well-kept secret among those who are desperate enough to learn about it.  If you are new to it, go here for a basic article and helpful videos that explain it in layman’s terms as well as MSM, a derivative of DMSO.  I also include helpful info on dosages, etc.

I’ve used it many times over the years and always with good, measurable results.

I highly recommend reading a Midwestern Doctor’s thorough article in full as the good doctor goes through many conditions DMSO treats as well as the scientific studies and experiences behind them.

He goes through DMSO use for MS, Lupus, Asthma, Interstitial cystitis, Uveitis, inflammatory bowel diseases, Myasthenia gravis, Sjogren’s syndrome, as well as the possible bacterial component (even the challenges of pleomorphism) in many of these conditions and how DMSO is bacteriostatic, antiviral and antifungal.

You can use DMSO topically (recommended for newbies first), orally, intramuscularly, and intravenously.

Its only downsides are the tingling, itching in topical applications as well as the odor for all applications.  The severity of smell is commiserate with the amount used.

Go here for more:

[DMSO’s] virtues were extolled in another Congressional Hearing, this one taking place on March 24, 1980, before Claude Pepper’s Select House Committee on Aging. The drug was DMSO, and the opponent, as in Senator Johnson’s Hearing, was once again the FDA.

As with Ivermectin, the FDA [Bureau of Drugs] Director, Dr. J. Richard Crout, explained—tongue in cheek—that the agency would be the first to advocate DMSO’s use if it had only evidence that it worked.

“The FDA is willing, indeed anxious, to approve DMSO for such uses whenever controlled trials meeting the statutory standard are available [Page 61].

In place of Dr. Pierre Kory sat Dr. Stanley Jacob, a professor of surgery at the University of Oregon Medical School. Dr. Jacob was the dynamic Harvard-trained physician who headed the University of Oregon Transplant Program and had discovered many of the benefits of DMSO after first using it as a cryoprotectant.

Dr. Jacob testified before the committee in 1980, just as Dr. Kory would do some 40 years later, in 2020, and told an unbelievable story to a group of Washington D.C. insiders about the miraculous benefits of an almost unknown drug.

Like Dr. Kory, he has been proven correct.

Dr. Kory authored a book about his experience entitled The War Against Ivermectin: The Medicine that Saved Millions and Could Have Ended the Pandemic.

Dr. Jacob authored the book Dimethyl Sulfoxide (DMSO) in Trauma and Disease.

DMSO met the same fate in 1980 as Ivermectin did following Dr. Kory’s Congressional hearing in 2020: The FDA buried it.

The FDA shut down research on DMSO in 1965 after an estimated 100,000 patients began enjoying its benefits.

Many states have laws that steer licensed physicians away from prescribing DMSO for anything other than interstitial cystitis.

Sound familiar?