https://thevaccinereaction.org/2022/05/monkeypox-cases-in-u-s-coincide-with-vaccine-purchases-by-barda/

Monkeypox Cases in U.S Coincide With Vaccine Purchases by BARDA

______________________

**UPDATE May, 2022**

I’m reminded of the following fact:Source

The CDC admits that people recently vaccinated with the existing FDA-approved smallpox vaccine can shed the virus in the vaccine to others.

Given the risk for vaccinia virus transmission from recently vaccinated persons through inadvertent inoculation, nonemergency use of ACAM2000 is also contraindicated in persons with household contacts with a history or presence of atopic dermatitis, other active exfoliative skin conditions (e.g., eczema, burns, impetigo, varicella zoster, herpes, severe acne, severe diaper dermatitis with extensive areas of denuded skin, psoriasis, or Darier disease [keratosis follicularis]); conditions associated with immunosuppression (e.g., HIV/AIDS, leukemia, lymphoma, generalized malignancy, solid organ transplantation, or therapy with alkylating agents, antimetabolites, radiation, TNF inhibitors, or high-dose corticosteroids [i.e., ≥2 mg/kg body weight or 20 mg/day of prednisone or its equivalent for ≥2 weeks], hematopoietic stem cell transplant recipients <24 months post-transplant or ≥24 months, but who have graft-versus-host disease or disease relapse, or autoimmune disease [e.g. systemic lupus erythematosus] with immunodeficiency as a clinical component); household contacts aged <1 year; and household contacts who are pregnant (recommendation category: A, evidence type 2 [Box]). Household contacts include persons with prolonged intimate contact with the potential vaccinee (e.g. sexual contacts) and others who might have direct contact with the vaccination site or with potentially contaminated materials (e.g., dressings or clothing). ACIP also does not recommend nonemergency vaccination with ACAM2000 for children and adolescents aged <18 years.

And guess what one of those side effects is that shares a common side effect with the COVID-19 vaccines?

Myopericarditis has also been associated with ACAM2000 and is estimated to occur at a rate of 5.7 per 1,000 primary vaccinees based on clinical trial data. (Source.)

Yes, weakened hearts resulting in heart disease is also a side effect of the smallpox vaccines.
You can read about all the other Precautions and Contraindications for this FDA-approved smallpox vaccine here on the CDC website.

https://palexander.substack.com/p/smallpox-vaccine-to-prevent-monkey?

Smallpox vaccine to prevent monkeypox could cause global smallpox (vaccinia) epidemic; I warn, do not be that stupid, understand you have damaged the immune systems of m (b)illions with COVID vaccines

Experts are saying smallpox vax 85% effective in monkey pox; this is NOT good news, for millions/billions are now immunocompromised from COVID vax; CDC sounds alarm for gay-bisexual men

May 21, 2022

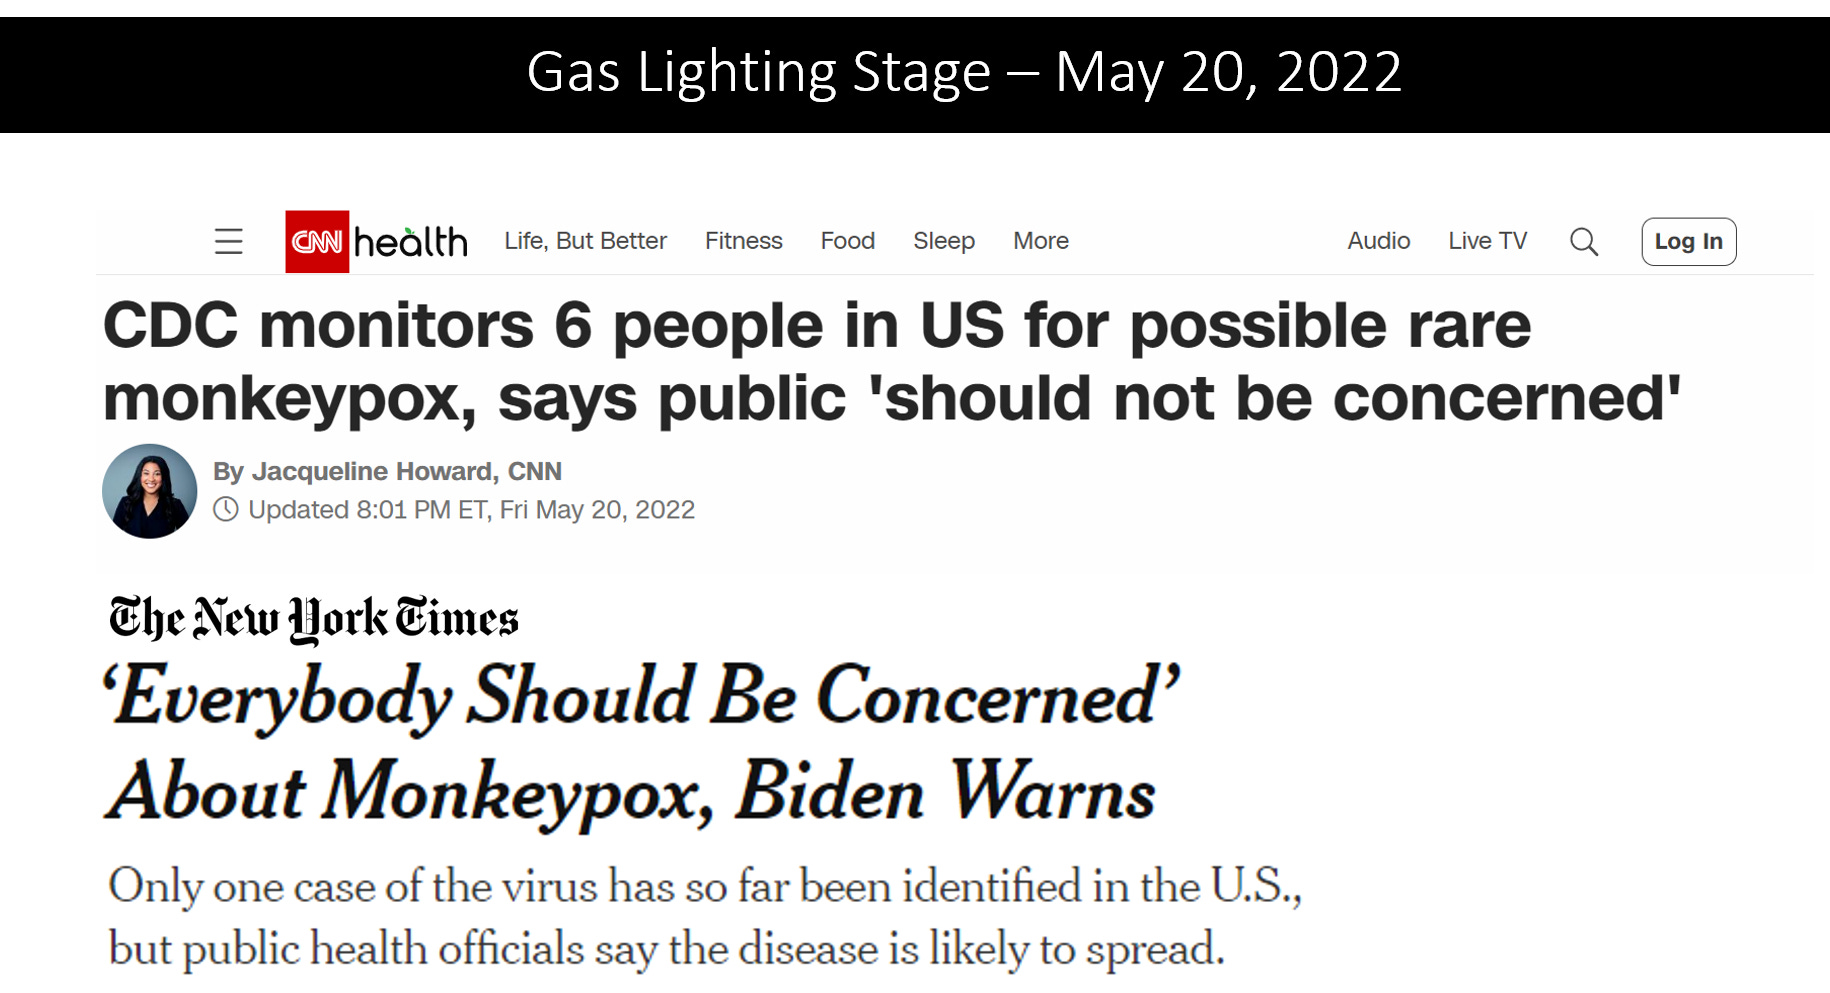
First, I would ask POTUS Biden to go back out to the nation and address his prior statement about monkeypox risk which was misinformed and served to scare the nation (‘Everybody Should Be Concerned’ About Monkeypox, Biden Warns’). There was no basis for Biden to say what he did and whomever cleared him to say that e.g. para ‘concerned about monkeypox’, should be fired. This has caused needless concern by the general population. The legacy media must be shut down for the utter reckless manner in which they report on this monkeypox and it is clear they are seeking to cause panic and hysteria when the general population, children, low-risk persons etc. are not at risk. Based on all we know today, the fear mongering MUST be stopped.

Now an i) update from CDC on the risk-group that monkeypox is focused in (as of Monday 23rd May 2022), ii) updated evidence of transmission by WHO expert, iii) some preliminary thoughts on the failed COVID mRNA vaccine, iv) the WHO pandemic treaty, and then v) further details on this issue of smallpox vaccination and monkeypox with a special shoutout to Dr. Vinay Prasad for his balance and common sense in this.  (See link for article)

___________________

**Comment**

Highlights on smallpox vaccination & monkeypox (I highly recommend reading the entire article):

  • By initiating smallpox vaccination, if it contains smallpox or viccinia virus, smallpox and vaccinia could be re-introduced to populations and would be catastrophic.
  • Monkeypox should be fought with tried and tested successful focused public health containment tools such as acute contact tracing and isolating infected/symptomatic people, not mass vaccination of the population.
  • Even vaccinating the identified at-risk group – bisexual and homosexuals, needs careful study for HIV/AIDS patients who have been COVID “vaccinated” now have 2 existing challenges beyond the risk of monkeypox as their immune systems are suppressed due to HIV as well as being compromised/dysregulated due to the COVID shots.  Lyme/MSIDS patients would also fit into this category.
  • The immune system is suppressed for 2 weeks post COVID shots leaving people vulnerable to COVID and other viral infections/pathogens as well as the fact white blood cells are depressed during this time and explains why there are so many adverse events, hospitalizations and deaths in the first 2-3 weeks post ‘vaccine’.  The fact the CDC/NIH do not count these as occurring in the ‘vaccinated’ is fraudulent & done to make a ‘pandemic of the unvaccinated’ narrative. 
  • Corrupt public health ‘officials’ did not warn the ‘vaccinated’ of their vulnerability post jab and that they may be at risk of developing a broad range of illnesses including cancers.  Please see Dr. Urso’s 5-minute video explaining about the explosion of cancer and latent disease (reactivated latent viruses, etc) post COVID shots.
  • It appears to be transmitted as a STD, although this has been debated.
  • As of today, there have been ZERO deaths due to monkeypox cases in Europe and North America.
  • Do not take any more COVID shots. COVID is continuing due to the continued “vaccination” with non-sterilizing, non-neutralizing shots with antibodies that are targeting the infectiousness of the virus (the spike).
  • “Increasing the number of vaccinated persons will inevitably lead to increases in morbidity and mortality due to vaccinia, and current evidence suggests net harm would result if smallpox vaccine were made available to the general public on a voluntary basis.”  SOURCE
  • Valid conjecture is COVID shots suppressing immune systems has caused monkeypox to emerge in Europe and N. America. COVID ‘vaccinated’ could be at dramatic risk to monkeypox and a host of other pathogens/viruses.
  • The smallpox vaccine can potentially drive cases of smallpox and vaccinia in COVID ‘vaccinated’.

“Smallpox vaccine is less safe than other vaccines routinely used today. The vaccine is associated with known adverse effects that range from mild to severe. Mild vaccine reactions include formation of satellite lesions, fever, muscle aches, regional lymphadenopathy, fatigue, headache, nausea, rashes, and soreness at the vaccination site.13,18,19 A recent clinical trial reported that more than one-third of vaccine recipients missed days of work or school because of these mild vaccine-related symptoms.18…

In the 1960s, serious adverse events associated with smallpox vaccination in the United States included death (1/million vaccinations), progressive vaccinia (1.5/million vaccinations), eczema vaccinatum (39/million vaccinations), postvaccinial encephalitis (12/million vaccinations), and generalized vaccinia (241/million vaccinations).20 Adverse events were approximately ten times more common among those vaccinated for the first time compared to revaccinees.20 Fatality rates were also four times higher for primary vaccinees compared to revaccinees.21…

Progressive vaccinia (a.k.a. vaccinia necrosum, vaccinia gangrenosum) is defined as an uncontrolled replication of vaccinia virus at the vaccination site that leads to a slow and progressive necrosis of surrounding tissue.24 Satellite necrotic lesions typically develop, and ultimately vaccinia virus may be found in other tissues and organs.24 This condition typically affects individuals with incompetent immune systems.24,25 The cardinal clinical signs of progressive vaccinia include an unhealed vaccination site >15 days post vaccination, and the lack of inflammation or an immune response at the vaccination site.24,25 Untreated progressive vaccinia is fatal, but treatment with VIG or the antiviral cidofovir may be effective in some cases.”  SOURCE

“There are more than 100 million doses of another vaccine, ACAM2000. This is an older generation vaccine meant to prevent smallpox, but could also be used to prevent monkeypox, McQuiston said. That vaccine, however, can come with significant side effects, and would be considered only for very close personal contacts of those with monkeypox infection, as well as health care workers.” SOURCE

Dr. Alexander is a COVID-19 Consultant Researcher in EBM, Research Methodology, and Clinical Epidemiology and informally provides support to some members of the US Congress and Senate.

For more:
https://thehighwire.com/videos/tony-fauci-americas-gaslighting-expert/

May 20, 2022

Out of the Horse’s Mouth: Social Distancing, School & Business Closures, Wearing Masks.  ‘Whatever it Takes’

– But has the gall to say we never locked down…..

Fauci gives viewers a teachable moment in gaslighting, something Lyme/MSIDS patients are quite experienced with, as he attempts to tell Americans that they didn’t experience any lockdowns over the last two years.

“Now is the time to do what you are told.” ~ Dr. Anthony Fauci

For more:

BTW: Fauci’s wife, U.S. Bioethics Chief at the NIH, just published a paper telling corporations they can ethically ‘pressure employees’ and ’embarrass vaccine resistors.’  The paper posits ‘vaccine’ mandates can “be ethically appropriate” if there is “clear articulation about the consequences of not complying with the policy.”  The paper also gives the tactic of using “targeted statistics (such as 75% of the company or unit have been vaccinated) to spur competition or even implicitly embarrass vaccine resistors.”

The unearthed paper comes amidst controversy over Fauci’s decision to fund research on “killer” bat coronaviruses at the Wuhan Institute of Virology. His wife’s supervision of ethics of NIH research and policy are a conflict of interest given Fauci’s role in shaping COVID-19 response and ‘vaccination’ guidelines.  Source

And speaking of papers…..

https://thenationalpulse.com/2022/05/22/wuhan-assembled-monkeypox-strains/

The Infamous Wuhan Lab Recently Assembled Monkeypox Strains Using Methods Flagged For Creating ‘Contagious Pathogens’

Natalie Winters

May 22, 2022

The Wuhan Institute of Virology assembled a monkeypox virus genome, allowing the virus to be identified through PCR tests, using a method researchers flagged for potentially creating a “contagious pathogen,” The National Pulse can reveal.

The study was first published in February 2022, just months before the latest international outbreak of monkeypox cases which appear to have now reached the United States. The publication’s Editor-in-Chief is Wuhan’s infamous “bat lady,” Shi Zhengli, who is the lab’s premier bat coronavirus researcher and a recipient of funds from Anthony Fauci through Peter Daszak’s EcoHealth Alliance.

The paper, which was authored by nine Wuhan Institute of Virology researchers and published in the lab’s quarterly scientific journal Virologica Sinica, also follows the wide-scale use of Polymerase Chain Reaction (PCR) tests to identify COVID-19-positive individuals.  (See link for article)

___________________

SUMMARY:

  • The paper is titled: “Efficient Assembly of a Large Fragment of Monkeypox Virus Genome as a qPCR Template Using Dual-Selection Based Transformation-Associated Recombination.”
  • Monkey pox viruses – referred to as “MPXVs” in the paper – have strains that are “more pathogenic and [have] been reported to infect humans in various parts of the world.”
  • The paper acknowledged that TAR “applied in virological research could also raise potential security concerns, especially when the assembled product contains a full set of genetic material that can be recovered into a contagious pathogen.”
  • While the study conducted experiments on mice and chicken, it noted that H7N9 variants are “also highly transmissible in ferrets, posing the threats of pandemic potential in humans.”
  • The Wuhan lab conducted similar research into strains of bat coronaviruses that could infect humans and has admitted the lab lacks proper safety protocols.
For a brief bit of history:

In 1958, lab monkeys were shipped from Singapore to Denmark of which 30% developed a “pox-like skin eruption” 7-9 weeks after arrival, according to a March 1973 paper  published in what is now the peer-reviewed journal Microbiology and Molecular Biology Reviews.

    • A year later 200 lab monkeys in a Philadelphia Merck facility were infected.
    • There were outbreaks at the Walter Reed Army Institute in Washington D.C.
    • There were outbreaks at the Zoological Garden in the Netherlands in 1962 & 1964.
    • The WHO reported FOUR more pox-like outbreaks in U.S. lab monkeys from 1965-67.

Monkeypox did not affect humans until 1970 in Africa and researchers made sure to highlight the six infected were not vaccinated against smallpox.

History shows monkeypox came from Singapore and was enhanced via gain of function in the U.S., but the narrative is that it originated in Africa in 1958 but nobody explains where or how.  Source

Deja Vu

____________________

https://popularrationalism.substack.com/p/12-monkeypox-facts-what-you-need

12 Monkeypox Facts: What You Need to Know

After a deluge of requests from people, here’s the essential information you need to know.

I have to start this article by saying I loathe articles with titles. My immediate reaction to seeing these in MSM is “all you WANT me to know”.

So, here’s a list of unannotated (mostly) facts.

  1. They ran a simulation on a monkeypox outbreak in March 2021. Who? Here.
  2. FDA approved of Tecovirimat, (aka TPOXX), an antiviral that is effective against Monkeypox, in July 2018.
  3. Transmission requires intimate (very close) contact (although it’s not an STD)
  4. CDC says you should not be concerned. Biden says you should.
  5. There are about 1,000 doses of vaccine for Pox viruses (smallpox and monkeypox) that could be used on patients in the US. CDC says for those at “high risk). So that means no one.
  6. Doctors are being told to be on the lookout for Monkeypox cases.
  7. It’s been around since 1958, about the time scientists were injecting African subjects with blood products from monkeys to see which viruses might be transmissible. Zika virus came into our species about the same time.
  8. If you see an overturned truckload of escaped monkeys, keep driving. Don’t stop and “help”, or, according to the official narrative, a monkey might “hiss” in your face.
  9. There are only about 200 recent cases worldwide.
  10. WHO’s Interim Guidance suggests the use of RT-PCR with positive controls. (What???? Where were the positive controls for SARS-CoV-2????)
  11. WHO and CDC have both said it can be “contained”.
  12. Moderna has jumped onto the Monkeypox vaccine bandwagon.More later.

___________________

**Comment**

Clarification: Monkeypox IS spreading through sexual contact, but is not considered a STD.  See this article for more:  https://fortune.com/2022/05/23/monkeypox-spread-sexual-contact-not-sexually-transmitted-infection-who/  This point is being debated.

For more:  https://madisonarealymesupportgroup.com/2022/05/23/monkeypox-outbreak-follows-germ-game-preparations/

https://www.globallymealliance.org/videos/two-best-friends-are-fighting-lyme-disease-together

Chase and Natalie, two best friends, are supporting one another on their Lyme journeys.
Watch Here:

Chase and Natalie have both been diagnosed with Lyme disease. They discuss the challenges they face as young adults battling such a debilitating disease. They try to embody a positive attitude as they receive their treatments. Natalie is in a wheelchair because the Lyme has affected the muscles in her legs. She also has been dealing with severe pain in her jaw for the past three years, having received four surgeries. They both talk about how those with Lyme may appear healthy on social media, but you never know what’s really happening behind the scenes. By sharing their experiences, they are spreading awareness and helping others with Lyme to feel less alone.

____________________

**Comment**

What a perfect example of how support makes all the difference.  Having traveled this journey myself I understand the pain, confusion, fear, and gaslighting common with Lyme/MSIDS.  To see two people laughing about what they are going through perfectly demonstrates the importance of friendship and support. One of the worst aspects of this journey is not being believed.

For more:

I really appreciated her comment about being careful about accepting advice from those who are not infected as they truly don’t know what it’s like and what you are going through.  One of the most difficult times for me was when a well-meaning homeschool, Christian mom told me I was in sin for not trusting God by taking antibiotics. Being faithful is important to me but these antibiotics were saving my life.

Be careful what you tell others.
Words have the power of life and death.  Tread carefully.

On the other hand, I vividly remember my son’s marital arts coach tell me, “Alicia, Lyme doesn’t stand a chance against your indomitable spirit.”

That one floored me, because I felt anything but indomitable at the time.  Barely making it through each day, and shuffling through the house trying to just keep the ball rolling, this man put hope into a very weary heart. I will never forget his words.  They still put a clip into my steps.

Let your words inspire and be a catalyst for healing.

https://www.globallymealliance.org/blog/lyme-disease-and-bells-palsy-new-considerations-for-differential-diagnosis

Neurological disorder resulting from COVID-19 may confound Lyme disease diagnosis.

Bell’s palsy is a non-progressive neurological disorder of one of the facial nerves (7th cranial nerve). Bell’s palsy is fundamentally a clinical diagnosis with no specific laboratory test to confirm the disorder.1 This disorder is characterized by the sudden onset of facial paralysis that may be preceded by a slight fever, pain behind the ear on the affected side, a stiff neck, and weakness and/or stiffness on one side of the face. Paralysis results from decreased blood supply and/or compression of the 7th cranial nerve. This compression can be caused by inflammation of the tissue around the nerve. Approximately 40,000 individuals are diagnosed with Bell’s palsy in the US each year, affecting males and females in equal numbers.

The exact cause of Bell’s palsy is not known, however, bacterial infections (like Lyme disease),1 and viral infections (like Herpes and Epstein-bar virus),2 immune disorders (like Guillain-Barre syndrome) and neuropathies (like brain tumors), are frequently implicated as a cause.

Neurological Lyme Disease and Bell’s Palsy

Bell’s palsy is the most common manifestation of Lyme neuroborreliosis (or neurological Lyme disease) in the US.1 Clues pointing toward Lyme neuroborreliosis include a history of rash compatible with a bull’s-eye erythema migrans (EM) rash or fever in the weks preceding the palsy. Treatment with antibiotic therapy is highly effective, and most patients will fully recover facial nerve function.1 According to Dr. Nate Jowett, M.D. (Massachusetts General Brigham) ~5% of patients with Lyme disease will develop some degree of sudden facial weakness, where one or both sides of the face droop. This tends to occur seven- to 21-days after tick exposure in infected patients.

COVID-19 and Bell’s Palsy

More recently, though a rare occurrence, Bell’s palsy has also been associated with COVID-193 and adverse drug reactions following mRNA-based vaccination for COVID-19.4-7 A recent systematic review found 20 COVID-19 patients whose only major neurological manifestation was Bell’s palsy. In a separate report, according to Colella et al.,an otherwise healthy 37-year-old white Caucasian male developed Bell’s palsy within days after COVID-19 vaccination. Of note, there was no history of trauma, cold or other identifiable triggers reported and no other signs or symptoms were present. Specifically, no history of a preceding infection, including recent SARS-CoV-2 infection, was reported and there was no evidence of a cutaneous rash suggestive of Herpes zoster infection.6 Lack of a cutaneous rash (e.g., EM) might also rule out Lyme disease, though it should be noted that EM may be missed or not develop in some Lyme disease cases.8

Bell’s palsy associated with SARS-CoV-2 infection was either the first neurological manifestation or appeared two to 28 days after the appearance of other clinical manifestations.3 When associated with COVID-19 vaccination Bell’s palsy developed between three and 30 days post second-dose vaccination.6 The FDA points out that cases of Bell’s palsy in vaccine groups did not represent a frequency above that expected in the general population and concluded that currently available information was insufficient to determine a causal relationship with the vaccine. Nevertheless, they also recommend surveillance for cases of Bell’s palsy with deployment of the vaccine into larger populations.6

Since the time frames for onset of Bell’s palsy associated with Lyme disease and SARS-CoV-2 infection or COVID-19 vaccination overlaps, it is important for front-line physicians to be aware that when faced with differentially diagnosing a patient that presents with Bell’s palsy they should consider:

  1. The prevalence of ticks and Lyme disease in the geographic area in which the patient resides
  2. Case history of the individual that may increase the risk of coming into contact with ticks and contracting Lyme disease (time of year, outdoor activities, pets, ), finding a tick on themselves, and/or travel to a Lyme-endemic area to name a few
  3. Other symptoms consistent with Lyme disease (g., EM, arthritis, carditis, other neurological complications, etc.)
  4. Timing of the onset of Bell’s palsy and when they contracted COVID-19 or underwent vaccination for COVID-19

In conclusion, the COVID-19 pandemic, in addition to causing a whole new set of public health challenges associated with SARS-CoV-2 infections, has also further confounded physicians’ efforts to distinguish Lyme neuroborreliosis from other disorders that cause neurological disease. It is recognition of these complexities that leads GLA to invest financial resources and support research that will ensure rapid and accurate diagnosis and effective treatment of Lyme neuroborreliosis.

REFERENCES

1          Marques, A., Okpali, G., Liepshutz, K. & Ortega-Villa, A. M. Characteristics and outcome of facial nerve palsy from Lyme neuroborreliosis in the United States. Ann Clin Transl Neurol 9, 41-49, doi:10.1002/acn3.51488 (2022).

2          Zhang, W. et al. The etiology of Bell’s palsy: a review. J Neurol 267, 1896-1905, doi:10.1007/s00415-019-09282-4 (2020).

3          Gupta, S., Jawanda, M. K., Taneja, N. & Taneja, T. A systematic review of Bell’s Palsy as the only major neurological manifestation in COVID-19 patients. J Clin Neurosci 90, 284-292, doi:10.1016/j.jocn.2021.06.016 (2021).

4          Cirillo, N. & Doan, R. The association between COVID-19 vaccination and Bell’s palsy. Lancet Infect Dis 22, 5-6, doi:10.1016/S1473-3099(21)00467-9 (2022).

5          Cirillo, N. & Doan, R. Bell’s palsy and SARS-CoV-2 vaccines-an unfolding story. Lancet Infect Dis 21, 1210-1211, doi:10.1016/S1473-3099(21)00273-5 (2021).

6          Colella, G., Orlandi, M. & Cirillo, N. Bell’s palsy following COVID-19 vaccination. J Neurol 268, 3589-3591, doi:10.1007/s00415-021-10462-4 (2021).

7          Cirillo, N. Reported orofacial adverse effects of COVID-19 vaccines: The knowns and the unknowns. J Oral Pathol Med 50, 424-427, doi:10.1111/jop.13165 (2021).

8          Schutzer, S. E. et al. Atypical erythema migrans in patients with PCR-positive Lyme disease. Emerg Infect Dis19, 815-817, doi:10.3201/eid1905.120796 (2013).

__________________
For more:

Eleven month old DIES from mask asphyxiation in Taiwan.

https://www.medrxiv.org/content/10.1101/2022.05.10.22274813v1

Inhaled CO2 concentration while wearing face masks: a pilot study using capnography

ABSTRACT

None of the available evaluations of the inhaled air carbon dioxide (CO2) concentration, while wearing face masks, used professional, real-time capnography with water-removal tubing. We measured the end-tidal CO2 using professional side-stream capnography, with water-removing tubing (Rad-97™ capnograph), at rest, (1) without masks, (2) wearing a surgical mask, and (3) wearing a FFP2 respirator, in 102 healthy volunteers aged 10-90 years, from the general population of Ferrara province, Italy. The inhaled air CO2 concentration was then computed as: ((mask volume × end-tidal CO2) + ((tidal volume – mask volume) × ambient air CO2)) / tidal volume).

The mean CO2 concentration was 4965±1047 ppm with surgical masks, and 9396±2254 ppm with FFP2 respirators. The proportion of the sample showing a CO2 concentration higher than the 5000 ppm acceptable exposure threshold recommended for workers was 40.2% while wearing surgical masks and 99.0% while wearing FFP2 respirators

The mean blood oxygen saturation remained >96%, and the mean end-tidal CO2 <33 mmHg. Adjusting for age, gender, BMI, and smoking, the inhaled air CO2 concentration significantly increased with increasing respiratory rate (with a mean of 10,143±2782 ppm among the participants taking 18 or more breaths per minute, while wearing FFP2 respirators), and was higher among the minors, who showed a mean CO2 concentration of 12,847±2898 ppm, while wearing FFP2 respirators. If these results will be confirmed, the current guidelines on mask-wearing could be updated to integrate recommendations for slow breathing and a more targeted use when contagion risk is low.

https://thehighwire.com/videos/new-science-shows-mask-harms/  Video Here  (Approx. 13 Min)

NEW SCIENCE SHOWS MASK HARMS

The mask insanity may have reached its peak this week when unmasked stage actress, Patti LuPone, unleashed a tirade on an audience member for letting her mask slide below her nose, despite the lack of studies from the CDC proving mask efficacy against the spread of Covid-19. In fact, a new study out of Italy concluded that wearing a mask increases levels of inhaled CO2.

A study called “Correlation Between Mask Compliance & COVID-19 Outcomes in Europe found:

  • masks were unable to reduce COVID transmission 
  • countries with high levels of mask usage did not perform better than those with low usage
  • there was moderate positive correlation between mask usage and DEATHS

For more:

What nobody is touching with a 10-foot-pole is the 80 fold increase in mask-littering due to mask mandates and the impact on animal life as well as the environment.  But none of that matters in the topsy-turvy world of COVID.