https://www.globallymealliance.org/blog/melissas-battle-against-lyme-and-bartonella

Melissa Mclnerney is sharing her story in order to raise awareness for Lyme disease and Bartonella.

I was bitten by a tick while hiking to Robert Frost’s house in Bennington, Vermont. I found it stuck to my rib cage when I showered later that day. I returned home to Denver, Colorado and ten days later got sick with flu-like symptoms. My primary care doctor told me that since I did not have a bull’s eye rash, I could not have Lyme. He was following the CDC guidelines for diagnosing Lyme. I was unschooled in Lyme disease and I wanted to believe his words. Big mistake.

Finally, we were able to get all three of my infections under control. One, however, keeps coming back. That one is Bartonella.

Fast forward eighteen months. I am sitting in the waiting room of an LLMD in Albany, New York. There is an LLMD in Colorado, but the next available appointment was six months out. He has my test results in front of him. A Western blot test confirmed his suspicions that I had Bartonella. I also tested positive on two bands for borrelia. He made a clinical diagnosis for babesia. For the next three years, I was sick almost all of the time or herxing. Finally, we were able to get all three of my infections under control. One, however, keeps coming back. That one is Bartonella.

I had so many symptoms with Bartonella. The top symptoms were neurological: rage, depression, anxiety, depersonalization, and debilitating cognitive decline. These were the days when my daughter drove me to the grocery store (because I forgot how to drive a stick), made sure I got what was on my list, and carried my purse and paid (I left my purse at the store more than once). I couldn’t remember words. I had a system to make sure I was taking all of my medications; I moved them from one side of the sink to the other, one with a sticky note that said “am”, the other “pm.” I had piercing headaches and neck aches. My teeth hurt. My eyes played tricks on me and itched and burned. I had chronic sore throats and zings in my hands and feet. I was exhausted all the time. My liver ached. I had pain in my feet. Many mornings I hobbled into the bathroom wondering if this was going to be my life now.

Seven years later, I am mostly in remission, and my relapses are almost always Bartonella. It’s difficult to get any kind of consensus on why Bartonella is emerging as one of the co-infections that becomes chronic in some patients. When a flare-up begins, I don’t often recognize the sore throat, neck ache and brain fog. I’m amazed each time it happens. I obsessively read the symptoms and tick them off one by one. I start to find mistakes in my writing. Housework becomes more difficult. I cry for no reason and anxiously fret over my life. Nothing is as I intended it to be. I was in Vermont for an MFA in Creative Writing, a degree I hoped to parlay into teaching, or a job in writing and editing until I was able to retire in ten or fifteen years. That didn’t happen.

thumbnail_MelissaKatieWhat happened is I have had to rethink my life. I chose to simplify things by selling my big house and buying a smaller townhome with my daughter. I live with my ninety-three-year-old dad in Tucson most of the year in a retirement community. I have reduced bills, stress, and responsibilities to the bare minimum, so I can prepare for my future, whatever that may be. I need the time and space for relapses. I look for silver linings (and I do, every single day). I can spend precious time with my dad. We lean on each other. In turn, my daughter and I are extremely close. We also take care of each other, all three of us, in a way I had never imagined before Lyme. I contribute in the ways that I can, and continue to hope. In some ways, I am healthier than ever, the demands of Lyme forcing me to get enough sleep and exercise (I walk the dog every day, and swim and lift weights when I am well enough). I have found an anti-inflammatory diet (no gluten, dairy, sugar, caffeine, or alcohol) helpful. I have a therapist who has been invaluable by helping me stay flexible as I adapt to my circumstances.

When a relapse happens, I have to let go and simply hold on until it is over. It’s not the physical discomforts that make this difficult, but the mental ones. The neurological impact of Bartonella has been, and continues to be, the worst of all of the symptoms I have experienced. Whatever terms I choose to use (a preview of dementia, an inflamed brain, madness) none of them do justice to it. I cope by reading everything I can about Lyme. I find solace in knowing that I am not alone in my suffering. GLA is one of the sites I turn to. We need funds and support to help with every facet of Lyme, including debilitating co-infections like Bartonella.

***

GLA is currently fundraising for The Bartonella Discovery Program, a research project bringing together some of the top researchers world-wide who are experts on Bartonellosis. These researchers will learn more about the bacteria and which treatments are most likely to cure all patients. None of the work GLA has accomplished would be possible without your support.

GLA Contributor

Melissa Mclnerney

GLA Contributor

*Opinions expressed by contributors are their own. Melissa McInerney earned her MFA in fiction from Bennington College in 2015 and her BA from the University of Texas Austin in 1981. She has written a series of short stories about growing up in boomtown Houston and blogs about living with Lyme disease at http://lifeandlyme.net/blog/. Her work has appeared in Logophile, Blue Lake Review, Good Works Review, Jet Fuel Review and https://www.fiftiness.com/. She tolerated the south and its unrelenting heat for years. Now she thrives in Colorado with her grown daughter, three dogs, and a cat. She hikes, swims, avoids skiing, and is learning Spanish.

___________________

For more:

While fact-checkers & corrupt public health ‘authorities,’ who aren’t even monitoring VAERS reports for safety signals, continue to dismiss and mock fertility concerns, the truth is eventually coming out.

Please watch this important 2 Min. video of highly experienced German pathologist Dr. Arne Burkhardt who shows that sperm is almost completely replaced by Spike Protein in the “vaccinated.”  

If I were a woman in fertile age, I would not plan a motherhood from a man who has been vaccinated’.” ~ Dr. Arne Burkhardt

And while the authors of the study qualify their findings with a positive spin by reporting that after five months sperm levels recover, others have pointed out the actual data do not support this and sperm levels actually continue to decline.

As Alex Berenson states, positive spin is now a commonplace tactic among researchers who are under overwhelming political pressure, but who discover issues which raise concerns about the shots. These researchers say one thing, but publish the data which shows another thing.

To downplay the unpleasant reality, the researchers focused on the fact that median rather than average counts did recover after five months, but by using the median rather than the average, it will hide extreme outliers such as men with near-zero sperm counts, which is more important than the median change.

____________________

https://onlinelibrary.wiley.com/doi/10.1111/andr.13209

Covid-19 vaccination BNT162b2 temporarily impairs semen concentration and total motile count among semen donors

First published: 17 June 2022

CAPSULE: A retrospective longitudinal multicenter comparison reveals temporary sperm concentration reduction 3 months post BNT162b2 vaccination and later recovery. Semen volume and motility remain stable.

This article has been accepted for publication and undergone full peer review but has not been through the copy editing, typesetting, pagination and proofreading process, which may lead to differences between this version and the Version of Record. Please cite this article as https://doi.org/10.1111/andr.13209

Abstract

Background

The development of covid-19 vaccinations represents a notable scientific achievement. Nevertheless, concerns have been raised regarding their possible detrimental impact on male fertility

Objective

To investigate the effect of covid-19 BNT162b2 (Pfizer) vaccine on semen parameters among semen donors (SD).

Methods

37 SD from three sperm banks that provided 220 samples, were included in that retrospective longitudinal multicenter cohort study. BNT162b2 vaccination included two doses, and vaccination completion was scheduled 7 days after the second dose. The study included four phases: T0 – pre-vaccination baseline control, which encompassed 1–2 initial samples per SD; T1, T2 and T3 – short, intermediate, and long terms evaluations, respectively. Each included 1–3 semen samples per donor provided 15–45, 75-120, and over 150 days after vaccination completion, respectively. The primary endpoints were semen parameters. Three statistical analyses were conducted: 1) generalized estimated equation model; 2) first sample and 3) samples’ mean of each donor per period were compared to T0.

Results

Repetitive measurements revealed −15.4% sperm concentration decrease on T2 (CI -25.5%–3.9%, p = 0.01) leading to total motile count 22.1% reduction (CI -35% – -6.6%, p = 0.007) compared to T0. Similarly, analysis of first semen sample only and samples’ mean per donor resulted in concentration and TMC reductions on T2 compared to T0 – median decline of 12 million/ml and 31 million motile spermatozoa, respectively (p = 0.02 and 0.002 respectively) on first sample evaluation and median decline of 9.5×10⁶ and 27.3 million motile spermatozoa (p = 0.004 and 0.003, respectively) on samples’ mean examination. T3 evaluation demonstrated overall recovery. Semen volume and sperm motility were not impaired.

Discussion

This longitudinal study focused on SD demonstrates selective temporary sperm concentration and TMC deterioration three months after vaccination followed by later recovery verified by diverse statistical analyses.

Conclusions

Systemic immune response after BNT162b2 vaccine is a reasonable cause for transient semen concentration and TMC decline. Long-term prognosis remains good.

___________________

**Comment**

The results fall in line with the following:

https://rumble.com/v16wbg9-baby-die-off-lactation-issues-miscarriages-and-post-birth-death-dr.-naomi-w.html    Video Here (Approx. 2 Min)

Baby Die-Off: Lactation Issues, Miscarriages, and Neonatal Death

  • Babies who are nursing are getting sick from vaccinated mothers, and at least one has died.
  • Out of the 270 women who got pregnant in the Pfizer trials, 236 of the participants’ records disappeared, but out of the 34 women who remained, 28 of their babies died.
  • In Scotland, twice the number of babies died. In Ontario, Canada, 86 babies died (the average is five or six per year), and deaths among vaccinated mothers are up 34% in Israel.

“[This] should be making news; it’s the biggest news there is.” ~ Dr. Naomi Wolf

https://healthimpactnews.com/2022/almost-3000-increase-in-eye-disorders-following-covid-19-vaccines/

Almost 3,000% Increase in Eye Disorders Following COVID-19 Vaccines

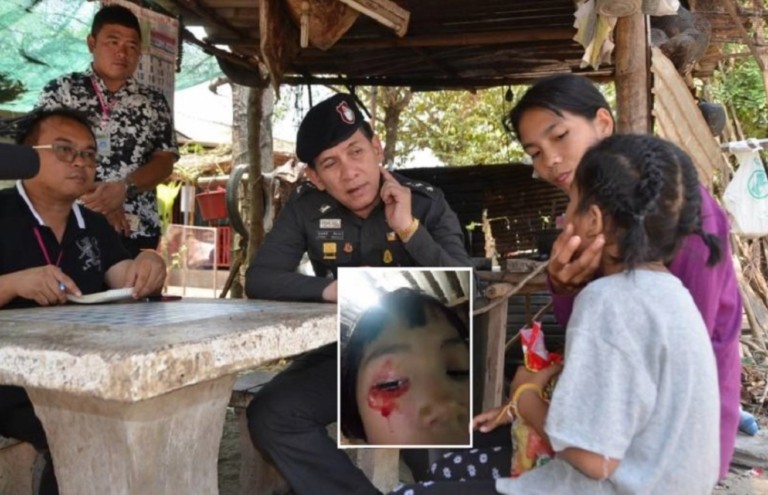
7-Year-Old Girl Oozes Blood from Eye After Receiving Pfizer COVID-19 Vaccine in Thailand. (Source.)

by Brian Shilhavy
Editor, Health Impact News

June 21, 2022

A case study was published earlier this month in the Journal Français d’Ophtalmologie reporting an anterior uveitis case that developed after the first dose of COVID-19 vaccine in a 54-year-old female.

Bilateral anterior uveitis after BNT162b2 mRNA vaccine: Case report

A 54-year-old female patient, who did not have any disease other than diabetes mellitus, had complaints of redness, blurred vision, eye and headache that started in both eyes 3 days after the first dose of BNT162b2 mRNA (Pfizer-BioNTech) vaccine. Three days later, she was referred to our clinic.

She had the best corrected visual acuity of 5/20 on the snellen chart in both eyes. Conjunctiva of both eyes were hyperemic, corneal epithelial edema and keratic prepitates were observed in the lower quadrant. There was intense reaction in the anterior chamber and posterior synechia in the right eye. Intraocular pressure values were 60 mmHg in the right and 55 mmHg in the left with the Goldman applanation tonometer. Corneal edema was attributed to high intraocular pressure.

The patient was hospitalized and necessary blood tests were taken. (Full study.)

We have previously reported on a case of a 7-year-old girl in Thailand who began oozing blood from her eyes and skin after receiving the Pfizer mRNA vaccine. Her case was published in CTN News, which reported:

According to the Multidisciplinary Digital Publishing Institute MDPI, there have been recent reports of hemorrhage, blood clots, and thrombocytopenia following the administration of mRNA COVID-19 vaccines that have raised concerns over the safety of genetic vaccines for people with pre-existing coagulation disorders or those on certain medications. (Full article.)

With the dangerous COVID-19 mRNA shots now being extended to babies and toddlers, I decided to search the Government VAERS (Vaccine Adverse Reporting System) database for cases filed for various eye disorders. The list of eye disorders that I searched can be seen here. They are:

  • Abnormal sensation in eye
  • Abscess of eyelid
  • Autoimmune eye disorder
  • Binocular eye movement disorder
  • Decreased eye contact
  • Eye allergy
  • Eye contusion
  • Eye discharge
  • Eye disorder
  • Eye haemangioma
  • Eye haematoma
  • Eye haemorrhage
  • Eye infection
  • Eye infection bacterial
  • Eye infection fungal
  • Eye infection intraocular
  • Eye infection staphylococcal
  • Eye infection toxoplasmal
  • Eye infection viral
  • Eye inflammation
  • Eye injury
  • Eye irritation
  • Eyelid abrasion
  • Eyelid bleeding
  • Eyelid boil
  • Eyelid contusion
  • Eyelid cyst
  • Eyelid disorder
  • Eyelid function disorder
  • Eyelid haematoma
  • Eyelid infection
  • Eyelid injury
  • Eyelid irritation
  • Eyelid margin crusting
  • Eyelid pain
  • Eyelid tumour
  • Eyelid vascular disorder
  • Eye movement disorder
  • Eye pain
  • Eye pruritus
  • Eye rolling
  • Eyes sunken
  • Eye swelling
  • Eye ulcer
  • Floppy eyelid syndrome
  • Glassy eyes

For the past 18 months since the COVID-19 vaccines were given emergency use authorizations, there have been 17,858 cases of eye disorders reported, including 59 deaths, 1,232 permanent disabilities, 2,882 ER visits, and 1,466 hospitalizations, with 307 life threatening events. (Source.)

That’s an average of 992 cases of eye disorders reported each month following COVID-19 vaccine injections, and this is most certainly NOT an exhaustive list of eye disorders.

But it does give us a sub-set of data to compare to all other FDA-approved vaccines for the previous 30 years (360 months) prior to the roll out of the COVID-19 vaccines.

Using this exact same set of eye disorders, we find 11,898 cases filed for eye disorders over the course of 30 years following all other FDA-approved vaccines, which averages out to 33 cases a month. (Source.)

So that is a 2,902% increase in eye disorders following the very dangerous COVID-19 vaccines, which the health “authorities” now want parents to inject into their babies.

__________________

**Comment**

Oozing blood after these shots is also documented here, and German physicians showed alarming footage and slides of multiple vaxxed patients’ blood after the shots.  Also, listen to an important podcast where Dr. Jane Ruby explains embalmers are finding white, fibrous substances in the vasculature of the vaxxed.  Scroll to 9:00 to listen and see pictures.

Way back in 2020 I posted a video of Italian pathologists who performed more than 50 autopsies and who explain COVID patients are not dying from interstitial pneumonia (why ventilators don’t work and actually do more harm) but from DIC (disseminated intravascular coagulation) a medical term for blood clotting causing lack of oxygen. Chinese researchers performed 74 autopsies and confirmed this.  Interestingly, Dr. Fauci told the government, “Don’t do autopsies,” so little has been studied and revealed in the U.S.  This article explains how a German pathologist who stated that 30-40% of vaxxed autopsies died from the ‘vaccine’ went oddly silent and suddenly stopped doing autopsies.

Autopsies are key for discovery.

“You can not find that for which you do not look.” ~ Dr. Ryan Cole

The Italian pathologists state in the video:

SARS, COVID2 was invented in a British lab (Pirbright Institute) from a U.S. patent(Bickerton et al.) which has 4 genetic inserts:
  • HIV
  • Malaria
  • TB
  • most likely Dengue or Zika, which most likely were carried out in the biosafety lab in Wuhan China, and then escaped or were released.

Of these diseases Malaria, Dengue, Zika, and HIV can cause Thrombocytopenia, which means decreased platelets and formation of micro clots or thrombus, which produces purpuric lesions on the skin, which results in red dots on the limbs, that have been reported in some patients asymptomatic but infected with COVID-19 – mainly in young people, and the worst cases are capable of inducing coagulation, Disseminated Intravascular, which is a systemic event triggered by damage in the blood vessels, caused by inflammation.This has two consequences:

  • Severe, localized micro thrombus formation OR
  • Generalized or localized bleeding

Dr. Hoffe used D-dimer tests on his vaxxed patients complaining of breathlessness, and found that 62% showed microscopic blood clots, with capillaries plugging up which will eventually lead to a serous cardiovascular event.  This also helps explain why embalmers are now finding arteries filled with blood clots, why many are needing leg amputations after the shots, and how Chinese cupping on those who got the shots shows blood like jelly.  Within this article is a video showing pictures from embalmers of “biostructures” within the vaxxed vascular systems. Evidently these are not clots but appear to be some sort of organic crystals and extremely thin wires.

These blood clots are found mainly in the lungs, heart, brain and kidney. It is feasible that many died of hemorrhagic vascular brain ischemia, others with kidney failure, and others with heart disease such as myocardial infarction or failure of cardiac dilation of the heart.

This also explains why hydroxychlorquine (HCQ), an antimalarial (along with zinc)is working, as well as Azithromycin as it stops the growth of bacteria like TB.  HCQ also prevents the virus from binding to hemoglobin.
Dr. Haridopolos (FL Board of Medicine) states the following about hydroxychloroquine:
  • alkalizes the blood, reducing the virus’ ability to replicate
  • causes 02 to dissociate from hemoglobin, similarly as carbon monoxide replaces the 02 molecule
  • reduces cytokine storm


This article explains how the shots cause thrombocytopenia (low platelets) caused by antibodies against the toxic spike protein, resulting in depletion of platelets which can lead to DIC which eventually exhausts the coagulation system which will result in hemorrhaging, and explains why people are bleeding out their eyes, nose, skin, etc. This article reveals there is graphene hydroxide (extremely sharp carbon molecule which is not found in nature and is NOT biodegradable and stays in the body) in the injections which act as nano-razors and cut the epithelial lining of recipients’ veins. This too can exhaust the coagulation system.

Twelve scientists wrote about this to EU regulators in March 2021, asking them to address these safety concerns or halt the ‘vaccines.’ Crickets.

But, you are soundly warned.


https://www.lymedisease.org/lyme-disability-insurance-claims/

10 tips for Lyme disability insurance claims

by Jennifer Hess, Esq., Partner at Riemer Hess LLC

Obtaining disability insurance benefits for Lyme disease is no easy feat. Insurance companies unreasonably scrutinize Lyme disability claims – often denying claims by dismissing symptoms as “unsupported” or “exaggerated.”

This incredibly unfair practice is designed to increase insurer profits at the expense of people disabled by Lyme disease. The only way to increase your chances of approval is with careful preparation, strategic planning and sufficient evidence supporting your disability.

Below are our top 10 tips to help you obtain disability benefits for Lyme disease.

1. Secure the support and cooperation of your doctor

Before filing your disability claim, talk to your doctor to confirm that they not only believe you are disabled, but also that they will participate in the disability claim process. The process will require your doctor’s time and efforts to complete forms and respond to inquiries from the insurance company. If your doctor isn’t willing to cooperate in support of your claim, the insurance company will automatically assume that your claim is not legitimate

2. Ask your doctor to supplement the claim forms with a letter

Standard disability claim forms contain traps designed to help the insurance companies deny claims. For example, the claim form may only prompt your doctor about physical symptoms even though you might experience other disabling symptoms, such as cognitive difficulties. Unless your doctor supplements the form with more information, the insurance company will receive an incomplete picture of your condition.

Thankfully, your doctor is not limited to the forms provided by your insurance company. You can ask your doctor to supplement the forms with a detailed letter.

The letter should explain the nature, frequency, and duration of your Lyme disease symptoms, while also explaining how these symptoms impact your ability to work. Other pertinent information, such as lab results or abnormal clinical findings, can add further valuable support.

3. Undergo a functional capacity evaluation, neuropsychological evaluation, or cardiopulmonary exercise testing

Insurance companies always want to see objective proof of your disability, where possible. Testing that your doctor recommends for treatment purposes may be helpful to your disability claim.

However, there may be other tests available to substantiate your disability claim with the goal of measuring your symptoms’ impact on your physical functions rather than as treatment. These tests include the following:

Functional Capacity Evaluation If your Lyme disease causes physical symptoms such as stiffness or muscle weakness, consider undergoing a functional capacity evaluation (also known as an “FCE”). An FCE is a series of tests, practices, and clinical observations that objectively measure your physical ability to perform work-related activities. These activities include: sitting; standing; walking; lifting/carrying; pushing/pulling; performing gross or fine manipulations (for example, typing); and many other occupational functions.

Neuropsychological Evaluation If your Lyme disease causes cognitive symptoms such as brain fog, consider undergoing a neuropsychological evaluation. This is an in-depth assessment of how well your brain functions with respect to certain skills and abilities. It involves testing your performance in the areas of: reading; language; memory; attention/concentration; processing speed; learning; reasoning; problem solving; and more.

Cardiopulmonary Exercise Test If your Lyme disease causes significant physical fatigue and exertional intolerance, consider undergoing a cardiopulmonary exercise test (also known as a “CPET”). A CPET is a highly specialized stress test that objectively measures your ability to exercise and physically exert yourself.

Each of the above-noted tests may be used as acceptable proof of a Lyme disability. However, the insurance company will want to see that the testing included measures to ensure that you consistently put forth maximum efforts (known as “validity testing”), and that you passed all such measures. If you don’t satisfy validity measures, the insurance company will dismiss the results as unreliable and invalid.

4. Explain how your Lyme symptoms impact your ability to work

You will need to complete forms and talk to the insurance company representative about how your Lyme disease impacts your ability to work. This is your opportunity to tell your story. Do so by listing each of your symptoms and describing how each impacts your ability to perform the specific duties of your occupation. Where possible, provide everyday examples and be sure to describe any work activities that exacerbate your symptoms. Don’t forget to detail the non-exertional demands of your work, such as performing analytical thinking.

If your symptoms unpredictably fluctuate in nature or severity, be sure to detail that as well. The ability to maintain a normal work schedule on a consistent, reliable, and sustained basis is a requirement of any gainful employment. If your fluctuating symptoms prevent you from meeting that requirement, the insurance company should find that you are disabled.

5. Keep a Lyme symptom diary or journal

A symptom diary or journal can help demonstrate the nature, frequency, and duration of your Lyme disease symptoms. A contemporaneous, daily log of your symptoms is ideal.

For example, if you had joint pain on Tuesday, you should put that in your diary. If you could not get out of bed on Wednesday,you also should put that in your diary. The more specific your diary entries are, the better. Specificity helps the insurer view and evaluate your symptoms in context – making it easier to prove your Lyme disease disability claim.

Consider giving your doctor a copy of your Lyme disease symptom diary to put in your file. This will better enable your doctor to evaluate the full spectrum of your symptoms, rather than just the ones that you remember to report during your visit. This also can help your doctor keep better treatment notes that accurately reflect the totality of your symptoms.

6. Don’t forget to document any co-morbid conditions contributing to your disability

If you have any medical conditions other than Lyme disease contributing to your inability to work, be sure to document them. Co-morbid diagnoses can have a major impact on your disability, whether tick-related (for example, Babesiosis) or not (for example, rheumatoid arthritis). Gather documentation from the doctors that are treating any co-morbid conditions and be sure to explain the impact of such to your disability insurer

7. Gather and neatly organize your evidence with an index

The insurance company will not gather evidence of your disability on your behalf. That responsibility is on you. The more supportive evidence that you can proactively provide, the better.

Gather all medical evidence (for example, testing results, treatment notes, and statements from your doctors), occupational evidence (for example, a job description and a statement written by you detailing how you cannot perform the demands of your work), and anything else that might support your claim.

There is no limit on what you can submit, so feel free to get creative. You can submit photographs, witness statements from co-workers or friends, or even work performance evaluations.

Neatly organize, label, and index the evidence. This will help ensure that nothing goes unseen or unreviewed.

In addition to the testing detailed above, you’ll want to get the results of any serological testing. This is laboratory blood testing that typically involves two tiers to identify Lyme antibodies: (1) the “EIA” (enzyme immunoassay) or sometimes an “IFA” (indirect immunofluorescence assay); and (2) an immunoblot test, commonly referred to as the “Western Blot” test.

The Western Blot is arguably a more reliable indicator of Lyme, but it is not necessary to make a diagnosis. Although serological testing is not necessary to diagnosis Lyme disease, positive results will be helpful for your disability claim. Even if the results are not positive, the insurer will still want to see that you have had this testing done.

8. Satisfy the deadlines set forth in your disability insurance policy

Your long term disability insurance policy contains deadlines that you must satisfy. If you do not satisfy the deadlines, you will lose your opportunity to pursue your claim.

The two most important deadlines you must meet are “notice of claim” (the date by which you must notify the insurer that you intend to file a claim) and “proof of claim” (the date by which you must submit your supportive evidence).

These deadlines can be surprisingly short. For example, the deadline to file notice of claim could be as short as 7 days after the onset of your disability.

Always check your long term disability policy and be sure to keep proof of your submissions to demonstrate timeliness.

9. Receive consistent and frequent treatment while your disability claim is pending

You must continue to receive medical treatment for Lyme while your disability claim is pending. This is because most disability insurance policies require that you are under the continuous care of an appropriately qualified medical provider to be eligible for benefits.Consistent and frequent treatment is ideal, but you should always talk to your doctor about what frequency they deem appropriate.

Eventually, your insurer will want to see those updated treatment records to evaluate how you are doing.

10. Cooperate with the insurance company’s investigation within reason

Disability insurers have a right to investigate your claim, and they generally obligate you to cooperate with this process. As part of the investigation, your disability insurer might want to interview you or talk to your doctors.

Your disability insurer also might demand that you submit to a so-called “independent” medical examination by one of their doctors. The more supportive information that you can proactively throw at the insurer to support your claim, the less likely it is that the insurer will ask for more information during the investigation process. It is always best to proactively submit as much supportive evidence as possible.

Conclusion

The success of your Lyme disability insurance claim will boil down to careful, strategic planning and sufficient evidence. Without this, your chances of securing disability insurance benefits will substantially decrease. Always seek help from a disability insurance attorney who has relevant experience with Lyme disease.

Jennifer L. Hess is an attorney partner at Riemer Hess LLC in New York City, a law firm focusing on disability insurance claims. For more educational information about proving Lyme disability insurance claims, visit their FAQ Center page, “Is Lyme Disease a Disability?”

________________

For more:

https://danielcameronmd.com/knee-swelling-child-lyme-disease/

Unilateral knee swelling in a child due to Lyme disease

swollen-knee-lyme-disease

In their case report, “Pediatric unilateral knee swelling: a case report of a complicated differential diagnosis and often overlooked cause,” Guardado et al. describe a 3-year-old girl who presented to a hospital in Pennsylvania after two weeks of limping from a swollen right knee.¹

According to the authors, “The mother initially denied history of a tick bite, yet after focused questioning, the mother stated that the child had ticks on her approximately 9 months ago.”

Unfortunately, the child was not taken to her clinician because she did not develop any skin rashes which could indicate Lyme disease.

The child demonstrated right knee effusion with signs of crepitus and decreased range of motion secondary to swelling, the authors explain. “In addition, she had an unsteady gait without joint tenderness, crepitus, or overlying skin pathology.”

A Western blot test for Lyme disease was positive.

“Lyme arthritis is a diagnosis that is often missed, even in children, who are the population with the highest incidence of Lyme disease,” the authors point out.

“When this diagnosis is missed, it can result in long-term morbidity, which is generally refractory to intravenous antibiotic therapy, oftentimes requiring synovectomy.”

The child had a complete resolution of symptoms following a 2-day treatment with IV Rocephin and 21 days of oral amoxicillin.

“This case demonstrates the importance of including Lyme arthritis as part of the differential diagnosis of joint swelling regardless of the recollection of a tick bite,” the authors suggest.

Furthermore, the case raises awareness of mono- or oligoarticular arthritis as one of the signs of Lyme disease.

Related Articles: