90 (And Counting) Young Canadian Doctors Dead After COVID Jabs, Studies Show More Clotting – Natural Immunity Still Better
**UPDATE Nov. 2022**
Originally posted as 80 doctors, unfortunately this number continues to climb and is now at least 90 doctors dead after the COVID shots without ANY investigation by the organization supposedly protecting its members, the Canadian Medical Association (CMA). The agency has ignored two letters of concern with research findings from Dr. William Makis and has turned around and stated that this doctor’s research is dangerous “disinformation.”
When you can’t offer any meaningful dialog or answers, just name-call and bully those who give inconvenient data.
These medical associations are completely controlled by unelected officials in bed with Big Pharma who are using censorship and persecution tactics against any doctors who dissent from the accepted narrative. These organizations need to be disbanded and rendered defunct.

80 Young Canadian Docs Died Since “Vaccine” Rollout -Dr. Makis Pleads With CMA To Investigate
80 young Canadian doctors have died since the Covid-19 “vaccines” were given “warp-speed” emergency authorization without any long-term safety or efficacy data. The short-term data submitted to approving regulatory health agencies around the world have been exposed to be corrupt, rife with fraudulent data manipulation and poor laboratory management, patient safety concerns, and data integrity issues exposed by whistleblower Brook Jackson at the Ventavia-run Pfizer phase III trial site.
Dr. William Makis, MD (watch our interview here on 32 Canadian doctor deaths or see video below), has been investigating and raising alarm bells since the rollout of Covid-19 “vaccines” in Dec. 2020. Dr. Makis defines “a young doctor” as someone up to 70-years-old, given most physicians practice into their 60’s and 70’s and are generally healthy individuals.
Dr. Makis penned another letter for the Canadian Medical Association (CMA) presidents, Dr. Alika Lafontaine and Dr. Katharine Smart, October 15, 2022, raising concerns about the “sudden deaths” of 80 young Canadian doctors since the rollout of the COVID-19 “Vaccines” and vaccine mandates. His first letter to the CMA regarding 32 deaths young doctor deaths temporally related to the vaccine rollout went ignored.
Read Dr. Makis’ letter.
Follow Dr. Makis on Getter LINK.
___________________
https://takecontrol.substack.com/p/covid-vaccine-and-blood-clots
The Trail of Blood From the COVID Jabs
These two doctors claim they’ve discovered a way to test for spike protein in human tissue, and they’ve found spike protein in individuals who were injured or died from the shots.
- Abnormal blood clotting was one of the first mysterious health effects to emerge in the COVID pandemic, first, as an effect of the natural infection, and later, as a side effect of the COVID jabs. By mid-March 2021, 20 countries had suspended the use of AstraZeneca’s COVID shot, either in full or in part, following reports of deadly blood clots
- In December 2021, a team of international scientists detailed the mechanism behind the AstraZeneca jab’s propensity to trigger blood clots. The shell of the vector — a weakened chimpanzee cold virus — in some people acts like a magnet and attracts platelets. Your body mistakes these platelets as a threat and produces antibodies to fight them, resulting in dangerous blood clots
- Israeli researchers have also linked the Pfizer jab with a rare blood clotting disorder
- A Swedish study found two doses of the COVID jab were 43% protective against Omicron infection at week 4. By week 14, protection had dropped to zero. Effectiveness against COVID-related hospitalization remained around 80% until week 25, but dropped to 40% by week 40. Using one statistical analysis method, COVID jabbed Swedes had a higher risk of death or hospitalization from COVID roughly a year after receiving their second dose
- A recent case report links the COVID shots to lethal myocarditis (heart inflammation) and encephalitis (brain inflammation)
Steve Kirsch goes on to cite other evidence showing the COVID shots can kill, including a report20 titled “On COVID Vaccines: Why They Cannot Work, and Irrefutable Evidence of Their Causative Role in the Deaths After Vaccination,” written by Drs. Sucharit Bhakdi and Arne Burkhardt.
“Of the 15 bodies their team examined — all of whom had died seven days to six months’ post-jab — 14 (93%) were found to have been killed by the COVID shot.
Bhakdi and Burkhardt claim to have developed a way to test for spike protein in human tissue, and say they’ve found spike protein in the tissues of people who have been injured and/or killed by the jabs.
(See link for article)
______________________
Red Cross admits they are not separating “vaccinated” from “unvaccinated” blood.
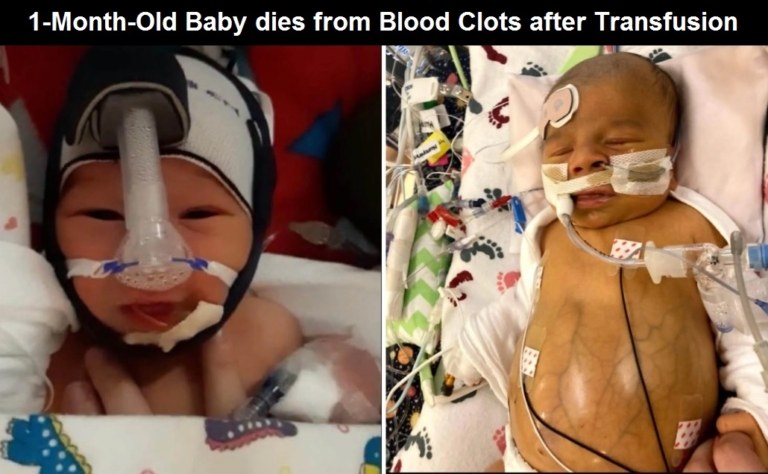
Baby Alexander before and after the blood transfusion (Source: Cornelia Hertzler via Gatway Pundit)
____________________
Japanese Researchers Publish Cases of Strange Blood Clots Following Pfizer COVID Vaccines

by Brian Shilhavy, Oct. 8, 2022
Editor, Health Impact News
Excerpts:
More cases of damage done by the COVID-19 vaccines continue to be published in the medical journals, and now Japanese researchers have published a couple of cases of unusual blood clots found through autopsies after the Pfizer COVID vaccines that seem to corroborate what some funeral home embalmers are also reporting in terms of strange blood clots found in the bodies of dead people.
A study published in the November, 2022 edition of Legal Medicine titled An autopsy case report of aortic dissection complicated with histiolymphocytic pericarditis and aortic inflammation after mRNA COVID-19 vaccination, reported about a Japanese male in his 90s with no previous illness that died two weeks after his third dose of the Pfizer COVID-19 vaccine.
The report of microscopic examination is interesting because they report seeing “elastic fibers” similar to what Richard Hirschman, a funeral home director and embalmer, has also reported seeing.
A second Japanese case was published in Thrombosis Journal titled Histopathologically TMA-like distribution of multiple organ thromboses following the initial dose of the BNT162b2 mRNA vaccine (Comirnaty, Pfizer/BioNTech): an autopsy case report.
This case was a 72-year-old woman who received the first dose of the Pfizer mRNA vaccine and died 2 days later.
__________________
https://thehighwire.com/videos/natural-immunity-better-in-new-covid-vaccine-studies/ Video Here (Approx. 13 Min)
Natural Immunity is Better Than COVID Injections
Numerous studies now demonstrate Covid mRNA injections fail to stop infection or transmission, while also establishing that natural immunity, once again, is superior to the Pharma products.
This shouldn’t shock anyone. The COVID shots have only shown what history has repeatedly shown: natural immunity is robust, long lasting, and more complete than “vaccination.” Further, these mRNA injections actually cause pathogenic priming, specifically antibody enhancement (ADE)- setting you up to become infected. These injections are linked to more VAERS reports of adverse reactions and death than any other vaccine in the history of VAERS.
More keeps tumbling out of the COVID shot barrel of monkeys including results of lawsuits exposing the following derived from this source:
- Of the 10 million people enrolled in V-Safe, 7.7% (770,000 people) required medical care after getting the shot
- 25% (2.5 million people) missed work or school or suffered a serious side effect that affected their day-to-day life
- Four million people — 40% — reported joint pain.
- Two million, or 20%, reported “moderate” joint pain
- 400,000, 4%, classified the pain as “severe”
- the formula the CDC uses to trigger a safety signal is seriously flawed, because the more dangerous a vaccine is, the less likely it is that a safety signal will be triggered.
- even using the flawed formula, “death” meets all three safety signal criteria and should have been flagged
- options for reporting a side effect are predefined and very generic, so people might be experiencing effects that didn’t fit any of the predefined categories of injury.
- death is not reportable to V-Safe, as dead people cannot use their phones which makes it impossible to know how many actually have died
- Not only has the CDC taken no action, they deliberately concealed all the V-Safe data from everyone the entire time, until they were sued. See this three part series on how they did this: Part 1, Part 2, Part 3
- The mainstream media are ignoring all of this which means it’s up to us to inform our loved ones.
- Please see this video of civil rights attorney Aaron Siri explain the data, and go here for ICAN’s V-Safe data obtained from the CDC.
The CDC needs to explain why they spent our tax dollars to fight the release of the V-Safe data for 15 months, and why they didn’t halt the shots when a “death” signal was evident. The mainstream press, members of Congress, the medical community and Universities also need to explain why they refuse to investigate these CDC data. To that end, here are a few suggestions for how you can help:
- Support Sen. Ron Johnson, currently the only senator willing to investigate the truth of the COVID jabs.
- Write or call your members of Congress and ask them to investigate the CDC’s safety monitoring. As noted by Kirsch, “You simply cannot have a safety agency not be able to monitor safety.”
- Contact your local newspaper and urge them to investigate and report on the V-Safe data, the VAERS data and the CDC’s failure to act when a safety signal was detected.
- Share the data on social media and ask why no one in the media, Congress, academia or medical community is investigating these matters.
- Share this information with your doctor and members of the medical community.
- Also share it with university administrators, and ask them to explain how and why, in light of these facts, they are still mandating COVID shots for their students.
Fluvid-19
Support Hibbeler Productions:
https://rokfin.co, the PCR, was never meant to diagnose people. It doesn’t even tell you if you are sick. News reports of many, many previously healthy athletes dropping after the “vax.” Dr. Cole explains how cancers are now exploding as well. Blood clotting also is occurring regularly now. **WARNING** Bad language.
People Are Dropping Like Flies
Robert Jay Rowen, MD
I know you have seen deaths in the movies. Of course, these are acted. But, have you ever seen people actually keeling over and dropping dead for real? I just saw a jaw dropping video that tore me up. Young people simply collapsing in the midst of talking or competing. You might want to take a look at this video. But I warn you, it is graphic and horrifying: https://tinyurl.com/mr3ssxrx
For more:
- https://madisonarealymesupportgroup.com/2022/06/22/cdc-admits-it-never-monitored-vaers-for-covid-vaccine-safety-signals-pfizer-classified-nearly-all-adverse-reactions-as-not-related-to-shots/
- https://madisonarealymesupportgroup.com/2020/12/30/cdc-thwarts-efforts-to-track-covid-19-vaccine-adverse-reactions/
- https://madisonarealymesupportgroup.com/2022/10/04/fda-refuses-to-release-autopsy-results-on-people-who-died-after-covid-vaccines/
- https://madisonarealymesupportgroup.com/2020/12/21/warning-3150-injuries-in-1st-week-of-covid-vaccines-among-american-healthcare-workers-pregnant-women-included/
- https://madisonarealymesupportgroup.com/2022/09/30/study-suggests-the-covid-shot-caused-one-in-800-adverse-events-spinning-vaccine-failure-into-a-win/
- https://madisonarealymesupportgroup.com/2022/08/18/fda-buries-head-in-sand-as-44-of-pregnant-trial-participants-suffer-miscarriages-then-has-the-audacity-to-re-categorize-them-as-recovered-adverse-events/
- https://madisonarealymesupportgroup.com/2022/07/05/for-every-454-covid-shots-an-adverse-event-is-recorded-in-vaers/
The CDC manipulates, hides, and dumps data whenever it disagrees with their accepted narrative. They’ve been doing this in Lymeland for over 40 years. And the CDC rigs the system for their own vested interests.