Archive for the ‘Testing’ Category

Study Uncovers Hidden Bartonella and Babesia Infections in ME/CFS Patients

Four years ago an article was posted asking if a chronic infection could be behind ME/CFS patients. The answer appears to be yes. A previous study found a link between Cytomegalovirus, EBS, and Human Herpesvirus-6 and ME/CFS. The following also connects Babesia and Bartonella to the condition.

https://www.lymedisease.org/bartonella-babesia-me-cfs/

Study uncovers hidden Bartonella and Babesia infections in ME/CFS patients

A new pilot study from North Carolina State University has found molecular evidence of Bartonella or Babesia infection in nearly half of 50 people diagnosed with myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS).

The findings suggest that vector‑borne pathogens may play a larger role in chronic illness than previously recognized.

Bartonella and Babesia are both transmitted primarily through arthropods—ticks, fleas, and lice—and have been linked to a range of persistent symptoms.

Improved testing has revealed that Bartonella, once thought to cause only short‑lived infections like cat scratch disease, can be associated with chronic and even neuropsychiatric symptoms. Babesia, best known as a tick‑borne parasite, has also been transmitted through blood transfusions and organ transplants.

For this study, researchers selected 50 participants from a larger group of chronically ill individuals with long‑term fatigue and neurological symptoms such as memory problems, tremors, disorientation, or anxiety.

Using quantitative PCR and DNA sequencing, the team detected:

  • Babesia in 10 participants
  • Bartonella in 11
  • Both pathogens in 2

That’s 23 out of 50 participants showing evidence of infection.

“ME/CFS diagnoses are primarily based on immunological biomarkers that can have numerous influences,” said study author Edward Breitschwerdt, Melanie S. Steele Distinguished Professor of Internal Medicine at NC State.

“Our goal was to detect the DNA of specific pathogenic microorganisms that might contribute to or cause a patient’s chronic illness.”

Breitschwerdt emphasized that the small sample size means the results can’t be generalized to all ME/CFS patients, but the unexpectedly high prevalence highlights the need for further research.

The study, supported in part by the Steven & Alexandra Cohen Foundation, appears in Pathogens.

SOURCE: North Carolina State University

________________

For more:

Why You Still Feel Sick After Standard Lyme Treatment

Why You Still Feel Sick After Standard Lyme Treatment

Dr. Jaquel Patterson

June 10, 2026

Lyme disease rarely travels alone, and unaddressed co-infections like Bartonella, Babesia, Ehrlichia, Anaplasma, Mycoplasma, and Rickettsia are some of the most common reasons chronic Lyme patients don’t recover. In this video, I walk through how each co-infection is distinct, why standard Lyme antibiotics don’t cover them, and what a truly comprehensive testing and treatment approach should look like. Learn more: https://www.fairfieldfamilyhealth.com

CHAPTERS

00:00 Why Lyme Treatment Often Isn’t Enough

01:32 What Tick Borne Co-Infections Actually Are

02:54 Bartonella, Babesia, and Why They Get Missed

06:55 Why Standard Lyme Testing Fails to Catch Co-Infections

08:46 The Clinical Patterns That Point to Hidden Infections

09:55 What Comprehensive Tick Borne Testing Looks Like

11:37 Treatment Protocols for Each Co-Infection

14:29 Final Takeaways for Chronic Lyme Patients

________________

**Comment**

And this, right here, is why many patients are not better and never get better. Further, testing absolutely sucks. ALL of it. Pathogens working together create a severe clinical picture. Many of these pathogens require completely different medications. Mainstream doctors are clueless on all of this and have furthered an antiquated, unscientific case definition and treatment protocol for over 40 years.

It is far, far more complex than most doctors are aware. They spend very little time studying this in med school and what they do study is completely wrong.

For more:

Seroprevalence of Borrelia, Anaplasma, Bartonella, Toxoplasma, Mycoplasma, Yersinia, and Chlamydia in Human Population From Eastern Poland

https://www.mdpi.com/2076-0817/14/1/96

Seroprevalence of BorreliaAnaplasmaBartonellaToxoplasmaMycoplasmaYersinia, and Chlamydia in Human Population from Eastern Poland

by Angelina Wójcik-Fatla 1, Anna Sawczyn-Domańska 1,*, Anna Kloc 1,Joanna Krzowska-Firych 2 and Jacek Sroka 1,3

*Author to whom correspondence should be addressed.

Pathogens 202514(1), 96; https://doi.org/10.3390/pathogens14010096

Submission received: 3 December 2024 / Revised: 15 January 2025 / Accepted: 16 January 2025 / Published: 18 January 2025

(This article belongs to the Special Issue Exploring the Biodiversity of Parasites in Humans, Wild and Domestic Animals)

Abstract

The epidemiological situation related to infectious diseases is influenced by many factors. To monitor actual trends in selected zoonoses, a total of 473 serum samples from farmers, forestry workers, and veterinarians were collected for serological examination. Anti-Borrelia burgdorferi sensu lato (s.l.) antibodies were tested with ELISA and Western blot (WB) tests; the detection of anti-Toxoplasma gondii antibodies was performed using an enzyme linked fluorescence assay (ELFA). Antibodies to bartonellosis, anaplasmosis, and chlamydiosis were determined by indirect immunofluorescent test (IFA), whereas antibodies to yersiniosis and mycoplasmosis were confirmed in the ELISA test.

Positive or borderline results of antibodies against B. burgdorferi s.l. in the ELISA test were detected in 33.8% of the study population. The borderline or positive ELISA test results for at least one antibody class were confirmed by WB in 58.7% of cases. The IgG antibodies against Anaplasma phagocytophilumToxoplasma gondii, and Mycoplasma pneumoniae were detected in 9.6%, 51.7%, and 63.6% of samples, respectively. Antibodies against Yersinia spp., Bartonella henselae, and Chlamydia pneumoniae were found to vary between 43 and 47%.

The Great Prostate Hoax

https://unbekoming.substack.com/p/the-great-prostate-hoax

The Great Prostate Hoax

By Richard Ablin and Ronald Piana – Unbekoming Book Summary

Unbekoming

Oct 16, 2024

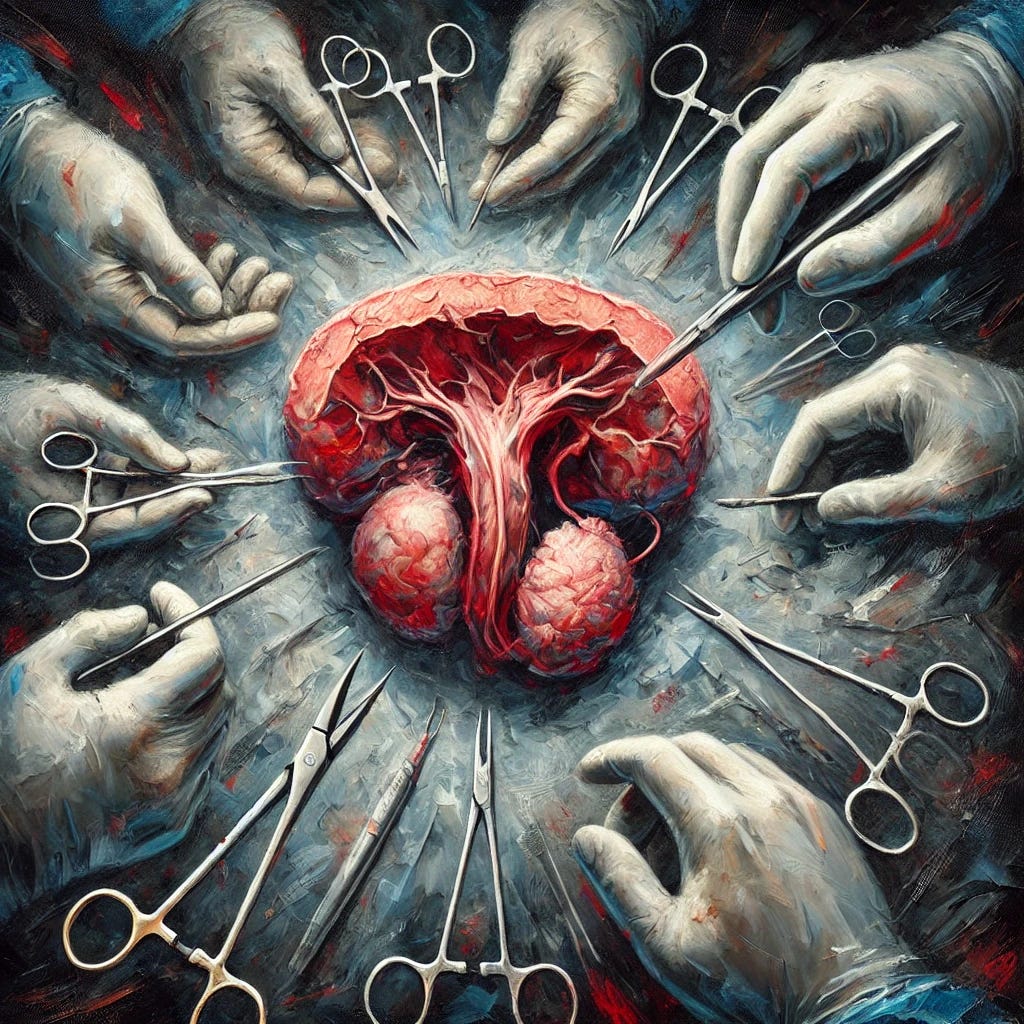
An expressive oil painting focused on the human prostate and its surgical removal, symbolizing the impact of PSA testing and prostate cancer treatment. The central image is a detailed representation of the prostate surrounded by surgical tools and hands preparing to perform the removal. The prostate is depicted with vulnerable, soft textures, while the background is dark and somber, with muted tones of blue, grey, and red, emphasizing the gravity of the procedure. Bold, dramatic brushstrokes highlight the intensity and emotional weight of the scene, evoking a sense of medical intervention and loss.

It’s not just women that Cartel Medicine feeds on, although it does prefer them.

Men are also meat for the grinder, especially when their privates are involved.

The screening hoax we witnessed with mammograms has a counterpart with prostates and the PSA test.

The predation here is especially synergistic as the maiming and destruction caused by prostate interventions feed two sub-Cartels: those of erectile dysfunction and incontinence. The adult diaper business is thriving because of this butchery.

Urologists, not wanting to be left behind by pediatricianspsychiatristscardiologistsdermatologists and  dentists have their own cozy racket.

With thanks to Richard Ablin and Ronald Piana for telling the truth. [in their book ‘The Great Prostate Hoax.’]

12-point summary

Here’s a 12-point summary of the book, including key data and statistics for those that don’t want to read the longer Q&A below.

  1. PSA (Prostate-Specific Antigen) is not cancer-specific. It’s present in normal, benign, and cancerous prostate tissue. There is no specific PSA level that definitively indicates cancer.
  2. Routine PSA screening leads to significant overdiagnosis and overtreatment. For every 1,000 men screened, only 1 man may avoid death from prostate cancer, while many others suffer unnecessary biopsies and treatments.
  3. Prostate cancer is age-related. About 40% of men aged 40-49, 70% of men 60-69, and 80% of men over 70 have prostate cancer. Most of these cancers are slow-growing and unlikely to cause death.
  4. The lifetime risk of dying from prostate cancer is only 3%, meaning 97% of men will die from other causes, even if they have prostate cancer.
  5. Radical prostatectomy, a common treatment resulting from PSA screening, often leads to significant side effects. Up to 60-80% of men experience erectile dysfunction and 10-20% have long-term urinary incontinence.
  6. PSA screening has not significantly reduced prostate cancer mortality. Studies show similar death rates between screened and unscreened populations.
  7. The PSA test has a high false-positive rate of up to 80%, leading to many unnecessary biopsies and treatments.
  8. Active surveillance is increasingly recognized as an appropriate option for many men with low-risk prostate cancer, potentially avoiding unnecessary treatments and their side effects.
  9. The U.S. healthcare system spends an estimated $3 billion annually on PSA tests alone, with billions more on subsequent procedures and treatments.
  10. New technologies like robotic surgery and proton beam therapy, while heavily marketed, have not shown superior outcomes to traditional treatments but are significantly more expensive.
  11. Conflicts of interest are prevalent in prostate cancer care. Many researchers and physicians promoting PSA screening have financial ties to companies that profit from increased screening and treatment.
  12. The FDA approved the PSA test for screening in 1994 despite significant reservations from its own advisory panel. This decision, along with aggressive marketing by medical companies, led to widespread adoption of PSA screening before its benefits and harms were fully understood.

(See link for article)

The Lyme Lie: How Hidden Infections Sabotage Immunity & Cancer Healing

http://  Approx. 18 Min

The Lyme Lie

How Hidden Infections Sabotage Immunity & Cancer Healing

Dr. Dio Prato

What You’ll Learn in This Episode:

  • Why Lyme disease is frequently missed
  • What “chronic Lyme disease complex” really means
  • How co-infections suppress immunity and drive inflammation
  • The link between infections, autoimmunity, and cancer recurrence
  • Why false-negative Lyme tests are common
  • How neuroborreliosis affects the brain and nervous system
  • Why infections must be treated before repair and recovery
  • The right questions to ask your doctor about testing

📍 Envita Medical Centers – Scottsdale, AZ 🌐 Learn more: https://www.envita.com/?utm_source=Dr… 📞 Speak with a care coordinator: 866-830-4576

Chapters:

0:00 – Understanding Lyme Disease and Its Hidden Dangers

2:00 – The Complexity of Tick-Borne Infections

4:45 – Testing and Diagnosis Lyme Disease

6:47 – The Link Between Lyme Disease and Cancer

9:10 – Real Patient Cases and Treatment Success

14:00 – Questions to Ask Your Doctor

For more: