Archive for the ‘research’ Category

Another Whistleblower Promptly Fired For Showing Pfizer Falsified Data. Got Science? Are You Sure?

**UPDATE Feb. 18, 2022**

Here is the case filing of the lawsuit against Pfizer:  https://www.documentcloud.org/documents/21206071-brook-jackson-lawsuit

Case 1:21-cv-00008-MJT Filed 01/08/21

Core allegations:

Making or Using False Records or Statements to Cause Claims to be Paid (31 U.S.C. § 3729(a)(1)(B)) 284.

  1. “From 2020 to the present, Defendants knowingly made, used, or caused to be made or used, false records or statements that were material to false and/or fraudulent claims paid or approved by the United States DoD. These false records or statements include the clinical trial protocol Pfizer submitted to the United States and the falsified source documents and data behind Defendants’ trial results and EUA application.

  2. By creating and carrying out their fraudulent schemes, Defendants knowingly and repeatedly violated Section 3729(a)(1)(B) of the False Claims Act. 286. Defendants’ false records were material to Pfizer’s claims for payment for the vaccine at issue. The United States DoD would not have paid Pfizer if it knew that the clinical trial protocol was not complied with by Defendants, because the protocol violations call the integrity and validity of both the entire clinical trial and Pfizer’s EUA into question.

  3. Defendants’ false records also went to the very essence of the bargain the United States contracted for. DoD contracted to purchase vaccines found effective by a valid clinical trial conducted according to the protocol submitted by Pfizer. The integrity of the entire clinical trial was compromised by the trial protocol violations, false source documents, and the false data that resulted, which calls the vaccine’s EUA into question. Had the United States DoD known of Defendants’ false records, it would not have paid Pfizer. 288. Defendants’ use, or causation of use, of material false records was a foreseeable factor in the United States DoD’s loss and a consequence of Defendants’ schemes. By virtue of Defendants’ actions, the United States DoD has suffered actual damages and is entitled to recover treble damages plus a civil monetary penalty for each false and/or fraudulent claim.”

    Access: Case 1:21-cv-00008-MJT Filed 01/08/21

https://www.bmj.com/content/375/bmj.n2635.full

Covid-19: Researcher blows the whistle on data integrity issues in Pfizer’s vaccine trial

BMJ 2021; 375 doi: https://doi.org/10.1136/bmj.n2635 (Published 02 November 2021) Cite this as: BMJ 2021;375:n2635

 
Paul D Thacker, investigative journalist
Revelations of poor practices at a contract research company helping to carry out Pfizer’s pivotal covid-19 vaccine trial raise questions about data integrity and regulatory oversight. Paul D Thacker reports

In autumn 2020 Pfizer’s chairman and chief executive, Albert Bourla, released an open letter to the billions of people around the world who were investing their hopes in a safe and effective covid-19 vaccine to end the pandemic. “As I’ve said before, we are operating at the speed of science,” Bourla wrote, explaining to the public when they could expect a Pfizer vaccine to be authorised in the United States.1

But, for researchers who were testing Pfizer’s vaccine at several sites in Texas during that autumn, speed may have come at the cost of data integrity and patient safety. A regional director who was employed at the research organisation Ventavia Research Group has told The BMJ that the company falsified data, unblinded patients, employed inadequately trained vaccinators, and was slow to follow up on adverse events reported in Pfizer’s pivotal phase III trial. Staff who conducted quality control checks were overwhelmed by the volume of problems they were finding. After repeatedly notifying Ventavia of these problems, the regional director, Brook Jackson, emailed a complaint to the US Food and Drug Administration (FDA). Ventavia fired her later the same day. Jackson has provided The BMJ with dozens of internal company documents, photos, audio recordings, and emails.

Poor laboratory management

On its website Ventavia calls itself the largest privately owned clinical research company in Texas and lists many awards it has won for its contract work.2 But Jackson has told The BMJ that, during the two weeks she was employed at Ventavia in September 2020, she repeatedly informed her superiors of poor laboratory management, patient safety concerns, and data integrity issues. Jackson was a trained clinical trial auditor who previously held a director of operations position and came to Ventavia with more than 15 years’ experience in clinical research coordination and management. Exasperated that Ventavia was not dealing with the problems, Jackson documented several matters late one night, taking photos on her mobile phone. One photo, provided to The BMJ, showed needles discarded in a plastic biohazard bag instead of a sharps container box. Another showed vaccine packaging materials with trial participants’ identification numbers written on them left out in the open, potentially unblinding participants. Ventavia executives later questioned Jackson for taking the photos.

Early and inadvertent unblinding may have occurred on a far wider scale. According to the trial’s design, unblinded staff were responsible for preparing and administering the study drug (Pfizer’s vaccine or a placebo). This was to be done to preserve the blinding of trial participants and all other site staff, including the principal investigator. However, at Ventavia, Jackson told The BMJ that drug assignment confirmation printouts were being left in participants’ charts, accessible to blinded personnel. As a corrective action taken in September, two months into trial recruitment and with around 1000 participants already enrolled, quality assurance checklists were updated with instructions for staff to remove drug assignments from charts.

In a recording of a meeting in late September2020 between Jackson and two directors a Ventavia executive can be heard explaining that the company wasn’t able to quantify the types and number of errors they were finding when examining the trial paperwork for quality control. “In my mind, it’s something new every day,” a Ventavia executive says. “We know that it’s significant.”

Ventavia was not keeping up with data entry queries, shows an email sent by ICON, the contract research organisation with which Pfizer partnered on the trial. ICON reminded Ventavia in a September 2020 email: “The expectation for this study is that all queries are addressed within 24hrs.” ICON then highlighted over 100 outstanding queries older than three days in yellow. Examples included two individuals for which “Subject has reported with Severe symptoms/reactions … Per protocol, subjects experiencing Grade 3 local reactions should be contacted. Please confirm if an UNPLANNED CONTACT was made and update the corresponding form as appropriate.” According to the trial protocol a telephone contact should have occurred “to ascertain further details and determine whether a site visit is clinically indicated.”

Worries over FDA inspection

Documents show that problems had been going on for weeks. In a list of “action items” circulated among Ventavia leaders in early August 2020, shortly after the trial began and before Jackson’s hiring, a Ventavia executive identified three site staff members with whom to “Go over e-diary issue/falsifying data, etc.” One of them was “verbally counseled for changing data and not noting late entry,” a note indicates.

At several points during the late September meeting Jackson and the Ventavia executives discussed the possibility of the FDA showing up for an inspection (box 1). “We’re going to get some kind of letter of information at least, when the FDA gets here . . . know it,” an executive stated. (See link for article)

Important excerpt:

Since Jackson reported problems with Ventavia to the FDA in September 2020, Pfizer has hired Ventavia as a research subcontractor on four other vaccine clinical trials (covid-19 vaccine in children and young adults, pregnant women, and a booster dose, as well an RSV vaccine trial; NCT04816643, NCT04754594, NCT04955626, NCT05035212). The advisory committee for the Centers for Disease Control and Prevention is set to discuss the covid-19 paediatric vaccine trial on 2 November.

Speaking off the record, other employees confirmed that the fired employee’s concerns were valid:
  • “Everything that you complained about was spot on.”
  • “I don’t think it was clean data. It’s a crazy mess.”
  • “I’ve never had to do what they were asking me to do, ever, It just seemed like something a little different from normal—the things that were allowed and expected.”
  • One employee with over 4-dozen clinical trials under her belt said she had never experienced such a “helter skelter” work environment.
  • Ventavia lacked enough employees to test trial participants who reported COVID-like symptoms, which is important because symptomatic COVID was the trial’s primary endpoint.  An FDA review showed that swabs were not taken from 477 people with suspected COVID.

____________________

For more on Pfizer’s corruption:

https://live.childrenshealthdefense.org/shows/doctors-and-scientists-with-brian-hooker-phd  Video Here from Oct. 28, 2021

Live Every Thursday at 9:00a.m. PT, 11:00a.m. CT, 12:00p.m. ET

Got Science? Are you sure?

‘Doctors And Scientists’ With Brian Hooker, PHD.

Dr. Brian Hooker invites some of the leading voices in science and medicine to break down the studies and weigh in on the controversies so the rest of us have an opportunity to understand the science that drives public health policy and medical progress.

See previous episodes within link as well.

For more:

58% of Infant Deaths Reported to VAERS Occurred Within 3 Days of Vaccination, Research Shows & ‘This is Really a Giant Experiment’

58% of Infant Deaths Reported to VAERS Occurred Within 3 Days of Vaccination, Research Shows

© [8/3/21] Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.

In a new research paper published in the journal Toxicology Reports, author Neil Z. Miller found that out of a total of 2,605 infant deaths reported to VAERS between 1990 and 2019, 58% occurred within three days of vaccination, and 78% occurred within seven days of vaccination.

In a new research paper published in the journal Toxicology Reports, author Neil Z. Miller reports on the relationship between sudden infant death syndrome (SIDS) death and the timing of vaccination, based on the Center for Disease Control and Prevention’s (CDC) Vaccine Adverse Events Reporting System (VAERS) database.

SIDS is defined as the sudden and unexpected death of an infant that remains unexplained after a thorough investigation. Although there are no specific symptoms associated with SIDS, an autopsy often reveals congestion and edema of the lungs and inflammatory changes in the respiratory system, according to the National Center for Health Statistics Vital Statistics of the United States 1988, Volume II, Mortality, Part A, Public Health Service, 1991.

Prior to contemporary vaccination programs, SIDS — sometimes referred to as “crib death” — was so infrequent it was not mentioned in infant mortality statistics.

After the national immunization campaigns were initiated in the U.S. in the 1960s, for the first time in history, most U.S. infants were required to receive several doses of DPT, polio, measles, mumps and rubella vaccines.

Shortly after, in 1969, medical certifiers presented a new medical term — sudden infant death syndrome.

In 1973, the CDC’s National Center for Health Statistics added a new cause-of-death category — SIDS — to the World Health Organization’s International Classification of Diseases (ICD).

By 1980, SIDS had become the leading cause of postneonatal mortality (deaths of infants from 28 days to one year old) in the U.S.

As Miller points out in his article, the ICD category for vaccine-related death, or cause of death as “prophylactic inoculation and vaccination,” was eliminated when the ICD was revised in 1979 — despite the fact that this information would be useful in trying to understand the relationship between vaccination and death.

But Miller, a medical research journalist and the director of the Thinktwice Global Vaccine Institute, provides an alternative route for establishing such a correlation — by observing the temporal relationship between vaccines and reported infant deaths, including SIDS deaths, in the CDC’s VAERS database.

Miller found that out of a total of 2,605 infant deaths reported to VAERS from 1990 through 2019, the majority “clustered” in close temporal proximity to vaccination — 58% occurred within three days of vaccination, and 78% occurred within seven days of vaccination.

Miller found the excess deaths within these ranges were statistically significant (p<0.00001), meaning the chance that this result is random is less than 0.001%.

The same type of clustering was present in the 1,048 reports of infant deaths (out of the total 2,605) reported to VAERS specifically as SIDS.

According to Miller, if there were no correlation between vaccination and infant deaths, one would expect to see an even spacing of deaths within the time range reported prior to vaccination —- not a clustering of deaths as Miller found.

Miller included a comprehensive literature review in his paper refuting the “official” claim that the SIDS epidemic was curtailed by having infants sleep on their backs — as recommended by the “Back to Sleep” campaign, initiated in 1992 by the American Academy of Pediatrics.

The subsequent rate of SIDS dropped by an annual average of 8.6% between 1992 and 2001. However, the neonatal mortality rate due to “suffocation in bed” increased during that same time at an average annual rate of 11.2%.

Other similar causes of infant death also increased significantly during this period, as reported by Miller. Further, from 1999 through 2015, the U.S. SIDS rate declined 35.8%. while infant deaths due to accidental suffocation increased 183.8 %.

Miller also affirms his main results from the paper (i.e., the temporal clustering of SIDS deaths with vaccination) through the discussion of seven additional peer-reviewed studies and two confidential reports.

On average, these authors found that substantial proportions of infant deaths occurred within one day (mean = 25%), three days (mean = 49%) and seven days (mean = 71%) post-vaccination, matching the results of the present study.

Mechanistically, vaccine injury has been tied to SIDS multiple times. Matturri et al. (2014) examined 13 SIDS deaths occurring within seven days of a hexavalent vaccine.  Analysis of the brainstem and cerebellum of the deceased infants showed brain edema and congestion in all victims.

The authors hypothesized that “several compounds and immuno-potentiation adjuvants of the hexavalent vaccine might easily go beyond the blood-brain barrier, which in the first year of life is still immature and quite permeable, inducing neuronal molecular alterations in DNA, RNA and proteins of brainstem neurons regulating vital functions, with consequent fatal disorganization of respiratory control in particularly predisposed infants.”

Specifically, these authors implicated aluminum-based adjuvants in the dysregulation of respiratory control.

Scheibner and Karlsson (1991) monitored infant breathing during sleep before and after the DPT vaccination, revealing an increase in episodes where breathing nearly ceased or stopped completely. These episodes, which continued for several weeks post-vaccination, were not seen prior to vaccination.

Despite the official insistence that SIDS deaths are not caused by vaccination, as Miller points out, the National Vaccine Injury Compensation (NVICP) is set up to compensate families of individuals who are injured and/or die from vaccine administration.

Death from vaccination is compensated with $250,000 for “pain and suffering” to family members of the deceased victim. Conditions typically leading to death that are considered “table injuries” to be compensated under the NVICP include anaphylaxis and encephalopathy or encephalitis.

‘Healthy babies just don’t die for no apparent reason’

Kari Bundy, who lost her son after his four-month vaccinations, said she’s always been “flabbergasted” at the denial of the medical community of the link between SIDS and vaccines. “For me, it was too obvious to even attempt to ignore,” Bundy said.

Bundy lost her third-born child, Mason, in 2011.

“A few days after his routine four-month vaccinations, my husband and I discovered his dead body in the middle of the night, laying on his side, his body still warm,” Bundy said

Mason’s autopsy came back “unremarkable,” aside from some thymic petechiae, which is the most common gross finding in SIDS cases at autopsy.

“I was assured time and time again that he had not suffocated,” Bundy said.

When Mason died, Bundy learned if you can’t pay for a funeral, you can’t have one. So a few months after Mason’s death, she founded a nonprofit called Mason’s Cause, to provide grants to cover funeral costs for families who had experienced the loss of a child under the age of 1.

“I never wanted any parent to experience this devastating loss and not be able to bury their child,” Bundy said. She continued running the charity for just under 2 years, during which time she worked with 94 different families who experienced the death of a child under age 1.

Of those 94 infant deaths, 87 died from SIDS, or from causes “unknown.” Of the SIDS cases, 81 — or 93% — died within seven days of routine vaccinations.

“When I realized SIDS seemed to be undeniably related to vaccines, I realized I could no longer dedicate my life to running a charity that would help bury babies,” Bundy said. “That’s when I realized I wanted to save babies by speaking out about the real risks of vaccination.”

Bundy, who works for Children’s Health Defense as translations coordinator, said she’s grateful for research like Miller’s because it shows what she and all SIDS parents already knew — healthy babies don’t just die for no apparent reason.

Listen to the interview with Neil Miller, author of the study of SIDS and vaccines, on the “Right on Point” Podcast by clicking on top link.

________________

https://www.theblaze.com/news/ben-carson-covid-vaccinations-children-giant-experiment

Dr. Ben Carson blasts COVID vaccinations for children: ‘This is really a giant experiment’

Excerpt from article:
“Plus, we don’t know what the long-term impact of these vaccines is, so this is really sort of a giant experiment,” Carson explained. “Do we want to put our children at risk, when we know that the risk of the disease to them is relatively small, but we don’t know what the future risks are? Why would we do a thing like that? It makes no sense whatsoever.” Dr. Ben Carson

For more:

Increase in Tick Bites During COVID-19 Pandemic

https://danielcameronmd.com/increase-in-tick-bites-during-covid-19-pandemic/

Increase in tick bites during COVID-19 pandemic

tick-bites-COVID-19

In a recent article, “Effects of COVID-19 Pandemic on Reported Lyme Disease, United States, 2020,” McCormick and colleagues assessed how the pandemic might influence the risk of tick bites and affect patients seeking medical care and the reporting of Lyme disease cases.

“The data suggested that individuals were more likely to spend time outside, more likely to visit the CDC website describing tick bite removal, were less likely to visit an ER, and tested for Lyme disease,” according to the authors.¹

Approximately 50% of U.S. residents spent more time outdoors in 2020 than in 2019, but fewer tick bite–related emergency department visits and Lyme disease laboratory tests were reported, according to a survey by Porter Novelli.¹ “Only 20.9% of respondents reported spending less time outdoors in 2020.”

Furthermore, there was an 25% increase in visits to the CDC’s website page which describes tick bite removal procedures.

ED visits for tick bites

Despite an increase in tick bite exposures, there was a decrease in the number of individuals visiting the Emergency Department (ED) for tick bites and fewer tests for Lyme disease. “The largest relative decreases were observed in May,” according to the authors.

During the month of May, between 2017 and 2019, there was an average of 12,693 ED visits for tick bites. However, in May 2020, only 5,845 ED visits for tick bites occurred. And, the number of Lyme disease tests decreased by 25%.

“These findings suggest that the risk of acquiring Lyme disease was similar or potentially higher in 2020 compared with risk during prior years, but fewer persons sought care, and fewer positive laboratory reports were referred for case investigation.”

The authors point out, “Lyme disease case reporting for 2020 might be artificially reduced due to coronavirus disease–associated changes in healthcare-seeking behavior,” the authors point out.

 Editor’s perspective

I have had Lyme disease patients who have put delayed visiting the Emergency Department or their doctor’s office during the COVID-19 pandemic.  I’ve also had Lyme disease patients who were initially tested for COVID-19 but not Lyme disease. Their treatment for Lyme disease was delayed, making it more difficult to treat them.

Rickettsia burneti and Brucella melitensis Co-Infection: A Case Report & Literature Review

https://bmcmicrobiol.biomedcentral.com/articles/10.1186/s12866-021-02323-x

Rickettsia burneti and Brucella melitensis co-infection: a case report and literature review

Abstract

Rickettsia is the pathogen of Q fever, Brucella ovis is the pathogen of brucellosis, and both of them are Gram-negative bacteria which are parasitic in cells. The mixed infection of rickettsia and Brucella ovis is rarely reported in clinic. Early diagnosis and treatment are of great significance to the treatment and prognosis of brucellosis and Q fever. Here, we report a case of co-infection Rickettsia burneti and Brucella melitensis. The patient is a 49-year-old sheepherder, who was hospitalized with left forearm trauma. Three days after admission, the patient developed fever of 39.0°C, accompanied by sweating, fatigue, poor appetite and headache. Indirect immunofluorescence (IFA) was used to detect Rickettsia burneti IgM. After 72 hours of blood culture incubation, bacterial growth was detected in aerobic bottles, Gram-negative bacilli were found in culture medium smear, the colony was identified as Brucella melitensis by mass spectrometry. Patients were treated with doxycycline (100 mg bid, po) and rifampicin (600 mg qd, po) for 4 weeks. After treatment, the symptoms disappeared quickly, and there was no sign of recurrence or chronic infection. Q fever and Brucella may exist in high-risk practitioners, so we should routinely detect these two pathogens to prevent missed diagnosis.

Artemisinin From Sweet Wormwood Inhibits SARS-CoV-2 & Two New Studies Test Quercetin And COVID Outcomes

https://articles.mercola.com/sites/articles/archive/2021/10/20/artemisinin-from-sweet-wormwood-inhibits-sars-cov-2.

Artemisinin From Sweet Wormwood Inhibits SARS-CoV-2

Analysis by Dr. Joseph Mercola Fact Checked

Story at-a-glance

  • An antimalarial treatment made from the plant Artemisia annua (Sweet Wormwood) shows promise as a COVID-19 treatment
  • The drug artesunate — which contains two compounds found in Artemisia annua: artemisinin and dihydroartemisinin — is a first-line treatment for malaria
  • In a recent in vitro study, both pretreatment and treatment with artemisinin extracts, synthetic artemisinin and the drug artesunate were able to inhibit SARS-CoV-2 infection. However, artesunate was the most potent in terms of treatment, and from a clinical perspective may be the only one worth pursuing
  • Artesunate’s mechanism of action against SARS-CoV-2 is as yet unknown, but artemisinin does have confirmed antiviral activity
  • The World Health Organization has come out in opposition to artemisinin-based products, warning their use can bolster drug-resistant strains of malaria parasites. For this reason, people living in malaria-prone areas should be cautious about using this plant remedy

This article was previously published January 4, 2021, and has been updated with new information.

A second antimalarial treatment is now being seriously considered and evaluated for its efficacy against COVID-19. The treatment is made from the plant Artemisia annua, which most people know as Sweet Wormwood. Other names for this plant include Annual Sagewort and Sweet Annie.

Research over the past few decades has revealed multiple health benefits from this medicinal herb, which has a centuries-long history of use in folk medicine. In 2015, Chinese scientist Tu Youyou received a partial Nobel Prize in Physiology or Medicine for his discovery of artemisinin and dihydroartemisinin,1 both of which have potent malaria-fighting properties.

As reported by the University of Kentucky,2 “The popular malaria drug artesunate was developed from those compounds and is still used as a first-line treatment for the disease today.”

Artemisinin — A Viable COVID-19 Remedy?

Interestingly, in addition to having a long-standing history of being used as a highly effective antiparasitic, it also has anticancer properties. Additionally, artemisia annua has antiviral activity that might be helpful against SARS-CoV-2.

In an April 8, 2020, SEC filing, Mateon Therapeutics reported3 that “Artemisinin is highly potent at inhibiting the ability of the COVID-19 causing virus (SARS-CoV-2) to multiply while also having an excellent safety index.”

After testing the plant’s antiviral effects in a laboratory setting for a couple of years, University of Kentucky researchers are also exploring its use for the treatment of COVID-19,4 as are researchers in Denmark and Germany.5 According to the University of Kentucky:6

“Surprisingly, results showed that the plant’s leaves, when extracted with absolute ethanol or distilled water, provided more antiviral activity than the actual drug itself — meaning that an Artemisia annua-blended coffee or tea could possibly be more effective than taking the drug.”

Based on these findings, researchers have decided to test artemisinin in patients diagnosed with COVID-19. Some of the first human studies, set to investigate both the extract blended into coffee and tea, as well as the drug artesunate, were implemented by UK HealthCare.

University of Kentucky researchers have founded a company called ArtemiFlow to develop and manufacture the drug, in collaboration with the Kentucky Tobacco Research & Development Center.7 A sister company, ArtemiLife, is marketing Artemisia tea and coffee to raise research funds.

Mechanism of Action Remains Unknown

As for its mechanism of action, such details still remain to be discovered. C&EN explains:8

“When countering malaria, artemisinin exploits the parasite’s taste for hemoglobin in its host’s blood. As the parasite digests hemoglobin, it frees the iron-porphyrin heme complex from the protein.

Because this heme is toxic to the parasite, the organism normally converts the complex to a more benign crystalline form. ‘But artemisinin corrupts this heme-detoxification pathway,’ says Paul O’Neill, a medicinal chemist at the University of Liverpool.

If artemisinin does have any effect against SARS-CoV-2, though, it likely relies on a completely different mechanism than the one it uses against the malaria parasite, Harvard’s [malaria researcher Dyann F.] Wirth says.”

In Vitro Study Reports Positive Results

An in vitro study9,10 looking at the efficacy of artemisinin-based treatments against SARS-CoV-2, posted on the prepublication server bioRxiv, October 5, 2020, report promising results.

The study was a collaboration between researchers from Germany, Denmark and Hong Kong, led by Kerry Gilmore, Ph.D., from the Max Planck Institute for Colloids and Interfaces in Potsdam, Germany.

Three artemisinin extracts, as well as pure, synthetic artemisinin, artesunate and artemether were evaluated. During the initial screening for antiviral activity, a German SARS-CoV-2 strain obtained from Munich was used.

Later on, during the concentration-response phase of the trial, they used a Danish SARS-CoV-2 strain from Copenhagen. These two strains are said to be “more closely related to the majority of SARS-CoV-2 strains circulating worldwide than the Wuhan strain.”11,12

In summary, they found that both pretreatment and treatment with artemisinin extracts, synthetic artemisinin and the drug artesunate were able to inhibit SARS-CoV-2 infection of Vero E6 cells and human hepatoma Huh7.5 cells. That said, artesunate was the most potent in terms of treatment, and from a clinical perspective may be the only one worth pursuing.13,14

World Health Organization Warns Against Its Use

While the world is eager to add another remedy to its COVID-19 treatment list, the World Health Organization has come out in opposition to artemisinin-based products. In a May 27, 2020, article, C&EN reported:15

“One of the most high-profile advocates for using the herbal remedy against the novel coronavirus is Madagascar president Andry Rajoelina, who has been touting Covid-Organics, a tonic containing A. annua that the Malagasy Institute of Applied Research developed …

But health officials are deeply concerned about the promotion and use of these herbal remedies for three principal reasons. First, no evidence exists that A. annua extracts can prevent or cure COVID-19 …

Second, A. annua preparations such as teas, tonics, or herbal capsules also contain a cocktail of bioactive compounds in addition to artemisinin that can have side effects such as dizziness, hearing problems, and vomiting.

Third, and perhaps most worrying of all, widespread use of A. annua herbal extracts could bolster drug-resistant strains of malaria parasites such as Plasmodium falciparum.16

For people living in regions where malaria is endemic, exposure to subtherapeutic doses of artemisinin in A. annua may be enough to kill off some of the parasites in their bodies, but not all of them. Clearing out weakling parasites leaves more room for drug-resistant siblings to proliferate, rendering vital ACTs [artemisinin-based combination therapies] ineffective.”

According to Pascal Ringwald, who heads up the drug resistance and response unit of the WHO Global Malaria Program, artemisinin resistance is a significant problem in Southeast Asia, where Artemisia readily grows and is commonly used.17

That said, this risk is bound to be slight for Americans and people in many other Western countries where malaria is exceedingly rare. According to C&EN,18 “Scientists interviewed by C&EN agree that although this use is against WHO recommendations, it does not risk accelerating resistance because there are so few cases of malaria in the U.S.”

– Sources and References

_________________

https://articles.mercola.com/sites/articles/archive/2021/10/14/quercetin-improves-covid-outcomes

Two New Studies Test Quercetin And COVID Outcomes

Analysis by Dr. Joseph Mercola Fact Checked
quercetin improves covid outcomes
Story at-a-glance
  • Two recently published studies confirm quercetin is useful as an adjunct therapy in the early outpatient treatment of mild SARS-CoV-2 infection
  • In one study, COVID patients who received quercetin in addition to analgesics and an antibiotic cleared the virus faster than those who only received analgesics and antibiotics, and a greater number of patients reported reduced symptoms
  • In the second study, daily quercetin supplementation for one month reduced the frequency and length of hospitalization, the need for noninvasive oxygen therapy, intensive care and deaths
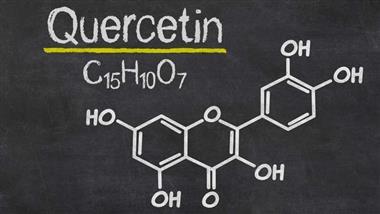
  • Quercetin has antiviral, anti-blood clotting, anti-inflammatory and antioxidant properties, all of which are important in the treatment of SARS-CoV-2 infection
  • Quercetin also inhibits binding of specific spike proteins to your ACE2 receptors, thereby blocking the virus’ ability to infect your cells. It’s also been shown to directly neutralize viral proteins that are critical in the replication of SARS‐CoV‐2

In an August 21, 2021, newsletter,1 Dr. Michael Murray discussed the use of quercetin for respiratory infection symptoms. In November 2020, he’d suffered a “very mild and brief bout of COVID-19.”

He also recounts an anecdotal story of a friend who developed suspicious respiratory symptoms. His friend had been taking a number of supplements said to offer protection, but was still feeling awful.

As it turns out, the one thing he’d not taken was quercetin, and as soon as he did, that same day, his symptoms started to dissipate. This experience, Murray says, “is consistent with the results from two clinical trials” that were recently published.

Quercetin seems to be a safe, far less expensive, and easier-to-obtain and it works by a similar mechanism, driving zinc into the cells to stop viral replication.

Statistical Improvement in Clinical Outcomes

In the first study,2 42 COVID-19 outpatients were divided into two groups. One group of 21 patients received standard medical therapy consisting of analgesics and an antibiotic (acetaminophen 500-milligram (mg) to 1,000-mg dose if body temperature was higher than 37.5 degrees C — 99.5 F — with a maximum daily dosage of 3 grams, and 500 mg azithromycin for three consecutive days).

The other group of 21 patients received standard therapy plus the equivalent of 600 mg of quercetin per day (divided into three doses) for seven days, followed by another seven-day course of 400 mg of quercetin per day (divided into two doses).

The quercetin was used with sunflower lecithin, which has been demonstrated to increase absorption in the gut by as much as 20 times, compared to pure quercetin formulations.

The main outcomes being evaluated were virus clearance and symptoms. After one week of treatment, 16 of the 21 patients in the quercetin group tested negative for SARS-CoV-2 and 12 reported that all symptoms had diminished.

In the standard care group, only two tested negative and four had partially improved symptoms. By the end of Week 2, the five remaining patients in the quercetin group tested negative. In the standard care group, 17 of the 19 remaining patients tested negative and one had died.

“These results are impressive and hopefully additional studies will be conducted on hospitalized patients to see how quercetin might be helpful in more severe cases,” Murray wrote in his newsletter.

Can Quercetin Reduce Hospitalizations and Deaths?

The second study3 — a prospective, randomized, controlled and open-label trial — gave 152 COVID-19 outpatients a daily dose of 1,000 mg of quercetin for 30 days to evaluate its adjuvant effects in the treatment of early symptoms and the prevention of severe infection. According to the authors:

“The results revealed a reduction in frequency and length of hospitalization, in need of non-invasive oxygen therapy, in progression to intensive care units and in number of deaths. The results also confirmed the very high safety profile of quercetin and suggested possible anti-fatigue and pro-appetite properties.

QP (Quercetin Phytosome®) is a safe agent and in combination with standard care, when used in early stage of viral infection, could aid in improving the early symptoms and help in preventing the severity of COVID-19 disease. It is suggested that a double-blind, placebo-controlled study should be urgently carried out to confirm the results of our study.”

Mechanisms of Action

As noted in the first study4 above, quercetin was chosen based on the fact that it has antiviral, anti-blood clotting, anti-inflammatory and antioxidant properties, all of which are important in the treatment of SARS-CoV-2 infection. In the second study, more detailed mechanisms of action are reviewed. According to the authors:5

“SARS-CoV-2 proteases, like 3-chymotrypsin-like protease (3CLpro), papain-like pro-tease (PLpro), RNA-dependent RNA polymerase, spike (S)protein and human angiotensin-converting enzyme 2 (hACE2) are considered possible targets for developing effective anti-COVID-19 drugs.

Recently, molecular docking studies have suggested the possible binding interaction of quercetin with the 3CLpro, PLpro, and S-hACE2 complex. Some recent results, obtained by biophysical techniques, appear to support the results of the molecular docking studies.

Quercetin, a flavonol not naturally present in the human body, is the most abundant polyphenol in fruits and vegetable and is widely used as a dietary supplement to boost the immune system and promote a healthy lifestyle.

Quercetin is characterized by three crucial properties: antioxidant, anti-inflammatory and immunomodulatory. The combination of these actions allows quercetin to be a potential candidate to support all unhealthy conditions where oxidative stress, inflammation and immunity are involved.”

Initially, quercetin gained attention because it’s a zinc ionophore, meaning it shuttles zinc — which has well-known antiviral effects — into your cells just like the drug hydroxychloroquine.

Some proposed the primary reason hydroxychloroquine and quercetin worked was because of this feature. Of course, you also had to take zinc along with either of them. To effectively act as a zinc ionophore, the quercetin also needs vitamin C.

Since then, other studies, including the two reviewed here, have shown quercetin has other actions that makes it useful against SARS-CoV-2 as well. As reported by Murray in his newsletter:

“In particular, quercetin exerts significant inhibition on the binding of specific spike proteins to ACE-2 receptors, thereby blocking the ability of the virus to infect human cells. Quercetin has also been shown to directly neutralize viral proteins the are critical in the replication of SARS-CoV-2.”

In some studies, quercetin has also been shown to inhibit the release of inflammatory cytokines, which could help alleviate infection-related symptoms and suppress excessive inflammatory responses from occurring. Its antioxidant effects may also help prevent tissue damage caused by scavenging free radicals, thereby aiding in the recovery process of viral infections.6

Quercetin’s Antiviral Properties

Quercetin’s antiviral properties have been attributed to three main mechanisms of action:

  1. Inhibiting the virus’ ability to infect cells
  2. Inhibiting replication of already infected cells
  3. Reducing infected cells’ resistance to treatment with antiviral medication

For example, research7 funded by the U.S. Defense Advanced Research Projects Agency (DARPA), published in 2008, found it lowers your risk of viral illness such as influenza and boosts mental performance following extreme physical stress, which might otherwise undermine your immune function and render you more susceptible to infections.

Here, cyclists who received a daily dose of 1,000 mg of quercetin in combination with vitamin C (which enhances plasma quercetin levels8,9) and niacin (to improve absorption) for five weeks were significantly less likely to contract a viral illness after bicycling three hours a day for three consecutive days, compared to untreated controls. While 45% of the placebo group got sick, only 5% of the treatment group did.

Quercetin Works Against Many Common Viruses

Before the COVID-19 pandemic struck, several studies had highlighted quercetin’s ability to prevent and treat the common cold and seasonal influenza.10,11,12,13,14,15,16,17,18 By attenuating oxidative damage, it also lowers your risk of secondary bacterial infections,19 which is actually the primary cause of influenza-related deaths.

Importantly, quercetin increases mitochondrial biogenesis in skeletal muscle, which suggests part of its antiviral effects are due to enhanced mitochondrial antiviral signaling.20 Quercetin also works against other viruses, as demonstrated in the following studies:

• A 1985 study found quercetin inhibits infectivity and replication of herpes simplex virus type 1, polio-virus type 1, parainfluenza virus type 3 and respiratory syncytial virus (RSV).21

• A 2016 animal study22 found quercetin inhibited mouse dengue virus and hepatitis virus.

• Other studies have confirmed quercetin’s power to inhibit both hepatitis B23 and C24 infection.

• A March 2020 study25 found quercetin provides “comprehensive protection” against Streptococcus pneumoniae infection, both in vitro and in vivo, primarily by neutralizing pneumolysin (PLY),26 one of the toxins released from pneumococci that encourages S. pneumoniae infection to blossom in the first place.

Streptococcus pneumoniae is responsible not only for pneumonia, but can also be involved in some ear and sinus infections, meningitis and certain blood infections.27 As reported by the authors of this study:28

“The results indicated that quercetin significantly reduced PLY-induced hemolytic activity and cytotoxicity via repressing the formation of oligomers.

In addition, treatment with quercetin can reduce PLY-mediated cell injury, improve the survival rate of mice infected with a lethal dose of S. pneumoniae, alleviate the pathological damage of lung tissue and inhibit the release of cytokines (IL-1β and TNF-α) in bronchoalveolar lavage fluid.

Considering the importance of these events in antimicrobial resistant S. pneumoniae pathogenesis, our results indicated that quercetin may be a novel potential drug candidate for the treatment of clinical pneumococcal infections.”

How Quercetin Combats Inflammation and Boosts Immunity

Aside from its antiviral activity, quercetin is also known for boosting immunity and combating inflammation. As noted in a 2016 study29 in the journal Nutrients, mechanisms of action include (but is not limited to) the inhibition of:30

  • Lipopolysaccharide (LPS)-induced tumor necrosis factor α (TNF-α) production in macrophages. TNF-α is a cytokine involved in systemic inflammation, secreted by activated macrophages, a type of immune cell that digests foreign substances, microbes and other harmful or damaged components
  • LPS-induced mRNA levels of TNF-α and interleukin (IL)-1α in glial cells, which results in “diminished apoptotic neuronal cell death”
  • The production of inflammation-producing enzymes
  • Calcium influx into the cell, which in turn inhibits pro-inflammatory cytokine release, as well as histamine and serotonin release from intestinal mast cells31

According to this paper, quercetin also stabilizes mast cells, has cytoprotective activity in the gastrointestinal tract, and “a direct regulatory effect on basic functional properties of immune cells,” which allows it to inhibit “a huge panoply of molecular targets in the micromolar concentration range, either by down-regulating or suppressing many inflammatory pathways and functions.”32

Bioavailability

While quercetin does have potent antiviral effects, in order for it to work effectively you need sufficiently high dosages to raise the level of quercetin in your body’s tissues.

The relatively low absorption rate of quercetin is why a sunflower lecithin formulation was used.

Research33 published in the July-December 2021 issue of the Journal of Natural Health Products Research, found a quercertin matrix has the same total absorption rate as quercetin phytosome — and higher peak blood levels.

“Since both of these forms of quercetin produce similar blood levels, they should produce the same effects at equal dosages based upon quercetin content,” Murray wrote in his newsletter, adding:

“My dosage recommendation as part of a nutritional supplement program to support immune function is 250 mg twice daily.

And in patients with active Infection, my recommendation is … six capsules twice a day providing a total of 3,000 mg of quercetin. This high dosage should be taken for at least 10 days and then reduced to a maintenance dosage of 250 mg twice daily …

[This] high dosage may not be necessary. But my dosage calculations are based upon likely tissue concentrations needed to exert the strongest antiviral effects. And given the safety of quercetin, there is no harm at this level.”

Protocol Using Quercetin

One doctor who early brought quercetin into the limelight was Dr. Vladimir Zelenko. As hydroxychloroquine became difficult to obtain, Zelenko switched to recommending quercetin instead, as it’s readily available as an over-the-counter supplement. For a downloadable “cheat sheet” of Zelenko’s protocol for COVID-19, visit VladimirZelenkoMD.com.

Other Health Benefits of Quercetin

There are also other lesser known benefits and uses for quercetin, including the prevention and/or treatment of:34

High blood pressure35,36
Cardiovascular disease37
Obesity38 and metabolic syndrome39 (a cluster of conditions including high blood pressure, high blood sugar, high triglyceride levels and fat accumulation around the waist that raise your risk for Type 2 diabetes, heart disease and stroke)
Certain kinds of cancer, in particular leukemia, and to a lesser degree breast cancer40
Nonalcoholic fatty liver disease (NAFLD)41
Gout42
Arthritis43
Mood disorders44
Aluminum-induced neurodegenerative changes, such as those seen in Alzheimer’s, Parkinson’s and amyotrophic lateral sclerosis (ALS).45
Longevity, thanks to its senolytic benefits (clearing out damaged and worn-out cells)46,47

Research has also highlighted quercetin’s epigenetic influence and ability to:48

  • Interact with cell-signaling pathways
  • Modulate gene expression
  • Influence the activity of transcription factors
  • Modulate microRNAs

MicroRNAs used to be considered “junk” DNA. But far from being useless, research has revealed so-called “junk” DNA is actually microRNA and plays a crucial role in regulating genes that make the proteins that build your body.

The microRNA function as “on/off” switches for the genes. Depending on the microRNA input, a single gene can code for any of more than 200 protein products. Quercetin’s ability to module microRNA may also help explain its cytotoxic effects, and why it appears to improve cancer survival (at least in mice).

– Sources and References