Archive for the ‘research’ Category

Dr. Gatti is Back: New Paper Shows Metals and Parasites in Plasma From a Treated Lyme/MSIDS Patient & That DFPP With Chelating Agents Might Detox These Microparticles

https://popularrationalism.substack.com/p/pollutants-in-human-plasma-found

Pollutants in Human Plasma Found via Double-Filtration Plasmapheresis Plasma Exchange

Studies in toxicology usually study urine, feces, and other secretions and measure indirectly. Dr. Gatti, whose lab was raided for reporting detection of nanoparticles in vaccines, has a new study.

Does everyone remember Drs. Gatti and Montanari?  We flew them in from Italy in 2017 to the IPAK Vaccine Safety Conference in Pittsburgh, PA? Probably not.

To help you remember:  https://www.ageofautism.com/2018/02/the-european-medicines-agency-attacked-gatti-and-montanari-last-year-in-british-medical-journal.html

and

Earlier this year, Dr. Gatti let me know they are back up and running.

The new study is of pollutants and toxins found in the extract of eluate from double-filtration plasmapheresis plasma exchange.

The new study, by Dr. Gatti and Dr. Felix Scholkmann, is entitled:

Particles in the Eluate from Double Filtration Plasmapheresis—A Case Study Using Field Emission Scanning Electron Microscopy/Energy-Dispersive X-ray Spectroscopy (FE-SEM/EDX)

By using plasmapheresis, they found

“aflatoxin B1, chromium, lead, cadmium, arsenic, lindane, cobalt, polycyclic-aromatic-hydrocarbons, disulfoton and aluminium (listed in descending concentration).”

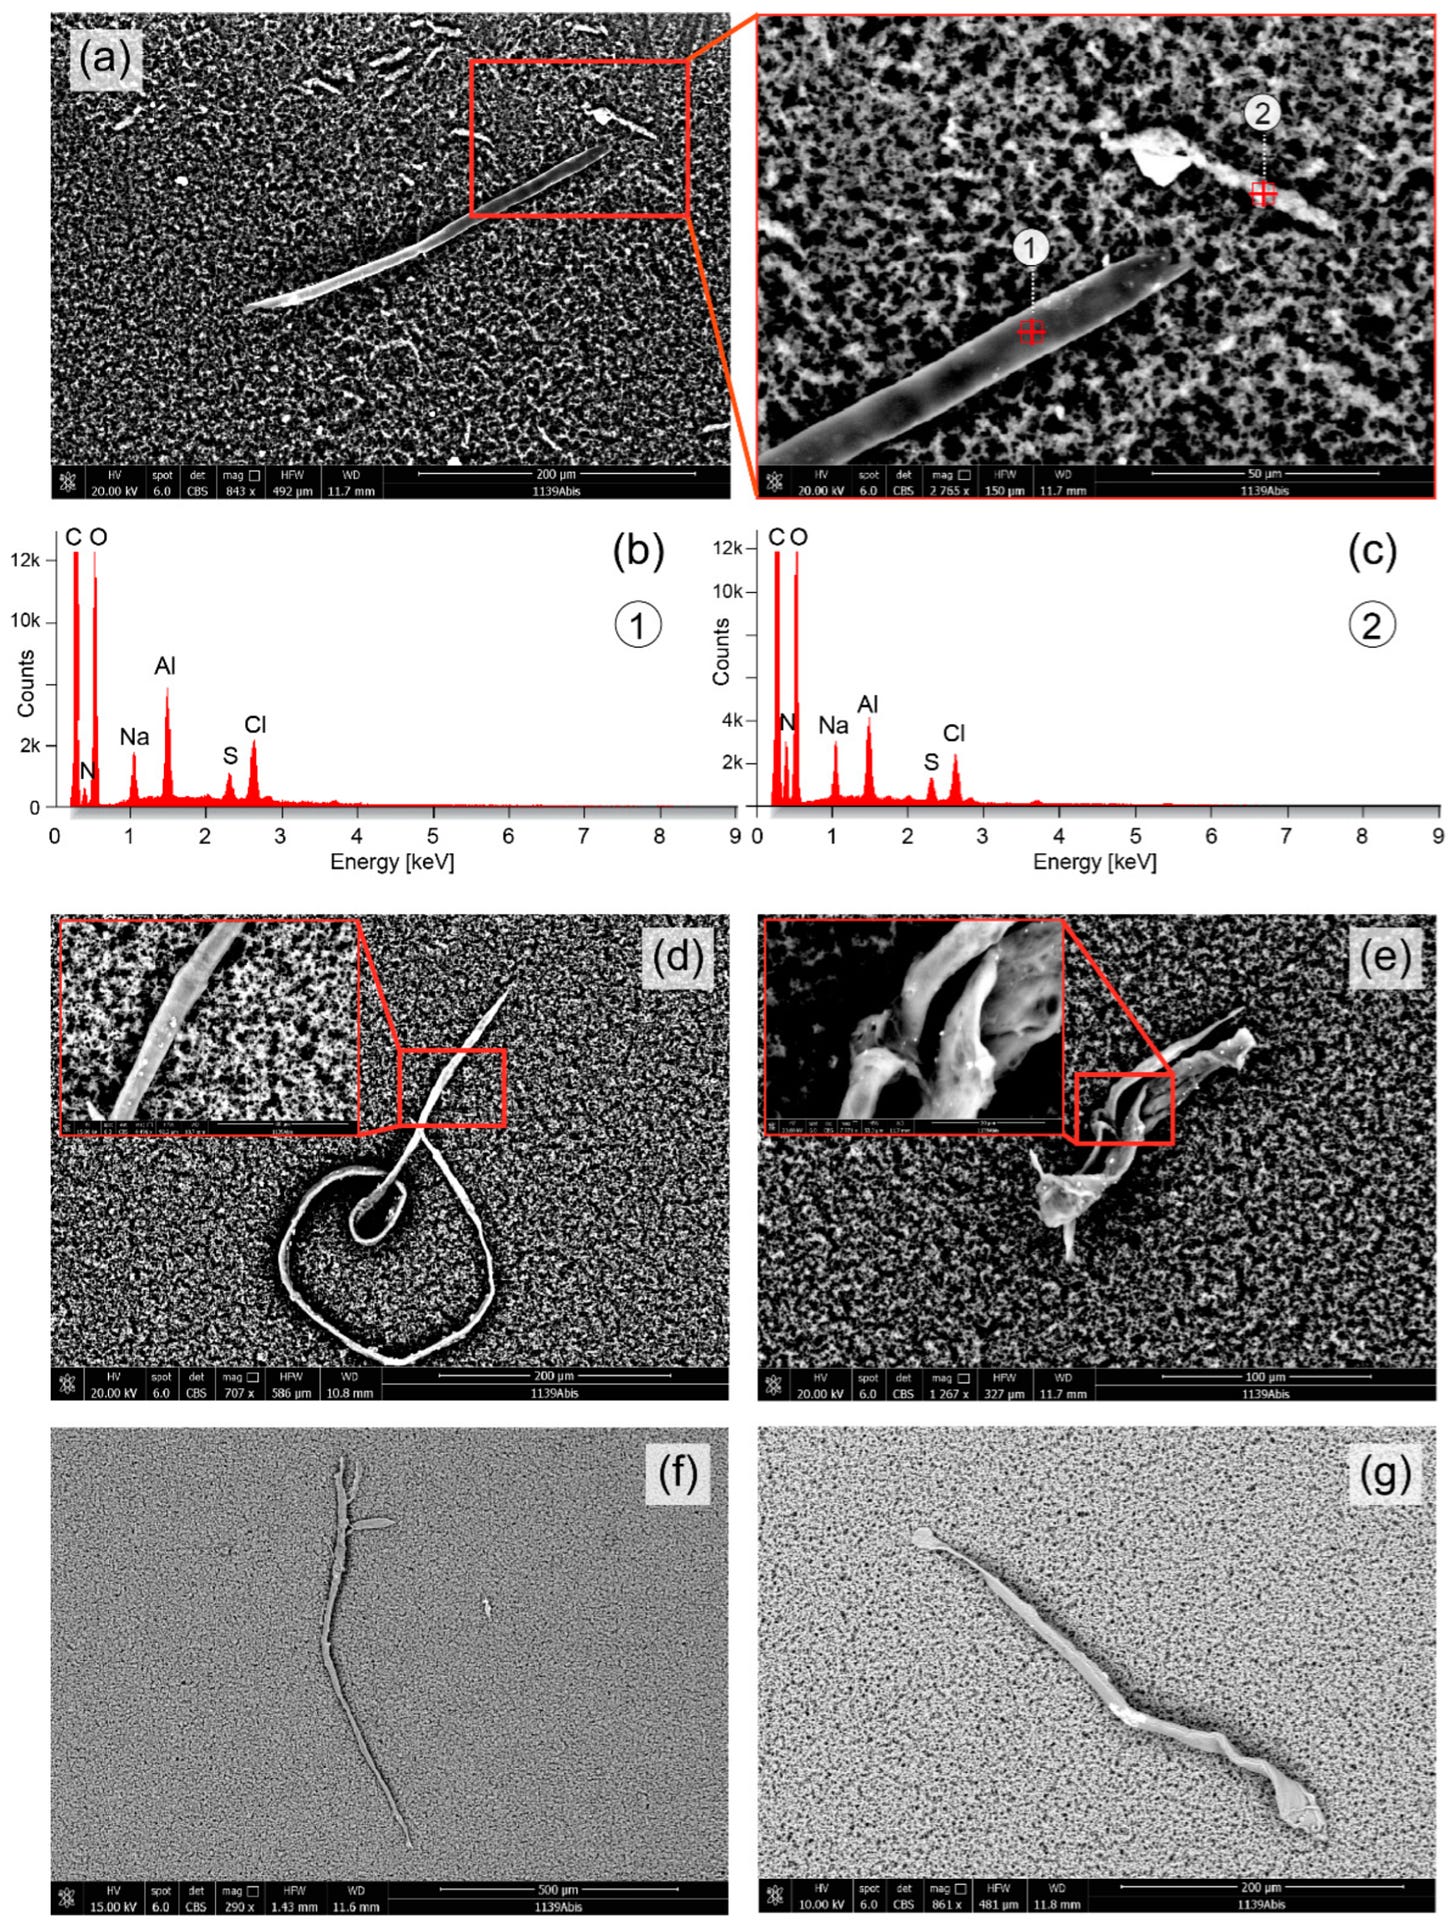
They also found unknown thread-like objects.

Makes me wonder if we should all detox this way once a year?

Dr. Gatti, congratulations on your new study and on surviving the attack on your lab by Italian authorities.

It should be possible to estimate the blood and body levels of compounds to which we are exposed, say, before and after vaccination.

Citation:

Scholkmann, Felix, and Antonietta M. Gatti. 2022. “Particles in the Eluate from Double Filtration Plasmapheresis—A Case Study Using Field Emission Scanning Electron Microscopy/Energy-Dispersive X-ray Spectroscopy (FE-SEM/EDX)” Compounds 2, no. 4: 367-377. https://doi.org/10.3390/compounds2040030

_______________

**Comment**

Plasmapheresis or plasma exchange, around since the 50’s, has been used to treat autoimmune conditions, blood disorders, viral infections, chronic inflammation, pulmonary fibrosis, MS, Graves’ disease, Myasthenia gravis, transverse myelitis, HIV-related neuropathy, cancer, and even Lyme/MSIDS. Plasma is extracted from your blood, treated, and then put back into the body.

The limitation of this study is it was on a singular patient who had been treated for the following chronic infections: 

  • Borrelia afzelii
  • Borrelia burgdorferi (CH)
  • Borrelia burgdorferi (USA)
  • Borrelia garinii
  • Chlamydia pneumoniae
  • Babesia divergens
  • Bartonella henselae
  • Rickettsia Helvetica
  • Rickettsia conorii
  • Rickettsia helvetica

The thread-like object in Figure 4d, however, has a similar morphology and size as a thread-like parasitic nematode (roundworm) of the superfamiliy Filarioridea. Ticks can be also infected with these filarial nematodes [59,60].

Excerpt:

The pollution of nano- and microparticles is an emerging health concern [32,61] and novel ways of quantifying the individual exposure as well as methods to remove these particles from the body are of imminent interest for preventing and treating human diseases. DFPP, possibly in combination with the application of chelating agents, might be a powerful way to remove these nano- and microparticles from the body. The analysis of the eluate with FE-SEM/EDX seems be a useful approach to proof this possibility.
In summary, our analysis of the eluate obtained from a DFPP application revealed particles and objects in the nm and µm range of different shape and chemical composition. Our study is the first to date to investigate the composition of an eluate obtained by DFPP with FE-SEM/EDX.
IMO, while plasmapheresis might certainly help Lyme/MSIDS, the organism(s) often don’t remain in the blood for long but migrate to immunopriviledged sites like the brain, synovial fluid, spine, and organs.  This is the problem with all treatments, and testing which rely on delivery via blood, and perfectly illustrates why the current CDC monotherapy is an absolute joke.  Further, it doesn’t take into account the relapsing nature of these pathogens which change forms in the body.  Savvy treatment purposely cycles antimicrobials which helps address these complex issues, which mainstream medicine/research is completely oblivious about.
This clearly illustrates why we should not give another dime to corrupt public health/research because insanity is doing the same thing over and over but expecting different results.
For more:

Genes As Biomarkers for Chronic Lyme?

https://www.lymedisease.org/35-genes-biomarkers-lyme/

Could these 35 genes be used as biomarkers for chronic Lyme?

Nov. 15, 2022

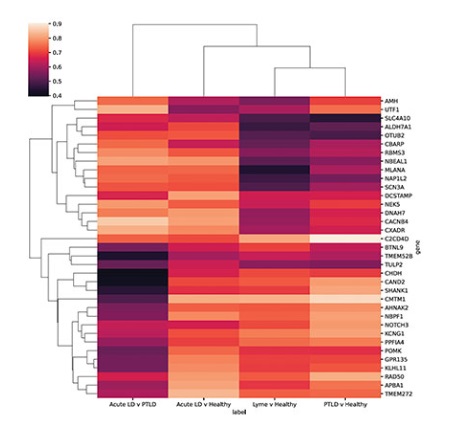
Researchers at the Icahn School of Medicine at Mount Sinai in New York have identified 35 genes that are particularly highly expressed in people with long-term Lyme disease.

These genes could potentially be used as biomarkers to diagnose patients with the condition, which is otherwise difficult to diagnose and treat.

The findings, published November 15 in the journal Cell Reports Medicine, may also lead to new therapeutic targets.

The study is the first to use transcriptomics as a blood test to measure RNA levels in patients with long-term Lyme disease.

Lyme disease is a tick-borne illness that is not well understood. Approximately 30,000 diagnosed cases are reported to the CDC each year, but the estimated real number is closer to 476,000 cases, carrying an annual healthcare cost of about $1 billion in the United States. While most patients are diagnosed and treated with antibiotics at the earliest stages of Lyme disease, about 20 percent of the patients develop long-term complications, which could include arthritis, neurologic symptoms, and/or heart problems.

“We wanted to understand whether there is a specific immune response that can be detected in the blood of patients with long-term Lyme disease to develop better diagnostics for this debilitating disease. There still remains a critical unmet need, as this disease so often goes undiagnosed or misdiagnosed,” said Avi Ma’ayan, PhD, Professor, Pharmacological Sciences, and Director of the Mount Sinai Center for Bioinformatics at Icahn Mount Sinai, and senior author of the paper. “Not enough is understood about the molecular mechanisms of long-term Lyme disease.”

Image above: Researchers at Icahn Mount Sinai in New York identified 35 genes that could be used as biomarkers to potentially diagnose patients with long-term Lyme disease. Image credit: Cell Reports Medicine

As part of the study, RNA sequencing was conducted using blood samples from 152 patients with symptoms of post-treatment Lyme disease to measure their immune response.

Differences in gene expression

Combined with RNA sequencing data from 72 patients with acute Lyme disease and 44 uninfected controls, the investigators observed differences in gene expression. They found that most of the post-treatment Lyme disease patients had a distinctive inflammatory signature compared with the acute Lyme disease group.

In addition, by analyzing the differentially expressed genes in this study along with genes that are differentially expressed due to other infections from other published studies, the researchers identified a subset of genes that were highly expressed, which have not been previously established for this Lyme-associated inflammatory response.

Using a type of artificial intelligence called machine learning, the researchers further reduced the group of genes to establish an mRNA biomarker set capable of distinguishing healthy patients from those with acute or post-treatment Lyme disease. A gene panel that measures the expression of the genes the investigators identified could be developed as a diagnostic to test for Lyme.

A new diagnostic for Lyme?

“We should not underestimate the value of using omics technologies, including transcriptomics, to measure RNA levels to detect the presence of many complex diseases, like Lyme disease. A diagnostic for Lyme disease may not be a panacea but could represent meaningful progress toward a more reliable diagnosis and, as a result, potentially better management of this disease,” said Dr. Ma’ayan.

Next, the investigators plan to repeat the study using data from single-cell transcriptomics and whole blood, apply the machine learning approach to other complex diseases that are difficult to diagnose, and develop the diagnostic gene panel and test it on samples from patients.

The paper is titled “Gene set predictor for post-treatment Lyme Disease.” Additional co-authors are Daniel J.B. Clarke, MS (Icahn Mount Sinai, New York), and Alison W. Rebman, MPH, Jinshui Fan, MD, PhD, Mark J. Soloski, PhD, and John N. Aucott, MD, all from Johns Hopkins University of Medicine in Baltimore.

The project was partially supported by funds from the Cohen Lyme & Tickborne Disease Initiative and the National Institutes of Health.

SOURCE: MountSinai.org

Study Shows Expanding Tick Populations in Colorado

https://www.lymedisease.org/study-ticks-colorado/

Study shows expanding tick populations in Colorado

A new study published in the peer-reviewed journal Ticks and Tick-borne Diseases shows that ticks capable of carrying diseases pose an emerging threat in Colorado.

The results demonstrate that American dog ticks are present in 16 Colorado counties where they had not been previously identified by the CDC.

Furthermore, Rocky Mountain wood ticks are found in 38 of the 64 Colorado counties, whereas they had only been identified in 33 previously.

The study leveraged several sources for the study, including ticks collected by citizen scientists as part of a free tick testing program offered by the Bay Area Lyme Foundation.

“The critical takeaway from this study is that Coloradans need to take preventative measures against ticks when outdoors, such as tick checks, and doctors should be more vigilant for symptoms of tick-borne diseases including those carried by Rocky Mountain wood ticks and American dog ticks,” said Linda Giampa, executive director, Bay Area Lyme Foundation.

Citizen science

“This ecology study illustrates the power of leveraging citizen science, and we are grateful for the more than 20,000 ticks that were submitted to our national program and made this study possible.”

Conducted by researchers from Colorado State University and funded by the Bay Area Lyme Foundation, the study aimed to quantify the current county-level distribution of Rocky Mountain wood ticks, Dermacentor andersoni, and American dog ticks, Dermacentor variabilis.

The study evaluated data from ticks collected by citizen scientists and evaluated  at Northern Arizona University as part of Bay Area Lyme Foundation’s Free Tick Testing program, distribution data from the Colorado Department of Public Health and the Environment, veterinary surveillance at Oklahoma State University, and literature data.

“It was interesting to us to see American dog ticks in unexpected counties in Colorado which appear to be invading from nearby states or traveling with people and pets. And also to show that Rocky Mountain wood ticks appear, for the most part, to inhabit counties at higher elevations than American dog ticks,” said co-author Daniel Salkeld, PhD, Colorado State University.

A red flag

“This study is a red flag that, on the county-level, it is necessary to increase tick surveillance locally, and, on an individual level, to take precautions and know the symptoms of tick-borne diseases.”

Rocky Mountain wood ticks and American dog ticks are both known carriers of Rickettsia rickettsii, which causes Rocky Mountain spotted fever, a disease that is on the rise in the US. They also carry Francisella tularensis which causes tularemia, a potentially life-threatening disease that has seen a spike in incidence in recent data.

According to this study, both species of tick were found on humans and dogs. Rocky Mountain wood ticks appear to be more attracted to humans, with this tick representing 58% of ticks attached to humans, compared to the American dog tick, which represented 92% of ticks attached to dogs.

“The citizen science approach has been critical to supporting our efforts as widespread active surveillance programs in Colorado have had difficulty due to the state’s diverse terrain and no Colorado counties regularly conduct these,” said lead author Elizabeth Freeman, MPH, Colorado State University.

More surveillance needed

“With the knowledge that there is a risk of encountering both the Rocky Mountain wood tick and American dog tick in Colorado, there should be more motivation to further enhance surveillance studies to fully understand the public’s risk of disease.”

Citizen scientists collected and provided the ticks evaluated in the study as part of Bay Area Lyme Foundation’s Free Tick Testing program, which collected more than 20,400 ticks, of which 8,954 are Ixodes ticks capable of carrying the most common tick-borne pathogens.

This new study expands on previous research identifying ticks capable of carrying Lyme and other tick-borne diseases in 83 counties (in 24 states) where these ticks had not been previously recorded.

Some of the new county reports are likely due to travel-associated exposures (e.g., Montana), but many counties, such as those in Colorado, are in close proximity to previously known locations, illustrating either spreading range of ticks or the need for expanded on-the-ground surveillance.

The research was conducted through a partnership between Bay Area Lyme Foundation, Northern Arizona University, Colorado State University and the Translational Genomics Research Institute (TGen).

Interactive maps show the distribution by county of the tick species collected, including western blacklegged tick, blacklegged tick, American dog tick, lone star tick. Prevalence of Rocky Mountain wood ticks in this study were not previously evaluated and reported.

Ticks sent to the initiative from January 2016 through August 2019 were tested free of charge. These data were categorized, mapped, and recorded, as well as provided to the submitter. Ticks were submitted from every state except Alaska. The program received a six-fold increase in tick submissions over initial estimates, representing unprecedented national coordination of a ‘citizen science’ effort and diagnostic investigation.

Click here to read the study.

SOURCE: Bay Area Lyme Foundation

________________

For more:

I am ever grateful they did not blame the climate.  Independent research has shown the climate is a nothing burger when it comes to tick and disease proliferation despite the continued narrative by corrupt science, politics, and climate alarmists.

Experts continue to speak out to deaf ears.

Anesthetic Concerns for Lyme Disease Patients

https://danielcameronmd.com/anesthetic-concerns-lyme-disease/

ANESTHETIC CONCERNS FOR LYME DISEASE PATIENTS

Doctors gives anesthetic medication to patient with Lyme disease.

Some Lyme disease patients require anesthetic evaluation before a procedure. Tammy Smit, MSNA, CRNA discussed a helpful approach for patients who required anesthesia for a surgical procedure in the American Association of Nurse Anesthesiology (AANA) journal. [1]

In her article “Lyme Disease and Anesthesia Considerations,” Smit discusses three approaches:Disease awareness

Some patients may have Lyme disease that has not been diagnosed.

“Infected patients in whom the diagnosis has not yet been made or has been missed may present for invasive investigations such as biopsies or arthroscopies or for larger surgical interventions such as joint replacement or pacemaker insertion,” wrote Smit. A good history and physical examination should help.

Assessment of Target-Organ Damage

Some patients might need consultations. Lyme patients may present with Lyme carditis. Others can present with neurologic Lyme disease.

“This leads to a wide range of clinical presentations, the most common of which are headaches, cranial nerve palsies (in particular, bilateral upper and lower seventh cranial nerves), and meningitis,” wrote the author. “Borrelia encephalopathy, which rarely occurs, has also been described and is associated with disturbances in mood, personality, sleep, memory, and concentration.”

“Anesthetic practitioners should be aware of the clinical presentations of the disease as well as have a clear understanding of the anesthetic implications of the disease.”

Anesthesia-Specific Concerns

The author raised potential anesthesia-specific concerns. Central neuraxial blockade may introduce infective agents into the central nervous system.

“General anesthesia may suppress the immune system,” wrote the author. “A strong body of evidence has emerged demonstrating that volatile anesthetic agents adversely affect the function of neutrophils, macrophages, and natural killer cells…. the effect has not been described with propofol.”

“It may therefore be prudent to avoid the use of volatile anesthesia in patients with active disease and to rather make use of propofol-based total intravenous anesthesia.”

The author advised that oral antibiotics for Lyme disease be continued if a patient undergoes prolonged therapy. If they are unable to take oral therapy (i.e. being ventilated or NPO), they should receive intravenous antibiotics to cover the dosage.

Lastly, patients with cardiac or neurologic complication of Lyme may need closer perioperative monitoring.

The author concluded, “The impact that the choice of anesthetic technique may have on disease progression should be considered and discussed with the patient.”

References:
  1. Smit T. Lyme Disease and Anesthesia Considerations. AANA J. Dec 2017;85(6):427-430.

USA Today Still Distributing Dangerously Misleading Article About Lockdown Efficacy & Safety and New Ivermectin Study Eerily Similar to the Old Flawed One

https://popularrationalism.substack.com/p/usa-today-still-distributing-dangerously

USA Today Still Distributing Dangerously Misleading Article About Lockdown Efficacy and Safety

The business of “Fact-Checking” has thankfully been fairly well debunked. Let USA Today know that they have left up a dangerously misleading article.

Citing an array of so-called “Fact-Check” resources and some medical dude’s opinion as their sources on the monopoly on truth, USA Today published this embarrassing article in Feb 2022, full of bravado and certainty, claiming that a position paper published by economists was incorrect.

The paper in question was an evidence-based meta-analysis that examined published, peer-reviewed estimates of the impact of lockdowns on mortality from COVID-19, which came in at merely 0.2%.

The paper, “A Literature Review and Meta-Analysis of the Effects of Lockdowns on COVID-19 Mortality” was never represented by the authors or the publishing website as a peer-reviewed meta-analysis, but USA Today found some people on the internet who incorrectly described it as such, and used their error as a ding against the paper and its authors, which of course, is non-sequitur.

The paper also reported the massive economic costs of lockdowns, which is unquestionably correct and is now widely established.

But for USA Today, in their opinion, and in the opinion of their “experts”, the findings of the study were “missing context”, citing unidentified “public health and medical experts”.

“Public health and medical experts say the paper is flawed, in part due to its overly broad definition of ‘lockdown.’ Experts have also criticized the working paper’s emphasis on the immediate effect of lockdowns on COVID-19 deaths instead of disease transmission. Other peer-reviewed studies have found lockdowns prevent deaths.”

(See link for article)

_______________

**Comment**

USA Today has been previously criticized for falsely labeling truth as “misinformation.”  Spin doctors are gonna spin.

Weiler also tackles faulty PCR testing, and the failure to stop COVID in countries which adopted a “zero-COVID” policy and who are now suffering some of the highest rates of COVID, hospitalizations, and yes, even death.

Weiler states we should “remind USA Today that listing their ‘sources’ as a bunch of blog articles expressing someone’s opinion is woefully bad form for a professional media company as they were clearly ALL wrong.”

_______________

https://doyourownresearch.substack.com/p/activ-6-and-together-bear-strangely

ACTIV-6 And TOGETHER Trials Bear Strangely Similar Design Fingerprints

By Alexandros Marinos

Nov. 14, 2022

A while ago, I wrote an article enumerating ten questionable features of the TOGETHER trial on ivermectin, conducted in Brazil. What are the chances those same features would make an appearance in the ACTIV-6 trial on ivermectin, conducted by the NIH in the USA? Pretty good, apparently, because that is exactly what seems to be happening.

#1 – Randomization Anomalies

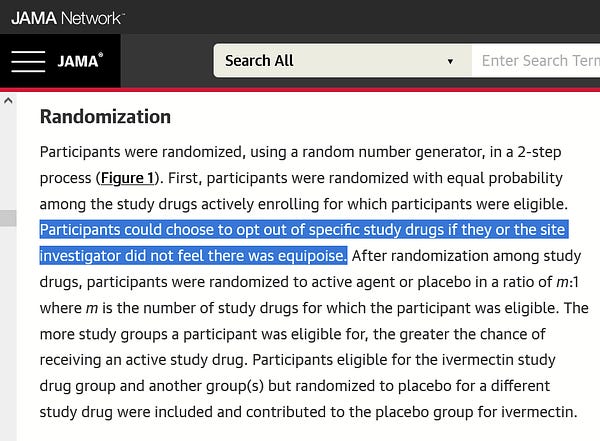
While the shape of the issue is different, the result is the same: the randomization of the trial is under question due to the fact that the treatment and control groups of the trial were drawn from different populations. As the ACTIV-6 trial participant I spoke to revealed, he was asked to pick which drug study he would be enrolled in. In contrast, the placebo group contained patients assigned to other drugs, most or all of whom chose to be randomized into that different drug. This is a systematic difference between the populations not accounted for in the trial.

Alexandros Marinos @alexandrosM
ACTIV-6 ivermectin paper out… looking at the randomization section… WHAT?! Participants could opt out of a drug if they didn’t FEEL it works. Or the site investigator could opt them out. “Here’s our ite menu, what drug would you like to randomize for?” This is not an RCT.
Image

#2 – Dosing

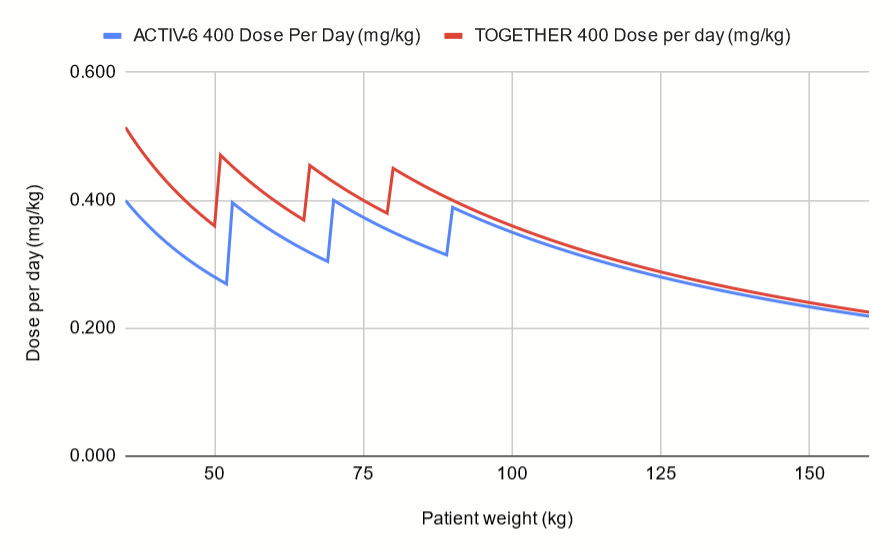
The ACTIV-6 trial takes the flawed dosing of the TOGETHER trial and makes it worse. This is one of those cases where a picture is worth 1000 words:

Not only does ACTIV-6 underdose those at highest risk the most, it also underdoses people with lower weights, effectively falsifying the dose given to patients.

(See link for article)

_______________

SUMMARY:

  • On top of randomization and dosing issues, ACTIV-6 and the TOGETHER trials did not exclude patients who had used ivermectin but allowed them to randomize into other drugs, which means patients allocated to fluvoxamine and fluoxetine may have also been taking ivermectin.
  • Placebo patients from all arms were commingled and utilized variable placebos, demonstrating the potential unblinding of the investigators and clinical staff.  The TOGETHER trial suffered this issue as well.
  • Despite the TOGETHER trial being heavily criticized for using ER visits as the endpoint, ACTIV-6 also used a composite secondary novel endpoint that intermingled ER visits, hospitalizations, and deaths.  COVID hospitalizations were not reported separately.
  • The trial has missing data such as information on patient populations.
  • Determination of dosages used is shrouded in mystery.
  • An author of the trial was also an author in the TOGETHER trial.
  • No information about the number of patients who actually adhered to the protocol and took their drugs as described was given.
  • Both trials failed to have an independent monitoring board, and the public-private partnership has numerous conflicted pharmaceutical companies in its management committee and membership.
  • To date, the data has not been made available to any researcher for any reason.
  • While the TOGETHER trial started out recruiting high-risk patients, this changed mid-trial towards low-risk patients. They then limited the number the could participate in the trial by adding new inclusion criterion, suggesting that Cytel, the company that “designed and led the TOGETHER trial”—using Clinical Trial optimization simulation software, was running interim data through simulations to figure out which kind of inclusion/exclusion criteria would give them the results they wanted.
  • Interestingly, this change made in TOGETHER was in May 2021, the exact date that ACTIV-6 trial protocol was first posed on clinical trials.gov.
  • The eery design defects and flawed decisions between both trials raise questions about whether the design of ACTIV-6 trial was informed by interim results of the TOGETHER trial, particularly since Dr. David Boulware is a shared author of both trials.
  • Transparency of data would alleviate suspicions but does not appear to be forthcoming.

These are the shenanigans in research now.  Question everything.  And Thank God for those willing to go through mounds of data with a fine-toothed comb, like this heroic mom with a scientific background who exposes junk COVID shot data.

FYI: Ivermectin and HCQ work:

For more:

Why research can not be trusted at face-value: