Author Archive

Who Owns Big Pharma & Big Media? You’ll Never Guess

https://childrenshealthdefense.org/defender/blackrock-vanguard-own-big-pharma-media/

Who Owns Big Pharma + Big Media? You’ll Never Guess.

BlackRock and the Vanguard Group, the two largest asset management firms in the world, combined own The New York Times and other legacy media, along with Big Pharma.

Story at-a-glance:

  • Big Pharma and mainstream media are largely owned by two asset management firms: BlackRock and Vanguard.
  • Drug companies are driving COVID-19 responses — all of which, so far, have endangered rather than optimized public health — and mainstream media have been willing accomplices in spreading their propaganda, a false official narrative that leads the public astray and fosters fear based on lies.
  • Vanguard and BlackRock are the top two owners of Time Warner, Comcast, Disney and News Corp, four of the six media companies that control more than 90% of the U.S. media landscape.
  • BlackRock and Vanguard form a secret monopoly that own just about everything else you can think of too. In all, they have ownership in 1,600 American firms, which in 2015 had combined revenues of $9.1 trillion. When you add in the third-largest global owner, State Street, their combined ownership encompasses nearly 90% of all S&P 500 firms.
  • Vanguard is the largest shareholder of BlackRock. Vanguard itself, on the other hand, has a unique structure that makes its ownership more difficult to discern, but many of the oldest, richest families in the world can be linked to Vanguard funds.

What does The New York Times and a majority of other legacy media have in common with Big Pharma? Answer: They’re largely owned by BlackRock and the Vanguard Group, the two largest asset management firms in the world. Moreover, it turns out these two companies form a secret monopoly that owns just about everything else you can think of too. As reported in the featured video:

“The stock of the world’s largest corporations are owned by the same institutional investors. They all own each other. This means that ‘competing’ brands, like Coke and Pepsi aren’t really competitors, at all, since their stock is owned by exactly the same investment companies, investment funds, insurance companies, banks and in some cases, governments.

“The smaller investors are owned by larger investors. Those are owned by even bigger investors. The visible top of this pyramid shows only two companies whose names we have often seen …They are Vanguard and BlackRock.

“The power of these two companies is beyond your imagination. Not only do they own a large part of the stocks of nearly all big companies but also the stocks of the investors in those companies. This gives them a complete monopoly.

“A Bloomberg report states that both these companies in the year 2028, together will have investments in the amount of 20 trillion dollars. That means that they will own almost everything.’”

Who are the Vanguard?

The word “vanguard” means “the foremost position in an army or fleet advancing into battle,” and/or “the leading position in a trend or movement.” Both are fitting descriptions of this global behemoth, owned by globalists pushing for a Great Reset, the core of which is the transfer of wealth and ownership from the hands of the many into the hands of the very few.

Interestingly, Vanguard is the largest shareholder of BlackRock, as of March 2021. Vanguard itself, on the other hand, has a “unique” corporate structure that makes its ownership more difficult to discern. It’s owned by its various funds, which in turn are owned by the shareholders. Aside from these shareholders, it has no outside investors and is not publicly traded. As reported in the featured video:

“The elite who own Vanguard apparently do not like being in the spotlight but of course they cannot hide from who is willing to dig. Reports from Oxfam and Bloomberg say that 1% of the world, together owns more money than the other 99%. Even worse, Oxfam says that 82% of all earned money in 2017 went to this 1%.

“In other words, these two investment companies, Vanguard and BlackRock hold a monopoly in all industries in the world and they, in turn, are owned by the richest families in the world, some of whom are royalty and who have been very rich since before the Industrial Revolution.”

While it would take time to sift through all of Vanguard’s funds to identify individual shareholders, and therefore owners of Vanguard, a quick look-see suggests Rothschild Investment Corp. and the Edmond De Rothschild Holding are two such stakeholders. Keep the name Rothschild in your mind as you read on, as it will feature again later.

The video above also identifies the Italian Orsini family, the American Bush family, the British Royal family, the du Pont family, the Morgans, Vanderbilts and Rockefellers, as Vanguard owners.

BlackRock/Vanguard own Big Pharma

According to Simply Wall Street, in February 2020, BlackRock and Vanguard were the two largest shareholders of GlaxoSmithKline, at 7% and 3.5% of shares respectively. At Pfizer, the ownership is reversed, with Vanguard being the top investor and BlackRock the second-largest stockholder.

Top owners of Pfizer Inc.

Keep in mind that stock ownership ratios can change at any time, since companies buy and sell on a regular basis, so don’t get hung up on percentages. The bottom line is that BlackRock and Vanguard, individually and combined, own enough shares at any given time that we can say they easily control both Big Pharma and the centralized legacy media — and then some

Why does this matter? It matters because drug companies are driving COVID-19 responses — all of which, so far, have endangered rather than optimized public health — and mainstream media have been willing accomplices in spreading their propaganda, a false official narrative that has, and still is, leading the public astray and fosters fear based on lies.

To have any chance of righting this situation, we must understand who the central players are, where the harmful dictates are coming from, and why these false narratives are being created in the first place.

As noted in Global Justice Now’s December 2020 report “The Horrible History of Big Pharma,” we simply cannot allow drug companies — “which have a long track record of prioritizing corporate profit over people’s health” — to continue to dictate COVID-19 responses.

In it, they review the shameful history of the top seven drug companies in the world that are now developing and manufacturing drugs and gene-based “vaccines” against COVID-19, while mainstream media have helped suppress information about readily available older drugs that have been shown to have a high degree of efficacy against the infection.

BlackRock/Vanguard own the media

When it comes to The New York Times, as of May 2021, BlackRock is the second-largest stockholder at 7.43% of total shares, just after The Vanguard Group, which owns the largest portion (8.11%).

In addition to The New York Times, Vanguard and BlackRock are also the top two owners of Time Warner, Comcast, Disney and News Corp, four of the six media companies that control more than 90% of the U.S. media landscape.

Needless to say, if you have control of this many news outlets, you can control entire nations by way of carefully orchestrated and organized centralized propaganda disguised as journalism.

BlackRock-and-Vanguard own the media.

If your head is spinning already, you’re not alone. It’s difficult to describe circular and tightly interwoven relationships in a linear fashion. The world of corporate ownership is labyrinthine, where everyone seems to own everyone, to some degree.

However, the key take-home message is that two companies stand out head and neck above all others, and those are BlackRock and Vanguard. Together, they form a hidden monopoly on global asset holdings, and through their influence over our centralized media, they have the power to manipulate and control a great deal of the world’s economy and events, and how the world views it all.

Considering BlackRock in 2018 announced that it has “social expectations” from the companies it invests in, its potential role as a central hub in the Great Reset and the “build back better” plan cannot be overlooked.

Add to this information showing it “undermines competition through owning shares in competing companies” and “blurs boundaries between private capital and government affairs by working closely with regulators,” and one would be hard-pressed to not see how BlackRock/Vanguard and their globalist owners might be able to facilitate the Great Reset and the so-called “green” revolution, both of which are part of the same wealth-theft scheme.

BlackRock and Vanguard own the world

That assertion will become even clearer once you realize that this duo’s influence is not limited to Big Pharma and the media. Importantly, BlackRock also works closely with central banks around the world, including the U.S. Federal Reserve, which is a private entity, not a federal one. It lends money to the central bank, acts as an adviser to it, and develops the central bank’s software.

BlackRock/Vanguard also own shares of a long list of other companies, including Microsoft, Apple, Amazon, Facebook and Alphabet Inc. As illustrated in the graphic of BlackRock and Vanguard’s ownership network below, featured in the 2017 article “These Three Firms Own Corporate America” in The Conversation, it would be near-impossible to list them all.

In all, BlackRock and Vanguard have ownership in some 1,600 American firms, which in 2015 had combined revenues of $9.1 trillion. When you add in the third-largest global owner, State Street, their combined ownership encompasses nearly 90% of all S&P 500 firms.
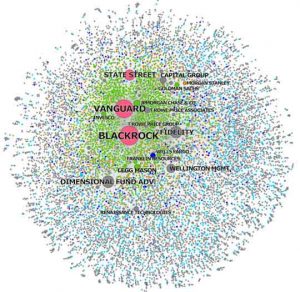
Blackrock and Vanguard ownership

A global monopoly few know anything about


To tease out the overarching influence of BlackRock and Vanguard in the global marketplace, be sure to watch the 45-minute-long video featured at the top of this article. It provides a wide-view summary of the hidden monopoly network of Vanguard- and BlackRock-owned corporations, and their role in the Great Reset. A second much shorter video (above) offers an additional review of this information.

How can we tie BlackRock/Vanguard — and the globalist families that own them — to the Great Reset? Barring a public confession, we have to look at the relationships between these behemoth globalist-owned corporations and consider the influence they can wield through those relationships. As noted by Lew Rockwell:

“When Lynn Forester de Rothschild wants the United States to be a one-party country (like China) and doesn’t want voter ID laws passed in the U.S., so that more election fraud can be perpetrated to achieve that end, what does she do?

“She holds a conference call with the world’s top 100 CEOs and tells them to publicly decry as ‘Jim Crow’ Georgia’s passing of an anti-corruption law and she orders her dutiful CEOs to boycott the State of Georgia, like we saw with Coca-Cola and Major League Baseball and even Hollywood star, Will Smith.

“In this conference call, we see shades of the Great Reset, Agenda 2030, the New World Order. The UN wants to make sure, as does [World Economic Forum founder and executive chairman Klaus] Schwab that in 2030, poverty, hunger, pollution and disease no longer plague the Earth.

“To achieve this, the UN wants taxes from Western countries to be split by the mega corporations of the elite to create a brand-new society. For this project, the UN says we need a world government — namely the UN, itself.”

As I’ve reviewed in many previous articles, it seems quite clear that the COVID-19 pandemic was orchestrated to bring about this New World Order — the Great Reset — and the 45-minute video featured at the top of the article does a good job of explaining how this was done. And at the heart of it all, the “heart” toward which all global wealth streams flow, we find BlackRock and Vanguard.

Originally published by Mercola.

The views and opinions expressed in this article are those of the authors and do not necessarily reflect the views of Children’s Health Defense.

© [6/18/21] Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.

__________________

For more:

WHO Declares Monkeypox Outbreak a Global Health Emergency After Only 5 Deaths & A Vaccine-Derived Polio Case in NY

https://www.theblaze.com/news/monkeypox-global-health-emergency-who

WHO declares monkeypox outbreak a global health emergency after 5 deaths worldwide

The World Health Organization (WHO) has declared the monkeypox outbreak a global health emergency.

“I have decided that the global monkeypox outbreak represents a public health emergency of international concern,” WHO Director-General Tedros Adhanom Ghebreyesus announced on Saturday morning during a briefing in Geneva.

Members of an expert committee met on Thursday to decide if the current monkeypox outbreak should be escalated to a public health emergency of international concern (PHEIC). Of the virologists, vaccinologists, epidemiologists, and health experts, nine voted against declaring monkeypox a PHEIC, and six voted in favor, according to Reuters.

The International Health Regulations Emergency Committee were “resolved by consensus to advise the WHO Director-General that at this stage the outbreak should be determined to not constitute a PHEIC.”

“However, the Committee unanimously acknowledged the emergency nature of the event and that controlling the further spread of outbreak requires intense response efforts,” according to the WHO. “The Committee advised that the event should be closely monitored and reviewed after a few weeks, once more information about the current unknowns becomes available, to determine if significant changes have occurred that may warrant a reconsideration of their advice.”

(See link for article)

__________________

SUMMARY:

  • Tedros overrode the committee & gave monkeypox the highest level of alert.  So much for having experts and a committee.
  • The big takeaway is the designation gives the WHO authority to raise public awareness to raise funding and resources from member nations.  In short, this is a great moneymaker and we don’t want to miss out on that.
  • This is the 7th alert declared since 2007.  The other six were:
    • H1N1 influenza pandemic of 2009 (the fast-tracked H1N1 vaccine increased miscarriages, narcolepsy, and febrile convulsions in 1 in every 110 in Australia). The WHO by May, 2006 stated H1N1 only killed 100 people. H1N1 is another scam.
    • Ebola outbreak in West Africa from 2013 to 2015 (Please read Dr. Rowan’s successful experience with ozone in Sierra Leone.
    • Ebola outbreak in the Democratic Republic of the Congo from 2018 to 2020
    • Zika outbreak in 2016. (Please read this showing they took TWO tissue samples from TWO fetuses containing Zika to “prove” causation.  Rather than taking years to complete lab work, they took ONE paper & plopped it into Shepherd’s criteria where it only met 3 of the 7 criteria, to establish a causal link).  Zika was another scam.
    • poliovirus that started in 2014
    • COVID-19 pandemic.  A complete and utter scam.
  • Tedros admits the outbreak is concentrated in gay men, particularly those who have multiple partners.
  • There is a total of FIVE monkeypox deaths worldwide
  • Predictably, BARDA has purchased a total of 6.9 million monkeypox vaccines through mid-2023.
  • Experts are warning that using a small pox vaccine to prevent monkeypox could cause a global smallpox (vaccinia) epidemic.

_____________________

https://www.scientificamerican.com/article/new-york-polio-case-revives-questions-about-live-oral-vaccine/

New York Polio Case Revives Questions About Live Oral Vaccine

An unvaccinated person became infected with the virus, which can be traced to a live, weakened virus commonly used in the oral polio vaccine abroad
New York Polio Case Revives Questions About Live Oral Vaccine
TEM of Polio viruses: the causative agent of poliomyelitis (infantile paralysis). Although rounded in shape, each virus has a cubic symmetry. They are RNA picornaviruses. RNA genetic material occurs in the core of each virus, surrounded by a protein coat (blue). Credit: Eye of Science/Science Source

Excerpt:

The New York patient reportedly contracted a form of polio that can be traced back to the live, but weakened, poliovirus used in the oral polio vaccine. This version of the vaccine has not been used in the U.S. since 2000. Health officials said the virus affecting the male patient, who has muscle weakness and paralysis, likely originated somewhere overseas, where oral vaccines are still administered.

(See link for article)

___________________

**COMMENT**

The article misleadingly states that vaccines introduce a harmless version of a pathogen to your body to train your immune system to fight off the real germ if you ever encounter it.

This is the narrative we’ve been told ad nauseum, yet people are damaged and killed by vaccines daily.

For a great read on the biological mechanisms of vaccine injury please read part 1 and part 2.  This reality is similar to the reality of chronic Lyme/MSIDS. It just isn’t discussed, believed, or acted upon by mainstream medicine.  And similarly, according to mainstream medicine, both topics (Lyme/MSIDS & vaccines) state everything is rare, even when it isn’t.

Regarding polio, many believe routine vaccination may have replaced one disease with another and that acute flaccid myelitis (AFM) outbreaks – a polio-like disease- have been recorded on a biennial basis.

For decades, it’s been known that under certain conditions a phenomenon referred to as “provocation polio” can occur after injections, including injections of vaccines. Yet this issue is being largely, if not entirely, ignored in today’s discussions about AFM.

And while we all envision frightening posters of kids in iron lungs, the very contagious enterovirus infection usually causes mild flu-like symptoms or no symptoms at all, and most people recover from polio without lasting health problems (nonparalytic polio).

While the global poliovirus eradication effort appears to have been successful, the consequences of routine use of OPV are not fully known. In 2009, the World Health Organization warned that live polio vaccine may be responsible for a rise in vaccine strain polio termed Vaccine Derived Polio Disease (VDPD).

Not only has live vaccine strain poliovirus been found to cause paralytic disease in some cases, but evidence also shows that mutated vaccine-derived viruses are responsible for some outbreaks.15,16 As reported by NPR in 2017:

“For the first time, the number of children paralyzed by mutant strains of the polio vaccine are greater than the number of children paralyzed by polio itself. So far in 2017, there have been only six cases of ‘wild’ polio reported anywhere in the world …  Source

We are always given part of the truth – not the whole enchilada. Vaccines have always come with risks and always will.  
The polio case might be a foreshadowing of smallpox in the future.

COVID Risks May Be Heightened by History of Lyme Disease

https://www.news-medical.net/news/20220717/COVID-19-risks-may-be-heightened-by-history-of-Lyme-disease

COVID-19 risks may be heightened by history of Lyme disease

In a recent study published on the preprint server Research Square*, researchers report that individuals with a history of Borrelia infection, otherwise known as Lyme disease, caused by tick bites are at a higher risk of severe coronavirus disease 2019 (COVID-19).

Study: Correlation between COVID-19 severity and previous exposure of patients to Borrelia spp. Image Credit: Kateryna Kon / Shutterstock.com

(See link for article)

__________________

SUMMARY:

  • Serological testing is not sufficient to differentiate between recent and past infections because antibodies persist in the blood – even after treatment.  What the article doesn’t say is that THIS, RIGHT HERE, is why current CDC 2-tiered testing should never be used solely to diagnose patients and why doctors need to be educated to make correct clinical judgments. 
  • What started the whole ball of wax is a case report of a patient infected with Lyme who was unsuccessfully treated with one round of antibiotics and who then got COVID.  The patient’s Lyme was suppressed (lower IgG test) due to the anti-COVID meds (umifenovir, hydroxychloroquine, azithromycin, and ceftriaxone).
  • The study included:
    • 31 severely ill & hospitalized patients who were either required non-invasive or invasive ventilation.
    • 28 COVID positive patients who had either mild or asymptomatic cases who were either treated at home or unaware of infection.
    • 28 seronegative controls
  • Serum samples were collected for COVID and Borrelia infections
    • A multi-antigen microblot-array utilizing 19 antigens revealed Lyme in all hospitalized COVID patients. 
    • Of the 28 mild or asymptomatic patients, 19 had Lyme, whereas in the control group of 28, 8 had Lyme.
    • Severe COVID patients also had significantly higher levels of antibodies targeting Anaplasma.
  • Regarding seropositivity for IgM antibodies (1st antibodies to show up after infection that stay for a short period of time):
    • 24 of the 31 hospitalized patients had Lyme antibodies
    • 13 of the 28 mild/asymptomatic patients had Lyme antibodies
    • 15 of the 28 in the control group had Lyme antibodies
  • Risk of COVID-related hospitalizations increased with each positive IgG (antibodies produced later on in infection and can remain after infection resolves. Having high IgG can be indicative of chronic Lyme), but was not observed for IgM.
  • Post-hoc analysis of selected antigens (Osp proteins, p41, and VlsE) was also
    included; multivariate analysis showed that odds of hospitalization increased with increasing levels of:
    • IgG antibodies targeting OspB, OspC B. burgdorferi sensu stricto, and OspC
      B. spielmanii
    • For IgM antibodies, the same association was observed for antibodies targeting OspC B. spielmanii and OspE
  • Interestingly, the authors state that they observed in many patients antibodies targeting different species (e.g. B. burgdorferi sensu stricto, and at the same time
    B. afzelii, and/or B. garinii) which may reflect cross-reactivity but also may result from coinfections with more than one species.
  • Previous exposure to Lyme and other tick-borne diseases can increase risk of severe COVID and this is the first observation that suggests links between Lyme disease and COVID-19 prognostics.
  • The authors state that screening of anti-Borrelia antibodies in COVID patients could identify high-risk patients and improve their management.
Journal reference:
  • Szewczyk-Dabrowska, A., Budziar, W., Harhala, M., et al. (2022). Correlation between COVID-19 severity and previous exposure of patients to Borrelia spp. Research Square. doi:10.21203/rs.3.rs-1799732/v1.

_________________

**Comment**

This is a very interesting study but I come up with slightly different take-aways.  The first of which is – don’t let this article frighten you.  1) there are cheap, effective, safe treatments for COVID.  Far safer & cheaper than Lyme/MSIDS treatment! 2) it only makes logical sense that those with Lyme/MSIDS are sitting ducks for pretty much everything including highly contagious viruses (if that’s what this even is). Lyme/MSIDS patients already struggle with EBV, Herpes, cytomegalovirus, and much, much more.  You are not a hopeless, helpless victim. There are answers and actions you can take to protect yourself and treat yourself should you contract COVID.:

  • The case study states that the person’s Lyme was suppressed due to anti-COVID meds, yet list antibiotics (ceftriaxone & azithromycin) that are used often for Lyme – which would explain the suppression.  Suppression doesn’t mean the Lyme goes away, it just means it isn’t being picked up on the test – a common, well-known problem patients deal with on a daily basis.
  • HCQ was used, which is also used for Babesia, a coinfection they didn’t look for but is known to cause much more severe Lyme for a greater duration IF the patient has both infection concurrently.
  • And Umifenovir is a broad‐spectrum antiviral, which while it doesn’t treat Lyme directly, could assist by beating back other viruses like herpes, EBV, and others – all of which are big players in Lyme.  Treating Lyme/MSIDS is a balancing act.  Giving appropriate treatment to beat back infections and supporting your immune system to handle what’s there without freaking out is more in line than a “cure” of erradicating everything within you.  We are covered in germs/viruses and most are held in check by our immune system.  A tick/insect bite changes that balance (or other modes of transmission such as congenital or sexual, etc)
  • They looked for 19 antigens which is unheard of for average folk!
  • They found Lyme (antibodies) in nearly everyone – even the controls!  This, to me, is the real finding. 
  • Their suggestion to “screen for anti-Borrelia antibodies in COVID patients” to identify potential “high risk” patients only has one flaw:  testing sucks and is not to be trusted!

Tick-Related Disease Can Trigger Chemical Sensitivities

https://www.lymedisease.org/wallace-tbdwg-mcs/

To TBDWG: Tick-related disease can trigger chemical sensitivities

Kathleen Wallace gave the following public comments to the Tick-Borne Disease Working Group on July 19.

I have been an active listener and participant in public comment since inception of the Tick Borne Disease Working Group. I thank each of you for your hard work and dedication. It is much appreciated.

Objectives as defined in the 21st Century Cures Act include gaps in the tick-borne disease research. I speak again about one of those gaps–MCS or Multiple Chemical Sensitivities.

MCS is a medical condition characterized by adverse health effects from exposure to common chemicals and pollutants from products such as pesticides, new carpet, paint, renovation materials, diesel exhaust, cleaning supplies, perfume, scented laundry products and air fresheners. (1)

The symptoms of MCS are diverse and unique to each person. Symptoms range from mild to life threatening and include headache, trouble concentrating, nausea, diarrhea, fatigue, muscle and joint pain, dizziness, difficulty breathing, irregular heartbeat and seizures. (2)

With MCS we lose the ability to use public transportation, public housing, or hotels. We are unable to participate in many community activities. The social impact is gruesome. Our quality of life is significantly degraded, Access to healthcare can be difficult as we have to tolerate hospital and office air.

Our needs regarding MCS are vast. We need a medical code. We need research. We need education for physicians. We need better air quality control.

My passion to make a difference has grown through my journey. I was a successful business owner and manager for a national company. I lost my home, my business, and my family life because of MCS. Resilience has become my middle name.

Many “don’t believe in” MCS

One of the most challenging issues to navigate through has arisen from physicians, family and friends not believing in my MCS. Many chose to ignore pleas to use MCS friendly products on themselves and their clothing. Imagine spending all your holidays in complete solitude: it is not fun.

You speak of equality in tick-borne disease and conditions, however, the syndrome of MCS remains to be investigated.

This 2022 clinical presentation and pathogenesis subcommittee report’s priority #3 focuses on alpha-gal syndrome. I couldn’t agree more. However, there’s no mention of other difficult syndromes associated with tick-borne disease.

Also shared by this TBDWG–results of clinician-encountered barriers including scientific knowledge gaps that identify alpha-gal syndrome–but again, no mention of other syndromes.

Please note that MCS is the pure definition of invisible illness.

Part of your core values is collaboration. To actively listen to the patient experiences shared with you, respect the lived experiences of patients and their advocates and to learn from these experiences in your pursuit of objective truth.

I live the experience, while science can provide research.

I suffer daily. Please include MCS in your areas for discussion. Thank you for your time.

Kathleen Wallace lives in New York state.

References

1. Dr. Anne Steinemann, Journal of Occupational and Environmental Medicine, March 2018 volume 60 Issue 3 pg.152-156

2.Anne McCampbell, M.D. Co-chair of the MCS task force of New Mexico. New Mexico MCS brochure by the MCS task force of New Mexico 11/00

FDA Relied on Scientific Fraud to Authorize Pfizer’s COVID Shot For Infants/Toddlers & Israel Caught Concealing “Vax” Injuries

https://popularrationalism.substack.com/p/hammond-fda-relied-on-scientific

Hammond: FDA Relied on Scientific Fraud to Authorize Pfizer’s COVID-19 Vaccine for Infants and Toddlers

A Guest Post by Journalist Jeremy R. Hammond

I invited objective and ethical independent journalist Jeremy R. Hammond to share his latest in his series of newsletters summarizing how the FDA relied on scientific fraud to authorize Pfizer’s COVID-19 vaccine for infants and toddlers. In this piece, he reports how the FDA attempted to justify its decision by exaggerating the risk to children from “Long COVID“.

If you missed the prior newsletters in this series, you can read Part I here (introduction to the FDA’s willful dishonesty), read Part II here (willful ignorance of natural immunity the very low risk to children), and read Part III here (lying about the risk of hospitalization).

Since it is widespread common knowledge that the risk to children of dying from COVID-19 is statistically zero, and the risk of hospitalization is also extraordinarily low, the FDA in its emergency use authorization decision memorandum highlighted the risk to children of Long COVID.

The FDA acknowledged that the data are “sparse” but cited a report from the UK Office for National Statistics finding that 7.2% of children who tested positive for SARS-CoV-2 reported continued symptoms at 12 weeks post-infection.

Thus, the FDA implies that seven out of every one-hundred children infected with the virus may develop Long COVID.

However, because that report was based on a survey of self-reported symptoms and was otherwise not methodologically sound enough to estimate the true rate of long-term symptoms in children attributable to SARS-CoV-2 infection, the UK report explicitly states, “It is not possible to infer from this analysis whether self-reported symptoms are caused by coronavirus infection.”

That naturally didn’t stop the FDA from fraudulently drawing precisely that inference in order to push its emergency use authorization through.

Estimates from such surveys or observational data of the proportion of people who develop persistent symptoms after SARS‑CoV‑2 infection are confounded by other causal or contributing factors, including the negative health effects of governments’ “lockdown” measures and the traumatism of simply having tested positive resulting from the persistent and intensive fearmongering about the risks from the virus emanating incessantly from the government and mainstream media over the course of the pandemic.

An article in JAMA in October 2020 astutely observed that the negative health effects of the government lockdowns and general trauma to the population needed to be differentiated from true cases of persistent symptoms caused by SARS-CoV-2 infection.

A study in Acta Paediatrica in April 2021 found that 43% of children previously diagnosed with COVID-19 reported one or more symptoms more than 60 days post-infection, but the authors emphasized that they lacked a control group and that their finding was confounded by the negative health effects of the lockdowns, and they therefore called for further studies to be done including a control group to estimate the true prevalence of Long COVID.

A study by German researchers on the preprint server medRxiv in May 2021 did include a control group and found no statistical difference when comparing the reported persistent symptoms of adolescents who tested positive for antibodies to SARS-CoV-2 with those who tested negative.

A study by Swiss researchers reported in JAMA in July 2021 found that 4% of children who tested positive for antibodies to SARS-CoV-2 reported at least one symptom lasting more than 12 weeks, which compared to 2% of children who reported persistent symptoms but had no evidence of prior infection.

A study by UK researchers on the preprint server Research Square in August 2021 found that 67% of children and adolescents reported persistent symptoms three months after having tested positive for SARS-CoV-2, but this compared with 53% of children who tested negative. As the authors appropriately noted,

“it is unclear whether the features associated with Long COVID are related to the viral infection or the effects of the pandemic, lockdown and school closures with consequent social isolation.”

A particularly illuminating study by French researchers in JAMA Internal Medicine in November 2021 found reported persistence of symptoms to be associated with the mere belief among subjects that they had previously been infected with SARS-CoV-2. With the sole exception of loss of taste or smell, they found no significant difference in the rate of self-reported symptoms between individuals who had evidence of prior infection and those who believed they had been infected but tested negative for antibodies.

The authors appropriately concluded that “persistent physical symptoms after COVID-19 infection may be associated more with the belief in having been infected with SARS-CoV-2 than with having laboratory-confirmed COVID-19 infection.” They further cautioned that practitioners should do a careful medical evaluation so as not to erroneously attribute symptoms to “Long COVID“.

A systematic review and meta-analysis published in the Journal of Infection in November 2021 found an inverse association between the quality of studies and estimated prevalence of Long COVID in children: specifically, the higher the quality of the study, the lower the estimated prevalence.

Narrowing their analysis to only those studies that included a control group, they found that the frequency of most persistent symptoms reported by people who tested positive for SARS-CoV-2 was similar to that reported by people who tested negative. The authors appropriately concluded by emphasizing the importance of including a control group so as not to artifactually inflate the prevalence of Long COVID in the childhood population.

In sum, the FDA’s reliance on a single source from which it is logically “not possible to infer” whether the self-reported symptoms were caused by SARS‑CoV‑2 infection to willfully mislead people into the belief that more than 7 percent of children infected may develop Long COVID is just another illustration of how the agency serves the pharmaceutical industry by engaging in deliberate fearmongering and scientific fraud.

Furthermore, even if we were to assume for the sake of argument that over 7 percent of children do develop Long COVID, the FDA failed to produce any data to support its assumption that vaccination would reduce that risk.

The FDA acknowledges this failure, noting understatedly in its “limitations” section that “available data are not conclusive on the effectiveness of COVID‑19 vaccines currently in use against long-term sequelae of COVID‑19 among individuals who are infected despite vaccination. Additional evaluation is needed to assess the effect of this vaccine in preventing long-term effects of COVID‑19, including data from clinical trials and from the vaccine’s use post-authorization.”

To justify its authorization of the vaccine for infants and toddlers, the FDA simply assumed that it would be protective against persistent symptoms following breakthrough infection — once again, a faith-based and not evidence-based approach.

In my next newsletter, I’ll go over how the FDA misled about the risk of myocarditis from COVID-19 versus the risk of myocarditis from COVID-19 vaccination.


Wow. Jeremy is spot-on, and thorough. I would like to suggest that all of my readers head to JeremyRHammond.com and sign up for his free newsletter for more content like this, that would be perfect. Each of the newsletters in this series is a summary version of a section of the major paper he is working on, which he will be publishing as a downloadable e-book, so subscribers can also stay tuned for that more extensive and fully reference

__________________

https://ahrp.org/israel-was-caught-concealing-childrens-vaccine-injuries/

Israel Was Caught Concealing Children’s Vaccine Injuries

July 19, 2022

by Vera Sharav
Alliance for Human Research Protection

Israel’s Ministry of Health commissioned a study analyzing reports of adverse events from Pfizer’s COVID vaccine to Israel’s vaccine database, known as the Nahlieli system, between December 2021 and May 2022. The research team was headed by Professor Matti Berkowitz, director of the Clinical Pharmacology and Toxicology Unit at Assaf Harofeh Hospital (Shamir).

Prof. Berkowitz’s team found that children in the 5-11-year age group had twice to four times as many adverse events following the Pfizer shot as children in the 12-17 age group. This doubling of vaccine injuries is, in itself, extremely disturbing — and should have been immediately brought to the attention of the nation’s parents.

The parents were not informed. What’s more, the Ministry officials recommended booster shots for youngsters aged 5-11—thereby increasing the risk for serious harm.

Furthermore,  the doubling of adverse events is only the beginning of the bad news.
As Dr. Yaffa Shir-Raz, a health and risk communication researcher at the University of Haifa and at Reichman University, explained: the 2-dose immunization rate for 5 to 11-year-olds is less than 18%, while older children have rates of 55-72% (3-4 times higher).

“That means that the young children would thus be expected to have ⅓-¼ of the number of adverse events experienced by the older children, not twice as many. This means that the adverse event rate for young children is actually 6-8 times that of the older children, i.e., at 600-800% of the baseline injury rate!”

It is unconscionable that the Israeli Health Ministry knew about the serious risks of harm posed to young children, concealed the evidence, and further expanded the ever-increasing risk for children by authorizing the use of these UNSAFE and medically unjustifiable genetically manipulated injections for infants and toddlers!

(See link for article)

___________________

To gain insight into the scope and magnitude of harm to individual, previously healthy Israelis, I highly recommend that you check Avital Livni’s Israel Testimonies Project

The Testimonies Project was created to provide a platform for all those who were affected after getting the covid-19 vaccines, and to make sure their voices are heard, since they are not heard in the Israeli media.

We hope this project will encourage more and more people to tell their story.

For more: