https://www.medpagetoday.com/special-reports/exclusives/93485?xid=nl_mpt_DHE_2021-07-

Awaited Ivermectin Review Is Out

— Findings are positive, but critics still want a randomized controlled trial
Boxes and blister pack of Ivermectin Tablets USP Boxes and blister pack of Ivermectin Tablets USP and a prescription bottle.a

Proponents of ivermectin for COVID-19 have long been talking about an expected review and meta-analysis led by Andrew Hill, PhD, of the University of Liverpool.

These results were finally published this week in Open Forum Infectious Diseases, and they’re positive — but they haven’t escaped criticism, and most researchers still want results from a randomized controlled trial.  (See link for article)

___________________

**Comment**

The following was found from the review:

  • There was a 56% reduction in mortality (relative risk [RR] 0.44, 95% CI 0.25-0.77, P=0.004), with 3% of patients on ivermectin dying compared with 9% of controls
  • A 70% improvement in survival (RR 0.30, 95% CI 0.15-0.58, P=0.0004)
  • A reduction in time to recovery of 1.58 days compared with controls (95% CI -2.8 to -0.35, P=0.01) 
  • A shorter duration of hospitalization (-4.27 days, 95% CI -8.6 to -0.06, P=0.05).
But this still wasn’t good enough for critics.

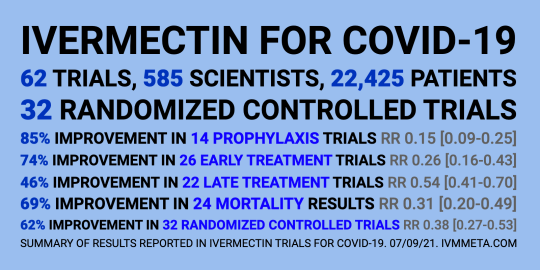
And there’s been 32 randomized controlled trials done to date, but that still isn’t good enough for critics.

The key for this is found in the following quote:

“Of course, rolling out vaccination as quickly and widespread as possible would negate the need to use ivermectin as a treatment,” he added. “So big picture, vaccines are the better solution.”

This is completely backwards.

Rolling out effective treatments as quickly and widespread as possible negates the need for a vaccine!  But history is being rewritten to state natural immunity will only be achieved through vaccines – the magic bullet for mankind.

Despite what mainstream news and medical rag journals like Medscape state, current research shows:

isummarySource: Database of all ivermectin COVID-19 studies – www.c19ivermectin.com – (constantly updated)

For the backstory on how Remdesivir obtained EUA status despite lack of effectiveness, while Ivermectin languished on shelves see this article for the sordid history.

In what can only be described as “shennanigans,” researchers changed the primary outcome measures in the study for Remdesivir to make it appear more successful.  Go here for more info.

For more on Ivermectin:

“We now have four large randomized control trials totaling over 1,500 patients each trial showing that as a prophylaxis agent [against COVID-19] it is immensely effective,” Kory said. “You will not get sick. You will be protected from getting ill if you take it in early outpatient treatment.”

Please see FLCCC’s COVID-19 treatment protocols for every stage of illness: https://covid19criticalcare.com/covid-19-protocols/  as well as the research on it:   https://covid19criticalcare.com/ivermectin-in-covid-19/

Lastly, the following was written about the Medscape piece:

I have years of experience with Ivermectin in the Brazilian Amazon. The drug in general, has acceptable safety profile. Ivermectin has few established mechanisms of action; chief among them are its immunomodulatory and antiinflammatory properties. Recently, Australian scientists conducted an in vitro study of the MOA of Ivermectin with respect to SARS-CoV-2 replication. The Australian study showed it interferes with a specific protein product which is essential in the viral replication cycle. Considering the benefit of this drug outweighs the risk, Ivermectin is a reliable and practical solution in resource-limited countries where access to COVID-19 meds is scarce. It is commonly understood that in the western countries, the Big Pharma resists prescription of Ivermectin for COVID19 cases.  – Prof. Dr. Nassiri, July 9, 2021

BINGO!

https://danielcameronmd.com/lyme-disease-triggers-hearing-loss/

LYME DISEASE AND SUDDEN ONSET HEARING LOSS

lyme-disease-sudden-onset-hearing-loss

An article by Sowula and colleagues, published in the Journal of Clinical Medicine, describes nine patients with Lyme disease who had sudden sensorineural hearing loss (SSNHL), also referred to as sudden deafness.[1]

The study aimed to assess the prevalence of this type of sudden onset hearing loss, particularly among Lyme disease patients. The authors explain, “Sudden sensorineural hearing loss (SSNHL) is defined as sensorineural hearing loss of 30 dB or more over at least three adjacent audiometric frequencies occurring within a 72-h period of time.”

This type of sudden onset hearing loss can be caused by a viral infection, vascular insufficiency, autoimmune disorder, neoplasm, stroke and irradiation. 

Treatment is directed towards the cause with standard therapy typically involving corticosteroid, vasodilators, and ionotropic agents, the authors write. Unfortunately, the cause is unknown in 90% of the cases.

The study looked at 86 patients who were hospitalized, between 2017 and 2018, due to sudden sensorineural hearing loss. As part of their evaluation for sudden onset hearing loss, patients were tested for Lyme disease.

Out of 86 patients, 9 tested positive for Lyme disease. Other studies, however, indicate that up to 21% of patients with sudden sensorineural hearing loss test positive for Lyme disease, the authors write.

Hearing loss patients with Lyme disease

On average, the 9 patients were around 47 years old, with an age range between 30 and 70. None of the Lyme disease patients responded to intravenous corticosteroids, microcirculatory drugs, or ionotropic drugs.

Seven of the nine patients with sudden onset sensorineural hearing loss were treated with oral doxycycline or intravenous ceftriaxone.  

Four patients were treated with doxycycline. Hearing improved by 10dB for one of the patients.

Complete hearing recovery with IV ceftriaxone

The remaining 3 patients, who were treated with intravenous ceftriaxone, had complete improvement in their hearing loss.  

“Those three patients reported a complete recovery of hearing (PTA shows respectively 15.20 dB HL for low frequency and 28.35 dB HL for high frequency),” the authors write.

“Infections caused by Borrelia burgdorferi may contribute to the development of inflammatory and angiopathic lesions, which are a possible cause of [sudden sensorineural hearing loss].”

Unfortunately, 2 patients were left with high-frequency tinnitus. “In these patients, tinnitus was present from the beginning of the disease,” the authors write.

The group of 9 Lyme disease patients “was treated with antibiotics and experienced partial or complete regression of their deafness,” the authors conclude. “This may suggest a relationship between [sudden sensorineural hearing loss] and Lyme disease.”

“The longer the duration of the infection, the greater the likelihood of permanent and irreversible changes in the vessels of the cochlea or auditory nerve,” the authors caution.

References:
  1. Sowula K, Szaleniec J, Stolcman K, Ceranowicz P, Kocon S, Tomik J. Association between Sudden Sensorineural Hearing Loss and Lyme Disease. J Clin Med. Mar 8 2021;10(5)doi:10.3390/jcm10051130

___________________

For more:

https://twitter.com/wakeupfromcovid/status/1413296314960515072?s=20  2 Minute Video Here

“Don’t take the 2nd shot.” — Professor Sucharit Bhakdi

For the whole video (16 Min) go here.

Links to papers summarized in the video:

For more:

https://madisonarealymesupportgroup.com/2021/07/07/what-is-in-the-pcr-tests/  Excerpt:

The masks being used and currently marketed contain graphene oxide. Not only the ones that were withdrawn at the time, as indicated by the media, the swabs used in both PCR and antigen tests also contain graphene oxide nanoparticles.

The COVID vaccines in all their variants, AstraZeca, Pfizer, Moderna, Sinovac, Janssen, Johnson & Johnson, etc., also contain a considerable dose of graphene oxide nanoparticles. This has been the result of their analysis by electron microscopy and spectroscopy, among other techniques used by various public universities in our country.  Source

https://articles.mercola.com/sites/articles/archive/2021/07/09/niaid-moderna-covid-vaccine-candidate.aspx?

NIAID, Moderna Had COVID Vaccine Candidate in December 2019

Analysis by Dr. Joseph MercolaFact Checked, July 09, 2021
niaid moderna covid vaccine candidate
STORY AT-A-GLANCE
  • Moderna, together with the National Institute of Allergy and Infectious Diseases (NIAID), sent mRNA coronavirus vaccine candidates to the University of North Carolina at Chapel Hill on December 12, 2019 — raising significant red flags
  • The providers agreed to transfer “mRNA coronavirus vaccine candidates developed and jointly-owned by NIAID and Moderna” to the university’s investigator and was signed by Ralph Baric
  • Baric pioneered techniques for genetically manipulating coronaviruses, which became a major focus for research at the Wuhan Institute of Virology (WIV)
  • Baric worked closely with WIV’s Shi Zhengli, Ph.D., on research using genetic engineering to create a “new bat SARS-like virus … that can jump directly from its bat hosts to humans”
  • Serious questions need to be answered, including: Were Moderna, NIAID and Baric aware that COVID-19 was circulating in mid-December 2019, or did they have knowledge far before that such a vaccine would soon be in demand?

So much has happened over the past year that it may be hard to remember what life was like pre-COVID. But let’s flash back to December 2019, when the idea of social distancing, compulsory masking and lockdowns would have been met with disbelief and outrage by most Americans.

At that time, most were blissfully unaware of the pandemic that would change the world in the next few months. It wasn’t until December 31, 2019, that the COVID-19 outbreak was first reported from Wuhan, China,1 and at this point it was only referred to as cases of viral pneumonia, not a novel coronavirus.2 I say “most” because it seems some people may have been aware of something lurking much earlier than it appeared.

In confidential documents3 revealed by the U.K.’s Daily Expose, Moderna, together with the National Institute of Allergy and Infectious Diseases (NIAID), sent mRNA coronavirus vaccine candidates to the University of North Carolina at Chapel Hill December 12, 2019 — raising significant red flags. As The Daily Expose reported:4

“What did Moderna [and NIAID] know that we didn’t? In 2019 there was not any singular coronavirus posing a threat to humanity which would warrant a vaccine, and evidence suggests there hasn’t been a singular coronavirus posing a threat to humanity throughout 2020 and 2021 either.”

COVID-19 Vaccine Candidate Was Released Prior to Pandemic

The confidential disclosure agreement relays a material transfer agreement between the providers — Moderna, NIAID and the National Institutes of Health (NIH) — and the University of North Carolina at Chapel Hill. The providers agreed to transfer “mRNA coronavirus vaccine candidates developed and jointly-owned by NIAID and Moderna” to the university’s investigator.5

“The material transfer agreement was signed the December 12th 2019 by Ralph Baric, PhD, at the University of North Carolina at Chapel Hill, and then signed by Jacqueline Quay, Director of Licensing and Innovation Support at the University of North Carolina on December 16th 2019,” Daily Expose noted.

At this point, some backstory information is more than relevant. We know with great certainty that researchers at China’s Wuhan Institute of Virology (WIV) had access to and were doing gain-of-function research on coronaviruses, and manipulating them to become more infectious and to more easily infect humans. We also know that they collaborated with scientists in the U.S. and received funding from the National Institutes of Health for such research.

Baric, who signed the material transfer agreement to investigate the mRNA coronavirus vaccine candidate before there was a known COVID-19 pandemic, pioneered techniques for genetically manipulating coronaviruses, according to Peter Gøtzsche with the Institute for Scientific Freedom,6 and these became a major focus for WIV.

Baric worked closely with Shi Zhengli, Ph.D., the director of WIV’s Center for Emerging Infectious Diseases, also known as “bat woman,” on research using genetic engineering to create a “new bat SARS-like virus … that can jump directly from its bat hosts to humans.” According to Gøtzsche:7

“Their work focused on enhancing the ability of bat viruses to attack humans so as to ‘examine the emergence potential.’ In 2015, they created a novel virus by taking the backbone of the SARS virus replacing its spike protein with one from another bat virus known as SHC014-CoV. This manufactured virus was able to infect a lab culture of cells from the human airways.

They wrote that scientific review panels might deem their research too risky to pursue but argued that it had the potential to prepare for and mitigate future outbreaks. However, the value of gain-of-function studies in preventing the COVID-19 pandemic was negative, as this research highly likely created the pandemic.”

Moderna Gets Emergency Use Approval for COVID Vaccines

The rest of the story, as the saying goes, is history. December 12, 2019, Amy Petrick, Ph.D., NIAID’s technology transfer specialist, signed the agreement, along with Dr. Barney Graham, an investigator for NIAID, whose signature is undated.8 May 12, 2020, just months later, Moderna was granted a fast-track designation for its mRNA-1273 vaccine by the U.S. Food and Drug Administration. According to Moderna’s news release:9

“mRNA-1273 is an mRNA vaccine against SARS-CoV-2 encoding for a prefusion stabilized form of the Spike (S) protein, which was selected by Moderna in collaboration with investigators from Vaccine Research Center (VRC) at the National Institute of Allergy and Infectious Diseases (NIAID), a part of the NIH.”

December 18, 2020 — about one year after the material transfer agreement was signed — the FDA issued emergency use authorization for Moderna’s COVID-19 vaccine for use in individuals 18 years of age and older.10 June 10, 2021, Moderna also filed for emergency use authorization for its COVID-19 shot to be used in U.S. adolescents aged 12 to 17 years.11 Yet, we still have no answers to some glaring questions:12

“It was not until January 9th 2020 that the WHO reported13 Chinese authorities had determined the outbreak was due to a novel coronavirus which later became known as SARS-CoV-2 with the alleged resultant disease dubbed COVID-19. So why was an mRNA coronavirus vaccine candidate developed by Moderna being transferred to the University of North Carolina on December 12th 2019?

… Perhaps Moderna and the National Institute of Allergy and Infectious Diseases would like to explain themselves in a court of law?”

SARS-CoV-2 Appears To Be Uniquely Able to Infect Humans

Nikolai Petrovsky, professor of endocrinology at Flinders University College of Medicine in Adelaide, Australia, is among those who has stated SARS-CoV-2 appears to be optimally designed to infect humans.14

His team sought to identify a way by which animals might have comingled to give rise to SARS-CoV-2, but concluded that it could not be a naturally occurring virus. Petrovsky has previously stated it appears far more likely that the virus was created in a laboratory without the use of genetic engineering, by growing it in different kinds of animal cells.15

To adapt the virus to humans, it would have been grown in cells that have the human ACE2 receptor. Over time, the virus would then adapt and eventually gain the ability to bind to the human receptor. U.S. Right to Know (USRTK) pointed out that the issue of binding sites is an important one, as the distinctive binding sites of the SARS-CoV-2 spike protein “confer ‘near-optimal’ binding and entry of the virus into human cells.“16

Scientists have argued that SARS-CoV-2’s unique binding sites may be the result of either natural spillover in the wild or deliberate recombination of an unidentified viral ancestor. Baric and others, including Peter Daszak, EcoHealth Alliance president, to which he is closely tied, were quick to dismiss the lab-leak hypothesis, which suggests that SARS-CoV-2 accidently leaked from a laboratory in Wuhan, China. Yet, according to Gøtzsche:17

“On 9 December 2019, just before the outbreak of the pandemic, Daszak gave an interview in which he talked in glowing terms of how his researchers at the Wuhan Institute had created over 100 new SARS- related coronaviruses, some of which could get into human cells and could cause untreatable SARS disease in humanized mice … ”

Daszak’s EcoHealth Alliance funded controversial GOF research at WIV; NIAID gave funding to the EcoHealth Alliance, which then funneled it to WIV.18 Daszak, despite working closely with WIV, was part of the World Health Organization’s investigative team charged with identifying the origin of SARS-CoV-2. Not surprisingly, the team dismissed the lab-accident theory.

Baric’s SARS-Like Virus Wasn’t Made Public Until May 2020

Regarding the novel SARS-like virus that Shi and Baric created in 2015, this research was conducted using a grant from EcoHealth Alliance.

While the information relating to the virus’ DNA and RNA sequences was supposed to have been submitted to a national biotechnology information database when the research was published, this wasn’t done until years later, in the midst of the COVID-19 pandemic. As reported by Alexis Baden-Mayer, political director for the Organic Consumers Association:19

“The work, ‘A SARS-like cluster of circulating bat coronaviruses shows potential for human emergence,’20 published in Nature in 2015 during the NIH’s moratorium21 on gain-of-function research, was grandfathered in because it was initiated before the moratorium … and because the request by Shi and Baric to continue their research during the moratorium was approved by the NIH.

As a condition of publication, Nature, like most scientific journals, requires22 authors to submit new DNA and RNA sequences to GenBank, the U.S. National Center for Biotechnology Information Database. Yet the new SARS-like virus Shi and Baric created wasn’t deposited23 in GenBank until May 2020.”

Meanwhile, both Baric24 and Daszak were involved in organizing the publication of a scientific statement, published in The Lancet and signed by 26 additional scientists, condemning inquiries into the lab-leak hypothesis as “conspiracy theory.”25

Daszak was also made a commissioner of the Lancet Commission on COVID-19, but now that his extreme conflict of interest has been made public, he was recused from the commission.26

Baric, Daszak Downplay Lab-Leak Theory

At the time The Lancet statement was released in February 2020, Daszak had advised Baric against adding his signature because he wanted to “put it out in a way that doesn’t link it back to our collaboration so we maximize an independent voice.”27 The authors also declared no competing interests.

In an update published June 21, 2021, The Lancet stated, “Some readers have questioned the validity of this disclosure, particularly as it relates to one of the authors, Peter Daszak.”28 The journal invited the authors to “re-evaluate their competing interests,” and Daszak suddenly had much more to say. His updated disclosure statement reads, in part:29

“EcoHealth Alliance’s work in China includes collaboration with a range of universities and governmental health and environmental science organizations, all of which are listed in prior publications, three of which received funding from US federal agencies as part of EcoHealth Alliance grants or cooperative agreements, as publicly reported by NIH.

… EcoHealth Alliance’s work in China involves assessing the risk of viral spillover across the wildlife–livestock–human interface, and includes behavioral and serological surveys of people, and ecological and virological analyses of animals.

This work includes the identification of viral sequences in bat samples, and has resulted in the isolation of three bat SARS-related coronaviruses that are now used as reagents to test therapeutics and vaccines.

It also includes the production of a small number of recombinant bat coronaviruses to analyze cell entry and other characteristics of bat coronaviruses for which only the genetic sequences are available.”

Also of note, a special review board, the Potential Pandemic Pathogens Control and Oversight (P3CO) committee, was created within the Department of Health and Human Services to evaluate whether grants involving dangerous pathogens are worth the risks.

Baden-Mayer explained, “This committee was set up as a condition for lifting the 2014-2017 moratorium on gain-of-function research. The P3CO committee operates in secret. Not even a membership list has been released.”30

Daszak stated in his updated disclosure, “NIH reviewed the planned recombinant virus work and deemed it does not meet the criteria that would warrant further specific review by its Potential Pandemic Pathogen Care and Oversight (P3CO) committee.”31

However, according to Rutgers University professor Richard Ebright, an NIH grant for research involving the modification of bat coronaviruses at the WIV was sneaked through because the NIAID didn’t flag it for review.32 In other words, the WIV received federal funding from the NIAID without the research first receiving a green-light from the HHS review board.

The NIAID apparently used a convenient loophole in the review framework. As it turns out, it’s the funding agency’s responsibility to flag potential GOF research for review. If it doesn’t, the review board has no knowledge of it. According to Ebright, the NIAID and NIH have “systemically thwarted — indeed systematically nullified — the HHS P3CO Framework by declining to flag and forward proposals for review.”33

Who Knew What, and When?

We now have proof that Moderna and NIAID sent their mRNA coronavirus vaccine candidates to Baric at the University of North Carolina at Chapel Hill in mid-December 2019.

Were they aware that COVID-19 was circulating at that time, or did they have knowledge far before that such a vaccine would soon be in demand? The red flags, and cover-ups, continue to mount, but ultimately the truth will prevail.

_____________________

For more:

Over 55,327 emails have been sent to key congressional committee members regarding the need for an investigation into the CDC’s death certificate data disaster and 41,201 names have been placed on our petitions to urge assistant U.S. attorneys nationwide to convene a special independent grand jury investigation into the CDC’s conduct during COVID-19.

With each passing week, it continues to become clear that an investigation—free of conflict-of-interests—into the CDC’s conduct surrounding COVID-19 is desperately needed. Here is how you can help, now!

1️⃣  Learn The Latest
Stand for Health Freedom Executive Director and Co-founder Leah Wilson recently interviewed Dr. Henry Ealy, lead author on five research papers about COVID-19 related to public health policies. His COVID Research Team has dedicated more than 20,000 hours to investigating all aspects of COVID-19, with the aim of their findings being used to empower advocates like you as well as elected officials, attorneys, professional organizations, and the general public to make informed decisions and to take action!

Thanks to Dr. Ealy and his team, Stand for Health Freedom, has solid evidence that the official COVID numbers being reported are not accurate. Moreover, these numbers have been skewed to incite fear and invoke public policies that have radically changed how we as a society work, worship, learn, move about society and interact with others, including our own family members. The United States has been in a state of public health emergency for well over a year now. We cannot idly sit by and allow agencies that are entrusted with protecting our health to invoke bad policies, keep us in a state of perpetual lockdown, or engage in acts of potential willful misconduct at the expense of our basic human rights.

2️⃣  Use Your Voice

Your voice matters—get inspired to talk to your family members, neighbors and community about the irrefutable truth that is surfacing each week alongside the questionable motives emerging; ask critical questions, share published research and invite them to watch the peer-reviewed and published experts that the mainstream media willfully ignores.

3️⃣  Easy Steps You Can Take
Take a stand and call upon U.S. Attorneys and key members of Congress to investigate the CDC’s conduct.

✔️ Step One: Take Action by adding your signature today to join our petition to call on key U.S. Attorneys to investigate the CDC’s conduct through a formal Grand Jury investigation.

https://standforhealthfreedom.com/action/cdc-grand-jury-investigation/ Sign here

✔️ Step Two: Take Action by sending a letter to ask members of Congress to formally investigate the CDC’s conduct during COVID-19 through congressional hearings.

https://standforhealthfreedom.com/action/investigate-the-cdc/  Sign here

“It is incumbent upon you to do your homework and be a part of your own rescue because the people who are in positions of power right now are abusing their power. They are corrupt, and they do not have our families and our children’s best interests at heart. And their actions prove it over and over again, regardless of the lies they continue to spill out of their mouths. … We cannot protect our children by being polite and silent about this anymore. It is incumbent upon us to be the shield that protects our families, and the way we do that is through knowledge and love.”– Dr. Henry Ealy

In Solidarity

Stand for Health Freedom

P.S. Dr. Ealy appeared in Stand for Health Freedom’s CDC Data Disaster panel event this past February, where a panel of experts discussed why we should be concerned about death certificate data, why accuracy, integrity and transparency are so important during a public health crisis, how the CDC set the stage for widespread devastation — physical, psychological and economic, and some simple steps we can take so that incidents of this magnitude never happen again.

P.S.S. Support our efforts in growing the health freedom voting bloc by donating here.

____________________

For Stand for Freedom’s Peer-Reviewed position paper & petition to investigate the CDC, go here.

Please also sign Lyme advocate Carl Tuttle’s petition to investigate the CDC over the mismanagement of Lyme/MSIDS:   https://madisonarealymesupportgroup.com/2019/04/23/cdcs-long-history-of-incompetence-deception-in-the-management-of-lyme-disease/

For more: