A public hearing has just been scheduled for Thursday, July 29 at 9:00 am for the Complementary and Alternative Health Care Practitioners Exemption bill (SB 98/AB 86) in the Assembly Health Committee!  Write to your own legislators asking them to support the bill. 

CLICK TO ASK YOUR LEGISLATORS TO SUPPORT SB 98/AB 86

Then, please prepare and submit testimony in support of the bill too (details below). 

When passed, Wisconsin will join eleven other states in protecting the thousands of wonderful complementary and alternative practitioners who are providing great services to health seekers in Wisconsin.  This bill already passed unanimously out of the Senate Insurance, Licensing and Forestry Committee on April 1 and it passed the Senate, as amended, on a unanimous voice vote on April 14.  

To refresh your memory: It was introduced last session (2019 AB 546/SB 492). It passed the Assembly Health Committee, the Assembly floor and the Senate Committee on Health before stalling in the Senate due to COVID-19. Unfortunately, this legislation was moved aside and was not addressed before the end of the legislative session.  

What the Bill Does:

SB 98/AB 86 is a bill to protect your access to services provided by practitioners of complementary and alternative health in Wisconsin such as herbalists, traditional naturopaths, nutritional consultants, homeopaths, Reiki practitioners and many more.  This exemption bill will make it possible for practitioners to provide their services without fear of being charged with practice of medicine without a license as long as they avoid a list of prohibited acts in the bill such as the use of prescription drugs, or puncture of the skin, and as long as they give out proper disclosures.

What you can do:

1. Take Action here to send a message of support for SB 98/AB 86 to your personal legislators.  Please take the time to write a personal note on your letter as this will have a greater impact with the legislator or send the letter we have provided. Start building a relationship with your personal Senate and Assembly Representatives. 

2. Call your legislators to leave a message reiterating your support of SB 98/AB 86.  Identify who your legislators are here by entering you address in the box under “Who are my legislators?” and click “Find your Legislator”.  Use their contact info to leave a message with each office letting them know why you support SB 98/AB 86.  Note: if your legislator is a sponsor of the bill, say Thank You!  Current sponsor and cosponsors of the bill include 14 Representatives (Dittrich, Horlacher, Kitchens, Murphy, Mursau, Schraa, Skowronski, Wichgers, Zimmerman, Callahan, Edming, Sortwell, Moses and Rozar) and 3 Senators (Felzkowski, Kooyenga and Bernier). 

The message for your personal legislators:

“As a constituent of [Senator/Assemblymember] [Insert Legislator’s Last Name] I want [him/her] to know that I support SB 98/AB 86, a bill Protecting Consumer Access to Complementary and Alternative Health Care Practitioners.  AB 86 is scheduled for a hearing on July 29 in the Assembly Health Committee.  Please tell the [Senator/Assemblymember] that I want [him/her] to please vote yes on the bill when it is heard on the floor of the [Senate/Assembly].  [Insert your own brief reason why you support access to complementary and alternative health care (i.e., I depend on complementary and alternative health care for myself and my family and I want Wisconsin law to protect my rights as a consumer to a free and educated choice in health care providers.)] Thank you.” 

3. Prepare Your Testimony for the Committee. It’s so important for legislators to hear from the public on a bill.  Your story could be just what a legislator needs to hear in order to vote in favor of the bill.  Written testimony should be given to the Committee in person but we can collect your written testimony and deliver it the day of the hearing.  Please send it to rosanne.lindsay@gmail.com and Nathan.Halbach@huschblackwell.com and we’ll deliver it to the committee for you.  Note: Due to COVID restrictions and the size of the hearing room, the committee is requesting written testimony over in-person testimony.  They are not allowing virtual testimony at this time.  Therefore, your written testimony is that much more important.  A few sentences about why you support SB 98/AB 86 is all that’s needed.  Please draft and submit it asap. 

4. Spread the word about SB 98/AB 86.  Please forward this email to your friends and family so they can Take Action to support SB 98/AB 86 too. THANK YOU for your commitment to Health Freedom!  If you have questions, contact us at info.nhfa@nationalhealthfreedom.org.   

Now more than ever it is important that we use the tools that are available to us as Americans. Your donation makes a huge difference in our ability to educate, foster and mobilize with people like you in states across the country. Together we can create the laws “we wish to see in the world”. Laws that protect our rights to make choices about our own health and the health of our children. 

___________________

**Comment**

I’ve put in a call to NHFA regarding not being able to have my information sent to ask my legislators to support SB 98/AB 86. I keep getting “Error code 500, try again later.”

I will try again later, and so should you if you get this code; however, hopefully my alerting them of this will help matters get resolved.

Since Lyme/MSIDS patients have such a hard time receiving medical treatment, it’s imperative alternative practitioners are free to help patients obtain treatment.
https://danielcameronmd.com/lyme-disease-skin-rash-misdiagnoses/

LYME DISEASE SKIN RASH PUZZLES DOCTORS, LEADS TO MISDIAGNOSES

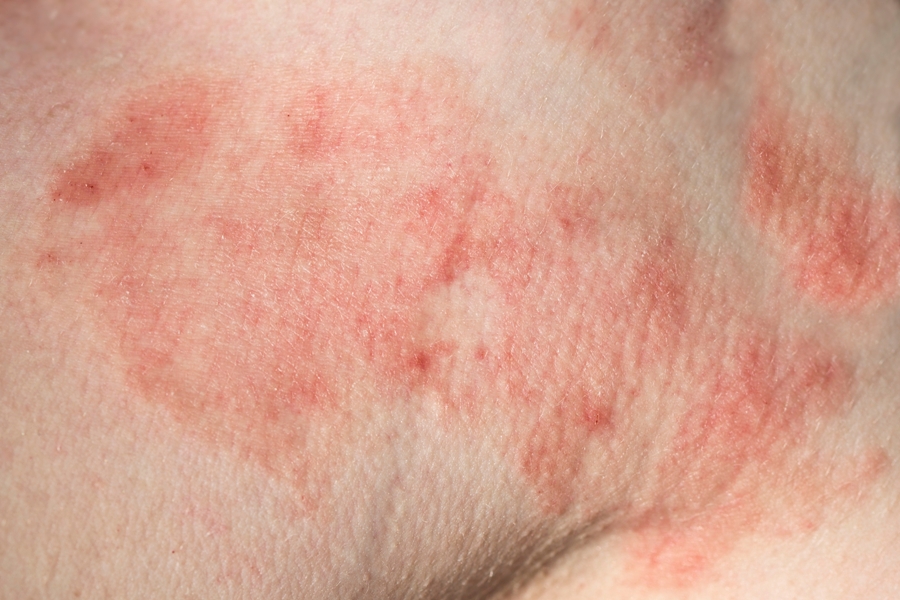
Patient with Lyme disease skin rash

Lyme disease can cause an atypical skin rash that may be mistakenly attributed to another illness, as this case report demonstrates. In their article, Suzuki and colleagues describe a 43-year-old woman who developed a rash which puzzled doctors and led to several misdiagnoses before Lyme disease was correctly identified.


Lyme disease can cause an atypical skin rash, which may be overlooked by clinicians. In this case report, a 43-year-old woman, who was an avid gardener and lived in Wisconsin, developed pink papules behind her right knee.1  Over the next several days, the rash “evolved into painless vesicles with surrounding faint erythema.” She also developed fever, chills, neck pain and malaise.

Diagnoses: shingles, cellulitis, necrotizing fasciitis

Doctors initially suspected shingles (Herpes Zoster) but treatment with valacyclovir, an antiviral medication, did not improve the skin rash or symptoms. “The blisters increased in size and showed purple discoloration,” the authors wrote.

The doctors then diagnosed her with cellulitis, a bacterial skin infection which also causes a skin rash. She was prescribed ceftriaxone, followed by cephalexin and trimethoprim-sulfamethoxazole. But the woman remained ill.

She was then referred for evaluation for suspected necrotizing fasciitis, an inflammation of the vessel walls.  At this time, she had a fever of 101.3°F.

“The atypical appearance of skin rash might confuse physicians with many differential diagnoses, such as spider bite, herpes zoster, bullous cellulitis, necrotizing fasciitis, and so on.”

Additionally:

“Physical examination showed blister and a surrounding round erythematous patch at the right popliteal fossa and right inguinal lymphadenopathy,” the authors wrote.

Lyme disease skin rash

The woman was diagnosed clinically with “early Lyme disease with bullous erythema migrans.”

“Given the season, geographic location, outdoor activity, and progression despite treatment for cellulitis and shingles, she was clinically diagnosed with early Lyme disease,” the authors report.

The woman was treated for Lyme disease with a 10-day course of doxycycline and her skin rash resolved.

Laboratory tests for Lyme disease were negative – a common occurrence with early Lyme disease.

“The atypical appearance of skin rash might confuse physicians with many differential diagnoses, such as spider bite, herpes zoster, bullous cellulitis, necrotizing fasciitis, and so on,” the authors point out.

Editor’s comments:  I have seen rashes described in this article in my Lyme disease patients. I am concerned when a patient is diagnosed with shingles, cellulitis or necrotizing vasculitis before Lyme disease is considered as a possible cause of an atypical skin rash.

If uncertain about the root cause of the rash, I will typically treat patients with a combination of medications including an antiviral agent and an antibiotic that is effective in treating cellulitis, a spider bite and Lyme disease.
References:
  1. Suzuki H, Carlson JR, Matsumoto E. 43-Year-Old Female With Fever and Bullous Skin Lesion. Clin Infect Dis. Dec 17 2020;71(10):2763-2764. doi:10.1093/cid/ciaa206

_____________________

**Comment**

Everyone knows that delayed treatment for Lyme/MSIDS is causing chronic/persistent symptoms, yet it continually appears doctors would rather diagnose patients with anything other than Lyme/MSIDS.  It’s almost like they want to run through a litany of other causes first, treat for those, and finally if nothing works throw up the white flat and admit it’s tick-borne illness.

For more:

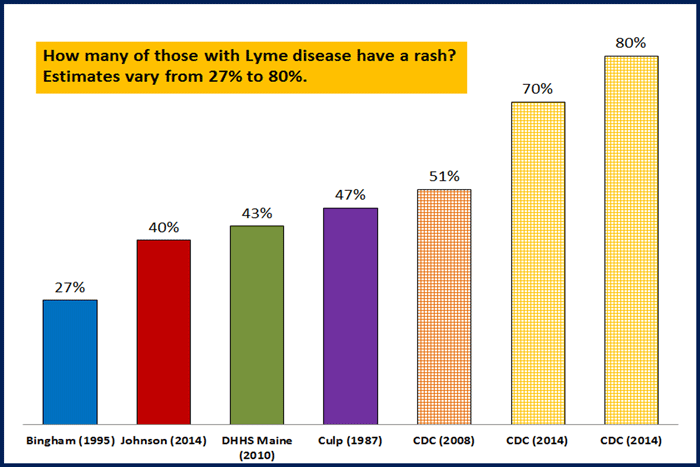
Please remember that those getting the rash is highly variable and certainly not a sure thing.  If you get it, it is diagnostic for Lyme – no testing needed; however, if you don’t get it, you can still be infected:

Rashes-larger-blog-4

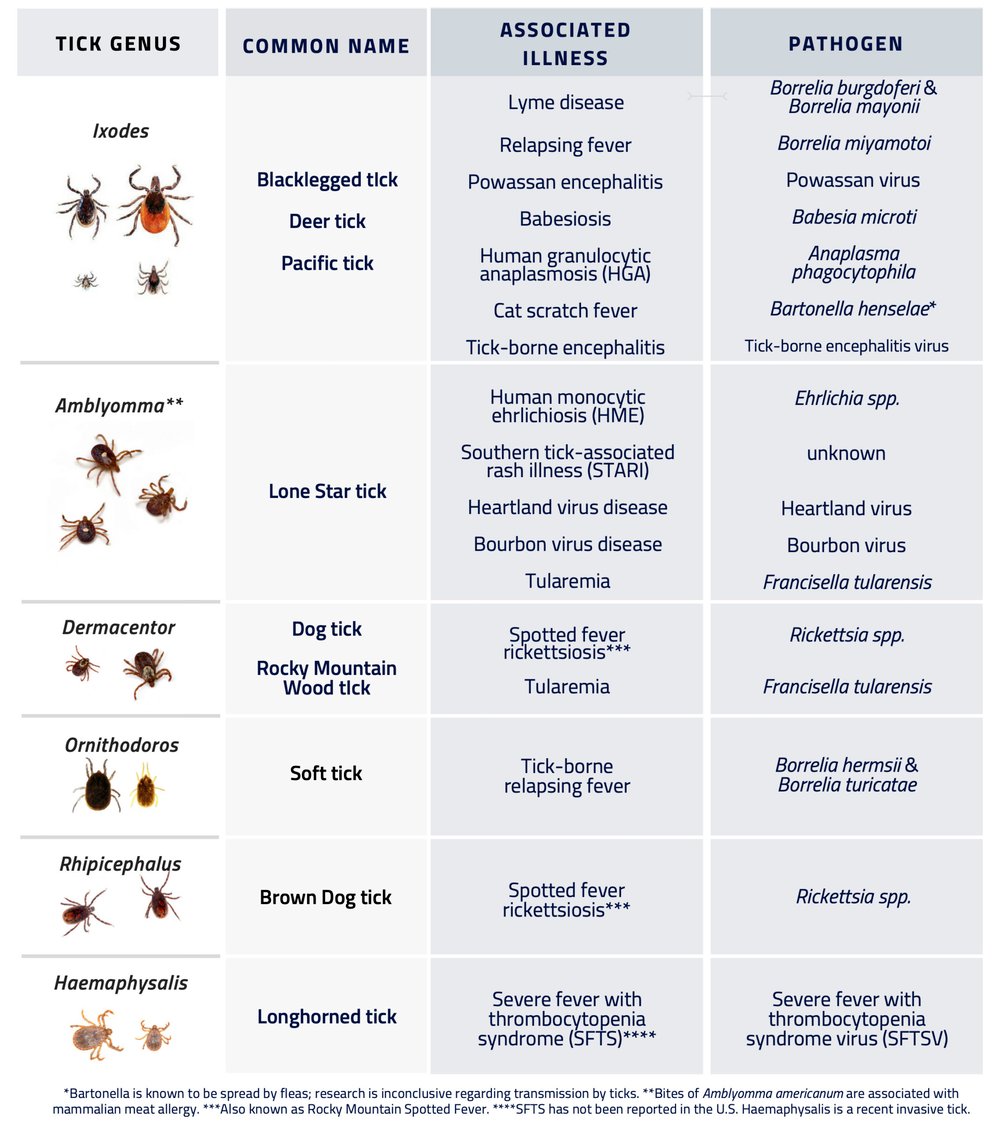
Know Your Ticks

https://www.globallymealliance.org/tick-table/

Know your ticks

Easy to read table shows the most common ticks found in the U.S. that transmit pathogens to humans.
Note: only a partial list. To learn more about tick-bite prevention and how to be Tick AWARE, click here

Click here to download the Tick Table

Tick Table

For more:

Remember, in Wisconsin, ticks are found in every county in the state. Researchers are also finding them in bright, open, mowed lawns.

https://danielcameronmd.com/babesia-microti-multiple-sclerosis-patient/  Go Here for Podcast

BABESIA MICROTI IN A MULTIPLE SCLEROSIS PATIENT

babesia microti in MS patient

Welcome to another Inside Lyme Podcast. I am your host Dr. Daniel Cameron. In this episode, I will be discussing the case of a 54-year-old male with a 12-year history of multiple sclerosis who was diagnosed with Babesia microti.

Haberli and colleagues describe the case in the journal Multiple Sclerosis and Related Disorders.1

Babesia microti, a tick-borne pathogen that infects red blood cells, can cause severe disease in immunocompromised individuals. This patient was immunocompromised due to multiple sclerosis (MS) and the immunosuppressive drug he was receiving, ocrelizumab.

Disease Modifying Therapy

Ocrelizumab (sold under the brand name Ocrevus™ in the US) was approved in 2017 for the treatment of multiple sclerosis (MS). It is a humanized anti-CD20 monoclonal antibody, which targets mature B-cells that contribute to demyelination and damage to nerve cells.

Ocrelizumab is a disease modifying therapy (DMT) approved to treat both primary progressive MS and relapse-remitting MS. Ocrevus™ can cost just over $65,000 per year if not covered by insurance.

The patient was prescribed Ocrevus™. 

“The use of ocrelizumab has been associated with increased risk of infections involving upper respiratory, gastrointestinal, and urinary tracts, in addition to herpes simplex reactivation,” wrote the authors. 

“Data from one randomized clinical trial has shown a statistically significant increase in the incidence of malignancy among ocrelizumab users compared to placebo and interferon β1,” they added.

Rituximab, a medication with a similar mechanism of action, has been associated with rare infections in non-MS patients including severe or relapsing Babesia microti infections, the authors wrote.

MS patient fails treatment

This is the first published case of Babesia microti in a patient treated with Ocrevus™.

The 54-year-old man had been diagnosed with major depressive disorder, hypertension and had a 12-year history of relapse-remitting multiple sclerosis.

He was hospitalized with malaise, fever, fatigue for one week and episodes of syncope. He failed treatment with 4 different disease modifying drugs ─ glatiramer acetate, natalizumab, dimethyl fumarate, and fingolimod.

The man refused further therapy and was lost to follow-up.

6 years later, MS symptoms worsen

Six years later, the man’s MS symptoms worsened and he was prescribed Ocrevus™.

Four months later, he was hospitalized and treated for possible sepsis. He had unexplained thrombocytopenia (low blood platelet count).

Tests positive for Babesia microti

As part of his sepsis work-up, the patient was tested for tick-borne infections with PCR test results for Babesia microti returning positive.

The man was treated with 500mg daily azithromycin and 750mg twice daily atovaquone. 

“At week 8, his therapy was discontinued due to complete resolution of pancytopenia, negative B. microti PCR, and negative Giemsa-stained blood smear,” wrote the authors.

There have been other cases of Babesia microti patients treated with Ocrevus™.  

“There were five babesiosis cases associated with ocrelizumab reported between June 2018 and August 2020 on the FAERS database,” the authors wrote.²

“There were two females and two males with an age range of 45 to 51 years old, and one female 65 to 85 years old, all of whom had serious events without reported fatalities,” wrote the authors based on a review of the FDA Adverse Event Reporting System (FAERS) public dashboard.

The following questions are addressed in this podcast episode:  

  1. What is Babesia microti?
  2. How do you diagnose Babesia?
  3. Is testing accurate?
  4. How severe is Babesia?
  5. Are there asymptomatic cases of Babesia?
  6. Why do immunosuppressive drugs pose a risk to Babesia patients?
  7. What are the risk factors for symptomatic Babesia?
  8. What is a disease modifying agent?
  9. What is Ocrevus™?
  10. What was the treatment for Babesia?
  11. What is the significance of 8 weeks of treatment with Babesia?

    Thanks for listening to another Inside Lyme Podcast. You can read more about these cases in my show notes and on my website @DanielCameronMD.com. As always, it is your likes, comments, reviews, and shares that help spread the word about Lyme disease. Until next time on Inside Lyme.

Please remember that the advice given is general and not intended as specific advice to any particular patient. If you require specific advice, then please seek that advice from an experienced professional.

Inside Lyme Podcast Series

This Inside Lyme case series will be discussed on my Facebook page and made available on podcast and YouTube.  As always, it is your likes, comments, and shares that help spread the word about this series and our work. If you can, please leave a review on iTunes or wherever else you get your podcasts.

References:
  1. Haberli N, Coban H, Padam C, Montezuma-Rusca JM, Creed MA, Imitola J. Babesia microti infection in a patient with multiple sclerosis treated with ocrelizumab. Mult Scler Relat Disord. Feb 2021;48:102731. doi:10.1016/j.msard.2020.102731
  2. Ezequiel M, Teixeira AT, Brito MJ, Luis C. Pseudotumor cerebri as the presentation of Lyme disease in a non-endemic area. BMJ Case Rep. 2018;2018.

________________________

**Comment**

This case brings up a very important point: MS can be caused or exacerbated by tick-borne infections. Immune-suppressing drugs are contraindicated for people with TBI’s. The only caveat to that is if they are used in conjunction with antibiotics.

I can’t help but wonder how many other patients are out there with this exact same scenario.

For more:

https://www.globallymealliance.org/blog/dear-lyme-warrior-help-1

Every few months, Jennifer Crystal devotes a column to answering your questions. Do you have a question for Jennifer? If so, email her at lymewarriorjennifercrystal@gmail.com.

Is it helpful to pulse antibiotics?

Pulsing is a method of antibiotic administration where the patient takes the medication for a certain amount of time (for example, two weeks) and then stops it for a period (say, another two weeks), and then repeats the cycle. Some people have found great success with this method (Steven Phillips, MD talks about it in his new book Chronic: The Hidden Cause of the Autoimmune Pandemic and How to Get Healthy Again). He writes about patients who were on antibiotics all the time for years and only reached a certain level of wellness, but then felt completely better after switching to a pulsed regimen. Pulsing allows the body to detox, especially after intense Herxheimer reactions, and gives the gut a break, too.

That said, pulsing doesn’t work for everyone. Some feel that doing so allows the spirochetes to build up a stronger load during the off-period, making them harder to kill (and causing worse Herxheimer reactions) during the on-periods. My own body has difficulty adjusting to any kind of on-off regimen (for example, if I’m weaning off a medication, it never works for me to take it every other day; this just causes a jerking effect). For others, that method works just fine. The bottom line is that you need to speak with your Lyme Literate Medical Doctor (LLMD) to see if pulsing is the right choice for you, and you may need to do a little trial-and-error to find out.

I’ve been battling Lyme for four months and just started getting rashes and hives on my legs at random times. It seems it may coincide with something I ate. Did you have any trigger foods, and did you find anything to help rashes and hives long-term?

Lyme is an inflammatory disease. As I explain in my post “Stop the Itching! Lyme and Hives,” Lyme can cause an inflammatory response anywhere in the body, manifesting as redness, swelling, heat, pain, or loss of function. I started getting hives four years after getting a tick bite, but it would be another four years before I got accurately diagnosed and started treatment. Once I did get proper antibiotic treatment, the hives stopped.

Before then, itchiness and redness could sometimes be triggered by exercise. After a run, my legs might turn bright red and grow incredibly itchy. The reaction was never triggered by food, but one of two things may be going on for you. You may simply be having an allergic reaction to something you’re eating (try to find a common denominator in your meals, and see an allergist who can test for food allergies). Or, maybe you are eating an inflammatory food that is exacerbating the inflammation you’re already experiencing from Lyme. (See my post “The Lyme Diet” for information on inflammatory and anti-inflammatory foods). It helped me to switch to an anti-inflammatory diet, which I’ve been on for over a decade. What helped the most with my inflammation, though, was proper treatment with antibiotics and anti-inflammatory medication. If you are not already seeing a LLMD, I encourage you to find one who can address your systemic inflammation, check for co-infections, and help you consider dietary changes. (To find a good LLMD in your area, please click here).

Before sleep medication, can you describe your insomnia? Was it every night? For how long?

Once tick-borne illnesses crosses the blood-brain barrier, they can cause a host of neurological issues, including sleep disturbances. Before I was accurately diagnosed with and treated for Lyme disease, babesiosis, and ehrlichiosis, I had horrendous insomnia. At one point, I was literally awake for weeks. I tried everything: meditating, counting sheep, using lavender oil, taking over-the-counter sleep aids, but nothing worked. Despite my exhaustion, my brain would not turn off. I had word and song iteration—words and songs playing in my head like a mash-up, over and over again. It felt like my body was in park and my brain was in overdrive.

Some nights I did sleep, but it wasn’t restful. I experienced hallucinogenic nightmares that left me more tired when I woke up than when I went to sleep. Sleep disturbances went on for a couple years before I was accurately diagnosed, and persisted (with some improvements) for a few months during the start of treatment. These issues came back when I relapsed. The first step in getting them under control was to treat the infections that were causing it. I saw a sleep specialist who did neurofeedback, taught me good sleep hygiene, and figured out, through some trial-and-error, the best medication to help me sleep.

Writer

Jennifer Crystal

Opinions expressed by contributors are their own. Jennifer Crystal is a writer and educator in Boston. Her work has appeared in local and national publications including Harvard Health Publishing and The Boston Globe. As a GLA columnist for over six years, her work on GLA.org has received mention in publications such as The New Yorker, weatherchannel.com, CQ Researcher, and ProHealth.com. Jennifer is a patient advocate who has dealt with chronic illness, including Lyme and other tick-borne infections. Her memoir about her medical journey is forthcoming. Contact her via email below.

Email: lymewarriorjennifercrystal@gmail.com

______________________

**Comment**

This post took me back in time.

The crazy manifestations of this complex multi-faceted illness can not be overstated.  They are unbelievable.  This is one of the reasons main-stream medicine thinks we are all nuts.  I’m sure it appears that way when we frantically diatribe through our litany of bizarre symptoms.  It truly takes a special practitioner to quietly listen to patients, believing that there is a real, physiological cause behind it all.  To believe that thousands upon thousands of patients are saying similar things are all crazy is a lazy way out.

I’ve pulsed antibiotics successfully and taken them everyday successfully.

Pulsing is based upon the fact that Lyme disease has a 4-week cycle, where every 4 weeks patients experience a symptom flair. Burgdorfer found this in mice studies, and IGeneX found the same thing in urine antigen studies.Borrelia grow and are active, then become inactive.Four weeks later they activate.This has been shown recently in vitro. Think of Bb as a slow relapsing fever.This nuance is important because antibiotics only kill during the active phase.You need a minimum of a month to bracket a whole generation cycle. 

Slightly different than pulsing, is something called “cycling”, used when patients reach a plateau. You discontinue antibiotics until symptoms return.  Then, when symptoms return, go to full treatment until symptoms are gone again. Dr. Burrascano states that many patients become symptom free after 4 of these cycles.  He used this on himself as well with success.  Burrascano found 3 other physicians doing the exact same thing with patients. This approached worked for all of them despite the different geographical areas they were in.

But, like all things Lyme/MSIDS, this doesn’t work with every patient.  But – it’s still worth trying!

My LLMD states Lyme/MSIDS causes all sorts of rashes – everywhere on the body.  I had one that looked like ring-worm that was on my derrière.  It expanded outwardly until finally it disappeared.  I believe treatment resolved it.

Rashes-larger-blog-4

A reminder that the EM rash is diagnostic for Lyme.  If you have the EM rash, you have Lyme, but many never see or get the rash.  This graph beautifully demonstrates that getting the “classic” EM rash is highly variable.

Insomnia is a real pain.  

For more: