https://www.yahoo.com/lifestyle/daisy-kent-actually-makes-spoiler-

Daisy Kent Actually Makes It To [SPOILER] On Joey’s ‘Bachelor’ Season

Article Excerpts:

When she was 15, she woke up and realized she couldn’t hear when her dad had trouble waking her up. “He was shaking me, and I was like, ‘This is weird,’” she told CBS 8. “I looked at him, I couldn’t hear him, then sat up and realized something was wrong with my left ear.”

Daisy said she had “a lot of high-pitched ringing and then just progressively got worse, and I couldn’t understand speech very well.” She said the experience was “super isolating” and that she felt very alone at the time.

When she was 17, she was diagnosed with Meniere’s disease, a disorder of the inner ear. At 21, tests confirmed that she also had Lyme disease, which doctors think could have potentially caused her Meniere’s disease.

Daisy ended up experiencing seizures, hair loss, joint pain, and severe dizziness, according to a video she made for NEXA Cares.

Hearing aids didn’t work for Daisy, so she ended up getting a cochlear implant, which allows people with profound hearing loss to hear better, per CBS 8.

She actually documented her experience on TikTok and built up a big following.   (See link for article, videos and pictures)

________________

For more:

https://www.lymedisease.org/lyme-stealth-bombers/

Why Lyme spirochetes are like stealth bombers

By Lonnie Marcum
12/7/23

Borrelia burgdorferi, the bacteria that causes Lyme disease, can persist in animals and humans because it has evolved complex mechanisms to avoid the immune system.

In a 1996 interview with The Scientist magazine, Stephen Barthold, DVM, PhD, the researcher who developed the first mouse model of Lyme disease, described Borrelia burgdorferi’s ability to avoid immune detection as a form of cloaking. “It’s using some sort of stealth-bomber-type mechanism,” he said.

Since then, Professor Barthold has gone on to partner with many researchers in the pursuit of learning how B. burgdorferi causes chronic infection, including Monica Embers, PhD, from Tulane University.

Nicole Baumgarth, DVM, PhD, now the director of the Johns Hopkins Lyme and Tickborne Diseases Research and Education Institute, has years of experience collaborating with Barthold.

The latest research by Baumgarth, Barthold and others at University of California, Davis offers the science community one more clue as to how Borrelia is able to subvert the immune system leading to persistent infection in mice.

Their paper entitled, “Borrelia burgdorferi Infection–Induced Persistent IgM Secretion Controls Bacteremia, but Not Bacterial Dissemination or Tissue Burden,” has shed new light on how these pathogens persist in tissues, but present in very low numbers in the blood.

As Dr. Baumgarth tells me, “Blood is not the way Borrelia gets around the mice. Rather it migrates through tissues.”

These new findings may offer a possible explanation as to why disseminated Borrelia is both harder to treat, and so difficult to detect in blood samples.

Immune system basics

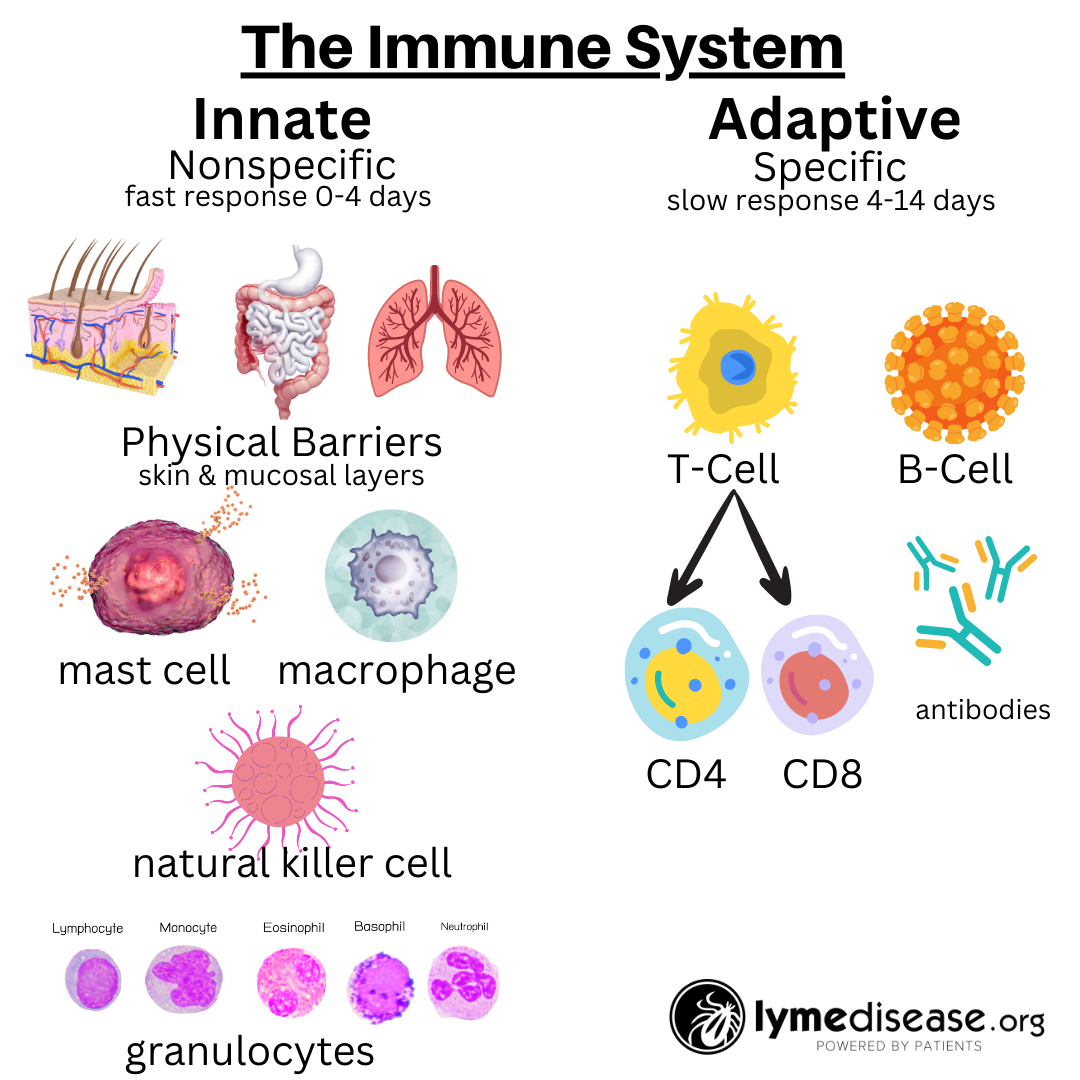
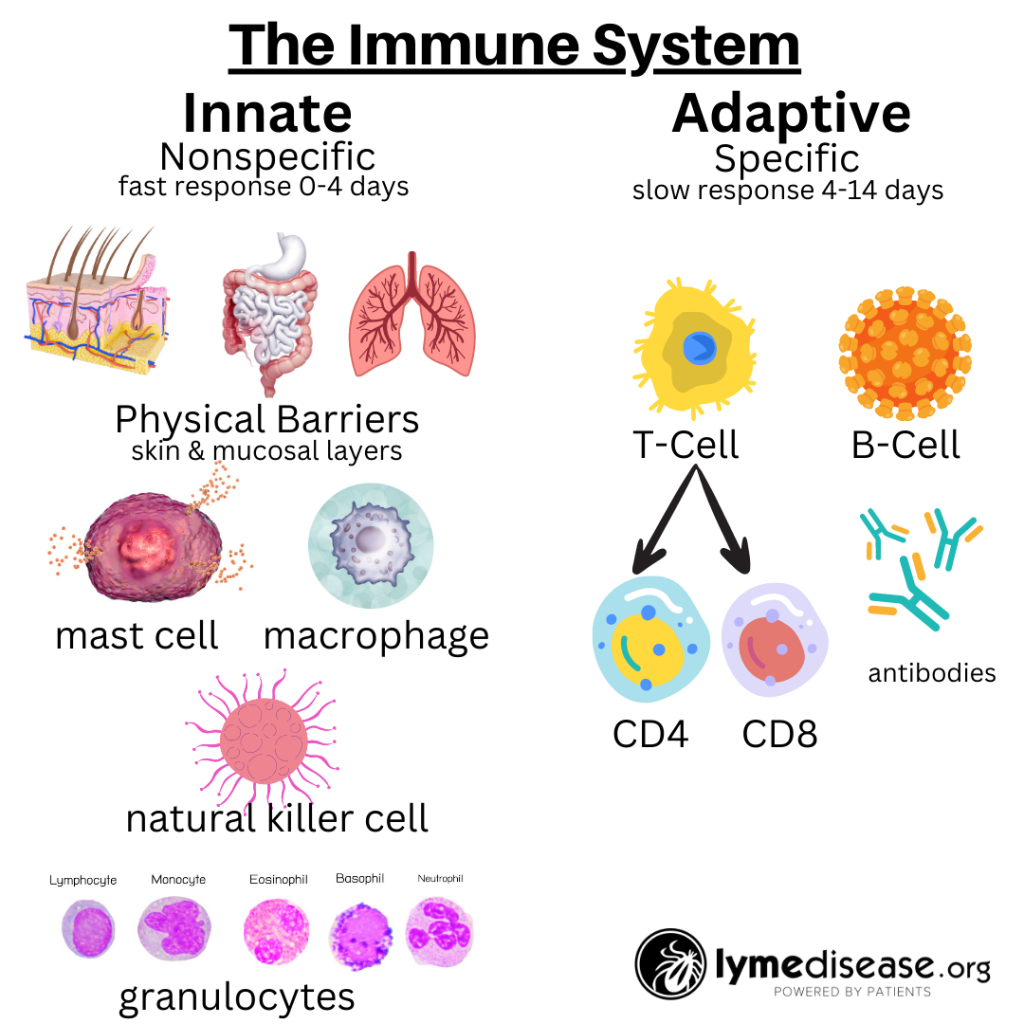
The immune system is roughly divided into two: the innate immune system and the adaptive immune system.

The innate immune system is our body’s first line of defense against pathogens and harmful substances. When working properly, it reacts immediately, but non-specifically, to all foreign invaders.

In contrast, the adaptive immune system is more targeted. It relies on prior exposure to learn and generate protective antibodies. The adaptive immune system remembers previous encounters and develops specific weapons (B-cells and T-cells) to fight each pathogen.
IgM vs IgG Antibodies

When the immune system detects any foreign substance, it produces antibodies which trigger the innate and later the adaptive immune system. IgM (immunoglobulin M) and IgG (immunoglobulin G) are two types of antibodies produced by the immune system.

IgM, the larger of these two immunoglobulins, is an early type of antibody to emerge in the development of an immune response. It acts as the initial defense against infections and is a strong activator of the complement system immune response that helps to clear pathogens.

The complement system consists of multiple proteins (C1 to C9) that summon phagocytes to the site of infection. Phagocytes (macrophages, neutrophils, lymphocytes) are components of the innate immune system that destroy pathogens. [For a crash course on the complement system watch this video.]

IgM is very effective in the blood stream. However, the size of IgM antibodies impedes their ability to penetrate all the tissues of the body. This limits IgM’s ability to send phagocytes into deeper tissues (eg. joints, heart, brain) where infection may be hiding.

IgG, a smaller, more penetrable antibody, is produced later in the immune response. IgG levels typically increase over a longer period of time, in some cases promoting the immune system to develop long-term immunity to future infection.

Study shows Borrelia impairs immune response

This new study shows how persistent Borrelia burgdorferi triggers a prolonged initial (IgM) immune response, and can impair a secondary (IgG) immune response.

This initial (IgM) response leads to fewer Borrelia burgdorferi (Bb) in the blood stream while the infection continues to spread throughout the body.

In addition, Borrelia’s prolonged IgM response in both humans and animals leads to a reduction in antibody-mediated clearance of the infection from deeper tissues.

The authors state, “Together the data demonstrated that IgG, but not IgM, is critical for the long-term control of B. burgdorferi tissue burden or disease induction. Despite that, Borrelia tissue dissemination in mice appeared very little affected by the rate of bacteremia, suggesting the B. burgdorferi main mode of dissemination in mice occurs by means other than via the blood.”

How IgM causes false-negatives

This research has shown that the standard definition of IgM as an acute response versus IgG as chronic response may be problematic in the classification of Lyme disease.

The Lyme disease Western Blot detects IgM and IgG responses to specific proteins found on Borrelia burgdorferi—for example: OspC (band 23-25), OspA (band 31), OspB (ban 34), BmpA protein (band 39), and flagellin protein (band 63-93).

In people with healthy immune systems, the Lyme disease IgM is normally detectable within a couple of weeks after infection, typically peaking around 4-6 weeks, then slowly declining over the next several months. The IgG begins around 4-6 weeks, peaking around 4-6 months, then slowly declining over the next several years.

Unfortunately, people who are immune-compromised, and/or fighting more than one infection (co-infection), may never develop a robust IgG response. The lack of the IgG response also prevents the immune system from finding and clearing bacteria embedded within deeper tissues, further impairing the healing process.

 In the experimental Bb mouse model, despite extensive antibiotic treatment, IgM production continued for months. This is consistent with human Lyme disease studies demonstrating continued IgM response as long as 10 years, even in patients treated with antibiotics.

As the authors state, this is “a remarkable observation, given the short half-life of IgM, considered to be <24 hours.” Meaning a prolonged IgM is likely coming from the immune system reacting to persistent Borrelia.

The continued production of IgM in the blood stream may explain why Borrelia is so difficult to detect in blood samples.

And because the CDC discredits the presence of IgM after four weeks, the prolonged IgM is likely contributing to the high rate of false-negative standard tests for Lyme disease.

Per the CDC website, “the IgM Western Blot test result is only meaningful during the first four weeks of illness. If you have been infected for longer than 4 to 6 weeks and the IgG Western Blot is still negative, it is highly likely that the IgM result is incorrect (e.g., a false positive). This does not mean that you are not ill, but it does suggest that the cause of illness is something other than the Lyme disease bacterium.”

We now have evidence that this is simply not true in all cases.

Difficult to Detect

In 2019, I attended a vector-borne disease conference at University of California, San Francisco. While there, *Dr. Charles Chiu explained how his powerful direct detection DNA sequencing system—able to detect thousands of pathogens—was just not finding enough Borrelia burgdorferi in the blood stream of humans to work effectively. (See my live tweets of Chiu’s presentation here.)

I was just baffled how such a powerful tool could not consistently detect Lyme disease in humans. Now, knowing that IgM remains in the blood stream longer, keeping the bacteria numbers low, may help us understand this phenomenon.

The fact that the prolonged IgM reduces the presence of Bb in the blood stream helps to explain why next-generation serologic tests using direct detection of DNA or proteins may not be able to detect Bb in patients who are suffering from chronic Lyme disease.

[*Since then Dr. Chiu has gone on partner with Johns Hopkins University where they have developed a next-generation gene sequencing technique, called RNA-seq, to map the immune response to infection. And most recently Chiu has partnered with Columbia University to open the first West Coast Center for the Clinical Trials Network.]

Immune Disruption

Also covered in Baumgarth’s paper is another strategy Bb has developed to evade the immune system. Within 24 hours after the tick bite, Bb quickly invades and is detectible in the lymph nodes nearest the site of infection.

On the surface, this seems counterintuitive, as the lymph nodes contain many life-saving immune cells.

However, once Bb is in the lymph nodes, the spirochetes induce a signal that disrupts the “germinal centers” within the lymph node architecture. Ultimately, this alters the adaptive immune response of the lymphatics and impairs the immune system by limiting memory B and T cell production.

In addition, new research from Johns Hopkins has shown that Bb impairs dendritic cells. Dendritic cells are a type of immune cell spread throughout the body. Once activated, dendritic cells migrate to the lymph nodes, where they activate the adaptive immune response. Bb’s alteration of the dendritic cells also impairs the formation of memory B and T cells.

When the immune system functions properly, IgM is produced and triggers an immune response that is good at controlling bacteremia in the blood stream. From there, an IgG response is required to control dissemination outside the blood stream.

IgM and IgG also help to trigger macrophages, a type of white blood cell that envelops and destroys pathogens. The lack of this secondary IgG response prevents macrophages from getting the message to enter and clear Bb infection from deeper tissues—which contributes to persistent infection outside the bloodstream.

Conclusion

In conclusion, the authors “propose that the continued production of immune IgM is a manifestation of B. burgdorferi mediated B cell response subversion and represents an immune evasion strategy of B. burgdorferi. It may promote B. burgdorferi dissemination out of the blood and into the skin, where it can remain until attachment and bite of a tick will induce it to migrate toward the site of the tick bite.”

I was always told Bb likes to leave the blood stream and hide in zones of the body where it is protected from the immune system. This new study shows how Bb actually uses our own immune system to aide in its ability to hide. This strategy allows Bb to survive and attain its ultimate goal— which is not to kill the host, but to get picked up by another tick and spread to another host.

Over 40 years since the discovery of the spirochete responsible for Lyme disease, we are inching closer to understanding how Borrelia burgdorferi suppresses and evades the immune system.

LymeSci is written by Lonnie Marcum, a physical therapist and mother of a daughter with Lyme. She served two terms on a subcommittee of the federal Tick-Borne Disease Working Group. Follow her on Twitter: @LonnieRhea  Email her at: lmarcum@lymedisease.org.

Reference

Hastey CJ, Olsen KJ, Elsner RA, Mundigl S, Tran GVV, Barthold SW, Baumgarth N. Borrelia burgdorferi Infection-Induced Persistent IgM Secretion Controls Bacteremia, but Not Bacterial Dissemination or Tissue Burden. J Immunol. 2023 Nov 15;211(10):1540-1549. doi: 10.4049/jimmunol.2300384. PMID: 37782044.

_______________

For more:

https://www.theepochtimes.com/health/study-finds-higher-incidence-of-covid-19-among-consistent-mask-wearers

Higher Incidence of COVID-19 Found Among Consistent Mask-Wearers: Study

Some mask wearers were found to have up to 40 percent higher incidence of infection, contradicting earlier studies and opposing the narrative of mask mandates.

11/27/2023
People who wore protective masks were found to be more likely to contract COVID-19 infections than those who didn’t, according to a recent Norwegian study.The peer-reviewed study, published in the journal Epidemiology and Infection on Nov. 13, analyzed mask use among 3,209 individuals from Norway. Researchers followed them for 17 days, and then asked the participants about their use of masks. The team found that there was a higher incidence of testing positive for COVID-19 among people who used masks more frequently.

Among individuals who “never or almost never” wore masks, 8.6 percent tested positive. That rose to 15 percent among participants who “sometimes” used masks, and to 15.1 percent among those who “almost always or always” wore them.

Adjusting for factors such as vaccination status, the study determined that individuals who sometimes or often wore masks had a 33 percent higher incidence of COVID-19, compared to those who never or almost never wore masks. This jumped to 40 percent among people who almost always or always wore them.  (See link for article)

_____________

**Comment**

Defying all logic and common sense, mask mandates are returning in many areas despite a Cochrane review analyzing 78 randomized controlled trails that found masks did not show “a clear reduction in respiratory viral infection with the use of medical/surgical masks.”

Florida Surgeon General Joseph Ladapo highlighted the issue of the ineffectiveness of masking policies:

“What do you call re-imposing mask policies that have been proven ineffective or restarting lockdowns that are known to cause harm? You don’t call it sanity,” he said in a post on X. “These terrible policies only work with your cooperation. How about refusing to participate.”

Even the highly bought out CNN is finally questioning masks.

https://gregreese.substack.com/p/italian-health-minister-gave-orders?  Video Here (Approx. 4 Min)

Italian Health Minister Gave Orders To Conceal Vaccination Deaths – Now Under Investigation For Murder

They knew the shots were killing people from the start and gave orders to conceal deaths
“The Rome Public Prosecutor’s Office is investigating Roberto Speranza, the Italian government’s Health Minister during the time of COVID measures.  He was responsible for the ‘vaccination’ campaign.
The investigations are the result of complaints related to the so-called AIFA emails from the Italian Medicines Agency.  The former director of AIFA, Nocola Magrini, is also under investigation.
The publication of these internal emails revealed that they had been aware of the dangers of the COVID ‘vaccination’ from the start.  The accusation is that the responsible minister and the head of the drug authority knowingly and deliberately exposed the unsuspecting Italian population to this risk.  Yes, they encouraged Italians to get ‘vaccinated.’  
Vaccination was even made mandatory for certain professional groups.  Consequently, many side effects, including fatal ones, came to light.  The investigations are for murder, serious bodily harm, and more, because Speranza and Magrini evidently gave instructions to the local health authorities to conceal the deaths and serious side effects that occurred immediately after the ‘vaccinations’ began, in order not to jeopardize the ‘vaccination’ campaign and to reassure the citizens about their safety.  
The responsible minister and the head of AIFA are now expected to answer for these actions, according to the complaints from the police unions and the financial police, as well as from the private organization Listen to Me, which represents 4,200 people damaged by ‘vaccines.’  In Italy, police officers and teachers were subjected to mandatory COVID ‘vaccination.’
Speranza bragged about the 89.41% ‘vaccination’ rate they achieved, and that just over 10% of the population remains unvaccinated.
He is now accused of ‘ideological falsehood’ and murder.

But that’s just the tip of the gene therapy iceberg.

  • Philippines Government Committee Votes in Favor to Launch  investigation into over  327,000 Unexplained Excess Deaths Between 2021 and 2022.  Source  Chairperson says he “was shocked” when referring to the number of unexplained excess deaths.
  • This video features Austrian Dr. Cornelia Tschanett stating that after 3,000-4,000 ‘vaccinations,’ 10% now have health problems.
  • Canadian health experts say 300% increase in ‘unspecified causes’ of death should be investigated.
As well as the mounting list of adverse reactions and deaths in VAERS.
  • Then there’s the New Zealand scandal where the government would rather raid the home and arrest the Health NZ whistleblower who leaked COVID shot mortality data, than check the veracity of the data.  Perhaps the bigger scandal is COVID Payola where “providers” got paid per shot given – which is also going on here in the U.S. 
    • The data shows the jabs killed an estimated 13 million people globally (1 death per 1,000 doses). Youtube censored it within minutes of posting. The data has been validated by two of the world’s most highly respected experts on data, risk, and epidemiology; but true to form, the mainstream media and the “authorities” are framing it as “unauthorized disclosure and misuse of data,” and use the now highly overused term ‘misinformation.’
    • British MP Penny Mordaunt states it’s all been debunked around the world. But Steve Kirsch presented data from 3 countries, including NZ, showing it has not been debunked at all.
    • Tellingly, there were 11,000 “vaccine” exemptions given in NZ reserved for the elites, politicians and media propagandists.  
    • Go here for “NZ’s COVID Vaccine Massacre Exposed”
    • And here for an update & dataset which can be used by every country to hold these criminals accountable.

For more:

http://  Approx. 13 Min

Shot Dead

Nov. 13, 2023

Documentary directors, Teryn Gregson and Ernest Ramierz discusses the tragic deaths of those who got the COVID gene therapy injections.

https://celiafarber.substack.com/p/behind-blue-eyes-the-paramedic-who?

Behind Blue Eyes: The Paramedic Who Lived To Tell What He Saw On The Frontlines Of America’s Covid Injection Carnage

“Now that we’re finally not being banned from talking, let’s see if I can finally get some stuff off my chest…”

Harry Fisher is a paramedic who works in rural areas, reservations, and suburbs, (all around the US) by his own description, and has been in the health field since 1997. He has not taken any Covid shots, and did not wear masks—his health is good, and he is creating short video testimonials about what he has seen on the battlefield.

The first clip of his that I saw, a few nights ago, told of nine women coming in in one shift, bleeding profusely from what he calls spontaneous abortions, a few months into the vaccine rollout/push for pregnant women.

“I had to get someone to come clean the chairs in the waiting room because the blood was so bad.”  Clip here.

Another clip describes the horrific pressures health care workers were under to get injected, even as their loved ones were dropping dead. The staff had to intubate their recently injected nurse manager.  (See link for article and video clips)

Fisher says he was banned for “terroristic activity,” when he first started to speak out about the strokes, clots, deaths, and more of what he saw after the COVID gene therapy injections.

But the real story, is the lack of answers about Happy Hypoxia.

Here, Fisher talks about happy or silent hypoxia (also seen in altitude sickness)and the fact that COVID can cause dangerously low oxygen levels but that patients don’t suffer breathlessness, and look and feel fine. Their oxygen levels are so low they should be fainting or experiencing organ damage, but they seemingly do fine until eventually they collapse.  Hypoxia, on the other hand, is accompanied with a high respiratory rate.  Since happy hypoxia doesn’t have this, it is called “the silent killer.”  When he first tried to talk about this on social media, he was banned.

Fisher says he began to study what would make a patient’s saturation levels so low yet allow them to function normally.  He found that certain parasites (avian haemosporidian parasites that cause malaria) allow birds to fly higher.

In birds, regenerative or haemolytic anaemia leads to increased erythropoiesis that is rapid production of immature red blood cells stimulated by hypoxia and yet showing normal Hct (and Hb or haemoglobin), despite a substantial parasite load (intensity). Source

It is interesting that researchers have found parasites and their eggs in the COVID gene therapy shots.
He also mentions that anti-malarial medicine (HCQ) for COVID works.

It must also be mentioned that while funding was suspended to the Wuhan Lab, a secret Chinese-linked Biotech lab was found in California which was home to 20 potentially infectious agents including malaria.  Malaria has also been found in the US for the 1st time in 20 years where they state it’s locally acquired.  Perhaps these cases were not caused by mosquitoes.

Please go here to learn how Spanish researchers point out that interstitial pneumonia & Acute Respiratory Distress Syndrome (ARDS) are not causing the death of COVID patients, which proves why ventilators have killed up to 70% of patients. These patients are really suffering from disseminated intravascular coagulation (DIC) – a medical term for blood clotting causing a lack of oxygen.  The mRNA shots have also caused thrombocytopenia and microscopic blood clots that will build over time and explain the frightening clots embalmers are finding in the deceased who were “vaccinated,” as well as all the cases of myocarditis.

Guess what else causes hypercoagulation/thrombosis/blood clotting?  Yep.  Malaria.

This is why things like HCQ, zinc, aspirin, ivermectin, and azithromycin work.

For more:

Despite the poor health and fragile medical system of many sub-Saharan African countries, they persisted with a statistically significantly low number of COVID-19 cases. This was attributed to many factors such as the young population age, the warm weather, the lack of proper diagnosis, previous infection with malaria, the use of antimalarial drugs, etc. Additionally, population genetics appears to play a significant role in shaping the COVID-19 dynamics. This is evident as recent genomic screening analyses of the angiotensin-converting enzyme 2 (ACE2) and malaria-associated-variants identified 6 candidate genes that might play a role in malaria and COVID-19 incidence and severity. Moreover, the clinical and pathological resemblances between the two diseases have made considerable confusion in the diagnosis and thereafter curb the disease in Africa. Therefore, possible similarities between the diseases in regards to the clinical, pathological, immunological, and genetical ascription were discussed.

The majority of studies were about COVID-19 co-infected with malaria, followed by strongyloidiasis, amoebiasis, chagas, filariasis, giardiasis, leishmaniasis, lophomoniasis, myiasis, and toxoplasmosis.

COVID-19 conditions and treatment regimens may cause some parasites re-emergence, relapse, or re-activation.