We patients must remember that Lyme is an inflammatory disease. Flare-ups often involve increased inflammation.
by Jennifer Crystal
Last week I had an incredibly busy schedule. I did research, had several long conversations over Zoom, taught a class, and wrote a lot. The work required a good amount of mental energy, or “spoons”. I also happened to have a physically busy week, running around doing errands and going to doctor’s appointments, as well as meeting friends for socially distanced walks.
But what Lyme patients need to do and what we want to do don’t always match up.
By Thursday evening, my brain felt as if it was filling with cotton, a pressure I remember well from my acute days with Lyme disease, ehrlichiosis, and babesiosis. This should have been my cue to stop and rest. What I really needed to do was darken the lights, put on some soft music, and relax. But what Lyme patients need to do and what we want to do don’t always match up. In this case, I wanted to relax by watching a favorite show, something I’d been looking forward to as a reward all week. And so I watched. Big mistake. Halfway through the program, my feet got very hot. They weren’t under a blanket. It was cool in the room. But my feet felt like they were on fire.
Burning extremities are a common manifestation of neurological Lyme disease. While my own infections are in remission, pushing myself physically and mentally can cause flare-ups. The sensory overload of the TV show was the proverbial straw that broke the camel’s back. My nervous system was inflamed, and needed a cool down, stat. What exactly causes nervous system inflammation in tick-borne illness?
As Richard I. Horowitz, MD explains in How Can I Get Better? An Action Plan for Treating Resistant Lyme & Chronic Disease, “Inflammation underlies the symptoms in many neurological diseases. In a study published in 2007 in Lancet Neurology, researchers reported that the neurological syndromes associated with Borrelia burgdorgferi are also associated with inflammation in the central nervous system, in particular amyloid metabolism. Amyloids are proteins that aggregate and change the structure of cells, damaging them.” He goes on to say, “Amyloid is just one of several neurotoxins: substances that can damage or kill off the brain’s neurons that are produced by inflammation and can alter the normal activity of the cells of the central nervous system…Neurotoxins and inflammation both can alter the normal activity of the nervous system.” [i]
For patients, this altered activity can manifest as the peripheral neuropathy (burning extremities, numbness, tingling) and “ brain fog” I experienced, as well as headaches, memory loss, confusion, anxiety, depression, sleep disturbances, and more. We patients must remember that Lyme is an inflammatory disease. Flare-ups often involve increased inflammation. That’s easy to remember when you’re in an acute stage and your entire body hurts or you’re getting systemic hives. For those of us who are doing well, we can easily forget how quickly inflammation can rev back up.
Last week was a sobering reminder for me. After watching my TV show, I had crazy dreams. When I woke up, I texted a friend, “I feel like I’ve been electrocuted.” To quiet my nervous system, I relied on tricks that have helped in the past: I went for an integrative manual therapy appointment, where my practitioner did some cranial sacral massage. I increased my consumption of anti-inflammatory foods. I stayed away from screens and even reading. That weekend, I wanted to go for a walk, but my body was too tired, so instead of pushing it as I had all week, I just stayed home. By Monday, I felt much better.
For those in acute stages of infection, increased inflammation may be a sign of needing additional, or different, antibiotics. Your Lyme Literate Medical Doctor (LLMD) may want to add an anti-inflammatory medication to your regimen. They may recommend certain supplements that can reduce inflammatory cytokines. Only you and your doctor can decide what treatment will work best for your specific case of inflammation, but everyone can benefit from rest, hydration, good sleep hygiene, and an anti-inflammatory diet. I’m glad to report that this past week was much better. My body and brain speak up when I’ve pushed them too far. Though I don’t always heed the messages quickly enough, I do heed them at all, and that’s made recovery from nervous system inflammation faster and better.
[i] Horowitz, Richard I., MD. How Can I Get Better? An Action Plan for Treating Resistant Lyme & Chronic Disease. New York: St. Martin’s Press, 2017 (183-4).
Opinions expressed by contributors are their own. Jennifer Crystal is a writer and educator in Boston. Her memoir about her medical journey is forthcoming. Contact her using her email.
Ms. Crystal wrote about getting the first COVID injection in March, and that she struggled with, “slight nausea and achiness. This feeling continued through the next morning. By about 10:00 a.m. on Tuesday, I felt like I had a mild flu: chills, achiness, headache, and fatigue. I did not run a fever.”
She also stated the symptoms prevented her from working the rest of the day.
If she received the 1st injection in March, that means the second shot, according to the CDC, would have been given 21, or 28 days or later – but not before.They also state:
Side effects after your second shot may be more intense than the ones you experienced after your first shot.
I wonder if she’s considering the fact this injection may be partially or fully to blame for her issues in April.
We’ve been falsely told these injections are “safe and effective,” despite the warnings of numerous doctors and researchers to the contrary. In previous animal studies utilizing this technology, EVERY SINGLE ANIMAL DIED.We also know people are still contracting COVID-19after receiving all the injections, clearly demonstrating they don’t stop you from getting it. They also don’t stop you from transmitting it to others – so getting the injections because you visit grandma doesn’t hold any water. A researcher has warned about the unsafe epitopes.
Food for thought.
And please remember the plethora of effective treatments being censored or banned:
The mainstream media spin is in full effect now with headlines declaring unvaccinated people are the cause of #Covid19 outbreaks among the fully vaccinated. It has to make you wonder, do they realize their attempts to scare people into getting the shot is only helping to prove it does not even prevent the infection?
World renown vaccine specialist, Geert Vanden Bossche, gave a groundbreaking interview risking his reputation and his career by bravely speaking out against administration of #Covid19 “vaccines”. In what may be one of the most important stories ever covered by The Highwire, the vaccine developer shared his extreme concerns about these vaccines in particular and why we may be on track to creating a global immunity catastrophe.
Bossche states mass vaccination drives viral immune escape.
In the countries whom have undertaken mass vaccination, (UK, Israel, USA), they will initially experience a drop in infectivity rates, but they will inevitably suffer from a steep incline in severe COVID cases in the weeks to come.
UPDATE: Bossche has been proven to be completely correct.
Nations participating in the “Zero COVID” movement with draconian edicts and mass vaccination campaigns have had explosions in COVID-19 cases across the board.
There are no longer any “success stories” involving nations using tyrannical means in an attempt to stop a virus. Source
Senator Ben Ray Luján informed the public on April 19, 2021 that he, along with his Minnesota colleague, Senator Amy Klobuchar, sent a letter to Twitter CEO Jack Dorsey and Facebook CEO Mark Zuckerberg urging them “to remove the accounts that have been identified by experts as responsible for producing the majority of this disinformation on social media platforms. A recent report from the Center for Countering Digital Hate (CCDH) identified a dozen specific content producers as the original sources of an estimated 65 percent of coronavirus disinformation online.”As Luján and Klobuchar called for Dorsey and Zuckerberg to remove the 12 individuals from their social media platforms, their justification for censorship of constitutional speech was the promotion of their own public policy preferences in their statement: “A crucial step to increase vaccine confidence is to address primary spreaders of this vaccine disinformation, including the twelve accounts — referred to as the “Disinformation Dozen” and are responsible for a majority of disinformation — in a swift and decisive manner.”
The Senators failed to note that the individuals targeted for censorship are highly respected professionals, researchers, and health freedom leaders in our country who are trusted by a large number of citizens for providing valuable sources of information often not available by other sources. The 12 trusted leaders are: Joseph Mercola, Robert F. Kennedy, Jr., Ty and Charlene Bollinger, Sherri Tenpenny, Rizza Islam, Rashid Buttar, Erin Elizabeth, Sayer Ji, Kelly Brogan, Christiane Northrup, Ben Tapper, and Kevin Jenkins.
The Senatorsare well aware that there are laws against fraud, and that truth is a defense to fraud. They use the terms “disinformation” and “misleading”. Yet they do not solicit an avenue where truth as a defense can be heard. They do not call for a Congressional hearing or public forum that would include a time for leaders to answer any questions they might have about the content of their work and messaging. They do not discuss the profound impact of Senators calling for censorship in the face of a constitutional issue of freedom of speech. Instead, they want to prohibit the conversation of truth as a defense and are calling for outright censorship.
The great strength of America is our Constitution, including our sacred Bill of Rights. The Bill of Rights includes the first 10 Amendments to the Constitution. The 1st Amendment protects free speech. Protecting freedom of speech and of the press is our powerful shield, essential in preventing abuse of power by any government.
“Congress shall make no law respecting an establishment of religion, or prohibiting the free exercise thereof; or abridging the freedom of speech, or of the press; or the right of the people peaceably to assemble, and to petition the government for a redress of grievances.” U.S. Const. Amend. 1.
Without freedom of speech, a single source of government-endorsed information (whether from legislators, government agencies, or government-endorsed corporations) could eliminate truth and cause the takeover of our country and the hearts and minds of its people. We must protect our First Amendment Freedom of Speech!!!
Tell your elected members of Congress to stop any requests for censorship and acknowledge that the 12 leaders listed above have First Amendment rights that deserve to be protected! Click here now.
12 state attorneys general demand Facebook, Twitter crack down on vaccine ‘misinformation’
Given ‘anti-vaxxers’ reliance on your platforms, you are uniquely positioned to prevent the spread of misinformation about coronavirus vaccines that poses a direct threat to the health and safety of millions of Americans in our states and that will prolong our road to recovery.’
Tue Apr 27, 2021
By Calvin Freiburger
April 27, 2021 (LifeSiteNews) — The attorneys general of twelve states have signed a joint letter to Facebook CEO Mark Zuckerberg and Twitter CEO Jack Dorsey, calling on the world’s top social networks to do more to suppress negative claims about COVID-19 vaccines.
“The people and groups spreading falsehoods and misleading Americans about the safety of coronavirus vaccines are threatening the health of our communities, slowing progress in getting our residents protected from the virus, and undermining economic recovery in our states,” declares the letter, spearheaded by Connecticut Attorney General William Tong and co-signed by his counterparts in Delaware, Iowa, Massachusetts, Michigan, Minnesota, New York, North Carolina, Oregon, Pennsylvania, Rhode Island, and Virginia.
Specifically, the attorneys general want Facebook and Twitter to “remove from all their platforms the accounts of prominent ‘anti-vaxxers’ who have repeatedly violated the companies’ terms of service”; “consistently apply misinformation labels and popups on Facebook pages and groups that discuss vaccines or COVID-19”; and to stop allowing so-called “anti-vaxxers” to “skirt its policy of removing misinformation that health experts have debunked, by failing to prevent them from using video and streaming tools like Facebook Live and sites like Bitchute, Rumble, and Brighteon to evade detection.” (See link for article)
Over the past year, I’ve been researching and writing as much as I can to help you take control of your health, as fearmongering media and corrupt politicians have destroyed lives and livelihoods to establish global control of the world’s population, using the COVID-19 pandemic as their justification
Through it all, I have refused to succumb to these relentless attacks. I have been confident and willing to defend myself in the court of law
Unfortunately, threats have now become very personal and have intensified to the point I can no longer preserve much of the information and research I’ve provided to you thus far. So, effective immediately, much of the information on my website will be permanently removed (See link for article)
________________________
**Comment**
Hopefully it’s abundantly clear how dangerous censorship is. Experienced and knowledgable professionals in the health field are have been banned and censored at an unprecedented rate. These are people with training, education, and experience – but it doesn’t matter because they are defying the accepted narrative. Science should be subject to healthy debate and opinions. This is how Science evolves. It’s rarely “settled.” Public ‘authorities’ insist that the Science on Lyme/MSIDS is settled, but anyone who takes more than a minute to dig into this discovers what research has been done has been tightly controlled, flawed, biased, and extremely damaging to sick patients.
Lastly, people should be free to share their personal experiences with others without being censored.
If it wasn’t for the personal experiences of others, many Lyme/MSIDS patients wouldn’t be here today. It’s this personal, one on one, communication that can often save lives.
In addition to this flip-flopping guidance, these experimental, fast-tracked injections are only available to the public due to EUA authorization (Emergency use authorization), which means clinical trials were performed in less than a year when historically it takes a minimum of 2-4 years. To state they were rushed would be an understatement. And the reports of harm and death continue to pour in. Those getting injected are effectively test subjects in an ongoing clinical trial.
CDC Rewrites COVID Testing Measures for Post-Vaccine Breakthrough Infections
Summary by Cindy Olmstead, April 29, 2021
In a move to investigate COVID-19 breakthrough infections among persons vaccinated against the virus, the U.S. Centers for Disease Control and Prevention has announced new and revised testing measures just for vaccinated individuals.
Previously, the CDC had recommended something called a PCR threshold of 40, meaning that the test would be considered positive even if it took 40 testing cycles to find a tiny shed of virus. During the height of the pandemic, critics said that threshold was too high, as it was marking people positive when they actually had only genetic fragments or leftovers from an infection that posed no risk of contagion.
The New York Times likened those tests as “akin to finding a hair in a room long after a person has left.”
Criticisms aside, the high threshold testing procedure stayed in place — until now.
With more and more breakthrough cases being reported, the CDC quietly changed its PCR threshold for testing breakthrough infections to 28 or less.
This means that far fewer cases will be identified as positive than were they to stay at the 40 threshold.
“The entire epidemic would have looked very different if [28] had been used [for a regular infection],” Alex Berensen tweeted.
On its website, the CDC noted that it also would not test every breakthrough case, but instead would “focus on identifying and investigating only vaccine breakthrough infections that result in hospitalization or death” — a move that will also lower the total case counts among vaccinated individuals.
Regarding the PCR testing the whole house of cards is built upon, please see the following quote from its creator:
This informative article also points out the complete hypocrisy when it comes to counting COVID deaths vs vaccine-related deaths. The CDC accepts ALL suspected cases and records them as COVID deaths, even false positives cases and cases with serious underlying health conditions.The corrupt CDC also conveniently stopped counting seasonal flu and funneled those numbers to increase COVID deaths as well.
Dr. Henry Ealy and his team started looking at CDC data on COVID-19 cases and fatalities in mid-March 2020, quickly realizing the agency was vastly exaggerating fatalities
Over-reporting of fatalities was enabledby a March 2020 change in how cause of death is reported on death certificates. Rather than listing COVID-19 as a contributing cause in cases where people died from other underlying conditions, it was to be listed as the primary cause
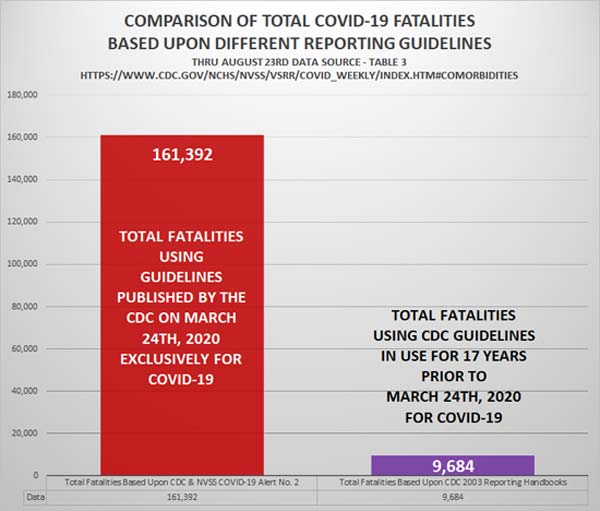
As of August 23, 2020, the CDC reported 161,392 fatalities caused by COVID-19. Had the long-standing, original guidelines for death reporting been used, there would have only been 9,684 total fatalities due to COVID-19
The CDC violated federal law, as the Paperwork Reduction Act requires data collection and publication to be overseen by the Office of Management and Budget. Proposed changes must be published in the Federal Register and be open to public comment. None of these transparency rules were followed
We don’t yet know who was responsible for altering the reporting rules in violation of federal law. To identify the culprits, formal grand jury investigation petitions have been sent to all U.S. attorneys and the U.S. Department of Justice,requesting a thorough, independent and transparent investigation; a direct public effort to gather signatures also commenced on the one-year anniversary of the CDC reporting change
Dr. Mercola Interviews the Experts
This article is part of a weekly series in which Dr. Mercola interviews various experts on a variety of health issues. To see more expert interviews, click here.
In this interview, Dr. Henry Ealy, ND, BCHN, better known as Dr. Henele, a certified holistic nutritionist and founder/executive community director of the Energetic Health Institute,1reviews how U.S. federal regulatory agencies have manipulated COVID-19 statistics to control the pandemic narrative.
He earned his doctorate in naturopathic medicine from SCNM. After graduating from UCLA with a bachelor of science in mechanical engineering, he worked for a major aerospace company as a primary database developer for the International Space Station program.
He holds over 20 years of teaching and clinical experience and was the first naturopathic doctor to regularly teach at a major university in the U.S., when he headed up a program at Arizona State University on bioanxiety management.
As he points out, he’s an avid data collector. In October 2020, Henele and a team of other investigators published a paper2 in Science, Public Health Policy and the Law, titled, “COVID-19 Data Collection, Comorbidity & Federal Law: A Historical Retrospective,” which details how the U.S. Centers for Disease Control and Prevention has enabled the corruption of case- and fatality-reporting data in violation of federal law.
Accuracy of Data Is Paramount for Public Health Policies
The team started looking at CDC data on COVID-19 cases and fatalities in mid-March 2020. He explains:
“What I started doing on March 12 was going through all the data we could find from the Italian Ministry of Health and South Korea. We couldn’t validate any of the data coming out of China. There was just no independent way to do it. What we were seeing out of Italy and South Korea was that we were going to be concerned about people who are over 60, over 70 years of age with preexisting conditions.
That was the main thing coming out of that data. So, we were expecting the same kind of trends here … I started tracking the data on a daily basis from each state health department, and then making sure that what the CDC was reporting was matching up.
What we started to see, very early on, were some significant anomalies between what the states were reporting and what the CDC was saying. It was concerning, because the variance was growing with each day. We have an old saying: ‘Garbage in equals garbage out.’ And that was the concern, because we knew public health policies are going to be based upon the data, so accuracy is of paramount importance.
Then we started delving in a little deeper into how the CDC was supposedly collecting their data. That’s where we saw the National Vital Statistics Systems (NVSS) March 24 guidelines, which were very concerning, and we saw the CDC adopt the Council for State and Territorial Epidemiologists paper on April 14.
What was incredibly concerning about this was that it was all done without any federal oversight, and it was all done without any public comment, especially scientific comment. That became increasingly problematic. We started to see discrepancies in the state of New York alone, in the thousands of fatalities.”
Special Rules for COVID-19 Fatalities Were Implemented
Importantly, in March 2020, there was a significant change made to the definition of what a COVID-19 fatality was. As explained by Henele, there’s a handbook on death reporting, which has been in use since 2003. There are two key sections on a death certificate. In the first part, the cause of death is detailed. In the second part, contributing factors are listed.
Contributing factors are not necessarily statistically recorded. It’s the first part, the actual cause of death, that is most important for statistical accounting.March 24, 2020, the NVSS updated its guidelines on how to report and track COVID-19-related deaths.
“They were saying that COVID-19 should be listed in Part 1 for statistical tracking, but [only] in cases where it is proven to have caused death, or was assumed to have caused death,” Henele explains.
“What was really concerning about this document was that it specifically stated that any preexisting conditions should be moved from Part 1, where it has been put for 17 years, into Part 2.
So, it was basically taking this and saying, ‘We’re going to create exclusive rules for COVID-19 and we’re going to do a 180 for this single disease …’ The big problem with that is that now you remove the ability for a medical examiner, a coroner, a physician, to interpret [the cause of death] based upon the collective health history of that patient …
You remove their expertise, and you say, ‘You have to count this as COVID-19.’ That takes on an added measure when you incentivize it financially, and that’s what we saw with some of the Medicare and Medicaid payouts …”
Who’s Responsible?
Who has the authority to do this? The answer is “no one.” A federal agency has the ability to propose a data change, at which time it would be registered in the Federal Register. At that point, federal oversight by the Office of Management and Budget kicks in, and the proposed change is opened up for public comment.
Since they did not register the proposed change, there was no oversight and no possibility for the public to comment on the change. Basically, what happened is that these changes were simply implemented without following any of the prescribed rules. “They acted unilaterally, and that’s not how [it] is supposed to work,” Henele says.
As to who took it upon themselves to alter the reporting rules, we don’t know. To identify the culprits, Henele and his team have sent out formal grand jury investigation petitions to every U.S. attorney and the U.S. Department of Justice (DOJ), requesting a thorough, independent and transparent investigation.
“We did it at both state and federal levels. We have sent physical copies to every U.S. attorney and their aides. We sent out over 247 mailings in October [2020],” Henele explains. “We sent out an additional 20 to 30 to various people at the Department of Justice …
They would have the ability to call a grand jury, and that grand jury would have the ability to subpoena all those records to determine who were at fault … All we need is one U.S. attorney. All we need is one person at the Department of Justice to take up the cause.”
Dramatic Implications
The consequences of that change in the definition of the cause of death where COVID-19 is involved have been dramatic. For the full implications, I recommend reading through Henele’s peer-reviewed paper, “COVID-19: CDC Violates Federal Law to Enable Corruption of Fatality-Reporting Data.”3
“We’ve accumulated about 10,000 hours of collective team research into this [paper]. It’s been reviewed by nine attorneys and a judge for accuracy. It’s gone through the peer-review process before being published. We feel it’s tight.
On page 20 of the paper, we have a big graphic showing what the estimated actual fatality count should have been as of August 23, 2020. What was reported on August 23 was 161,392 fatalities caused by COVID-19 …
Had we used the 2003 guidelines, our estimates are that we would have roughly 9,684 total fatalities due to COVID-19. That’s a significant difference. That’s a difference on the scale of as much as 96%. The range that we calculated was 88.9% to 96% inflation.“
Indeed, this matches up with an admission by the CDC in late August 2020, at which time they admitted that only 6% of the total death count had COVID-19 listed as the sole cause of death. The remaining 94% had had an average of 2.6 comorbidities or preexisting health conditions that contributed to their deaths.4
“For absolute 100% accuracy, we’d have to do something like what we were just alerted to by a whistleblower in Florida, where they’ve actually gone in and reexamined every single death certificate and the medical records with them. What they found was that roughly 80% of the fatalities were wrongfully classified as COVID-19 fatalities,” Henele says.
Science Foundations Have Been Violated
Mainstream media have justified pandemic measures “based on the science,” yet the very foundation of science has been violated. The ramifications are enormous, from the destruction of local economies and skyrocketing suicide rates to people being forced to die alone, their family members being barred from being at their bedside during their last moments.
“I lost my mother in in 2002,” Henele says. “The grace of it all was that we were able to get her out of the hospital and fulfill her last request, which was to pass away in her bed with family around her. I grieve for every single person who’s lost someone [during this pandemic] who was not able to be there.
Americans should not have to die alone because we’re worried about some virus that they’re telling us is a problem, when the data, even the data that we know to be inflated and fraudulent, still doesn’t suggest the virility that they want us to believe.”
COVID-19 Timeline
In their paper, Henele and his team detail a timeline of the COVID-19 pandemic and federal laws that impact data handling. Here’s a summary:
In 1946, certain administrative procedures were implemented. The Administrative Procedures Act requires federal agents and agencies to follow certain rules to get things done. These rules are to ensure transparency in government.
“If you’re a federal agency, you have an obligation to the people of this country to make sure that the data you’re publishing is not only accurate, but that it is transparent,”Henele explains.
In 1980, the Paperwork Reduction Act was written into law. In 1995, the Act was amended, designating the Office of Management and Budget (OMB) as the oversight body for all federal agencies’ data.
In October 2002, the Information Quality Act was implemented, which doubles down even further on the accuracy and integrity and data gathering. This act requires federal agencies to meet explicit criteria in order for their data to be published and analyzed.
In 2005, the Virology Journal published research demonstrating that hydroxychloroquine has strong antiviral effects against SARS-CoV (the virus responsible for SARS) primate cells. This finding was hailed by Dr. Anthony Fauci, Henele notes. In other words, 15 years ago, Fauci admitted that hydroxychloroquine works against coronaviruses. This is public record.
This fraudulent research was then used to discourage and in some cases block the use of hydroxychloroquine worldwide. As noted by Henele, “It’s not science. We’re in this very weird faith-based model of science, which isn’t science at that point.”
In 2014, Fauci authorized $3.7 million to the Wuhan Institute of Virology (WIV). In 2019, WIV received another $3.7 million. In both instances, this funding was for gain-of-function research on bat coronaviruses.
October 18, 2019, Johns Hopkins Center for Health Security hosted Event 201, in conjunction with the Bill & Melinda Gates Foundation, the World Economic Forum and a few other financial partners. November 17, 2019, China recorded the first known case of COVID-19.
“Now, they could be completely unrelated,” Henele says, “but for us, it’s a very incredible coincidence that you run a simulation a month before a pandemic breaks out. It’s a little tough for me to digest as just a coincidence.”
January 29, 2020, the White House installed a coronavirus task force, which included Fauci and then-CDC director Dr. Robert Redfield, as well as Derek Kan, then-deputy director of the OMB.
“I found this to be a little interesting,” Henele says. “Why would you need an OMB person on a coronavirus task force?”
March 9, 2020, the CDC alerted Americans over 60 with preexisting conditions that they might be in for a long lockdown out of safety concerns.
March 24, the CDC changed how COVID-19 is recorded on death certificates, de-emphasizing preexisting conditions and comorbidities, and basically calling all deaths in which the patient had a positive SARS-CoV-2 test a COVID-19 death.
“We have, legitimately on record, people who’ve died in a motorcycle accident listed as a COVID-19 death. These are not fictitious things that we’ve made up. Rhode Island had over 80% of their fatalities at one point in either assisted living centers or hospice care. Why are we testing people in hospice care and life care? That’s another interesting question,” Henele says.
April 14, 2020, the CDC adopted a position paper from a nonprofit, the Council for State and Territorial Epidemiologists, which identifies every single methodology for how to report a probable COVID-19 case, a confirmed COVID-19 case, an epidemiologically-linked or contact-traced COVID case.
“What’s so incredible about this is the standard of proof for a probable case is literally one cough. That’s all a physician needs, [according to] this document, to validate that that person is a probable COVID case,” Henele says.
“And it gets worse. On Page 6 of that document, Section 7B, it explicitly states that they are not going to define a methodology to ensure that the same person cannot be counted multiple times. So, what we end up with is a revolving door.
Now, in terms of new cases, the same person can be counted over and over and over again, without being tested, without having any symptoms. All they need to do is be within 6 feet of someone [who has been deemed positive for SARS-CoV-2] and then a contact tracer can say, ‘OK, well, that person is [also] positive.’
When we looked at data from last week, roughly 27% of the people who were said to be positive actually had a positive test. That means 73% were just told ‘Yeah, we think you got it.’ And that’s good enough, because we’re in this faith-based model of science, instead of a verifiable framework for science, which we’re supposed to be based on.
That person then cannot go back to work until they show a negative test. Well, let’s say they get tested 13 times. Guess what happens? That’s 13 new cases, when it really should only be one.
So, there are major flaws, and the issue that I think a lot of scientists like myself … have with this document and its adoption is that there was no oversight, and there was no public comment period to question some of the obvious flaws in what they were defining as data collection — let alone to ask a very simple question: ‘You’re the CDC, you’re supposed to be the pinnacle of this.
Why do you need to outsource rules and criteria for data collection to a nonprofit entity?’ That doesn’t make much sense to me.”
Transparency Rules Have Been Grossly Violated
So, what exactly is the connection between the Paperwork Reduction Act and the COVID-19 fatality data? Why is it so important?
“Well, the Paperwork Reduction Act is really about establishing oversight,” Henele explains. “It established the Office of Management and Budget, the OMB, which is under the executive branch. It established them as the key agency for oversight of all data in the entire federal government.
So, when you start seeing IHME [Institute for Health Metrics and Evaluation] out of the University of Washington — which is heavily funded by the Bill & Melinda Gates Foundation, to the tune of $384 million in two installments — when you see their data being used at federal levels, you go and look at the Federal Register and you say, ‘OK, where is the 30 to 60 days that we were supposed to have to comment on the use of that data?’
Public comment is part of the Paperwork Reduction Act. That’s what it’s all about. What we saw instead was just, ‘Hey, this is what the IHME is putting out there. We’re going to go with it.’ Well, you can’t do that if you’re a federal agency … IHME is … technically an independent organization, but they don’t have any governmental designation.
They’re not a 501(c)(3), they’re not a 501(c)(4), they’re not a 501(c)(6). They’re just this amorphous nongovernmental organization within our country, and it’s kind of concerning. We’re doing more research on that, but it’s very, very concerning because they don’t have anybody to account to.“
Test-Based Strategy Has Been an Egregious Fraud
In addition to the manipulation of fatality statistics, the statistics of “cases” were also manipulated. Traditionally, a “case” is a patient who is symptomatic; someone who is actually ill. When it comes to COVID-19, however, a “case” suddenly became anyone who tested positive for SARS-CoV-2 using a PCR test, or worse, assumed positive based on proximity to someone who tested positive.
“The CDC specifically enacted what’s called a test-based strategy, which we’ve never done before in medicine for anything. What that test-based strategy means is if you test positive, you got [COVID-19]. But what they didn’t do for the PCR testing was they didn’t identify the agreed upon number of cycles across all states across all labs that are testing.
What most people don’t know is that the closer you get to zero in terms of cycle times, the more likely that the result is going to be negative. The closer you get to 60, the more likely that it’s going to be positive.
Well, we’ve never seen a document coming out of the FDA, coming out of the CDC, coming out of any of the state health departments, that says, ‘We need all labs to be at this specific cycle [threshold]. And if a person is not deemed positive with that number of cycles, then they are not positive.’ So, there’s just flaw after flaw after flaw.”
Data Manipulation Created COVID-19 Pandemic
Most labs used cycle thresholds above 40 — as recommended by the CDC and the World Health Organization — which exponentially increased the likelihood of a positive test,even among completely healthy and noninfectious individuals. The only justification for all of this is that it was done to perpetuate the narrative that we were in a raging pandemic, which was then used to justify the unprecedented destruction of personal freedom and the economy.
“The thing I have to give the folks that have been involved in this credit for is the incredible number of sleights of hands,” Henele says. “It’s a little bit here, a little bit here, a little bit here, a little bit here.
And when that happens, it leads to something that is very dangerous scientifically, and very dangerous for public health policy, which is control of data — the ability to manipulate data … and if you can control the data, you get to control the narrative …
If we’re not going to have an absolute, transparent and verifiable data collection process that is based upon accuracy and integrity of that data, then you can turn that [pandemic emergency] dial up and down at your whim. My hope is that the objective scientist within all of us understands that this is bigger than politics. This is beyond it. This is a severely broken system that we have to fix, and we better do it.”
As discussed in many other articles, it appears the COVID-19 pandemic has in fact been a preplanned justification for the implementation of a global technocrat-led control system, which includes a brand-new financial system to replace the central bank-manufactured fiat economy that is now at the end of its functional life. Fiat currency is manufactured through the creation of debt with interest attached, and the whole world is now so laden with debt it can never be repaid.
If people understood how the central banks of the world have pulled the wool over our eyes, we would simply demand an end to the central banks. Currency ought to be created and managed nationally.
The central banks, of course, do not want this reality to become common knowledge, because then they will no longer be able to manipulate all the countries of the world, so they need the economic breakdown to appear natural. For that, they need a global catastrophe, such as a major war, or a fearsome pandemic necessitating the shutdown of economies.
Through this willful manipulation of case- and fatality statistics, the CDC has been complicit in willful misconduct by generating needless fear that has then been used against you to rob you of your personal freedoms and liberties and help usher in this massive transfer of wealth and global tyranny. As noted by Henele:
“People are going to be complicit in their own slavery. People are complicit in putting digital shackles around themselves and really restricting their civil liberties.”
Hopefully, people will begin to understand how pandemic statistics have been, and still are, manipulated to control the narrative and generate unjustified fear for no other reason than to get you to comply with tyrannical measures designed to enslave you, not just temporarily but permanently.
“I’m looking forward to the day when we look back on this, and go, ‘Oh, we almost fell for one, but we woke up in time and we figured this out. And now we have a good balance of technology, but technology that doesn’t have the right to censor us, technology that doesn’t have the right to control us; we have figured out that having too much control in the hands of too few is not a good recipe for us as a species on this planet.’
We know it doesn’t pass the smell test, so it’s important to get informed and educated and it’s papers like this — and this isn’t the only one out there — that have done the homework. If we’re going to trust someone, it’s important to me that we trust people who’ve done the homework and have no vested interest in the outcome.
My team is a team of volunteers. We all do this in our spare time.We’re not making any money. We’re not going to seek to make any money off of this. We’re doing this because we believe in this country. We love this country and we love the people of this country. When I see people suffering, I have to help. I got to get in and help.
So, if you are an American that wants to help, we are setting up resources for you to be able to get engaged and help us push this forward, maybe grease some of these wheels of justice, so we can get an independent grand jury investigation.”
For additional information, or if you want to help, you can email Henele and his team at COVIDResearchTeam@protonmail.com. You can also use your voice and actions to support an investigation into the CDC’s actions.
Two Easy Ways You Can Take Action
Add your signature to this petition to help mount public pressure to convene a formal grand jury to investigate allegations of willful misconduct by federal agencies during COVID-19 through Stand For Health Freedom, a nonprofit advocacy organization that Henele and his team have collaborated with
Send a predrafted, customizable letter through Stand For Health Freedomurging key members of Congress to thoroughly investigate alleged violations of federal law by the CDC that compromised COVID-19 data
__________________________
**Comment**
Excellent, excellent paper which delineates the scam. And, it is a scam.
Notice how the CDC uses testing for COVID in an opposite manner as for Lyme/MSIDS. With tick-borne illness they have rigged testing which purposelytook out the most specific band for Lyme, and force patients to meet an incredibly high, yet completely arbitrary testing standard which nearly nobody meets – despite having every symptom in the book!
Similarly with COVID-19, they’ve used these tests to control the narrative, educating doctors that patients must get a positive test to be infected with Lyme/MSIDS and if they don’t – well, they just aren’t infected. Worse yet, many doctors tell patients they have a “false” positive when they do manage to miraculously test positive!
It’s a damned if you do, damned if you don’t scenario we’ve been in for over 40 years, which continues unabated.
And then there’s the issue that most patients are infected with far more than Lyme disease. This fact isn’t even on the radar of most doctors and testing for these infections is as bad if not worse than Lyme disease.
They also want everyone to take their controversial Lyme (and COVID) injections which would only work if Lyme disease does not cause chronic illness – hence the continual denial of persistent infection.
COVID-19 vaccine manufacturers have been exempted from legal liability for vaccine-induced harm. It is therefore in the interests of all those authorising, enforcing and administering COVID-19 vaccinations to understand the evidence regarding the risks and benefits of these vaccines, since liability for harm will fall on them.
In short, the available evidence and science indicate that COVID-19 vaccines are unnecessary, ineffective and unsafe.
Necessity: Immunocompetent individuals are protected against SARS-CoV-2 by cellular immunity. Vaccinating low-risk groups is therefore unnecessary. For immunocompromised individuals who do fall ill with COVID-19 there is a range of medical treatments that have been proven safe and effective. Vaccinating the vulnerable is therefore equally unnecessary. Both immunocompetent and vulnerable groups are better protected against variants of SARS-CoV-2 by naturally acquired immunity and by medication than by vaccination.
Efficacy: Covid-19 vaccines lack a viable mechanism of action against SARS-CoV-2 infection of the airways. Induction of antibodies cannot prevent infection by an agent such as SARS-CoV-2 that invades through the respiratory tract. Moreover, none of the vaccine trials have provided any evidence that vaccination prevents transmission of the infection by vaccinated individuals; urging vaccination to “protect others” therefore has no basis in fact.
Safety: The vaccines are dangerous to both healthy individuals and those with pre-existing chronic disease, for reasons such as the following:
risk of lethal and non-lethal disruptions of blood clotting including bleeding disorders,
thrombosis in the brain
stroke and heart attack
autoimmune
allergic reactions
antibody-dependent enhancement of disease
vaccine impurities due to rushed manufacturing and unregulated production standards
The risk-benefit calculus is therefore clear: the experimental vaccines are needless, ineffective and dangerous. Actors authorising, coercing or administering experimental COVID-19 vaccination are exposing populations and patients to serious, unnecessary, and unjustified medical risks.
1. The vaccines are unnecessary
Multiple lines of research indicate that immunocompetent people display “robust” and lasting cellular (T cell) immunity to SARS-CoV viruses [1], including SARS-CoV-2 and its variants [2]. T cell protection stems not only from exposure to SARS-CoV-2 itself, but from cross-reactive immunity following previous exposure to common cold and SARS coronaviruses [1,3–10]. Such immunity was detectable after infections up to 17 years prior [1,3]. Therefore, immunocompetent people do not need vaccination against SARS-CoV-2.
Natural T-Cell immunity provides stronger and more comprehensive protection against all SARS-CoV-2 strains than vaccines, because naturally primed immunity recognises multiple virus epitopes and costimulatory signals, not merely a single (spike) protein. Thus, immunocompetent people are better protected against SARS-CoV-2 and any variants that may arise by their own immunity than by the current crop of vaccines.
The vaccines have been touted as a means to prevent asymptomatic infection [11], and by extension “asymptomatic transmission.” However, “asymptomatic transmission” is an artefact of invalid and unreliable PCR test procedures and interpretations, leading to high false-positive rates [12–15]. Evidence indicates that PCR-positive, asymptomatic people are healthy false-positives, not carriers. A comprehensive study of 9,899,828 people in China found that asymptomatic individuals testing positive for COVID-19 never infected others [16]. In contrast, the papers cited by the Centre for Disease Control [17,18] to justify claims of asymptomatic transmission are based on hypothetical models, not empirical studies; they present assumptions and estimates rather than evidence. Preventing asymptomatic infection is not a viable rationale for promoting vaccination of the general population.
In most countries, most people now have immunity to SARS-CoV-2 [19]. Depending on their degree of previously acquired cross-immunity, they will have had no symptoms, mild and uncharacteristic symptoms, or more severe symptoms, possibly including anosmia (loss of sense of smell) or other somewhat characteristic signs of the COVID-19 disease. Regardless of disease severity, they will now have sufficient immunity to be protected from severe disease in the event of renewed exposure. This majority of the population will not benefit at all from being vaccinated.
Population survival of COVID-19 exceeds 99.8% globally [20–22]. In countries that have been intensely infected over several months, less than 0.2% of the population have died and had their deaths classified as ‘with covid19’. COVID-19 is also typically a mild to moderately severe illness. Therefore, the overwhelming majority of people are not at risk from COVID-19 and do not require vaccination for their own protection.
In those susceptible to severe infection, Covid-19 is a treatable illness. A convergence of evidence indicates that early treatment with existing drugs reduces hospitalisation and mortality by ~85% and 75%, respectively [23–27]. These drugs include many tried and true antiinflammatory, antiviral, and anticoagulant medications, as well as monoclonal antibodies, zinc, and vitamins C and D. Industry and government decisions to sideline such proven treatments through selective research support [24], regulatory bias, and even outright sanctions against doctors daring to use such treatments on their own initiative, have been out of step with existing laws, standard medical practice, and research; the legal requirement to consider real world evidence has fallen by the wayside [28]. The systematic denial and denigration of these effective therapies has underpinned the spurious justification for the emergency use authorisation of the vaccines, which requires that “no standard acceptable treatment is available” [29]. Plainly stated, vaccines are not necessary to prevent severe disease.
2. The vaccines lack efficacy
At a mechanistic level, the concept of immunity to COVID-19 via antibody induction, as per COVID-19 vaccination, is medical nonsense. Airborne viruses such as SARS-CoV-2 enter the body via the airways and lungs, where antibody concentrations are too low to prevent infection. Vaccine-induced antibodies primarily circulate in the bloodstream, while concentrations on the mucous membranes of lungs and airways is low. Given that COVID-19 primarily spreads and causes disease by infecting these mucous membranes, vaccines miss the immunological mark. The documents submitted by the vaccine manufacturers to the various regulatory bodies contain no evidence that vaccination prevents airway infection, which would be crucial for breaking the chain of transmission. Thus, vaccines are immunologically inappropriate for COVID-19.
Medium to long-term vaccine efficacy is unknown. Phase 3, medium term, 24-month trials will not be complete until 2023: There is no medium-term or long term longitudinal data regarding COVID-19 vaccine efficacy.
Short term data has not established prevention of severe disease. The European Medicines Agency has noted of the Comirnaty (Pfizer mRNA) vaccine that severe COVID-19 cases “were rare in the study, and statistically certain conclusion cannot be drawn” from it [30]. Similarly, the Pfizer document submitted to the FDA [31] concludes that efficacy against mortality could not be demonstrated. Thus, the vaccines have not been shown to prevent death or severe disease even in the short term.
The correlates of protection against COVID-19 are unknown. Researchers have not yet established how to measure protection against COVID-19. As a result, efficacy studies are stabbing around in the dark. After completion of Phase 1 and 2 studies, for instance, a paper in the journal Vaccine noted that “without understanding the correlates of protection, it is impossible to currently address questions regarding vaccine-associated protection, risk of COVID-19 reinfection, herd immunity, and the possibility of elimination of SARS-CoV-2 from the human population” [32]. Thus, Vaccine efficacy cannot be evaluated because we have not yet established how to measure it.
3. The vaccines are dangerous
Just as smoking could be and was predicted to cause lung cancer based on first principles, all gene-based vaccines can be expected to cause blood clotting and bleeding disorders [33], based on their molecular mechanisms of action. Consistent with this, diseases of this kind have been observed across age groups, leading to temporary vaccine suspensions around the world — The vaccines are not safe.
Contrary to claims that blood disorders post-vaccination are “rare”, many common vaccine side effects (headaches, nausea, vomiting and haematoma-like “rashes” over the body) may indicate thrombosis and other severe abnormalities. Moreover, vaccine-induced diffuse micro-thromboses in the lungs can mimic pneumonia and may be misdiagnosed as COVID-19. Clotting events currently receiving media attention are likely just the “tip of a huge iceberg” [34] — The vaccines are not safe.
Due to immunological priming, risks of clotting, bleeding and other adverse events can be expected to increase with each re-vaccination and each intervening coronavirus exposure. Over time, whether months or years [35], this renders both vaccination and coronaviruses dangerous to young and healthy age groups, for whom without vaccination COVID-19 poses no substantive risk.
Since vaccine roll-out, COVID-19 incidence has risen in numerous areas with high vaccination rates [36–38]. Furthermore, multiple series of COVID-19 fatalities have occurred shortly after the onset vaccinations in senior homes [39,40]. These cases may have been due not only to antibody-dependent enhancement but also to a general immunosuppressive effect of the vaccines, which is suggested by the increased occurrence of Herpes zoster in certain patients [41]. Immunosuppression may have caused a previously asymptomatic infection to become clinically manifest. Regardless of the exact mechanism responsible for these reported deaths, we must expect that the vaccines will increase rather than decrease lethality of COVID-19 — The vaccines are not safe.
4. The vaccines are experimental by definition.
They will remain in Phase 3 trials until 2023. Recipients are human subjects entitled to free informed consent under Nuremberg and other protections, including the Parliamentary Assembly of the Council of Europe’s resolution 2361 [42] and the FDA’s terms of emergency use authorisation [29]. With respect to safety data from Phase 1 and 2 trials, in spite of initially large sample sizes the journal Vaccine reports that, “the vaccination strategy chosen for further development may have only been given to as few as 12 participants” [32]. With such extremely small sample sizes, the journal notes that, “larger Phase 3 studies conducted over longer periods of time will be necessary” to establish safety. The risks that remain to be evaluated in Phase 3 trials into 2023, with entire populations as subjects, include not only thrombosis and bleeding abnormalities, but other autoimmune responses, allergic reactions, unknown tropisms (tissue destinations) of lipid nanoparticles [35], antibody-dependent enhancement [43–46] and the impact of rushed, questionably executed, poorly regulated [47] and reportedly inconsistent manufacturing methods, conferring risks of potentially harmful impurities such as uncontrolled DNA residues [48]. The vaccines are not safe, either for recipients or for those who administer them or authorise their use.
5. Initial experience might suggest that the adenovirus-derived vaccines (AstraZeneca/Johnson & Johnson) cause graver adverse effects than the mRNA (Pfizer/Moderna) vaccines. However, upon repeated injection, the former will soon induce antibodies against the proteins of the adenovirus vector. These antibodies will then neutralize most of the vaccine virus particles and cause their disposal before they can infect any cells, thereby limiting the intensity of tissue damage.
In contrast, in the mRNA vaccines, there is no protein antigen for the antibodies to recognize. Thus, regardless of the existing degree of immunity, the vaccine mRNA is going to reach its target — the body cells. These will then express the spike protein and subsequently suffer the full onslaught of the immune system. With the mRNA vaccines, the risk of severe adverse events is virtually guaranteed to increase with every successive injection. In the long term, they are therefore even more dangerous than the vector vaccines. Their apparent preferment over the latter is concerning in the highest degree; these vaccines are not safe.
4. Ethics and legal points to consider
Conflicts of interest abound in the scientific literature and within organisations that recommend and promote vaccines, while demonising alternate strategies (reliance on natural immunity and early treatment).
Authorities, doctors and medical personnel need to protect themselves by evaluating the sources of their information for conflicts of interest extremely closely. Authorities, doctors and medical personnel need to be similarly careful not to ignore the credible and independent literature on vaccine necessity, safety and efficacy, given the foreseeable mass deaths and harms that must be expected unless the vaccination campaign is stopped.
Vaccine manufacturers have exempted themselves from legal liability for adverse events for a reason. When vaccine deaths and harms occur, liability will fall to those responsible for the vaccines’ authorisation, administration and/or coercion via vaccine passports, none of which can be justified on a sober, evidence-based risk-benefit analysis.
All political, regulatory and medical actors involved in COVID-19 vaccination should familiarise themselves with the Nuremberg code and other legal provisions in order to protect themselves.
References
Le Bert, N.; Tan, A.T.; Kunasegaran, K.; Tham, C.Y.L.; Hafezi, M.; Chia, A.; Chng, M.H.Y.; Lin, M.; Tan, N.; Linster, M.; Chia, W.N.; Chen, M.I.; Wang, L.; Ooi, E.E.; Kalimuddin, S.; Tambyah, P.A.; Low, J.G.; Tan, Y. and Bertoletti, A. (2020) SARS-CoV-2-specific T cell immunity in cases of COVID-19 and SARS, and uninfected controls. Nature 584:457–462
Tarke, A.; Sidney, J.; Methot, N.; Zhang, Y.; Dan, J.M.; Goodwin, B.; Rubiro, P.; Sutherland, A.; da Silva Antunes, R.; Frazier, A. and al., e. (2021) Negligible impact of SARS-CoV-2 variants on CD4+ and CD8+ T cell reactivity in COVID-19 exposed donors and vaccinees. bioRxiv -:x-x
Anonymous, (2020) Scientists uncover SARS-CoV-2-specific T cell immunity in recovered COVID-19 and SARS patients.
Beasley, D. (2020) Scientists focus on how immune system T cells fight coronavirus in absence of antibodies.
Bozkus, C.C. (2020) SARS-CoV-2-specific T cells without antibodies. Nat. Rev. Immunol. 20:463
Grifoni, A.; Weiskopf, D.; Ramirez, S.I.; Mateus, J.; Dan, J.M.; Moderbacher, C.R.; Rawlings, S.A.; Sutherland, A.; Premkumar, L.; Jadi, R.S. and al., e. (2020) Targets of T Cell Responses to SARS-CoV-2 Coronavirus in Humans with COVID-19 Disease and Unexposed Individuals. Cell 181:1489–1501.e15
Mateus, J.; Grifoni, A.; Tarke, A.; Sidney, J.; Ramirez, S.I.; Dan, J.M.; Burger, Z.C.; Rawlings, S.A.; Smith, D.M.; Phillips, E. and al., e. (2020) Selective and cross-reactive SARS-CoV-2 T cell epitopes in unexposed humans. Science 370:89–94
McCurry-Schmidt, M. (2020) Exposure to common cold coronaviruses can teach the immune system to recognize SARS-CoV-2.
Palmer, S.; Cunniffe, N. and Donnelly, R. (2021) COVID-19 hospitalization rates rise exponentially with age, inversely proportional to thymic T-cell production. J. R. Soc. Interface 18:20200982
Sekine, T.; Perez-Potti, A.; Rivera-Ballesteros, O.; Strålin, K.; Gorin, J.; Olsson, A.; Llewellyn-Lacey, S.; Kamal, H.; Bogdanovic, G.; Muschiol, S. and al., e. (2020) Robust T Cell Immunity in Convalescent Individuals with Asymptomatic or Mild COVID-19. Cell 183:158–168.e14
Drake, J. (2021) Now We Know: Covid-19 Vaccines Prevent Asymptomatic Infection, Too.
Jefferson, T.; Spencer, E.; Brassey, J. and Heneghan, C. (2020) Viral cultures for COVID-19 infectivity assessment. Systematic review. Clin. Infect. Dis. ciaa1764:x-x
Borger, P.; Malhotra, R.K.; Yeadon, M.; Craig, C.; McKernan, K.; Steger, K.; McSheehy, P.; Angelova, L.; Franchi, F.; Binder, T.; Ullrich, H.; Ohashi, M.; Scoglio, S.; Doesburg-van Kleffens, M.; Gilbert, D.; Klement, R.J.; Schrüfer, R.; Pieksma, B.W.; Bonte, J.; Dalle Carbonare, B.H.; Corbett, K.P. and Kämmer, U. (2020) External peer review of the RTPCR test to detect SARS-CoV-2 reveals 10 major scientific flaws at the molecular and methodological level: consequences for false positive results.
Mandavilli, A. (2020) Your Coronavirus Test Is Positive. Maybe It Shouldn’t Be.
Cao, S.; Gan, Y.; Wang, C.; Bachmann, M.; Wei, S.; Gong, J.; Huang, Y.; Wang, T.; Li, L.; Lu, K.; Jiang, H.; Gong, Y.; Xu, H.; Shen, X.; Tian, Q.; Lv, C.; Song, F.; Yin, X. and Lu, Z. (2020) Post-lockdown SARS-CoV-2 nucleic acid screening in nearly ten million residents of Wuhan, China. Nat. Commun. 11:5917
Moghadas, S.M.; Fitzpatrick, M.C.; Sah, P.; Pandey, A.; Shoukat, A.; Singer, B.H. and Galvani, A.P. (2020) The implications of silent transmission for the control of COVID-19 outbreaks. Proc. Natl. Acad. Sci. U. S. A. 117:17513–17515
Johansson, M.A.; Quandelacy, T.M.; Kada, S.; Prasad, P.V.; Steele, M.; Brooks, J.T.; Slayton, R.B.; Biggerstaff, M. and Butler, J.C. (2021) SARS-CoV-2 Transmission From People Without COVID-19 Symptoms. JAMA network open 4:e2035057
Yeadon, M. (2020). What SAGE got wrong. Lockdown Skeptics.
Ioannidis, J.P.A. (2020) Global perspective of COVID‐19 epidemiology for a full‐cycle pandemic. Eur. J. Clin. Invest. 50:x-x
Ioannidis, J.P.A. (2021) Reconciling estimates of global spread and infection fatality rates of COVID‐19: An overview of systematic evaluations. Eur. J. Clin. Invest. -:x-x
CDC, (2020) Science Brief: Community Use of Cloth Masks to Control the Spread of SARS-CoV-2.
Orient, J.; McCullough, P. and Vliet, E. (2020) A Guide to Home-Based COVID Treatment.
Procter, {.B.C.; {APRN}, {.C.R.{.; {PA}-C, {.V.P.; {PA}-C, {.E.S.; {PA}-C, {.C.H. and McCullough, {.{.P.A. (2021) Early Ambulatory Multidrug Therapy Reduces Hospitalization and Death in High-Risk Patients with SARS-CoV-2 (COVID-19). International journal of innovative research in medical science 6:219–221
McCullough, P.A.; Kelly, R.J.; Ruocco, G.; Lerma, E.; Tumlin, J.; Wheelan, K.R.; Katz, N.; Lepor, N.E.; Vijay, K.; Carter, H.; Singh, B.; McCullough, S.P.; Bhambi, B.K.; Palazzuoli, A.; De Ferrari, G.M.; Milligan, G.P.; Safder, T.; Tecson, K.M.; Wang, D.D.; McKinnon, J.E.; O’Neill, W.W.; Zervos, M. and Risch, H.A. (2021) Pathophysiological Basis and Rationale for Early Outpatient Treatment of SARS-CoV-2 (COVID-19) Infection. Am. J. Med. 134:16–22
Anonymous, (2020) Real-time database and meta analysis of 588 COVID-19 studies.
Hirschhorn, J.S. (2021) COVID scandal: Feds ignored 2016 law requiring use of real world evidence.
Anonymous, (1998) Emergency Use of an Investigational Drug or Biologic: Guidance for Institutional Review Boards and Clinical Investigators.
Anonymous, (2021) EMA assessment report: Comirnaty.
Anonymous, (2020) FDA briefing document: Pfizer-BioNTech COVID-19 Vaccine.
Giurgea, L.T. and Memoli, M.J. (2020) Navigating the Quagmire: Comparison and Interpretation of COVID-19 Vaccine Phase 1/2 Clinical Trials. Vaccines 8:746
Bhakdi, S.; Chiesa, M.; Frost, S.; Griesz-Brisson, M.; Haditsch, M.; Hockertz, S.; Johnson, L.; Kämmerer, U.; Palmer, M.; Reiss, K.; Sönnichsen, A.; Wodarg, W. and Yeadon, M. (2021) Urgent Open Letter from Doctors and Scientists to the European Medicines Agency regarding COVID-19 Vaccine Safety Concerns.
Bhakdi, S. (2021) Rebuttal letter to European Medicines Agency from Doctors for Covid Ethics, April 1, 2021.
Ulm, J.W. (2020) Rapid response to: Will covid-19 vaccines save lives? Current trials aren’t designed to tell us.
Reimann, N. (2021) Covid Spiking In Over A Dozen States — Most With High Vaccination Rates.
Meredith, S. (2021) Chile has one of the world’s best vaccination rates. Covid is surging there anyway.
Bhuyan, A. (2021) Covid-19: India sees new spike in cases despite vaccine rollout. BMJ 372:n854
Morrissey, K. (2021) Open letter to Dr. Karina Butler.
Anonymous, (2021) Open Letter from the UK Medical Freedom Alliance: Urgent warning re Covid-19 vaccine-related deaths in the elderly and Care Homes.
Furer, V.; Zisman, D.; Kibari, A.; Rimar, D.; Paran, Y. and Elkayam, O. (2021) Herpes zoster following BNT162b2 mRNA Covid-19 vaccination in patients with autoimmune inflammatory rheumatic diseases: a case series. Rheumatology -:x-x
Anonymous, (2021) Covid-19 vaccines: ethical, legal and practical considerations.
Tseng, C.; Sbrana, E.; Iwata-Yoshikawa, N.; Newman, P.C.; Garron, T.; Atmar, R.L.; Peters, C.J. and Couch, R.B. (2012) Immunization with SARS coronavirus vaccines leads to pulmonary immunopathology on challenge with the SARS virus. PLoS One 7:e35421
Bolles, M.; Deming, D.; Long, K.; Agnihothram, S.; Whitmore, A.; Ferris, M.; Funkhouser, W.; Gralinski, L.; Totura, A.; Heise, M. and Baric, R.S. (2011) A double-inactivated severe acute respiratory syndrome coronavirus vaccine provides incomplete protection in mice and induces increased eosinophilic proinflammatory pulmonary response upon challenge. J. Virol. 85:12201–15
Weingartl, H.; Czub, M.; Czub, S.; Neufeld, J.; Marszal, P.; Gren, J.; Smith, G.; Jones, S.; Proulx, R.; Deschambault, Y.; Grudeski, E.; Andonov, A.; He, R.; Li, Y.; Copps, J.; Grolla, A.; Dick, D.; Berry, J.; Ganske, S.; Manning, L. and Cao, J. (2004) Immunization with modified vaccinia virus Ankara-based recombinant vaccine against severe acute respiratory syndrome is associated with enhanced hepatitis in ferrets. J. Virol. 78:12672–6
Czub, M.; Weingartl, H.; Czub, S.; He, R. and Cao, J. (2005) Evaluation of modified vaccinia virus Ankara based recombinant SARS vaccine in ferrets. Vaccine 23:2273–9
Tinari, S. (2021) The EMA covid-19 data leak, and what it tells us about mRNA instability. BMJ 372:n627
Anonymous, (2021) Interview with Dr. Vanessa Schmidt-Krüger.