Archive for the ‘Lyme’ Category

Seeking to Unlock the Mysteries of Lyme Arthritis

https://www.lymedisease.org/unlock-mysteries-lyme-athritis/

Seeking to unlock the mysteries of Lyme arthritis

By Richard Harth
Biodesign Institute at Arizona State University

A nature lover from early childhood, Karie Behm found peace and renewal through hiking and cross-country running. She spent much of her time exploring the forested terrain of her native Kansas, as well as Minnesota and Colorado, during family vacations.

She did not suspect that on one unremarkable day, microscopic, corkscrew-like pathogens known as spirochetes would stealthily invade her body, causing a succession of painful, debilitating and perplexing disease symptoms. It would take physicians over six years to untangle the mystery.

Behm had contracted Lyme disease, following a tick bite.

A recent doctoral graduate from the School of Molecular Sciences and the Biodesign Institute at Arizona State University, Behm has devoted her energies to unlocking some of the secrets of Lyme disease, a tenacious ailment affecting some 500,000 Americans every year.

“People have finally come to the realization that Lyme disease has been around a long time and has been affecting a lot of people who have been chronically ill and couldn’t get help,” Behm says. “Patient advocacy groups have been working tirelessly for the last 20 years to try to bring attention to this problem. It’s not a little thing and it’s not a joke. It can affect you your entire life.”

Studying the disease that debilitated her

Behm came to ASU in 2016, with a personal goal in mind — to study the disease causing her often incapacitating symptoms. A highly motivated scholar and researcher, she managed to convince her advisor, Debra Hansen, of the importance of studying this underreported and misunderstood ailment.

Behm and Hansen, both researchers with the Biodesign Center for Applied Structural Discovery (CASD), then consulted Petra Fromme, director of the center and an authority on the structural characterization of proteins, including those associated with infectious disease.

The team hatched a plan to study Lyme arthritis, a pervasive symptom found in many Lyme disease cases. “Petra loves students who share her passion,” Behm says.

“During my first interview with her, she got really excited about how the lab’s structural techniques could be applied to Lyme disease.” Prior to her arrival at the lab, Behm, working independently, had already completed an NSF proposal to study Lyme disease.

The project gathered momentum when Behm conducted a literature search, identifying a suite of proteins believed to decorate the surface of Borrelia burgdorferi, the bacterial parasite transmitted by a tick bite that causes Lyme disease.

Drawing on a recent award from ASU Women and Philanthropy, the team is advancing its efforts by using a powerful method known as cryo-EM to observe membrane proteins found on the surface of the Borrelia parasite in stunning detail.

A remarkable discovery
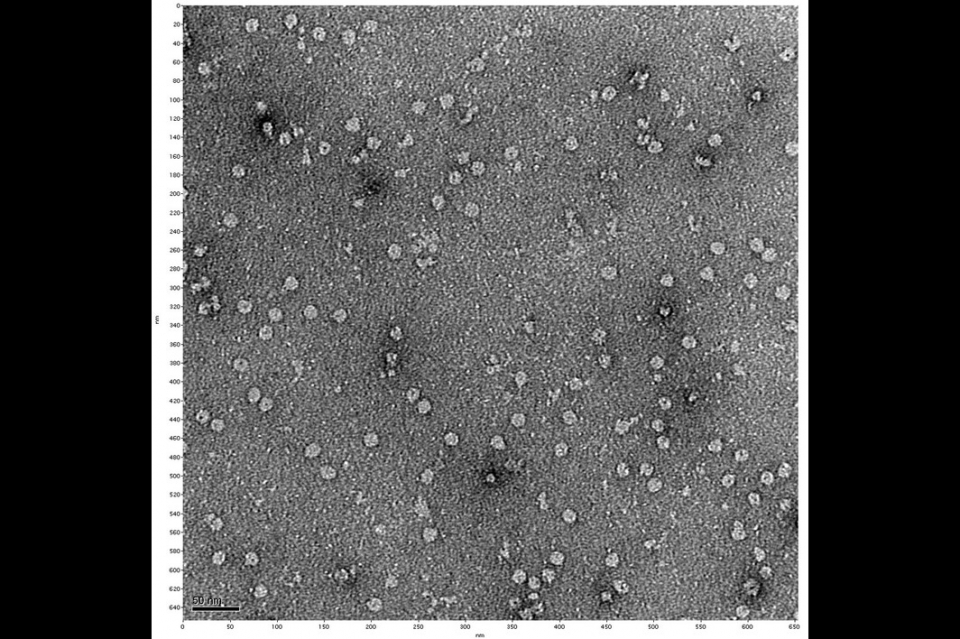
Eureka moment: Behm’s negative stain electron microscopy image, offering the first visual evidence of a membrane pore identified by the researchers. This pore may provide an attractive therapeutic target for future drug design against Lyme arthritis. Photo courtesy Biodesign Institute.

The research has already led to a remarkable discovery. One such membrane protein, known as BBA57, binds to copies of itself to form a complex at the membrane surface. The result appears to be a portal to and from the cell’s interior — a pore.

The discovery arrived late one night in the lab, in the form of fresh electron microscope images. It was the culmination of years of dogged research and opens the door to effective therapies against Lyme disease, and potentially other serious afflictions as well.

Of the 100 or so membrane proteins recognized in B. burgdorferi, BBA57 is special. Its presence is linked to Lyme arthritis, a painful, untreatable and often lifelong affliction occurring in 20% of Lyme disease patients.

The discovery of the membrane hole may be a turning point, as it provides an ideal site to attack Lyme arthritis by designing a drug that can plug up the pore.

“This project aims to discover the first structure of the major protein responsible for Lyme arthritis, BB57, which forms a pore-like structure in the membrane,” Fromme says. “When we unravel the structural basis for Lyme arthritis, new drugs can be developed to fight the condition and prevent the lifelong suffering of hundreds of thousands of patients.”

Climate change and Lyme disease

The bacteria responsible for Lyme disease are carried in the saliva of several tick varieties. In the Northeast and upper Midwestern U.S., the disease is transmitted by the blacklegged tick (Ixodes scapularis), and by the western blacklegged tick (Ixodes pacificus) along the Pacific Coast.

Lyme-carrying ticks operate by stealth. They are not able to fly or jump, instead finding their targets through a process known as questing. Resting atop grasses or shrubs, the ticks hold fast to leaves or grass using their lower legs. The upper pair of legs is kept outstretched, awaiting an unsuspecting passerby. When a suitable host brushes past the place where the tick lies in wait, it quickly climbs onto the host and locates a place to bite and feed on blood.

Ticks may attach themselves to any part of the human body but are often found in well-concealed regions, including the groin area, armpits and scalp. Once a tick has attached and begun feeding, it usually takes 36–48 hours for the Lyme bacteria to be transmitted.

While Borrelia bacteria can cause severe illness in their human hosts, in a diabolical twist, they may improve the tick’s fitness by modifying its central nervous system, extending the length of time the tick spends questing and making it more resistant to extremes of temperature and dryness. To make matters worse, many Lyme disease patients become co-infected with other pathogenic microbes lurking in ticks.

Another area of concern is the fact that reported cases of the disease have roughly doubled since 1991. This is likely due to a combination of factors, including more awareness of the disease and better diagnostic approaches. But there is also mounting evidence that the geographic range over which Lyme-carrying ticks wander may be expanding due to climate change.

Disease of a thousand faces

Many factors may affect the timing and nature of symptoms of Lyme disease, which typically begin three to 30 days following infection. Such symptoms may include fever, chills, headache, fatigue, muscle and joint aches, and swollen lymph nodes, with or without an accompanying rash.

One reason Lyme disease is so vexing to properly diagnose is that it can manifest in many ways in different patients. While 70% of Lyme cases develop the signature circular rash according to reporting, even this figure remains a topic of fierce controversy, and the CDC believes there may be a significant overreporting of rashes. This is because without the rash, Lyme cases are less likely to be diagnosed and treated in a timely manner by physicians.

Should the telltale rash known as erythema migrans occur, it will appear at the site of the tick bite, expanding gradually over several days. The rash may feel warm to the touch but is usually not painful or itchy. The rash sometimes clears as it enlarges, producing a characteristic bullseye appearance, but can assume different shapes, if it is present at all.

An array of further symptoms can develop days or months after infection, including facial palsy; neck stiffness; severe headache; intermittent pain in tendons, muscles, joints and bones; heart palpitations or an irregular heartbeat (known as Lyme carditis); nerve pain and inflammation of the brain and spinal cord; episodes of dizziness; and shortness of breath.

Behm recalls the perplexing constellation of symptoms at the start of her illness: “As a younger teenager, I had random medical issues that came up that just didn’t seem to make sense,” she says.

“There were visits to a lot of medical facilities. They knew something was wrong but couldn’t figure out what it was. I got passed around to specialists until I was officially diagnosed my senior year of high school.”

Lyme arthritis can cause severe pain and permanent joint damage

Approximately one in four Lyme disease patients may develop Lyme arthritis, involving chronic joint pain and swelling, particularly the knees and other large joints. The disorder occurs when the Lyme disease bacteria migrate to joint tissues, causing inflammation.

If left untreated, Lyme arthritis causes permanent damage to joints. While knees are the most commonly affected area, other large joints may be involved, including the shoulder, ankle, elbow, jaw, wrist or hip.

Following diagnosis, Lyme disease is treated with a course of antibiotics, which can work to eliminate the spirochete bacteria and gradually relieve symptoms. Yet, there is an important caveat: time is of the essence.

“The existing treatments generally don’t work if you’ve been infected more than two to six months prior,” Hansen says.

By this time, “the bacteria have disseminated in your body, and go into a persistent, antibiotic-resistant form. So if you’re diagnosed six years later, like Karie, and you’re treated for the disease, that treatment probably doesn’t work because the bacteria are resistant,” she says.

The result can be a collection of symptoms referred to [by some] as Post-Treatment Lyme Disease Syndrome. The causes are varied and remain poorly understood. It may be that the bacterium has changed form and sequestered itself in ways that evade detection. In other cases, autoimmune responses may be involved. To date, no treatment exists for these common complications.

Roughly 70,000 people in the U.S. each year experience lifelong, untreatable Lyme disease. Among these are some 42,000 who develop Lyme arthritis. Currently, physicians have had little to offer such patients, but that may be about to change.

Protein components of Lyme unmasked

Using electron microscopy, Behm, Hansen and Fromme were able to zero in on a protein that had been identified in previous research as an essential element in the process leading to Lyme arthritis. This work had been carried out by Dr. Uptal Pal, a Lyme disease authority from the University of Maryland, who is now collaborating with the ASU group.

The Lyme disease protein complex at the membrane surface of B. burgdorferi is comparatively large, tricky to crystallize and not easily amenable to X-ray crystallography, the conventional gold standard for protein structural analysis. Instead, a relatively new and powerful method known as cryo-EM, ideal for large proteins, was used.

Cryo-EM, a groundbreaking method for investigating 3D protein shapes, has racked up a long list of impressive achievements since 2017, when its discoverers were awarded the Nobel Prize in Chemistry. Nevertheless, the new study marks the first time it has been applied to the study of Lyme disease.

The technique involves flash-freezing solutions of proteins or other biomolecules in vitreous ice, then bombarding them with electrons to produce images of individual molecules suitable for electron microscopy. The images are used to reconstruct the 3D structure of the molecule, an essential step in understanding how proteins work, how their dysfunction (or use by pathogens) can trigger disease and how drugs may be custom engineered to target them.

Molecular mugshot spurs eureka moment

Peering at the specimens through electron eyes, the researchers began to produce a molecular portrait of the suspect believed to be responsible for Lyme arthritis, through the acquisition of thousands of cryo-EM snapshots.

Research by Pal had already shown that strains of Borrelia engineered to lack BBA57 did not produce Lyme arthritis, though the reasons for this remained obscure. It was only through the work of Behm and her team that a plausible mechanism gradually came into focus.

In addition to complex sample preparation, thousands of images had to be carefully assembled. Often, it seemed the researchers were feeling their way through the dark. But late one evening in the lab, a new set of negative stain electron microscopy images were developed, and the results were riveting. At long last, the team had pictures with just enough resolution to make out what unmistakably appeared as a small hole in the membrane, composed of protein subunits.

It was the break they had been waiting for, after three years of work.

The team had theorized that perhaps Borrelia causes Lyme arthritis by transporting some disease factor from within the cell, out into the extracellular environment. And here, before their eyes, was the transport tunnel likely used as a passageway from inside the cell to outside, into the host’s bloodstream.

“Debbie, Petra and I were all there, having a late-night meeting when we saw the images. And everyone shouted, ‘Yay!’” Behm recalls.

The elusive pores they had long suspected had materialized with unmistakable clarity.

The race for a cure

The most gratifying news for the group was not simply that their hard work was rewarded with an important insight into the structure of BBA57, but that the finding suggests a promising approach for preventing Lyme arthritis.

The basic idea is simple: Design a drug that plugs up the hole on the Borrelia membrane surface. But to accomplish this, the protein structure of BBA57 will require much more refinement.

The team has calculated that the images of a million pores will be needed to visualize the protein with sufficient resolution to permit drug design. The researchers are using the new award from ASU Woman and Philanthropy to achieve this feat, collecting the mass of images that will permit structural determination down to the locations of atoms.

Achieving atomic resolution will allow the researchers to see where each of the roughly 800,000 atoms making up each pore-forming molecule are situated.

“We’ll know the position of each of those atoms, and that kind of intimate detail is enough to be able to computationally look for drug binders, with existing drug libraries,” Hansen says.

Teaming up with Pal, the researchers are pursuing long-term funding through a $3 million grant proposal to NIH, due to begin as early as 2023. The funding will be contingent on the early results the group is producing now, so the pace of study is hectic.

Once the final structural determination of a given protein has been made, drug companies can take the 3D data and use high-performance computers to begin designing drugs to act on it.

The long and winding road ahead

BBA57 is just one protein active in Lyme disease. Many others exist, and once they have been characterized, may also be targeted by smart drugs. The possibility of preventing Lyme disease altogether may be on the horizon, and the general approach pursued by Behm and her colleagues may be applicable to other tick-borne diseases or, possibly, other spirochete afflictions, such as syphilis, yaws and relapsing fever.

Having suffered through the ups and downs of this enigmatic illness, Behm is doubly committed to finding answers. She describes the early days of her pitched battle with the disease as a mixture of fear and determination.

Behm continues her explorations of Lyme disease at her new position as ORISE Fellow at the CDC in Atlanta.

__________________

**Comment**

I have numerous issues with this article:

  1. Lyme arthritis IS treatable.  Please see the comment section after the article:  https://madisonarealymesupportgroup.com/2022/05/04/why-do-some-people-develop-severe-lyme-arthritis-others-dont/  I must also add that chelation (pulling heavy metals out of the body) is another strategy I am currently using. I have also found the following form of curcumin completely eradicated my pain. Dealing with inflammation is a must.
  2. Minimum transmission times have never been studied and to continue to regurgitate the mantra that it “usually takes 36-48” hours for it to happen is causing untold suffering.
  3. There is often more than Lyme at play and transmission time can be within minutes.
  4. “Climate change” has NOTHING to do with tick and disease proliferation but continues to be chanted like a mantra from research institutions who depend upon government grants.  It is part of a much larger scheme for power and money.
  5. Pigeon-holing symptoms happening three-30 days after infection is mythology also dooming thousands.  Nothing is said about psychological issues often experienced.
  6. It is a complete LIE that 70% develop the EM rash. It is highly variable & often not there.
  7. We need to drop the PTLDS label like a bad habit.  It does not explain a huge subset of patients but is still being used to put patients into a four-cornered box.
  8. To throw out that 70,000 in the US experience untreatable Lyme is complete guesswork.  According to this, the actual number is much, much higher.  No research is done on this group.  They simply don’t exist because mainstream medicine/research, led by the nose by the CDC/NIH/IDSA, don’t believe chronic/persistent Lyme exists.  Nobody even talks about the coinfections and the ramifications of having both.
  9. While researchers are riveted on finding/creating an expensive pharmaceutical “smart” drug (with patents to go all around making everyone wealthy) to plug up the elusive “pore” or conduit through which supposedly arthritis is created from, they ignore cheaper, safer, options such as nutraceuticals which desperate Lyme patients have had to discover, often on their own, to be effective.  Unfortunately, this myopic patent-oriented thinking is the “new norm” in research – even led by a patient who should know better due to the prolific and blatant corruption in all things in Lymeland.
US Government Agent Testing: Biological, Chemical Agents Making Thousands Sick – Tick-borne Illness

https://rumble.com/vq4k3f-us-government-agent-testing-biological-chemical-agents-making-thousands-sic.  Video Here (Approx. 15 Min)

Karma Newberry is the founder and CEO of Discovery Hydrovac, which serves the oil and gas industry. She’s become a successful businesswoman in a male-dominated field despite years of severe health problems that she’s suffered from for decades. At her peak, Karma was on more than 25 medications. After years of searching and consulting with more than 15 doctors, Karma says a physician finally checked her for tick-borne illnesses like Lyme disease. And the results shocked her: Karma had a bunch of them, including diseases that aren’t even present in the U.S. So how would she have them?

Those involved with classified human domain bioweapon testing:

  • Pfizer
  • Merck
  • Boeing
  • General Mills
  • University of Utah
  • DOD
  • Health Insurance Companies
  • Utah Medical facilities

Please remember that Fauci was at the helm for this entire history.

Find Newberry on Telegram (you have to download it)

Also here:  Lyme Justice

For more:

Chronic Lyme Disease & Insurance: Why Patients Can’t Get the Care They Need

https://www.lymedisease.org/chronic-lyme-disease-insurance/

Chronic Lyme Disease and Insurance: Why Patients Can’t Get the Care They Need

Previous studies have shown that patients who have persistent or chronic Lyme disease (PLD/ CLD) have a hard time obtaining the medical care they need to get well (Johnson 2011). A new study has found that clinicians who treat this population face significant challenges in providing patients care that is local, timely, and affordable (Johnson 2022).

Between September 23 and December 1, 2021, LymeDisease.org conducted a survey of U.S. clinicians who treat PLD/CLD patients. One hundred and fifty-five clinicians from 30 states responded to the survey and 45 provided comments in the open text survey item. The results of this survey were published this week: Access to Care in Lyme Disease: Clinician Barriers to Providing Care. The primary goal of this survey was to identify the difficulties that clinicians face when caring for patients with PLD/CLD.

The CDC estimates that 476,000 cases of Lyme disease occur annually (Kugeler 2021). Even when diagnosed and treated early, up to 44% of patients fail treatment, with only 56% considered to have returned to health (Aucott 2022). In later disease, treatment failure rates are higher. Lyme disease patients who remain ill after antibiotic treatment are regarded as having persistent or chronic Lyme disease. These patients may have been diagnosed early or late.

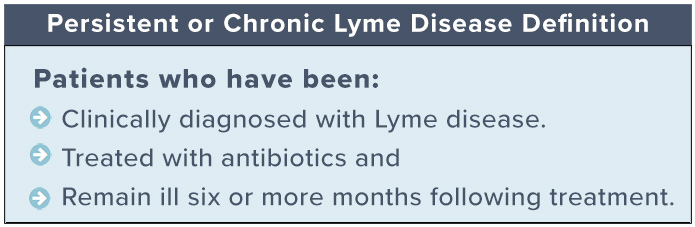
Chronic Lyme disease definition

Clinicians who treat PLD/CLD

Clinicians treating patients with PLD/CLD have developed significant clinical expertise. Most clinicians (55%) are  medical doctors (MD) or doctors of osteopathy (DO); the remainder are naturopaths with prescription privileges (15%), nurse practitioners (12%) or physician assistants (6%).

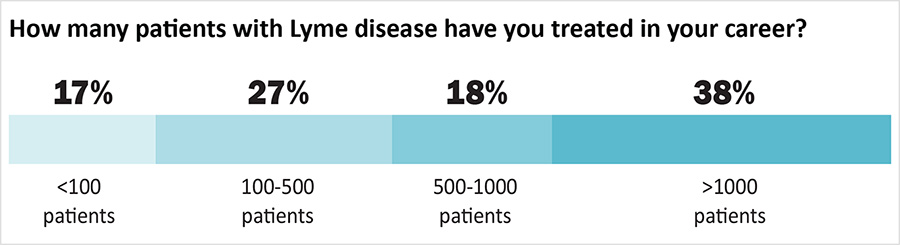
Over half of the clinicians (56%) have treated more than 500 patients and 38% have treated more than 1000 patients. Most (57%) dedicate more than half of their practice treating Lyme disease. Almost all (98%) have taken continued medical education for Lyme disease treatment. Eighty-nine percent belong to the International Lyme and Associated Diseases Society (ILADS) and most belong to other medical societies as well.

How many patients have you treated with Lyme disease?

Why Clinicians Who Treat Chronic Lyme Disease Find it Difficult to Provide Care

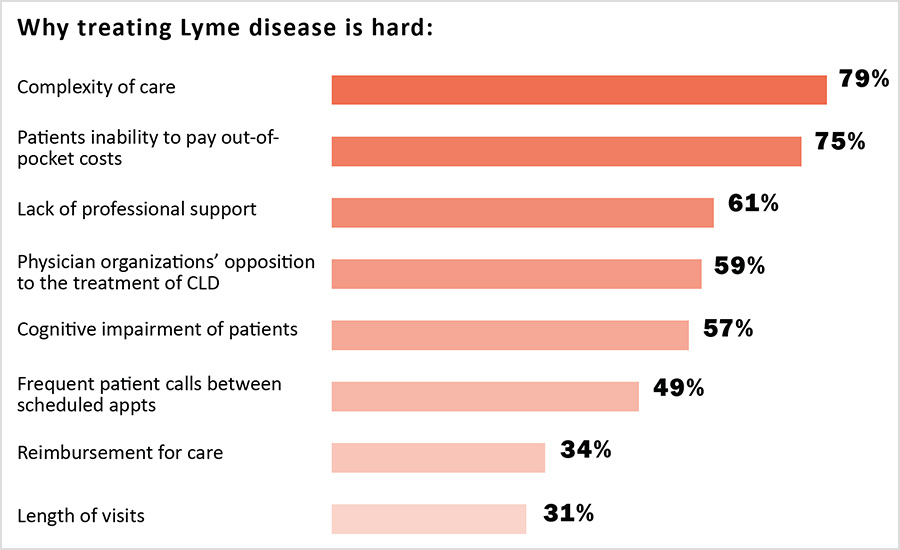
Despite their considerable expertise, clinicians report that providing care to PLD/CLD patients is challenging. In particular, the complexity of the care provided and the time it takes to provide that care make it difficult for clinicians to provide care using the traditional insurance-based healthcare model. This increases the cost of care provided to patients and makes it difficult for patients to pay for the care that can be given.

Why treating Lyme disease is hard

The complexity of care needed requires longer clinician visits than treatment for other conditions. For example, 25% of clinicians said their first consultations took more than two hours, and 44% said their follow-up visits took between one and two hours.

Clinicians reported that the length of healthcare visits for PLD/CLD coupled with the additional insurance administrative burdens and reimbursement payment issues make it hard for care to be given under a traditional insurance-based model, which typically relies on clinicians seeing a high volume of patients for short office visits. As one clinician explained:

“The most difficult problem is the cost of providing this amount of complex care on a cash basis. To really review hundreds of records, spend time with the patient and do a proper workup, takes hours. I’d like to see more support for patients and clinicians who choose to help this set of patients.”

As a result of these challenges, most PLD/CLD providers do not accept insurance:

  • 74% do not participate in insurance networks
  • 76% do not directly bill insurers
  • 77% do not participate in Medicare, Medicaid, or other government supported plans

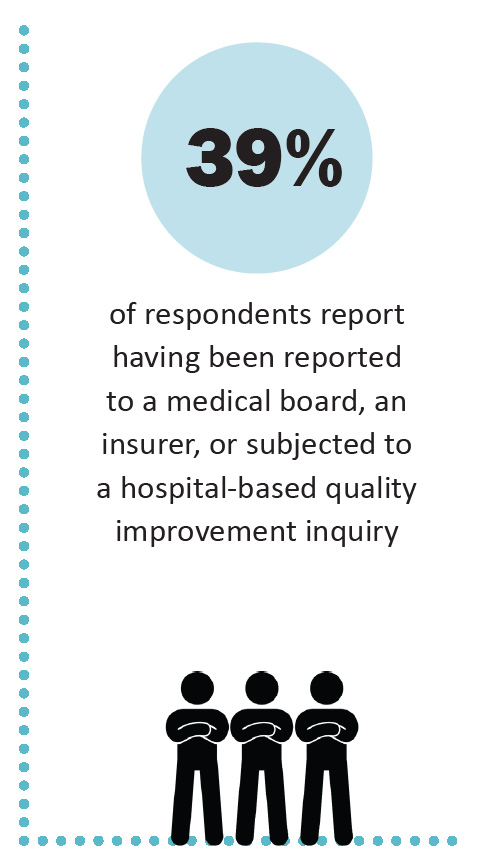
Another reason the insurance model of providing care does not work for PLD/CLD is that the risk of legal or regulatory action by medical boards, insurance companies, and other organizations is heightened for clinicians who accept insurance. Three-quarters of the clinicians who answered the survey say that they have been professionally stigmatized. More than a third (39%) report that they have been threatened with actions by medical boards, insurance companies, or hospital quality improvement committees.

One clinician commented:

“While my patients are generally very supportive, some of my colleagues have stopped speaking to me and I worry about the medico-legal repercussions of what I do.”

39 percent reported to medical board

Another said:

“I used to practice in a state where physicians who treat complex patients, including people with chronic Lyme, were specifically targeted by health insurance companies for medical board complaints and other attacks ESPECIALLY WHEN THEY HELPED PATIENTS OTHER DOCTORS GAVE UP ON. Eventually I elected to move to [a state] where there is less interruption of care and more protection of vulnerable patients from predatory insurance entities.”

One way clinicians can avoid targeting by insurance companies and other groups is by opting out of insurance networks, Medicare, and Medicaid. Clinicians who are stigmatized or don’t participate in insurance networks have fewer chances to share office space and overhead costs. This increases the cost of providing care. Treating PLD/CLD also imposed additional insurance related burdens that increase the cost of providing care exist even for clinicians who do not participate in insurance networks. These include prior authorization of medications (77%), insurance denials (71%), and other insurance-related problems (49%).

When clinicians do not participate in insurance networks, the economic burden of shouldering the cost of care is shifted to patients. This makes care more expensive for patients who have to pay for care out-of-pocket. It doesn’t come as a surprise then that 75% of clinicians say that a central problem in their practice is the patients’ inability to pay out of pocket costs. One clinician commented:

“I knew that at some point I would be forced to stop taking insurance and move forward on a cash pay only basis. Looking at the numbers, taking commercial insurance for these patients just doesn’t make any sense. I believe that the main issue that causes many of these patients to be without access to care is the amount they need to spend on their practitioners plus the out of pocket costs for out of network testing, labs, and treatment. For most of these patients that is anywhere from $10 to $20K per year. It is a huge burden.”

Essentially, the insurance model of providing healthcare is broken for patients with PLD/CLD. Not only does this increase the costs of providing care for providers and shift the cost burden to patients, it also means that patients can’t get care from their regular provider, must obtain care from places that don’t take their insurance, and need to navigate a complex healthcare maze to even find the care they need. Patient surveys published previously also identify the high cost of out-of-pocket care (Johnson 2011).

In addition, previous surveys have found that patients incur substantial diagnostic delays, misdiagnosis, see many clinicians before being diagnosed, and travel significant distances to receive care (Johnson 2011, 2014, 2020). To obtain care, 49% of patients report traveling more than 50 miles; 31% report traveling 100 miles or more for care (Johnson 2011). Because obtaining care can be expensive, inconvenient, and interfere with work responsibilities, many patients may choose not to get care at all (Johnson 2022).

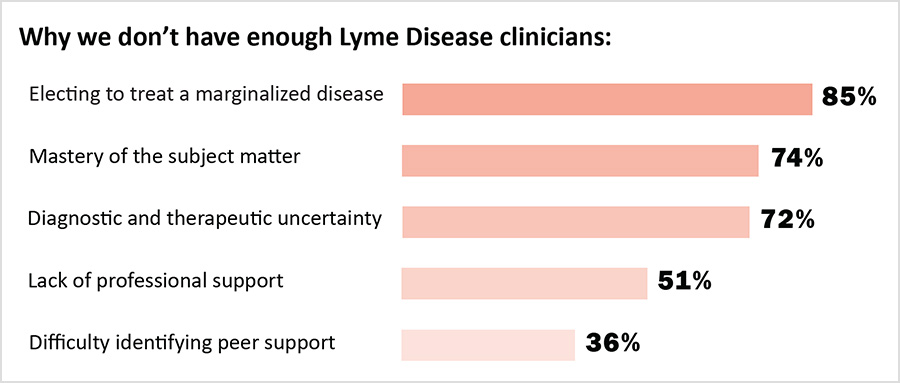
Clinicians here reported that patients with PLD/CLD often had to wait a long time for their first appointments, and that many of their patients traveled from outside their state of practice to obtain care. These factors point to a supply/demand crisis in the treatment of PLD/CLD. There are simply not enough clinicians to supply the amount of care required by patients to get well. The challenges identified by clinicians here—a broken insurance model of care, professional stigma, and heightened liability exposure—also discourage other clinicians from providing care to people with PLD/CLD.

Not enough Lyme disease clinicians

Why Early Diagnosis and Avoiding Misdiagnosis is Important

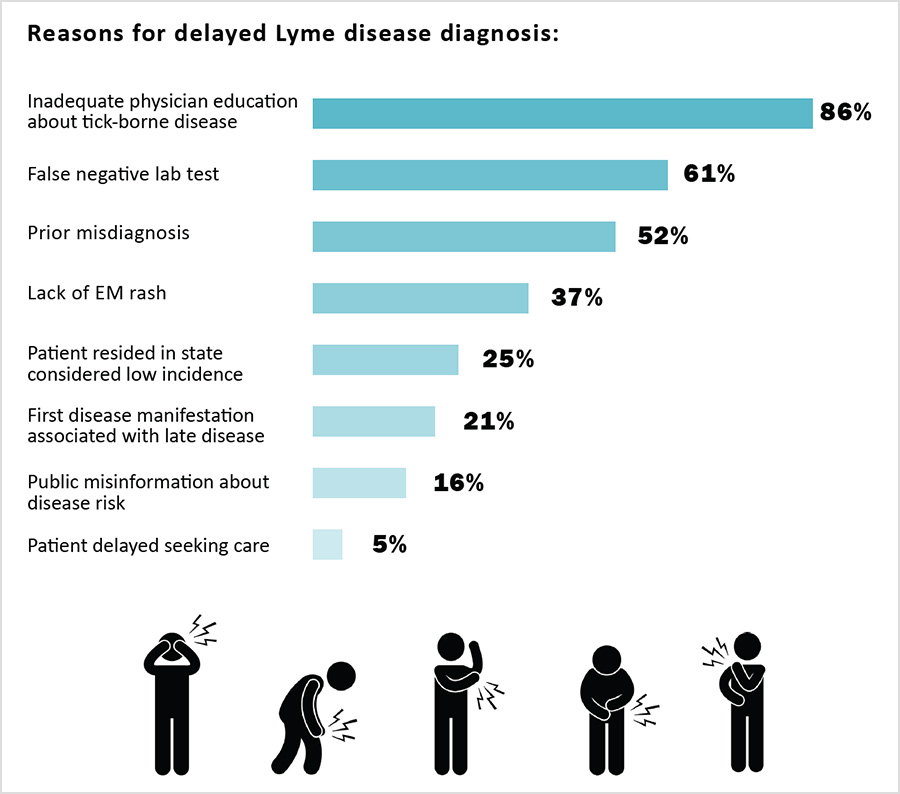
To address the supply/demand crises, it is important to reduce the number of patients who develop PLD/CLD. This requires early diagnosis and treatment. Clinicians identified inadequate physician education about tick borne diseases, false negative lab tests, and misdiagnosis as key causes of delayed diagnosis.

Delayed Lyme disease diagnosis

Nearly three quarters of patients report having initially been misdiagnosed. Misdiagnosis is often caused by the lack of education of other clinicians about tick-borne diseases (Johnson 2011, 2018). In a case series of people who might have had early Lyme disease but didn’t have a rash, 54% of Lyme disease patients who didn’t have a rash were given the wrong diagnosis (Aucott 2009). Because of this, misdiagnosis should be seen as a major risk factor for PLD/CLD.

Conclusion

The challenges identified here related to insurance and professional stigma make it hard to keep and hire clinicians who can care for the rapidly growing number of people with PLD/CLD, which is currently estimated to be slightly less than 2 million cases (Delong 2019). They also make care more costly for patients. Diagnostic delays and misdiagnosis increase the number of patients who develop PLD/CLD, exacerbating the supply/demand problem.

As Lyme disease cases rise, the demand for PLD/CLD providers will rise. The limited number of educated practitioners and the expanding number of PLD/CLD patients have created a substantial supply and demand imbalance that must be addressed.

Resolving the supply/demand imbalance is vital for PLD/CLD patients to become healthy. To do this we must:

  • improve clinician education to prevent diagnostic delay and misdiagnosis
  • retain and recruit more clinicians to address the supply demand crises by reducing professional stigma and recognizing that divergent treatment approaches exist in PLD/CLD
  • develop insurance reimbursement models that take into account the complexity of care and the time it takes to provide care.

Failing to address these issues will leave patients unable to access or afford the care that they need.

If you are a patient who is not enrolled in MyLymeData,  please enroll today. If you are a researcher who wants to collaborate with us, please contact me directly.

The MyLymeData Viz Blog is written by Lorraine Johnson, JD, MBA, who is the Chief Executive Officer of LymeDisease.org. You can contact her at lbjohnson@lymedisease.org. On Twitter, follow her @lymepolicywonk. 

Misdiagnosed For 30 Years – Had Lyme Disease

https://www.lymedisease.org/some-thoughts-about-30-years-of-misdiagnosed-lyme-disease/

Some thoughts about 30 years of misdiagnosed Lyme disease

Sept. 29, 2022

Kat Garza is what’s known in the industry as a “mature model”–pretty much any model over the age of 30.

One look at her photos easily demonstrates that women with gray hair can still be beautiful. But you have to dig a little deeper to find the life experiences that helped shape who she is.

Among other challenges, she suffered from unrecognized Lyme disease for three decades.

She also raised seven children, got divorced in her early 60s, and three years ago, at age 64, began her career as a model and Instagram “influencer.”

Here’s something she posted on Instagram the other day:

by Kat Garza

Can we talk about Lyme disease?

“But you look so healthy,” they say.

I was chatting with with my son today and he asked how I was doing. I had to answer that today – Lyme disease was kicking my butt.

Many days I feel just fine. Some days, not so good. But almost all days, I have to push myself and I do push.

Just last week I read an article about a 22 year old women who ended her life because she could no longer deal with the pain associated with Lyme disease. It hurts my heart to think that someone so young was in so much pain – a pain that was not taken seriously.

I know far too many others with Lyme disease who are not being listened to. They are not taken seriously and pushed aside with a misdiagnosis. I know I was. I was told:

• get tested for MS

• it’s your gallbladder

• it’s your heart

• it’s fibromyalgia

• it’s your diet

• it’s in your head

• it’s stress

• it’s lupus

#adnauseam tests after tests.

I was bitten by ticks 30 years ago and misdiagnosed, over and over and over again. I even had a massive brain tumor 23 years ago ago – something, I’m finding, that many with Lyme disease have also experienced. After multiple scans and tests almost three years ago, I finally found a doctor who listened and discovered it.

Why is it so difficult for a doctor to find it? Because they aren’t looking. If Lyme disease isn’t dealt with early on, it will attack the major organs of the body.

We are not told to see a doctor immediately when bitten by a tick. I have had people literally roll their eyes at me. It’s time for those ‘in the know,’ those in power, to take us seriously and listen to our plight, and believe us.

Do we need to march on Washington? Our congressional representatives aren’t listening. Certainly doctors aren’t listening. This disease needs to be brought to the forefront now. Maybe Amélie Champagne, age 22, would still be with us. If only someone would have listened.

You can follow Kat Garza here on Instagram.

TOUCHED BY LYME is written by Dorothy Kupcha Leland, Board President of LymeDisease.org. She is co-author of When Your Child Has Lyme Disease: A Parent’s Survival Guide. Contact her at dleland@lymedisease.org.

Quebec Coroner Calls For Inquiry Into Suicide of Woman With Lyme Disease

https://www.lymedisease.org/quebec-coroner-calls-for-inquiry/

“Hijacked by Lyme”: Quebec coroner calls for inquiry into suicide

The death by suicide of a young woman battling Lyme disease garnered international attention recently after her father—a prominent Canadian businessman—shared the news on LinkedIn.

Alain Champagne — the CEO and president of the Jean Coutu Group, a chain of Quebec pharmacies—posted the following:

“It is with the heaviest of hearts (and still in shock) that I share the tragic news that our sweetheart Amelie (22) took her own life this past Sunday…We were witnesses as to how challenging life had become for her in dealing with the evolving Lyme disease symptoms (after years of medical errance and finally getting a positive test in the US this past June, over time and despite the recent treatments, the disease had evolved way beyond the numerous physical symptoms and was now severely impacting her brain). Over time, Lyme essentially highjacked her.”

Now, CBC News reports that Quebec’s chief coroner has ordered a public inquiry into Amelie’s death.

Champagne told an interviewer that his daughter had suffered from significant sleep disorders and auditory hallucinations. He said her personality had changed in the weeks leading up to her death.

After a suicide attempt at the family’s cottage, Champagne said his daughter was taken to the Hôtel-Dieu, a teaching hospital in Quebec City. However, Champagne said hospital staff told him his daughter’s situation had stabilized and she did not represent a danger to herself.

Amelie was released without treatment and took her own life shortly thereafter.

Quebec’s outgoing junior health and social services minister, Lionel Carmant, said in an interview that this situation was unacceptable.

“That’s why we’ve called for a coroner’s inquiry, to see what practices caused this, where the system failed, and what needs changing. And we will change it,” he said.

TOUCHED BY LYME is written by Dorothy Kupcha Leland, Board President of LymeDisease.org. She is co-author of When Your Child Has Lyme Disease: A Parent’s Survival Guide. Contact her at dleland@lymedisease.org.

__________________

**Comment**

The story, while tragic beyond words, is one of many others in a similar situation.  But, it’s going to take a miracle for this mountain to move.  I’m not saying we shouldn’t try – it’s all I do on a daily basis- but the corruption regarding Lyme/MSIDS is so deep and so vast that it is truly going to take a miracle.  If working with the very organizations that are behind this debacle yields any positive change I will eat my hat.  I personally believe we are going to have to do our own work – including the science – to prove what we already know clinically.

Lyme/MSIDS is relapsing in nature and often causes chronic illness.
Those who follow the one microbe, one drug theory need not apply.

For more: