The Link Between Autoimmune Disease, Chronic Fatigue, And Hidden Infections
May 5, 2021
Pandemic aside, we’re seeing a national immune crisis. Autoimmune conditions continue to rise to record numbers, not to mention all of the chronic mystery illnesses that so many people struggle with daily. I’ve experienced this firsthand, along with the corresponding frustration and fear. There is an intriguing hypothesis about these conditions that I get into with my guests, Dana Parish and Dr. Steven Phillips, today on The Doctor’s Farmacy: underlying infections. Sneaky tick-borne diseases like Lyme, parasitic infections, and certain viruses can be extremely hard to diagnose. Meanwhile, they can contribute to an immune system collapse and other life-threatening breakdowns throughout the entire body.
Dr. Phillips and Dana Parish share their incredible stories of overcoming chronic stealth infections after numerous doctors couldn’t help them. Lyme was a common factor for both of them, while Dr. Phillips was also able to diagnose Bartonella in Dana. At their worst, they both had extremely limited mobility and felt their lives were at risk. Dana shares that in addition to recovering her mobility and strength, treating these infections also had a profound impact on her mental health by reducing her anxiety and depression. Dr. Phillips’ journey not only forced him to be his own detective to find healing, but also showed him how much discordance there is among conventional medicine in treating diseases like Lyme.
The CARES Act, which provides hospitals with bonus incentive payments for all things related to COVID-19 (testing, diagnosing, admitting to hospital, use of remdesivir and ventilators, reporting COVID-19 deaths, and vaccinations)
Waivers of customary and long-standing patient rights by the Centers for Medicare and Medicaid Services (CMS) which allows hospitals to “violate the rights of patients or their surrogates with regard to medical record access, to have patient visitation, and to be free from seclusion. This simply means COVID patients are literally prisoners in the hospital, are isolated, and have no say in their treatment.
Hospital payments include:
A “free” required PCR test in the Emergency Room or upon admission for every patient, with government-paid fee to hospital.
Added bonus payment for each positive COVID-19 diagnosis.
Another bonus for a COVID-19 admission to the hospital.
A 20 percent “boost” bonus payment from Medicare on the entire hospital bill for use of remdesivir instead of medicines such as Ivermectin.
Another and larger bonus payment to the hospital if a COVID-19 patient is mechanically ventilated.
More money to the hospital if cause of death is listed as COVID-19, even if patient did not die directly of COVID-19.
A COVID-19 diagnosis also provides extra payments to coroners.
CMS implemented “value-based” payment programs that track data such as how many workers at a healthcare facility receive a COVID-19 vaccine.Now we see why many hospitals implemented COVID-19 vaccine mandates. They are paid more. Source
Damning’ Ivermectin Tape Exposes Pressure by Big Pharma to Suppress Ivermectin, RFK, Jr.’s New Book Reveals
Robert F. Kennedy, Jr.’s new book, “The Real Anthony Fauci,” includes a revealing transcript — printed here — of a conversation with Dr. Andrew Hill, who admitted to caving to pressure to downplay the benefits of ivermectin as a COVID treatment.
Dr. Andrew Hill, author of a favorable analysis of ivermectin studies.
He had subsequently performed a “neck-wrenching” U-turn on the issue, claiming the studies comprised “low certainty” of value and that more trials were needed.
Lawrie was trying to persuade Hill to participate in and co-author an immediate review of all published ivermectin studies in the medical literature, to be conducted by the eminent Cochrane Network, which uses thousands of volunteers to make high-quality, independent treatment recommendations.
“It was an exciting opportunity,” Kennedy writes. “Under normal circumstances, Hill should have pounced on this chance to serve as lead author with some of the world’s most prestigious researchers. He was nevertheless noncommittal.
The article states that Lawrie spoke to Hill by Zoom and the call was recorded.
“Dr Lawrie asked Hill to explain his U-turn on ivermectin, which his own analysis found overwhelmingly effective. ‘How can you do this?’ she inquired politely. ‘You are causing irreparable harm.’ Hill explained that he was in a ‘tricky situation’ because his sponsors had put pressure on him. Hill is a University of Liverpool virologist who serves as an adviser to Bill Gates and the Clinton Foundation. He told me his sponsor was Unitaid.
“Unitaid is a quasi-governmental advocacy organization funded by the Bill & Melinda Gates Foundation (BMGF) and several countries — France, the United Kingdom, Norway, Brazil, Spain, the Republic of Korea and Chile — to lobby governments to finance the purchase of medicines from pharmaceutical multinationals for distribution to the African poor.
“Its primary purpose seems to be protecting the patent and intellectual property rights of pharmaceutical companies — which, as we shall see, is the priority passion for Bill Gates — and to ensure their prompt and full payment. About 63 percent of its funding comes from a surtax on airline tickets.
“The BMGF holds a board seat and chairs Unitaid’s Executive Committee, and the BMGF has given Unitaid $150 million since 2005. Various Gates-funded surrogate and front organizations also contribute, as does the pharmaceutical industry.
“The BMGF and Gates personally own large stakes in many of the pharmaceutical companies that profit from this boondoggle.Gates also uses Unitaid to fund corrupt science by tame and compromised researchers like Hill that legitimizes his policy directives to the WHO.
“Unitaid gave $40 million to Andrew Hill’s employer, the University of Liverpool, four days before the publication of Hill’s study. Hill, a Ph.D., confessed that the sponsors were pressuring him to influence his conclusion. When Dr. Lawrie asked who was trying to influence him, Hill said, ‘I mean, I, I think I’m in a very sensitive position here …’”
Please take the time to read the article in the top link. You won’t regret it. It’s all right there. Conflicts of interest and researchers cow-towing to ‘the powers that be.’ In this case everyone’s genuflecting to Unitaid.
Best quote:
“Yeah. Well, I don’t know how you sleep at night, honestly.” – Dr. Tess Lawrie
All around the world, disinformation articles are being written and read that claim that there is no evidence that Ivermectin saves lives, reduces hospitalization, or reduces symptoms of COVID-19. Such as this one. INFURIATING.
Every one of those articles is wrong. Every last one.
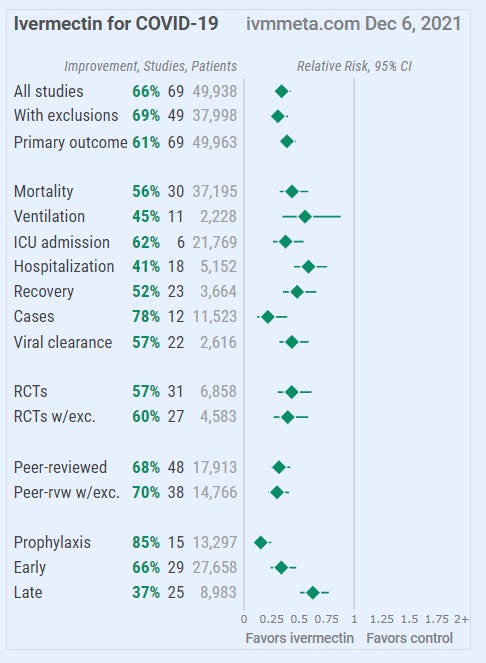
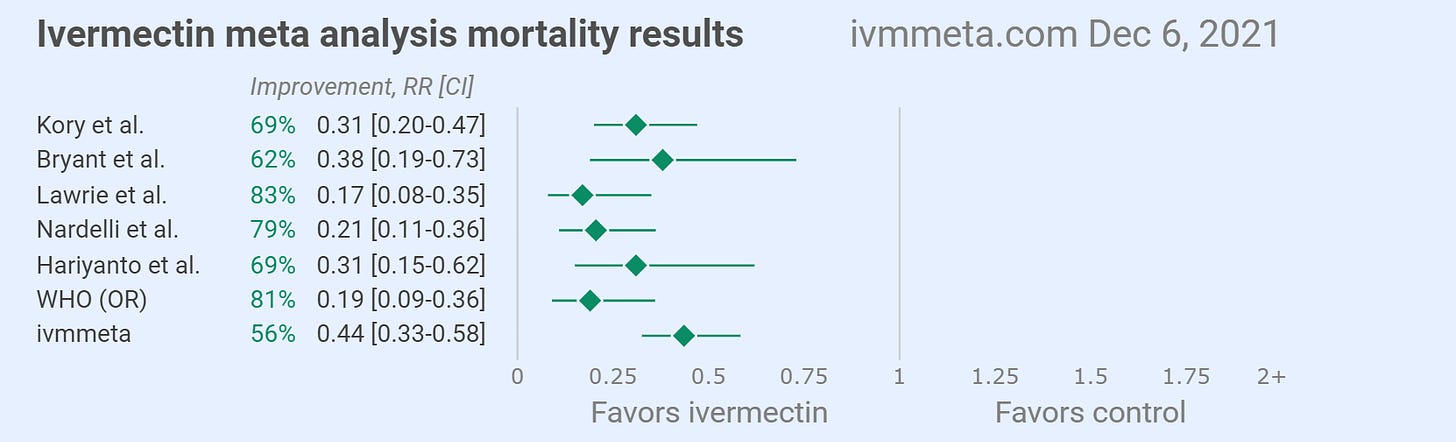
The clinical studies that do exist, and the consilience of the real-world data (RWD), show that early use of ivermectin reduces mortality by somewhere between 50 and 85%.
Patients are suing hospitals in multiple states to have judges decide whether a doctor should be ordered by the court to write a prescription for ivermectin.
In some cases, the family wins, and the patient recovers.
In some cases, the patient dies before a ruling.
This is moronic.
Look, we cannot use “Compassionate Use” laws due to the delay that the paperwork processing by FDA requires.
A legal analyst published their opinion on Montana’s “Right to Try” law. This was reviewed recently in the context of COVID-19. From The Billings Gazette:
In a recent newsletter from the Montana Medical Association obtained by the Montana State News Bureau, Justin Cole, a partner at Garlington, Lohn, & Robinson, PLLP, wrote “in short, the ‘Right to Try’ Act under either federal or state law does not compel a provider to prescribe any particular medication or therapy.”
Cole went on to write the act “does not create substantive rights for a patient to compel a provider to administer any given medication. Rather, it permits a provider to either prescribe or not prescribe, providing immunity for the provider, in either case, based on a narrow set of circumstances that must be met before the Right to Try Act applies.”
The act, Cole continued, “should not supplant a provider’s medical decision-making (whether to prescribe or not prescribe certain medications or therapies) within appropriate standards of care, based on the facts and circumstances presented to the clinician.”
The Montana Right to Try law requires a patient to have received a recommendation for a drug from their treating health care provider, among other requirements.”
Let’s say the analysis is correct. Since public health and the medical juggernaut has decided to misrepresent and ignore the science on the life-saving benefits of ivermectin, the people need to take matters into their own hands and pass bills into laws that in circumstances in which one of the outcomes of disease progression is death, patients (or patients families) can order a physician to write a script for any drug that the family has provided evidence that shows potential reduction in risk of death.
The On Demand laws should also have two additional steps:
no medical board can prosecute any physician for providing a script under these circumstances
doctors and hospitals are free from liability for adverse events or patient’s deaths if the patient invokes their On Demand rights
This has to happen in all states NOW. Consider sending this article to your State Congressional Representative and all of your contacts.
Science shows that ivermectin saves lives. The effect is stronger and more clear than that for remdesivir, and there is far, far more evidence that ivermectin is effective than for molnupiravir.
This video was produced as evidence in a legal case to obtain a temporary restraining order against Sentara Healthcare System. That is where Dr. Paul Marik, the most highly published Critical Care Intensivist in the world, is being prohibited from giving his critically ill ICU patients the medicines in the MATH+ Protocol he believes will save their lives—and for which mountains of scientific evidence exists. The video presents four brief synopses of the experiences of critically ill COVID-19 patients who survived after receiving components of the MATH+ Hospital Protocol in the ICU.
The son of one of the patients in the video had to file a court order compelling the hospital to provide his mother with ivermectin. Another patient was life-flighted to a MATH+ hospital in Houston after being denied the protocol at his local hospital. The story of a man—who was nearly placed on a ventilator but was given MATH+ components instead— is featured; as well as the story of a rapidly deteriorating COVID patient whose attending physician gave his patient ivermectin— and ultimately saved his life.
A Chicago area judge also recently saved a grandfather’s life by telling Edward’s Hospital to “step aside” and prescribe ivermectin. The doctor stated:
“Every day after ivermectin, there was accelerated and stable improvement,” said Dr. Bain, who administered the drug in two previous court cases after hospitals refused. “Three times we’ve shown something,” he told me. “There’s a signal of benefit for ventilator patients.”
Despite our corrupt public health ‘authorities’ and the corrupt American Medical Association (AMA), the American Pharmacist Association (APhA) and the American Society of Health-System Pharmacists (ASHP) threatening doctors and pharmacists, 12,700 doctors and scientists have signed the Rome Declaration and have endorsed ivermectin as a COVID treatment.
Back in December 2020, a GSK whistleblower stated that the mRNA injections cause sterility in 97% of women, and negatively impact men’s sexual organs as well. Then in June 2021, a vaccine researcher admitted that the toxic spike protein in the injections do not stay in the arm muscle as believed, but goes systemically throughout the body and is found circulating in the blood and accumulating in the ovaries,testes, liver, spleen, bone marrow, adrenal glands and crosses the blood brain barrier. It can bind to receptors that are on our platelets & the cells that line our blood vessels. This can cause platelets to clump, leading to clotting, or bleeding.
Now, a toxicologist is also warning about the COVID shots causing sterility.
**Note**
The article below states more than 300 between ages 12-18 have died of myocarditis due to COVID shots. It doesn’t mention the fact there have been 2,809 fetal deaths in the past 11 months compared to 2,168 fetal deaths following ALL FDA-approved vaccines for the past 30+ years. This is an 80% increase in fetal deaths recorded in VAERS, and yet the CDC & FDA continue to recommend them to pregnant women and nursing mothers. Hello? Go here for an excellent article and video on the topic. And yesterday, Vietnam province HALTS Pfizer injections after 120 students are hospitalized for nausea, high fever, and breathing difficulties. Of the 120, 17 experienced even more severe reactions that require a greater level of medical care and monitoring.
Janci Chunn Lindsay, Ph.D., a molecular biologist and toxicologist, has called for an immediate halt to COVID-19 mRNA and DNA vaccines due to multiple safety concerns
There’s credible concern that the COVID jabs will cross-react with syncytin (a retroviral envelope protein) and reproductive genes in sperm, ova and placenta in ways that may impair fertility and reproductive outcomes
In the case of the COVID shots, important animal studies that help ascertain toxic and systemic effects were not done. We’re now seeing danger signals that are not being heeded. Preliminary safety results of mRNA COVID shots used in pregnant women, published in April 2021, revealed an 82% miscarriage rate when the jab was administered during the first 20 weeks of pregnancy
CDC data reveal more than 300 children between the ages of 12 and 18 have died from myocarditis, a now-recognized side effect of the COVID jab, yet the shot is now authorized for children as young as 5
Since the COVID gene therapies do not prevent infection, but only lessen symptoms, they are actually a treatment, not a prevention. And there are far safer and more effective treatment available, including nebulized peroxide, ozone therapy, and hydroxychloroquine and ivermectin regimens
Janci Chunn Lindsay, Ph.D., is a molecular biologist and toxicologist and director of toxicology and molecular biology for Toxicology Support Services LLC. April 23, 2021, she delivered a three-minute public comment to the U.S. Centers for Disease Control and Prevention’s Advisory Committee on Immunization Practices (ACIP).
Her expertise is analysis of pharmacological dose-responses, mechanistic biology and complex toxicity dynamics. In her ACIP comment (see video below), Lindsay described how she aided the development of a contraceptive vaccine in the 1990s that ended up causing unintended autoimmune destruction and sterility in animals which, despite careful pre-analysis, had not been predicted. She explains:
“We were developing what was meant to be a temporary contraceptive vaccine, which was very attractive because it prevented fertilization rather than preventing implantation — or it should have; that was the idea.
Unfortunately, even though quite a bit of analysis was done in different animal models to make sure that it did not have an autoimmune action, it did end up having an autoimmune action and caused complete ovarian destruction.
Now it’s used in that manner [for permanent sterilization] in dogs, cats and other animals. So, that’s a cautionary tale of how animal studies can help us avoid mistakes in humans when they’re used properly, and when proper animal studies are done.”
We May Be Sterilizing an Entire Generation
At the time, she called for an immediate halt to COVID-19 mRNA and DNA vaccines due to safety concerns on multiple fronts. In particular, she noted there is credible concern that they will cross-react with syncytin (a retroviral envelope protein) and reproductive genes in sperm, ova and placenta in ways that may “impair fertility and reproductive outcomes.”
Not a single study has disproven this hypothesis, she noted. Another theory of how these injections might impair fertility can be found in a 2006 study,1 which showed sperm can take up foreign mRNA, convert it into DNA, and release it as little pellets (plasmids) in the medium around the fertilized egg.
The embryo then takes up these plasmids and carries them (sustains and clones them into many of the daughter cells) throughout its life, even passing them on to future generations. It’s possible that the pseudo-exosomes that are the mRNA contents would be perfect for supplying the sperm with mRNA for the spike protein.
So, potentially, a vaccinated woman who gets pregnant with an embryo that can (via the sperms’ plasmids) synthesize the spike protein according to the instructions in the vaccine, would have an immune capacity to attack that embryo because of the “foreign” protein it displays on its cells. This then would cause a miscarriage.
“We could potentially be sterilizing an entire generation,” Lindsey warned. The fact that there have been live births following COVID-19 vaccination is not proof that these injections do not have a reproductive effect, she said.
Lindsay also pointed out that reports of menstrual irregularities and vaginal hemorrhaging in women who have received the injections number in the thousands,2,3,4 and this too hints at reproductive effects. In this interview, we dive deeper into these mechanisms.
Something Has Gone Horribly Wrong
When asked how she ended up getting so passionately involved in this controversial topic, Lindsay replies:
“I became interested in the issue because science was not making sense anymore. For instance, herd immunity was being redefined. Herd immunity has always been defined by a combination of the natural infection with vaccination practices that work.
Suddenly, herd immunity was changed to only being attained through vaccination, and I knew that that was horribly wrong, yet it was being touted everywhere. It was certainly being touted by [Dr. Anthony] Fauci and others who know better.
Other things were also happening within the scientific world. Two of our top tier journals, The New England Journal of Medicine and The Lancet, published fraudulent hydroxychloroquine studies.
Ostensibly they had gone through peer review, and it should’ve been easy to catch the errors in these studies — as well as many other studies that allow for the emergency use authorization of these gene therapies — and they weren’t caught.
Hydroxychloroquine and ivermectin are very safe. They’ve been used safely in pregnant women and children for decades, and suddenly they were being vilified as if they were not safe. As a toxicologist, I know they are safe.
So, these types of things really piqued my attention along with all of the stuff going on in the background with respect to the New World Order and the agenda set by the World Economic Forum, and our joining into this, along with so many other countries, despite their intent, their materials, which claim life will be changed as we know it.
We will ‘own nothing and be happy [about it]’ in just a few years. All of these things converged for me into a sense that something had gone horribly wrong, that our regulatory institutes were captured, and that our scientific journals were not being honest anymore …
There’s a paper that came out in 2006 called ‘Disease Mitigation Measures in the Control of Pandemic Influenza.’5 This paper is wonderful. It goes through World Health Organization and CDC guidelines on how to react during a pandemic, what works and what doesn’t work, and it clearly points out that masks don’t work.
They knew at that point they don’t work. Travel lockdowns don’t work. It’s a wonderful paper to basically go through everything we have done in response to this pandemic, and say that’s an inappropriate way to respond, and we have scientific data that proves it. So, I encourage everybody to go back to that paper … to really see how crazy we’ve gotten in the mandates that make no scientific sense at all.”
Massive Danger Signal Is Being Ignored
As noted by Lindsay, in the case of the COVID shots, important animal studies that help ascertain toxic and systemic effects were not done. But we’re still seeing danger signals that need to be heeded.
Preliminary safety results of mRNA COVID shots used in pregnant women, based on data from the V-Safe Registry, were published in The New England Journal of Medicine (NEJM) in April 2021.6
According to this paper, the miscarriage rate within the first 20 weeks of pregnancy was 12.5%, which is only slightly above the normal average of 10%. (Looking at statistical data, the risk of miscarriage drops from an overall, average risk rate of 21.3% for the duration of the pregnancy as a whole, to just 5% between Weeks 6 and 7, all the way down to 1% between Weeks 14 and 20.7)
However, there’s a distinct problem with this calculation, as highlighted by Drs. Ira Bernstein and Sanja Jovanovic, and Deann McLeod, HBSc, of Toronto. In a May 28, 2021, letter to the editor, they pointed out that:8
“In table 4, the authors report a rate of spontaneous abortions <20 weeks (SA) of 12.5% (104 abortions/827 completed pregnancies). However, this rate should be based on the number of women who were at risk of an SA due to vaccine receipt and should exclude the 700 women who were vaccinated in their third-trimester (104/127 = 82%).”
In other words, when you exclude women who got the shot in their third trimester (since the third trimester is AFTER week 20 and therefore should not be counted when determining miscarriage rate among those injected BEFORE week 20), the miscarriage rate is a whopping 82%.
Of those 104 miscarriages, 96 of them occurred before 13 weeks of gestation, which strongly suggests that getting a COVID shot during the first trimester is an absolute recipe for disaster.
“They concluded, very fraudulently, in my estimation, that it was safe to vaccinate in the third trimester, and said nothing about the clear safety signal in the first trimester,” Lindsay says. “It’s just so dishonest, so purposefully manipulative.”
As for the women who get the shot in their third trimester, there’s still no telling what the ramifications might be in the long term.
“We just don’t know, and that’s the problem,” Lindsay says. “There are all kinds of things that can go wrong with these types of therapies, and have gone wrong in animal models. We don’t know what will happen in the future for these women or for their children. This could be passed on.
We’re seeing now a lot of mention of constitutive expression, whether that’s failure of the mRNA to degrade or integration into the genome. That’s still being investigated.”
Children Are Dying From COVID Jab-Induced Myocarditis
Lindsay goes on to cite a CDC report that shows more than 300 children between the ages of 12 and 18 have died from myocarditis, a now-recognized side effect of the COVID jab.
We also know, based in part on whistleblower testimony, that more than 50,000 Americans have died within three days of these shots,9,10 and that’s just from one database (the Vaccine Adverse Event Reporting System or VAERS). There are 10 other databases that feed into the CDC that the public does not have access to.
“This many deaths, it’s appalling and alarming,” Lindsay says. “Dr. Peter McCullough says the safety signal for typical vaccines, other than this gene therapy, would’ve been around 186 total. We’re now up to [17,128 reported deaths in VAERS, as of October 15, 202111], but they haven’t paused this in children.
They have not paused this while they’re investigating the myocarditis. Instead, they’re pushing it even more. Has this ever happened before? I mean, does this happen in a scenario where the population is at essentially zero risk for the disease? …
The cardiac deaths alone in perfectly healthy kids, and pulmonary embolism deaths in kids, should’ve stopped this. They are at no risk [from COVID-19]. There is no reason to vaccinate them, absolutely zero reason to give them these gene therapies because they’re at no risk [from the infection] …
You know [the shot] is causing heart failure, pulmonary emboli, cardiac arrest in healthy teenagers, and you’re not pausing to investigate the risk versus reward scenario? Something is horribly wrong.
Unfortunately, our regulatory institutions are not going to stop this. They’ve clearly been captured. It’s something that we’re going to have to do. Vaccinated and non-vaccinated must stand together to say, ‘No, you’re not going to experiment on my children’ …
With the RSV vaccines and the dengue fever vaccines, we had deaths in children that were much fewer in number that stopped those campaigns as well. It’s very, very clear — if you don’t get anything else out of this interview with me, understand that our regulatory and safety agencies have been captured.
They’re not doing their job to protect you or your children. You must not trust them, because they are not doing anything according to practices that used to be adhered to. It’s clear that they’ve been captured and compromised, and I hate to say that. I really hate to say that, but that’s the only logical answer …
We have all these breakthrough cases too. If you look at Michigan, and I’ve actually been privy to some other databases of true death numbers in different states [comparing] those who are vaccinated and those who don’t, and I can tell you that the media is lying with respect to the unvaccinated making up 99% of hospitalizations. They’re absolutely lying.”
How the Jab Can Sabotage Fertility
Getting back to the fertility issue, Lindsay cites a Singaporean study that examined the COVID jab’s ability to interfere with fertility by triggering anti-syncytin-1. The study included 15 women, two of whom were pregnant. She explains:
“They did something that I had asked to be done a long time ago, which was to measure anti-syncytin antibodies in an ELISA test. The syncytins are conformationally and genetically similar to the [SARS-CoV-2] spike protein, this fusogenic spike protein.
The thought by several experts was that you could have an autoimmune reaction to the syncytins by developing an immune reaction to the spike protein, and then that would prevent successful pregnancy.
But the syncytins are also important in a number of psychological diseases, such as bipolar depression. They’re important on autoimmune disease, lupus and multiple sclerosis. They are present in skeletal muscle. There’s some association with breast cancer. They’re really important ancient retroviral elements.
What this study found was extremely interesting. It found that every single one of these women who had been vaccinated developed autoantibodies to syncytin-1. Now, the authors kind of dismissed this and said, ‘Oh, but we don’t think that those antibodies were high enough to mean anything.’
But there was a clear difference between the pre-gene therapy sera [blood sample] and the post-therapy sera … What it shows is that there is an antibody response, and the significance of it, we don’t really know. But every single one of the women developed an antibody response that was different from the baseline … and I think that’s probably what’s causing some of these pregnancy losses.”
Are COVID Jabs a Population-Wide Immunocontraceptive?
When asked what she thinks the motive behind this mass injection campaign might be, considering the clear danger signals, she replies:
“I certainly think that to discount that it is a form of population-wide contraceptive would be naïve. There’s a paper that came out in 2005. It’s called ‘Evaluation of Fusogenic Trophoblast Surface Epitopes as Targets for Immune Contraception.’12
This paper tried to find contraceptive peptides in persons that had infertility problems already that were isolated to placentation. So, it was taking a backwards approach, getting the sera from people who had fertility problems and trying to see what they had antibodies to that was causing the fertility problems …
This work was sponsored by the WHO and the Rockefeller Foundation [and the National Institutes of Health]. No surprise there. It was then picked up by a company called AplaGen that took it to patent in 2007.
These are 12-mer peptides, and there’s a series of eight of them that can be used to induce sterility. When they patented it, they also said that it could be used to ameliorate sterility. Interestingly, it was also associated with all of the things that we know syncytin is associated with, — lupus, skeletal muscle disorders, bipolar depression [and] a number of other things.
Even though they don’t name syncytin proteins as the proteins that are targeted, they worked backwards from these peptides, and then said they were a series of other proteins. Sometimes we know that proteins can be called the same thing in different discovery realms. So, that’s going to take more research, but it was certainly interesting to me.
What it really points out is that there were efforts to use peptides or immunocontraceptive means at the placental trophoblast interface to cause sterilization … So, it would be naïve to think that this was not on the plate for future use.”
How Long Will Effects Last?
An obvious question is, how long might these effects last? Are they lifelong? Of course, any answer we come up with here will be hypothetical only, as the studies simply haven’t been done. That said, with her background in molecular biology, Lindsay is at least qualified to theorize.
The mRNA is extremely fragile, which is why a nanolipid with polyethylene glycol delivery system is used. In addition, about 30% of the mRNA has been genetically modified to decrease degradation. As a result, the mRNA being injected is magnitudes sturdier than natural mRNA.
What’s more, the nanoliposomes allow for superior penetration into tissues, and we now know it spreads throughout your body. It doesn’t stay in your deltoid. How long this modified and stabilized mRNA remains viable is still unknown, however. A corollary question is whether this mRNA might be integrated into your genome to become a permanent fixture.
“The answer is, we don’t know for sure,” Lindsay says. “Of course, with the adenoviral vector vaccines [Janssen and AstraZeneca], they’re more prone to integration into the genome. We know that from animal studies and past experiments.
With the mRNA technology, we’ve never stabilized something like this in this manner. What we do know is that recent studies have come out — Bruce Patterson’s group and another group — both came out with the finding that the spike protein is being expressed, [it’s] present on monocytes, as far out as from the time that the people were given the gene therapy.
So, that gives us an indication that it is resistant, for sure, to degradation. The longer it stays around, and is resistant to degradation, the more likely that genomic integration events can occur. But I don’t know the answer to whether or not it will become a permanent feature.”
Make a Rational Choice
As explained by Lindsay, no coronavirus vaccine has ever been successfully brought to market, despite 20 years of effort. All have failed due to antibody dependent enhancement, where the vaccination facilitates infection rather than protects against it.
Now, we’re to believe a safe and effective coronavirus “vaccine” has been developed in mere months. She also makes another important point. Since the COVID gene therapies do not prevent infection, but only lessen symptoms, they are actually a treatment, not a prevention.
And there are far safer and more effective treatments available, including nebulized peroxide, ozone therapy, and hydroxychloroquine and ivermectin regimens.
“If all these gene therapies do is lessen the diseases, then they’re not a vaccine, they are a treatment,” she says. “They are a treatment that you don’t know the mid- or long-term consequences of, that have already caused a number of adverse events. You have to use your common sense to say, why wouldn’t I use a treatment that has been known to be safe over 70 years as opposed to one that is brand-new, that is experimental?”
Other Safety Signals
Aside from fertility issues, heart inflammation and blood clots, another side effect seen among the fully “vaccinated” is de novo Type 1 diabetes in adults. This makes sense considering Pfizer’s biodistribution study showed the spike protein accumulates in the pancreas. The natural SARS-CoV infection can also have this effect.
Type 1 diabetes is a serious problem, as it leaves you metabolically handicapped for the rest of your life, dependent on extremely costly insulin injections. Doctors are also reporting an increase in pancreatic cancer and acute myeloid leukemia.
Where Do We Go From Here?
“Many scientists and physicians feel as I do, and are trying to figure out where we go from here,” Lindsay says, “because our typical safety and regulatory agencies have been compromised.” She believes we need to continue sharing the data and facts that mainstream media refuse to discuss, and continue urging those who have received the jab to at least protect their children.
“We need to stand together as one people and say we’re not going to accept this, especially not for our children, and try to get to the bottom of this and see what’s really behind all these efforts. Is it really about a virus, or is it more about other political motivations and campaigns, as it seems to be?”
I’m less optimistic about the idea of breaking through the brainwashing to get people to not sacrifice their children. So many have their minds set in cement with the wrong information. They could have their brother, sister, mother or father get the shot and die with the needle still on their arm, and they’d still go out to get a booster the next day.
I’ve seen it so many times. My friends, their parents, their siblings and loved ones — there’s this barrier that prevents any openness to new information. They’ve made their decision.Mark Twain said, “It’s far easier to fool someone than to convince them they’ve been fooled.” And it’s true.
So, while I agree that we must keep trying, and have faith that truth will prevail, I also think it’s important to have realistic expectations. We’re up against the most effective propaganda campaign in modern history. It’s psychological warfare at its best.
From my perspective, being a pragmatic realist, I believe the best strategy is to reinforce and support those who didn’t buy into the propaganda narrative to begin with, because they don’t struggle with that cognitive dissonance. If we stick together and support each other, so none of us get sucked into the lunacy, then we can at least preserve the control group.
Ultimately, the truth will come out, as long as we can preserve the control group. In a year or two, or three, we will clearly be able to tell how devastating this intervention was simply by comparing the two groups. I suspect those who got the shot will be severely crippled in various ways, and those who didn’t get the shot will have far better health in comparison.
“I absolutely agree that we have to preserve a control group. We also have to think of ways that we can help those that have been injured. I brought this out in a letter I recently wrote, advocating for Dr. McCullough.
People who have gotten this inoculation, if they have mid- to long-term effects, if you deny that any adverse effects are really going on, then the efforts going into those treatments for people who are having side effects are not going to be there. We have to accept that these [side effects] are real in order to help people who have already taken the inoculations, and I believe we have to try.”
ACTION ALERT: Click To Tell Your Senator To Vote No On The Federal Tracking System
This bill paves the way for state and local health departments, as well as public and private health care providers, to share personal health data with the federal government. The bill has hundreds of millions of taxpayer dollars allocated to the tracking system’s success. It’s easy to see this bill is meant to strengthen the enforceability of federal vaccine mandates and normalize vaccine-status discrimination. Let us be clear, this is the tracking system to which the government can tie a digital passport.
Click now to tell your U.S. senators that we are not for sale. Americans know the importance of privacy and are joining together to say no to taking and sharing our personal, private data. Share this campaign with 10 of your friends, as we must push back on this bill and it’s agenda.
TOUCHED BY LYME: “Deep Places” explores one man’s Lyme fight
Dorothy Kupcha Leland
Dec. 1, 2021
Ross Douthat was a busy man.
In addition to his regular opinion column in the New York Times, he wrote books, gave speeches, traveled, interviewed people, and was often interviewed himself.
In 2015, he and his wife had two kids and another on the way. They decided to leave Washington DC and relocate to Connecticut, where they had both grown up and still had family.
They found a rambling old country house that they fell in love with. After walking through the dwelling and briefly strolling around the property surrounding it, they made an offer which was accepted. Then, they returned to DC to prepare for the move.
And that’s when Douthat’s life changed dramatically.
It started with a stiff neck and an enlarged lymph node. (“Nothing to worry about,” said an internist.) It progressed to migrating pain that moved from his head to his spine to his chest to his arms and legs. (“Maybe drink more Gatorade–for the electrolytes,” suggested a neurologist.) Other specialists prescribed sleeping pills and antidepressants. (“Stress,” they declared. “Too much going on in your life.”)
The reason or the symptom?
“I did feel stressed,” Douthat remembers. “But the illness felt like the reason rather than the symptom.”
He was tested for Lyme disease a couple of times, with negative results.
Meanwhile, the bizarre symptoms continued. Before he and his family left Washington, crushing chest pain sent him to the emergency room on two different occasions. Doctors there found nothing wrong with him. He followed up with various specialists, who theorized that his symptoms were psychosomatic.
As one infectious diseases doctor put it: “Look, I know it’s hard to see, but you should feel happy. It’s a good thing not to have a disease, you know…. And, if you need a mental health referral, we can definitely help with that.”
Caught in the middle
In his recently published book, The Deep Places: A Memoir of Illness and Discovery, Douthat writes about being caught between what he was feeling in his body and what the doctors confidently proclaimed didn’t exist.
By this point, I was deep into self-doubt about the reality of my experience. On the one hand, there was the pain, the burning, the vibrations, the feeling of invasion; I knew I’d never felt anything like this before. But what were mere feelings set against the certainties of so many doctors, the repeated negative readings of my blood?
The family moved to the big country house, Douthat’s condition continued to deteriorate, and he consulted new doctors in Connecticut.
First stop was a psychiatrist, who listened, took notes, and then surprised Douthat by saying, “I’m pretty sure you have a tick-borne disease, Ross.” (Had a tick nailed him during his initial inspection of the Connecticut property? The timing certainly seemed right.)
This sent him in search of Lyme specialists and to dig even deeper into learning about the illness: the problematic testing, difficulty of diagnosis, controversial treatments, and how mainstream medicine looks at Lyme with a mixture of disdain and denial.
Frustrating illogic
He notes the frustrating illogic that Lyme patients face:
If you were a positive case with lingering, persistent symptoms after treatment, then your Lyme officially belonged to the past, and you no longer had a CDC-recognized disease. Instead, you had something called Post-Treatment Lyme Disease Syndrome (PTLDS), and the CDC’s advice for anyone suffering through it was to basically keep on suffering.
And he wonders:
If someone has an illness, takes a drug to treat it, and afterward retains exactly the same symptoms, why wouldn’t you assume that they have simply continued to have the same disease? Why invent a mysterious “post-disease syndrome” to explain what is experienced by the patient as one continuous sickness?
Douthat consulted different Lyme specialists that prescribed various antibiotic combinations. Some helped in some ways—but nothing got to the heart of the matter. He was still desperately ill.
At that point, Douthat started branching out into more alternative realms such as muscle testing, magnets, and a Rife machine—along with continuous heavy-duty prayer—and by the close of 2019, he was doing much better. “2020, I told myself, is going to be a good year.”
Then he and other family members got nasty cases of COVID. And he writes:
The coronavirus era soon came to feel like a shattered mirror of the tick-borne epidemic and its controversies, with different pieces of the Lyme wars reflected and refracted in different aspects of the world-wide COVID crisis.
In the following excerpt of The Deep Places, Douthat expands on this comparison between Lyme disease and COVID-19. (See top link for book excerpt)
Prominent deniers of chronic Lyme
Douthat recently published three articles in the New York Times that drew on the experiences chronicled in this book.
On November 27, the newspaper published seven letters to the editor in response to Douthat’s trio of articles. Three of the letter writers are prominent IDSA members, all well known deniers of chronic Lyme. Another one consults for Big Pharma. Any guesses about what those guys had to say about Douthat’s columns?