Dr. Carrie Madej D.O. discusses the COVID-19 vaccine in this ground-breaking, informative documentary. It is critical you educate yourself and others on this frightening technology that can monitor, track, and potentially control your behavior.
Download the video, so you can upload it everywhere: Facebook, Youtube, Bitchute, etc.
There are also other articles of interest within the link as well.
For anyone reading the posts on this website, the information Dr. Madej presents is not new, but it’s been carefully collected and presented within this one easy to understand video. Please share with others.
Here’s the articles corroborating her information:
Milwaukee County’s chief medical examiner says the state’s coronavirus death total includes more than 100 people who had COVID-19 but died primarily of other causes.
The difference is significant and possibly confusing.
As of Wednesday, the state reported 532 COVID-19 deaths in Milwaukee County, but the county’s COVID dashboard lists 428 — a difference of 104 deaths. (See link for article)
______________________
**Comment**
The confusion and fear-mongering continue – based on fallacies.
The inflation problem goes back to the beginning of the pandemic.
It’s the comorbidity effect — the simultaneous presence of two chronic diseases. When serious health conditions like diabetes, hypertension, and cardiovascular disease meet COVID-19, well, it can be like throwing gasoline on a fire.
But that doesn’t necessarily mean COVID is the primary cause of death.
As Wisconsin Spotlight reported in May, Milwaukee County Medical Examiners office data obtained by CRG Network (Citizens for Responsible Government) found that residents 65 and over made up 75 percent of 193 COVID-19-related deaths in Milwaukee County. All but four of the victims had at least one underlying health condition.
Underlying conditions included cancer, COPD, heart attacks, stroke, congestive heart failure. Many of the victims were obese, many morbidly obese. The No. 1 comorbidity among the deceased was high blood pressure; No. 2 was diabetes.
“Moreover, 78% of intensive care unit (ICU) admissions and 94% of deaths (where complete information on underlying conditions or risk factors was available) occurred in those with at least one underlying health condition,” the Lancet Diabetes & Endocrinology reported in May.
DHS acknowledges that they’re dumping comorbidity deaths into the COVID-19 pot.
Gilead Sciences Update on Supply and Distribution of Veklury® (remdesivir) in the United States
— Supply of Veklury Is Meeting Real-Time Demand in the U.S. —
— Clinical Benefits of Veklury Consistently Demonstrated Across Three Randomized, Clinical Trials Are Now Available to All Clinically Appropriate Hospitalized COVID-19 Patients in the U.S. —
— Veklury Distribution Has Transitioned from the U.S. Government to Gilead —
FOSTER CITY, Calif.–(BUSINESS WIRE)– Since the COVID-19 pandemic began, Gilead has worked diligently to ramp up production and rapidly expand the supply of our investigational antiviral drug Veklury® (remdesivir) by making significant investments to increase internal manufacturing capacity, expand our contract manufacturing network and implement process improvements. While working to increase our manufacturing capacity over these past months, the company also donated 1.5 million vials of Veklury and provided clinical drug supply at no cost for evaluation as an investigational agent in clinical trials around the world. As a result of the decision to make early investments to increase Veklury manufacturing efforts, Gilead is now meeting real-time demand for Veklury in the United States and anticipates meeting global demand for Veklury in October, even in the event of potential future surges of COVID-19.
Starting on October 1, Gilead will be responsible for distributing Veklury in the United States upon conclusion of the previous distribution agreement with the U.S. Federal government. To ensure stable management of drug supply in the near term, AmerisourceBergen will continue to serve as the sole U.S. distributor of Veklury through the end of this year and will sell the product directly to hospitals. This distribution model closely reflects the traditional model hospitals use to procure medicines. Hospitals will control the quantity of Veklury that they order, enabling them to have ample, predictable supply of Veklury in advance of any anticipated increase in COVID-19 incidence. (See link for article)
Source: Gilead Sciences, Inc.
__________________
**Comment**
Oh goody. Now public officials can reclaim their lost profits when Remdesivir bombed for Ebola.
Fauci has financial ties to new drugs that are being pushed through the pipeline as alleged remedies for the Wuhan coronavirus (covid-19), which explains his anomalous opposition to HCQ, which he once promoted.
Every doctor and medical professional who has bravely come forward in support of HCQ during the current pandemic, by the way, despite the deep state’s opposition to it, has faced ridicule and persecution.
Gilead was able to strongarm the federal government back in 2009 into buying up stocks of Tamiflu, enriching the pocketbooks of not just Rumsfeld but also George Schultz, a former U.S. secretary of state. Rumsfeld chaired Gilead while Schultz sat on the company’s board.
“The interesting part is, Gilead was part of the vaccine lobby at whose behest the WHO faked the H1N1 pandemic in 2009, and kept it a secret from people until committees were setup (sic) which exposed the entire racket,” reports Great Game India.
As a background, Gilead appears to be a creation of the military-industrial complex with a dark history of bioterrorism, according to Great Game India.
Despite its benign image as a mere pharmaceutical manufacturer, Gilead has been accused of engaging in illegal bioweapons research programs in the country of Georgia, where 73 people are said to have died at the hands of Gilead researchers who were testing deadly chemicals on them.
And public officials and the media wonder why the public no longer trusts government employees and their directives…..
A former FDA commissioner and a vaccine co-inventor told a House panel on Wednesday that they are confident in the FDA’s review process for vaccines…..
Pressure from the administration to approve drugs such as hydroxychloroquine and convalescent plasma through an EUA “without clear evidence of safety or efficacy” has created concern that “the same low standards” would apply to a vaccine, he said.
Here’s the real clincher from Dr. Paul Offit, co-inventor of the rotavirus vaccine:
“If COVID-19 vaccines are released before they’re ready to be released, you will hear from these people, and … from people like Drs. Francis Collins and Tony Fauci who are trusted by the American public,” he said.
Well, I don’t know what ‘public’ is trusting these people but it sure isn’t me.
A woman started leaking cerebral fluid out of her nose after she received a COVID-19 test administered with a nasal swab, according to a new case report. (JAMA Otolaryngology/University of Iowa Hospitals and Clinics)
TORONTO — A woman with an undiagnosed skull defect started leaking cerebral fluid out of her nose after she received a COVID-19 test administered with a nasal swab, according to a new case report.
The report, published Thursday in the journal JAMA Otolaryngology – Head & Neck Surgery, described a singularly unusual situation, where the nasal swab disturbed a mass in the woman’s nasal cavity containing cerebrospinal fluid and brain tissue. (See link for article)
_______________________
**Comment**
The article states that it’s not uncommon to screen patients for COVID before elective surgeries, which is what happened here.
The patient had a COVID test prior to hernia surgery. A CT scan done in 2017 showed the skull issue existed then, but was misdiagnosed as paranasal sinus disease (inflammation of the sinuses). She also had a medical history of high pressure in the brain due to CSF buildup.
They theorize the swab itself did not cause the hole in the patient’s bone.
The article states that CSF leaks are ‘rare’ but sometimes misdiagnosed as migraines or other headaches.
Important quote:
“As the number of daily COVID-19 nasal and nasopharyngeal swab specimen collection procedures increases, a greater burden is placed on the health care system to properly train clinicians and even the general public to safely perform nasal and nasopharyngeal swab testing,” the report stated.
They suggested that alternative testing methods be used for patients with a history of sinus issues or skull base defects. (I would argue Lyme/MSIDS patients fit into this group)
The patient developed a runny nose, metallic taste, headache, neck stiffness, sensitivity to light, and vomiting.
I post this article not to scare the bejesus out of you but for your illumination, because as you know, things are often not as ‘rare’ as authorities often state. Also, Lyme/MSIDS patients often have a lot of symptoms in their head including a ton of inflammation. They are also battling a brain infection(s) that can cause major brain swelling.
I’ve written about this before, but I personally had this. It was one of my marquee symptoms that took years to get on top of. Sticking anything high up into the nasal cavity for Lyme patients seems risky to me. It is my opinion that extra precautions should be taken with Lyme/MSIDS patients who are having anything done in the nasal cavity, as well as in the mouth (dental work) due to the proximity of pathogens in the brain.
While health experts in the U.S. and many other countries are warning of a second wave of COVID-19 as we move into fall and winter, Sweden does not expect a reemergence of widespread contagion as herd immunity appears to have been established
Rather than locking down the whole country, Sweden only temporarily closed high schools and colleges, banned gatherings of more than 50 people and asked seniors over the age of 70 to self-isolate
Anders Tegnell, the chief epidemiologist in charge of Sweden’s coronavirus response says the primary goal has been to slow the spread to avoid overwhelming medical services
As of mid-September 2020, Sweden’s infection rate had reached an all-time low and COVID-19 related deaths were at zero; 22 of 31 European countries, most of which enacted strict lockdowns, had higher infection rates
As a result of their sensible approach to the pandemic, Sweden has also largely escaped the financial ruin and skyrocketing mental health problems experienced in other areas, including the U.S.
While health experts in the U.S. and many other countries are warning of a second wave of COVID-19 as we move into fall and winter, one nation that does not appear to worry about a resurgence of people testing positive for the virus and/or hospitalizations and deaths attributable to COVID-19 is Sweden.
Anders Tegnell, the chief epidemiologist in charge of Sweden’s coronavirus response, has stated1he does not believe Sweden will see a second wave with widespread contagion as the country is seeing a rapid decline in positive tests, indicating herd immunity has been achieved.2
Sweden’s Trajectory Shows How Unnecessary Lockdowns Are
Sweden, one of the few countries that did not shut down schools and businesses or mandate strict social distancing or mask wearing rules, choosing the route of natural herd immunity development instead, has been sharply criticized by many over the past several months.
Rather than locking down the whole country, Sweden only temporarily closed high schools and colleges, banned gatherings of more than 50 people and asked seniors over the age of 70 to self-isolate. All others were simply asked to respect physical distancing recommendations, and to work from home whenever possible.
Tegnell told The Guardian3 that the primary goal has been to slow the spread to avoid overwhelming medical services. As you may recall, this was the original plan just about everywhere.The difference is, Sweden actually stuck to the original goal, whereas other nations have twisted response plans to, apparently, prevent infection transmission altogether, even among those for whom the risk of such an infection is vanishingly minor.
At this point, Sweden is proving to be a valuable test case, demonstrating just how ineffective and unnecessary the global shutdowns have been. Countries that enacted draconian freedom-restrictions are faring no better than Sweden, which allowed its citizenry to largely go about their business as usual. As noted by the National Review back in April 2020:4
“In theory, less physical interaction might slow the rate of new infections. But without a good understanding of how long COVID-19 viral particles survive in air, in water, and on contact surfaces, even that is speculative …
It is possible that the fastest and safest way to ‘flatten the curve’ is to allow young people to mix normally while requiring only the frail and sick to remain isolated.
This is, in fact, the first time we have quarantined healthy people rather than quarantining the sick and vulnerable. As Fredrik Erixon, the director of the European Centre for International Political Economy in Brussels, wrote5in The Spectator(U.K.) last week:
‘The theory of lockdown, after all, is pretty niche, deeply illiberal — and, until now, untested. It’s not Sweden that’s conducting a mass experiment. It’s everyone else.'”
UK Enacts New Restrictions in Face of Mounting ‘Cases’
Despite Sweden’s tactical success, many countries are continuing to enforce and even enact new lockdown restrictions due to new upticks in positive tests. For example, September 22, 2020, British Prime Minister Boris Johnson announced6 new restrictions, which he predicts may remain in place for the next six months, warning that if Britons fail to follow the rules, they may be looking at a second lockdown.
This, even though there’s no concomitant rise in hospitalizations or deaths.
The vast majority of people testing positive at this point remain asymptomatic.
Johnson’s announcement came on the heels of dire — and completely implausible — predictions by professor Chris Whitty and Sir Patrick Vallance, whose models predict the U.K. may be looking at 50,000 new “cases” (i.e., positive tests) per day by mid-October unless new restrictions are put into place.
In the video below, journalist Ben Swann reviews why such predictions are likely to be a gross overestimation, and one that is unlikely to result in a dramatic increase in hospitalizations or deaths.
Sweden’s Death Rate Hits Zero
Meanwhile, in Sweden, infection rates have reached an all-time low. As reported by The Guardian, September 16, 2020:7
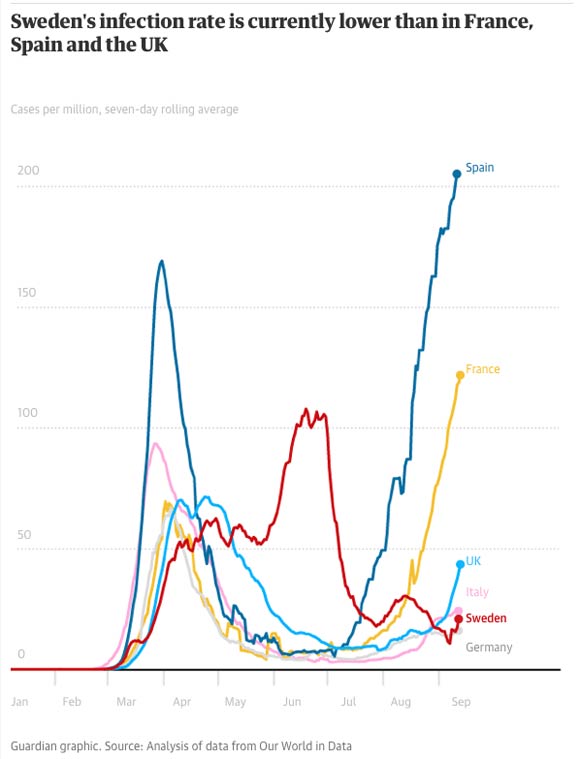
“According to the European Centre for Disease Prevention and Control (ECDC), the Scandinavian country’s 14-day cumulative total8 of new caseswas 22.2 per 100,000 inhabitants on Tuesday, against 279 in Spain, 158.5 in France, 118 in the Czech Republic, 77 in Belgium and 59 in the UK, all of which imposed lockdowns this spring.
Twenty-two of the 31 European countries surveyed by the ECDC had higher infection rates. New cases, now reported in Sweden only from Tuesday to Friday, are running at roughly the rate seen in late-March, while data from the national health agency showed only 1.2% of its 120,000 tests last week came back positive …
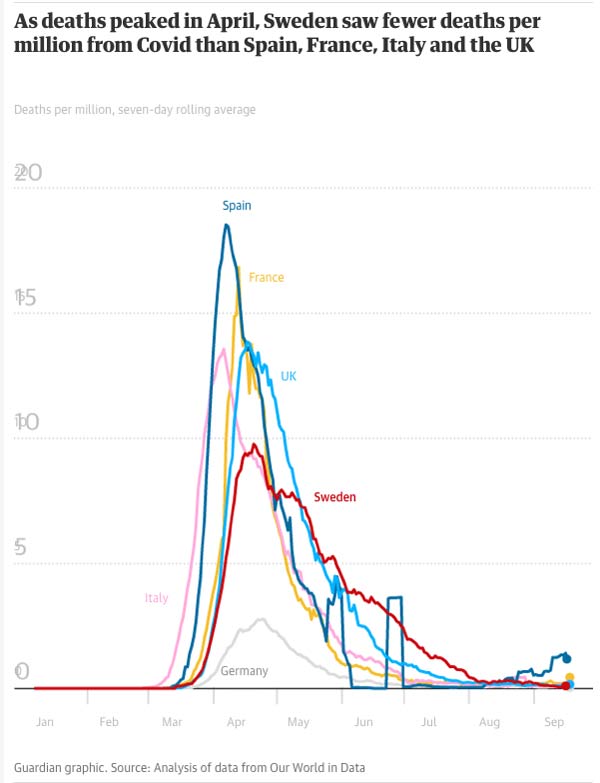
Thirteen Covid-19 patients are in intensive care in Swedish hospitals, and its seven-day average of coronavirus-related deaths is zero.”
The two graphs from The Guardian, below, show Sweden’s infection rate and deaths per million, compared to other countries that enforced stricter lockdown rules.
High Mortality Was Due to Nursing Home Failures
Initially, Tegnell’s approach came under fire as Sweden’s death toll soared five to 10 times higher than its neighboring countries, Denmark, Norway and Finland. However, Tegnell insists this early spike in deaths was not due to a lack of lockdowns or social distancing in general, but rather due to a failure to prevent infection in nursing homes, where a majority of the deaths actually occurred.
“Of course something went wrong there,” Tegnell told The Guardian.9 Other than that, Swedish authorities insist the strategy to encourage and trust citizens to take personal responsibility for their health and well-being has been the correct one.
Contrary to other nations, Sweden’s decision has also resulted in consistent public messaging about disease prevention, thereby avoiding the confusion, frustration and distrust that comes from getting mixed messages.
In April 2020, Emma Frans, science communicator and a postdoctoral researcher in medical epidemiology at the Karolinska Institutet in Stockholm, told the National Review:10
“The strategy in Sweden is to focus on social distancing among the known risk groups, like the elderly. We try to use evidence-based [measures]. We try to adjust everyday life. The Swedish plan is to implement [measures] that you can practice for a long time.”
The Vanishing Middle-Class
As a result of their sensible approach to the pandemic, Sweden has also largely escaped the financial ruin experienced in other areas, including the U.S. This also means they’ve minimized the impact of the pandemic on mental health. As Tegnell told11 The Daily Mail, April 4, 2020, “We can’t kill all our services. And unemployed people are a great threat to public health. It’s a factor you need to think about.”
Indeed, preventing healthy people from working is upending the middle-class in the U.S. and elsewhere, and has (as expected) resulted in a massive rise in suicide and other tragedies. As noted by Robert F. Kennedy Jr. in “How the Government Uses Fear to Control,” research from the 1980s found that for every 1-point rise in unemployment there were 37,000 excess deaths, 4,000 excess imprisonments and 3,300 excess admissions into mental institutions.
Kennedy also cites recent data from a hospital in San Francisco that stated they saw one year’s-worth of suicides in a single month, a 1,200% increase, and British research showing that while there were 30,000 excess deaths in nursing homes during a five-week period during the lockdown, only one-third of them were due to COVID-19.
In other words, the death rate from isolation was double that of the virus itself. People didn’t get the proper medical care for chronic conditions and so on. Kennedy also rightly points out that what we will see — and are already seeing — is the obliteration of the middle-class and the shift of wealth from the poor to the already ultra-rich.
A September 20, 2020, article12 in The Wall Street Journal highlights the financial devastation experienced by the American “loan-laden white-collar” middle-class. Journalist AnnaMaria Andriotis tells the story of Alysse Hopkins, a Rockland County, New York foreclosure and personal-injury lawyer:
“In a good year, the 43-year-old lawyer and her husband, Ian Boschen, 41, together brought in about $175,000, the couple said — enough to cover the mortgage, two car leases, student loans, credit cards and assorted costs of raising two daughters in the New York City suburbs.
After the coronavirus halted many foreclosures and closed courts, her work dried up. Unemployment benefits have helped, Ms. Hopkins said, but the family is running low on savings and can’t keep up with $9,000 in monthly debt payments including mortgage installments. ‘It frustrates me to not be able to earn a living,’ she said. ‘I have a law degree, almost 20 years of practice’ …
While lower-wage workers have borne much of the brunt, the crisis is wreaking a particular kind of havoc on the debt-laden middle class … The coronavirus has spared few industries and expanded unemployment benefits designed to replace the average American income didn’t cover all the lost pay of higher-earning workers, especially in or near expensive cities.
The extra $600 weekly payments expired in July, putting them even further behind. ‘What I see happening here is a core assault on successful college-educated families, which are the new breed of middle-class American families,’ said Anthony Carnevale, director of the Georgetown University Center on Education and the Workforce. ‘There’s a professional workforce that’s getting slammed.'”
Lockdowns Have Likely Done More Harm Than Good
So far, most efforts to curb COVID-19 infection have proven to be ill advised. Evidence shows the illness spreads mostly indoors,13,14,15 for example, casting doubt on the sanity of closing parks and beaches, especially during the summer.
Importantly, the total all-cause mortality is not significantly different than in previous years, as discussed by my interview with Denis Rancourt. Many other deaths have been shifted to COVID-19, bringing a high spike in deaths, but when you look at the area under the curve for total deaths, it really doesn’t differ from previous years.
This statistic has also been highlighted by the American Institute for Economic Research.16 As early as April 2020, they referred to the COVID-19 pandemic as “An egregious statistical horror story” that resulted in “a vandalistic lockdown on the economy,” which:
” … would have been an outrage even if the assumptions were not wildly astronomically wrong. Flattening the curve was always a fool’s errand that widened the damage …
The latest figures on overall death rates from all causes show no increase at all. Deaths are lower than in 2019, 2018, 2017 and 2015, slightly higher than in 2016. Any upward bias is imparted by population growth.
Now writing a book on the crisis with bestselling author Jay Richards, [statistician William] Briggs concludes: ‘Since pneumonia deaths are up, yet all deaths are down, it must mean people are being recorded as dying from other things at smaller rates than usual.’ Deaths from other causes are simply being ascribed to the coronavirus.
As usual every year, deaths began trending downward in January. It’s an annual pattern. Look it up. Since the lockdown began in mid-March, the politicians cannot claim that their policies had anything to do with the declining death rate.
A global study17 published in Israel by Professor Isaac Ben-Israel, chairman of the Israeli Space Agency and Council on Research and Development, shows that ‘the spread of the coronavirus declines to almost zero after 70 days — no matter where it strikes, and no matter what measures governments impose to try to thwart it.’
In fact, by impeding herd immunity, particularly among students and other non-susceptible young people, the lockdown in the U.S. has prolonged and exacerbated the medical problem.”
______________________
**Comment**
The news states that there is an uptick in cases, hospitalizations, and deaths in Wisconsin from COVID. Please keep in mind a few things:
Since the data from Sweden proves harsh draconian lockdowns don’t work, we should adjust policies to reflect this fact rather than continue the fear-mongering and isolation. Remembering the goal of ‘slowing the spread,’ we should allow and encourage the young and healthy to freely move about, while protecting the elderly and infirm.


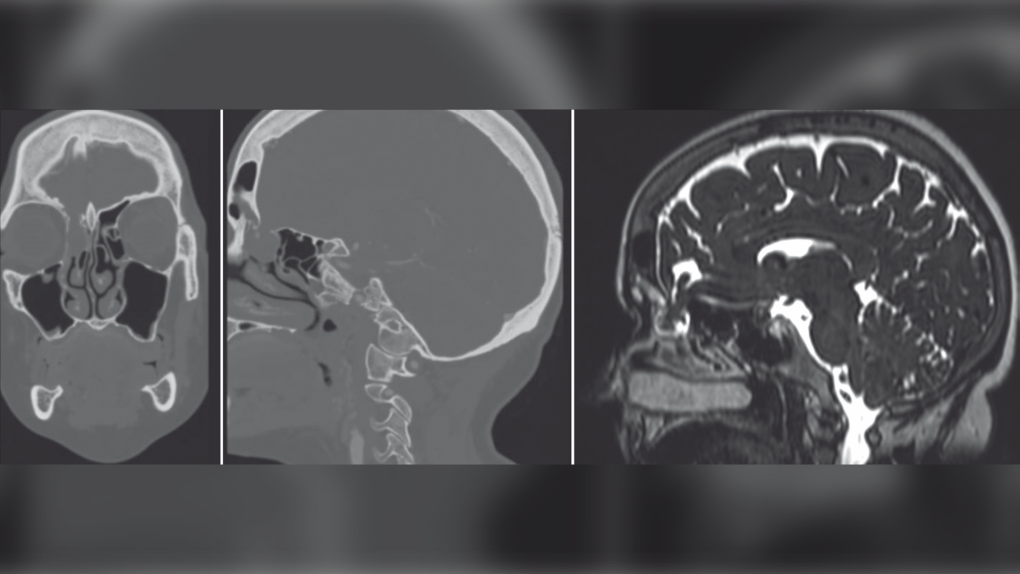 A woman started leaking cerebral fluid out of her nose after she received a COVID-19 test administered with a nasal swab, according to a new case report. (JAMA Otolaryngology/University of Iowa Hospitals and Clinics)