https://popularrationalism.substack.com/p/if-you-read-one-thing-on-sars-cov?

If You Read One Thing on SARS-CoV-2 Vaccine Pathogenesis, Read This (Part 1)

All of this was predicted in April 2020. Here is the undeniable evidence that mass-exposure to the SARS-CoV-2 Spike protein is a very bad idea.

In April, 2020, I predicted the spike protein would cause problems with health.

What my analysis precipitated was a flurry of studies, including laboratory work that confirmed that pathogenic priming was likely to happen.

My findings, as well as those by others who did subsequent similar analyses, point to autoimmunity as a prime driver of COVID-19 disease and of long-term reactions to COVID-19 “vaccination”.

Looking back at the list of proteins that we could see would likely become targets of our own immune system, so much pain & suffering could have been avoided. Given the tissue distribution of the self-antigens in particular, the analyses foretold of a future of clotting disorders, cardiovascular problems, issues with sperm production and female reproduction.

One of the very best summaries was published in a beautiful opus by Seneff and Nigh in the journal “International Journal of Vaccine Theory, Research and Practice” about a year after my initial predictions. That article, entitled “Worse Than the Disease? Reviewing Some Possible Unintended Consequences of the mRNA Vaccines Against COVID-19”, is as comprehensive a piece as you will find warning against the dangers of widespread exposure to the SARS-CoV-2 spike protein. I recently had occasion to re-read the article while preparing written testimony for one of the lawsuits in which I serve as expert witness, and it is absolutely, an “If you read one thing.”

Here is the section on Pathogenic Priming, Multisystem Inflammatory Disease and Autoimmunity, from their article:

“Pathogenic Priming, Multisystem Inflammatory Disease, and Autoimmunity

Pathogenic priming is a concept that is similar in outcome to ADE, but different in the underlying mechanism. We discuss it here as a unique mechanism through which the mRNA vaccines could provoke associated pathologies.

In April 2020 an important paper was published regarding the potential for self reactive antibodies to be generated following exposure to the spike protein and other antigenic epitopes spread over the length of SARS-CoV-2. Lyons-Weiler (2020) coined the phrase ‘pathogen priming’ because he believed the more commonly used ‘immune enhancement’ fails to capture the severity of the condition and its consequences. In his in silico analysis, Lyons-Weiler compared all antigenic SARSCoV-2 protein epitopes flagged in the SVMTriP database (http://sysbio.unl.edu/SVMTriP/) and searched the p-BLAST database (https://blast.ncbi.nlm.nih.gov/Blast.cgi) for homology between those epitopes and endogenous human proteins. Of the 37 SARS-CoV-2 proteins analyzed, 29 had antigenic regions. All but one of these 29 had homology with human proteins (putative self-antigens) and were predicted to be autoreactogenic. The largest number of homologies were associated with the spike (S) protein and the NS3 protein, both having 6 homologous human proteins.

A functional analysis of the endogenous human proteins homologous with viral proteins found that over 1/3 of them are associated with the adaptive immune system. The author speculates that prior virus exposure or prior vaccination, either of which could initiate antibody production that targets these endogenous proteins, may be playing a role in the development of more severe disease in the elderly in particular. In this case the pre-existing antibodies act to suppress the adaptive immune system and lead to more severe disease.

Another group (Ehrenfeld et. al., 2020), in a paper predominantly about the wide range of autoimmune diseases found in association with a prior SARS-CoV-2 infection, also investigated how the spike protein could trigger such a range of diseases. They report, in Table 1 of that reference, strings of heptapeptides within the human proteome that overlap with the spike protein generated by SARS-CoV-2. They identified 26 heptapeptides found in humans and in the spike protein. It is interesting to note that 2 of the 26 overlapping heptapeptides were found to be sequential, a strikingly long string of identical peptides to be found in common between endogenous human proteins and the spike protein. Commenting on the overlapping peptides they had discovered and the potential for this to drive many types of autoimmunity simultaneously, they comment, ‘The clinical scenario that emerges is upsetting.’ Indeed, it is.

In May of 2020 another important paper in this regard was published by Vojdani and Kharrazian (2020). The authors used both mouse and rabbit monoclonal antibodies against the 2003 SARS spike protein to test for reactivity against not only the spike protein of SARS-CoV-2, but also against several endogenous human proteins. They discovered that there was a high level of binding not only with the SARS-CoV-2 spike protein, but against a wide range of endogenous proteins. ‘[W]e found that the strongest reactions were with transglutaminase 3 (tTG3), transglutaminase 2 (tTG2), ENA, myelin basic protein (MBP), mitochondria, nuclear antigen (NA), α-myosin, thyroid peroxidase (TPO), collagen, claudin 5+6, and S100B.’ (Vojdani and Kharrazian, 2020).

These important findings need to be emphasized. Antibodies with a high binding affinity to SARSCoV-2 spike and other proteins also have a high binding affinity with tTG (associated with Celiac Disease), TPO (Hashimoto’s thyroiditis), myelin basic protein (multiple sclerosis), and several endogenous proteins. Unlike the autoimmune process associated with pathogen priming, these autoimmune diseases typically take years to manifest symptomatically.

The autoantibodies generated by the spike protein predicted by Lyons-Weiler (2020) and described above were confirmed with an in vitro study published more recently. In this follow-on paper, Vojdani et. al., (2021) looked again at the issue of cross reactivity of antibodies, this time using human monoclonal antibodies (mAbs) against the SARS-CoV-2 spike protein rather than mouse and rabbit mAbs. Their results confirmed and extended their prior findings. ‘At a cutoff of 0.32 OD [optical density], SARS-CoV-2 membrane protein antibody reacted with 18 out of the 55 tested antigens.’ These 18 endogenous antigens encompass reactivity to tissue in liver, mitochondria, the nervous and digestive system, the pancreas, and elsewhere in the body.

In a report on multisystem inflammatory syndrome in children (MIS-C), Carter et. al. (2020) studied 23 cases. Seventeen of 23 (68%) patients had serological evidence of prior SARS-CoV-2 infection.

Of the three antibodies assessed in the patient population (nucleocapsid, RBD, and spike), IgG spike protein antibody optical density (which quantifies antibody concentrations against a standardized curve (Wikipedia, 2021)), was highest (see Figure 1d in Carter et al., 2020).

MIS-C is now commonly speculated to be an example of immune priming by prior exposure to SARS-CoV-2 or to other coronaviruses. Buonsenso et. al. (2020) reviewed multiple immunologic similarities between MIS-C and disease related to prior β hemolytic Group A streptococcal infection (GAS). The authors write, ‘We can speculate that children’s multiple exposition to SARS-CoV-2 with parents with COVID-19 can work as a priming of the immune system, as happens with GAS infection and, in genetically predisposed children, lead to [MIS-C] development. Another hypothesis is that previous infections with other coronaviruses, much more frequent in the pediatric population, may have primed the child immune system to SARS-CoV-2 virus.’

In June 2019 Galeotti and Bayry (2020) reviewed the occurrence of both autoimmune and inflammatory diseases in patients with COVID-19. They focus their analysis on MIS-C. After reviewing several previously published reports of a temporal link between COVID-19 and onset of MIS-C and describing a number of possible mechanistic connections between the two, the authors noted that no causal link had been established. In a somewhat prescient recommendation, they wrote, ‘A fine analysis of homology between various antigens of SARS-CoV-2 and self-antigens, by use of in silico approaches and validation in experimental models, should be considered in order to confirm this hypothesis.’ It is precisely this type of in silico analysis (that had already been) carried out by Lyons-Weiler (2020) and by Ehrenfeld et. al. (2020) described in the opening paragraphs of this section which found the tight homology between viral antigens and self-antigens. While this may not definitively confirm the causal link hypothesized by Galeotti and Bayry, it is strong supporting evidence.

Autoimmunity is becoming much more widely recognized as a sequela of COVID-19. There are multiple reports of previously healthy individuals who developed diseases such as idiopathic thrombocytopenic purpura, Guillain-Barré syndrome and autoimmune haemolytic anaemia (Galeotti and Bayry, 2020). There are three independent case reports of systemic lupus erythemosus (SLE) with cutaneous manifestations following symptomatic COVID-19. In one case a 39-year-old male had SLE onset two months following outpatient treatment for COVID-19 (Zamani et.al., 2021).

Another striking case of rapidly progressing and fatal SLE with cutaneous manifestations is described by Slimani et.al. (2021).

Autoantibodies are very commonly found in COVID-19 patients, including antibodies found in blood (Vlachoyiannopoulos et. al., 2020) and cerebrospinal fluid (CFS) (Franke et. al., 2021).

Though SARS-CoV-2 is not found in the CSF, it is theorized that the autoantibodies created in response to SARS-CoV-2 exposure may lead to at least some portion of the neurological complications documented in COVID-19 patients. One important Letter to the Editor submitted to the journal Arthritis & Rheumatology by Bertin et. al. (2020) noted the high prevalence and strong association (p=0.009) of autoantibodies against cardiolipin in COVID-19 patients with severe disease.

Zuo et. al. (2020) found anti-phospholipid autoantibodies in 52% of hospitalized COVID-19 patients and speculated that these antibodies contribute to the high incidence of coagulopathies in these patients. Schiaffino et. al. (2020) reported that serum from a high percentage of hospitalized COVID-19 patients contained autoantibodies reactive to the plasma membrane of hepatocytes and gastric cells. One patient with Guillain-Barre Syndrome was found to have antibody reactivity in cerebrospinal fluid (CFS), leading the authors to suggest that cross-reactivity with proteins in the CFS could lead to neurological complications seen in some COVID-19 patients. In a more recent review, Gao et. al. (2021) noted high levels of autoantibodies in COVID-19 patients across multiple studies. They conclude, ‘[O]ne of the potential side effects of giving a mass vaccine could be an emergence [sic] of autoimmune diseases especially in individuals who are genetically prone for autoimmunity.’

A recent publication compiles a great deal of evidence that autoantibodies against a broad range of receptors and tissue can be found in individuals who have had previous SARS-CoV-2 infection. ‘All 31 former COVID-19 patients had between 2 and 7 different GPCR-fAABs [G-protein coupled receptor functional autoantibodies] that acted as receptor agonists. (Wallukat et. al. 2021) The diversity of GPCR-fAABs identified, encompassing both agonist and antagonist activity on target receptors, strongly correlated with a range of post-COVID-19 symptoms, including tachycardia, bradycardia, alopecia, attention deficit, PoTS, neuropathies, and others.

The same study, referencing the autoantibodies predicted by Lyons-Weiler (2020) mentioned above, notes with obvious grave concern: ‘The Sars-CoV-2 spike protein is a potential epitopic target for biomimicry-induced autoimmunological processes [25]. Therefore, we feel it will be extremely important to investigate whether GPCR-fAABs will also become detectable after immunisation by vaccination against the virus.’

We have reviewed the evidence here that the spike protein of SARS-CoV-2 has extensive sequence homology with multiple endogenous human proteins and could prime the immune system toward development of both auto-inflammatory and autoimmune disease. This is particularly concerning given that the protein has been redesigned with two extra proline residues to potentially impede its clearance from the circulation through membrane fusion. These diseases could present acutely and over relatively short timespans such as with MIS-C or could potentially not manifest for months or years following exposure to the spike protein, whether via natural infection or via vaccination.

Many who test positive for COVID-19 express no symptoms. The number of asymptomatic, PCR-positive cases varies widely between studies, from a low of 1.6% to a high of 56.5% (Gao et. al., 2020). Those who are insensitive to COVID-19 probably have a very strong innate immune system.

The healthy mucosal barrier’s neutrophils and macrophages rapidly clear the viruses, often without the need for any antibodies to be produced by the adaptive system. However, the vaccine intentionally completely bypasses the mucosal immune system, both through its injection past the natural mucosal barriers and its artificial configuration as an RNA-containing nanoparticle. As noted in Carsetti (2020), those with a strong innate immune response almost universally experience either asymptomatic infection or only mild COVID-19 disease presentation. Nevertheless, they might face chronic autoimmune disease, as described previously, as a consequence of excessive antibody production in response to the vaccine, which was not necessary in the first place.

The Spleen, Platelets and Thrombocytopenia

Dr. Gregory Michael, an obstetrician in Miami Beach, died of a cerebral hemorrhage 16 days after receiving the first dose of the Pfizer/BioNTech COVID-19 vaccine. Within three days of the vaccine, he developed idiopathic thrombocytopenic purpura (ITP), an autoimmune disorder in which the immune cells attack and destroy the platelets. His platelet count dropped precipitously, and this caused an inability to stop internal bleeding, leading to the stroke, as described in an article in the New York Times (Grady and Mazzei, 2021). The New York Times followed up with a second article that discussed several other cases of ITP following SARS-CoV-2 vaccination (Grady, 2021), and several other incidences of precipitous drop of platelets and thrombocytopenia following SARS-CoV-2 vaccination have been reported in the Vaccine Adverse Event Reporting System (VAERS).’

SARS-CoV-2 may have effects on the human vascular system, including that of the brain. The primary function of the Spike protein is to allow the entry of the virus into a host cell via binding to the ACE2 receptor located in the cell membrane. ACE2 is a type I integral membrane protein that cleaves angiotensin II in angiotensin I, thus removing angiotensin II and lowering the blood pressure.”

Since that paper was published, much more has come to light about the pathogenesis of the SARS-CoV-2 Spike Protein. I’ll be reviewing those works in Part 2.


https://danielcameronmd.com/physician-frustration-with-lyme-disease-patients/

Physician frustration with Lyme disease patients

physician-frustration-lyme-disease-patients

In their study, “Primary care clinical provider knowledge and experiences in the diagnosis and treatment of tick‑borne illness: a qualitative assessment from a Lyme disease endemic community,” Mattoon and colleagues examined frontline and primary care doctor’s knowledge and practices for identifying patients with tick-borne diseases.

They found that some physicians are frustrated with Lyme disease (LD) patients. “Providers described challenges and frustrations in counseling patients with strong preconceptions of LD diagnosis and treatment in the context of chronic infection,” the authors wrote.

The authors came to this conclusion after a series of focus groups with 14 clinicians from three primary care practices and a survey of 24 urgent and emergency care clinicians.

The diagnostic process contributed to some of the frustration.

“Clinicians had a self-professed lack of awareness of TBDs [tick-borne diseases] outside of Lyme disease, noting that they were unfamiliar with the signs, symptoms, and appropriate serologic testing needed to diagnose non-Lyme TBDs, as well as the prevalence of these TBDs in their local communities.”

More specifically, nearly 50% of clinicians reported feeling “not at all knowledgeable on anaplasmosis.”

Treatment approaches also led to frustration. Clinicians:

“appeared to have difficulty in identifying the appropriate treatment approach for patients with nonspecific symptoms and negative Lyme disease serology, with only 66.7% [of clinicians] providing the correct answer,” the authors wrote.

Problems presented by patients with chronic illness

Some doctors were frustrated when patients challenged their treatment plan.  “This commonly came in the form of patients rejecting results of serologic testing, wanting a different length of antibiotic course than that prescribed, or seeking an alternative treatment modality.”

Some doctors were frustrated with the time and effort involved in taking care of these patients.

“Clinical encounters with these patients were described as time consuming and difficult.”

Finally, some doctors were frustrated by contradictory information by outside providers. “Two focus group discussions centered around differences in care plans between participants’ primary care offices and what they termed the ‘Lyme literate’ community.”

Need for more education and training

Clinicians felt additional training would be help avoid some of these problems. The authors cited an example:

“I ordered what I thought was sort of the standard Lyme titer. It came back negative and this kid continued to have a swollen knee…He went to the orthopedist. They couldn’t figure it out. He’s going up to the rheumatologist. And it’s just because I ordered the wrong test…I think [I] ordered the PCR, which was like, you know, the quick and easy one. But actually that wasn’t probably a good one to do.” [FG3, Pediatrics]

“The gaps in knowledge identified through the focus group and online survey data, coupled with the consistent necessity to provide point-of-care counseling and education to patients,” the authors concluded, “highlight a pressing need for resources and support for primary care and frontline providers treating patients for TBDs.”

Editor’s perspective

Neither the authors nor the participating clinicians questioned the accuracy of the diagnostic testing and treatment plans they administer.
References:
  1. Mattoon, S., Baumhart, C., Barsallo Cochez, A.C. et al. Primary care clinical provider knowledge and experiences in the diagnosis and treatment of tick-borne illness: a qualitative assessment from a Lyme disease endemic community. BMC Infect Dis 21, 894 (2021). https://doi.org/10.1186/s12879-021-06622-6

_____________________

**Comment**

A cringe-worthy article for sure.  I couldn’t help but think that if doctors think they are frustrated, try being a severely sick patient, perhaps who’s spouse is just as ill, whose life is spiraling down a vortex of doom in every way possible and your doctor, the person who is supposed to have the answers, is completely and hopelessly in the dark.

Talk about frustration!

My advice: bypass these doctors at all costs and get straight to an educated, Lyme literate doctor with experience.  It will save you time, money, and heartache in the end.

https://reason.com/2021/11/09/the-cdcs-director-implies-that-face-masks-are-more-effective-than-vaccines-at-preventing-covid-19-infection/

The CDC’s Director Implies That Face Masks Are More Effective Than Vaccines at Preventing COVID-19 Infection

Rochelle Walensky seems to be relying on a laboratory study that did not measure infection risk.

| 

Are face masks more effective than vaccination at preventing COVID-19 infection? That is the implication of a new public service announcement from the Centers for Disease Control and Prevention (CDC) featuring Rochelle Walensky, the agency’s director.

“The evidence is clear,” Walensky says in the 37-second video, which she posted on Twitter last Friday. “Masks can help prevent the spread of COVID-19 by reducing your chance of infection by more than 80 percent, whether it’s an infection from the flu, from the coronavirus, or even just the common cold. In combination with other steps like getting your vaccination, hand washing, and keeping physical distance, wearing your mask is an important step you can take to keep us all healthy.”

If wearing a mask reduced your risk of infection by “more than 80 percent,” as Walensky seems to be saying, that safeguard would be amazingly effective. Such a risk reduction would be higher than the effectiveness rates found in several real-world studies of mRNA vaccines. (See link for article)

________________

**UPDATE, Nov. 24, 2021**

Watch a series of brief videos where Tyson Gabriel, an industrial hygienist, safety engineer, and risk manager who trains doctors and has 20 years of experience implementing exposure prevention plans in industry, and is lead researcher for his team, examined each mask study on the CDC’s website.  Also see these reports.

Once again our corrupt public health ‘authorities’ are convoluting data.

  • The author asked the CDC about this claim. When they finally responded, they did not cite any specific research to back it up and essentially gave boilerplate advice
  • It appears Walensky is relying on a laboratory study that was reported in the journal Science Advances last September where researchers used a camera to record laser-illuminated respiratory droplets from speakers wearing 14 different types of face masks which found:
    • valveless N95 mask was 99.9 percent effective at retaining “droplet sizes larger than 0.5 μm” (the estimated detection limit) Please listen to a N95 developer explain the reason your glasses fog up wearing these masks is due to holes at the top where viruses can easily gain entry. Further, he estimates that 70% of the air you are breathing does not go through the mask
    • neck gaiter seemed worse than useless and actually broke larger droplets into smaller ones
    • three-layer surgical masks and several kinds of cloth masks reduced the number of droplets detected by more than 80%. Again, the PPE N95 develper shreds this to bits by stating when you cough or sneeze with a cloth mask on, it goes right through the mask.  Another PhD in infectious disease states cloth masks offer NO protection against COVID
Based on these results of a study done in a lab the CDC’s summary says “upwards of 80% blockage has been achieved in human experiments that have measured blocking of all respiratory droplets.”

Her statement is misleading as it doesn’t include the numerous limitations in the study, and it certainly doesn’t quantify real-world implications of masks on a study contained in a lab that didn’t even measure for it. The study contained some laughable details:

  • In one particular study, the person wearing a mask spoke through a hole in a box reciting the phrase “Stay healthy, people,” but did not cough, sneeze, shout, or sing
  • Masks were clean and worn properly, which rarely happens in the real world
  • Walensky’s message assumes everyone is wearing the most effective mask
  • When parents had their child’s masks tested, the lab found Lyme, Tularemia, Ridkettsia, and other bacteria
  • Worse, Walensky’s ambiguous statement could be interpreted to mean that people who wear masks reduce their own risk of catching COVID-19 by “more than 80 percent.” The study, which looked at droplets emitted by mask wearers, provides no basis for this claim
  • There continues to be no basis in science for wearing masks unless you are trying to filter dust
  • A large meta-analysis shows that while masks may filter droplets there are numerous drawbacks which our corrupt public health ‘authorities’ never mention including that they may actually increase transmission. Every time I see someone wearing a mask, they are constantly touching it.  Constantly.  They also lower the oxygen you are breathing which is terrible for overall health
  • Walensky has repeatedly caught flak for distorting COVID-19 research
  • In a large, randomized controlled study on 6,000 people, no statistically significant difference was noted in infection rate between the mask wearing group vs the unmasked group.  These results reflect other reviews and nine other trials that found masks make little or no difference in infection rates.  But, again, none of this matters in a world without logic

https://www.nytimes.com/2021/08/19/well/live/coronavirus-restaurants-classrooms-salons

Clear barriers have sprung up at restaurants, nail salons and school classrooms, but most of the time, they do little to stop the spread of the coronavirus.
Credit…Rich Pedroncelli/File, via Associated Press

Covid precautions have turned many parts of our world into a giant salad bar, with plastic barriers separating sales clerks from shoppers, dividing customers at nail salons and shielding students from their classmates.

Intuition tells us a plastic shield would be protective against germs. But scientists who study aerosols, air flow and ventilation say that much of the time, the barriers don’t help and probably give people a false sense of security. And sometimes the barriers can make things worse.

Research suggests that in some instances, a barrier protecting a clerk behind a checkout counter may redirect the germs to another worker or customer. Rows of clear plastic shields, like those you might find in a nail salon or classroom, can also impede normal air flow and ventilation.

Under normal conditions in stores, classrooms and offices, exhaled breath particles disperse, carried by air currents and, depending on the ventilation system, are replaced by fresh air roughly every 15 to 30 minutes. But erecting plastic barriers can change air flow in a room, disrupt normal ventilation and create “dead zones,” where viral aerosol particles can build up and become highly concentrated.  (See link for article)

__________________

**Highlights**

  • A study published in June and led by researchers from Johns Hopkins showed that desk screens in classrooms were associated with an increased risk of coronavirus infection
  • In a Massachusetts school district, researchers found plexiglass dividers with side walls in the main office were impeding air flow
  • A study looking at schools in Georgia found desk barriers had little effect on the spread of the coronavirus compared with ventilation improvements and masking
  • A study published in 2014 found that office cubicle dividers were among the factors that may have contributed to disease transmission during a tuberculosis outbreak in Australia
  • British researchers have conducted modeling studies simulating what happens when a person on one side of a barrier exhales particles while speaking or coughing under various ventilation conditions. The screen is more effective when the person coughs, because the larger particles have greater momentum and hit the barrier. But when a person speaks, the screen doesn’t trap the exhaled particles — which just float around it. While the store clerk may avoid an immediate and direct hit, the particles are still in the room, posing a risk to the clerk and others who may inhale the contaminated air
  • A study published in 2013 that looked at the effect of partitions between beds in hospitals. The study showed that while some people were protected from germs, the partitions funneled the air in the room toward others
  • All the aerosol experts interviewed agreed that desk shields were unlikely to help and were likely to interfere with the normal ventilation of the room. Depending on the conditions, the plastic shields could cause viral particles to accumulate in the room
  • As with everything else in this ‘pandemic’, those in charge are simply in lockstep following corrupt public health advice without consulting with engineering experts.  It appears those in authority are tin men lacking a brain.

https://popularrationalism.substack.com/p/acip-fda-cdc-have-no-data-but-approve

ACIP, FDA, CDC Have No Data, But Approve Boosters For All

The Public Can See What They Did. You Can Help Others Learn About It.

Yesterday, U.S. Rep. Troy Carter asked the Biden administration for third-party monitoring of air emissions in the Mississippi River corridor between Baton Rouge and New Orleans — and for money to study the cumulative impact of those emissions on public health. (The Advocate). Currently, petroleum companies monitor their own emissions.

Yesterday, no one asked the Biden administration for third-party monitoring of vaccines used across the country in millions of people — nor for money to study the cumulative impact of those injections on public health. Currently, vaccine manufacturers conduct their own safety studies.

We have an EPA and state agencies that supposed to be monitoring the emissions of corporations and the CDC and FDA to track vaccine safety, yet we are allowing the very companies who profit massively from their products to tell us, now through press releases – that their products are safe.

The suppression of information on social media is nearly complete. So, it’s probably not a surprise that you missed the details of the piss-poor regulatory review processes of boosters for adults that went down yesterday across the agencies. I’m sure you heard that the new recommendations are “Boosters for All”. You may have even heard of some press releases from vaccine manufacturers that boosters help – and of course the legacy media made certain that you heard Fauci’s opinion.

But it’s very likely you didn’t have time to sit through another day of meetings and track what hat-tricks the FDA, CDC and ACIP pulled yesterday.

The good news is that people did take the time, and that other people I know send me important things.

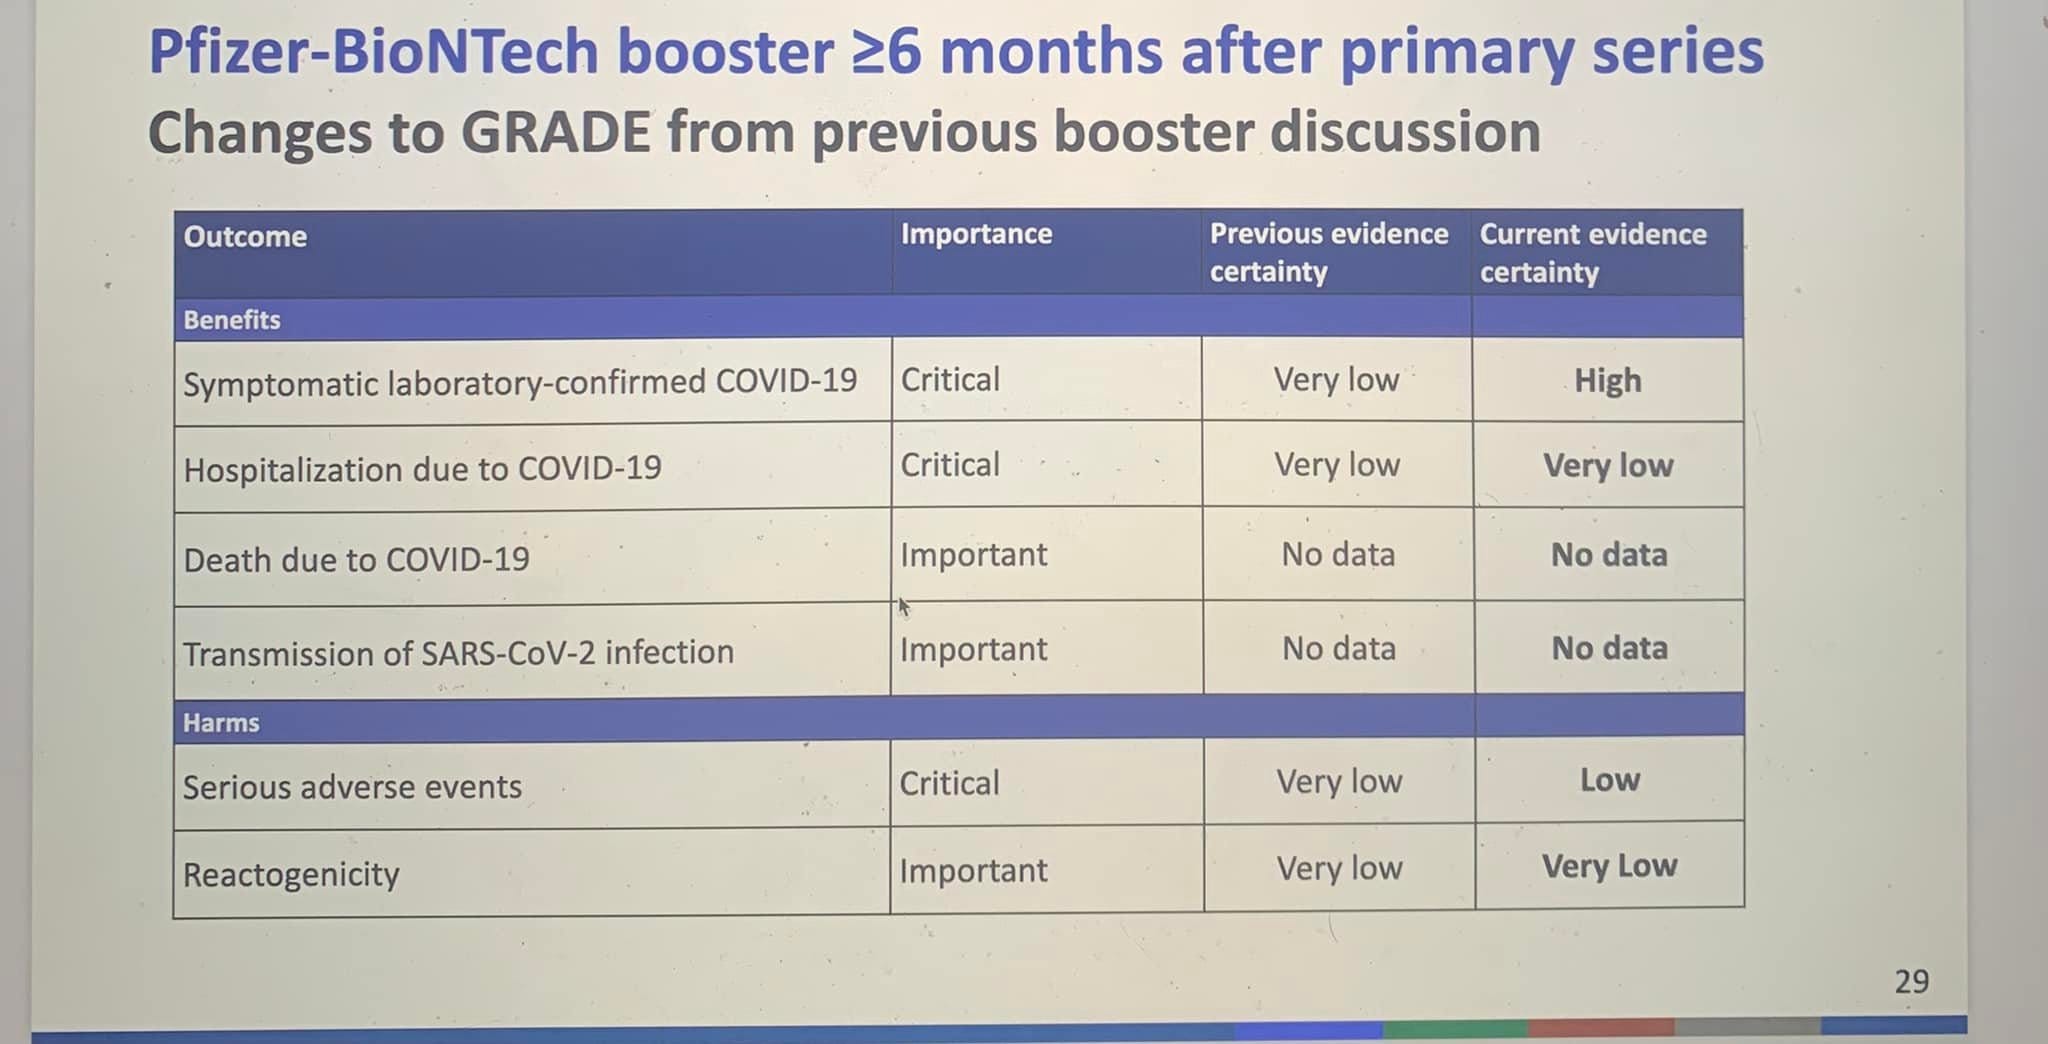
So, I’m going to put screen shots of yesterday’s ACIP meeting reviewing the level of evidence available to inform them on their historic and important vote to recommend, and if thereby mandate, pending court cases against OSHA, third boosters for all.

You won’t believe what you see.

Keep in mind that last we checked, every member of the ACIP committee has conflicts of interest with vaccine manufacturers.

Thank you, Patricia N. for doing your part to watch-dog the fascists in control of our government agencies that are supposed to be protecting us.

Are we going to take this laying down?

Tell your Senator and Congressional representative that we need to ban conflicts of interest among ACIP members and their families.

Tell your Senator and Congressional representative that the people who approved these boosters on NO DATA must step down.

What You Can Do

You’ve read what’s going on in Gibraltar now that they are boosting. If not: After fully vaccinating their population, and a summer of no problems, they started boosting. They have had to cancel Christmas. I’ll be publishing this kind of analysis on Popular Rationalism until we see a wholescale reform consistent with #PlanB.

So, yes, share on social media. And for that I thank you. But if you give a gift subscription to your Congressional Representatives and Senators (or people close to them), your school board members, your doctors, etc.), they will receive Popular Rationalism right in their inbox.

Let’s turn this thing around.

_________________

**Comment**

Predictably, and within days of each other, Gates and Fauci admit the COVID jabs aren’t effective.  Their coordinated answer, predictably, is more boosters! 

Robert F. Kennedy, Jr.’s forthcoming book “The Real Anthony Fauci” explores the “carefully constructed Pharma-Fauci-Gates alliance,” and details how “Gates and Fauci engaged in almost daily communications throughout the lockdown, and coordinated virtually every decision about COVID-19 countermeasures with each other.”  Source

Despite nearly 900,000 adverse reactions reported to VAERS, the corrupt FDA & CDC sign off on Pfizer and Moderna boosters for all adults without any input from its advisory committee which voted 16 to 2 against boosters in September citing lack of data.  Yet here we are in the COVID world of the absurd where facts and data no longer matter.

In this article we learn that Children’s Health Defense Fund has filed a lawsuit against the FDA due to the fact you cannot have a vaccine that is both an emergency use product and a licensed product at the same time. That’s against the law, but the government has done it anyway. The request for an injunction was initially thrown out, but CHD is still pursuing the case.

Again, the only FDA approved COVID injection for adults is for Pfizer/BioTech’s Comirnaty, which currently isn’t available. The experimental, emergency use (EUA) Pfizer shot is being substituted for Comirnaty but the two are legally distinct from one another, which means you could sue Pfizer if you were injured by Comirnaty when it comes out – but this must be done before it is added to the recommended childhood vaccination schedule.  Confused yet?  That’s exactly what they hope and want.

Dr. Meryl Nass states the following:

“I concluded that the legal distinctions were the fact that under EUA, there was essentially no manufacturer liability, but once the vaccine got licensed, the manufacturer would be subject to liability claims unless and until the vaccine was placed on the childhood schedule or recommended in pregnancy, in which case it would then fall … under the NVICP,” Nass says.

“Right now, Comirnaty is still not in that injury compensation program, and it’s licensed, so it no longer falls under the CICP. So, it is in fact subject to liability if you get injured with a bottle that says Comirnaty on it. Of course, if you’re Pfizer, what do you want to do?

You don’t want to make that licensed product available until several months have gone by and Comirnaty has been put into the National Vaccine Injury Compensation Program. So, Pfizer and FDA have not made the licensed product available yet.

What has happened instead, in the military, is the FDA has made a secret deal with the military and said, certain emergency use lots can be considered equivalent to the licensed vaccine, and [told military medical staff] which QR codes — which lots can be used. [These specific lots] can then be given to soldiers as if they’re licensed.

Subsequently, we’re told that military clinics are actually putting Comirnaty labels onto bottles that are under EUA. Now, that probably can happen in the military, but only in the military, because there are likely to be memoranda of understanding within the military that we haven’t seen yet that say soldiers cannot sue Pfizer for injuries …

In the military, the government and Pfizer feel like they have set up a situation where nobody can sue, but in the civilian world, that has not happened, and so there is no Comirnaty available.

Yet, on the basis that FDA licensed this product, the federal government is still telling employers that they can mandate it and that they must fire employees that have not taken the vaccine, or they will lose government contracts. We’re in a very interesting situation that is ripe for litigation, and Children’s Health Defense, which is an organization I represent, is litigating some of this.

However, the litigation situation has been very difficult since the pandemic began. Cases that normally would’ve been easy wins are being thrown out by the courts, both in the U.S. and in Europe. Something strange has happened and the judges are looking for any way out, so they don’t have to rule on the merits of these cases.”

___________________

https://healthimpactnews.com/2021/vaccinated-doctors-are-dying-and-unvaccinated-doctors-are-quitting-or-being-fired-who-will-run-the-hospitals/

Vaccinated Doctors are Dying and Unvaccinated Doctors are Quitting or Being Fired: Who will Run the Hospitals?

by Brian Shilhavy, Nov. 19, 2021
Editor, Health Impact News

Since the roll out of the experimental COVID-19 shots began we have reported many sad stories of medical professionals dying or being crippled by the experimental shots.

The corporate media tries to hide these stories, because it is bad business for their main sponsors, large pharmaceutical companies like Pfizer.

It has been widely reported in the Alternative Media this week that the public is catching on to the fact that when publicly visible people die, the corporate media is hiding their COVID-19 vaccination status, so searches such as “died suddenly” or “died unexpectedly” have soared in recent weeks, as this is how the corporate media typically now reports these deaths of otherwise healthy, young people.

So here is an update of medical doctors who have died after receiving a COVID-19 shot, or when their vaccination status is not mentioned, died suddenly or unexpectedly.

If this is just a small sampling of the total deaths that have become known through media reports, the hospital system could be in serious trouble, as many unvaccinated medical doctors have already been either fired or have quit due to COVID-19 vaccine mandates, and those mandates for medical staff to be completely vaccinated kick in on January 4th.

According to Forbes, about one third of hospital staffs in the U.S. are not yet “vaccinated.”

If most of these staff end up quitting or being fired, who is going to be left to run the hospitals??

Here are some recent reports of medical doctors who “died suddenly.” In almost all of these stories in the corporate media they will blame the deaths on “COVID.”

And why not? A patient who dies with a COVID diagnosis is worth about $100,000.00 of reimbursements to the hospitals, which is why you see reports of people dying in motor vehicle accidents or from gun violence being diagnosed with “COVID” even after they are dead.

Dr. Kevin Walsh – Roanoke, Virginia

Dr. Justin Nasser – Benowa, Queensland (Australia)

Dr. Stephanie Bosch – Waldport, Oregon

Dr. Craig Shannon – Poughkeepsie, New York

Dr. Elliott Gagnon – Wasilla, Alaska

Dr. Daniel McBride – West Hatfield, Massachusetts

Dr. Janak Patel – Marietta, Ohio

Read their stories on The COVID Blog.

Previous stories published on Health Impact News of doctors dying after receiving a COVID shot:

From our Bitchute channel.

For more:

https://www.lymedisease.org/stricker-new-drugs-for-lyme/

What will it take to develop new drugs for Lyme disease?

Dr. Raphael Stricker, a San Francisco internist and hematologist, is an internationally recognized leader in tick-borne disease diagnosis and treatment.

He is also a board member of LymeDisease.org.

Dr. Stricker recently delivered a recorded overview of tick-borne diseases to the European Society of Medicine Congress 2021. The title of his talk was “Lyme Disease: The New Pharma Frontier.”

As he notes in his introduction,

“Over the past year, there have been at least four novel antiviral drugs for Covid-19 that have been developed. It’s disappointing that we haven’t seen the same kind of drug development for Lyme disease over the years. [In this presentation], I’d like to focus on that type of drug development.”

Click below to view his talk.

___________________

To answer the question: we, the sick, must do it ourselves.
For more: