https://pubmed.ncbi.nlm.nih.gov/28613720/

Lyme Disease

In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2025 Jan.
.
  • PMID: 28613720

Excerpt

Lyme disease, or Lyme borreliosis, is the most commonly transmitted tick-borne infection in the United States (US) and among the most frequently diagnosed tick-borne infections worldwide. Lyme disease is divided into 3 stages: early localized, early disseminated, and late. Early localized disease is distinguished by the red ring-like expanding rash of erythema migrans at the site of a recent tick bite. Other symptoms experienced at this stage may be malaise, headache, fever, myalgia, and arthralgia. Most patients only experience the symptoms of early localized disease. About 20% of patients develop early disseminated disease, with the most common symptoms being multiple erythema migrans lesions.

Other symptoms of the disseminated stage are flu-like symptoms, lymphadenopathy, arthralgia, myalgia, palsies of the cranial nerves, especially of cranial nerve VII, ophthalmic conditions, and lymphocytic meningitis. Additionally, cardiac manifestations, including conduction abnormalities, myocarditis, or pericarditis, may occur. The most common late-stage manifestation is arthritis, which is usually pauciarticular and affects large joints, especially the knees. Lyme disease is a curable condition if identified and treated appropriately.

_______________

**Comment**

Sigh……here we go again.  Our tax dollars at work killing patients by regurgitating the same myths for over 40 years.

  1. The ‘3 stages’ of Lyme myth has been dispelled numerous times yet repeated with abandon.  Here we learn of a child who within 4-6 hours of tick bite developed widely disseminated disease where she suddenly couldn’t walk or talk.  The ‘stage’ narrative is killing people by giving them a false sense of time.  Some people have very little time before chronic/persistent infection becomes a reality.
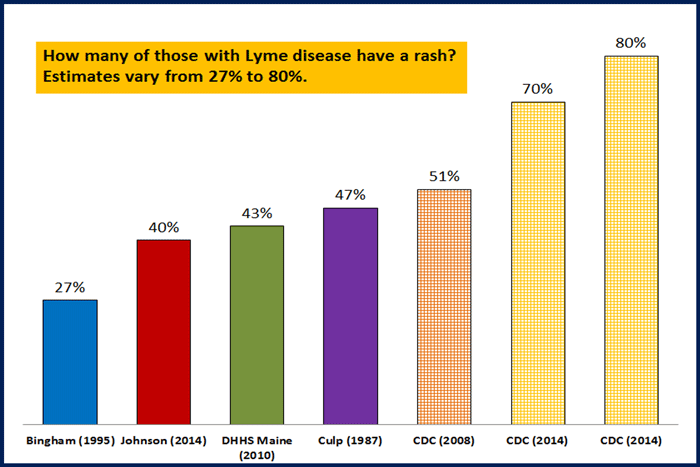
  2. Hardly anyone I work with gets an EM rash, and a study found only 6% got it.  The rash is highly variable and prone to misdiagnosis.  There is nothing ‘classic’ about it.

    • The rash issue, as well as waiting for the results of a faulty test, has caused frequent, unnecessary delays in diagnosis and treatment, dooming patients to a lifetime of suffering, as doctors are not properly educated on actual science, but have been fed a CDC-narrative that continues on with ratchet studies like this one.  Most doctors are unaware that while this rash is diagnostic for Lyme disease and that misdiagnosis can have fatal consequences, lack of a rash means zippo.
    • Aucott reports that 54% of Lyme disease patients who present without a rash are misdiagnosed.
  3. The litany of symptoms (that can be psychiatric) continues to be ignored despite case after case after case showing this reality. Many of these symptoms are often caused by coinfections that come with Lyme, but this factoid is repeatedly ignored by mainstream research. Therefore the statement: “Most patients only experience the symptoms of early localized disease,” is completely and utterly erroneous.  Further, the statement: “the most common late-stage manifestation is arthritis, which is usually pauciarticular (involvement of 4 or fewer joints) and affects large joints, especially the knees,” is also utter garbage. They insist on propagating an acute illness, caused by a singular bacterium because it fits the ‘vaccine’ narrative.  This is also why the vaccine topic is huge and should be taken seriously by the Lyme/MSIDS community, and in order for that to happen, an understanding of the ‘vaccine’ fraud is mandatory reading, not to mention the fact every patient I know who got ‘vaccinated’ relapsed.
  4. Sexual and congenital transmission is also categorically ignored.
  5. The statement: “Lyme disease is a curable condition if identified and treated appropriately,” is sheer hopium based upon nothing but pixie dust.
  6. Besides the fraudulent ‘vaccine’ narrative, it’s imperative to understand government ‘public health’ is nothing more than a peddler for Big Pharma.  This is why mainstream research via government grants and/or industry funding will only continue to regurgitate damaging information presented in this recent article. The design of Lyme/MSIDS research purposely omits the sickest patients, ignores seronegativity, and relies upon a test that misses around 90% of all cases – utilizing a rash nobody can identify and few have! 
There is no greater example of having the deck stacked against you.

The only hope for chronically ill patients is N-of-1 Trials.

This study and all others funded by government is a waste of time and money.

https://rairfoundation.com/kill-shot-dr-mark-trozzi-exposes-mrna-vaccines/

‘Kill Shot’: Dr. Mark Trozzi Exposes mRNA Vaccines as a Genetically Engineered Bioweapon and Reveals Groundbreaking Recovery Solutions (Video)

Rair Foundation

1/27/25

The top link will take you to a five part series with Dr. Trozzi.  Part IV is the treatment and recovery section posted below.

Article Excerpt:

Part IV: Treatment and Recovery

Dr. Trozzi concluded with practical strategies to mitigate the effects of mRNA vaccines and support recovery. He emphasized the importance of both natural and medical interventions.

  • Enhancing Autophagy: Autophagy, the body’s process of clearing damaged cells and proteins, can be stimulated through:
    • Intermittent Fasting: Restricting food intake to a 6-8 hour window daily.
    • Extended Water Fasts: Periodic 3-day water fasts to boost cellular cleanup and regeneration.
  • Key Supplements:
    • Nattokinase: An enzyme derived from fermented soybeans, effective in breaking down blood clots and degrading spike proteins.
    • Bromelain: Found in pineapples, this enzyme reduces inflammation and targets amyloid structures linked to spike proteins.
    • N-Acetylcysteine (NAC): An antioxidant that blocks spike protein binding and reduces oxidative stress.
    • Curcumin: The active compound in turmeric, enhanced with black pepper extract (piperine) for greater efficacy.
  • Repurposed Medications:
    • Ivermectin: Binds to spike proteins and neutralizes their effects.
    • Hydroxychloroquine: Facilitates zinc entry into cells, inhibiting viral replication and modulating immune responses.
  • Holistic Health Principles: Dr. Trozzi recommended a “NEW START” approach:
    • Nutrition: Emphasizing organic, nutrient-dense foods.
    • Exercise: Promoting regular physical activity.
    • Water: Staying hydrated with clean, fluoride-free water.
    • Sunshine: Ensuring adequate vitamin D levels.
    • Temperance: Avoiding excessive alcohol, smoking, and other harmful habits.
    • Air: Benefiting from fresh, outdoor environments.
    • Rest: Prioritizing quality sleep.
    • Trust in God or Spirituality: Reducing stress and cortisol levels through faith or mindfulness.

I also highly recommend his article: PCR Testing was a scam & How to Heal Post Injection.

THE COVID DOSSIER

‘COVID was not a public health event’

A record of military and intelligence coordination of the global Covid event.

Please watch the interview with Debbie Lerman and Sasha Latypova.  (Approx. 30 Min)

Also, read the COVID Dossier pdf file in the top link which is a set of facts and references compiled by Lerman and Latypova.

All measures deployed were not public health measures.  They are ineffective, dangerous, and were simply intended to spread fear and panic so the public would embrace whatever countermeasure was introduced, which in this case was the experimental mRNA gene therapy never used in humans before.

Latypova gives an executive summary here going back five years.

Bulletpoints:

  1. Two declarations for CBRN (weapons of mass destruction) emergencies – EUA and PREP Act – made by the U.S. Secretary of Health and Human Services, were registered on this date. [ref][ref]
  2. A pharmaceutical executive was caught on tape saying that the U.S. Department of Defense called to inform him “that the newly discovered Sars-2 virus posed a national security threat.” [ref]
    1. On February 4, 2020, there were fewer than 12 confirmed cases in the US and zero deaths. Worldwide, the death count was less than 500, proving Covid was rooted in national security, not public health. No public health parameters justifying that a novel virus posed a “threat to national security” existed at the time of the EUA and PREP Act declarations. Within 6 weeks of this date, in order to ensure a market for the countermeasures, the lockdown-until-vaccine response – which is a military/counterterrorism plan and has nothing to do with public health [ref] – went into effect all over the world.
  3. Covid was a globally coordinated response, based on legal frameworks intended for biodefense/biowarfare situations. Nothing about the response – masking, distancing, lockdowns, ‘vaccines’ – was part of a public health plan.
Who ordered and directed these operations?
Who benefited from them?

Who was and still is covering them up?

The researchers have been investigating these questions for the last several years, and they hope many who read this will join them moving forward.

CALL TO ACTION

Most journalists in both corporate and alternative spaces are either unaware or unwilling to cover the military/intelligence/biodefense/global coordination aspects of Covid. We need to change that.

Please help us shift the conversation to focus on the true nature of the Covid response and the existential questions raised by it.

The top link also includes dossiers on Australia, Canada, Netherlands, Germany, and Italy as well.

For more:

Military/IC-affiliated groups involved in messaging/propaganda/censorship:

  • Ministry of Defense team [ref]
  • iSAGE [ref]
  • 77th Brigade [ref]
  • Nudge Unit [ref from March 11 2020] / Behavioral Insights Team – now “fully owned by Nesta” (National Endowment for Science, Technology and the Arts) [ref]
  • RAF analysts [ref]
  • Cyber Threat Intelligence League (CTIL) (crossover US/UK)[ref]

Key figures in Covid response linked to military, IC, UN/WHO

  • Roy Anderson [ref]
  • Dominic Cummings [ref][ref]
  • Jeremy Farrar [ref] [ref][ref]
  • Clare Gardiner [ref]
  • Richard Hatchett (crossover US/UK) [ref][ref][ref][ref]
  • Tom Hurd [ref] [ref]
  • Thomas Waite [ref]
  • Simon Manley (UK Director-General Covid-19) [ref]

Asking who is trying to stop us from being healthy should be important to everyone, but particularly to Lyme/MSIDS patients.  You don’t have to be in Lymeland for very long before realizing ‘things are not right.’

“Lyme Monsters: Doctors who repeatedly attack sick patients, advocates, nonprofits, and Lyme literate doctors”.

It’s also important to ask due to the fact an alarming new study shows deaths of Americans aged 25-44 spiked to 70% above the expected rate in 2023.  They examined over 3.3 million deaths.

Predictably ignoring the elephant in the room, drug overdoses, suicides, alcohol, and the pandemic are blamed for the trend, despite the fact the causes of these deaths normally kill much older people, as well as the sudden contribution of cardio–metabolic conditions.

Dr. Pierre Kory notes:

“the inexplicable and unprecedented rises in group term life insurance claims among young people 25-44, which occurred suddenly in the 3rd quarter of 2021 when mandates were all the rage.”

Dr. James Thorp is also sparking widespread concern that babies from COVID ‘vaccinated’ mothers are dying from placentas failing to grow and blood flowing incorrectly to the umbilical cord.

In the following article, A Midwestern Doctor gives the sordid history.  Please remember the many and varied Big Pharma tactics including the fact that Merck created a hit list to ‘destroy,’ ‘neutralize,’ or ‘discredit’ dissenting doctors.  This tactic is common everywhere in ‘public health‘ and the medical industrial complex and was routinely used during COVID.

________________

https://www.midwesterndoctor.com/p/whos-trying-to-stop-america-from?

Who’s Trying to Stop America From Being Healthy Again?

Untangling the century of dark industry tactics that have poisoned the health of America

Silencing Dissent

Since COVID-19 began, those who tried to warn the public about the clear dangers of how we were addressing COVID-19 (e.g., lockdowns, vaccines, and remdesivir) have been targeted and silenced. While many were initially in disbelief our government could do something like this, more cynical parties (e.g., myself) suspected something like this would happen (as it always does) and caught the early warning signs of it.

In my eyes, beyond the over-the-top marketing throughout the media to promote the COVID boondoggle, there were three particularly noteworthy (and interwoven) facets to this campaign:

  1. Widespread censorship of opposing ideas (e.g., GoFundMe deleting fundraisers for individuals who had severe COVID vaccine injuries and nowhere else to turn for help since those fundraisers alerted people to the vaccines not being completely “safe and effective” and most of the news networks refusing to question the COVID narrative). Of note, from the start, I assumed there had to be shadow banning occurring (as I could see the effects of it happen in real time) and coordination between the social media platforms and the Biden administration—an illegal activity which was gradually confirmed by lawsuits (e.g., due to the Twitter file) and other leaks that revealed shadow banning was widespread on the tech platforms.
  2. The establishment targeted anyone who dissented against the narrative in a coordinated fashion. For example, many absurd complaints were used to target the medical licenses of physicians who were saving patients from dying from COVID (e.g., Meryl Nass, whose suspension was so absurd that 13 members of Maine’s legislature formally complained to the medical board about it).
  3. A very aggressive and coordinated campaign to neutralize anyone who disputed the narrative on social media. Early on, I began to suspect this was happening because I’d see the same bad actors (typically doctors) use the same sculpted talking points. In April 2024, I found out an industry funded group did indeed exist, and that: •Many of the people I’d suspected were in a coordinated conspiracy did indeed belong to a secret group (“Shots Heard”) dedicated to fighting misinformation online.  •That group was tied to the Federal Government and funded by the pharmaceutical industry. •That group, one by one, would target dissident healthcare workers and attempt to both get them removed from social media, to have their medical licenses taken away or get them fired from work, and in some cases, to directly harass them at their homes.

(See link for article)

_________________

**Comment**

Once again, a very astute piece by AMD on important history that is imperative to understand.

A brief bullet-point of items discussed:

  • A chronology of the FDA’s war against America’s health and how many toxic food additives got ‘grandfathered’ into or food supply as ‘generally recognized as safe,’ as well as the cutthroat lobbying from the food industry and the resulting monopolization of food.
  • Due to powerful lobbyists defending industries that contribute to poor health, actions to address ‘the root causes of disease,’ are never taken.
  • The power of public relations and the common tactic they underhandedly deploy:
    • by paying a ‘trusted’ 3rd party ‘expert’ to promote their message
    • by creating an organization with a name that implies the opposite of what it actually does and then having the group promote policies that harm their stated cause to support the industry that in turn funds it all

https://johncatanzaro.substack.com/p/n-of-1-trials-the-only-hope-for-long?

N-of-1 Trials: The Only Hope for Long COVID, Spike Protein Complications, and Vaccine-Injured Patients

Signal-Based Medicine | N-of-1 Trials

Feb 03, 2025

The Current Dilemma

The current medical system is failing those suffering from Long COVID and vaccine injuries—patients are gaslit, dismissed, and left to deteriorate without real solutions. The reason? Our healthcare model is built around randomized controlled trials (RCTs), which were never designed for individualized treatment.

What Is an N-of-1 Trial?

An N-of-1 trial is a personalized, single-patient clinical study that aligns treatment based on the individual’s unique biomolecular response. Instead of relying on population-based statistics, this method uses real-time molecular surveillance, patient-specific peptide therapeutics, and adaptive treatment adjustments to achieve true precision medicine.

Unlike traditional one-size-fits-all drug development, N-of-1 trials are built around the patient—tracking their unique exome, transcriptome, and proteome to correct faulty molecular signaling at the source.

We do not have time to wait for mass-scale trials designed for bureaucratic approval pipelines rather than real-world recovery. Lives are deteriorating daily, careers are lost, and families are crumbling. The answer is clear: we need a personalized, adaptive medical model that responds to the patient in real-time—not a slow-moving, industry-driven system.

A Stark Illustration:

Recent breakthroughs in gene-based therapies have demonstrated impressive success in conditions like spinal muscular atrophy, sparking renewed hope for addressing complex neurogenetic diseases. However, many of these interventions are designed to target specific genetic variations, and the rigid structure of traditional clinical trials has created a severe bottleneck in innovation.

Economic and bureaucratic barriers ensure that commercial development is prioritized only for high-prevalence druggable genetic variants— those deemed profitable and feasible for large-scale trials. As a result, countless patients with rare or individualized molecular disruptions are left without viable treatment options, reinforcing the urgent need for N-of-1 trials that bypass these restrictive models and deliver precision-driven solutions in real-time.

Unfortunately, this progress has not extended to Long COVID and vaccine-related injuries, where patients are suffering from Spike-protein-induced immune dysregulation, severe cardiac damage, neuroinflammation, and persistent spike-related organ damage with no viable path to treatment.

The reason is clear: traditional clinical trial models prioritize druggable conditions with large, commercially profitable patient populations while existing N-of-1 trials are still shackled by the same flawed system, failing to deliver the personalized, compassionate care that patients with complex, individualized needs urgently require. The solution is simple: individualized N-of-1 trials must operate independently, untainted by the dysfunction of the current medical research model.

The Catastrophic Failure of RCTs in Chronic Disease

RCTs were designed for standardized drug testing, not complex, multi-systemic conditions like Long COVID and vaccine injuries. These illnesses vary drastically between individuals, yet the medical system continues to force them into rigid study parameters that discard individualized responses.

Why the System Is Broken:

• Deliberate Exclusion of the Suffering – Long COVID and vaccine-injured patients don’t fit neatly into RCT parameters, so they are ignored.

• Slow, Bureaucratic Approval Processes – Years-long trials mean patients deteriorate while waiting for an answer.

• Generalized Data Over Personalized Care – RCTs focus on “majority response,” discarding those who don’t fit the mold.

This isn’t science—it’s systemic neglect.

A System Rigged Against Individualized Care

We don’t see this approach in mainstream medicine because it threatens the financial strength of the pharmaceutical industry.

• Precision-targeted treatments mean fewer mass-produced drugs—which cuts into Big Pharma’s profit margins.

• A truly individualized medical system means fewer hospitalizations, fewer unnecessary interventions, and fewer chronic patients dependent on expensive lifelong medications.

• RCT-based gatekeeping ensures only patented, billion-dollar drugs get approval—while peptide and precision small molecule therapeutics remain buried under regulatory red tape.

This system is not designed to heal people—it is designed to sustain an industry. We Can’t Afford to Wait—Patients Are Deteriorating Now  (See link for article)

Further reading:

  1. https://www.nature.com/articles/s41591-021-01519-y
  2. https://jamanetwork.com/journals/jamaneurology/fullarticle/2829260?guestAccessKey=37236d8c-7c7d-4581-b9a3-a0bc7166de92&utm_source=silverchair&utm_medium=email&utm_campaign=article_alert-jamaneurology&utm_content=olf&utm_term=012725&adv=004812881201
  3. https://ascpt.onlinelibrary.wiley.com/doi/10.1002/cpt.2425

__________________

**Comment**

I was struck with how this article directly pertains to many of the problems in Lymeland.  RCTs have been the bane of research for Lyme/MSIDS.  Because mainstream medicine denies this complex illness can be chronic with persistent pathogen infection, and the inclusion of numerous coinfections, RCTs only include those who test positive on a test that misses nearly 90% of cases, and have a rash that is highly variable.  Maternal-fetal transmission was identified in 1985, but it took 27 years to recognize and investigate. While ‘the powers that be’ acknowledge it can be transmitted congenitally, they still claim it’s rare.  Due to this stance, doctors continue to fail to acknowledge and treat it.

Everything’s rare, until it isn’t.

The sickest patients are not represented in the research.