Archive for the ‘Treatment’ Category

CDC Misses the Mark With Chronic Lyme Disease

https://www.envita.com/lyme-disease/missing-the-mark-with-chronic-lyme-disease

Missing the Mark with Chronic Lyme Disease

Missing the Mark with Chronic Lyme Disease

It is important as one of the nation’s leaders in chronic Lyme disease complex, and after nearly two decades of helping patients, to point out how the CDC has missed the mark entirely with their current study and publication on prolonged treatment for Lyme disease. Unfortunately this information is quite literally too little and too late. Too little, because it is old information and too late, because it offers nothing new to help the many patients that have been suffering. On its face, this small study is designed to discourage physicians from helping their patients.

http://

Chronic Lyme disease Complex, Not Just Chronic Lyme

Patients with chronic Lyme never have just the one infection, they have multiple infections that have gone untested and untreated for extended periods of time. Antibiotics are not even effective for many of these infections, such as with viral, fungal, and parasitic infections.

When chronic Lyme disease is mentioned, most often they are actually referring to chronic Lyme disease complex which involves the spirochete which causes Lyme, Borrelia burgdorferi, and also associated co-infections, which enter the body with Borrelia in the initial tick bite: Babesia, Ehrlichia, Bartonella, Rocky Mountain Spotted Fever etc. Chronic Lyme disease complex can also include secondary infections which occur as a result of a compromised immune state. This is important to keep in mind because antibiotics do not work against viral infections and similarly, fungal infections require antifungal medication and so on. The secondary and co-infections must be identified in order for treatment to be effective. This is the number one reason why antibiotics alone cannot be used to treat these patients.

It is important to understand that Borrelia has a number of mechanisms both for evading and distracting the immune system and that Borrelia is capable of burrowing and spreading throughout most of the body’s tissues, including the blood-brain barrier. Antibiotics cannot easily pass the blood-brain barrier which allows borrelia and others infections like babesia to attack the brain and central nervous system unimpeded. Borrelia implants itself in tissues and within individual cells to avoid being consumed and lysed by the immune system. The microbe is also adept at countering the adaptive immune system through constant variation in its surface proteins, or antigens, a feat enabled by its complex single chromosome and its circular DNA plasmids. Usually, by the time the body can create antibodies to target Borrelia, its surface has already changed so much that the new antibodies are no longer effective. In serum, Borrelia has the ability to inactivate C3, a protein marker which would normally trigger the immune response for free floating microbes. When Borrelia does find a place to settle down and multiply, the microbe secretes a protein mesh called biofilm which shields it and its progeny from direct exposure to many antibiotics and other compounds that might otherwise harm the infection. Our team has published on this subject extensively and we have assembled a great deal of information on the biology and survival mechanisms used by Borrelia in our published study Borrelia burgdorferi: Cell Biology and Clinical Manifestations in Latent Chronic Lyme.

While the spirochete Borrelia is responsible for causing primary Lyme disease, it is usually not the only factor to consider when approaching treatment for chronic Lyme disease, or more commonly, Lyme disease complex. When a tick bites, various bacteria and parasites enter the wound besides just Borrelia. These simultaneous infections are called co-infections and can include Babesia, HHV-6, Epstein-Barr, and Rocky Mountain Spotted Fever, just to name a few. These co-infections are able to gain a firmer foothold in the body and potentially become chronic since Borrelia excels at distracting and depressing the host immune system. Secondary infections can also be picked up after the initial bite due to a depressed immune response from the infected person. The result is a condition that is chronic and can linger for months or even years, typically worsening over time without proper treatment.

In our published study, Chronic Lyme Disease Complex and Its Commonly Undiagnosed Primary and Secondary Co-Infections, we discuss the various co-infections which can coincide with Lyme to form Lyme disease complex. The presence of multiple different infections in the body simultaneously seriously complicates any potential treatment as is discussed below. Many of these other infections complicate treatment and increase the risk for auto-immune diseases depending on the patient’s genetic background and can also be a precursor to various cancers. Treating these infections in their totality is essential to full recovery and for the patient to achieve health which is why often antibiotics alone don’t work clinically.

Single Antibiotic Treatments Inevitably Fail against Lyme Complex

The organism Borrelia has multiple strategies for evading, inactivating, and depressing the immune response including the ability to insulate itself inside tissues and biofilm to avoid contact with substances which might kill it, like antibiotics. A critical flaw with the four randomized trials funded by the CDC to study chronic Lyme disease is that they all used a single antibiotic regimen (ceftriaxone) compared against placebo. As well, this is not typically the antibiotic of choice with a resistant chronic Lyme. Patients’ co-infections also need to be identified in a case of chronic Lyme disease complex. Each patient should receive a personalized regimen based on their infection profile, neurological involvement, immune state and genomics. Also, their ability to eliminate toxins from the body should be evaluated.

With the advent of multi-drug resistant (MDR) strains of bacteria, we have found in our clinical experience that chronic Lyme disease will not respond effectively to antibiotic regimens without the addition of MDR blockers. In chronic patients, these infections have often become “super bugs” and blocking MDR is essential. Also, multiple organisms can survive and propagate within biofilm communities formed by the Borrelia bacteria. This enables Lyme disease to essentially shield other infections from treatment. Adding compounds which are designed specifically to break up biofilm is part of the treatment often needed to help chronic Lyme disease complex. The signs and symptoms of chronic Lyme and the ways in which it evades treatment by antibiotics is outlined in our published paper Chronic Lyme Disease: Persistent Clinical Symptoms Related to Immune Evasion, Antibiotic Resistance and Various Defense Mechanisms of Borrelia burgdorferi.

Another factor which is not considered in any of the published studies listed by the CDC is the genetic variation in the patients. Each person responds to medication in a slightly different way. A lot of this variation is due to Single Nucleotide Polymorphisms (SNP’s) which also make up a large portion of physical differences between humans. SNP’s will cause each patient to metabolize drugs at a greater or lesser rate than the “average person” which is an amalgamate based off of data from thousands of studies rather than a patient’s own particular medical history. Treating patients based off national averages is always risky, which is why people continue to have adverse reactions to medications prescribed by doctors. This personalized testing is essential for several reasons. Finding blocked genes and variations in HLA-DR are highly common in chronic Lyme disease patients, which is why this disease is often linked to autoimmune diseases. Knowing how to access a genetic profile in the Lyme patient is essential to better tailor the therapy and support pathways of elimination as dealing with biotoxins and neurotoxins is a complex problem.

Other than the terribly flawed placebo-driven studies released, the CDC would have you believe that treatments for chronic Lyme disease complex are risky and potentially life threatening. Below, we point out that…

Treatments for Chronic Lyme Are Not Any More Dangerous than Other IV Therapies

The CDC listed five cases of patients who sought treatment for chronic Lyme disease and experienced adverse events due to intravenous therapy. While the article seems to imply that the resulting infections were due to the treatment for chronic Lyme disease, an impartial reader will notice that each of these adverse events occurred after the installation of a permanent port, in particular PICC’s or Peripherally Inserted Central Catheter. The PICC is essentially an open line directly into a central artery near the heart and thus is extremely prone to infection when proper care is not adhered to. That is why at Envita, our physicians and specialized nursing staff do not prefer to use PICC’s with our patients. Instead, if the patient is to undergo extended intravenous therapy for their condition, an implanted subcutaneous port is recommended and we work with the best interventional radiologist to ensure safety. The implanted port is a soft silicone tube inserted below the skin into which a small needle can be used to deliver drugs in a similar way to a PICC. However, a subcutaneous port is covered by skin which makes it lower maintenance for the patient and reduces the risk of infection drastically. Our nursing staff works in this environment daily and excel at making sure patients ports are properly accessed and maintained.

Whenever the skin is broken for any reason, however, there is always a risk for infection, even in a hospital with trained staff; and nowadays, you may be at greater risk of a MDR infection while in a hospital than not. This risk is reduced when doctors and staff follow rigid sterilization protocols while adverse events tend to occur when discipline relaxes. While the risk continues over a greater length of time in treating a chronic ailment like Lyme, the risk does not inherently grow as a result of the duration and just like at any medical facility, the risks are managed with careful attention to detail and patient compliance. As a facility with many years of helping patients we rarely see any infections because our team is very good at what they do and our facility is clean.

There is nothing inherent about therapy for Lyme that places patients at greater risk than other kinds of treatment. The antibiotics and nutritional IV, immune modulators, phytotheraptics and other medications that are prescribed are commonly used as required. At Envita, we prioritize attention to detail and patient safety, that’s why we personalize our treatments to each individual patient and are confident in our work and outcomes.

The articles released from the CDC seem to imply also that chronic Lyme disease is not even a real phenomenon at all and insist that other factors must be the cause for the patients’ symptoms. However the CDC is sadly mistaken. In our many years of work with these infections, we know that they are the cause of many auto-immune diseases and neurological problems. The message the CDC wants everyone to take home is to get “real” medical care for your problem, to keep using pain medications, neurological drugs, steroids, and deal with being bed ridden while suffering and letting your health decline because the conventional approach is best. The fact is these infections are real and patients can improve. Real hope exists when you treat the cause of your disease and not just the symptoms.

Yet curiously, the CDC does not deny that these symptoms do exist and cause detrimental harm to people’s lives, up to and including hospitalization for pain, fatigue, and neurological problems. The CDC does not discuss why, if Lyme disease is not a contributing factor to these symptoms, the patients do not recover after traditional therapy and why these cases continue to appear in areas prone to tick infestations. To dismiss out of hand a potential explanation with inadequate evidence is unusually irresponsible of this institution responsible for guarding the public against infectious agents. Therefore, in our professional opinion, it’s too little (not enough helpful detailed information), too late (leaving patients to suffer and still question the cause of their illness). Maybe the CDC should read our published studies and look at our materials to help them better design studies for the future instead conducting studies of which they already know the outcomes only to mislead and misdirect the public. We make this statement as the CDC has had a very untrusting relationship with chronic Lyme disease issue in this country.

However, at Envita, we have taken the time to specialize and gather all available information about Lyme disease and its impact on the body. We are proud and blessed to see our patients return to health and we let our success stories speak for themselves. If you are interested in learning more about the risks of Lyme disease, feel free to give us a call at 1-866-457-9956 and one of our trained patient care coordinators will be more than happy to answer your questions. You can also learn more about Lyme disease at our webpage here.

_______________

**Comment**

Envita puts out great materials and we are the better for them.  I just love how this article essentially states that the CDC is full of crap – something we all know but it’s nice to hear it from professionals treating this complex disease(s).

For more: https://madisonarealymesupportgroup.com/2019/07/31/post-lyme-disease-syndrome-vs-chronic-lyme-disease-syndrome/

https://madisonarealymesupportgroup.com/2019/03/06/top-7-overlooked-factors-for-treating-lyme-disease/

https://madisonarealymesupportgroup.com/2019/02/25/how-lyme-evades-the-immune-system-video/  Great video

This short 7 min. video from Envita explains:The helper T-cells come along and pick up the processed antigen off the dendritic cell and then passes it along to the killer T cells. The Killer T cells follow the spirochete throughout the body and proceeds to destroy healthy tissues and organs because they can’t differentiate between the antigen of the spirochete and the antigen of healthy tissue.As the killer T cells come into contact with the antigen on the healthy tissue it becomes inflamed and destroys healthy tissue and is autoimmune in nature.


 

Interview With Morgellons Expert Dr. Ginger Savely

Interview With Morgellons Expert, Dr. Ginger Savely

November 8, 2019

You have to fast forward to 8:24 for the start.

Thank God for Dr. Savely.  Morgellons patients are believed even less than Lyme disease patients which hardly seems possible yet is. These poor patients are marginalized and told they are making it all up.

For more on Morgellons:   https://madisonarealymesupportgroup.com/2019/05/29/mixed-borrelia-burgdorferi-helicobacter-pylori-biofilms-in-morgellons-disease-dermatological-specimens/

https://madisonarealymesupportgroup.com/2016/06/17/morgellons-believe-it/

https://madisonarealymesupportgroup.com/2019/08/19/interview-marianne-middelveen-on-morgellons/

https://madisonarealymesupportgroup.com/2019/05/19/skin-deep-the-battle-over-morgellons/

https://madisonarealymesupportgroup.com/2016/12/10/morgellons-in-dogs/

https://madisonarealymesupportgroup.com/2016/12/05/new-book-on-morgellons/

https://madisonarealymesupportgroup.com/2016/10/27/research-on-morgellons/

https://madisonarealymesupportgroup.com/2018/11/16/study-strengthens-association-between-tickborne-infections-morgellons-disease/


Call to Challenge Minnesota Medical Review Board on Ending 5-Year Moratorium to Not Persecute Lyme Doctors

iu-33

Thomas Grier
902 Grand View Ave
Duluth, MN, 55812
218-216-5670

To: ILADS, MLA, LDA, MLA
Attention – Dr. Elizabeth Maloney, Lorraine Johnson, Pat Smith, Phyliss Mervine,

CC. Dr. Eva Sapi, Dr. Alan MacDonald, Dr. Kenneth Leigner, Dr. Robert Bransfield, Dr. Brian Fallon.

https://mnlyme.org
https://www.ilads.org
https://lymediseaseassociation.org/…/the-lyme-wars-are-not…/
https://lymediseaseassociation.org

Dear Lyme disease patient advocates and researchers,

The recent decision of the Minnesota Medical Review Board (MRB) to end their five-year moratorium to not persecute Lyme disease doctors who treat aggressively with antibiotics beyond the IDSA recommended guidelines, is a historic decision that cannot go unchallenged.

During the five-year moratorium in MN, which banned the persecution of doctors who treat tick-borne illnesses aggressively with antibiotics, the MN MRB members only cited a single patient antibiotic study for their actions. This study mostly simply looked at patient’s symptoms after antibiotic treatment.

This and other similar studies relied on the use of defective blood tests like the B-31 based ELISA serology tests, which we know only detects just one Borrelia species. The experts refusal to accept that we are now dealing with over a dozen human pathogenic Borrelia-Lyme species continues to be intolerable.

It was the hard work of several people and groups working together almost 10 years ago to get the MRB to originally agree to the moratorium to allow MN doctors to continue to treat Lyme disease as they see fit. Many of these same advocates have worked on political efforts to protect doctors and patients. Now it is time that we combine politics with PATHOLOGY.

I am asking our most influential Lyme activist groups and researchers to work together to petition our legislators to force the Minnesota Department of Health to do pathology-based brain studies to look for the persistence of Borrelia in dementia and MS brains using state-of-the-art research tools such as FISH stains, confocal Laser Microscopy, Atomic Force Electron Microscopy and more emerging technologies.

Or at the very least we must create an independent review council to review Lyme-Pathology studies published and unpublished showing persistence of Borrelia post antibiotics, and the persistence of Borrelia in the brain, and heart. A council to bring to the MRB any pathology-based associations to chronic illnesses like dementia or MS.

We all know the cost of untreated illness, but our medical insurance providers only see the cost in terms of treatments, and not the cost of long-term medical care for untreated seronegative neurologic patients.

To achieve the goal of getting a State-paid brain pathology study or a pathology review committee; groups and individuals will have to come together and form a take-action committee to define and refine our goals and to assemble teams to lobby our legislative body, our health department and the MRB.

Such topics as multiple Borrelia species, poor blood-tests, immune system evasion, and immune sequestered sites are all huge topics much too big for non-medical legislators to fully understand without proper navigation.

Please support this effort!

Thomas Grier 218-216-5670

__________________

**Comment**

For those just tuning in:  https://madisonarealymesupportgroup.com/2019/11/17/minnesota-medical-board-reinstates-sanctions-on-controversial-lyme-disease-treatment/

Microbiologist Tom Greer makes some astute observations:

  1. A study which only looks at symptoms is very subjective and certainly should NOT become a mandate on how a doctor can and can not treat
  2. There’s a real problem with a  test which only looks at one borrelia species
  3. We desperately need pathology studies which show pathogen persistence as well as the fact it sequesters in tissues making blood tests nearly worthless
  4. On top of all of these points, advocate Carl Tuttle continues to drill home the point that those diagnosed and treated early that remain with symptoms have a completely different disease process than those who are diagnosed and treated late.  For a great read on this: https://madisonarealymesupportgroup.com/2019/02/25/medical-stalemate-what-causes-continuing-symptoms-after-lyme-treatment/  According to microbiologist Holly Ahern, when you add both groups together, there’s a whopping 60% of patients going on to develop chronic/persistent symptoms.

Also, this is another great reason to write your Wisconsin representative and tell them to squash Assembly Bill 313 if you haven’t already done so. More Minnesotans are going to be coming to Wisconsin for treatment. The last thing we need is a panel dictating how our doctors diagnose and treat:  https://madisonarealymesupportgroup.com/2019/11/06/wisconsinites-a-reminder-to-please-write-oppose-assembly-bill-ab313-today/


If Disulfiram is the Cure for Lyme Disease, Should it Be Prescribed to All Lyme Disease Patients?

https://docs.google.com/document/d/1P_Vd-au29HEJb5ZoZbfyBGKPQLUuCsIXzE-vCeOrg1Y/mobilebasic#

If Disulfiram is the cure for Lyme disease,  should Disulfiram be prescribed to all Lyme disease patients?

by Alain Mass, M.D.

Disulfiram is particularly effective on Borrelia Burgdorferi, the Lyme disease bacteria, and Babesia, far more potent than any antibiotics. The difficulty in treating Lyme disease has always been not only to choose the appropriate antibiotics to kill the active bacteria responsible for the disease but also a subpopulation of Lyme disease bacteria, called “persister-cells”, known to stay in a dormant, latent state, avoiding the destructive effect of antibiotics, waking up after the course of antibiotics to cause relapses of the disease. Persisters are largely responsible for high levels of biofilm impeding the effects of antimicrobials. Disulfiram has not only an excellent effect on active Lyme bacteria but also on persister-cells and may, therefore,  be regarded as a true breakthrough in the treatment of Lyme disease not only to treat efficiently but also potentially to eradicate Lyme disease.

Disulfiram is not new and unknown medication. It is an FDA approved- drug that has been used since 1949 for the treatment of alcoholism. Researchers regularly screen medicinal compound libraries to identify molecules that may be effective against specific bacteria. After screening about 7,450 drug molecules, Disulfiram was identified as highly active against both B. burgdorferi and babesiosis, a common Lyme disease coinfection. Its use in the treatment of Lyme disease and other tick-borne diseases is, however, off-label meaning that there is no FDA approval for these indications. The obvious question is why should Disulfiram not be prescribed to all Lyme disease patients?

The first reports presented, first, by Dr. Liegner and later by other clinicians are astonishing by a dramatic and persisting improvement of patients who resisted multiple treatments and by the scarcity of side effects. It does not mean, however, that the medication is safe and can be prescribed without precaution. As for any medication or any new indication, a review of side effects and of the use of Disulfiram must be undertaken and are presented in this article.

Disulfiram dosage

What is the dosage of Disulfiram? The ‘target’ dose for patients of 100 Lbs. or less is 250 mg a day, from 101 to150 Lbs. 375 mg, from 151 to 200 Lbs. 500 mg and from 200 to 300Lbs. 750 mg and above 300Lbs 1 gram a day. Disulfiram dosing in alcoholics was tried in the past at doses up to 3000 mg/day. The precise effective dose and the duration of therapy are, however, still unknown. According to Dr. Liegner, a 6-week duration of therapy may be insufficient. Some say 60 to 90 day and some say 6 to 12 weeks. After this period, the treatment is suspended and the patient is surveilled. Because it takes two weeks for Disulfiram to be cleared from the body, it is recommended to wait for two weeks before increasing the dose. The target dose should never be given at the beginning. Not only the risk of Herxheimer’s reaction is real but the intensity may be severe. To the opposite, all agree that Disulfiram should be started at a very low dose and increased progressively according to a well-defined protocol. It seems that those side effects are dose-dependant. The lowest dose you start with, the less chance you have to encounter side effects. Many will start with 62.5 mg a day every 3 days and slowly will increase up to a maximum dose based on 1weight. Some are more prudent and start even at a dose of 10mg a day. Some will give Disulfiram at the beginning only once a week and will progress as tolerated. Hopkinton Drugs compound Liposomal Disulfiram form down to 25mg/cap, or the powder form down to 10mg… or whatever dose wanted. Disulfiram is also compounded with milk thistle. The main message at the annual ILADS conference in Boston in November 2019 was “start low and go slow.” Patients may be in a hurry to get rid of this chronic disease, to get over with. This is the big temptation and trap to avoid. Dr. Liegner remarks that the beneficial effects may be already noticeable at a very low dose. One more reason not to run after higher doses.

weight initial dose as low as possible following doses are increased every two weeks up to target dose target dose
up to 100Lb 62.5mg a day down to 25 or 10mg/day every 3 days or once a week 250mg/ day
101-150Lb 62.5mg a day down to 25 or 10mg/day every 3 days or once a week 375mg/ day
151-200Lb 62.5mg a day down to 25 or 10mg/day every 3 days or once a week 500mg/ day
201-300Lb 62.5mg a day down to 25 or 10mg/day every 3 days or once a week 750mg/ day
>300Lb 62.5mg a day down to 25 or 10mg/day every 3 days or once a week 1000mg/ day

Can you use Disulfiram alone or do you need to combine it with other drugs?

So far, the tendency is to combine Disulfiram with other drugs. For this, there are at least three reasons. The first one is that we are not sure that Disulfiram works on other co-infections, especially on Bartonella. Co-infections should also be treated. In this regard, comorbidities like mold and/or heavy metal toxicity should be addressed as well. The second reason is not to be confused in case of side effects and to be able to attribute the side effect to the causative drug. The third reason is that more than ever Herxheimer reactions, that can be severe, should always be prevented by a health support and detoxification regimen before and during the treatment.

The question is when to add other drugs. Disulfiram may need other antimicrobials to be fully effective but this may be at the risk of unwanted side effects. Like many other Lyme doctors, I recommend a prudent and progressive approach by starting with Disulfiram alone and by adding as tolerated. Herxheimer’s reactions with Disulfiram may be severe and may be far more severe with the association of other antimicrobials.

Disulfiram pharmacology

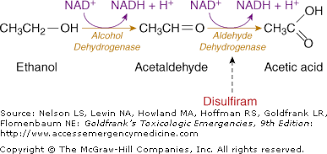
Disulfiram passes the blood-brain barrier and is well distributed throughout the body, working also intracellularly making it a drug of choice for intracellular forms of Borrelia as well as for such other intracellular tick-borne disease bacteria. Disulfiram is completely absorbed from the stomach after oral administration and is broken down in the liver and excreted in the urine. Normally, the enzyme alcohol dehydrogenase in the liver and brain transforms alcohol into acetaldehyde. The enzyme aldehyde dehydrogenase (ALDH), also in the liver and brain, oxidizes the acetaldehyde byproduct into acetic acid. Disulfiram blocks this oxidation by inhibiting ALDH, causing a rapid rise of acetaldehyde in the blood when alcohol is consumed. The result is called a disulfiram-alcohol reaction. The level of acetaldehyde concentration in blood may increase up to 5 to 10 times more than the level occurring without disulfiram. This is responsible for a very unpleasant side effect called the Antabuse effect aimed to discourage alcohol abusers.

The use of Disulfiram in tick-borne disease has, however, nothing to do with the original use of the drug. The mechanism of action in killing Borrelia is still unknown. There are several hypotheses to explain the effect of disulfiram on Borrelia. It is a heavy metal chelator. It also interferes with the Manganese-Superoxide Dismutase system and also inhibits lactate dehydrogenase that is present in the Lyme bacteria. Its action on biofilm is still uncertain. One major consequence of the effect of Disulfiram on alcohol metabolism is that any intake of alcohol during the treatment may cause an Antabuse effect. Not only alcoholic beverages must be avoided but also anything that may contain traces of alcohol including medications, supplements, etc… B. burgdorferi to thrive needs manganese, zinc, magnesium, etc.. Hence, the hypothesis that Disulfiram’s high avidity for metal ions may inhibit the Lyme bacteria metabolism.

Disulfiram efficacy

In 2016, Venkata Raveendra Pothineni and colleagues at Stanford University reported on the new drug against Borrelia burgdorferi, Disulfiram among their top 20 hits. Based on Pothineni’s work, Dr. Kim Lewis of Northeastern University compared the activity of disulfiram against a few other well-known drugs used in the treatment of Lyme disease. In his talk at the Precision Medicine conference, Dr.  Kim

Lewis showed the following slide.

This graph shows the number of colonies remaining after treating Bb with the following four drugs: doxycycline, ceftriaxone, vancomycin, and disulfiram. Disulfiram entirely sterilized the culture—there were no persisters. Caution should be paid that these results are in vitro. No animal or human studies on the efficacy of disulfiram in the treatment of Lyme disease have not yet been published aside from case reports.

Disulfiram and copper

Disulfiram chelates the copper. Copper deficiency may be responsible for neuropathy that may overlap with the Lyme disease neuropathy and Herxheimer’s reactions. Some recommend using enteric-coated capsules to avoid possible copper-related side effects. Keep in mind that Lyme disease may deplete copper, zinc, manganese, iron, and magnesium. The monitoring of these metals is recommended.

Disulfiram and alcohol

It is very important to be aware that only alcoholic beverages contain alcohol but also many medications, supplements, and other products commonly used may contain traces of alcohol that may interact with Disulfiram. Users of Disulfiram should have a list of products containing alcohol and must ask the pharmacist before taking any other product.

https://www.soberlink.com/products-containing-alcohol/

Side effects

Disulfiram toxicity may be classified as follows. The first type of toxicity is due to the interaction between Disulfiram and alcohol.  Secondly, Disulfiram has its own diverse  acute and chronic adverse drug reactions that will be summarized below. The side effects caused by Disulfiram may include effects include :

  • encephalopathy,
  • convulsion,
  • headaches
  • cranial and peripheral neuropathy: Neuropathy, though usually reversible may be irreversible.
  • toxic optic neuropathy,
  • irreversible injury to the basal ganglia with permanent neurological deficits,
  • hypertension,
  • psychosis, possibly due to the inhibition of dopamine beta-hydroxylase,
  • liver injuries which have required liver transplantation and/or resulted in death
  • fatal drug hypersensitivity reaction.
  • Severe permanent neurological injury has been reported in accidental disulfiram poisoning in children  On the other hand, it has been used, apparently safely, in adolescents (16–19 years of age) with alcohol addiction.
  • exfoliative dermatitis and allergic dermatitis: Peaks at about 2 weeks of treatment;
  • Gastrointestinal toxicity: to a lesser degree a rotten-egg odor on breath (sulfide metabolites), garlic-like or metallic aftertaste in the mouth. far more concerning, hypersensitive or toxic hepatitis – that peaks at about 2 months of therapy may be fatal.

Frequently reported aversive reactions are mainly hepatic, neurologic, dermatologic, and psychiatric.

  • Drowsiness is the most common side effect and occurs in up to 5% of patients. It generally resolves after 2 weeks of treatment. Other side effects include dyspnea, sweating, alteration of taste, vasodilation, impotence, amblyopia, dizziness, ataxia.

Disulfiram and psychosis

The possibility of psychosis with Disulfiram is especially of interest because of the inhibitory effect on the enzyme called dopamine-beta-hydroxylase that catalyzes the metabolism of dopamine to norepinephrine. It may, therefore, cause a buildup of dopamine and a depletion of norepinephrine that can potentially cause depression and psychosis.

Drug interactions

Drug interactions with Disulfiram may result from the effects of CYP450, CYP2E1 and other enzymes on drug metabolism affecting significantly the levels of other prescribed drugs, such as warfarin, phenytoin, barbiturates, opioids, tricyclic antidepressants, hypoglycemic agents, antihistamines, benzodiazepines, CNS stimulants, and psychopharmacologic agents.

To check drug interactions: https://www.drugs.com/drug-interactions/disulfiram.html

Monitoring

End of first week End of second week every two weeks
CBC & CMP & Zinc RBC & Cooper RBC & CPK & U/A CBC & CMP & CPK & U/A CBC & CMP & Zinc RBC & Cooper RBC & CPK & U/A

Unanswered Questions

  1. Can disulfiram be used safely in children less than 16 years of age?
  2. Is there any threshold dose below which no serious or irreversible side effects can occur?
  3. Is there any screening test prior to treatment to assess for susceptibility to serious side effects?

Effects on mold

Disulfiram has antifungal effects. The potency, spectrum and clinical relevance, however, are still unclear. Disulfiram is a P-glycoprotein efflux modulator that may have therefore potential antifungal effects. Disulfiram has antifungal activity against Aspergillus spp (1). Disulfiram reverses Cdr1p-mediated drug resistance by interaction with both ATP and substrate-binding sites of the transporter and may be useful for antifungal therapy (2). Disulfiram was also shown to be effective on candida (3)

If Disulfiram is the cure for Lyme disease,  should Disulfiram be prescribed to all Lyme disease patients?

The efficacy of Disulfiram on Borrelia is so far much higher than any other tested antibiotics. Studies at a much larger scale and of longer duration are needed to confirm the efficacy of Disulfiram. The first reports of Disulfiram on Lyme disease are, however, impressive enough for having improved or resolved chronic manifestations of Lyme disease that were resistant to multiple treatments and antimicrobials to consider Disulfiram as a new treatment of choice of Lyme disease. To authorize such a statement, this medication must prove its safety. The review of literature on side effects is concerning and needs to be analyzed at a deeper level. There is no medication without side effects and even the most common medications like Tylenol may have terrifying listed side effects. What allows us to take any way or prescribe medications is the knowledge that the side effects are rare and that the benefits outweigh the risks.

The first consideration to have in mind is that Disulfiram has been prescribed since 1949 to severely alcoholic patients with most often liver abnormalities, neuropsychiatric abnormalities, and nutritional deficiencies. And yet, in one study symptoms of encephalopathy, such as paranoid ideas, disorientation, impaired memory, weakened balance or coordination or slow or slurred speech were reported in only two patients. While a study reports a unique case of an extremely severe neuropathy involving cranial nerves that developed within weeks after regular dosage of 500mg/day disulfiram, the authors of this study admit that such a severe and rapidly-progressive course has never been described with disulfiram doses of only 500mg/day. Irreversible Parkinsonism has been reported but in only two patients. In 1979, The Western Journal of Medicine reported that only 47 cases of Disulfiram-induced psychosis were known after 30 years of use, noting that doses used to be much higher (up to 2,000 mg per day) than current doses. Only 8 cases of psychosis reported between 1992-2016 in PubMed. The causative effect of Disulfiram on psychosis is also questionable. Patients who received Disulfiram were prone to psychosis due to alcoholism and comorbidities. Psychosis could also have been due to Herxheimer’s reaction. I asked Dr. Liegner at the ILADS annual conference whether the dopamine beta-hydroxylase should be checked or not before treating to screen who is more predisposed to psychosis. His response was negative because the test is difficult to perform, probably expensive and most of all because a “start low and go slow” approach should avoid or minimize the occurrence of side effects. The British Medical Journal in 1977 reported 6 cases of liver damage and concluded that the evidence that disulfiram caused severe liver damage was only circumstantial. Here, too, Disulfiram has been given since 1949 to patients with liver often affected by alcohol. Toxic hepatitis that may be fatal has a fatality rate of approximately 1 in 25,000 cases.

Conclusion

Disulfiram is a drug, known since 1949 that may be the most potent drug against Lyme disease, superior to any other antibiotics but that may also cause serious side effects that may be irreversible.  The benefits of a drug must always outweigh the risks. Like any drug, potential side effects, almost always, are possible. The significance of side effects, however, should be related to the frequency of these side effects, the dose of the medication, the targeted population, and the indication. The side effects that are reported by the medical literature occurred were rare, for much higher doses than those used for Lyme disease, in severely alcoholic patients prone to liver disease, psychosis, malnutrition, and other comorbidities. Side effects should be expected to be even rarer in the Lyme disease population at much lower doses and beneficial effects already occurred at low doses. Higher doses may even not be necessary, especially when associated with other Lyme disease antimicrobials.

It is probably safe when “start low and go slow”. An expression that has been repeated several times at the ILADS conferences, which conveys the main message about Disulfiram. “probably safe” for a new medication or for a new indication does not mean safe for all. One cannot promise that individualized or extremely rare severe reactions will never happen. Dr. Liegner told that one of his patients who experienced a psychotic episode begged him not to discourage other patients to take Disulfiram because even despite this psychotic episode the patient felt so much better that he was not bothered by this incident. Disulfiram should certainly be prescribed with caution or avoided in patients with personal and familial antecedents of psychosis. Case reports are, however, not enough to guarantee the safety of a drug. Studies at larger scales are necessary. Some questions still remain unanswered. 1) are the side effects only dose-dependant? In other words, is there any threshold dose below which  no serious or irreversible side effects can occur? 2)  Is there any test that may help to predict who may be more susceptible than others to have serious side effects, especially psychosis or neurological complications? We know that Disulfiram inhibits the enzyme Dopamine-beta-hydroxylase responsible for the conversion of Dopamine to norepinephrine. Individuals who genetically have a deficit in this enzyme are more prone to psychosis and depression and will probably be more vulnerable to Disulfiram.  We may also, therefore,  consider with caution or to avoid Disulfiram in the presence of genetic abnormalities or variants that may predispose to higher levels of dopamine.

As long as these questions are not answered, the benefits would not outweigh the risks by starting with Disulfiram before giving a chance to other drugs known to be safer. Dr. Liegner states: “ Disulfiram appears to have conferred benefit in the treatment of a limited number of patients with Lyme disease and babesiosis in a clinical setting. Formal controlled trials of this agent for the treatment of Lyme disease and babesiosis may be warranted along with elucidation of mechanisms of its apparent anti-borrelial and possible anti-babesial effects.” Dr. Liegner at the ILADS conference discouraged to use Disulfiram as the first treatment for Lyme disease but to reserve this remarkable new pharmaceutical weapon to patients who failed multiple treatments. Selection of the right patient, patience, prudence, monitoring clinical signs and laboratory markers are key to success. As long as we do not know for sure if below a certain threshold dose no serious neuropsychiatric side effects may happen, I recommend testing especially for copper, zinc and neurotransmitters prior to starting a treatment.

Case report

My first case of Disulfiram.

16 years old boy who has suffered for the past 10 years of chronic sinusitis with severe daily 7-8/10 of intensity, lasting for days, maxillary and frontal headaches with nasal congestion with post nasal drip but without runny nose even when he blew his nose since the age of 6 years old. He saw multiple ENTs, neurologists, allergists and one infectious disease specialist at Montefiore, NYC who all diagnosed with chronic sinusitis that resisted Zithromax, amoxicillin, Augmentin, Duricef, and Netipot. The mother refused surgery that was offered. The CT scan only showed deviated septum and a polyp but no collection of pus. As a result of the past 10 years of chronic pain, the patient missed a significant amount of time at school. The patient came to see me for the first time on July 2019 for multiple symptoms of multiple systems alluding to tick-borne disease but also to mold toxicity with known mold exposure and known sensitivity to mold as symptoms got exacerbated by mold exposure. At that time the patient who was found to have Lyme disease by blood serology already received by another physician Doxycycline and rifampin that did not improve the symptoms. The workup revealed positive IgE for C herbarium, Low copper but normal ceruloplasmin and normal 24 urine copper, elevated CRP at 7.6. and of hyperthyroidism with a free T4 at 1.62, low IgG 10.7. The Bartonella serology was negative but there are Bartonella striae. Brucella IgM and Mycoplasma were positive. The porphobilinogen was elevated. 4.2 (<2.4). MMP9 is mildly elevated. CD57 is 13 Ochratoxin highly positive and positive Citrinin on the mycotoxin urine test. ERMI is pending.

I started by giving Resveratrol, GI detox, S-Acetyl-Glutathione, NAC, ALA, Burbur-Pinella, Phosphaline, Biocucurmin, Medcap DPO, Magnesium, Quercetin, Claritin, Cromolyn, Zantac and later silver nasal spray was added. Since this treatment only caused a mild improvement, I started Disulfiram at the dose of 62.5mg every three days on 09/21/2019. Happening the next day, the patient started to have a continuous runny nose of greenish thick whitish for two weeks. Now the headaches are 1-2/10 of intensity and the frequency once a week. Before Disulfiram headaches were every day.

Now after 6 weeks he takes Disulfiram 125mg every three days:

The following symptoms have completely disappeared

  • – Blurred vision and Cloudy
  • – Migratory numbness, tingling in feet, stabbing pain & ice-pick like pain
  • – New onset of impairment in the assimilation of new knowledge
  • – A decline in performances at school
  • – New onset of difficulty reading comprehension
  • – Disorientation making it difficult to find the way
  • – Anxiety
  • – Teary eyes
  • – Palpitations
  • – Right-hand cramps
  • – Neck crack
  • – Foot pain
  • – Difficulty breathing, nasal obstruction, chronic cough, air hunger
  • – Sleep disorder
  • – Orthostatic dizziness
  • – Near-syncope episodes
  • – Itching

Got improved

  • Memory impairment recent and old events: on and off
  • Depression: on and off

Did not get improve

  • Fatigue
  • Vertigo
  • Twitching
  • Dizziness
  • Brain fog
  • Difficulty finding words
  • Stuttering since 4th grade
  • Wording difficulty, reverse words
  • OCD
  • Chest pain or rib cage pain
  • Red eyes
  • Hypersensitivity to light
  • Migratory muscle pain and joint pain (mostly back and also both knees but at different times
  • Mild abdominal pain, constipation (Admits lactose intolerance)
  • Cold hands
  • Excessive unexplained sweats

Effects on mold

Before the treatment with Disulfiram, when he was exposed to mold he felt all of the symptoms above. Today when exposed to mold school or home and on Disulfiram he only feels the following remaining symptoms: fatigue, headaches, sweats, nasal cavity pain, red eyes, nausea, eye burning. The fatigue before Disulfiram was 10/10 now 8/10, headaches 10/10 now 8/10, nausea was 10/10 and now 6-7/10. Most of the symptoms that used to be exacerbated by mold exposure disappeared.

side effects

none

Alain Mass, M.D.                                                                                                                                                                                      Member of the International Lyme and Associated Disease Society (ILADS),                                                   Diplomate of International Society for Environmentally Acquired Illness (ISEAI)

400 Rella Boulevard, suite 165                                                                                                                                                                             Montebello, NY                                                                                                                                                                                                                      Tel: (845) 623-0047                                                                                                                                         contact@massfunctionalmd.com

(1) Antifungal potential of disulfiram. Khan S1, Singhal S, Mathur T, Upadhyay DJ, Rattan A. Department of Infectious Diseases, New Drug Discovery Research, R and D III, Sarhaul, Sector-18, Ranbaxy Research Laboratories, Gurgaon-122001, India.

(2) Disulfiram is a potent modulator of multidrug transporter Cdr1p of Candida albicans. Shukla S1, Sauna ZE, Prasad R, Ambudkar SV. Laboratory of Cell Biology, Center for Cancer Research, National Cancer Institute, National Institutes of Health, Bethesda, MD 20892-4256, USA.

(3) Repurposing FDA approved drugs against the human fungal pathogen, Candida albicans  Kevin Kim, Leeor Zilbermintz & Mikhail Martchenko Annals of Clinical Microbiology and Antimicrobials  volume  14, Article number: 32 (2015)

___________________

For more:  https://madisonarealymesupportgroup.com/2019/06/03/disulfiram-in-the-treatment-of-lyme-babesiosis-3-case-reports/

https://madisonarealymesupportgroup.com/2019/07/14/disulfiram-breakthrough-drug-for-lyme-other-tick-borne-diseases/

https://madisonarealymesupportgroup.com/2019/07/26/is-disulfiram-the-magic-bullet-for-chronic-lyme-disease/

https://madisonarealymesupportgroup.com/2019/10/15/disulfiram-psychosis-update/

https://madisonarealymesupportgroup.com/2019/10/27/disulfiram-psychosis-update-2/

https://madisonarealymesupportgroup.com/2019/09/18/dr-liegner-interview-on-disulfiram/

Link Between Inflammation & Mental Sluggishness Shown & How MSM, Systemic Enzymes, and Melatonin Can Help

https://neurosciencenews.com/inflammation-mental-sluggishness

Link between inflammation and mental sluggishness shown

Summary: Inflammation appears to have a negative impact on attention and cognition.

Source: University of Birmingham

Scientists at the University of Birmingham in collaboration with the University of Amsterdam have uncovered a possible explanation for the mental sluggishness that often accompanies illness.

An estimated 12M UK citizens have a chronic medical condition, and many of them report severe mental fatigue that they characterize as ‘sluggishness’ or ‘brain fog’. This condition is often as debilitating as the disease itself.

A team in the University’s Centre for Human Brain Health investigated the link between this mental fog and inflammation – the body’s response to illness. In a study published in Neuroimage, they show that inflammation appears to have a particular negative impact on the brain’s readiness to reach and maintain an alert state.

Dr Ali Mazaheri and Professor Jane Raymond of the University’s Centre for Human Brain Health, are the senior authors of the study. Dr Mazaheri says:

“Scientists have long suspected a link between inflammation and cognition, but it is very difficult to be clear about the cause and effect. For example, people living with a medical condition or being very overweight might complain of cognitive impairment, but it’s hard to tell if that’s due to the inflammation associated with these conditions or if there are other reasons.”

“Our research has identified a specific critical process within the brain that is clearly affected when inflammation is present.”

The study focussed specifically on an area of the brain which is responsible for visual attention. A group of 20 young male volunteers took part and received a salmonella typhoid vaccine that causes temporary inflammation but has few other side effects. They were tested for cognitive responses to simple images on a computer screen a few hours after the injection so that their ability to control attention could be measured. Brain activity was measured while they performed the attention tests.

On a different day, either before or after, they received an injection with water (a placebo) and did the same attention tests. On each test day, they were unaware of which injection they had received. Their inflammation state was measured by analyzing blood taken on each day.

The tests used in the study assessed three separate attention processes, each involving distinct parts of the brain. These processes are: “alerting” which involves reaching and maintaining an alert state; “orienting” which involves selecting and prioritizing useful sensory information; and “executive control” used to resolving what to pay attention to when available information is conflicting.

The results showed that inflammation specifically affected brain activity related to staying alert, while the other attention processes appeared unaffected by inflammation.

This shows a red brain

“These results show quite clearly that there’s a very specific part of the brain network that’s affected by inflammation,” says Dr Mazaheri. “This could explain ‘brain fog’.”

Professor Raymond says,

“This research finding is a major step forward in understanding the links between physical, cognitive, and mental health and tells us that even the mildest of illnesses may reduce alertness.”

Dr Leonie Balter the first author of the study which was completed as part of her PhD, concluded:

“Getting a better understanding of the relationships between inflammation and brain function will help us investigate other ways to treat some of these conditions. For example, further research might show that patients with conditions associated with chronic inflammation, such as obesity, kidney disease or Alzheimer’s, could benefit from taking anti-inflammatory drugs to help preserve or improve cognitive function.”

“Furthermore, subtle changes in brain function may be used as an early marker cognitive deterioration in patients with inflammatory diseases.”

The next step for the team will be to test the effects of inflammation on other areas of brain function such as memory.

ABOUT THIS NEUROSCIENCE RESEARCH ARTICLE

Source:
University of Birmingham
Media Contacts:
Beck Lockwood – University of Birmingham
Image Source:
The image is in the public domain.

Original Research: Open access
“Selective effects of acute low-grade inflammation on human visual attention”. Ali Mazaheri et al.
NeuroImage doi:10.1016/j.neuroimage.2019.116098.

Abstract

Selective effects of acute low-grade inflammation on human visual attention

Illness is often accompanied by perceived cognitive sluggishness, a symptom that may stem from immune system activation. The current study used electroencephalography (EEG) to assess how inflammation affected three different distinct attentional processes: alerting, orienting and executive control. In a double-blinded placebo-controlled within-subjects design (20 healthy males, mean age = 24.5, SD = 3.4), Salmonella typhoid vaccination (0.025 mg; Typhim Vi, Sanofi Pasteur) was used to induce transient mild inflammation, while a saline injection served as a placebo-control. Participants completed the Attention Network Test with concurrent EEG recorded 6 h post-injection. Analyses focused on behavioral task performance and on modulation of oscillatory EEG activity in the alpha band (9–12 Hz) for alerting as well as orienting attention and frontal theta band (4–8 Hz) for executive control. Vaccination induced mild systemic inflammation, as assessed by interleukin-6 (IL-6) levels. While no behavioral task performance differences between the inflammation and placebo condition were evident, inflammation caused significant alterations to task-related brain activity. Specifically, inflammation produced greater cue-induced suppression of alpha power in the alerting aspect of attention and individual variation in the inflammatory response was significantly correlated with the degree of alpha power suppression. Notably, inflammation did not affect orienting (i.e., alpha lateralization) or executive control (i.e., frontal theta activity). These results reveal a unique neurophysiological sensitivity to acute mild inflammation of the neural network that underpins attentional alerting functions. Observed in the absence of performance decrements, these novel findings suggest that acute inflammation requires individuals to exert greater cognitive effort when preparing for a task in order to maintain adequate behavioral performance.

___________________

**Comment**

As most of you are aware, Lyme/MSIDS patients suffer with infection, inflammation, insomnia, and quite often – brain fog. Finding successful ways of treating each of these issues is part of treatment success.  Personally, I’ve found a number of things to help with these issues.  One is an inexpensive supplement called MSM:  https://madisonarealymesupportgroup.com/2018/03/02/dmso-msm-for-lyme-msids/  Another is called systemic or proteolytic enzymes:  https://madisonarealymesupportgroup.com/2016/04/22/systemic-enzymes/ and https://madisonarealymesupportgroup.com/2018/03/05/how-proteolytic-enzymes-may-help-lyme-msids/.  Even though I am done with Lyme/MSIDS treatment, I still take both substances as they do so many good things for the body including:

  • Control inflammation throughout the body, not just in your joints.
  • Repair and rebuild the cardiovascular system.
  • Optimize blood flow & cleanses blood of debris
  • Prevent and dissolve blood clots by dissolving fibrin
  • Dissolve plaque in your arteries and dental plaque in your mouth.
  • Clean up your immune system.
  • Minimize the impact of allergies but breaking down and removing circulating immune complexes.
  • Improve the ability to exercise and speed up recovery times.
  • Kill bacteria, viruses, and other pathogens.
  • Accelerate recovery from sprains, strains, fractures, bruises & surgery
  • Help with arthritis
  • Help with detoxification
  • Improve body alkalinity
  • Help with sinusitis and asthma
  • Help reduce MS symptoms

Another supplement I’ve taken for years is melatonin, which according to Dr. Mercola, also reduces inflammation and is neuroprotective by strengthening the blood-brain barrier.

https://articles.mercola.com/sites/articles/archive/2019/11/18/melatonin-reduces-inflammation

Melatonin Has Anti-Inflammatory and Metabolic Effects

Analysis by Dr. Joseph Mercola
melatonin benefits

STORY AT-A-GLANCE

  • Melatonin is responsible for your sleep/wake cycle and it plays an important role in fighting inflammation and weight gain
  • It affects your immune system, gut health, pain level, blood pressure and recovery from stroke and traumatic brain injury
  • You can naturally boost your melatonin levels by getting at least 15 minutes of sun exposure in the morning, among other ways
  • Melatonin has a safe track record with few adverse reactions, but its long-term effects are unknown; supplementation may not be safe for those taking certain medications or dealing with specific health conditions

Your body is a complex organism requiring quality sleep to function optimally. Your body’s circadian rhythms are a combination of biological clocks regulating everything from your metabolism to psychological functioning. One sure way to cause dysregulation of your biological clock is to skimp on sleep.

Although you have a master clock in your brain to synchronize bodily functions, every organ and cell has its own biological clock as well. In a stunning discovery published in 2017, researchers found half your genes are controlled by circadian rhythms that turn them on and off in a cyclical wave.

The whole-body circadian rhythm is largely dictated by your pineal gland, which is responsible for secreting melatonin or N-acetyl-5-methoxytryptamine. This hormone normalizes your circadian rhythm as it signals your body it’s time for sleep. The production of melatonin will depend on how much and when your body absorbs light.

The gland is located near the center of your brain and usually starts secreting melatonin near 9 p.m. Without an adequate amount of sleep and exposure to sunlight, your levels will naturally drop. Researchers have found an association between melatonin and rising levels of inflammation.

Melatonin Reduced Inflammation and Obesity Markers in Mice

In a combined effort, scientists from universities in Brazil and Italy1 sought to identify the role melatonin may have in improving disorders commonly found in those who are obese. The researchers used mice who were induced to become obese and treated them for 10 weeks with melatonin.

The objective was to determine if the hormone could effectively delay or block the damage from eating too much. The researchers found multiple results supporting their theory that melatonin supplementation could have a significant effect on the animals, including reducing triglyceride levels and total and LDL cholesterol levels.

They also found that supplementation prevented larger weight gain by reducing the formation of fat tissue and increasing the capacity to break down white fat. This combination of effects helped to prevent the hypertrophy of fat cells caused by excessive eating.

Additionally, the researchers noted the supplementation reduced a characteristic inflammatory process found in obese subjects where macrophages infiltrate adipose tissue. The mice also experienced a reduction in inflammatory related factors through a decrease in gene expression.

Overall, at the end of the 10-week trial, the group of mice eating an excessive amount without melatonin gained 49% body mass over the control group that ate a normal diet. The group of mice supplemented with melatonin increased their body mass 28% over the control group, but 13% lower than the group eating excess food without melatonin.

The researchers believe the data suggest that melatonin could be considered as a therapeutic agent to help mitigate the metabolic and inflammatory conditions triggered in those who are obese.

The Importance of Melatonin to Sleep/Wake Cycles

As with many hormones and chemicals in the body, melatonin has more than one function. The best known role it plays is in controlling your sleep/wake cycle. This well-publicized function may be due to the fact that sleep plays a significant role in your overall physical and mental health.

An estimated 40% of Americans are sleep deprived every day, with many people getting less than 5 hours of sleep per night. Millions struggle to fall asleep and others find it challenging to stay asleep. Some wake up too early in the morning.

There are a number of hazards associated with sleep deprivation; you can read about these in my past article, “Nobel Prize-Winning Science Highlights Importance of Good Sleep for Health.”

Melatonin is a marker your body uses to influence what time of day or night it thinks it is. This happens regardless of the actual time. During a normal night of sleep, levels stay elevated for about 12 hours. As the sun rises, the pineal gland reduces production until the level in your blood is hardly measurable.

If you experience disruption to your circadian rhythms, your body will produce less melatonin and you will experience poor quality sleep. This can happen to those who work the night shift, have jet lag or are exposed to light during the night.

Melatonin Benefits More Than Sleep

A deficiency in this hormone may come with profound biological risks, such as potentially having higher levels of inflammation, a weaker immune system and an increased chance of developing cancer. The hormone interacts with receptor proteins that help control the different stages of sleep and are present in other organs and immune cells.2,3

Additionally, melatonin is a potent antioxidant that can raise the levels of other antioxidants, such as glutathione. Melatonin plays a role in the health and survival of mitochondria,4 your body’s powerhouse, where energy production takes place at a cellular level.

Melatonin has shown some promise for pain control in those suffering from endometriosis. In one study,5 10 mg per day decreased pain by 39.8% and dysmenorrhea by 38.01%. Topical application may help prevent sunburn,6 while oral supplementation was 150 times more effective at treating tinnitus as compared to other drugs. Melatonin may also play a protective role in:7

Delayed sleep phase syndrome Strengthening the blood-brain barrier Amyotrophic lateral sclerosis (ALS)
Reducing transplant complications Recovery from stroke and traumatic brain injury Diabetes
Vision and eye health Parkinson’s disease Thrombocytopenia
Gut health Jet lag Blood pressure and heart health
Acid reflux Aging Fertility

Boost Your Melatonin Naturally

Melatonin does come in supplemental form, but it’s also possible to raise your levels naturally. Researchers recognize nonpharmacological approaches to insomnia include better sleep hygiene, physical exercise and mindfulness meditation.

It makes sense to engage in simple habits to increase your natural production and improve your overall health and sleep without adding supplements. Four simple strategies include:

• Sunshine during the morning — Melatonin is affected by your exposure to light and dark. When it’s light, production of melatonin naturally drops. Getting at least 15 minutes of sunlight in the morning hours helps to regulate the production of melatonin, dropping it to normal daytime levels, so you feel awake during the day and sleep better at night.

• Sleep in the dark — Your body produces and secretes melatonin in the dark, helping you to go to sleep and stay asleep. Sleeping in a completely darkened room, without lights from alarm clocks, televisions or other sources will improve your sleep quality.

If you get up during the night to use the bathroom, it’s important to keep the lights off so you don’t shut off your production of melatonin. Also, wear blue-light blocking glasses after sunset to avoid blue-light exposure.

• Lower your stress level and your cortisol level — The release of melatonin is dependent on the release of another hormone, norepinephrine. Excess stress and the resulting release of cortisol inhibits the release of norepinephrine, and therefore the release of melatonin. Stress-reducing strategies you may find helpful before bed include yoga, stretching, meditation and prayer.

• Increase foods high in magnesium — Magnesium plays a role in reducing brain activity at night, helping you to relax and fall asleep more easily. It works in tandem with melatonin. Foods containing higher levels of magnesium include almonds, avocados, pumpkin seeds and green, leafy vegetables.

Supplementation and Potential Negative Effects

The beneficial effects associated with melatonin suggest it may primarily have a function as an antioxidant. In speaking with Time magazine, Helen Burgess, co-director of the Sleep and Circadian Research Laboratory at the University of Michigan, said:8

“Some of the emerging science is showing that in people with higher levels of inflammation — which could be because they’re obese, or because they’re in the [intensive care unit] for a transplant — melatonin in the range of 6 mg to 10 mg may decrease markers of inflammation.”

The authors of past studies have associated a deficiency in melatonin with obesity. It also may address inflammation, as supplementation has been associated with lowering oxidative stress and regulating adipokines involved in the inflammatory process. While believed to be relatively safe for up to 18 months, the long-term effects are largely unknown.

Possible negative interactions have been suggested for those with epilepsy or those taking Warfarin, a blood thinner. Melatonin is sometimes used in children to benefit those with sleep disorders, but long-term effects in children are also unknown. There has been some research suggesting that using melatonin during puberty may interfere with natural production of the hormone.

Researchers leading one study cautioned that supplementation should be limited in those with attention deficit hyperactivity disorder. They suggest considering the supplement only for those who also have chronic insomnia. It’s crucial to remember that melatonin is a hormone, and long-term supplementation with hormones can have unknown effects on the body.

In addition to the strategies listed above to boost your natural production, you may benefit from sleep habits information in my past article, “Top 33 Tips to Optimize Your Sleep Routine.”