Archive for the ‘Lyme’ Category

Autophagy Treatment For Spike Protein Damage and Beyond (Lyme/MSIDS?)

https://www.sciencedirect.com/science/article/pii/S2666396124000074

Exploring autophagy in treating SARS-CoV-2 spike protein-related pathology

https://doi.org/10.1016/j.endmts.2024.100163Get rights and content
Under a Creative Commons license
open access
 

Abstract

Fasting, a practice with historical roots in various cultures, has recently garnered significant interest in the field of medicine. In this article, we delve into the mechanisms underlying fasting-induced autophagy and its therapeutic applications for spike protein associated pathology. We explore the therapeutic potential of fasting on spike protein-related pathology and the role of interventions to upregulate autophagy, including compounds like spermidine, resveratrol, rapamycin, and metformin.

In conclusion, fasting, coupled with an understanding of its nuances, holds promise as a therapeutic intervention for SARS-CoV-2 spike protein related diseases; with broad implications for human health. This review presents the therapeutic possibility of using autophagy to treat spike protein related diseases, and details the interventions to deploy this therapeutic modality.  (See link for article)

_____________

**Comment**

Finally a treatment that is FREE and will actually save you money.  

I personally believe fasting helps everything – even if you are ‘healthy.’  It gives the body, a hard working machine, a well-deserved rest.  It isn’t fun, but with patience and practice, it can yield results nothing else can compare to.

I highly recommend reading: https://www.greenleafbookgroup.com/titles/starving-to-heal-in-siberia

In Starving to Heal in Siberia, Dr. Michelle Slater takes us on her journey from her bed, where she was sidelined much of the time, to Siberia, where she was cured of the debilitating effects of advanced Lyme disease. After a years-long struggle with extreme chronic fatigue, brain fog, joint pain, and other mysterious symptoms that ultimately prevented her from teaching and doing simple tasks like reading and driving, Michelle began considering assisted suicide. She had tried every known treatment, from aggressive allopathic methods to holistic remedies, without success. In a last-ditch effort to save her life, she found a radical alternative treatment offered by the world’s leading expert on dry fasting and traveled to Siberia to give it a chance.

http://  Approx. 32 Min

She recovered completely from Lyme disease, regaining her memory and returning to researching, writing, hiking, and running. Since 2017, she has not experienced a single symptom.

Here’s where you can find her: https://michelleslater.com/ https://www.instagram.com/michellesla… https://LifestyleLocker.com/Michelle_… 

For more:


Sharp Rise in Lyme Cases Due to Change in How They Are Reported

https://www.lymedisease.org/sharp-rise-in-lyme-cases/

Sharp Rise in Lyme Cases Due to Change in How They Are Reported

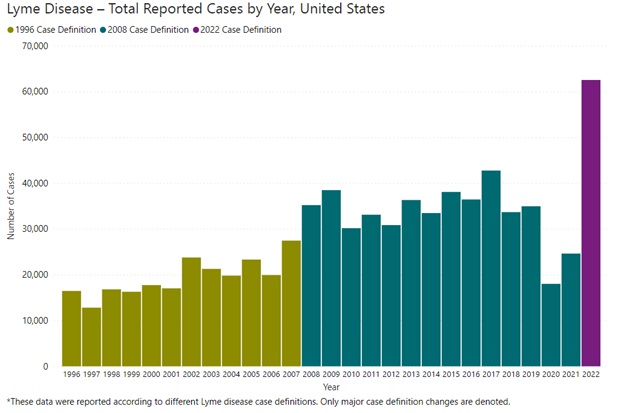
Reported Lyme disease cases in the U.S. rose nearly 70% in 2022. The CDC says it’s not because of a large increase of new infections, but rather because of a change in reporting requirements.

According to the CDC, there were more than 62,000 reported cases in 2022. This was up from about 37,000 a year from 2017 through 2019.

Although the CDC estimates that about half a million people get Lyme disease in the US every year, “reported cases” are those which follow a strict case definition and specialized requirements.

In the past, in order for a Lyme case to be officially counted, local health departments needed to go through a complicated verification process for each case. In 2022, reporting requirements were eased in states the CDC considers “high incidence.” In those states, Lyme cases are now counted based solely on a positive Lyme test.

Read more here:

Centers for Disease Control and Prevention

CNN

______________

**Comment**

Ha, ha, ha….this is a joke.

The chance of getting a positive test is akin to winning the lottery, so numbers in reality are exponentially higher yet.

For more:

It’s important to clearly understand that government sanctioned Lyme testing (like COVID testing) is utterly useless:


Core Principles for Healing Tick Borne Disease

http://projectlyme.org/wp-content/uploads/2024/01/10B-Approah-Handout.pdf  Click here for Dr. Hinchey’s printable sheet

Core Principles for Healing Tick Borne Disease

By Dr. Hinchey

I highly recommend you print out Dr. Hinchey’s sheet, study it, and take it along with you to your doctor appointment.  There are wonderful talking points and issues that every patient should consider.  Remember – you are a partner with your doctor in this journey and need to learn as much as you can.  As they say, “two heads are better than one.”

That said, I actually learned the most from listening to other patients and reading books and articles on my own.  There’s nothing like experience as a teacher.  Just remember that what works for one patient, may not work for another – so always keep an open mind and be willing to experiment.  As one person put it, “Lyme is a ‘do it yourself’ disease.”  Truer words were never spoken.

It’s also important to state here that sometimes you hit a roadblock with your practitioner.  Perhaps their mind is closed or you just feel they aren’t listening, etc.  After trying to work with them, you may need to consider moving on and changing doctors at some point; however, I must warn you that there are many, many bumps in this road as well as plateaus so be patient and reasonable.  Nothing about treating Lyme/MSIDS is quick or easy!

For more:

Implicit Costs of Illness

https://projectlyme.org/implicit-costs-of-illness/

Implicit Costs of Illness

By Grace Burns

2/7/24

Grace is earning her Master’s degree in Sustainability Management at Columbia University, works at S&P Global, and is a member of Project Lyme’s Junior Board.

My Journey

When facing illness, the last thing on your mind is the price of delivery for an at-home Covid test or order of chicken noodle soup from a local restaurant. Or is it?

As medication, food, and personal wellness prices rise amongst a price gauged economy, the cost of being sick grows increasingly staggering. As a Chronic Lyme and POTS patient for eight years, financing sickness has become woven into the fabric of my short-term and long-term budgets.

I first became sick at 16 years old; the financial burden of my care fell on my parents. My public-school teacher Mom would take sick days to take me to countless doctor’s appointments, take credit cards out to pay for MRIs, and skimp on annual family vacations in lieu of schlepping me to specialists across the country.

Neither my doctors nor my family expected me to need treatment at age 24. The financial burden has now shifted to me, aptly parallel to my transition to adulthood.

When I suffer from cyclical declines in my health: bouts of fevers, chills, flu-like symptoms, neuropathy, migraines and cognitive fogging, I notice a sharp uptick in my daily and weekly expenses. But how much could some broth and Kleenex be, anyway?

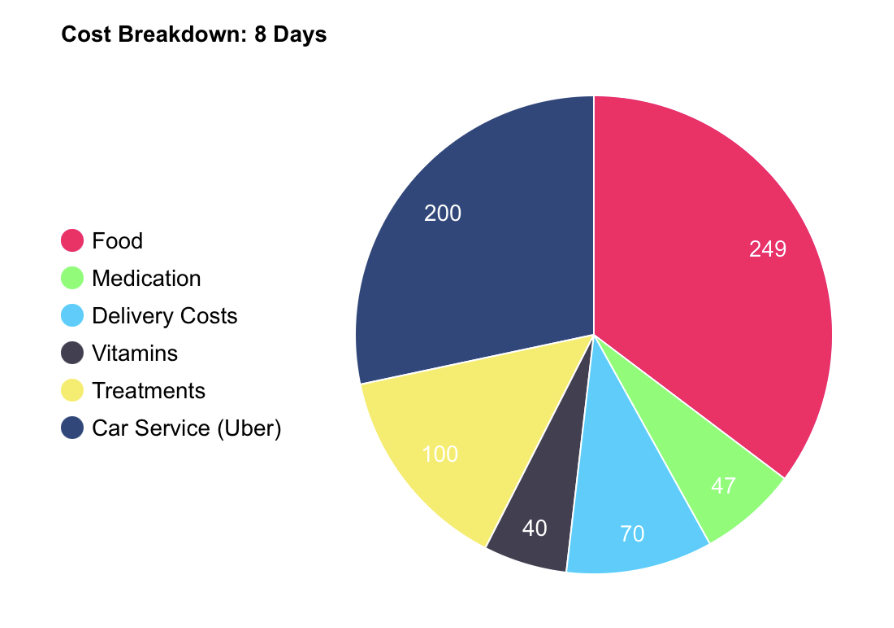
Most recently, I suffered from an eight-day long bout of illness related to my chronic Lyme. Below is a breakdown of my expenses across the eight-day span only related to being sick.

The above breakdown denotes expenses made during this bout of sickness, but are generally reflective of the categorical spending areas that increase when I am sick.

By The Numbers

Healthcare in the United States costs $12,555 per person annually. Omitted from that figure are the many ancillary services not listed strictly within the healthcare space. My loss in cognitive and muscle function requires me to get food delivered to my apartment. If I have to leave I use a car service like Uber, as I am too sick to walk, regardless of the distance.

Many of these expenses aren’t within reach for the average person; the tradeoff for maintaining full-time employment while chronically ill is the alleviation of financial burden during these bouts.

However, for the 38 million Americans living below the poverty level, and many more in the middle class, ordering takeout even for a meal is not a reality they can afford. Being sick, and properly caring for your physical wellbeing has barriers to entry in the 21st century.

Without proper immediate and preventative care, many chronic symptoms exacerbate. They result in increased future costs in the form of medication, lost wages when symptoms intensify, and piling hospital bills. As a direct result of the inflationary period in 2022, 100 million Americans– at the time 38% of the population- chose to delay or skip medical treatment and cut essentials like utilities and food to pay their medical bills.

While not all individuals are impacted by Lyme and POTS, 133 million Americans suffer from a chronic illness. The Center for Disease Control cites 6 out of 10 adults in the United States are chronically ill, 4 out of 10 suffering from 2 or more long-term conditions. Health-care, as we address these staggering, and growing, statistics, should address the total cost of operation of care.

There have been countless legislative initiatives in this light. The Patient Protection and Affordable Care Act, amongst others, served to expand health insurance coverage for individuals suffering from chronic disease, though its legislative progression is unclear at this juncture.

Most recently, the Chronic Disease Management Act of 2021 was introduced in the Senate, covering any preventative care service item used to treat a chronic condition, barring cost and efficacy stipulations. The bill never progressed.

There is also a profound opportunity cost of sickness. Along with every-day pain management and aforementioned incurred costs is the opportunity cost of a life without chronic illness.

Often, I have to log off right as the work day is over, or earlier, though I want to get a few extra hours in to prep for the week to come. I turned down demanding job offers with restrictive sick day policies or in-office mandates.

Despite achievement, I am financially bound by my illness, as are thousands of Americans suffering at the crux of an economic and burgeoning public health crisis.


Between the tests for Lyme disease and coinfections, doctor visits, and medications, the charges can add up for patients. Throughout the country, several organizations are working to make it easier to get a proper diagnosis and begin treatment. If you need financial assistance, click here to locate nonprofits that may be able to help you or your family with diagnostic testing and other Lyme-related expenses.

_______________

**Comment**

A topic that doesn’t get discussed much but is very important.

Back when my husband and I were in the thick of treatment we spent about $15K per year, per person under the care of a Lyme literate doctor.  I’m certain this has increased exponentially.

Now, after we have reached “remission,” and are no longer in active treatment we spent $25K for the two of us in 2022.  This includes doctor visits, supplements, prescriptions, etc.  I can only imagine what this would cost if we were in active treatment.

For more:

When Lyme Causes Dysfunction of the Autonomic Nervous System

https://www.lymedisease.org/lyme-autonomic-nervous-system/

When Lyme causes dysfunction of the autonomic nervous system

By Nancy Dougherty

2/8/24

Infection-associated chronic illnesses such as Long COVID, myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) and chronic Lyme disease share similar symptoms and may share important biologic mechanisms, too.

Dysautonomia, or autonomic nervous system dysregulation, is widely accepted as an underlying contributor to long COVID and ME/CFS.

A multidisciplinary team at Johns Hopkins University School of Medicine has published a research review in Frontiers in Neurology that implicates dysregulation of the autonomic nervous system in post-treatment/persistent Lyme disease.

Common symptoms of these infection-associated chronic conditions include severe fatigue, musculoskeletal pain, cognitive and sleep difficulties.

Although not yet well-established in the medical literature, the Johns Hopkins team, by scrutinizing case reports, autopsy and primate studies, found compelling clinical and biologic bases for the association between dysautonomia and Lyme disease.

More research is warranted to better understand disease mechanisms and identify biomarkers to improve diagnostics and treatments.

POTS

Postural Orthostatic Tachycardia Syndrome (POTS), the most common manifestation of dysautonomia, is reported to occur after an acute Lyme disease infection. POTS has been recognized by some clinicians as a contributor to post-treatment/persistent Lyme disease but has not been studied in depth.

POTS results from impaired regulation of blood flow, particularly when in an upright position. Symptoms can be debilitating and include brain fog, severe fatigue, profound weakness with standing, racing heart, exertional intolerance, light-headedness, and muscle aches. When properly evaluated with formal testing, POTS can be diagnosed and treated.

More research needed

There are gaps in knowledge that the Johns Hopkins researchers aim to address in prospective studies of Lyme disease-associated dysautonomia in order to:

  • Identify underlying abnormal biologic mechanisms causing Lyme disease-associated dysautonomia and to compare those with other infection-associated chronic illnesses
    • Investigate small-fiber neuropathy, endothelial dysfunction, mast-cell activation, autoantibodies, vagus nerve damage, gut microbiome disruption, neuroinflammation, neurotoxicity, genetic predeterminants and other factors
  • Determine the prevalence of small-fiber neuropathy and autonomic dysfunction in chronic Lyme disease using objective autonomic tests and skin biopsies
  • Understand the relationship between acute Borrelia burgdorferi infection and the development of small-fiber neuropathy and autonomic dysfunction
  • Understand the contribution of co-infections to chronic symptoms and dysautonomia
  • Expand prior autopsy and animal studies to better understand the mechanisms Borrelia burgdorferi utilizes to disrupt the autonomic nervous system

Investigating treatments

Treatment trials are also important to advancing patient care:

  • Randomized studies of IVIG treatments are needed
  • Vagus nerve stimulation treatment studies are in progress (at the Columbia University Alexandra and Steven Cohen Foundation Clinical Trial Network site)

Authors of this paper are renowned international authorities in ME/CFS, POTS, and Lyme disease. Research at the Johns Hopkins Postural Orthostatic Tachycardia Syndrome (POTS) Program is ongoing in ME/CFS and Long COVID, and Lyme disease POTS/dysautonomia research is now underway at the POTS Program as well.

To help address some of the gaps in knowledge, new prospective Lyme disease research studies at Johns Hopkins are utilizing transcranial doppler ultrasound, tilt table testing, and other objective tests to help elucidate the abnormalities and mechanisms of Lyme disease-associated dysautonomia. This is the first research program focusing on understanding POTS/dysautonomia in Lyme disease.

Please visit here for more background information on POTS and Lyme disease, including symptoms, diagnostic tests and treatments.

Nancy Dougherty is an education and communications consultant for the Johns Hopkins Lyme Disease Research Center. Other research investigations at the Center include Pilot Treatment Trials and the SLICE Studies.

_____________

**Comment**

Sadly, the study regurgitates the myth that only 10-20% go on to suffer chronic symptoms, when the truth is somewhere between 40-60% or even more.

Again, Lyme/MSIDS research has always been biased due to the extremely limited study design parameters. The sickest never test positive on the antiquated and unscientific CDC 2-tiered testing and most don’t have the EM rash – two parameters continually used despite their glaringly known flaws.

The study also uses the flawed Post Treatment Lyme Disease Syndrome (PTLDS) moniker.

The study authors hope their work will lead to new treatments to improve the quality of life; however, the concern is that these treatments will focus solely on dysautonomia that will ignore pathogen involvement and the need for antimicrobials (i.e. long term antibiotics).