Archive for the ‘Lyme’ Category

GLA Response to Proposed IDSA/AAN/ACR 2019 Draft Lyme Disease Guidelines

https://globallymealliance.org/gla-response-to-proposed-idsa-aan-acr-2019-draft-lyme-disease-guidelines/

lyme-disease-guidelines_gla_idsa

The Infectious Diseases Society of America (IDSA), along with the American Academy of Neurology (AAN), and the American College of Rheumatology (ACR), recently published a public request for comments on the “2019 Draft Guidelines for the Prevention, Diagnosis and Treatment of Lyme Disease.” Below is the official response from Global Lyme Alliance (GLA).

The 100-page guidelines document attempts to cover various aspects of Lyme disease, including prevention, acute Lyme disease, neurological Lyme disease, co-infections, and more. GLA purposefully focused on seven (7) specific areas of the Draft Lyme Disease Guidelines to comment on. The 7 areas are handpicked for two key reasons: they represent the most glaring oversights and omissions in the guidelines and there is strong scientific evidence to refute them.

GLA focused its comments on 1) the overall misses of the guidelines, 2) Lyme disease diagnostics, 3) tick bites and prophylactic treatment, 4) neurological Lyme disease, 5) post-treatment Lyme disease, 6) treatment for persisting Lyme infections, and 7) chronic Lyme disease.

1 – GENERAL COMMENTS

General comments on entire draft, pages 2-69, lines 45-1605: Throughout the 2019 draft revised guidelines, an overriding concern is the generation of false positive diagnoses and misattribution of symptoms to Lyme disease. In contrast, there is little, or no concern voiced about the possibility of false negative diagnoses and misattribution of Lyme disease symptoms to other etiologies. Obviously, all patients, whatever their ailment, should be accurately diagnosed in a timely manner. Testing methods more sensitive and reliable than the CDC standard two-tier test (STTT), as concluded by 40 Lyme disease academic and government specialists attending a Banbury Conference at Cold Spring Harbor Laboratory, and a year later by the Tick-Borne Disease Working Group, are desperately needed to differentiate between those who do and those do not have Lyme disease. Individuals suffering from Lyme and other tick-borne diseases (TBDs) who are not promptly diagnosed are likely contributing, at least in part, to the accumulation of patients suffering from post-treatment Lyme disease syndrome(PTLDS). Because of the severe consequences of missed or delayed diagnosis of Lyme disease, it is extremely important to minimize false negative diagnoses as well. Specific guidance on how best to avoid false negative diagnoses would be invaluable to medical care providers.

2 – LYME DIAGNOSTICS

Diagnostic Testing for Lyme disease, page 10, lines 228-229: It states that “IgG seronegativity in a patient with prolonged symptoms (months to years) essentially rules out the diagnosis of Lyme disease…”. This is only true if the patient with prolonged symptoms has no history of other objective, clinical measures of Lyme disease. Also, it is noteworthy that research has shown that seroreactivity to Borrelia burgdorferi antigens varies between individuals and during the course of disease within an individual. Therefore, a static test at one point in a dynamic disease process is a poor diagnostic tool. The IDSA/CDC criteria requiring that five of 10 IgG bands be present for positive diagnosis does not make sense immunologically as it suggests that a patient with only four bands does not have Lyme disease. How does one then explain away the presence of four distinct antibodies highly specific in their ability to recognize B. burgdorferi antigens? Furthermore, work published by researchers at Northeastern University and Johns Hopkins University have shown in vitro and in vivo (in a mouse model of Lyme borreliosis), respectively, that at different stages of growth B. burgdorferi expresses a distinct repertoire of antigens and degrees of antibiotic tolerance. While in vivo studies are ongoing to identify these persister forms in patients, it is premature to dismiss the possibility that persisters expressing variant antigens, and the antibodies they elicit, exist in PTLDS patients. Therefore, the Western immunoblot of the CDC standard two-tier test (STTT) may not include the full repertoire of antigens recognized by patients with prolonged symptoms. Their absence from the STTT could result in late stage patients failing to meet the “five of 10 IgG bands” criterion for a positive diagnosis. As the field transitions from use of the STTT to a modified two-tier test (MTTT) this same concern about whether the ‘correct’ antigens are targeted remains.

Another factor to consider is that continued B. burgdorferi-specific IgM reactivity has been observed in IgG seronegative patients. This scenario is confusing, because it can lead to a false positive Lyme diagnosis. However, there also are IgM-positive/IgG-negative patients who were previously diagnosed with Lyme disease, based upon presentation of erythema migrans or other CDC criteria. The Johns Hopkins University SLICE studies suggest that a diversity serological profiles exist in PTLDS patients; these include those who are IgM-positive/IgG-negative when tested months after cessation of treatment. In an initial case series of 60 patients, while 43% were IgG-positive, 11% were IgM-negative. Among these IgM-negative patients, most were IgG-negative as well. In short, the lack of B. burgdorferi-specific IgG does not necessarily preclude continued disease just as the continued presence of B. burgdorferi-specific IgM and/or IgG is not always indicative of active infection. Acknowledgement of these important, albeit nuanced, facts is absent from the revised guidelines.

3 – TICK BITES AND PROPHYLACTIC TREATMENT

Tick bites, prevention, and prophylaxis of Lyme disease – What diagnostic tests should be used following tick bite?, pages 19-20, lines 453-467: It states, “We recommend against testing for B. burgdorferi in an Ixodes tick following a bite”. While true that the presence of a pathogen does not reliably predict the likelihood of clinical infection, there still is valuable information to be gained by testing ticks. Primary care physicians, even in Lyme-endemic areas, are not always familiar with the tick species common to a given location or the pathogen(s) they may carry. The stated rationale for the recommendation not to test is that “Even in areas that are highly endemic for Lyme disease, patients presenting with an Ixodes tick bite have a low probability of developing Lyme disease…”. This statement is not referenced and is unsupported by the fact that in highly endemic areas, in the northeastern U.S. in particular, the carriage rate for B. burgdorferi can be 50% or greater and such high carriage rates correlate with a higher incidence of Lyme disease. Tick removal and sending it for testing is a relatively rare event and thus should not contribute significantly to unnecessary antibiotic prescriptions. A major benefit to tick testing is that if no pathogens are found, this information would put the patient’s mind at ease.  If instead, the tick tests positive for one or more pathogens, this will focus the physician’s and patient’s attention on what symptoms to look for and better inform a treatment strategy if such symptoms arise.

The guidelines also suggest that “Anticipatory guidance is recommended so that a prompt diagnosis of Lyme disease (as well as other Ixodes tick transmitted infections) can be made should a patient develop symptoms”. However, given the inadequate familiarity most physicians have regarding ticks and tick-borne agents in their area, let alone in an area(s) to which a patient may have traveled and been bitten, there is no basis for thinking such anticipatory guidance can be provided. It is hard to rationalize why the guidelines would advocate for physicians and patients to make decisions having less rather than more information in hand, especially when the benefits of a prophylactic single dose of Doxycycline are substantial and the risks negligible.

4 – NEUROLOGICAL LYME DISEASE

Neurological Lyme disease – For which neurological presentations should patients be tested for Lyme disease?, page 36, lines 840-841: It states that “In patients with cognitive decline the guidelines recommend against routine testing for Lyme disease.” Global Lyme Alliance vehemently disagrees with this statement because it does not take into consideration the extensive evidence in peer-reviewed medical journals describing the cognitive decline experienced by Lyme neuroborreliosis patients. Such studies include patients with PTLDS, as defined by the IDSA-proposed case definition, who experience cognitive decline as well as PTLDS patients with neuropsychiatric symptoms linked to neuroimmune responses. This latter reference also argues against the guidelines’ claim that “No studies suggest a convincing causal association between Lyme disease and any specific psychiatric conditions”. If patients present with otherwise unattributable cognitive decline, and they live in a Lyme-endemic area, why should a physician not consider Lyme disease in their differential diagnosis? To not do so risks a missed/delayed diagnosis, and it is well-established that the earlier the treatment for Lyme disease is initiated the more positive the prognosis for recovery and cure. It also is recognized that cognitive symptoms can vary depending on a patient’s age, so a “one size fits all” statement that patients with (otherwise) unexplained cognitive decline should not be tested for Lyme disease seems at odds with a careful process of differential diagnosis and best-practice medical care.

5 – POST-TREATMENT LYME DISEASE

Prolonged symptoms following treatment of Lyme disease, page 61, lines 1412-1419: Reference is made to studies of “patients appropriately diagnosed and treated for Lyme disease” who describe either “persisting or recurrent fatigue, musculoskeletal pain, neurocognitive and other non-specific subjective symptoms”.  These are in fact patients clinically defined by Rebman et al. as having PTLDS and yet reference to this seminal study and specific mention of this PTLDS patient population is missing and should be included in the body and bibliography of the guidelines. In this same section it states that long-term “symptoms appear to subside over time…”. For patients suffering from PTLDS, most continue to have debilitating symptoms. In fact, a Dutch study found an average of 1.7 disability-adjusted life years lost due to persisting symptoms attributable to Lyme, and even longer for some patients.

 6 – TREATMENT FOR PERSISTING LYME INFECTIONS

Prolonged symptoms following treatment of Lyme disease – Should patients with persistent symptoms following standard treatment of Lyme disease receive additional antibiotics?, pages 62-63, lines 1445-1449 and 1464-1468: Four randomized, controlled trials are cited as evidence against repeated antibiotic treatment (references #317, 321, 319). A careful statistical analysis of the trials and their design calls into question the conclusion that repeated antibiotic treatment has no benefit. DeLong et al. showed that two trials conducted by Klempner (reference #317) had sample sizes too small to detect true minimum clinically-important differences, particularly in SF-36 scores. The guidelines state that in study by Fallon et al. (reference #321) “A cognitive index score at week 24 did not differ between treatment and control groups.” While true that objective measures such as cognitive test results did not show differences between PTLDS patients and controls, it is important to note that PTLDS patients in the study had to invest considerably more effort to achieve the same test scores. This would argue against the notion “that this phenomenon, in whole or in part, represents anchoring bias…”. Additionally, the authors did note a positive effect on fatigue, similar to that observed in the Krupp trial (reference #319), and Fallon and co-authors highlighted the need for further study. In reviewing these clinical studies, DeLong et al. concluded that “primary outcomes originally reported as statistically insignificant were likely underpowered.” At the very least, DeLong’s analysis should be cited in the IDSA guidelines as evidence that further study of repeated antibiotic use should be very carefully designed, executed, and interpreted.

Regarding continued or repeated antibiotic treatment for persistent symptoms, the guidelines state that “A body of literature conducted in animal models has raised hypotheses of microbiological persistence”. While correct, this statement is wholly disingenuous as it fails to reference any of the studies and, worse, neglects to acknowledge that experimental results are presented that support the hypotheses put forward. It also is stated that “Moreover, animal models cannot reproduce the human experiences of fatigue and pain, and it is unlikely that any animal study can give reliable insight into the biology of humans experiencing such symptoms following treatment of Lyme disease.” Again, this statement neglects a significant body of literature describing animal models of human fatigue and chronic pain.  Such studies have been instrumental in advancing our understanding of the pathogenesis of these human conditions and have spurred the development of novel treatments. This statement also fundamentally misrepresents the intent of the diverse animal studies conducted that provide evidence of persistence of spirochetes post-antibiotic treatment of infected animals. The purpose of using animal models as articulated by Monica Embers, Ph.D. (Division of Bacteriology and Parasitology, Tulane National Primate Research Center, Tulane University Health Sciences Center) is “to understand the etiology of post-treatment Lyme disease syndrome (PTLDS), namely whether or not the spirochetes persist post-treatment and could thus contribute to chronic symptoms.” Symptoms experienced by PTLDS patients are not restricted to fatigue and pain, so one cannot reasonably discount the results of animal findings supporting spirochetal persistence because they are purported not to recapitulate all the symptoms experienced by humans.

Recent human evidence that continued bacterial presence may contribute to long-term symptoms was published by Jutras et al. in a 2019 PNAS article. They found that B. burgdorferi peptidoglycan, a component of the cell wall, was recovered from 94% of synovial fluid samples from Lyme arthritis patients, with specific IgG responses. Many of these patients had previously been treated with antibiotics. As peptidoglycan is shed from actively growing live bacteria, it’s at least plausible and worth further inquiry to study whether bacteria persist in these patients. If not, one is left with a less plausible explanation that foreign bacterial antigens must remain in inflamed tissues for weeks, months, or even years after (presumed) effective antibiotic-mediated killing of B. burgdorferi. With such intriguing findings at least hinting at the possibility of persistent organisms in Lyme disease patients, the authors of the revised guidelines should consider specifically referencing these animal and human studies rather than covering the entire topic by citing one publication (reference #320) and summarily discounting the results presented in so many other peer-reviewed scientific journals.

7 – CHRONIC LYME DISEASE

Prolonged symptoms following treatment of Lyme disease – Chronic Lyme disease, page 64, lines 1474-1479: It states that “The term ‘chronic Lyme disease’ as currently used lacks an accepted definition for either clinical use or scientific study, and it has not been widely accepted by the medical or scientific community”. Although this statement is correct with respect to the lack of an accepted clinical definition, at least 68 publications in peer-reviewed scientific and medical journals spanning 1985 to 2019 describe the chronic infectious and persistent nature of Lyme disease. While treatment of patients with Doxycycline or other standard-of-care antibiotics is quite effective when provided within the first few weeks of infection, no clinical studies have demonstrated complete clearance of spirochetes; just elimination of symptoms for some, but not all patients (i.e., PTLDS patients). When early treatment is ineffective or initial diagnosis is delayed, B. burgdorferi can avoid pharmaceutical and/or immune clearance and spirochetes have an opportunity to disseminate and cause persistent disease. Literally a dozen or more bacterial pathogens are capable of establishing persistent infection and associated chronic disease. It would be truly remarkable if B. burgdorferi were unable to do the same. To our knowledge, there is no scientific or medical evidence to suggest they are incapable.

Whether persistent disease is synonymous with persistent infection is an important scientific question worthy of objective consideration and further careful investigation, rather than recrimination, disparagement and dismissal. The revised guidelines would stand on firmer scientific/medical footing were it to acknowledge that the question of persistent disease vs. infection is still an open question, rather than suggesting the latter has no evidentiary support whatsoever.

—

To conclude, the content and bibliography of the 2019 revised IDSA guidelines fails to acknowledge evidence or reference published scientific and medical studies that could and should convey a more nuanced understanding of the complexities of Lyme disease diagnosis, symptomatology, treatment, and treatment failure. A more inclusive, open-minded, and informed approach to conveying information can only benefit the Lyme disease physician and patient community, as it will better serve to enhance co-operation, reduce controversies that divide the IDSA and ILADS ‘camps’, and ultimately reduce the likelihood of false negative and false positive diagnoses.

Learn more about important GLA-funded peer-reviewed Lyme disease research, ranging from basic science, treatment, to chronic Lyme disease.

________________

**Comment**

I all I can say is a hearty AMEN!

For more:  https://madisonarealymesupportgroup.com/2019/08/11/idsa-extends-comment-period-allows-downloads/

https://madisonarealymesupportgroup.com/2019/08/11/natcaplymes-response-to-updated-lyme-disease-guidelines-states-they-are-based-on-outdated-and-discredited-studies/

https://madisonarealymesupportgroup.com/2019/07/09/idsa-lyme-disease-treatment-management-business-as-usual-leaves-those-with-persisting-symptoms-to-suffer-die/

https://madisonarealymesupportgroup.com/2019/06/27/idsa-aan-acr-2109-draft-lyme-guidelines-public-comments-allowed-until-aug-10-2019/

https://madisonarealymesupportgroup.com/2019/07/22/idsas-insincere-request-for-guidelines-feedback/


Am I Losing My Mind, Or Is It Lyme Disease?

https://www.amenclinics.com/blog/am-i-losing-my-mind-or-is-it-lyme-disease/

Am I Losing My Mind, Or Is It Lyme Disease?

AM I LOSING MY MIND, OR IS IT LYME DISEASE?

Do you feel like you’ve got brain fog? Are you having trouble with problem-solving and decision-making? Is it getting harder for you to concentrate or pay attention? Are you struggling with memory problems? If so, you could be feeling like you’re losing your mind.

If you’re like most people, you might head to your primary care physician to complain about these issues. In some cases, you might be told it’s just part of the normal aging process, you might leave with a prescription for ADD/ADHD medication, you might get a recommendation to visit a psychiatrist, or you might be told you have Alzheimer’s disease. It’s highly unlikely, however, that you will be tested for Lyme disease.

That’s what happened to actor and singer-songwriter Kris Kristofferson. For years, he was told he was suffering from Alzheimer’s disease or some other form of dementia. His memory continued to deteriorate, and he was taking numerous medications. Eventually, the Hall of Fame singer went to Dr. Mark Filidei, an integrative medicine doctor who diagnosed Kristofferson with Lyme disease and treated him with antibiotics and hyperbaric oxygen therapy. After a few treatments, the singer reportedly told his wife, “I feel like I’m back,” and has done much better.

What is Lyme Disease?

Lyme disease (Borrelia burgdorferi) is a bacterial infection that is caused when a person gets bitten by an infected black-legged tick, or deer tick as it is commonly known. However, many people with Lyme disease don’t recall being bitten by a tick and who did not get the typical “bull’s-eye” rash that is considered a telltale sign of the infection. When left untreated, the infection can cause devastating, life-changing issues.

Psychiatric Symptoms of Lyme Disease

All of the neuropsychiatric issues mentioned above are considered symptoms of Lyme disease. In fact, 70% of people with Lyme disease say they experience negative changes in memory and mental sharpness. In some people, Lyme disease can also cause paranoia, mania, obsessive compulsive tendencies, anxiety, depression, and hallucinations. But many healthcare professionals are unaware of the debilitating psychiatric effects of the disease. For this reason, many people are treated with medications that don’t help, and in many cases, produce harmful side effects that make things worse.

How is Lyme Disease Diagnosed?

Lyme disease is notoriously difficult to diagnose. When laboratory testing for the infectious disease is performed by mainstream labs using the standard “Western blot” test, it can often give a false-negative result. If your results are negative, you could still have Lyme disease. It’s important for testing to be done at specialty labs that are better trained to detect the disease.

Because lab testing is not always definitive, Lyme disease is typically diagnosed by a “Lyme Literate Medical Doctor” (LLMD) who is a member of the International Lyme and Associated Diseases Society (ILADS). These trained healthcare professionals generally take a detailed clinical history, perform a thorough physical exam, and do appropriate laboratory testing.

Brain imaging studies using SPECT can also help. Brain scans of people with infections like Lyme disease tend to show low overall blood flow and have a toxic appearance. When a brain looks toxic, it prompts a psychiatrist or other medical professional to dive deeper into what the root cause may be. It increases the chances of Lyme disease being investigated.

Hope for Lyme Disease

Just as singer Kristofferson saw an improvement in his symptoms when properly diagnosed and treated for Lyme disease, there is hope for other sufferers. With an accurate diagnosis and a personalized treatment plan, people can experience a reduction in symptoms and a greater quality of life.

At Amen Clinics, we have seen hundreds of patients with resistant complex psychiatric symptoms or cognitive problems who tested positive for Lyme disease and got significantly better when it was treated. Dr. Mark Filidei, who diagnosed Kris Kristofferson with Lyme disease, is the director of integrative medicine at Amen Clinics, where we commonly use specialty labs to help diagnose Lyme disease.

_________________

For more: https://madisonarealymesupportgroup.com/2017/01/04/aluminum-alzheimers-ld/ Within this link you can watch a brief video of Kris Kristofferson, initially diagnosed with Alzheimers but was found to be infected with Lyme disease.

https://madisonarealymesupportgroup.com/2019/08/11/the-unfortunate-connections-between-lyme-disease-mental-illness/

https://madisonarealymesupportgroup.com/2019/05/30/why-lyme-disease-is-causing-a-mental-health-crisis/

https://madisonarealymesupportgroup.com/2019/05/27/uk-woman-isolated-pumped-full-of-anti-psychotics-told-its-all-in-her-head-until-finally-diagnosed-with-lyme/

https://madisonarealymesupportgroup.com/2015/10/18/psychiatric-lymemsids/

https://madisonarealymesupportgroup.com/2017/01/17/lymemsids-and-psychiatric-illness/

https://madisonarealymesupportgroup.com/2017/07/26/can-lyme-steal-your-mind/

Illinois Expands Insurance Coverage For Those With Tick-borne Diseases And Children Requiring EpiPens

https://wgem.com/2019/08/13/illinois-expands-insurance-coverage-for-those-with-tick-borne-diseases-and-children-requiring-epipens/?

Illinois expands insurance coverage for those with tick-borne diseases and children requiring EpiPens

SPRINGFIELD, IL (WGEM) — Governor JB Pritzker signed two new laws expanding insurance coverage for children whose allergies require life-saving EpiPens and Illinoisans suffering from Lyme disease.

“This legislation takes a big step forward in protecting our children and families,” said Pritzker. “Both of these new laws fulfill a core principle of this administration: state government ought to be standing up for working families. Lowering the cost of prescription drugs and expanding health care coverage is one important way to help lower costs and build a higher standard of living for all Illinoisans.”

The new laws include House Bill 889 and 3435.

House Bill 889

The Governor’s office stated that House Bill 889 requires insurance companies to cover office visits, testing and treatment for tick-borne diseases like Lyme disease. The new law aims to support farmers throughout the state who have struggled to afford continuing treatments. From 2004 to 2016, tick-borne diseases have risen dramatically according to the Centers for Disease Control.

“The ability to receive treatment when you have previously been insufficiently treated is life changing,” said Rep. Daniel Swanson (R-Woodhull). “By mandating insurance coverage of long-term antibiotic treatment needed for patients, we are putting another piece of the puzzle into place for some patients and removing one additional hassle on their path to recovery.”

House Bill 3435

Officials stated that House Bill 3435 requires insurance companies to cover EpiPens, for children with severe allergies. The cost of an EpiPen has skyrocketed over the last decade, rising by more than 400% for the two-pen injector pack. Without insurance, these EpiPens can cost a family nearly $700 and typically have a shelf life of a little more than a year before the medicine needs to be restocked in stores.

“With steady increases in food allergies and other serious allergic conditions, families are relying on EpiPens more than ever before,” said Sen. Julie Morrison (D-Deerfield). “We should be doing everything we can to expand access to affordable lifesaving drugs and medicines. No child with a serious allergy should be without an epinephrine injector because they cannot afford one.”

House Bill 889 takes effect immediately.

House Bill 3435 takes effect on January 1, 2020.

__________________
**Comment**
While legislators attempt to help Lyme patients by proposing bills such as these, the CDC Lyme Corps goes into every state and undermines them:  https://madisonarealymesupportgroup.com/2017/07/07/cdc-sabotages-state-laws-protecting-lyme-patients/  Excerpts: 
To be clear, the CDC is using Lyme Corps to tell health practitioners the only valid treatment for Lyme, chronic Lyme and complications from coinfections are found in the 2006 IDSA Lyme Guidelines.  However, key science institutions and federal agencies would not support this objective….
The CDC Lyme Corps was initiated in 2013 prior to the NGC delisting of the IDSA Lyme Guidelines. Nevertheless, as of July 4, 2016, the IDSA and the CDC Lyme policy and programs, including Lyme Corps continue to promote these outdated notions and noncompliant Guidelines.
The IDSA has also taken numerous actions against Lyme patients’ and practitioners’ protections.  One such IDSA website post  State-Level Lyme Disease Advocacy Efforts  openly admits to undermining Lyme patient rights in: California, Connecticut, Maine, Maryland, Massachusetts, Minnesota, Nebraska, New Hampshire, New Jersey, New York, Ohio, Oregon, Pennsylvania, Rhode Island, Texas, Vermont, Virginia, West Virginia and Wisconsin. [xvi]  Another such IDSA web announcement is the IDSA’s Lyme Disease Advocacy Efforts. [xvii] The ‘anti-protections’ advocacy letters are detailed.

A breach of public trust by the CDC Directors responsible for protecting the public health and welfare against Lyme epidemic – all these CDC officials are members of IDSA and there are no non-IDSA members among the Directors responsible for CDC’s Lyme policy and programs.  [xxviii]

This group of CDC officials show continuous and singular “preferential treatment” for the ‘Lyme product’ of a private medical society, the IDSA. The product is the IDSA Lyme Guidelines; these Guidelines have failed federal criteria for evidence-based medicine.

The promotion of these federally noncompliant IDSA Guidelines make waste of tax dollars and misinform the public. Such actions run contrary to protecting the health and welfare of the public against the Lyme epidemic and they show a strong a lack of “honest effort in the performance of their duties.”

Unfortunately, due to this undermining, I do not expect these well meaning bills to do anything of substance to truly help patients.
Regarding “doctor protection” bills, I’ve heard from doctors that they are under more scrutiny than before they had these supposed “protections.”
And regarding states that have adopted bills requiring doctors to tell patients they could still be infected even if the test is negative, I’ve heard many doctors aren’t complying.


Public Hearing Tomorrow (Aug. 15, 2019) Two WI Bills on Tick Prevention

I apologize for this late notice.  I just received it myself. I was told the two Lyme bills would be presented around noon.

https://docs.legis.wisconsin.gov/raw/cid/1509726

Assembly

PUBLIC HEARING Committee on Environment

The committee will hold a public hearing on the following items at the time specified below:

Thursday, August 15, 2019 11:00 AM
412 East

Assembly Bill 190

Relating to: wetland mitigation banks, providing an exemption from emergency rule procedures, providing an exemption from rule-making procedures, and requiring the exercise of rule-making authority.

By Representatives Tusler, Ohnstad, Sinicki, Kerkman and Mursau; cosponsored by Senators Wanggaard, Cowles, Wirch and Olsen.

Assembly Bill 210

Relating to: time limits for correcting violations found by the environmental compliance audit program.

By Representatives Brooks, Brandtjen, Knodl, Kulp, Skowronski, Tusler and Wichgers; cosponsored by Senators Jacque, Cowles and Miller.

Assembly Bill 297

Relating to: changes to the electronic waste recycling program and granting rule- making authority.

By Representatives Mursau, Hebl, Anderson, Ballweg, Billings, Ohnstad, Shankland, Sinicki, Skowronski, Spreitzer, Stubbs, Tusler, Vruwink, Spiros and Subeck; cosponsored by Senators Miller, Cowles, Larson, Smith, L. Taylor, Wirch and Carpenter.

Assembly Bill 315

Relating to: signs informing about Lyme disease in state parks, state trails, state recreational areas, and state forests and making an appropriation.

By Representatives Mursau, Milroy, Anderson, Considine, Crowley, Edming, Emerson, Gruszynski, Hesselbein, Kulp, B. Meyers, Ohnstad, Ott, Pope, Ramthun, Rodriguez, Sargent, Shankland, Sinicki, Snyder, Spiros, Spreitzer, Tauchen, C. Taylor, Thiesfeldt, Tusler and Rohrkaste; cosponsored by Senators Cowles, Miller, Carpenter, Hansen, Larson, Olsen, Petrowski, Ringhand and Smith.

Assembly Bill 316

Relating to: making insect repellant available for sale in state parks and state forests.

By Representatives Mursau, Milroy, Anderson, Crowley, Edming, Emerson, Gruszynski, Hesselbein, Kulp, B. Meyers, Ohnstad, Ott, Pope, Ramthun, Shankland, Sinicki, Snyder, Spiros, Spreitzer, Tauchen, C. Taylor, Thiesfeldt, Tusler and Rohrkaste; cosponsored by Senators Cowles, Miller, Carpenter, Hansen, Larson, Olsen, Petrowski, Ringhand and Smith.

Representative Joel Kitchens Chair

__________________

For more on the bills:  https://madisonarealymesupportgroup.com/wp-content/uploads/2019/05/time-to-bite-back-against-lyme-disease-05-23-19.pdf

News story on bills:  https://madisonarealymesupportgroup.com/2019/06/01/news-story-update-lawmakers-introduce-package-of-bills-aimed-at-lyme-awareness-in-wisconsin/

https://madisonarealymesupportgroup.com/2019/06/30/lawmakers-want-to-combat-lyme-disease-with-more-signs-insect-repellent-in-public-parks/


My Chronic Lyme, Your Ill-Informed Summertime Clickbait

https://medium.com/news-to-table/my-chronic-lyme-your-ill-informed-summertime-clickbait

My Chronic Lyme, Your Ill-Informed Summertime Clickbait

Aug 1
Coverage of Lyme disease often ignores science, vilifies alternative practitioners, and ridicules patients. And it’s making a bad crisis worse.
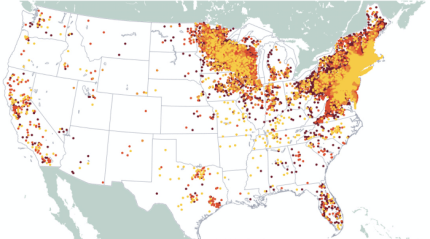
Cases of Lyme disease have been on the rise around the country for decades, with most reported in the northeast and upper Midwest. (Map credit: The Cary Institute of Ecosystem Studies)

By Lauren Rothman

This summer, as people take to the outdoors to hike, camp, fish and swim, news outlets across the country are united in their exhortations to be on the alert for ticks, the tiny arachnids whose bite can confer a host of illnesses, of which Lyme disease is the best-known and most widely feared. A quick Google News search for “ticks” brings up recent results from Self, The Atlantic, TIME and a variety of local news channels, all urging tick checks and sharing information on the many types of tick borne diseases. Tick populations are on the rise, these articles warn us; the illnesses they carry can be deadly, the chorus relates.

Generally, even the most headline-grabbing article on tick-borne diseases will end on an optimistic note, claiming that the majority of these illnesses are readily diagnosed and easily treated with a round of antibiotics. Such conclusions fly in the face of the experience of those who believe they suffer from so-called “chronic” Lyme disease — also called Post-Treatment Lyme Disease Syndrome (PTLDS) — an estimated ten to 20 percent of the population that continues to experience the symptoms of Lyme even after taking the Centers for Disease Control (CDC)-sanctioned treatment of two to three weeks of antibiotics.

For a disease as complex as Lyme, in which symptoms are diffuse, diagnostic testing is unreliable and treatments range from the conventional to the Wild West of alternative medicine, any black-and-white decree on how best identify and cure the disease is likely to remain elusive. But for patients — and I count myself among them, having fallen ill with Lyme after a trip to the Catskills two years ago — the shortcomings of most service journalism articles on Lyme are minor compared to two community-roiling pieces published this summer by the New York Times and New York Magazine. In the first, science writer Apoorva Mandavilli relates the story of her son contracting Lyme disease and quickly vanquishing it with a round of antibiotics; she concludes that Lyme is “an easily treated infection with no long-term consequences for children, or even the vast majority of adults.” In the second, journalist Molly Fischer takes a Gonzo-style dive into chronic Lyme, speaking with patients and attending support groups. Her thesis is that the disease has “grown into a phenomenon often untethered from scientific method or peer review.”

Taken together — and published within weeks of each other — these two misreported, factually inaccurate and seemingly bias-laden articles have heaped fuel upon the evidently inextinguishable fire of the so-called “Lyme Wars,” pitting those who don’t believe that Lyme can become chronic against those who are sure that it does. Within hours of its publishing, Mandavilli’s article — an op-ed entitled “My Son Got Lyme Disease. He’s Totally Fine” — had launched a heated online debate, with sufferers of chronic Lyme dismantling the article’s many errors on Instagram, Twitterand in its comments section, which eventually garnered more than 700 posts. Fischer’s examination of the chronic Lyme “community,” entitled “Maybe It’s Lyme: What Happens When an Illness Becomes An Identity?” paints sufferers as a naive group susceptible to charlatan doctors and snake-oil treatments, and ignited a similar response on Instagram, Twitter and elsewhere.

The lively debate around these two pieces testifies to a growing community that is pushing back against the use of chronic Lyme as clickbait. And make no mistake, this community is real and growing. Peer-reviewed scientific studies increasingly confirm the existence of PTLDS; Brown University statisticians recently predicted that by 2020, the population of sufferers in the U.S. will reach nearly 2 million.

The great Lyme Wars are just beginning.

Jenny Lelwica Buttaccio is a Chicago-based journalist who was diagnosed with Lyme in 2012, and has covered tick borne diseases for outlets including Real Simple, Prevention, and ravishly. She notes that when it comes to one-sided coverage of Lyme, articles like those from the Times and New York are nothing new. While Buttaccio said she has noticed cycles of coverage about the disease — in 2015 and 2016, “nobody wanted to hear about it”; then in 2017 and 2018, coverage ramped up again —there have always been inflammatory pieces that, at best, misrepresent Lyme and its symptoms and, at worst, slander its sufferers.

Specifically, Buttaccio recalled a 2016 VICE News article entitled, “If You Think You Have Chronic Lyme Disease, Most Doctors Say You’re Wrong.” The article characterizes so-called “Lyme-literate” doctors as “quacks” and focuses on the possible negative health outcomes of the long-term antibiotic treatment they often prescribe for chronic Lyme. She remembered that the article began as a dialogue between a group of journalists affected by Lyme and some editors at VICE, a situation that initially seemed hopeful until the actual article, authored by Sydney Lubkin in partnership with the medical news service MedPage Today, appeared.

“Everybody was appalled,” Buttaccio told me.“It was like, you were just talking to journalists about this subject, and now you went in the opposite direction?”

Just as the uproar over the VICE piece died down, yet another “anti-Lyme” piece was published in the Washington Post. Written by staff writer Lena H. Sun, “Dangerous unproven treatments for ‘chronic Lyme disease’ are on the rise” downplayed the severity of PTLDS symptoms and emphasized the wacky nature of unproven alternative treatments such as IV hydrogen peroxide, garlic supplements and stem cell transplants.

“It was a similar thing to the New York Times’ in that it was just a hatchet job on Lyme disease,” Buttaccio said. “It was like every wrong thing, smashed into one piece. They just got blasted for it.”

Given her memory of past articles that misrepresented Lyme disease and the struggles its sufferers face, Buttaccio said she wasn’t surprised when she first read Mandavilli’s Times piece.

“When you see that year after year after year, from different people, it’s always a mixed bag of emotions,” said Buttaccio, who took to Twitter to systematically dismantle each false and scientifically unsupported claim in the recent Times piece. “On one hand, you’re laughing, because it’s absurd. On the other hand, I always feel bad for patients who are harmed by this misinformation, and the people who potentially could be harmed in the future with such a cavalier approach to Lyme.”

As I do, Buttaccio believes that what articles on Lyme lack is nuance. Not every article has to toe the CDC-sanctioned line of “easily diagnosed, easily treated”; nor, at the other end of the spectrum, does every article have to tout the curative powers of stevia sugar substitute. In order to accurately reflect the experiences of those who live with chronic Lyme, the media has to do a better job finding gray-area stories between black and white.

“There should be people who want to check the accuracy of a diagnosis and who want to lean on science — those are good things,” Buttaccio said. “But you have to balance a little bit of that with what thousands of people are saying. There has to be something in your mind that goes, ‘Maybe we don’t have all the information we need. Maybe we do have some gaps to fill. Maybe it’s not as simple as we’re making it.’ And it seems like we never quite get to that place.”


Unless it can find some balance, the media runs two risks. One is undermining public trust, as evidenced by the many Times and New York readers who barraged both publications with Letters to the Editor, or stated that they would cancel their memberships, over their Lyme coverage. The other risk concerns losing much-needed contributions by the varied, and valuable, members of the Lyme community.

Jordan Younger, the influential blogger and Instagrammer known as The Balanced Blonde, has been sharing her struggle with Lyme disease since she was diagnosed last summer. Younger was interviewed extensively for the New York article, and is unflatteringly portrayed by its author Fischer as a wishy-washy Valley Girl hopping from expensive Beverly Hills doctor to expensive Beverly Hills doctor and leveraging her illness to gain more exposure for her brand.

“If you are an editor, assign Lyme pieces to people who have and understand Lyme please. Many of us are writers”: Porochista Khakpour, whose memoir, Sick, explores her experience with chronic Lyme.

“Lyme has also brought the Balanced Blonde to a new audience,” the article reads. “Instagram is home to an active Lyme community, and many of Younger’s photos are now hashtagged #lymewarrior; they receive hundreds of comments and thousands of likes. Target is among Younger’s sponsors, suggesting that perhaps Lyme content isn’t a bad way to reach wellness-minded American women. ‘Jordan younger lyme disease’ is among Google’s top suggested searches for her name, along with ‘jordan younger age’ and ‘jordan younger net worth.’”

Younger, who shared her outrage at what she said was a mischaracterization and manipulation of her conversation with Fischer both on Instagram and in a dedicated blog post, has written that, as a result of the experience, she will never speak to the media about Lyme disease again. Whatever your opinion — or lack thereof — of Younger and her brand, she’s a vocal member of the Lyme community who raises awareness of the disease, and now her voice on the matter has been silenced.

Another member of the chronic Lyme community who expressed her outrage with the New York piece is Porochista Khakpour, the acclaimed author of the 2018 memoir Sick, which chronicles her long battle with the disease. After the article’s publication, Khakpour took to Twitter to denounce it.

“Wish there would be a moratorium on Lyme pieces until they could figure out why people with Lyme disease are so hated and ridiculed,” she wrote on July 25.

Khakpour also expressed the need for a better diversity of voices when it comes to covering Lyme.

“If you are an editor, assign Lyme pieces to people who have and understand Lyme please. Many of us are writers.”

While Jenny Buttaccio, the journalist, expressly stated that she doesn’t believe that only journalists with Lyme have the right to cover it, more thorough communication with the Lyme community is precisely what she argues for as a step towards righting the ship.

“If you haven’t dealt with it personally, and you are a journalist and you want to write on the subject, you should tap into some of the places that the community itself goes to for valuable information,” she advised. “It isn’t always as easy as looking stuff up on Google. Don’t be afraid to look at both sides of the issue. You can do it in a diplomatic way.”

As it stands now, media coverage of chronic Lyme often ignores science, vilifies alternative practitioners, and ridicules patients. As a journalist, and as a sufferer of the disease, I argue that we need to do better. This is about much more than just bruised egos.

“When you dismiss or diminish the challenges that go along with a diagnosis, sure, it hurts people’s feelings,” Buttaccio said. “But more so, it takes us a step back from actually helping people.”

Lauren Rothman is a freelance journalist and a native of Brooklyn. Follow her on Instagram @laurenoliviarothman and @laurenstingslyme.