Archive for the ‘Lyme’ Category

Complex Role of Bartonella in Chronic Illness #1

https://www.lymedisease.org/med-detective-bartonella-part-1/

MEDICAL DETECTIVE: The complex role of Bartonella in chronic illness, part 1
This article was originally posted on Dr. Richard Horowitz’s Medical Detective Substack. It is Part 1 of a 5-part series. You can find more helpful content by subscribing here. 

Bartonella is the third “B” of the triad found in the vast majority of my chronically ill patients who suffer from chronic Lyme disease/PTLDS, along with Borrelia and Babesia.

A gram-negative intracellular bacteria, it’s controversial and misunderstood and has been throwing a monkey wrench into my treatments for decades.

I barely remember learning about it in medical school, except when they were teaching me about cat scratch fever in children that would cause small, localized rashes (papules) at the site of the scratch with swollen lymph nodes and fevers.

It would be treated with a short course of antibiotics like azithromycin. These images show classical cat scratch disease before and after treatment when the lesions are starting to crust up.
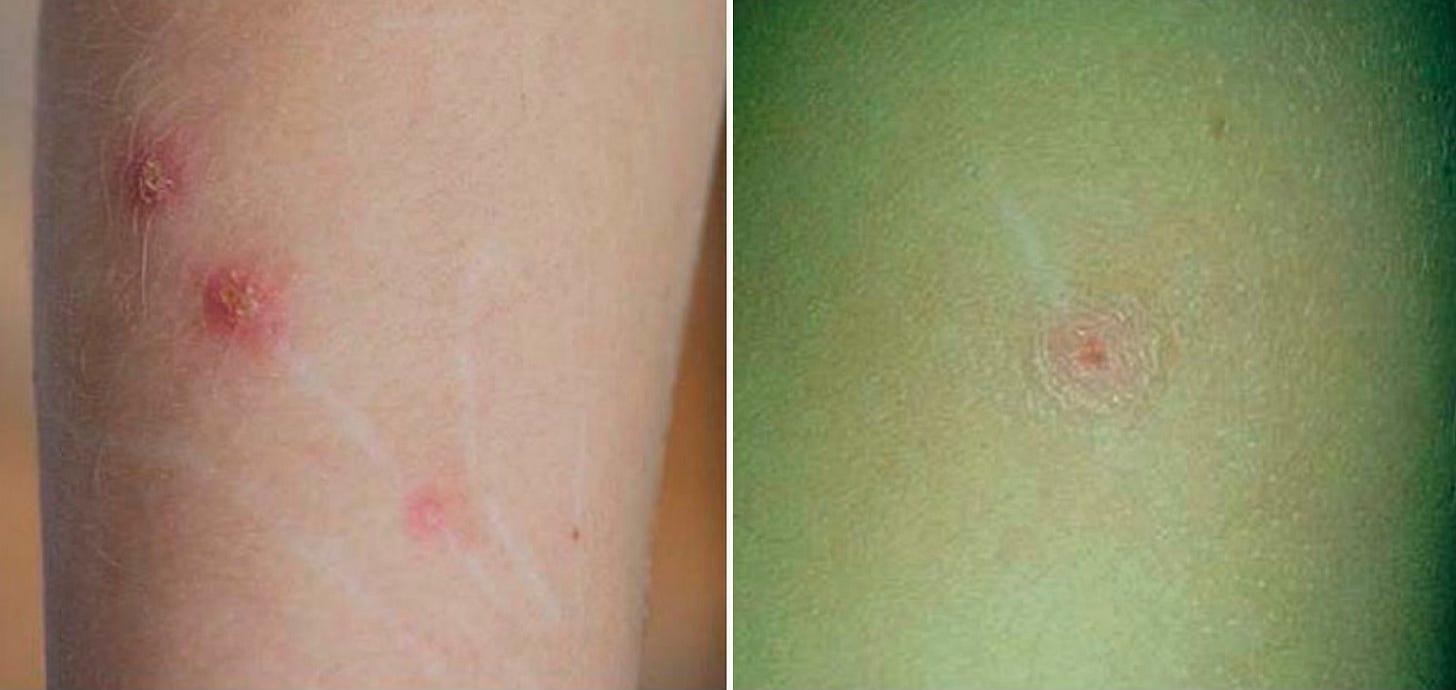
[From: Mazur-Melewska K, Mania A, Kemnitz P, Figlerowicz M, Służewski W. Cat-scratch disease: a wide spectrum of clinical pictures. Postepy Dermatol Alergol. 2015 Jun;32(3):216-20. doi: 10.5114/pdia.2014.44014. Epub 2015 Jun 15. PMID: 26161064; PMCID: PMC4495109.]

Unfortunately, Bartonella infections rarely resemble this one particular manifestation, or the general medical community would be diagnosing and treating it a lot more often.

It is a very tricky bacteria, and, like Lyme disease, has found a way to not only avoid immune recognition, but change its clinical characteristics so it resembles a broad range of other diseases.

Immune Evasion by Bartonella

Bartonella is referred to as a “stealth bacteria” because it evades the immune system by living inside red blood cells (intraerythrocytic persistence), blood vessel walls (inflaming them, causing vasculitis), endothelial cells, fibroblasts, epithelial cells of the skin (causing the classic Bartonella rashes described below), macrophages (immune cells that play a critical role of initiating and maintaining an inflammatory response, as well as potentially resolving inflammation) and bone marrow cells.

So it can hide throughout the body in areas where the immune system doesn’t easily penetrate and recognize the bacteria, not to mention, it can exist under biofilms in persister forms like Borrelia. Biofilms protect the bacteria from immune recognition and the effects of antibiotics.

[From: Okaro, U.; George, S.; Anderson, B. What Is in a Cat Scratch? Growth of Bartonella henselae in a Biofilm. Microorganisms 2021, 9, 835. https://doi.org/10.3390/microorganisms9040835%5D

Bartonella can manipulate host cell interactions to hide from immune detection by altering its surface proteins to avoid recognition (like Lyme disease), and possesses unique fat and sugar molecules (lipopolysaccharides) that minimize immune response activation; this often leads to prolonged, asymptomatic infections that can be difficult to diagnose with standard tests (it can hide in the body for years in some patients without symptoms), and then reactivate under certain conditions.

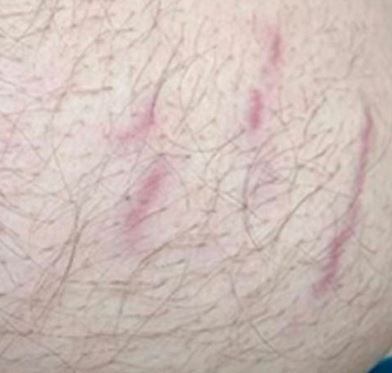
The patient below was in remission for one year after doing an 8-week course of double dose dapsone combination therapy (DDDCT), and then reactivated after being treated with antibiotics for a skin infection. This skin rash emerged when he got treated for cellulitis, which had nothing to do with his initial Lyme infection. You can see the classical Bartonella “stretch marks.”
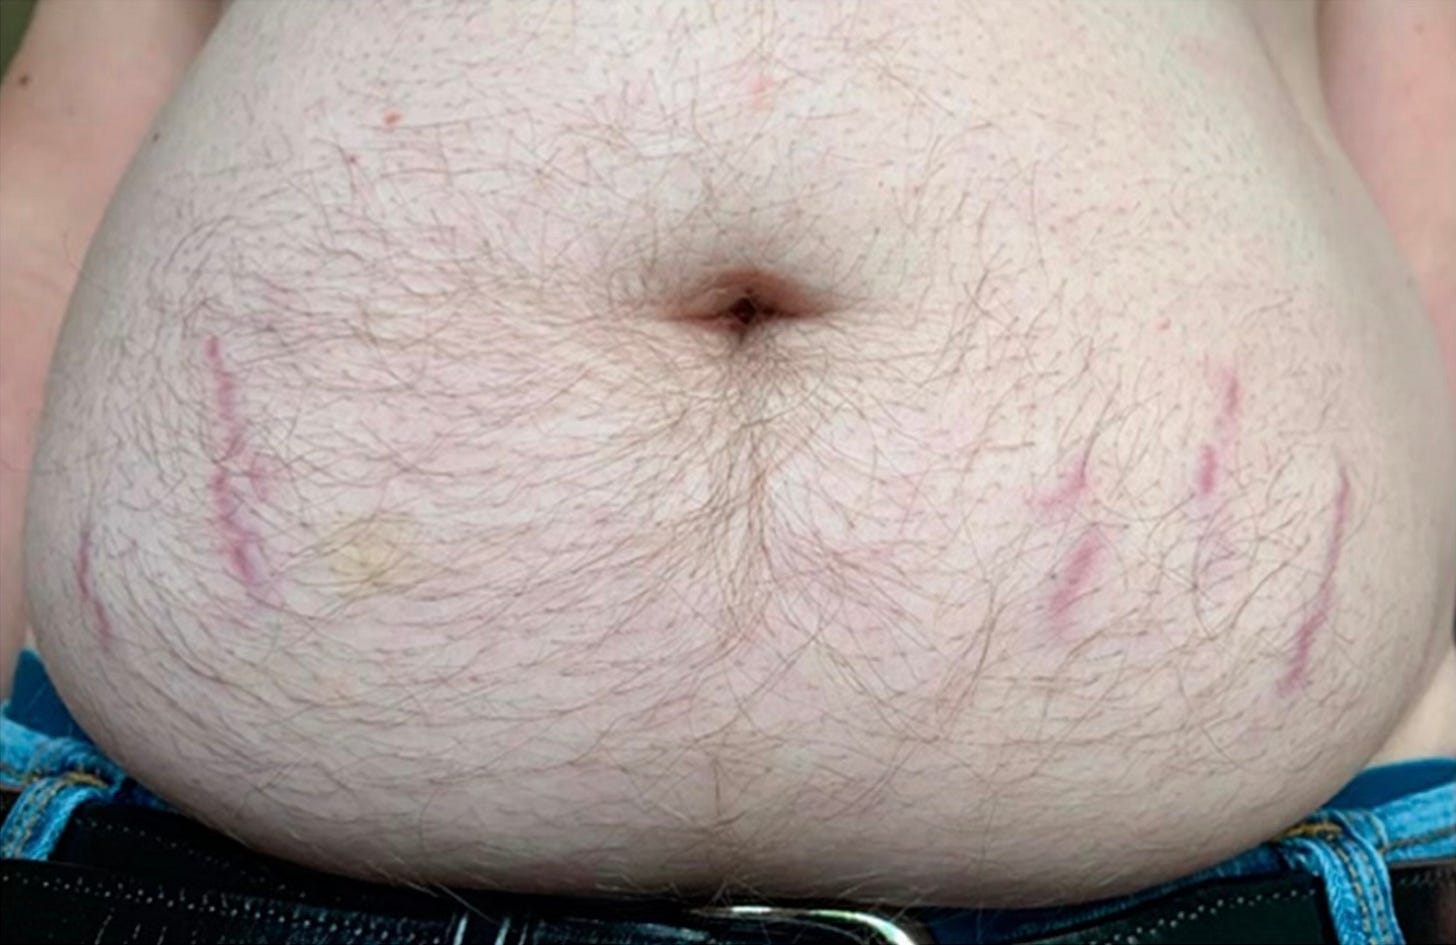
[From: Horowitz, R.I.; Fallon, J.; Freeman, P.R. Comparison of the Efficacy of Longer versus Shorter Pulsed High Dose Dapsone Combination Therapy in the Treatment of Chronic Lyme Disease/Post Treatment Lyme Disease Syndrome with Bartonellosis and Associated Coinfections. Microorganisms 2023, 11, 2301. https://doi.org/10.3390/microorganisms11092301%5D

Reactivation often happens when the immune system is unable to control the infection, due in part to the immunosuppressive nature of the bacteria.

I’ve found multiple species of Bartonella in our sickest patients leading to chronic variable immune deficiency (CVID), just as I’ve found Borrelia causing immune suppression, along with mold toxicity and Long Covid affecting immune functioning.

The multisystemic nature of Bartonella infections

When we see patients with Bartonella, as I mentioned, it has no resemblance whatsoever with the classical cat-scratch disease I learned about in medical school. Bacteria like Bartonella cause similar symptoms to those seen in chronic Lyme disease, presenting as a “great imitator.”

It can result in chronic fatiguing, musculoskeletal, cardiopulmonary, neuropsychiatric illness and can cause fevers, chills, fatigue, headaches, muscle/joint and nerve pain, cognitive difficulties, insomnia, depression, anxiety, and cause inflammation in every body system imaginable, just like Lyme disease, Borrelia burgdorferi, does.

There can also be inflammation in the eyes (optic neuritis, conjunctivitis, uveitis, arterial and venous occlusions); the brain, surrounding structures and spinal cord (meningitis, encephalitis, transverse myelitis, seizure disorders), with associated Bartonella “rage” and psychosis (Bartonella, like Lyme disease, can cause a broad range of psychiatric manifestations, including but not limited to severe depression, anxiety, Obsessive Compulsive Disorder, Bipolar disorder and schizophrenia with psychosis).

It also can cause inflammation in the muscles (myalgias), joints (arthritis, osteomyelitis), nerves (neuropathy) and blood vessels (vasculitis), as well as the heart valves (endocarditis, including culture negative endocarditis), heart muscle (myocarditis), and sac surrounding the heart (pericarditis) causing chest pain with masses in the chest (mediastinum) and lymph nodes resembling non-Hodgkins lymphoma.

Even the gastrointestinal tract can be affected (nausea, vomiting, weight loss, bleeding), as can the liver (hepatitis), spleen (splenitis, enlargement), and skin, which oftentimes shows signs of inflammation (stretch marks, i.e. striae; granulomas, hard fibrous areas over the knuckles, elbows, and Bacillary angiomatosis, which are tumor-like masses, raised dark areas, papules, nodules, and lesions in the skin, bones, and organs).

Bartonella is a frequently found infection in those suffering from chronic Lyme disease—I’ve seen it in up to 80-90% of all of my chronically ill patients these days and should be considered in any and all cases of FUO (fever of unknown origin).
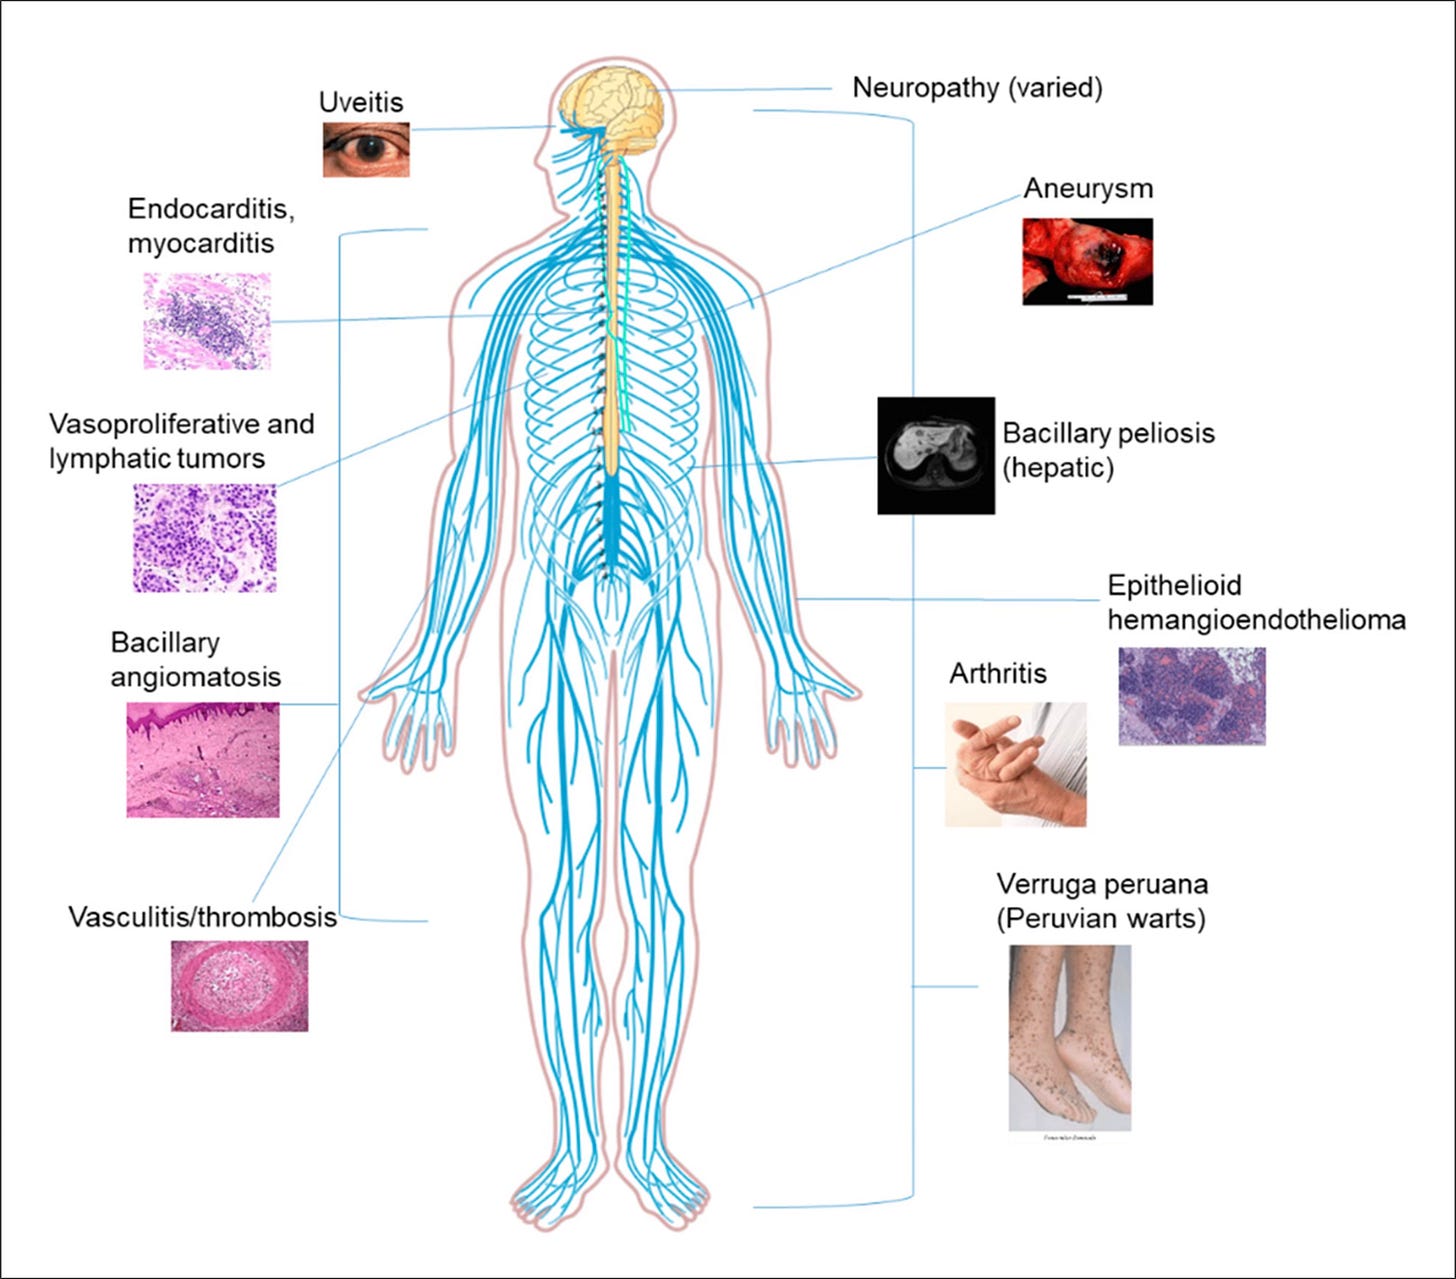
[From: Cheslock, M.A.; Embers, M.E. Human Bartonellosis: An Underappreciated Public Health Problem? Trop. Med. Infect. Dis. 2019, 4, 69. https://doi.org/10.3390/tropicalmed4020069%5D

Transmission of Bartonella

Part of the reason Bartonella has been a controversial topic in the Lyme community–at least among certain physicians and researchers–is because there has only been one study to date regarding tick transmission of the bacteria, and this was in European species of deer ticks (Ixodes ricinus) with one species, called Bartonella birtlesii.

The bacteria is, however, being found in ticks throughout the world, and other studies have shown the bacteria in different ticks and in chronic Lyme disease patients.

When I was co-chair of the HHS Tick-borne Disease Working Group (TBDWG) back in 2018, I had to fight to get Bartonella included as a co-infection of importance; whether all species are able to be transmitted by ticks or not, makes no difference.

Why? To date, the number of species able to transmit Bartonella keeps increasing over the years, and most of us are exposed to these vectors on a regular basis. The most common vectors transmitting the bacteria are fleas, mites, lice, keds (not the sneakers!), spiders, red ants, ticks (probable), sand flies, black and yellow flies, and mosquitoes.

Bartonella is showing up in a broad range of vectors, so it’s possible to get exposed from many different sources. That is why the vast majority of my sick patients are testing positive for it. In fact, for most of us living on this planet, I daresay we’ll all likely be exposed to Bartonella at some point during our lives. How we handle it, and whether we get symptoms, will depend on how our immune system is functioning.

Testing for multiple Bartonella species

The table below shows some of the most common species of Bartonella seen in human disease. This is not comprehensive, as there are now at least 45 species of Bartonella, and 18 of them or more are pathogenic [capable of causing disease].

Some of the most common ones are: B. henselae (Cat scratch disease, CSD; endocarditis, neuroretinitis, lymphadenopathy), B. quintana (Trench fever, endocarditis, bacillary angiomatosis [BA]), B. clarridgeiae (bacteremia, endocarditis, CSD, chest wall abscess), B. elizabethae (endocarditis, neuroretinitis),  B. bacilliformis (Carrion’s disease), B. koehlerae (endocarditis, including culture negative endocarditis), B. vinsonii subsp (bacteremia, endocarditis, fevers, neurological symptoms), B. berkhoffi (endocarditis, bacteremia, neurological symptoms), and B. grahamii  (neuroretinitis).

[From: Rebekah L. Bullard, Emily L. Olsen, Mercedes A. Cheslock, Monica E. Embers, Evaluation of the available animal models for Bartonella infections, One Health, Volume 18, 2024,100665, ISSN 2352-7714, https://doi.org/10.1016/j.onehlt.2023.100665.%5D

How do we test for Bartonella?

As you can see from the above table, testing for just one species makes no sense, because we can be exposed to a broad range of Bartonella species during our lifetime. I started to test for Bartonella over two decades ago. This is from an abstract I presented at the 16th International Scientific Conference on Lyme disease in 2003:

You can see from this abstract, even 22 years ago, by just testing for Bartonella henselae, one of the most common species, we found that using an ELISA and IFA (Immunofluorescent Assay) was positive in less than 50% of patients–but using DNA analysis with a PCR (Polymerase Chain Reaction) in the blood, we found 53% were positive when standard antibody assays were negative.

Which means the rule of thumb when testing for Bartonella is go as broad as you can. It is fine to start with local lab testing.

Level 1 testing

Using local labs like Quest, Labcorp, or Bioreference, you can send off antibody titers to B. henselae, B. quintana and B. bacilliformis, as well as PCRs and even a VEGF (vascular endothelial growth factor), an indirect marker of Bartonella exposure, indicating inflammation in the blood vessels (vasculitis). Often, however, you’ll want to use several specialty labs to prove infection.

Level 2 testing

If the above testing is negative, as it usually is, but you clinically suspect Bartonella, move on to the next level of tests. The three specialty labs include IgeneX laboratory (Bartonella IgM/IgG Immunoblots, Bartonella FISH [Fluorescent In-Situ-Hybridization test, an RNA test], T Labs (Bartonella FISH) with confocal microscopy, and Galaxy Laboratories, using their 4 species IFA antibody panel (for the most common species), and their ddPCR (direct droplet PCR) tests. The Bartonella Digital ePCR™ platform combines highly sensitive ddPCR technology with culture enrichment (BAPGM™).

I usually start with IgeneX laboratory and find that most of my patients have indeterminate or positive Immunoblots. Many times a negative Bartonella FISH test will turn positive later on during treatment, after the bacteria has been flushed out from the intracellular compartments where it’s been hiding.

I follow VEGF levels over time, as an indirect marker of Bartonella, when reactivation of infection is suspected. Keep in mind VEGF can be positive for other reasons (including Long Covid or cancer with metastases).

Level 3 testing

Skin biopsies can be done of the classical Bartonella rashes. Dr. Marna Ericson from T Labs has done this for me several times, and she found positive Bartonella in the skin, under biofilms, when it couldn’t be found through other methods.

I suspected Bartonella in two of my patients, but despite all classical testing, couldn’t prove exposure. The Bartonella fluoresces red under the microscope with this technique. I don’t suggest it as first level testing, but it can be very useful if you have looked for Bartonella using any and all of the above laboratories and methodologies.
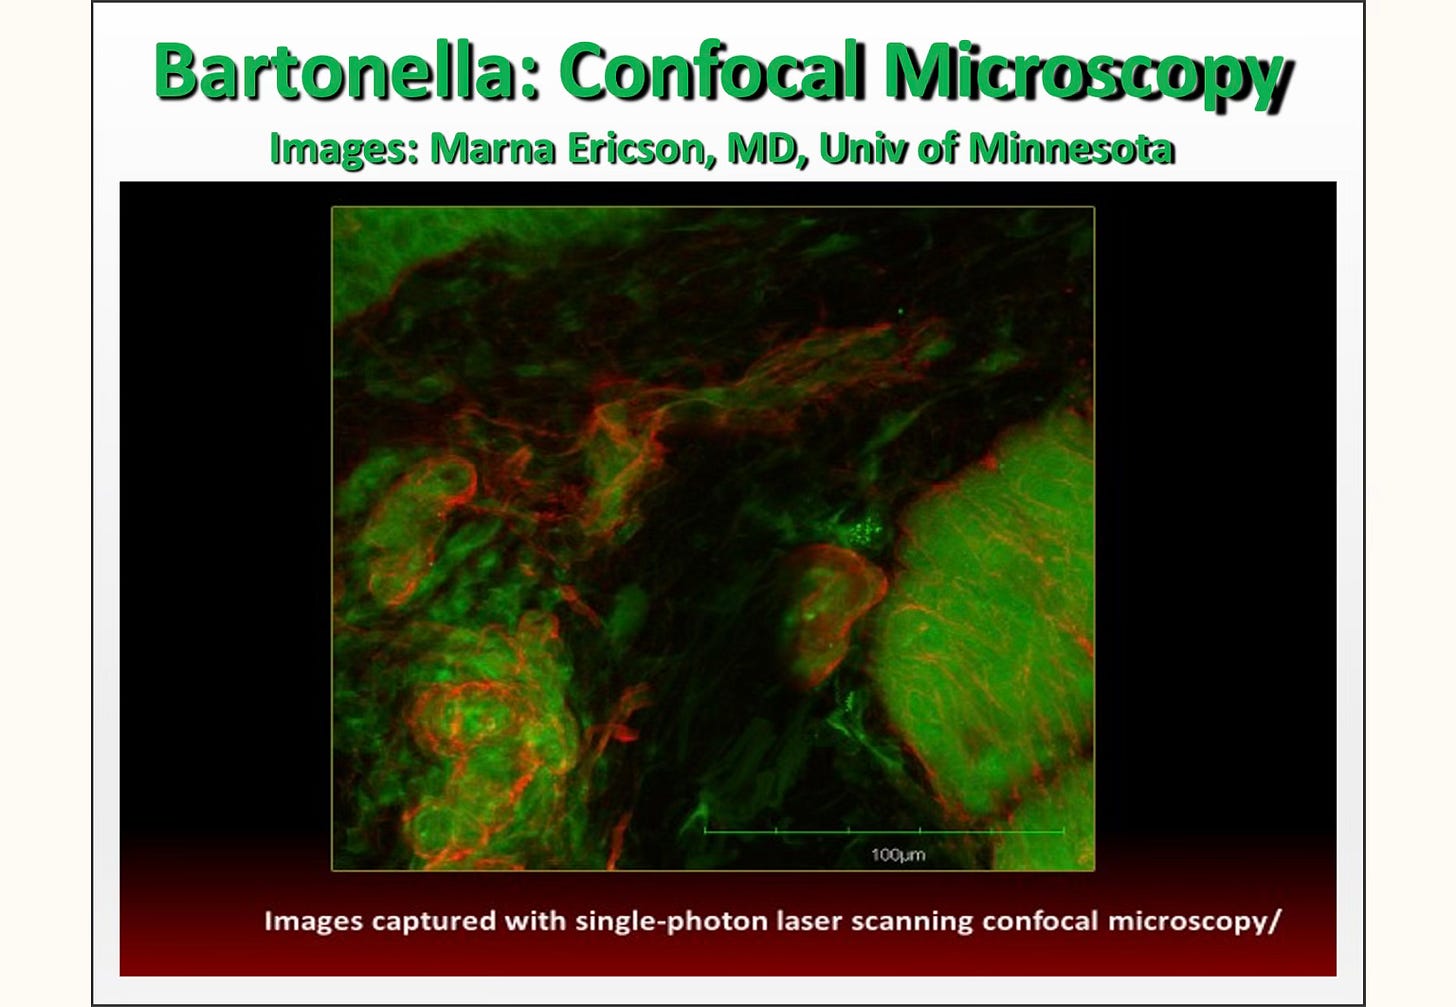
Stay tuned for parts 2, 3, 4 and 5

In Part 2, I’ll discuss more about establishing a diagnosis as well as an overview of how other co-infections may overlap and affect Bartonella symptoms. Part 3 will discuss effective treatments, and Parts 4 and 5 go into more detail about these treatments.

Dr. Richard Horowitz has treated 13,000 Lyme and tick-borne disease patients over the last 40 years and is the best-selling author of  How Can I Get Better? and Why Can’t I Get Better? You can subscribe to read more of his work on Substack or join his Lyme-based newsletter for regular insights, tips, and advice

For more:

Lyme Questions Answered and Mighty Methylene Blue

https://mailchi.mp/3e52484072a9/4i7vbuaut5-4797205

Conversations with Marty Ross MD: 1/9/25

Good Morning,

I enjoyed answering your questions on Wednesday night.

We discussed:

  1. Introduction and Webinar Format. Dr. Marty Ross explained the structure of his Lyme disease webinar, outlining guidelines for participation, including the use of the chat box for submitting questions, and detailed plans to provide session recordings and summaries.
  2. Addressing Sleep Jerks and Neurological Symptoms. Severe sleep jerks occurring when falling asleep were attributed to neurological irritation caused by infections like Bartonella, Borrelia, or mold toxicity, and potential remedies including curcumin, glutathione, and GABA-boosting supplements were discussed.
  3. Managing Nervous System Agitation. Strategies to calm the nervous system included treating infections, detoxifying mold, using anti-inflammatory supplements like curcumin and glutathione, and calming nerves directly via GABA enhancers such as L-theanine.
  4. Ozone and IV Vitamin C may Cause Nerve Damage. The use of oxidizing agents like IV vitamin C and UV ozone can worsen oxidation injury in tick-borne infection patients, with Dr. Ross warning against their potential nerve-damaging effects.
  5. Role of Hyperbaric Oxygen Therapy. While hyperbaric oxygen therapy (HBOT) may aid in neurological healing and support mitochondria, it is often ineffective for directly killing infections based on clinical experiences.
  6. Exploring White Blood Cell Counts in Tick-Borne Infections. Chronic infections like Borrelia, Bartonella, or Babesia often cause reduced neutrophil counts, which may normalize over time with effective treatment.
  7. Pregnancy Considerations and Tick-Borne Disease Testing. Pregnancy planning was addressed with recommendations for comprehensive infection testing, symptom-tracking, and considerations for treatment strategies that align with maternal and fetal health.
  8. Re-testing for Infections to See Where Your Are Is Not Accurate. Retesting for tick-borne infections was deemed unreliable as antibodies can fluctuate; instead, tracking symptoms was suggested as a better measure of disease progression.
  9. Indirect vs Direct Testing for Borrelia. Dr. Ross explained the differences in sensitivity between indirect (antibody-based) and direct (PCR or culture) testing methods, emphasizing the limitations of direct tests in chronic infections.
  10. Babesia Treatment Length before Pregnancy. Recommendations for treating Babesia included maintaining a five-month treatment course, balanced with probiotics and potential yeast management, to optimize health before pregnancy.
  11. Addressing Gastrointestinal Symptoms during Treatment. GI symptoms during antimicrobial treatment were linked to gut flora disturbance and potential yeast overgrowth, calling for probiotics and antifungal options like Nystatin or CapriPlus.
  12. Management of Cytokines and Herx Reactions. Elevated cytokines causing inflammation and herx reactions were addressed with anti-inflammatory interventions, including quercetin or curcumin, and glutathione supplementation.
  13. Best Ways to Lower Cytokines and to Control Herx. Suggestions to lessen herx reactions included increasing glutathione levels and using quercetin for both anti-inflammatory and mast cell-stabilizing effects.
  14. Meaning of a Single White Brain Lesion on MRI. A single white lesion on MRI is typically attributed to aging or limited blood flow rather than Lyme disease, which usually exhibits diffuse demyelination patterns.
  15. You Don’t Have to Herx to Make Progress. Not all patients experience herx reactions during treatment, yet progress is still possible, particularly as the germ load decreases over time.
  16. Methylene Blue and Its Uses. Methylene blue was recognized as a therapy for both Borrelia and Bartonella due to its efficacy against persister cells, as well as for its FDA-approved use in addressing methemoglobinemia. Go here for a sound warning of methylene blue, which is a man-made monoamine oxidase inhibitor.  Animal and human studies have shown that when monoamine neurotransmitters are over-activated it eventually makes those taking it subdued, apathetic and disengaged from their own feelings, those around them, and life itself.
  17. Methylene Blue for Improved Thinking and Mitochondria Function. Beyond pathogen-killing properties, methylene blue improves mitochondrial function, aids ATP production, and has shown promise for reducing brain fog and increasing energy.
  18. Potential Risks and Side Effects of Methylene Blue. Risks of methylene blue include bladder irritation, intestinal discomfort, and staining issues, though real-world human risks are minimal when dosed properly.
  19. Mitochondrial Function and Repair. Recommendations for repairing mitochondrial damage included supplements like glutathione and ATP 360 to enhance cellular energy production.
  20. Exploring Histamine Reactions. Unusual reactions like hives or hyperactive histamine levels during treatment were linked to mast cell activation, which can be managed with stabilizers and antihistamines.
  21. Taking Enzymes and EDTA. Potential interactions between enzymes and EDTA supplements were addressed, with Dr. Ross advising additional research to confirm compatibility.
  22. Impact of Biocidin on Direct Testing Results. Biocidin, containing antimicrobial ingredients like oregano oil and garlic, may reduce the accuracy of direct tests like PCR by lowering pathogen levels in the blood.
  23. Causes of Visual Issues. Neuropathic visual challenges like light sensitivity and convergence insufficiency were discussed as possible symptoms of Bartonella, Borrelia, or mold toxicity.
  24. Causes of Air Hunger. Air hunger, frequently caused by Babesia or Bartonella, results from disrupted oxygen delivery due to inflamed red blood cells or reduced red blood cell quantity.
  25. Muscle Contractions and Spasms. Severe muscle spasms were linked to magnesium deficiency or neurological irritation, with treatment approaches including supplements and anti-inflammatory support.
  26. Thoughts on Steps if You Are Not Getting Better. Persistent illness despite treatment prompted considerations for comprehensive reviews of treatment history and potential alternative strategies like addressing limbic system dysregulation.
  27. Role of Limbic System Retraining for Chronic Symptoms. Limbic system retraining methods such as dynamic neural retraining (DNRS) were recommended for addressing chronic illness patterns after addressing active infections.
  28. Senescent Cells may Cause Ongoing Inflammation and Chronic Symptoms. Cell senescence caused by infections may perpetuate inflammation, with solutions including senolytics, fasting mimicking diets, and autophagy-promoting supplements.
  29. Timing of Limbic System Retraining and Physical Medicine. Brain retraining exercises and somatic therapies are best initiated after active infections are controlled to avoid exacerbating symptoms.
  30. Evaluating ZenMen for Bartonella. The herbal formula ZenMen showed promise in addressing Bartonella but lacked sufficient evidence on effectiveness or ingredient concentrations for strong recommendations.
  31. Role of Ketotifen for Mast Cell Activation. Ketotifen was highlighted as an effective option for calming histamine-driven nervous system agitation by blocking histamines and stabilizing mast cells

Sign Up for the January Lyme Q&A Series Through LymeUNITED

We’ve Moved. Conversations with Marty Ross MD is located inside the LymeUNITED membership support community. LymeUNITED is now FREE. But you will need to join LymeUNITED and then RSVP to participate in the Wednesday webinar.

  • Step 1. Join LymeUNITED for Free
  • Step 2. Click “Dr. Ross Q&A Webinar” in the left column navigation menu
  • Step 3. Click on the title of the event you want to attend to RSVP and to learn all about Conversations with Marty Ross MD using the live Zoom Room through LymeUNITED.

Join LymeUNITED Now.

Watch Webinar Recordings

You have two options to watch Conversations with Marty Ross, MD Recordings.

  1. With Recording Headings and Time Stamp. In LymeUNITED you can watch the recording which includes time stamps and headings to find what you are looking for more easily. Once you are in LymeUNITED go to the “Zoom Event Recordings” located in the left hand navigation menu. Watch on LymeUNITED.(Note: if you are not a member, you will need to join first to watch from the video link above. Join LymeUNITED Now.)
  2. No Headings or Time Stamps. Watch on YouTube. This version does not require you sign up for a Free LymeUNITED membership. But, it does not include time stamps or section headings. Watch on YouTube.

Get Help and Support

If you have questions, there are three ways that we can help you.

  1. Join LymeUNITED: A Community Powering Health for FREE. This is our online support community hosted by Marty Ross, MD with an active group of supporting members. You don’t have to do it alone.
  2. Participate in our free weekly Lyme Q&A webinar called Conversations with Marty Ross MD.
  3. Read, or watch our helpful articles in the online Lyme Guide at Treat Lyme by Marty Ross MD.

In Health,

Marty Ross MD

*Comment*

I’ve never heard of ozone and IV C causing nerve damage.  Ever.  My LLMD uses this as a mainstay in treatment and would never use them if they in fact caused nerve damage. Of course the toxin is always in the dose.

Is a U.S. Bioweapons Program Behind Lyme Disease?

http://  Approx. 19 Min

Lyme Disease & POTS

https://www.globallymealliance.org/blog/lyme-disease-and-pots?

Learn about the connection between Lyme disease, POTS, and Lyme carditis, and discover the importance of early diagnosis and specialized medical care.

Have you heard of POTS?

Between my freshman and sophomore years of college, I was bitten by a tick while working at a summer camp in the woods of Maine. As I’ve described in many of my blog posts, it took eight years for me to be accurately diagnosed, and during that time I suffered from a range of physical and neurological symptoms. During the fall semester of my sophomore year, I had flu-like symptoms as well as symptoms of what the college nurses thought were panic attacks.

Looking back now, I wonder if my heart palpitations, lightheadedness, and dizziness were in fact signs POTS, or Postural orthostatic tachycardia syndrome. At the time, POTS was little if at all understood, but now researchers and physicians are seeing POTS not just in Lyme disease patients but also in conditions like long COVID and ME/CFS.

POTS occurs when moving from lying to standing causes an increase in heart rate by at least 30 beats per minute for adults and 40 beats per minute for children. In addition to this abnormal increase in heart rate, the Heart Rhythm Society defines POTS as a clinical syndrome characterized by symptoms of lightheadedness, blurring of vision, palpitations, intolerance to exercise, and fatigue, as well as the absence of orthostatic hypotension[i] (meaning the blood pressure does not drop when the heart rate rises). I experienced all of these symptoms that fall in college. Had POTS been more well-known, its symptoms could have pointed puzzled medical practitioners in the direction of tick-borne disease. That was 1997; a recent study shows that the incidence of POTS has increased four-fold since 2000.[ii]

Another Lyme-related condition, Lyme carditis

Heart-related symptoms such as racing heartbeat can also be a sign of another condition known as Lyme carditis, when the Lyme bacteria goes to the heart. This can cause atrioventricular block, often referred to as “heart block,” which is an electrical disconnect between the upper and lower chambers of the heart, causing them to beat at different rhythms. Lyme carditis can also manifest as costochondritis (inflammation of the cartilage that connects the ribs to the breastbone), tachycardia (racing heart rate) and bradycardia (slow heart rate). It can also cause myopericarditis (inflammation of the heart muscle and lining), which patients may feel as chest pain or shortness of breath.

Though Lyme carditis is rare, according to a 2008 study, 4% to 10% of all patients with Lyme borreliosis. Whenever the clinical suspicion of Lyme carditis arises, an ECG is mandatory to detect or exclude an atrioventricular conduction block.

If you have already been diagnosed with Lyme disease, it’s important that your doctor check specifically for Lyme carditis, and also evaluate you for POTS. If you are experiencing symptoms of either Lyme carditis or POTS, see a Lyme Literate Medical Doctor (LLMD) to find out if tick-borne disease may be the cause. I only wish I had seen a LLMD sooner; I might have avoided years of suffering.

Click here to read more blogs.

[i] https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7255540/

[ii]  Epidemiology of postural tachycardia syndrome. [Apr;2020 ];AbdelRazek M, Low P, Rocca W, Singer W. https://n.neurology.org/content/92/15_Supplement/S18.005 Neurology. 2019 92:0.

The above material is provided for information purposes only. The material (a) is not nor should be considered, or used as a substitute for, medical advice, diagnosis, or treatment, nor (b) does it necessarily represent endorsement by or an official position of Global Lyme Alliance, Inc. or any of its directors, officers, advisors or volunteers. Advice on the testing, treatment or care of an individual patient should be obtained through consultation with a physician who has examined that patient or is familiar with that patient’s medical history.
Writer

Jennifer Crystal

Opinions expressed by contributors are their own. Jennifer Crystal is a writer and educator in Boston. Her work has appeared in local and national publications including Harvard Health Publishing and The Boston Globe. As a GLA columnist for over six years, her work on GLA.org has received mention in publications such as The New Yorker, weatherchannel.com, CQ Researcher, and ProHealth.com. Jennifer is a patient advocate who has dealt with chronic illness, including Lyme and other tick-borne infections. Her memoir, One Tick Stopped the Clock, was published by Legacy Book Press in 2024. Ten percent of proceeds from the book will go to Global Lyme Alliance. Contact her via email below.

Email: lymewarriorjennifercrystal@gmail.com

Lyme Research – Same Crap, Different Day

https://pubmed.ncbi.nlm.nih.gov/28613720/

Lyme Disease

In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2025 Jan.
.
  • PMID: 28613720

Excerpt

Lyme disease, or Lyme borreliosis, is the most commonly transmitted tick-borne infection in the United States (US) and among the most frequently diagnosed tick-borne infections worldwide. Lyme disease is divided into 3 stages: early localized, early disseminated, and late. Early localized disease is distinguished by the red ring-like expanding rash of erythema migrans at the site of a recent tick bite. Other symptoms experienced at this stage may be malaise, headache, fever, myalgia, and arthralgia. Most patients only experience the symptoms of early localized disease. About 20% of patients develop early disseminated disease, with the most common symptoms being multiple erythema migrans lesions.

Other symptoms of the disseminated stage are flu-like symptoms, lymphadenopathy, arthralgia, myalgia, palsies of the cranial nerves, especially of cranial nerve VII, ophthalmic conditions, and lymphocytic meningitis. Additionally, cardiac manifestations, including conduction abnormalities, myocarditis, or pericarditis, may occur. The most common late-stage manifestation is arthritis, which is usually pauciarticular and affects large joints, especially the knees. Lyme disease is a curable condition if identified and treated appropriately.

_______________

**Comment**

Sigh……here we go again.  Our tax dollars at work killing patients by regurgitating the same myths for over 40 years.

  1. The ‘3 stages’ of Lyme myth has been dispelled numerous times yet repeated with abandon.  Here we learn of a child who within 4-6 hours of tick bite developed widely disseminated disease where she suddenly couldn’t walk or talk.  The ‘stage’ narrative is killing people by giving them a false sense of time.  Some people have very little time before chronic/persistent infection becomes a reality.
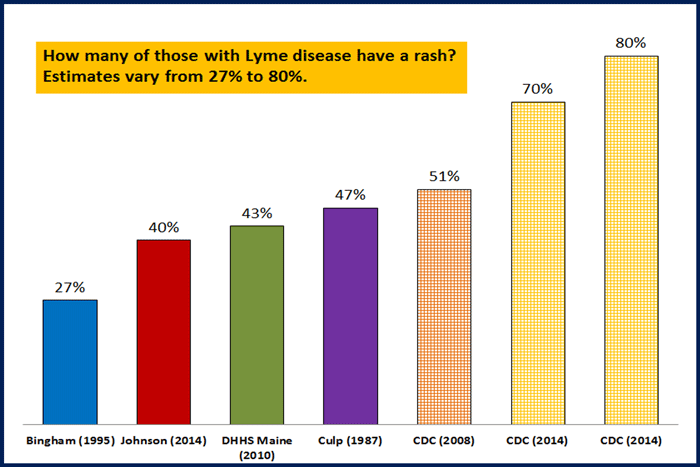
  2. Hardly anyone I work with gets an EM rash, and a study found only 6% got it.  The rash is highly variable and prone to misdiagnosis.  There is nothing ‘classic’ about it.

    • The rash issue, as well as waiting for the results of a faulty test, has caused frequent, unnecessary delays in diagnosis and treatment, dooming patients to a lifetime of suffering, as doctors are not properly educated on actual science, but have been fed a CDC-narrative that continues on with ratchet studies like this one.  Most doctors are unaware that while this rash is diagnostic for Lyme disease and that misdiagnosis can have fatal consequences, lack of a rash means zippo.
    • Aucott reports that 54% of Lyme disease patients who present without a rash are misdiagnosed.
  3. The litany of symptoms (that can be psychiatric) continues to be ignored despite case after case after case showing this reality. Many of these symptoms are often caused by coinfections that come with Lyme, but this factoid is repeatedly ignored by mainstream research. Therefore the statement: “Most patients only experience the symptoms of early localized disease,” is completely and utterly erroneous.  Further, the statement: “the most common late-stage manifestation is arthritis, which is usually pauciarticular (involvement of 4 or fewer joints) and affects large joints, especially the knees,” is also utter garbage. They insist on propagating an acute illness, caused by a singular bacterium because it fits the ‘vaccine’ narrative.  This is also why the vaccine topic is huge and should be taken seriously by the Lyme/MSIDS community, and in order for that to happen, an understanding of the ‘vaccine’ fraud is mandatory reading, not to mention the fact every patient I know who got ‘vaccinated’ relapsed.
  4. Sexual and congenital transmission is also categorically ignored.
  5. The statement: “Lyme disease is a curable condition if identified and treated appropriately,” is sheer hopium based upon nothing but pixie dust.
  6. Besides the fraudulent ‘vaccine’ narrative, it’s imperative to understand government ‘public health’ is nothing more than a peddler for Big Pharma.  This is why mainstream research via government grants and/or industry funding will only continue to regurgitate damaging information presented in this recent article. The design of Lyme/MSIDS research purposely omits the sickest patients, ignores seronegativity, and relies upon a test that misses around 90% of all cases – utilizing a rash nobody can identify and few have! 
There is no greater example of having the deck stacked against you.

The only hope for chronically ill patients is N-of-1 Trials.

This study and all others funded by government is a waste of time and money.