Archive for the ‘Lyme’ Category

The Three Bs – Borrelia, What, and What? Co-infections & Chronic Illness

https://www.lymedisease.org/the-three-bs-borrelia-what/

The three Bs – Borrelia, What, and What? Co-infections and chronic illness

By Nicole Bell, Galaxy Diagnostics CEO

3/10/25

While many people in the Lyme community are familiar with the three Bs – Borrelia, Bartonella, and Babesia – most people outside the community look confused when I mention these top flea and tick-borne pathogens. I understand their puzzled looks because back in 2017, I was confused too.

Even after my husband, Russ, was diagnosed with these three stealthy invaders, I focused all my research on Borrelia, the bacteria causing Lyme disease.

It ended up taking a tragic journey followed by years of studying the research to gain an appreciation for the complexities of all three pathogens – and that research is still unfolding.

In complex cases, co-infections are the rule, not the exception.

The first thing to understand when considering the three Bs, is that in complex cases, co-infections are common. In a survey of over 3,000 chronic Lyme disease patients published by LymeDisease.org, over 50% had co-infections, and 30% had two or more co-infections. Babesia and Bartonella top the co-infection list, each presenting in about 30% of chronic Lyme cases.
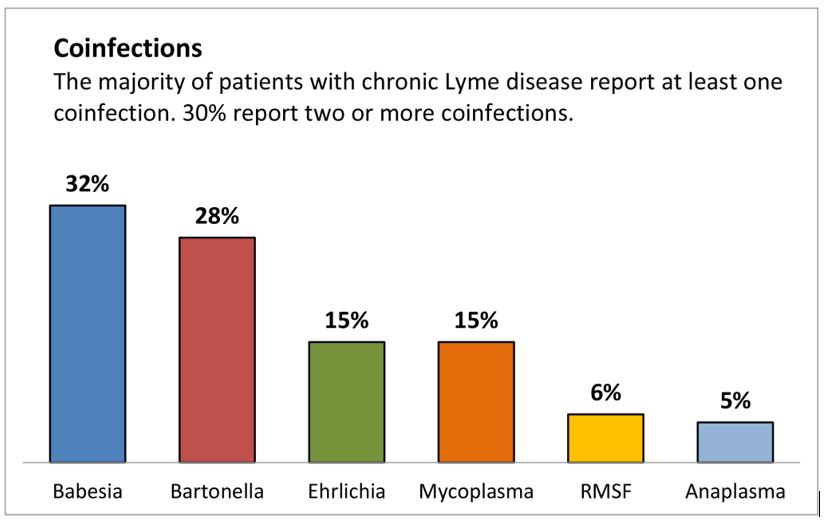
Source: About Lyme Disease Co-infections, LymeDisease.org

The second thing to understand about these pathogens is that calling them “Lyme co-infections” is misleading. All these pathogens – the other Bs and beyond – can be present without a Borrelia  infection (past or present).

The problem is that many doctors don’t have these invaders on their differential – and it’s easy for a pathogen to be considered rare if you never test for it. 

Rare disease? Or inadequate testing and data?

To understand the true prevalence of these pathogens, we need to dig into the details of each pathogen and how we count and test for them. For example, before 2013, Lyme incidence in the U.S. was estimated to be approximately 30,000 cases per year. Then, in 2013, the CDC looked at clinical records, laboratory reports, and public surveys and increased this estimate 10-fold.

In 2021, an analysis of insurance records increased the estimates again, and current data shows that approximately 500,000 Americans are diagnosed and treated annually. And since the standard of care test for Lyme leading to diagnosis and treatment is 40-60% accurate, even this number is likely underestimating the extent of the problem.

So, the question looms – what is the prevalence of the other two Bs? Are they destined for a similar exponential increase as we dig into the data? Emerging research points to yes.

Bartonella – The Hidden Pandemic

Bartonella is a genus of gram-negative bacteria that can infect humans and a wide range of animals. Googling the bacteria shows that it is the pathogen causing cat scratch disease or CSD, an acute form of the infection. But like Lyme, this pathogen has been associated with complex chronic conditions spanning multiple body systems, including the joints, eyes, heart, and brain.

Lyme disease has made people fearful of ticks, but Bartonella can be transmitted by a long list of biting insects – or vectors – including fleas, body lice, sand flies, and even spiders. Also, an underappreciated risk factor for bartonellosis is animal exposure, particularly exposure to cats, which are natural reservoirs of the bacteria.

In a study of veterinary workers, 44% were positive for Bartonella antibodies, and 28% had DNA of the pathogen detected directly from their blood. With approximately 66% of U.S. households owning at least one pet, the pathogen has the potential to be more widespread than generally thought.

Dr. Ed Breitschwerdt from North Carolina State University’s veterinary school has studied Bartonella since the 1990s. The advanced testing methods developed in his lab by collaborator Dr. Ricardo Maggi have uncovered key links between the pathogen and complex illnesses, such as arthritis, chronic fatigue, and fibromyalgia.

Neuropsychiatric conditions

Recently, using innovations in advanced PCR technology, the lab has made groundbreaking discoveries linking Bartonella and neuropsychiatric conditions, such as schizophrenia.

The investigation into schizophrenia started the way many discoveries in medicine do, with one case. A 14-year-old boy – who we will call Michael – suffered from sudden onset psychosis and received a formal diagnosis of schizophrenia. Michael was referred to Dr. B’s lab because he had marks on his skin, called striae, consistent with a Bartonella infection.

Dr. B and his team used their advanced test methods to confirm that Michael was infected with Bartonella. Upon treatment with the appropriate antibiotics, his symptoms evaporated.

The case inspired Dr. Breitschwerdt to consider a hypothesis – what if other patients were experiencing psychosis because of a Bartonella infection? Bartonella can cross the blood-brain barrier and infect endothelial cells, contributing to neuroinflammation.

The hypothesis had merit. His lab partnered with the University of North Carolina to test 17 schizophrenia patients. Sixty-five percent of those patients tested PCR positive for the pathogen, compared to 8% in healthy controls.

A subsequent study with Columbia University on over 100 patients found that people affected with psychosis were over three times more likely to have direct evidence of Bartonella in their blood than unaffected controls.

PANS

And schizophrenia isn’t the only neuropsychiatric condition linked to the pathogen. Pediatric patients with Bartonella infections have been reported to develop Pediatric Acute-onset Neuropsychiatric Syndrome (PANS) and symptoms like anxiety, obsessive-compulsive disorder, and cognitive dysfunction. Case studies have shown improvement in neuropsychiatric symptoms following treatment of the underlying infections.

With over 3 million Americans battling schizophrenia and 1 in 200 children in the U.S. affected by PANS, Bartonella may emerge as the great hidden pandemic.

Babesia – the tip of the iceberg

Babesia is a tick-borne parasitic infection, often touted as similar to malaria, because both parasites infect and replicate within red blood cells and can cause fever, chills, sweats, headache, muscle aches, fatigue, and hemolytic anemia.

Researching Babesia on the CDC Website shows that under 2000 cases were reported nationwide in 2020. The CDC notes that most Babesia cases in the U.S. are caused by Babesia microti, with occasional cases caused by other Babesia species.

Using the same advanced PCR technology that drove clinical discovery in Bartonella, Dr. B and his team turned their attention to Babesia. They found that what we “know” about Babesia may only be the tip of the iceberg.

In 82 individuals the lab was studying for Bartonella infection, 22 (27%) were also infected with Babesia. Furthermore, the top Babesia species identified was not Babesia microti, as expected from CDC data, but rather Babesia divergens (considered rare in the U.S.) and then Babesia odocoilei (considered rare in humans).

Before Dr. B’s work, only a handful of case reports in the U.S. have ever been reported for Babesia divergens. Their best-in-class assay turned up 12 new cases in a group that wasn’t even targeted for Babesia studies.

Dr. B’s team also recently published a paper where an entire family – all five members and one of their dogs – tested positive for a Babesia-divergens-like species. Similar new case discoveries have been made for Babesia odocoilei. His work poses the question – are the pathogens really rare, or are we just not testing for them properly?

Genus versus species – why it matters

Genus and species are terms commonly used by microbiologists, but when I first entered the world of tick-borne disease, I didn’t fully understand their significance. The “genus” is akin to a family name, grouping related individuals – think Hatfields and McCoys. The “species” is like the first name, identifying a specific individual in the family.

Translating this to Lyme disease, Borrelia is the genus or family name, and Borrelia burgdorferi is the species name identifying the particular pathogen.

So why does it matter? The current commercial test methods for all three Bs generally use serology or antibody testing. These assays measure antibodies created by the host’s immune response to the pathogen. The problem is that antibodies react to proteins on the surface of the pathogen, and these proteins can vary depending on the particular species.

In other words, the patriarch of the Hatfield family, Anderson Hatfield, looked and dressed differently than his son Cap Hatfield. Thus, sending out a warrant and a picture of Anderson is unlikely to lead to Cap’s arrest.

Antibody testing is similar, and testing for Babesia microti, may not accurately diagnose a case of Babesia odocoilei or Babesia divergens. There are over 100 known Babesia species, with 15 of those confirmed in human cases.

There are over 50 species of Bartonella, at least 20 of which have been documented to infect humans and other mammalian hosts. Dr. B’s research and testing technology is redefining what we know about these pathogens. And until these tests are launched commercially, millions have the potential to be misdiagnosed.

Direct Detection for BBB is Launching at Galaxy Diagnostics

Fortunately, Galaxy Diagnostics was founded by Dr. Breitschwerdt, Dr. Maggi, and Dr. Amanda Elam to bring these diagnostic advancements to market. This month, Galaxy is launching its digital PCR, direct detection assay for BBB.

This assay has been instrumental in driving clinical discovery in Dr. B’s lab and will now be commercially available to practitioners. Top features of the assay include:

  • Genus level detection, detecting each pathogen regardless of species.
  • Ultra-sensitive, digital PCR, which increases detectability for low abundance pathogens.
  • Multiplexed detection to provide three results in a single test.

The BBB assay is a blood-based assay that detects the DNA of each pathogen. The approach has previously been used only in a research setting, but the team at Galaxy has now validated the assay for commercial use.

Bartonella and Babesia – but what about Borrelia?

The BBB assay is a blood-based approach, and it is essential to note that blood is NOT the best matrix for Lyme Borrelia, as I have discussed previously.

Galaxy recommends its urine antigen test for Lyme since the concentrations of Lyme Borrelia are so low in the blood that a blood draw is unlikely to capture the pathogen in the test tube. And no matter how sensitive the technique is, if the pathogen isn’t in the tube, there is no way to detect it.

So then, why is Borrelia included in the BBB assay? The answer goes back to the genus versus species issue. While the species associated with Lyme Borrelia often hide in tissues and don’t free-circulate in high copy numbers in blood, the species associated with Relapsing Fever Borrelia do replicate to high numbers in the blood.

As a result, combining the BBB assay with Galaxy’s Nanotrap urine antigen test for Lyme provides optimal coverage for the top flea and tick-borne infections at the genus level.

Coming Full Circle – Avoiding Cases like Russ

After my husband Russ passed, the engineer in me knew there had to be better options. I immersed myself in the research and found Dr. B’s published peer-reviewed results. I introduced myself to the Galaxy team, and as I dug in, I became even more convinced that their technology would provide the clarity I craved as a caregiver.

In June 2024, I became Galaxy’s CEO to bring these advanced testing techniques to a broader market. We crystallized our mission to provide a new standard of care for diagnosing these devastating flea and tick-borne diseases. With the commercial launch of the BBB assay, we are one step closer to that goal. I know that Russ is watching – and smiling.

Nicole Bell, CEO of Galaxy Diagnostics, is also the author of What Lurks in the Woods and The State of Lyme Disease Research. 

For more:

Lyme Disease Increases Risk for Multiple Gynecological Conditions

https://www.medrxiv.org/content/10.1101/2025.03.03.25323258v1

Lyme disease increases risk for multiple gynecological conditions

Paige S. Hansen Colburn, Grace Blacker, Sarah Galloway, Qingying Feng, Prasanna S. Padmanabham, Guido Pisani, Brandon T. Lee, Grace Loeser, Monika W Perez, Kunzan Liu, Jade Kuan, Emelia von Saltza, Satu Strausz, Lisa M. Mattei, Sophie VanderWeele, George R. Nahass, Amie Kitjasateanphun,  Rangarajan Bharadwaj, Hari-Hara SK Potula, Maia Atzmon Shoham, Finngen, Victoria L. Mascetti, Eric Gars, Hanna M Ollila, Kaylon L. Bruner-Tran, Irving Weissman,  Sixian You, Beth Pollack, Linda Griffith, Nasa Sinnott-Armstrong,  Michal Caspi Tal

Abstract

Lyme disease (LD) is an illness caused by the spirochete Borrelia burgdorferi (B. burgdorferi). Borrelia is known to disseminate through organs, including the skin, joints, spinal cord, bladder, and heart, leading to Lyme arthritis, neuroborreliosis, and Lyme carditis. While previous studies have investigated the impact of LD on pregnancy in both mice and humans and have found the presence of B. burgdorferi in the uterus of mice, we studied the impact of LD on the non-pregnant female reproductive tract. We use a mouse model for LD and find an ongoing and severe infection of the reproductive tract of female mice, which persists up to 15-months post-inoculation. This infection results in uterine glandular cysts and endometrial hyperplasia as well as vaginal epithelial thickening, polymorphonuclear and mononuclear cell epithelial infiltration, and epithelial desquamation into the vaginal lumen. Strikingly, we find that age has an impact on the extent of gynecologic pathology such that aged female mice (1-year old) that are reproductively senescent have more gynecologic pathology with infection compared to young mice (15-weeks old) when infected for the same length of time. Using large-scale electronic healthcare record data, we report that LD additionally results in increased infection-associated risk of:

  1. menorrhagia (1.5-fold)
  2. miscarriage (1.62-fold)
  3. uterine fibroids (1.42-fold)
  4. endometriosis (1.93-fold)

Underreporting of gynecological outcomes is pervasive throughout many different infectious diseases, and LD-associated gynecological pathologies may have been similarly underappreciated in the field. This work suggests that further study of the female reproductive tract and the effects of B. burgdorferi infection therein will help clarify and expand the knowledge of myriad LD outcomes.

For more:

The Lymeland Emperor Has No Clothes On

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/33299384?

The emperor has no clothes!

Carl Tuttle
Hudson, NH, United States
Mar 3, 2025

Please see the following inquiry that will most likely go unanswered. Note that Dr. John Aucott is a coauthor of this study who often says he believes in chronic Lyme disease but only at Lyme disease events held by advocacy groups. 

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: “aghirsch@geisinger.edu” <aghirsch@geisinger.edu>
Cc: “aejustice1@geisinger.edu” <aejustice1@geisinger.edu>, “cmnordberg@geisinger.edu” <cmnordberg@geisinger.edu>, “nsjosyula@geisinger.edu” <nsjosyula@geisinger.edu>, “jaucott@jhmi.edu” <jaucott@jhmi.edu>, “alison.rebman@gmail.com” <alison.rebman@gmail.com>, “bschwar1@jhu.edu” <bschwar1@jhu.edu>, “bmcinfectiousdiseases@biomedcentral.com” <bmcinfectiousdiseases@biomedcentral.com>, “irina.masalagiu@springernature.com” <irina.masalagiu@springernature.com>, “rauf.bhat@springernature.com” <rauf.bhat@springernature.com>
Date: 03/01/2025 12:04 PM EST

Subject: A comparison of genome-wide association analyses of persistent symptoms after Lyme disease, fibromyalgia, and myalgic encephalomyelitis – chronic fatigue syndrome

A comparison of genome-wide association analyses of persistent symptoms after Lyme disease, fibromyalgia, and myalgic encephalomyelitis – chronic fatigue syndrome
https://bmcinfectdis.biomedcentral.com/articles/10.1186/s12879-024-10238-x

Annemarie G. Hirsch, Anne E. Justice, Amy Poissant, Cara M. Nordberg, Navya S. Josyula, John Aucott, Alison W. Rebman & Brian S. Schwartz

To: Annemarie G. Hirsch, Corresponding Author

I read your manuscript with great interest and wanted to share a comment on your article I received from a fellow researcher who has experienced first-hand the devastation of Lyme disease. I added HTML links (references) to his statement and included my own comment. Additionally, I have a question for you and your co-authors.

Comment received:

“With respect may I say as Lyme and PTLD victim, Borrelia has the following characteristics:

Or, maybe it’s as the authors claim that PTLD is associated with:

“Our top index single nucleotide polymorphism (SNP), rs77857587, is in high linkage disequilibrium with a long-range protein quantitative locus SNP, rs111774530, for the MARC2 (Mitochondrial Amidoxime Reducing Component 2) protein.”

Carl Tuttle’s comment:

If I’m interpreting his comment correctly, it would appear that we have been dealing with an antibiotic resistant/tolerant superbug and essentially, “the emperor has no clothes.”

Question:

What academic discipline would you encounter if your department acknowledged chronic Lyme disease and began focusing on finding effective antimicrobial treatments for all borrelia forms; round body, biofilm etc.?

A response to this inquiry is requested.

Carl Tuttle
Independent Researcher
Hudson, NH

Cc: Rauf Bhat, Senior Editor

Stefan Baral, Senior Editorial Board Member

Letter to the Editor of the BMJ published June 2020
https://www.bmj.com/content/369/bmj.m1041/rr-1

(It should be noted that the corresponding author refused to reply after repeated requests by BMJ Editor Fiona Godlee)

For more:


Prof. Holly Ahern’s Lyme Disease Comments to Australian Senate

https://www.lymedisease.org/holly-ahern-australian-senate/

Prof. Holly Ahern’s Lyme disease comments to Australian Senate

2/5/25

The Australian Senate has launched an inquiry into the access to diagnosis and treatment for people in Australia with tick-borne diseases. Professor Holly Ahern of the United States recently submitted the following written comments and was also asked to give verbal remarks. (See video at end of this article.)

Dear Committee Members:

I am a scientist, professor of microbiology, and co-founder of a Lyme disease advocacy organization in New York State. I am also the Scientific Advisor for the Focus on Lyme Foundation in Arizona, which has funded research on several projects directed at improving the state of diagnostic testing for Lyme disease and other tick-borne illnesses.

I have served on several state and federal committees convened to address the growing problem of tick-borne diseases in the United States, most recently the 2022 Dept. of Health and Human Services, Tick Borne Disease Working Group (TBDWG).

But most of all, I am mother of a daughter who went from a record setting collegiate All American swimmer to bed bound and disabled over the course of only a few weeks. She lost years of her life as a result of flawed medical guidelines that prioritize care for patients early in the infection, while providing only minimal guidance for the diagnosis and care of patients in later stages of the disease.

In my daughter’s case, we saw the tick bite but she developed no rash. Fever, profound fatigue, widespread pain, and other symptoms began months later, and were attributed to a viral illness. The difficulties we faced in getting her illness diagnosed and appropriately treated in 2010 match those of hundreds of thousands of other people with Lyme disease in the United States and Europe, and also in Australia.

Biologically complex organism

Lyme disease is a bacterial infection caused by a microbe with global distribution. They are transmitted to humans by several species of tick. The bacteria are biologically complex. They adapt and survive in environments that would kill most other bacteria.

During human infection, some subgroups (genospecies) of these bacteria linger in the bloodstream, while others disseminate to connective tissue-rich areas of the body. Regardless, infection triggers profound immune system and other physiological events, leading to a wide range of symptoms that vary significantly among patients and can be quite severe.

The standard medical definition implies that the overwhelming majority of Lyme borreliosis (Lyme disease) patients are infected with the same bacteria and have the same uniform disease presentation, which is straightforward to diagnose and treat. As defined, Lyme disease is caused by only a few specific genospecies of Borrelia (now named Borreliella). Several other genospecies of Borrelia are associated with diseases collectively referred to as “Relapsing Fever borreliosis.”

Differences between the two diseases are subtle. Relapsing Fever Borrelia fail to produce the skin manifestation (erythema migrans or “bull’s-eye” rash) that is noted in Lyme disease; however, other symptoms are very similar. Existing diagnostic tests for Lyme disease don’t detect infections caused by Relapsing Fever Borrelia.

Thus, a patient may be bitten by a tick and infected with a Relapsing Fever Borrelia, such as B. miyamatoi, show all the symptoms that a patient with Lyme disease would have, but may not be diagnosed or treated for the infection because the EM rash did not appear and/or the standard lab tests for Lyme disease were negative.  (See link for article)

_____________

For more:

The Biosecurity Ethics & Immune Tolerance Awareness Initiative And the Yale Study MSM Journals Refused to Publish

https://immunetolerance.substack.com/p/the-biosecurity-ethics-and-immune?

The Biosecurity Ethics & Immune Tolerance Awareness Initiative

Welcome to the Substack to raise awareness of #ImmuneTolerance and #VaccineInjuries #chronicdisease #autism #mentalillness #ADD #ADHD

Welcome to the Substack of the Biosecurity Ethics and Immune Tolerance Awareness Initiative. The Biosecurity Ethics & Immune Tolerance Awareness Initiative exists to educating the public about the role of immune tolerance in chronic diseases, neurological and neuropsychiatric disorders, and cancers. We further educate and advocate for ethical biosecurity practices and informed policy decisions made in full transparency, through ethical guidelines, working to close critical vulnerabilities, and defend actual national security from foreign influence in public health and biodefense strategies, rather than using National Security as guise to hide scandals and evade accountability.

The Truth of Chronic Disease in America Shall be Unveiled. The Health of All Depends on it.

In 1960, the science of slow, chronic disease and persistent infections, once baptized “immune tolerance” was obscured and marginalized to the realm of organ transplantation and its recipients, as the 1960 Nobel Prize was given in error to Frances MacFarland Burnet and Peter Medawar for immune tolerance through organ transplantation even though the two never worked together nor were they nominated together by anyone. However, it was Erich Traub, who had discovered it in 1935 through his discovery of Lymphocytic Choriomeningitis Virus (LCM) in white mice.

Immune tolerance is a term applied to the state of chronic suppression of the immune system, where the immune system is too overwhelmed to adequately fight back. It is specifically defined as :

A state of unresponsiveness to a specific antigen or group of antigens to which a person is normally responsive. Immune tolerance is achieved under conditions that suppress the immune reaction and is not just the absence of an immune response.

This same condition correlated to another phenomenon alternatively coined “immune paralysis” following injection of large doses of pneumococcal polysaccharide antigens. In short, immune tolerance is immune paralysis. This was a major finding that would have vastly changed our understanding of chronic disease and immunology, yet the scientific establishment ignored it and marginalized it to organ transplantation, because the same condition is also seen in organ transplant recipients, and this is also thought to be the result of antigenic stimuli. Attributing it to organ transplantation only totally ignores something so immensely important about immunology and the disease process that it might as well be considered one of the pillars of chronic disease showing that unlike acute diseases measured by heavy inflammation and immune response, there is a polar opposite side of disease, measured by immunosuppression, lack of visible inflammation, and chronic disease.

However, the Nobel Prize “given in error” appears more likely to have been a deliberate choice as it would have devastated Western immunology and the science of infectious disease determined by antibodies and observable inflammation. Equally so, it would have flipped vaccine science on its head and exposed the true nature of vaccine-induced “immunity” as a slow destruction of the immune system rather than building it up as strong and healthy.

Erich Traub first elucidated the condition during vaccine research at the Rockefeller Institute in 1935 when he injected the brains of mice with foreign proteins, reactivating dormant LCM virus from within the mice, causing an epidemic from scratch. The result was a slow chronic disease via immunosuppression and persistent viral infection that could be passed congenitally from mother to newborn, maintaining itself through generations, while silently degenerating the genetic integrity of subsequent generations, plaguing them with chronic disease, neurological syndromes/wasting disease, and cancer.

In short, antigenic stimuli were behind this condition which produced chronic immunodeficiency and reactivated dormant viruses from within the body, invited additional opportunistic infections to create a highly complex and complicated chronic disease accompanied by neurological/neuropsychiatric disorders, wasting disease, and cancer. It would present in the absence of detectable antibodies and little to no outward inflammation. Likewise, Traub’s experiments demonstrate how a vaccine antigen too toxic for the body can cause new outbreaks with other diseases already dormant in the vaccine recipient.

Since the 1960s when the infectious origins of immune tolerance were buried and obscured, the science of chronic disease and neurological/neuropsychiatric disorders began working in reverse. Public Health has been ignoring the underlying condition at the root of these diseases for decades by using tests and diagnostics that evade the evidence of the condition by using the wrong biomarkers of disease and calling it “evidence-based medicine.” This so-called Evidence-based medicine only uses antibody response and inflammation as its criteria for diagnosis but immune tolerance is the polar opposite. There are ways to detect and diagnose immune tolerance using other biomarkers, but these are very different than biomarkers used to study acute diseases marked by robust antibody response and heavy inflammation. By using inadequate biomarkers like antibodies and acute inflammation as criteria for diagnosis, this will invariably show nothing of value for diagnosing a disease that is marked by immune tolerance outcomes and as a result, no disease will be recorded.   (See link for article)

_______________

**Comment**

Important quote:

Nowhere is this more apparent than the recent wave of sick people injured by the COVID-19 vaccine.

Mandatory reading for each and every Lyme/MSIDS patient and every person who still believes in ‘vaccines.’

This, right here, is the pearl that has been trampled on by public health and mainstream medicine.

Yale scientists have found T-cell exhaustion and prolonged spike protein production in some COVID shot recipients with spike levels increasing over time leading to post-vaccine brain fog and immune dysfunction. Finally, someone is connecting the dots between ‘long COVID’ and post vaccination syndrome.  Findings Suggest Immune Imbalances and Viral Reactivation May Contribute to Chronic Symptoms After COVID-19 Vaccination.

But mainstream medical journals won’t publish it.

The variety of symptoms include:

  • Excessive fatigue (85%)

  • Tingling/numbness (80%)

  • Exercise intolerance (80%)

  • Brain fog (77.5%)

  • Difficulty concentrating (72.5%)

  • Sleep disturbances (70%)

  • Neuropathy (70%)

  • Muscle aches (70%)

  • Anxiety (65%)

  • Tinnitus (60%)

  • Burning sensations (57.5%)​

Immunosuppression can be caused by vaccinations of all kinds as well as unethical biodefense practices using simulants in open-air tests since the 50’s.  Finnegan states:

Lyme disease had been one such simulant spread through ticks on shorebirds in the early 1950s under the supervision of Erich Traub on Plum Island, using strains of Borrelia anserina that he had acquired from Rockefeller-funded psychiatrist Franz Jahnel through his student Werner Schäfer in 1939.

Finnegan goes on with the sordid history of immune tolerance and how public health officials understand it fully and are deliberately using it as a defense strategy, while misleading the public.

Certain antigens responsible for immune tolerance are also potent mitogens which are responsible for cancer through the upregulation of telomerase.

MAHA will fail if the origins of immune tolerance via toxic antigen is not addressed.

http://” data-wplink-url-error=”true”>http://

“If we had surveyed the public two years ago, would you be willing to take a genome cell therapy and inject it into your body, we would have probably had a 95% refusal rate.” ~ Dr. Oelrich

Now injections will probably become a thing of the past as airborne mRNA ‘vaccines’ are being created that can be delivered straight into the lungs without a shot.