
|
|||||
|
Webinar: Uncommon Lyme Questions Answered
June 17, 2022
Gov. Justice: Doctors confirm Lyme disease diagnosis
6/1/2022
|
FDA Recommends COVID Shots For Babies & What VRBPAC Got Wrong: Who Will Hold FDA & VRBPAC Accountable for Failing America?
June 16, 2022
The FDA vaccine advisory panel unanimously voted 21-0 to recommend Pfizer and Moderna’s COVID-19 vaccines for infants and young children, stating the totality of the evidence available shows the benefits of the vaccines outweigh the risks of use. It helps when you get hundreds of thousands of dollars from Pfizer like committee member Arnold Monto.
The Vaccines and Related Biological Products Advisory Committee (VRBPAC) ignored pleas from experts, the vaccine injured and a congressman representing 17 other lawmakers to halt authorization until questions about the safety and efficacy of COVID-19 vaccines for the nation’s youngest children could be properly addressed.
A top official at Moderna has already said a booster will be necessary.
Fauci even admits there are ZERO studies in children showing boosters reduce hospitalization or death. Senator Rand Paul, a medical doctor, explains that the only studies show people produce antibodies after the injections, but that many researchers question whether this shows efficacy or not.
Paul also pushed for information on how the NIH has continuously refused to release information on their royalties. “The NIH continues to refuse to voluntarily divulge the names of scientists who receive royalties and from which companies. Over the period of time from 2010 to 2016, 27,000 royalty payments were paid to 1800 NIH employees. We know that not because you told us but because we forced you to tell us through the Freedom of Information Act. Over $193 million was given to these 1800 employees. Can you tell me that you have not received a royalty from any entity that you ever oversaw the distribution of money in research grants?”
States have already ordered millions of doses made available prior to FDA authorization by the Biden administration and depending upon whether the FDA and CDC accept the recommendations of their advisory panels, the administration of vaccines for these age groups could start as early as June 21.
BTW: fully “vaxxed” and double boosted Dr. Anthony Fauci got COVID anyway, similarly to millions of others – continuing to show the futility of the injections. Please see this important article on how the CDC is withholding data and skewing “vaccine” effectiveness to prevent “vaccine” hesitancy and how you can not trust any numbers or data from this corrupt organization.
This important video on the Dr. Jane Ruby show, interviews Canadian Physician and molecular biologist, Dr. Daniel Nagase, who clearly explains how the bioweapon shots from ALL of the companies are poisoning human DNA for generations.
And go here for the latest VAERS data showing these shots are connected to more adverse reactions & deaths than any other vaccine in the history of VAERS.
https://popularrationalism.substack.com/p/what-vrbpac-got-wrong-who-will-hold?
What VRBPAC Got Wrong: Who Will Hold FDA and VRBPAC Accountable for Failing America?
VRBPAC Members Saw All the Same Information You Will See Here, But Voted Unanimously Anyway to Recommend Approval of a Worse Then Futile Vaccine for Toddlers and Babies
Here’s a few things VRBPAC members saw and voted to recommend approval anyway:
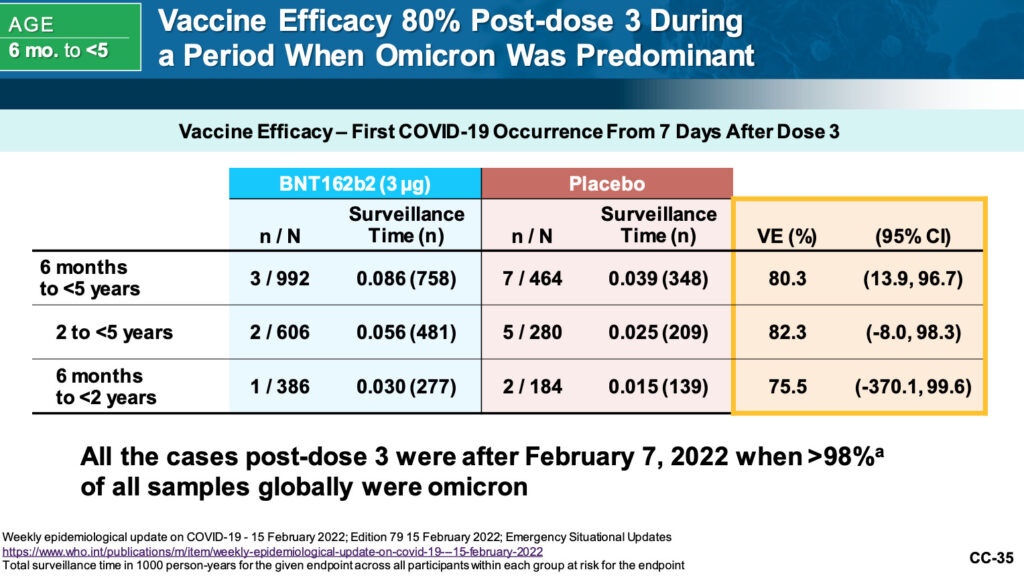
- They Proceeded for Recommendation of Approval Based on a Guess that Three Doses Will Correct Negative Efficacy.Pfizer has a serious problem: their two dose data reflected the reality I’ve been reporting about (and predicted) since the Israeli and Barnstable County data came out: the confidence interval for their estimate of the number cases prevented by three doses of their vaccine points, if anything, to negative efficacy (-369.1 to 99.6). The confidence interval crosses zero. The problem is not just that the result is based on a ridiculously small number of data points. See Point 2.
- The problem also is that this result confirms (validates) the result of the two-dose vaccine. Their measure of vaccine efficacy was only 14.5% seven days after the second dose the confidence intervals crossed zero, so they were not statistically significant.
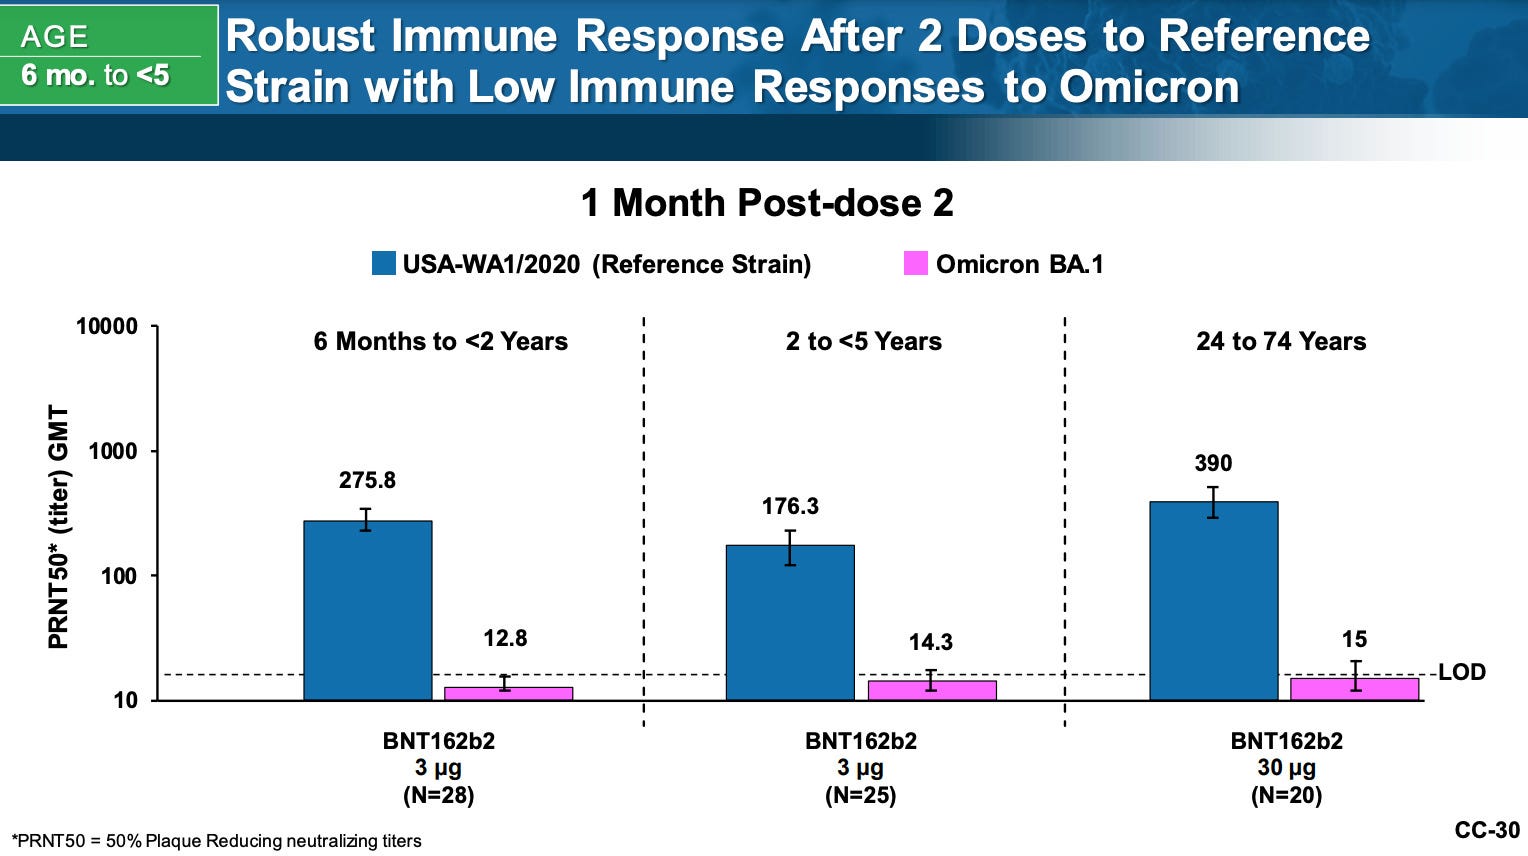
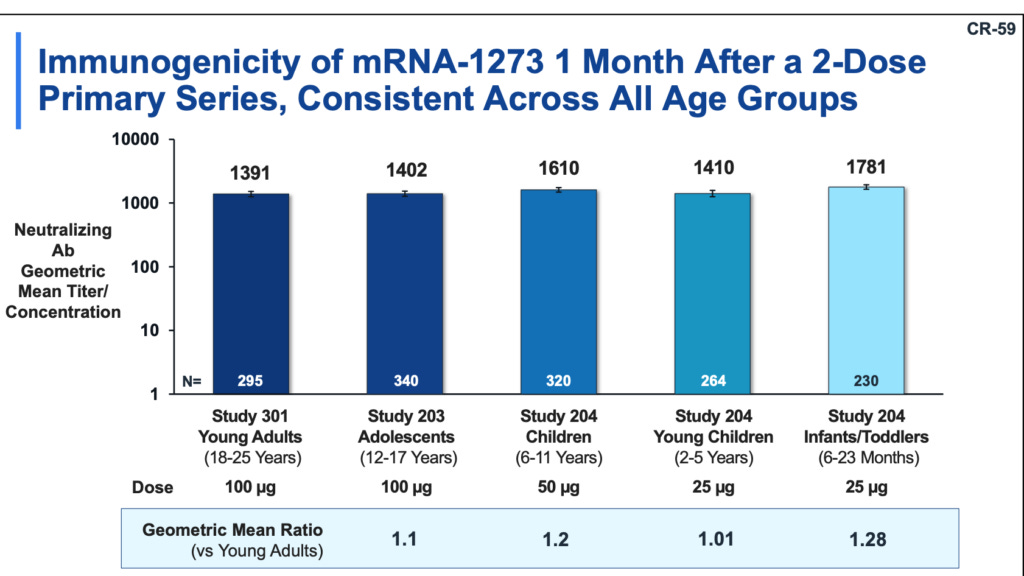
- They relied on proxy outcome measures (neutralizing antibodies). Neutralizing antibodies sound good, but they are the wrong antibodies (the Wuhan-1 virus is extinct). Look at the antibody response to Omicron (Pfizer):

I predict the entire vaccination program is going to drive COVID-19 numbers up across the board routinely and on a regular, ongoing basis due to antibody dependent enhancement, as predict by Dr. Fantini’s analysis.
- Given these three points alone, FDA might just as well be staring at a blank sheet of paper and rubberstamp the approval.Look at the confidence interest after Dose 2 and Dose 3.
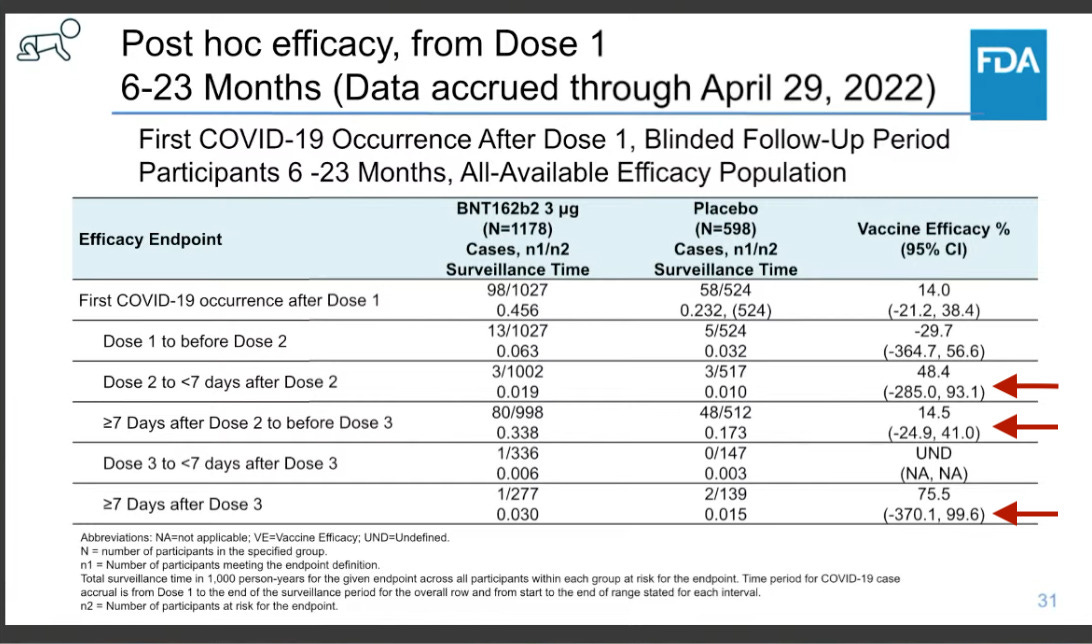
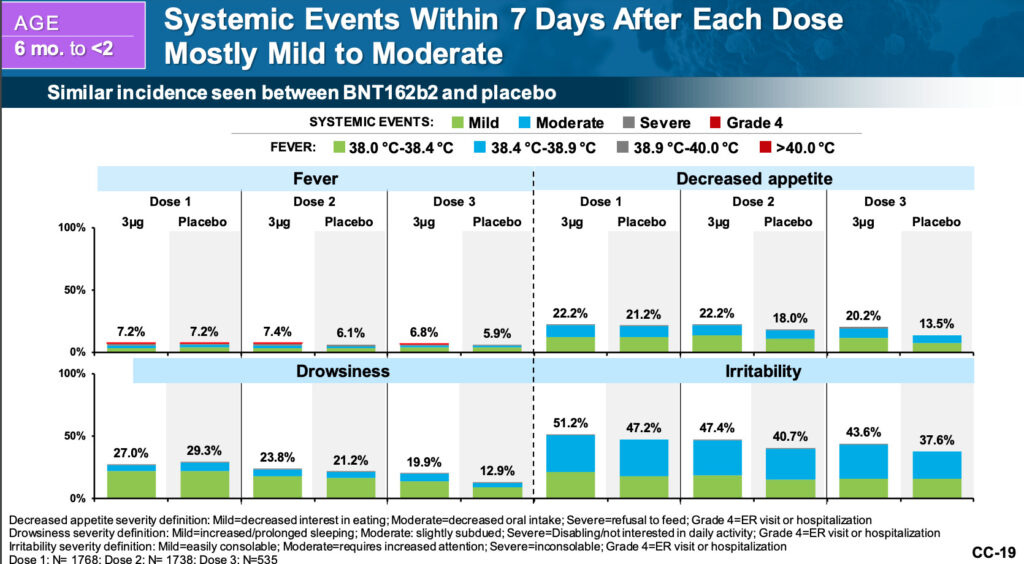
- No one raised the issue of Failure to Meet FDA’s required 50% efficacy. Moderna and Pfizer’s own endpoint data fall short of the 50% mark. Pfizer decreased their dose and this seems to have decreased the reported adverse events. But we’ll get to the real problem with adverse events shortly.
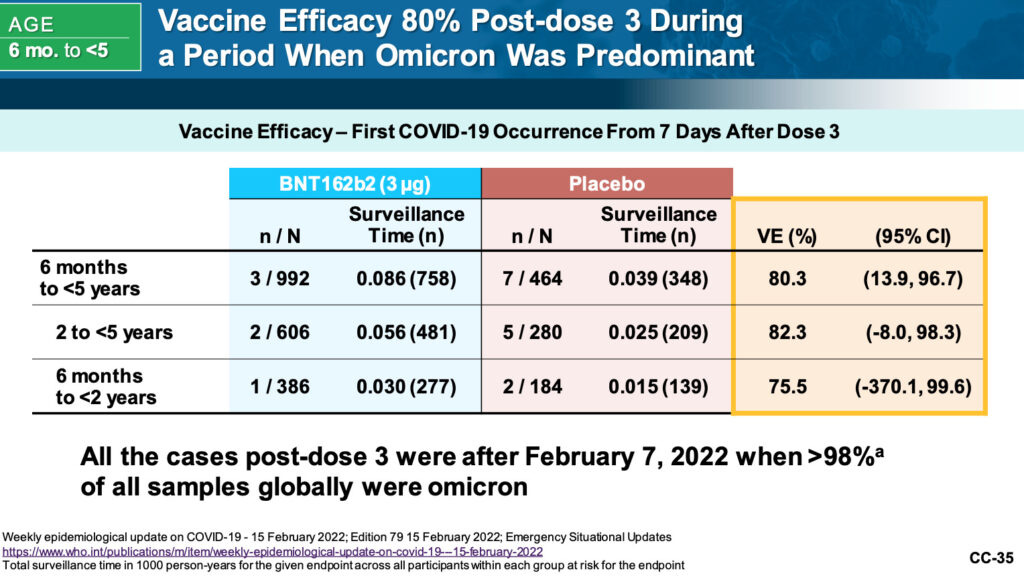
- Their numbers are ridiculously small. Pfizer showed an estimate of of 80.3% vaccine efficacy is based on – get this – 7 cases in the placebo group and 3 in the vaccine group. Notice the emblazoned 80% – as if that data point has any basis in reality.
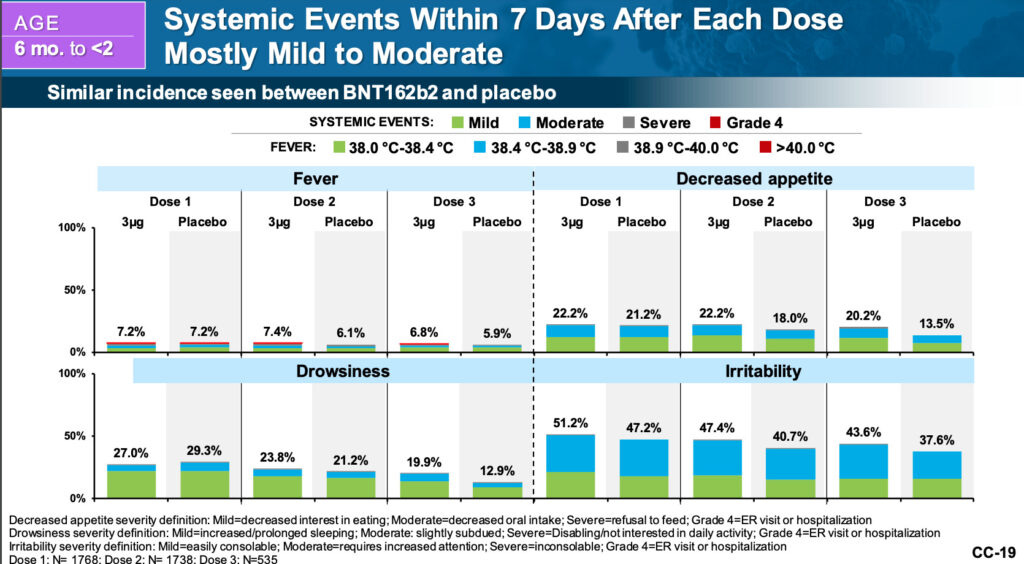
- They are ignoring the risk of altered neurodevelopment. The Moderna vaccine especially had high numbers of high fevers (>104°). Many studies exist that show that high fever following vaccination is associated with autism, especially if the kids are given acetominophen. Please see: https://popularrationalism.substack.com/p/three-years-later-after-ipak-alerted
- Moderna presented antibody data against the reference strain (Wuhan-1). But We don’t only care about how good a vaccine is at generating antibodies. Moderna knows this. VRBPAC knows this. Now you know this, too.

9. Inconsistent case definition. Moderna only ran PCR tests if patients in the vaccinated group had two symptoms. In other words, they made up their own clinical designation of “COVID-19”. Under CDC’s case definition (which is also not correct), Moderna’s data show that in kids 2 to 5, “vaccine efficacy” was 36.8% but under Moderna’s new definition, 46.4%. Moderna also used antigen tests, making any measure of efficacy incomparable to other studies.
10. Risk of Hospitalization Cited Out of Context.
One committee member compared the risk of a child dying from Covid to a person being struck by lighting (see my calculations here):
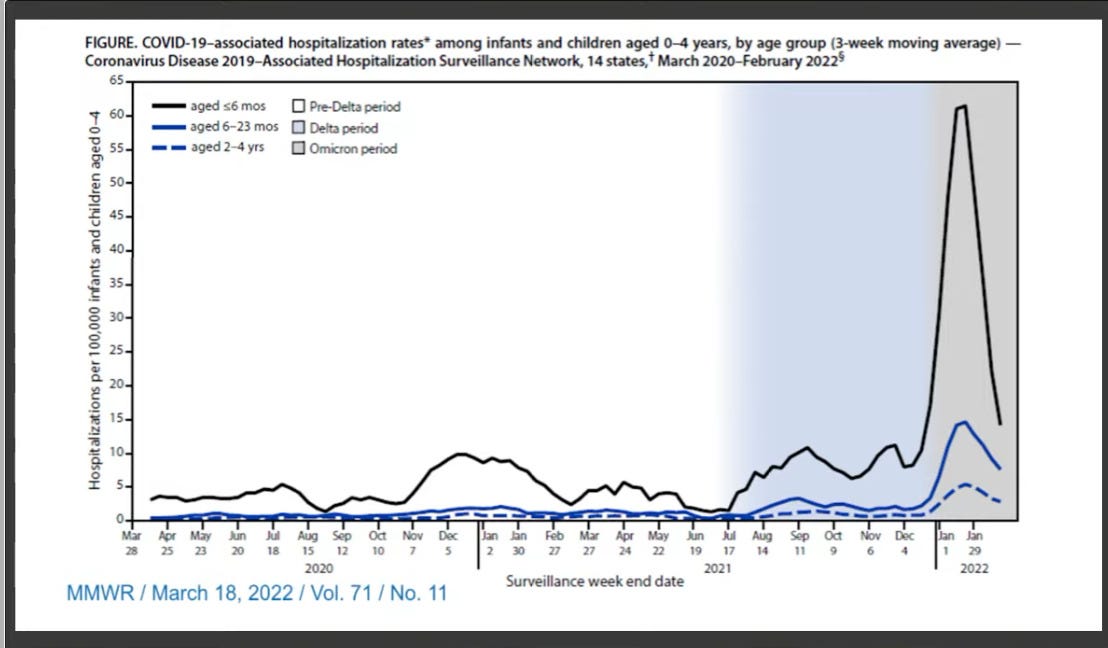
They showed the Omicron hospitalization rate “surge”:
Yet it’s much lower than that for influenza, per CDC:
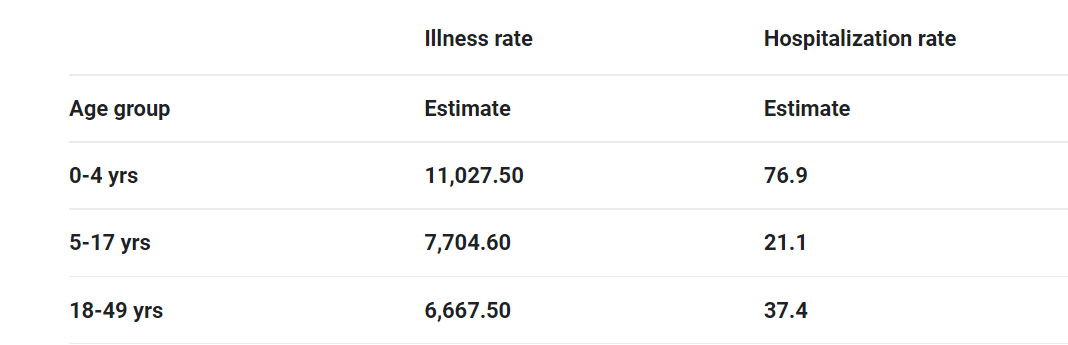
2015-2016 Hospitalization Rate (Per 100,000 cases) from Influenza (Source: CDC)
11. They May Have Broken the Rules of Engagement for Open Meetings
Any reasonable person would expect that public open meetings held by organizations such as VRBPAC would know and follow administrative rules for open meetings. How is it then that VPBPAC members only managed to ask questions and voice their opinions on how necessary (or not) COVID-19 vaccination in children might be AFTER the votes were made to approve the vaccine for children under 5?
Dr. Meryl Nass was denied an opportunity to speak in the public comment period, yet the same pro-vaccine mother was able to speak two days in a row. Thus, the public may have been denied the opportunity to contribute their comments. This is being looked at by lawyers; if it true the FDA broke the rules of open meetings, then any ethical judge would rule that this vote to recommend is null and void ab initio.
https://standforhealthfreedom.com/interview/who-updates/
Did we win against the WHO?
WHO treaty and IHR update after WHA 75
In the last few weeks, health advocates in the U.S. have seen massive wins in our stand against the rapid and coercive development of a global health governance. Thanks to your efforts to sound the alarm, the U.S. Congress has come alive with new bills, new sponsors on existing bills, and letters from the House and the Senate reminding the president that the Constitution is the supreme law of the land and no international agreement will push that aside.
So where are we now with the global health agenda? Read on for updates to the U.S. involvement with the World Health Organization so you can keep the momentum going!
What happened with the proposed US IHR amendments?
In January 2022, the United States, along with approximately 40 other countries, proposed amendments to 13 articles of the existing WHO International Health Regulations.[i] At WHA 75 in Geneva from May 22 through 28, 2022,[ii] the Assembly adopted a resolution to substantially amend one article of the International Health Regulations regarding timelines for amendments to the IHR, along with “necessary” changes to four additional articles to reinforce those major changes. Member States of the World Health Organization will have the opportunity to reject or accept the amendments with reservations (explained below). The other 12 amendments proposed by the U.S. are not off the table — these will now be addressed by the new Working Group on IHR Amendments which will report to the World Health Assembly in 2024, the same year the pandemic treaty is planned to be voted on.
The final version of the amendment was negotiated in “informal discussions” outside of the WHA meetings. U.S. Deputy Secretary Colin McIff of the HHS Office of Global Affairs explained on the record that, “Member States decided to commence a Member-State led process to consider proposed amendments2 to the International Health Regulations (2005) beyond those adopted below.” [iii] That footnote you see mid-sentence is in a WHA document and refers to the 12 proposed amendments rumored to be withdrawn. It refers to “Including the other proposed amendments set out in the annex of Document A75/18, as well as other amendments which have or may be submitted by other IHR (2005) States Parties or the Director-General, including through the above-mentioned Member State-led process.” (emphasis added) Document A75/18 includes the amendments as submitted by the U.S. to the WHO. So not only are all of the U.S. amendments still proposed for consideration, more amendments from other Member States are invited as well.
Details on the adopted amendment
The amendment adopted at the WHA to Article 59: Entry into force; period for rejection or reservations, regarding the timeline for new amendments to the IHR to be adopted and become legally binding on Member States was the one never thought to be withdrawn.
The U.S. wanted to reduce the timeline for adoption of new amendments from a 2-year process to a 6-month process. Right now, after notification of an adopted amendment, countries have 18 months to reject or make reservations, and an additional 6 months before those amendments go into force. The proposal adopted by WHA 75 decreases that timeline to 10 months instead of 18 months to reject or reserve, and two additional months for effect, shortening the entire timeline by a year.
Amendment to Section 59 adopted by the Assembly,[iv] along with additional language changes to Articles 55, 61, 62, 63, having to do with the amendment process, rejections and reservations, and the timeline for amendments to go into force was proposed to reinforce the changes proposed to Article 59. These additional articles were not in the original U.S. proposal but were deemed necessary after informal negotiations.[v]
Throughout the Assembly, countries voiced opposition to, or concern with, changes to WHO authority and reach by way of amending the IHR and creating a new pandemic treaty. Notably, Brazil President Jair Bolsanaro stated Brazil would have no part of a pandemic treaty[vi] (and has been on record since 2020 considering leaving the WHO entirely[vii]). Other countries expressing concern included Botswana, Iran, Bangladesh, Namibia, India, Brunei, the Russian Federation,[viii] and several African states.[ix]
What to watch for now?
Health Advocates can keep an eye on the WHO process through 2024, but pay attention to what is happening in the WHO’s backyard which will eventually come knocking.
WHA created two new WHO groups to work on IHR changes.
The Assembly agreed to the creation of two new groups in the WHO to work on updating the IHR. The Working Group on IHR Regulations (WGIHR) will meet over the next two years to collect, discuss, and propose “targeted” amendments to the IHR at the 77th World Health Assembly in 2024.[x] The WGIHR will be helped by a new IHR Review Committee to focus on “technical recommendations” (changes that are not considered substantial enough to be amendments but bring the IHR in line with amendments and goals for strengthening the WHO).
The WGIHR must coordinate with the Intergovernmental Negotiating Body (INB), “as both the International Health Regulations (2005) and the new instrument are expected to play central roles in pandemic prevention, preparedness, and response in the future.”[xi]
Timeline as of June 1, 2022 (all subject to change)
- TBD – Official notice from the WHO Director-General of adoption of resolution to amend Articles 59, 55, 61, 62 and 63 of the IHR, which starts the clock ticking for reservations or rejections
- TBD — Member States must reject or take reservation. By law, States should have 18 months, per the existing and legally binding regulations in force now. Some wonder, however, if the DG will impose the newly adopted timeline even though it is not yet in force. (In other words, the U.S. will have 10 to 18 months to respond to the amendments.)
- June 16-17 — Second meeting of INB to inform drafting of pandemic treaty[xii]
- August 2022 — First draft of pandemic treaty expected
- September 30, 2022 — Deadline for proposed amendments to IHR
- October 1, 2022 — Deadline for creation of IHR Review Committee for technical recommendations to proposed amendments and to inform the work of the WGIHR
- November 15, 2022 — Deadline for first meeting of WGIHR
- January 15, 2023 — Requested deadline for IHR Review Committee to submit a report to the DG, who will transfer it to the WGIHR immediately
- May 2023 — World Health Assembly 76
- May 2024 — World Health Assembly 77 to consider targeted amendments to IHR as well as pandemic treaty.
The IHR and treaty are not the only way to move a global health agenda forward.
Outside of these documents, meetings, and negotiations, there are other agreements strategically being put into place. The World Bank is setting up accounts for a new global health security fund for pandemic preparedness, which already has over $3.2 billion pledged by countries around the globe.[xiii] The WHO opened a new global hub for pandemic and epidemic intelligence in Germany for “data, surveillance, and analytics innovation…the largest network of global data to predict, prevent, detect, prepare for, and respond to pandemic and epidemic risks worldwide.”[xiv] The WHO also has ongoing research, pilot programs, and guidance regarding digital documentation of COVID-19 tests and vaccination certificates.[xv] Switzerland is home to the new WHO BioHub where countries can rapidly share novel biological materials and pathogens.[xvi] Negotiations to share intellectual property (patent rights) for pandemic medical products have been ongoing at the World Trade Organization.[xvii] Right now all of these agreements and negotiations are voluntary, but all of these issues are expected to be addressed and become legally binding through the pandemic treaty.
In America there are state and federal laws, bills, and regulations either aligning with or rejecting the WHO. Stand for Health Freedom already reported on the 2017 CDC quarantine regulation updates that included the WHO definition of public health emergency.[xviii] State legislatures started seeing bills referencing WHO definitions as well, including the Mental Health Parity Act that did not pass the Georgia House this past session.[xix] The Biden administration created an Office of Climate Change and Health Equity in 2021, [xx] and added to it an Office of Environmental Justice, within the Health and Human Services agency. [xxi] This new creation is in line with the “One Health” approach of the WHO for the new pandemic treaty, which includes humans, animals, and the environment together in public health.
Here’s the great news.
Americans have seen lawmakers wake up and start opposing WHO takeover of U.S. public health decisions.
Since the launch of the SHF action to support HR 419, No Taxpayer Funding for the WHO Act, there have been 39 new cosponsors! Two senators[xxii] as well as House members of the Freedom Caucus[xxiii] sent letters to the White House insisting the U.S. reform their relationship with the WHO or pull out altogether. Some representatives have been making public statements against WHO involvement, like Mary Miller from Illinois.[xxiv] Candidates for governor are speaking out against WHO overreach after witnessing two years of federal overreach and promising to stand strong to protect the health of their constituents.[xxv] State legislators, like in Louisiana, are voicing opposition as well![xxvi]
Additionally, in just one week three new bills were introduced in Congress to protect U.S. sovereignty in public health matters. Senator Rick Scott of Florida introduced S4305 on May 25, a bill to limit the authority of the WHO on the U.S. and oppose amendments not approved by Congress.[xxvii] Senator Ron Johnson announced his introduction of a bill, “No WHO Pandemic Preparedness Treaty Without Senate Approval Act.”[xxviii] And Representatives Rogers and Massie introduced HR 7806, the American Sovereignty Restoration Act,” which expands congressional oversight beyond the WHO to its parent organization the United Nations.[xxix]
Because of your voice, our lawmakers are taking action, and quickly!
Steps You Can Take Now:
You are making a difference! Our lawmakers are hearing your message about protecting our rights and our Constitution when it comes to health. Let’s keep the momentum going!
Step 1: Tell your lawmakers about the WHO’s plans for global health governance. Your representatives can support HR 419, and your senators can make sure they are doing their constitutional duty to advise and approve of any international treaties. Our campaign makes it easy to get in touch with email and phone scripts that you can use or adapt to send a message.
Step 2: We can stop medical tyranny by voting people into office who will stand for health freedom! To have good candidates on the ballot in November, we must vote now in the primaries. Check out where your candidates stand using our Vote for Health Freedom Guide for your state! Go to our Vote for Health Freedom page, or Text the letters VHF to 52886, to learn about candidates in your area!
Step 3: Please support our work in bringing this information to light. Every penny counts toward exposing the global health agenda and educating our lawmakers into action!
References & Sources
___________________
**Comment**
According to an article written last year, the U.S. is on course to become a ‘digital dictatorship’ under a proposed biomedical research agency. This agency would merge national security with public health, a perfect formula for a dangerous agenda that would destroy medical freedom as we know it.
This agency would “use both physical and mental health ‘warning signs’ to prevent outbreaks of disease or violence before they occur. Such a system is a recipe for a technocratic ‘pre-crime’ organization with the potential to criminalize both mental and physical illness as well as ‘wrongthink.’”
This article proves the political interference at HHS as well as the fact governments are working in lockstep to bring in digital I.D.s & a social credit system.
The CDC already rules both research and the medical profession with an iron fist and medical freedom is increasingly under fire.
All of this sounds like a perfect prelude to global “vaccine” passports.
For more:
- https://madisonarealymesupportgroup.com/2022/05/26/who-withdraws-12-of-bidens-sovereignty-amendments-to-ihr-may-revisit-them-later/
- https://madisonarealymesupportgroup.com/2022/05/10/the-global-pandemic-treaty-what-you-need-to-know/
- https://madisonarealymesupportgroup.com/2022/05/12/who-global-predators-plot-global-health-tyranny/
- https://madisonarealymesupportgroup.com/2022/04/04/the-chilling-reason-they-wont-declare-the-pandemic-over-creation-of-the-pandemic-treaty/
- https://madisonarealymesupportgroup.com/2020/09/30/proof-that-the-pandemic-was-planned-with-purpose/
- https://madisonarealymesupportgroup.com/2022/04/26/the-who-is-an-absolutely-corrupt-organization-that-needs-to-go-away/
- https://madisonarealymesupportgroup.com/2022/04/15/who-pandemic-treaty-supersedes-constitution/
- https://madisonarealymesupportgroup.com/2022/05/09/5-minutes-of-wef-truth-mass-surveillance/
https://www.localsyr.com/living-with-lyme/living-with-lyme-tiny-terror/ News Video Here (Approx. 24 Min)
Tiny Terror: The Truth About Ticks
SYRACUSE, N.Y. (WSYR-TV) Ticks are in our yards and they’re saturating Central New York. One bite can change everything. Most people do not know Central New York is an epicenter for tick-borne disease. Most recent data indicates a 439% increase in Central New York between 2008 and 2018.
What are some of the symptoms of Lyme disease?
- Brain fog
- Headaches
- Joint Pain
- Extreme Fatigue
Doctors and scientists struggle to agree on how to get this under control.
(See link for video and story)
___________________
SUMMARY:
- The reason Lyme/MSIDS patients are not treated appropriately is due to the faulty, unscientific, and fraudulent CDC Lyme guidelines which serve as an Iron Curtain in the medical community.
- It is imperative to get to a Lyme literate (LLMD) doctor trained by ILADS, a group of medical professionals who recognize the faulty, unreliable testing and ineffective CDC guidelines.
- The quote from a doctor in the news story that taking a single or double dose of doxycycline reducing the risk of transmission has been completely and utterly debunked.
- Based on animal studies, ILADS recommends that known blacklegged tick bites be treated with 20 days of doxycycline (barring any contraindications).
- Given the low success rates in trials treating EM rashes for 20 or fewer days, ILADS recommends that patients receive 4-6 weeks of doxycycline, amoxicillin or cefuroxime. A minimum of 21 days of azithromycin is also acceptable, especially in Europe. All patients should be reassessed at the end of their initial therapy and, when necessary, antibiotic therapy should be extended.
- ILADS recommends that patients with persistent symptoms and signs of Lyme disease be evaluated for other potential causes before instituting additional antibiotic therapy.
- ILADS recommends antibiotic retreatment when a chronic Lyme infection is judged to be a possible cause of the ongoing manifestations and the patient has an impaired quality of life.
- Lyme survivor Brenna Osmun, who lost her ability to walk, is interviewed on the report. Two months of IV antibiotics saved her life. She suffered years of relapses until she saw a LLMD, a specialist rarely covered by insurance. She also had Babesia and Bartonella and was treated with more than a dozen herbs and antibiotics. She says this to patients:
“It gets better. It really, really does. And my life changed for the better I wanna say. Even though I was really sick, it does get better. And having that support really helps you. Don’t give up. Please don’t give up. I didn’t and I’m still alive.” ~ Brenna Osmu
- Executive Director of the Central New York Lyme and Tick-Borne Disease Alliance, Royale Scuderi became infected years ago when doctors treating this were scarce. She had to drive to Long Island for year to get appropriately treated.
- Journalist and host of the news program, Nicole Sommavilla became septic with her organs shutting down. Years later she was diagnosed with Lyme disease and required a dozen drugs to treat Lyme, Babesia, and Anaplasmosis
“I went from years of oral medications and injections to just one medication I’m on now and just a lot of maintenance with diet and knowing when not to push myself past my limit, it’s a lot of self-awareness.” ~ Nicole Sommavilla
A MESSAGE FROM NICOLE:
If you’re fighting Lyme right now, please don’t give up.
Don’t quit in the darkness. Most days it may feel easier to give in, but hang on. Lean into your support system and keep fighting. Because joy and healing are coming. ~ Nicola Sommavilla
For more:
- https://madisonarealymesupportgroup.com/2019/04/16/ny-tv-reporter-tells-her-own-lyme-disease-story/ Nicole Sommavilla’s story here
- https://madisonarealymesupportgroup.com/2016/07/01/lyme-story-on-fox-5-ny/
- https://madisonarealymesupportgroup.com/2022/03/11/doctors-debate-patients-suffer-the-fight-over-chronic-lyme-disease-in-wisconsin/
- https://madisonarealymesupportgroup.com/2022/03/25/the-old-political-does-borrelia-persist-debate/
- https://madisonarealymesupportgroup.com/2022/06/13/wisconsins-chronic-lyme-patients-embrace-alternative-treatments-rack-up-big-bills/
- https://madisonarealymesupportgroup.com/2022/06/15/sacramento-mom-shares-struggle-with-lyme-disease/
- https://madisonarealymesupportgroup.com/2022/05/19/mum-who-thought-she-had-dementia-for-29-years-discovers-she-has-lyme-disease/

