Archive for the ‘Ticks’ Category

New Book on Human Experimentation & Biological & Chemical Weapons

https://www.activistpost.com/2021/09/u-s-indifferent-to-human-experimentation-and-biological-and-chemical-weapons-new-book-points-to-a-monstrous-agenda

U.S. Indifferent to Human Experimentation and Biological and Chemical Weapons — New Book Points to a Monstrous Agenda

Excerpts from article:

At the Breaking Point of History: How Decades of U.S. Duplicity Enabled the Pandemic by Activist Post contributor Janet Phelan details the US government’s indifference to the welfare of individuals and to its legal obligations under national and international accords prohibiting human experimentation and biological and chemical weapons. (The book is available at TrineDay and elsewhere.)

Ms. Phelan recently said,

“We are embroiled in a pandemic which has collapsed economies, caused death by starvation, and has resulted in severe new restrictions on civil rights in the US and elsewhere. Yet many medical professionals and researchers are questioning the genesis of Covid-19. Was it bioengineered? Was it deliberately released? They’re also questioning the numbers alleged to have died from it, pointing to dictates from the CDC to list deaths not directly caused by the virus as virus-caused deaths.”

Janet Phelan is an investigative reporter. Her articles have appeared in the Los Angeles Times, the San Bernardino County Sentinel, Orange Coast Magazine, New Eastern Outlook, and elsewhere. She currently writes for Activist Post and has previously published an intelligence expose, Exile, and two books of poetry.

TrineDay is a small publishing house that arose as a response to the consistent refusal of the corporate press to publish many interesting, well-researched and well-written books with but one key “defect”: a challenge to official history that would tend to rock the boat of America’s corporate “culture.” TrineDay believes in our Constitution and our common right of Free Speech.

_____________________

**Comment**

Hopefully Lyme/MSIDS patients are aware of the sordid backstory of tick-borne illness. This backstory that reads like a rap sheet is actually quite similar to the COVID debacle we find ourselves living through, with many of the same bioweaponization aspects, key players, and institutions that have severe conflicts of interest and have no business determining public health policy.

A year ago the House passed a measure to probe into our government’s tick experimentation, and bioweaponry.

It is known from previous interviews that researchers dumped infected ticks from airplanes.  Investigative journalist Kris Newby reported in her book, “Bitten,” that Willy Burgdorfer, the “discoverer” of Borrelia burgdorferi – the causative agent of Lyme disease, worked at the Rocky Mountain Lab in Montana, and for 13 years he was the military’s go-to expert for mass-producing disease agents inside ticks.  According to the book, A CIA/military project code named “Operation Mongoose” involved giving false identifies to agents in order to protect the U.S. government. They wore uniforms of a sham airline run by the CIA and dumped boxes of infected ticks out of the airplane. One agent’s son came down with a mysterious illness that caused brain inflammation that could have caused permanent brain damage if a resident with previous work in tropical medicine hadn’t recognized it and knew how to treat it.  When the agent asked the commander if there was a connection between his work and his son’s illness, the commander told him to burn all the clothing he took to Cuba.  “Burn everything.”

It is far more likely that the tick and disease proliferation we are seeing today is due to our own government’s work and the massive amount of infected ticks being dropped from airplanes, than the scapegoated reason of “climate change.”  These ticks were force-fed numerous pathogens – sometimes numerous ones simultaneously.  Burgdorfer also sent ticks to others for bioweaponry projects – one of which was to a researcher doing studies on radiation-induced mutations of various ticks and microbes.

We need look no further than our own government’s nefarious research to understand the mess we are in today.

With Three Invasive Tick Species Thriving in Connecticut, State Scientist Warns of Major Public Health Hazard

https://www.courant.com/news/connecticut/hc-news-ct-more-ticks-20210816-eafwrhehkbhspacc7r5qrw4m4m-story.html

With three invasive tick species thriving in Connecticut, state scientist warns of major public health hazard

Stratford, Ct. - 08/13/2021 - Dr. Goudarz Molaei, with Connecticut's Agricultural Experiment Station, searches for ticks trapped on a canvas dragged through shoreline vegetation. Photograph by Mark Mirko | mmirko@courant.com
Stratford, Ct. – 08/13/2021 – Dr. Goudarz Molaei, with Connecticut’s Agricultural Experiment Station, searches for ticks trapped on a canvas dragged through shoreline vegetation. Photograph by Mark Mirko | mmirko@courant.com (Mark Mirko/The Hartford Courant)

State scientist Goudarz Molaei pulled a square of cloth through brush and grass on the Stratford coast recently, then stopped and pointed to a crawling smear of larvae on the white fabric.

The tiny arachnids were either Gulf Coast or lone star ticks, two of three invasive species, along with the Asian long-horned tick, that have recently established footholds in Connecticut.

First seen only in pockets near the coast, the blood-sucking, disease-carrying ticks have spread into other parts of the state. Compared with past years, many more worried residents and visitors have submitted ticks to the Connecticut Agricultural Experiment Station, mostly deer ticks that may carry Lyme disease, Molaei said. The tally so far in 2021 is 4,700 tick submissions to the testing laboratory, compared with a total annual average of 3,000 submissions.

Milder winters and warmer temperatures overall are helping the ticks survive and thrive in Connecticut.

“This is going to be a major public health concern in the near future, if it is not already,” Molaei said.  (See link for article)

_____________________

**Comment**

Important takeaways:

  • Previously only .2% of submitted ticks were lone star ticks which increased to 4.2% this year. They transmit ehrlichiosis, STARI, spotted fever rickettsiosis, tularemia, Alpha-gal allergy, and Heartland and Bourbon Viruses.
  • The researcher states that it’s a matter of time before the entire state of Connecticut will be infested with Asian long-horned tick – the tick that can reproduce by cloning. It is supposedly less attracted to human skin but can spread diseases that make both animals and humans seriously ill.
  • The Gulf Coast tick overwintered successfully in Connecticut but currently is limited to coastal areas.  Thirty percent tested there were infected with rickettsiosis, which is similar to but less serious than Rocky Mountain Spotted Fever.
  • The deer tick, or blacklegged tick transmits Lyme disease and is active any time temperatures are above freezing.  All life stages bite humans.
  • The following percentages of ticks were sent to the Experiment Station this year:
    • 72.8% deer ticks (32% were positive for Lyme, 10% for Babesia, 4% for Anaplasmosis – and 2% tested positive for at least 2 disease agents concurrently)
    • 23.1% American dog ticks
    • the rest were lone star ticks

Asian Longhorned Tick Confirmed in Missouri

https://agriculture.mo.gov/news/newsitem/uuid/2510b251-b71d-4107-8d0b-45455a8d9834/asian-longhorned-tick-confirmed-in-missouri

July 27, 2021

Asian Longhorned Tick Confirmed in Missouri

JEFFERSON CITY —The Missouri Department of Agriculture, working in conjunction with the Missouri Department of Health and Senior Services and Missouri State University, has confirmed the first finding of an Asian longhorned tick (Haemaphysalis longicornis) in Missouri. Missouri becomes the 16th state with a presence of the tick species, following the first confirmed report of the Asian longhorned tick in the United States in 2017.

Asian longhorned ticks are light brown in color and are very small, often smaller than a sesame seed. Unlike other ticks, a single female Asian longhorned tick can produce offspring (as many as 1,000 at a time) without mating. That means individual animals could host thousands of ticks, which can cause great stress on a heavily infested animal.

The Department encourages producers to continue protective measures and to check their livestock regularly for ticks. Keeping grass and weeds trimmed and clearing away brush are important tick prevention practices. If you spot any unusual looking ticks or large infestations on your animals, contact your local veterinarian.

According to the Center for Disease Control, the Asian longhorned tick appears to be less attracted to human skin. However, ticks of any kind should be removed immediately, as they can carry diseases that affect human health. Use EPA-approved insect repellent when you will be in or near tall grasses or wooded areas.

Research on the presence of tick species in Missouri continues through a partnership between the Missouri Department of Conservation and A.T. Still University. Residents are asked to send ticks to the University through September 2022 so that University researchers can study the distribution of ticks in Missouri and any human pathogens transmitted by those ticks. For more information, or to find out how to submit a sample, visit Missouri ticks and tick-borne pathogen surveillance (atsu.edu).

To learn more about the Missouri Department of Agriculture, please visit Agriculture.Mo.Gov.

__________________

**Comment**

It spreads SFTS (sever fever with thrombocytopenia syndrome), “an emerging hemorrhagic fever,” causing fever, fatigue, headache, nausea, muscle pain, diarrhea, vomiting, abdominal pain, disease of the lymph nodes, and conjunctival congestion, but the potential impact of this tick on tickborne illness is not yet known. In other parts of the world, this Longhorned tick, also called the East Asian or bush tick, has been associated with several tickborne diseases, such as spotted fever rickettsioses, Anaplasma, Ehrlichia, and Borrelia, the causative agent of Lyme Disease.

For a 2016 literature review on SFTS:http://infectious-diseases-and-treatment.imedpub.com/research-advances-on-epidemiology-of-severefever-with-thrombocytopenia-syndrome-asystematic-review-of-the-literature.php?aid=17986
Although the clinical symptoms of SFTS and HGA are similar to each other, but the treatment methods of the two diseases are totally different. Doctors notice that the biggest difference between the clinical symptom of SFTS and HGA is that SFTS patients generally without skin rash, the dermorrhagia is also not seriously, and few massive hemorrhage cases were reported [23]. It is also reported that SFTS patients had gastrointestinal symptoms, such as nausea, vomiting, and diarrhea, which are rarely observed in HGA patients [2]. So these differences can be used as the auxiliary basis of differential diagnosis.

At present, there is still no specific vaccine or antiviral therapy for SFTSV infection. Supportive treatment, including plasma, platelet, granulocyte colony stimulating factor (GCSF), recombinant human interleukin 11, and gamma globulin is the most essential part of case treatment [44]. Meanwhile, some measures were taken to maintain water, electrolyte balance and treat complications are also very important.
Ribavirin is reported to be effective for treating Crimean-Congo Hemorrhagic Fever (CCHF) infections and hemorrhagic fever with renal syndrome, but it is still inadequate to judge the effect of ribavirin on SFTS patients because of the study limitation without adequate parameters were investigated [45]. Host immune responses play an important role in determining the severity and clinical outcome in patients with infection by SFTSV.

For Viral treatment options: https://madisonarealymesupportgroup.com/2016/03/28/combating-viruses/

And lastly, please know ticks parasitize one another, potentially spreading all manner of diseases to humans. This fact also shoots holes in the regurgitated mantra that only certain ticks carry certain pathogens.  If they are feasting on one another, they can potentially infect each other and then us: https://madisonarealymesupportgroup.com/2018/03/07/tick-bites-tick-hyperparasitism/

Also, over time, ticks can acquire the ability to transmit pathogens they didn’t transmit before.

Study Shows American Dog Ticks in Western U.S. Are a Separate Species

https://entomologytoday.org/2021/08/25/american-dog-ticks-western-new-species-dermacentor-similis/

Study Shows American Dog Ticks in Western U.S. Are a Separate Species

Dermacentor similis, male

Researchers have split the medically important American dog tick into two species: the existing Dermacentor variabilis in eastern states and the newly described Dermacentor similis west of the Rocky Mountains. An adult male D. similis tick is shown here. (Photo courtesy of Paula Lado, Ph.D.)

By Melissa Mayer

Melissa Mayer

Melissa Mayer

Rocky Mountain spotted fever spreads when Rickettsia rickettsia bacteria pour into a bite wound while an American dog tick takes a blood meal. Unlike some other tick-borne diseases, which require a longer bite to transmit, Rocky Mountain spotted fever infection may take place within the first 30 minutes of the tick bite.

The distribution of the American dog tick (Dermacentor variabilis) in the United States is a wide yet broken one. It’s mostly found throughout the central and eastern parts of the country—with a few western populations all the way on the other side of the Rocky Mountains. But are these widely separated populations really the same species?

In a study published this month in the Journal of Medical Entomology, a team of researchers at Ohio State University used an integrative taxonomy approach—looking at both physical and genetic evidence—to determine that the ticks formerly known as Dermacentor variabilis in the west are a new species, which they’ve named Dermacentor similis.

Wild, Wild West

Paula Lado, Ph.D.

Paula Lado, Ph.D.

“We were working on other aspects related to Dermacentor evolution and phylogenetics, and our results consistently showed a separation between populations from the western states and all other locations eastern of the Rockies,” says lead author Paula Lado, Ph.D., who is now with the Center for Vector-Borne Infectious Diseases at Colorado State University. “And that had been shown in other studies in the past, so we decided to explore the topic in depth.”

Dermacentor tick collection locations

(See link for article)

___________________

**Comment**

The study also found that ticks from Wisconsin and Michigan formed a small subcluster in the eastern group, which means there’s probably some variation there.

The difference between these ticks is in the minutia.  They both will happily infect you. While taxonomy considers this a “win” it’s just more research that doesn’t help patients at all. A tick is a tick is a tick.  All suck your blood and have the potential of transmitting life-altering pathogens into the human and animal body.

Important quotes:

And, because the American dog tick transmits the bacteria that cause Rocky Mountain spotted fever as well as other pathogens, describing a new species like D. similis means taking a close look at which diseases these ticks can carry and how well they do it, which is called vector competency.

“Splitting D. variabilis into two species may mean that they could be vectors for different pathogens,” Lado says. “In my opinion, it is crucial to determine the vector competency of the new species, D. similis. That will allow for us to know what pathogens are transmitted by both Dermacentor species.”

A word of warning on those quotes: all of these variables have been proven over time to be short-sighted as ticks can acquire the ability to transmit things they never used to transmit.  They have also been found in places they never were before.  Doctors looking at entomology maps have been misdiagnosing people for decades as the information is constantly changing, limited, and imperfect. Please see: The Confounding Debate Over Lyme in the South (Speilman’s maps)

Transmission times have been hotly contested for over 40 years. Mainstream medicine and conflict-riddled researchers and public health ‘authorities’ continue to doggedly state the party line that Lyme transmission takes at least 24-48 hours, whereas reality paints a far different picture, showing the potential transmission of Lyme (and other pathogens) can occur within a few hours.  It must also be remembered that minimum transmission time has never been determined, and some coinfections like Powassan virus can be transmitted within minutes. There’s also the sticky issue of partially fed ticks being able to transmit much sooner.

There is an absolute dearth of research on the issue of coinfected ticks and coinfected patients.  Does coinfection alter transmission times?  The coinfection issue remains in the Dark Ages, leaving patients and the doctors who dare to treat them muddling blindly through the process.  But, hey now we know some worthless information about the undersides of ticks!

Again, the only box Lyme/MSIDS fits into is “Pandora’s.” Trying to put a lid on this thing is completely futile.

For more:

Below is a picture of a tick, without food or water for days, and the thousands of eggs it laid.

Tick eggs

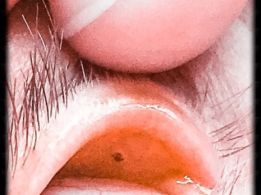
Ticks aren’t picky, and can show up in the wildest of places:

IMG_2121

636354599974837121-jcoyle-eye16059-1zz7fdgtyszqd-0lbizw1fg

Ecologically Diverse Texas Needs County-Level Data For Tick-borne Diseases

https://www.lymedisease.org/maxwell-texas-tick-borne-diseases/

Ecologically diverse Texas needs county-level data for tick-borne diseases

Aug. 2, 2021

By Sarah Maxwell, PhD

Welcome to the complex world of tick-borne disease surveillance. But honestly, it should not be so difficult. Why does the public health system fail to inform schools, camps, parents, physicians, pediatricians, psychiatrists, and others about county-level risks of tick-borne disease? Why are prevention and diagnosis so difficult?

The answers are rooted in the lack of available, dis-aggregated, and comprehensive data. But they are also complicated  by the use of “Lyme” as a catch-all phrase encompassing a variety of tick-borne diseases, when Lyme may be less endemic in some areas than other tick-borne diseases.

From a health policy perspective, the importance of county-level data to prevention, diagnosis, and treatment cannot be overstated.  For almost all other diseases, sustainable and reliable county data are the foundations to building healthy communities. So why not tick-borne diseases?

Focusing on Texas

In a recent article, Drs. Connie McNeely, Kip Thomas, and Chris Brooks and I employed promising new approaches to tick-borne disease surveillance in Texas with the goal of linking differing forms of tick-borne disease surveillance data into a comprehensive picture. The Centers for Disease Control (CDC) supports the “One Health Model,” which considers people, animals, and the environment as interconnected in assessing and addressing zoonotic disease.

In our article in the journal Healthcare titled “Tick-Borne Surveillance Patterns in Perceived Non-Endemic Geographic Areas: Human Tick Encounters and Disease Outcomes,” we compared canine serological reports of Lyme, ehrlichiosis, and anaplasmosis; patient self-reported diagnoses and tick-bite recall; official reports of Lyme disease from the CDC; and ecosystem habitat suitability through multi-layer thematic mapping.

As noted in our study: “The overall purpose was to determine if clinically diagnosed and CDC-positive Lyme disease human reports are geographically similar in disaggregated form via county, bordering county, and ecosystem to canine and official CDC counts. Comparisons between patient self-reported disease and official counts of disease are not widely used methods of surveillance, but are important epidemiological tools when disease can be linked to an event, such as a tick bite.”

Texas is a large state and often perceived to be non-endemic for tick-borne diseases. However, at the county level, the picture is quite different. Numerous counties in Texas are endemic to tick-borne diseases. So why the dilemma?

Importance of county-level data

The need for such comprehensive and new surveillance techniques is imperative. Here is why: The CDC publishes county-level Lyme disease data for anyone to view. However, the CDC limits all other tick-borne diseases to state-level surveillance only. The public and researchers do not have access to these data.[1]

CDC’s Lyme disease spreadsheet, on the other hand, is updated annually and published on the CDC website. Therefore, public health officials should, in theory, have the data they need to design prevention campaigns and assess human disease risk. Nationally, however, those data are known to undercount the real presence of Lyme disease, as numerous scholars have demonstrated.

Additionally, some of the cases within the CDC dataset may not be locally acquired. Hypothetically, an individual may travel to the Northeast, return ill, and be listed in the CDC database as a case in Contra Costa, California. Researchers who study Lyme disease prevalence must dig, and dig hard, state by state to double check those cases that may not be locally acquired.[2]

In our paper in Healthcare, we did just that. However, our focus was Texas, so the digging was concentrated to one state, where we were able to remove non-locally-acquired cases.

Even if Lyme disease data were perfect, however, researchers and some public health officials are faced with a constant obstacle: Lyme disease is not the only tick-borne disease. Ticks can carry many different pathogens. Yet, the CDC does not publish county-level data for tick-borne diseases other than Lyme. Given many patients with Lyme disease report having multiple co-infections, knowing the disease risk is imperative for physician knowledge and adoption of prevention behaviors among local community residents.

“Lyme” is often a catch-all phrase

At the same time, “Lyme” is often used as a blanket term and adopted by national and state organizations to cover a host of possible other infections such as Babesia or ehrlichiosis. The catch-all phrase “Lyme” could potentially detract from the wide range and prevalence of other tick-borne diseases in the United States.

In our study, we attempted to improve surveillance of tick-borne diseases, including Lyme, using data drawn from a specialized survey—the Texans and Ticks Survey (TTS)—developed to collect state-, county-, and zip-code-level self-reported patient information.

TTS included the geographic location of tick bite encounters. All survey respondents reported a Lyme disease diagnosis by a medical professional. Survey respondents were asked if they had received a diagnosis, and if so, how they had been diagnosed. They could select: (1) Clinically (the doctor thinks you have Lyme disease based on your history and symptoms); (2) Western Blot, where some bands were positive; (3) Western Blot, where five or more bands were positive (“CDC-positive”); (4) IGeneX or other specialty lab; or (5) I do not know/Not sure.

Respondent tick bite encounters of those who self-reported a Lyme diagnosis were mapped at the county level. Since counties with higher populations would naturally experience more tick bites (all else held constant), by-county raw case frequencies were corrected with respect to the county’s population density, and standardized as the number of cases per 100,000 individuals.

Comparing maps

We overlaid survey respondents’ tick bite encounter locations on maps with official CDC human Lyme disease cases and canine cases of Lyme, ehrlichiosis, and anaplasmosis. Examples are below:

Overall, we found that the survey respondents only reported tick bites in areas known to be suitable to ticks and tick-borne disease transmission as shown via canine serological and official CDC human reports. These findings held true for all official human Lyme cases, as well as canine Lyme, ehrlichiosis, and anaplasmosis (not pictured).
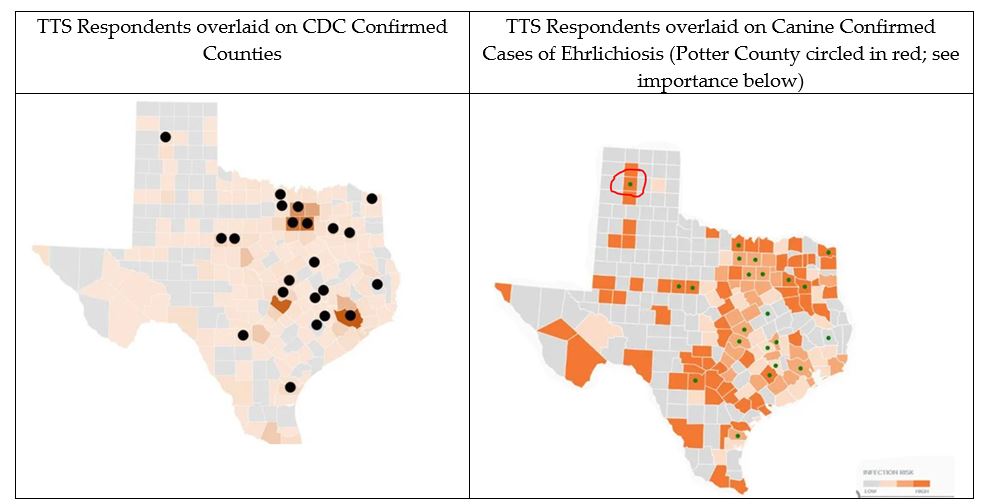
Importantly, clinically diagnosed patients match known and official cases of Lyme and other tick-borne diseases in Texas. Without access to CDC cases of other county-level tick-borne disease, self-reported tick bite encounters, associated diseases, and a one-health approach to assess overlap with human and canine cases, proved to be a promising exploratory study that warrants further attention at the national level. We suggest that self-reported clinically diagnosed patient reports and serological canine reports can serve as proxies for assessing human disease risk.

These findings were not a result of simple population density, and also followed the same hot-spot clusters as human and canine cases. Additionally, they occurred in ecosystems suitable for ticks. If these respondents were randomly lying about their tick bite locations, chances of all the respondents making up tick-bite encounters only in suitable or endemic counties would be almost impossible.

Diverse ecosystems

Back to our data dilemma: Why is providing only state level data insufficient? In states such as Texas, ecosystems are diverse and not all are suitable tick habitats. If the perception is that Texas is not endemic, we miss numerous counties where individuals have reported tick bites and a subsequent clinical Lyme diagnosis. Our study demonstrates that county-level data allow for more fine-tuned decision-making and risk assessment.

Take Potter County, Texas, as one example. The  drier northwestern area of the state, known as the Texas Panhandle, has an ecoregion suitable for tick habitat that extends into a drier, less tick-suitable ecosystem. The ecoregion that covers most of the panhandle is not as suitable for tick populations, However, the extension from the Rolling Plains into just a few counties does offer suitable tick habitat. We find overlap in Potter County with canine reports of tick-borne disease and CDC cases.
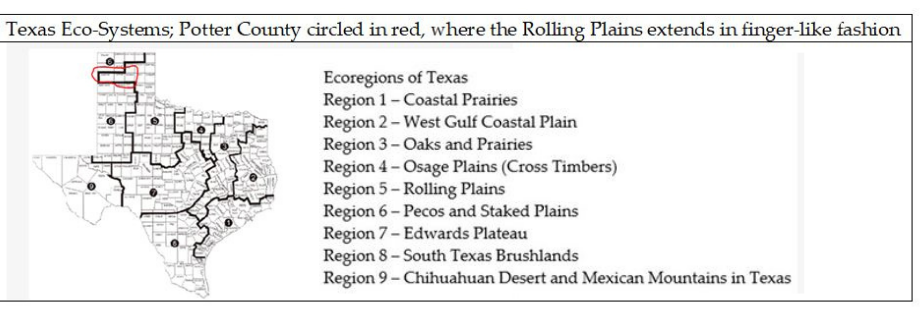
Did you know that in 2020, 1 in 20 dogs tested for ehrlichiosis in Potter County Texas was positive? However, only 1 in 1,000 canines in Potter County tested positive for Lyme disease. Should physicians test humans for ehrlichiosis in addition to Lyme disease in a few counties in the Texas Panhandle if the patient presents with tick-borne illness symptoms? I don’t have the answer to that. But I do know county-level data are desperately needed in tick-borne disease surveillance if public health officials hope to prevent disease.

Indeed, most diseases, for example West Nile, are incorporated into interactive, useful, county-level maps on the CDC webpage. Perhaps it is time to rethink the public health commitment to tick-borne disease surveillance so that both the general public and health officials can make informed and equitable decisions.

There are no sustainable, easy-to-access local tick-borne disease data that allow for communities to improve health outcomes for those who may be affected, including vulnerable populations who are the least likely to receive a diagnosis and care, especially in areas that are perceived to be “non-endemic.”

Click here to read the journal article.

Dr. Sarah Maxwell is an assistant provost and associate professor at the University of Texas at Dallas. Her research and grants focus on tick-borne disease surveillance and patient experiences with Lyme disease. She and her co-authors are founding members of ICI-Vector, created to Integrate, Communicate, and Inform others about tick-borne disease. She also serves on the scientific board of the Texas Lyme Alliance.

Footnotes

[1] Researchers may apply for these data from the CDC, but if granted access, are prohibited from publishing data at the county-level.

[2] My understanding is that not all states differentiate locally-acquired cases.