Archive for the ‘Supplements’ Category

Study: Oral NAD+ & NMN Increases Intracellular NAD+ & Lowers Triglycerides

https://www.townsendletter.com/e-letter-17-nad_plus-supplementation-and-cellular-energy/

Case Study: Oral Supplementation with the NAD+ Precursor Nicotinamide Mononucleotide (NMN)—Effects on Intracellular NAD+ and Triglycerides.

Alan Miller, ND

Abstract

NAD+ is a coenzyme that is essential in numerous metabolic reactions, the most important involving energy production. In the cellular respiration process, NAD+ is required for the production of ATP (adenosine triphosphate), the primary energy currency of cells. NAD+ transfers electrons from molecules including glucose during glycolysis and the citric acid cycle. These electrons are then transferred to the electron transfer chain, where NAD+ acts as an essential mediator in energy production, ensuring the efficient functioning of cells. NAD+ is also critically involved in DNA repair and healthy aging sirtuin enzymes.

Nicotinamide Mononucleotide (NMN) is the most direct biochemical precursor to NAD+ and thus supplementation of this molecule is an efficient method of increasing intracellular NAD+, which can improve cellular energetics and markers of aging. NMN may also lower triglycerides. In a study of intravenous dosing of 300 mg NMN in 10 healthy individuals, researchers discovered a significant reduction in serum triglycerides.

One concern with NMN is that when taken in an oral dose this molecule might be damaged or otherwise metabolized by stomach acid, pancreatic enzymes, or first pass hepatic enzymes. In other studies, we have shown that a liposomal powder preparation can protect other molecules, such as glutathione, from this type of degradation and significantly increase blood levels of the whole molecule.

We performed a small case study in which individuals were given 1000 mg of an oral liposomal NMN preparation (powder in a capsule) once after a baseline blood test. Serial triglyceride tests were performed hourly for five hours. Participants had an average of 15% decrease in triglycerides at hour five, compared to baseline. Another group was tested at baseline for intracellular NAD+ (Jinfinity Labs), then was given 1000 mg of a liposomal powder NMN daily for 15 days. An intracellular NAD+ test was then performed after 15 days. NAD+ levels increased 100 percent over this period.

This is the first case series that has demonstrated a rapid triglyceride-lowering effect of oral liposomal NMN (over 5 hours), along with a 100-percent increase in intracellular NAD+ over a 15-day period.

(See link for full article)

For more:

The Use of Natural Bioactive Nutraceuticals in the Management of Tick-Borne Illnesses

https://www.mdpi.com/2076-2607/11/7/1759

The Use of Natural Bioactive Nutraceuticals in the Management of Tick-Borne Illnesses

By Samuel M. Shor and Sunjya K. Schweig

Microorganisms 2023, 11(7), 1759; https://doi.org/10.3390/microorganisms11071759
Received: 14 May 2023 / Revised: 29 June 2023 / Accepted: 29 June 2023 / Published: 5 July 2023

Abstract

The primary objective of this paper is to provide an evidence-based update of the literature on the use of bioactive phytochemicals, nutraceuticals, and micronutrients (dietary supplements that provide health benefits beyond their nutritional value) in the management of persistent cases of Borrelia burgdorferi infection (Lyme disease) and two other tick-borne pathogens, Babesia and Bartonella species. Recent studies have advanced our understanding of the pathophysiology and mechanisms of persistent infections. These advances have increasingly enabled clinicians and patients to utilize a wider set of options to manage these frequently disabling conditions. This broader toolkit holds the promise of simultaneously improving treatment outcomes and helping to decrease our reliance on the long-term use of pharmaceutical antimicrobials and antibiotics in the treatment of tick-borne pathogens such as Borrelia burgdorferi, Babesia, and Bartonella.  (See link for full article)
___________________
Go here for an excellent article on the above study which breaks it down for the lay person.  The following graph is within the article and will interest you:

For a full list of all 30+ bioactive nutraceuticals, see Appendix A. Summary of Clinical Impact.

For more:

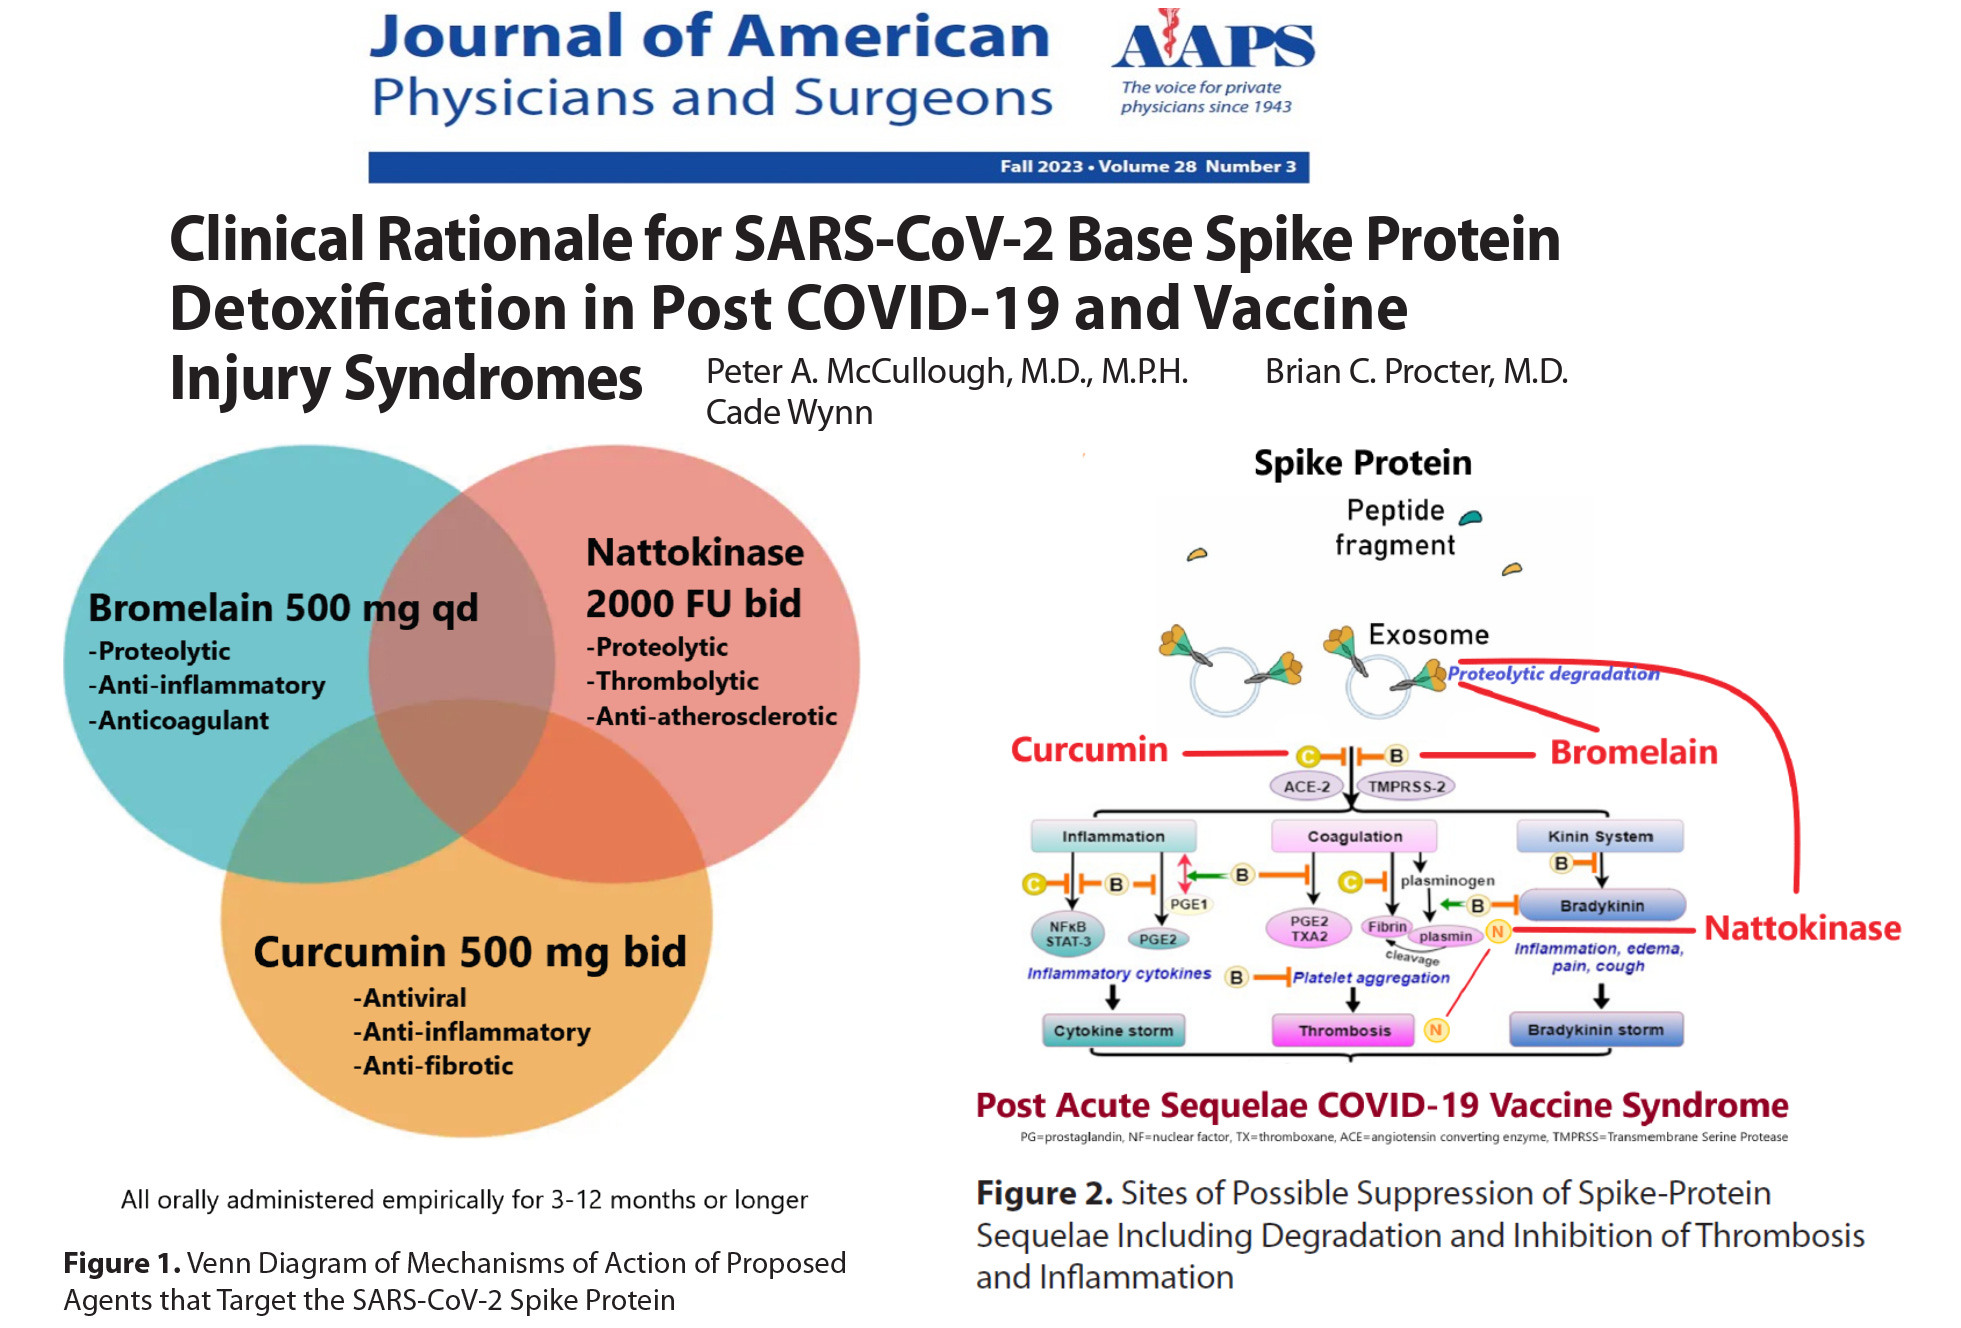
Baseline Protocol for Long-COVID & “Vaccine” Injury Syndromes

https://www.jpands.org/vol28no3/mccullough.pdf  Paper Here

Clinical Rational for SARS-SoV-2 Base Spike Protein Detoxification in Post COVID-19 and Vaccine Injury Syndromes

Publication of Baseline Protocol for Those Suffering from Long-COVID and Post-Acute Sequelae after COVID-19 Vaccination

Peter A. McCullough, M.D., H.P.H., Cade Wynn, Brian C. Procter, M.D.

For more:

Kratom : A Safer Opioid Alternative

https://www.paintreatmentdirectory.com/posts/kratom-as-an-opioid-alternative

Kratom as an Opioid Alternative


Kratom as an Opioid Alternative


Richard states, “I have suffered immense pain from fibromyalgia for 25 years, to the point of disability & early medical retirement from my job in government healthcare as a licensed psychiatric clinician at a county facility. I tried many medications to relieve my pain to no avail. I have also been a practicing herbalist for 22 years. It was recommended I try Kratom from another herbalist friend. I cannot begin to tell you of the immense relief immediately felt from the first dose of this amazing plant. I have been using kratom for several months now. I have no adverse effects, no withdrawal if not used, nor noticeable side effects. I can now go through the day with absolutely no pain! Period! This is one of the most valuable herbal remedies I have ever used.”

When Jason was 18 years old he broke his wrist and knuckles. He was given Vicodin and became addicted. He graduated to methadone and heroin. He had never used anything before but pot and alcohol occasionally. For the next seven years he was in and out of detox. All his plans went downhill. He had wanted to be a pro baseball player. He had trouble getting and keeping a job. He got a D.U.I. He watched eight of his friends die from heroin overdoses and he still couldn’t stop using. Then one day a friend posted on Facebook about kratom. Jason ordered a sample pack of a red vein strain, the most calming strain of Kratom. Since he started using kratom, he has not had the urge to use opioids again. Jason’s life is now back on track. He’s been clean for over eight months and is going to school to get a machinist certificate. He uses kratom for pain management,  anxiety, and depression. He doses twice a day and reports that it costs him $30-$40 a month. He’s now confident about his future. 

Millions of Americans now use kratom as an alternative to opioids. Many have similar stories.

Read other inspiring stories

What is Kratom?

Kratom is an herb that is native to tropical Southeast Asia and is part of the coffee family. Its scientific name is Mitragyna speciosa. The American Kratom Association says kratom is “more akin to tea and coffee than any other substances”. It has been used medicinally by the people of Southeast Asia for hundreds of years. More recently, millions of Americans have begun using kratom for pain management, anxiety, insomnia, as an energy booster, and to ease withdrawal from opioids. Many pain patients insist kratom has significantly improved their  quality of life and others, like Jason, say it has literally saved their lives.

The Johns Hopkins Kratom Study

The study, published online in the journal Drug and Alcohol Dependence in 2020, was an anonymous, online survey of 2798 kratom users. 59% of users reported taking kratom daily and the most common dosages were 1-3 grams.

Kratom was used by 91% of respondents for pain management, 67% for anxiety and 65% for depression, “with high ratings of effectiveness”. 41% reported using kratom as an opioid alternative. About a third of those using kratom for opioid withdrawal reported they were abstinent from opioids for over a year due to their kratom use.

About one third of respondents said they had adverse effects from kratom such as constipation, upset stomach or lethargy. They rated their adverse effects as mostly mild in severity and lasting less than 24 hours. A very small minority, .6%, sought treatment for adverse effects.

According to researchers, 2% of respondents met the diagnostic criteria for kratom-related substance abuse disorder. When asked how troubled they felt about their kratom use, the mean rating was 3.2 on a scale of 0 to 100.

A previous kratom study showed similar results

The results of this survey are similar to the 2016 online survey of 6150 kratom users by Pain News Network and the American Kratom Association. Nine out of ten respondents said kratom was “very effective” for pain management, depression, anxiety, insomnia, opioid addiction and alcoholism. Less than one percent said it didn’t help. The percentage of patients who rated kratom “very effective” for their pain condition:

  • Irritable bowel syndrome 94%
  • Migraine 93%
  • Fibromyalgia 93%
  • Rheumatoid arthritis 92%
  • Back pain 92%
  • Acute pain 92%
  • Lupus and other autoimmune diseases 91%
  • Osteoarthritis 90%
  • Neuropathy 90%
  • Trigeminal neuralgia 88%
  • CRPS 79% (Complex Regional Pain Syndrome)
  • Ehlers Danlos syndrome 76%

Is there any evidence that kratom has a high potential for abuse so that it would not be a good opioid alternative?

According to Dr. Jack Henningfield, a highly respected addiction specialist at Johns Hopkins, kratom is no more addictive than caffeine and “the factors that appear important in sustaining kratom consumption appear more similar to those that sustain dietary caffeine consumption, namely to better manage fatigue and daily life demands and provide mild effects considered enhancing to quality of life” including pain relief and enhanced work performance.

According to the National Institute on Drug Abuse, “Compared to deaths from other drugs, a very small number of deaths have been linked to kratom products and nearly all cases involved other drugs or contaminants.”

The federal government’s efforts to ban kratom

In 2016, the Drug Enforcement Administration proposed temporarily classifying kratom  as a Schedule I drug under the Controlled Substances Act, a drug with no known medical uses and a high potential for abuse. This would have made the use of kratom illegal. But the agency backtracked after a public outcry and pressure from some members of Congress. The DEA then asked the FDA to expedite scientific and medical evaluation instead.

In November 2017 the FDA issued a warning to consumers against using kratom, saying that there had been 36 deaths related to the herb. Scott Gottlieb, FDA Commissioner at the time, stated that kratom has similar risks of abuse, addiction, and death as opioids. This statement was ludicrous because the purported deaths from kratom occurred over a period of several years and were fewer than occurs in one day as a result of opioid overdoses. The National Institutes on Drug Abuse (NIDA) tested the FDA claims that kratom is associated with deaths, and they concluded those claimed deaths were actually caused by poly-drug users who abuse dangerous drugs or were caused by people who used an adulterated kratom product.

In 2018, the FDA published a report claiming that FDA scientists had “analyzed the chemical structures of the 25 most common compounds in kratom and concluded that all of the compounds share structural characteristics with controlled opioid analgesics, such as morphine derivatives. They also found that compounds in kratom that “bind strongly to mu-opioid receptors, comparable to opioid drugs”. This study and its conclusions have been widely criticized as misleading and unscientific. Other substances, such as Imodium, an over-the-counter remedy for diarrhea, also bind to opioid receptors but are not classified as opioids.

About 95% of kratom comes from Indonesia. The FDA reportedly played a role in the Indonesian government’s 2019 decision to ban the export of kratom as of 2022. Kratom advocates in Indonesia and the U.S. have convinced the Indonesian government to delay the export ban at least until 2024. There have been some restrictions placed on export by the Indonesian government that are negatively affecting supply and cost and hurting Indonesian farmers who were earning their living growing kratom.

In 2021, the FDA went to the World Health Organization and asked them for an international ban on kratom. In response, the WHO’s Executive Committee on Drug Dependency (ECDD) voted 11-1 to simply continue to monitor data on health impacts of kratom over the next two to three years, rather than institute strict controls. Members found “insufficient evidence” to warrant any action at the time. The committee based its decision on a scientific review of the benefits and risks of kratom. 80,000 people also submitted comments to the committee about their experiences with the herbal remedy.

The FDA continues to seize shipments of kratom to the United States  with no rationale other than that it is kratom.  The FDA’s continuous attempts to demonize kratom have also caused six states to criminalize kratom: Alabama, Arkansas, Indiana, Rhode Island, Vermont and Wisconsin.

These actions by the federal government and states have caused many consumers to be fearful of trying kratom. In my humble opinion, the FDA and DEA are more concerned about protecting pharmaceutical profits than protecting public health.

Conclusion: Kratom is a safe and effective alternative to opioids

Although extensive research is lacking on kratom, all indicators are that kratom is much safer than opioids and provides better pain relief, making it an excellent opioid alternative.

The author, Cindy Perlin, is a Licensed Clinical Social Worker, certified biofeedback practitioner and chronic pain survivor. She is the founder and CEO of the Alternative Pain Treatment Directory and the author of The Truth About Chronic Pain Treatments: The Best and Worst Strategies for Becoming Pain Free. She’s located in the Albany, NY area, where she has been helping people improve their health and emotional well-being for over 30 years. See her provider profile HERE. She is available for both in-office and virtual consultations.

_________________

**Comment**

Another perfect example of corrupt health “authorities’ banning anything that is considered a threat to Big Pharma and the medical monopoly.

For more:

ACTION ALERT: FDA Trying to Ban CBD

https://www.paintreatmentdirectory.com/posts/the-fda-is-trying-to-ban-cbd-supplements

The FDA is Trying to Ban CBD Supplements


The FDA is Trying to Ban CBD Supplements


Editor’s note: The following article and call to action about the FDA’s efforts to ban CBD supplements is being reprinted from the Alliance for Natural Health website. This is not the first time the FDA has tried banning natural treatments relied on by millions of Americans, but part of a long and corrupt history. The FDA has also been trying for several years to ban kratom, an herb being successfully used by millions of Americans to treat pain, opioid addiction and withdrawal, anxiety and more. Recently, the FDA has also taken action against homeopathy, a safe, natural system of medicine used worldwide since its development in 1810. The FDA has been trying to get stronger regulatory authority to take vitamins and other supplements off the market. It seems the FDA is leaving no stone unturned in its efforts to protect the profits of the pharmaceutical industry instead of protecting the health of the public.

The FDA Misleads on CBD Safety

…providing further evidence that the agency is trying to engineer a ban on affordable CBD to protect drug industry profits. Action Alert!

As the evidence of CBD’s myriad health benefits continues to pile up, it increasingly looks to us like the FDA is preparing to issue a ban on CBD supplements. We must support bills in Congress that take the issue out of the FDA’s hands by allowing the sale of CBD in supplement form.

Lawmakers do appear to be taking this issue seriously. In addition to the bill introduced by Representative Morgan Griffith (R-VA), another similar bill has just been introduced by Senators Ron Wyden (D-OR), Rand Paul (R-KY), Jeff Merkley (D-OR), and Representative Earl Blumenauer (D-OR) to allow the sale of CBD in supplements. Additionally, Congress is holding a hearing on July 27 during which members will formally scrutinize the impact of the FDA’s failure to develop a regulatory pathway for the sale of CBD in supplements and food. Let’s show the FDA the scale of our opposition to its unjustified plan and demonstrate the huge level of grassroots support for CBD supplements ahead of the hearing.

We want to make it crystal clear what we face if we don’t stop the FDA in its tracks. CBD, or cannabidiol, is one of over 100 natural compounds called cannabinoids found in a wide range of plants, most notably the hemp plant. The cells of our bodies are laced with cannabinoid receptors that form part of the endocannabinoid system that is essential to life and to robust health. We produce cannabinoids internally (endocannabinoids) and we also consume them in some foods (exocannabinoids). Most of these cannabinoids, including CBD, are not psychoactive – THC being an exception – but they all offer profound benefits. CBD is one of the most well researched non-psychoactive cannabinoids and it has an incredible array of health benefits, with evidence showing that has profound anti-inflammatory and immune modulating effects and can help with pain, anxiety, depression, certain cancers, and even heart health.

Let that sink in for a moment. The opioid epidemic is killing an astonishing number of Americans every year; rates of anxiety and depression are reaching new highs, particularly among young people; heart disease is the leading cause of death for adults in the US. CBD has been found to help with all of these conditions, but instead of working to make this compound more widely available as a supplement, which is the way it should be sold according to the Dietary Supplement and Health Education Act of 1994 (DSHEA), the FDA wants to stop all supplement sales of CBD. The FDA’s justification is the protection of the profits of one pharmaceutical company that has a CBD drug that will cost patients a stunning $32,500 per year. It will also mean citizens who have been benefiting from low-cost health support from CBD supplements since they became widely available a few years ago will have no further access to the supplements they have relied on. There is something deeply wrong with this picture.

How did we get here? For starters, the FDA says that CBD can’t be a supplement because it has approved a drug version of CBD called Epidiolex that is used to treat two rare forms of epileptic seizure, Lennox-Gastaut syndrome (LGS) or Dravet syndrome, in children over 2 years. This ability for FDA to rule in favor of drug companies has to do with the FDA back-channel that we’ve written about many times before. In short, if a substance is studied as a drug (i.e. a drug company has made an Investigational New Drug application) before there is evidence it was sold as a supplement (i.e. evidenced by a supplement company’s New Dietary Ingredient notification), then the drug company can ask the FDA to ban the supplement form of that compound.

Yet, as pressure mounts from Congress and a variety of stakeholders to make CBD more widely available, the FDA has been reviewing scientific information on CBD. Earlier this year, the agency released a statement explaining that the “existing regulatory framework” for foods and supplements is not appropriate for CBD and that a new regulatory pathway is needed.

One of the main issues raised by the FDA is that of safety. The agency claims that CBD presents various safety concerns, specifically the potential for harm to the liver and the reproductive system and concerns for vulnerable populations such as children and pregnant women.

These views are articulated in a review article authored in part by FDA staff. To support the assertion that CBD can pose threats to the male reproductive system, the authors cite a 1981 animal study in which monkeys were administered 30, 100, or 300 milligrams per kilogram of body weight per day (mg per kg bw/day) of CBD orally. But consider that 300 mg per kg bw/day for a human weighing 154 pounds would be 21,000 mg, or 21g, of CBD—far, far more than anyone would ever take as a supplement!

This is emblematic of a larger problem we’ve discussed before: the deeply flawed risk assessment models used by federal bureaucrats to prevent us from utilizing natural medicines to stay healthy. These types of models have been used by European regulators to set absurd limits on supplement dosages (known as tolerable upper limits, or ULs). ANH’s founder and Executive and Scientific Director, Robert Verkerk, PhD, has published several papers critiquing this approach that was originally developed by the Institute of Medicine (now the National Academy of Medicine), pointing to a fundamental flaw: in trying to restrict vitamin or other micronutrient dosages in this way, regulators completely ignore the fact that risks vary greatly depending on the form and dose of a nutrient used, and for most populations you’ll find overlap in the doses that cause health benefits for the majority and risks for a few. So if you then create a law that aims to eliminate a potential risk for everyone, you actually deprive the vast majority access to the micronutrient and all the benefits it offers.

Bringing it back to CBD: the fact that the FDA is, in part, using a decades-old animal study in which an absurdly high CBD dose was used to demonstrate that CBD has safety concerns once again demonstrates that the federal approach to assessing risk and benefit is fundamentally broken. It’s based on a defunct toxicological model that should have no place in modern day food or supplement law-making. The agency is also not giving proper weight to the incredibly favorable safety record of CBD used as a supplement or the multitude of benefits we can get from using CBD as a supplement. Instead, the FDA has chosen to focus on old evidence of harm that was only found when absurdly high doses were taken experimentally. To us, it seems like the agency is simply grasping at any information it can to demonstrate harm so it can justify its proposed ban on CBD supplements. The driver? Nothing less than preventing competition for the pharmaceutical drug version of CBD, given its the drug companies that are the FDA’s principal paymasters.

And, indeed, the FDA’s view on CBD’s safety is not supported by experts in the industry and elsewhere. A 2020 meta-analysis looked at human trials to assess CBD efficacy and safety. The authors concluded that most studies reported no adverse events with acute administration of CBD and mild to moderate effects with chronic administration, with the most common side effects being tiredness, diarrhea and changes of appetite/weight. Again, these side effects must be weighed against the benefits of CBD use for combatting opioid misuse, heart disease, anxiety, and depression. Harvard Health Publishing, the publication of the Harvard Medical School, states simply that, for adults, “CBD appears to be very safe.”

We cannot allow the FDA to cater to the drug industry at the expense of public health.

Action Alert! Write to Congress in support of bills that allow the legal sale of CBD in supplements. Please send your message immediately.

The FDA has said that they will not be allowing CBD to be in food or supplements, explaining that the “existing regulatory framework” for foods and supplements are not appropriate for CBD. The agency denied three Citizens Petitions requesting the agency issue a regulation that would allow CBD to be sold as a supplement. Clearly the FDA is more interested in protecting Big Pharma profits than with promoting consumer access to a product that can benefit their health. We need Congress to take the issue out of the FDA’s hands to create a legal pathway for CBD supplements.

Write to Congress and tell them to support the Hemp and Hemp-Derived CBD Consumer Protection and Market Stabilization Act of 2023 and the Hemp Access and Consumer Safety Act to protect access to CBD supplements.

Sign the Petition Here

_________________

**Comment**

The FDA wants patients between a rock and a hard place.  On one hand they state extended antibiotics are not to be used for Lyme/MSIDS because they are unsafe, and then they also want to remove important supplements that help us, but when the agency is alerted to the fact doctors have never witnessed so many “vaccine”-related injuries and VAERS reports are higher than any other vaccine in its history, after the mRNA gene therapy injections……crickets.

Something doesn’t smell right.

If the FDA had their way we’d just all die already.

For more:

The FDA has a long & sordid history of attempting to ban anything it views as competition to its lucrative drugs & vaccines due to its vested interests with Big Pharma.